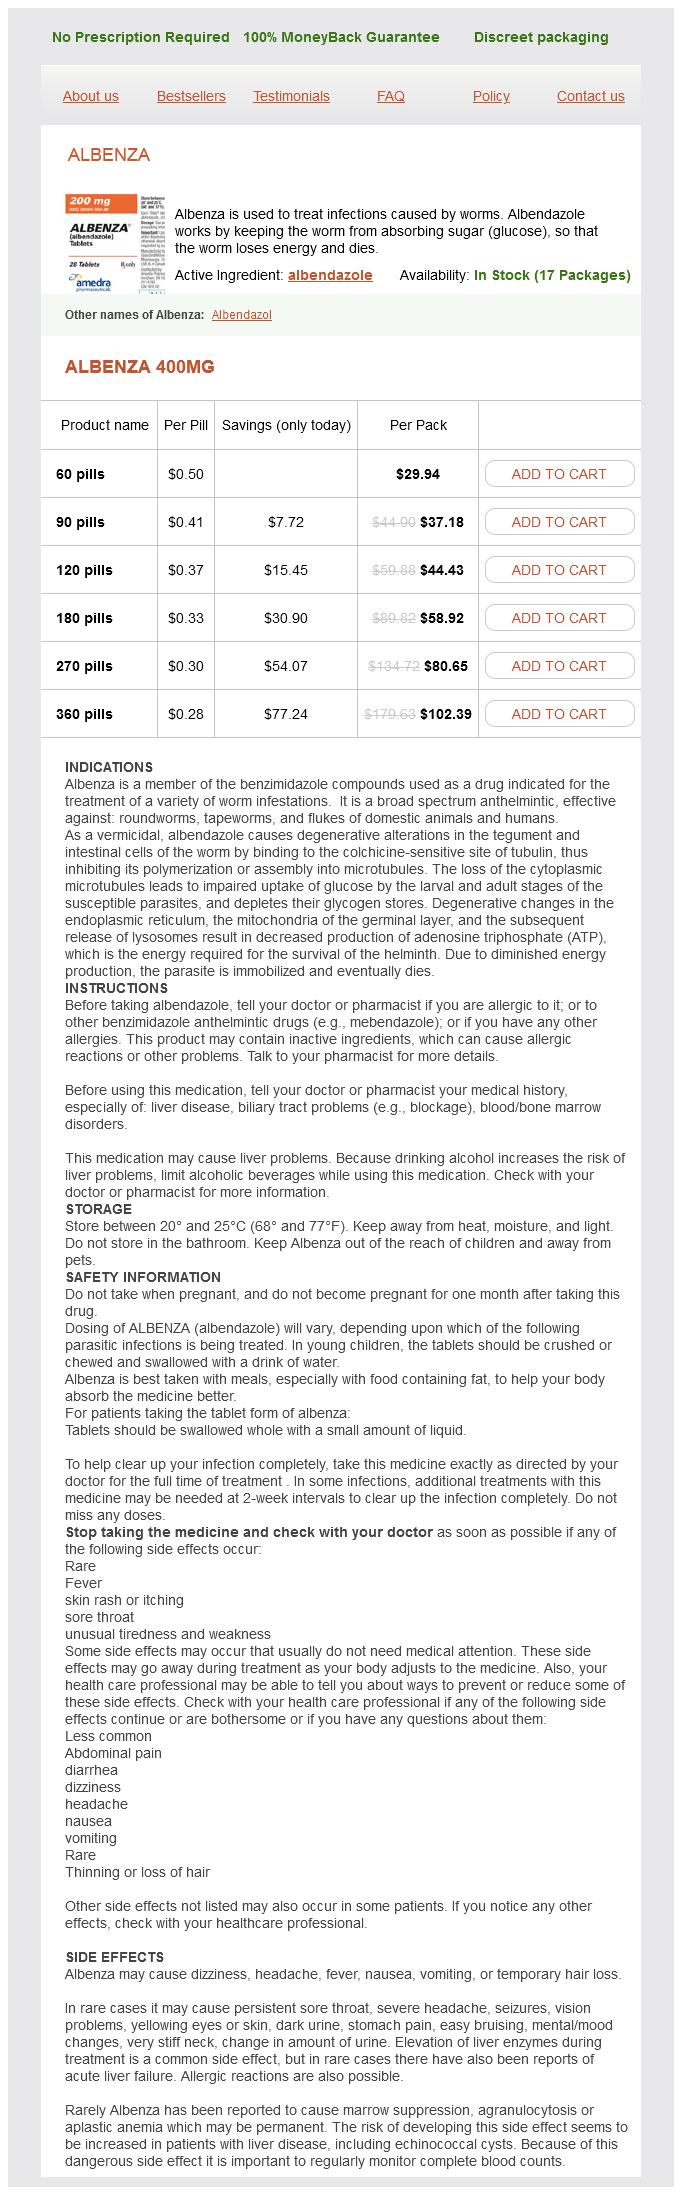
Albenza 400mg
- 60 pills - $29.94
- 90 pills - $37.18
- 120 pills - $44.43
- 180 pills - $58.92
- 270 pills - $80.65
- 360 pills - $102.39
Albenza dosages: 400 mg
Albenza packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 913
Only $0,3 per item
Description
The small spores could be seen by focusing the microscope on the edge of the epilated hair shaft medications that cause hyponatremia albenza 400 mg discount otc. Primary isolation is carried out at room temperature medications information 400 mg albenza quality, normally on Sabouraud agar containing antibiotics (penicillin-streptomycin or chloramphenicol) and cycloheximide (Acti-Dione) medications zanx cheap 400 mg albenza mastercard, an antifungal agent that suppresses the expansion of environmental contaminant fungi symptoms synonym discount albenza 400 mg without a prescription. In the case of nail illness, it may be very important use media with out cycloheximide as a result of certain fungi, such as Neoscytalidium, which will infect nails are delicate to the latter. Identification is determined by the gross colonial and microscopic morphologic features. In some circumstances, different checks involving nutritional necessities and hair penetration in vitro are necessary to verify the identification. Topical terbinafine can be used to clear lesions of tinea pedis in 7 days and can be out there as a single-dose film-forming answer utilized to the soles of the toes. The primary oral antifungal brokers used for dermatophytosis are terbinafine, itraconazole, and fluconazole. Griseofulvin is an older alternative therapy however continues to be utilized in tinea capitis brought on by Microsporum species. Newer triazoles, corresponding to posaconazole and voriconazole, are costly and never extensively used. Terbinafine is given in dosages of 250 mg every day for 2 weeks for tinea cruris or corporis. It produces fast and long-lasting remissions for dry-type dermatophytosis and different skin infections. Itraconazole could be given repeatedly in doses of 200 mg daily and is curative for tinea cruris or corporis after 1 week. Fluconazole can additionally be used as a remedy for dermatophytosis, but present regimens entail 150 to 300 mg weekly for infections of the pores and skin. All three medication are well tolerated and have evidence of efficacy in ringworm of the glabrous pores and skin. With terbinafine, interactions with antidepressants and -blockers may contraindicate use. Itraconazole and terbinafine are effective in treating scalp illness, and pediatric formulations are available in some nations. Terbinafine is much less energetic against tinea capitis caused by Microsporum species, for which griseofulvin is preferred and used for 8 to 12 weeks. Griseofulvin is given in doses of 10 to 20 mg/kg every day for the microsize Systemic Therapy the standard strategy to the administration of these dermatophyte infections is topical therapy if potential, although most nail and all hair infections and widespread dermatophytosis are best handled with oral medication (Table 266. The keratolytic brokers such as Whitfield ointment (salicylic and benzoic acid compound) at the second are hardly ever used. Currently, a big group of specific antifungal agents are utilized in therapy of dermatophytosis, though a few of these are largely confined to the treatment of tinea pedis. The most incessantly used drugs are the topical azole antifungal agents, which embrace miconazole, clotrimazole, econazole, tioconazole, ketoconazole, luliconazole, efinaconazole, bifonazole, and isoconazole. Other potent topical antifungal brokers used in the treatment of dermatophytosis are ciclopirox olamine, tavaborole, terbinafine, and naftifine. It is tough to choose among the different groups of these agents on the premise of well-constructed comparative research. A Cochrane Review of topical remedies for tinea cruris and corporis (126 studies with 18,086 participants) found many biases and poor-quality evidence however concluded that data advised that topical terbinafine and naftifine have been efficient. Therapy Ringworm of the Glabrous Skin (Tinea Pedis, Corporis, Manuum) Topical Therapy Tina Capitis 3208 formulation in either pill or syrup form. It is commonly useful to use a topical azole cream or shampoo along with systemic remedy for tinea capitis and, if crusts are current, to take away these with saline soaks. It is necessary to try to establish the organism causing scalp an infection because if the infection is of human origin, it can unfold to different contacts, and it could be essential to display classmates or members of the families of youngsters with anthropophilic infections. Nevertheless, several topical preparations are of potential value within the management of nail illness. One, a topically applied nail answer containing 28% tioconazole, has been found to produce some mycologic and medical remissions. Urea is a potent hydrating agent and softens nails after software beneath occlusion. The 40% urea paste may be used to remove residual areas of an infection after oral remedy for onychomycosis. Solutions with penetration enhancers, corresponding to ciclopirox olamine and amorolfine, are widely used as nail lacquers. They are efficient in a proportion of early instances of dermatophyte and Candida nail infection. They are applied once or twice weekly and are more and more being utilized in combination therapy with oral medicine in severe infections. Luliconazole 5%, efinaconazole 10% answer, and tavaborole 5% answer are utilized to the nail every day for forty eight weeks. Treatment is dear, and efficacy when used alone seems to be modest, often leading to only momentary improvement. Treatment is given for six weeks for fingernail infections and 12 weeks for toenail infections. In 70% to 80% of patients, terbinafine 250 mg as quickly as daily produces remedy in 6 weeks for fingernails and 12 weeks for toenails. Intermittent regimens with fluconazole (300 and 450 mg weekly) are additionally used in the therapy of onychomycosis. However, in one large double-blind research of patients with toenail onychomycosis, terbinafine, given continuously at 250 mg daily for 12 or 16 weeks, was in contrast with pulsed itraconazole, at 200 mg twice a day for 1 week every month repeated three or 4 instances. The results revealed significantly higher responses for both terbinafine teams than for itraconazole in both mycologic and clinical remission rates. Infections have been described in immigrants from tropical areas to the United Kingdom, Canada, and France. Deep infections corresponding to sporotrichoid Neoscytalidium infections and a brain abscess have rarely been reported, mainly in immunocompromised sufferers. Close inspection reveals that the structure is different from that usually seen with dermatophyte hyphae, however correct discrimination requires experience. Both organisms develop on Sabouraud agar but are inhibited if cycloheximide (Acti-Dione) is included in the medium. Whitfield ointment (6% benzoic acid and 3% salicylic acid) may be used to treat Neoscytalidium infections of the only real or the palm. However, not considered one of the specific antifungal medication currently out there produces consistent results. The most typical of those is Scopulariopsis brevicaulis, which usually causes an infection of the nice toenails. Treatment could additionally be tough, but chemical nail removing with 40% urea may be useful. In many instances they seem to be colonizing the undersurface of dystrophic nail plate. Examples of infections caused by a spread of different organisms, corresponding to Aspergillus and Fusarium spp. Fusarium is now known to cause a range of fungal nail infections from superficial white onychomycosis to paronychia and proximal subungual disease. In severely neutropenic patients, nail an infection could also be followed by systemic dissemination of this fungus. Oral antifungal remedy is unpredictable against these infections,53 and nail removing with 40% urea is usually used as an adjunctive treatment. Malassezia yeasts are difficult to tradition unless oil or Tween 80 is added to the medium. The most acceptable remedy for pityriasis versicolor is a topical azole or terbinafine cream55; cheaper options, now less typically used, are 2% selenium sulfide lotion or 20% sodium thiosulfate applied daily for 10 to 14 days. In some circumstances, intermittent functions of 50% propylene glycol in water prevent a relapse. Among oral remedies, itraconazole 200 mg day by day for five or 7 days and fluconazole 300 mg weekly for 2 weeks are effective. Patients normally have to be warned that the pigmentary changes might return to regular only after many months, even when the infection has been efficiently treated.
Caper Bush (Capers). Albenza.
- What is Capers?
- Dosing considerations for Capers.
- Diabetes, skin disorders, improving the function of enlarged capillaries, and dry skin.
- Are there any interactions with medications?
- How does Capers work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96711
Investigators in Asia medications for schizophrenia albenza 400 mg cheap visa, Africa medicine for high blood pressure purchase 400 mg albenza with visa, and Latin America have rigorously studied cryptosporidial diarrheal sickness amongst children symptoms 7 days after iui 400 mg albenza discount. Less frequent features could embrace abdominal ache medications used to treat schizophrenia albenza 400 mg cheap mastercard, fever, shortness of breath, cough, and foul stools. Although most instances resolve within a quantity of days, many affected individuals go on to develop prolonged, recurrent, or persistent diarrhea. Studies prospectively examining both dietary standing and Cryptosporidium an infection in cohorts of children demonstrated important variations in nutritional standing earlier than Cryptosporidium infection. In distinction, children contaminated earlier than 1 year of age or those in South Asia often by no means recovered. Animal fashions have confirmed the bidirectional interplay between malnutrition and cryptosporidiosis. Voluminous watery diarrhea or cholera-like sickness develops in a minority of sufferers. The scientific picture is often confused by other concomitant opportunistic infections, including microsporidiosis, disseminated Mycobacterium an infection, or cytomegaloviral colitis. Laboratory studies characteristically reveal elevated ranges of alkaline phosphatase. Ultrasound examination may reveal dilatation of the biliary duct and/ or indicators of gallbladder inflammation. Biopsy specimens of the biliary ducts, staining of the bile, or stool research may show the parasites. Many cases of biliary disease will reveal evidence of coinfection with cytomegalovirus or microsporidia. Cryptosporidiosis appears to be extra frequent in patients on tacrolimus than on cyclosporine, and the former sometimes have elevated tacrolimus levels. Cryptosporidiosis is particularly problematic amongst transplant sufferers in areas extremely endemic for cryptosporidiosis. Cryptosporidium an infection was historically recognized by way of microscopic examination of stool. Thus, conventional approaches to stool examinations often trigger the organism to be missed. All of the acid-fast stains detect different parasites which will cause related illnesses. Direct immunofluorescence using monoclonal antibodies is now a gold standard for stool examination. For example, antigen detection kits have been associated with pseudo-outbreaks stemming from falsepositive outcomes, and the results could also be less reliable in community hospitals. The immunochromatographic exams are rapid tests for Cryptosporidium and Giardia antigen. Antigen assays as a bunch have the benefit of not requiring skills in microscopic identification of organisms. This may be accomplished with immunoassays for antigen, with microscopic demonstration of the organisms, or through nucleic acid amplification. Because the organisms are related in dimension and shape to yeast normally present in stool, differential stains are required to establish the organism. These could embrace modified acid-fast staining (A) showing that the oocysts are red organisms; fluorescent stains, corresponding to auramine-rhodamine (B); or immunofluorescence (C) (green organisms). As is the case for all causes of diarrhea, alternative of fluids and electrolytes is a critically necessary first step in management. Oral rehydration is preferred, but severely sick sufferers could require parenteral fluids. Cryptosporidiosis is characterized by preferential loss of mature epithelial cells at the suggestions of the villi, and enzymes expressed on these cells, together with lactase, are misplaced. As is the case for different types of childhood diarrhea, breastfeeding should be continued and zinc supplementation provided for youngsters in low-resource settings. Opiates, corresponding to loperamide and diphenoxylate/atropine combination, may ameliorate mild signs, but their efficacy is proscribed in extreme illness. Overall, octreotide was effective however not persistently more practical than other oral antidiarrheal agents. For immunodeficient sufferers, restoration of the immune response should be pursued. Despite improved immune response, one study documented continued early mortality in sufferers treated with simply antiretrovirals. Cryptosporidiosis has been related to elevated ranges of tacrolimus, which may worsen the course of cryptosporidiosis. There are anecdotes of responses to antiparasitic medicine, together with nitazoxanide, paromomycin, and/or azithromycin. For example, the Cryptosporidium dihydrofolate reductase�thymidylate synthetase incorporates novel amino acids at sites related to antifolate resistance in different species. However, clinical development progressed solely after antiprotozoal activity was demonstrated within the early Nineteen Nineties. Nitazoxanide suspension was approved within the United States for treatment of cryptosporidiosis and giardiasis in kids in 2002. An outpatient examine was performed in Egypt in adults and kids with cryptosporidiosis and prolonged diarrhea (mean duration, 13 days). Diarrhea resolved by day 7 in 39 of 49 (80%) within the nitazoxanide group, compared with 20 of forty nine (41%) in the placebo group. Oocysts have been now not detected in 33 of 49 (67%) treated with nitazoxanide, in contrast with eleven of fifty (22%) handled with placebo. A second trial of outpatients in Egypt in contrast nitazoxanide tablets, suspension, and placebo. The response price was 26 of 28 (93%) within the nitazoxanide arms, in contrast with 10 of 27 (37%) in the placebo arm. All children were handled with nitazoxanide suspension (100 mg twice every day for 3 days) or matching placebo. Follow-up stool research were freed from oocysts in 13 of 25 (52%) youngsters within the remedy group, compared with three of 22 (14%) within the placebo group. A fourth trial in hospitalized youngsters in Egypt noted an 87% remedy fee with nitazoxanide compared with 69% with paromomycin. In a small placebo-controlled trial incorporating quantitation of oocyst excretion, the paromomycin arm demonstrated a major reduction in oocyst shedding (about 70%), decreased stool frequency in these handled with paromomycin, but no cures. There was no difference between groups when evaluation of these on therapy was carried out, however dropouts occurred only in the placebo arm. By intent-to-treat evaluation with dropouts grouped with failures, the response rate was much like that in the earlier trials, with a development favoring paromomycin over placebo. Dose escalation demonstrated no further enchancment with larger doses, and better doses have been related to gastrointestinal toxicity and ototoxicity. However, three managed trials have examined oral bovine anti-Cryptosporidium immunoglobulin preparations in cryptosporidiosis. A third trial was stopped with solely 5 members after demonstrating comparable improvement in hyperimmune and control colostrum. In vitro studies have advised that azithromycin and rifabutin may enhance the parasiticidal exercise of nitazoxanide. Overall, there was a 2-log lower in oocyst shedding, however few sufferers have been cured. Clinical failures had been related to biliary disease, coinfection with different enteric pathogens (especially cytomegalovirus), or unwanted aspect effects of the drugs. In current years, the increased recognition of cryptosporidiosis as a cause of childhood morbidity has led to renewed efforts at developing medicine for cryptosporidiosis. However, so far all have stopped wanting scientific trials because of unanticipated adverse effects. Recreational waters, similar to lakes, could pose a hazard for compromised hosts, who ought to keep away from untreated water. Personal measures can be used to decontaminate infected or probably infected water, corresponding to throughout travel to resource-poor countries when the public water supply is contaminated, or as a routine follow in compromised hosts. Water may be decontaminated by bringing it to a boil or by utilizing a filter with a pore dimension of 1 �m or smaller. Use of ceramic filters has decreased diarrheal ailments in some settings, however had combined leads to cryptosporidiosis. These people ought to avoid obvious sources of Cryptosporidium oocysts, corresponding to individuals with diarrhea (particularly avoiding sexual practices that might contain publicity to feces), farm animals (particularly cattle), and domestic pets that have diarrhea.
Specifications/Details
Endoscopic retrograde cholangiopancreatography-associated AmpC Escherichia coli outbreak medicine emoji albenza 400 mg trusted. Prior environmental contamination increases the risk of acquisition of vancomycin-resistant enterococci symptoms you may be pregnant albenza 400 mg buy on-line. Role of environmental contamination as a threat issue for acquisition of vancomycin-resistant enterococci in patients handled in a medical intensive care unit treatment plan purchase albenza 400 mg without prescription. Risk of acquiring multidrug-resistant Gram-negative bacilli from prior room occupants within the intensive care unit medicine pouch albenza 400 mg generic with amex. Disinfectants used for environmental disinfection and new room decontamination technology. Approach to the Investigation and Management of Patients With Candida auris, an Emerging Multidrug-Resistant Yeast. Survival of nosocomial bacteria and spores on surfaces and inactivation by hydrogen peroxide vapor. Efficacy, efficiency and safety aspects of hydrogen peroxide vapour and aerosolized hydrogen peroxide room disinfection systems. A head-to-head comparison of hydrogen peroxide vapor and aerosol room decontamination systems. An analysis of environmental decontamination with hydrogen peroxide vapor for decreasing the chance of patient acquisition of multidrug-resistant organisms. Enhanced terminal room disinfection and acquisition and an infection caused by multidrug-resistant organisms and Clostridium difficile (the Benefits of Enhanced Terminal Room Disinfection study): a cluster-randomised, multicentre, crossover examine. Plumbing of hospital premises is a reservoir for opportunistically pathogenic microorganisms: a review. First outbreak of nosocomial Legionella an infection in term neonates brought on by a chilly mist ultrasonic humidifier. Multiphasic strategy reveals genetic range of environmental and affected person isolates of Mycobacterium mucogenicum and Mycobacterium phocaicum associated with an outbreak of bacteremias at a Texas hospital. An outbreak of bacteremias related to Mycobacterium mucogenicum in a hospital water provide. A case of nosocomial Legionella pneumonia associated with a contaminated hospital cooling tower. Insidious threat of extreme Mycobacterium chimaera an infection in cardiac surgery sufferers. Outbreak of nosocomial urinary tract infections because of Pseudomonas aeruginosa in a paediatric surgical unit associated with tap-water contamination. Legionella pneumophila contamination in a steam towel hotter in a hospital setting. Point-of-use membrane filtration and hyperchlorination to stop patient publicity to quickly rising mycobacteria within the potable water provide of a talented nursing facility. Clonally related Burkholderia contaminans amongst ventilated sufferers with out cystic fibrosis. A nosocomial outbreak of Legionella pneumophila attributable to contaminated transesophageal echocardiography probes. Genotyping of Pseudomonas aeruginosa isolates from lung transplant recipients and aquatic environment-detected in-hospital transmission. Species association increases biofilm resistance to chemical and mechanical remedies. A cluster of instances of nosocomial legionnaires illness linked to a contaminated hospital decorative water fountain. Wastewater drainage system as an occult reservoir in a protracted clonal outbreak as a result of metallo-betalactamase-producing Klebsiella oxytoca. Non-touch fittings in hospitals: a attainable source of Pseudomonas aeruginosa and Legionella spp. Non-touch fittings in hospitals: a process to eradicate Pseudomonas aeruginosa contamination. Disinfection of Burkholderia cepacia advanced from non-touch faucets in a neonatal nursery. An outbreak of Legionnaires disease related to an ornamental water wall fountain in a hospital. Bioaerosol concentrations generated from rest room flushing in a hospital-based patient care setting. Door-opening movement can potentially result in a transient breakdown in negativepressure isolation circumstances: the importance of vorticity and buoyancy airflows. Guidelines for stopping the transmission of Mycobacterium tuberculosis in health-care settings, 2005. Airborne Aspergillus contamination throughout hospital construction works: efficacy of protective measures. Review of fungal outbreaks and infection prevention in healthcare settings throughout building and renovation. Successful management of an outbreak of invasive aspergillosis in a regional haematology unit during hospital development works. Impact of diagnostic standards on the incidence of ventilator-associated pneumonia. Strategies to forestall ventilator-associated pneumonia in acute care hospitals: 2014 replace. Oral hygiene care for critically ill patients to forestall ventilator-associated pneumonia. Silver-coated endotracheal tubes for prevention of ventilator-associated pneumonia in critically ill patients. Selective digestive tract decontamination and selective oropharyngeal decontamination and antibiotic resistance in patients in intensive-care units: an open-label, clustered group-randomised, crossover study. Incidence and traits of ventilator-associated events reported to the national healthcare security network in 2014. Use of ventilator bundle and employees education to decrease Ventilator-Associated pneumonia in intensive care patients. Clinical and financial burden of bloodstream infections in critical care sufferers with central venous catheters. Chlorhexidinesilver sulfadiazine- or rifampicin-miconazoleimpregnated venous catheters decrease the risk of catheter-related bloodstream an infection similarly. Effectiveness of minocycline and rifampin vs chlorhexidine and silver Sulfadiazine-Impregnated central venous catheters in stopping central Line-Associated bloodstream infection in a High-Volume academic intensive care unit: a earlier than and after trial. Catheter impregnation, coating or bonding for reducing central venous catheter-related infections in adults. Sustaining reductions in catheter related bloodstream infections in Michigan intensive care models: observational research. Use of disinfection cap to reduce central-line-associated bloodstream an infection and blood tradition contamination among hematologyoncology patients. Chlorhexidineimpregnated dressing for prevention of catheter-related bloodstream an infection: a meta-analysis*. Chlorhexidine gluconate to cleanse patients in a medical intensive care unit: the effectiveness of supply control to reduce the bioburden of vancomycin-resistant enterococci. Prevention of bloodstream infections by use of daily chlorhexidine baths for patients at a long-term acute care hospital. Effect of hospital-wide chlorhexidine affected person bathing on healthcare-associated infections. A central line care upkeep bundle for the prevention of central Line-Associated bloodstream infection in Non-Intensive care unit settings. Central lineassociated bloodstream an infection in a trauma intensive care unit: impression of implementation of Society for Healthcare Epidemiology of America/Infectious Diseases Society of America follow tips. Strategies to forestall catheter-associated urinary tract infections in acute care hospitals: 2014 replace. Preventing catheter-associated urinary tract infections in the intensive care unit. Trends in catheter-associated urinary tract infections in adult intensive care units-United States, 1990-2007.
Syndromes
- Are you afraid of sexual activity because of physical problems?
- Atrial fibrillation and atrial flutter
- Short stature
- Abnormal milk flow from the breast in a woman who is not pregnant or nursing (galactorrhea)
- Is there blood in the stools?
- Androgens
- Bladder control issues (urinary incontinence or leakage, or urinary retention, which means you are not able to completely empty your bladder)
Related Products
Additional information:
Reactive nitrogen and oxygen species medicine for anxiety 400 mg albenza order visa, and iron sequestration contribute to macrophage-mediated control of Encephalitozoon cuniculi (phylum Microsporidia) an infection in vitro and in vivo symptoms multiple sclerosis order albenza 400 mg fast delivery. Role of gamma interferon in cellular immune response towards murine Encephalitozoon cuniculi infection medications used to treat depression albenza 400 mg buy low cost. Humoral immune response to natural an infection with Encephalitozoon cuniculi in rabbits medicine zantac purchase 400 mg albenza with visa. Recognition profiles of microsporidian Encephalitozoon cuniculi polar tube protein 1 with human immunoglobulin M antibodies. Experimental mannequin for human intestinal microsporidiosis in interferon gamma receptor knockout mice infected by Encephalitozoon intestinalis. Induction of a rapid and powerful antigen-specific intraepithelial lymphocyte response during oral Encephalitozoon cuniculi an infection. Modification of the medical course of intestinal microsporidiosis in acquired immunodeficiency syndrome sufferers by immune standing and anti-human immunodeficiency virus remedy. Ultrastructure of atypical (teratoid) sporogonial levels of Enterocytozoon bieneusi (Microsporidia) in naturally contaminated rhesus monkeys (Macaca mulatta). Localization of an infection by the microsporidian Enterocytozoon bieneusi Chapter 270 Microsporidiosis one hundred sixty. Pathology of microsporidiosis: rising parasitic infections in patients with acquired immunodeficiency syndrome. The presence of Enterocytozoon bieneusi spores in the lamina propria of small bowel biopsies with no evidence of disseminated microsporidiosis. Intestinal microsporidiosis occurring in two renal transplant recipients treated with mycophenolate mofetil. Microsporidial polymyositis in human immunodeficiency virus-infected sufferers, a uncommon life-threatening opportunistic an infection: clinical suspicion, analysis, and management in resource-limited settings. Microsporidiosis myositis in a affected person with the acquired immunodeficiency syndrome. Pathology of symptomatic microsporidial (Encephalitozoon hellem) bronchiolitis within the acquired immunodeficiency syndrome: a model new respiratory pathogen diagnosed from lung biopsy, bronchoalveolar lavage, sputum, and tissue tradition. Parasitic sinusitis and otitis in patients infected with human immunodeficiency virus: report of 5 cases and evaluation. Microsporidial rhinosinusitis: is that this the subsequent pathogen to infect the sinuses of the immunocompromised host Disseminated microsporidiosis (Encephalitozoon hellem) and acquired immunodeficiency syndrome: autopsy evidence for respiratory acquisition. Pulmonary and intestinal microsporidiosis in a patient with the acquired immunodeficiency syndrome. Genetic evidence for the prevalence of extra-intestinal Enterocytozoon bieneusi infections. Chronic diarrhea because of intestinal microsporidiosis in a liver transplant recipient. Microsporidiosis in pediatric renal transplant sufferers in Cape Town, South Africa: two case reports. Enterocytozoon bieneusi microsporidiosis in stem cell transplant recipients handled with fumagillin. Successful treatment with fumagillin of the primary pediatric case of digestive microsporidiosis in a liver-kidney transplant. Intestinal microsporidiosis: a hidden danger in rheumatic illness patients undergoing anti-tumor necrosis issue therapy combined with disease-modifying anti-rheumatic medication Microsporidial stromal keratitis and endophthalmitis in an immunocompetent affected person. Encephalitozoon cuniculi genotype I as a causative agent of brain abscess in an immunocompetent patient. Successful treatment of disseminated Anncaliia algerae microsporidial infection with mixture fumagillin and albendazole. Kicia M, Kopacz S, Wesolowska M, et al Disseminated Encephalitozoon cuniculi infection in sufferers with hip implant loosening. International Workshops on Opportunistic Protists-14, Cincinnati, Ohio, 2017:1744. Intestinal microsporidiosis in human immunodeficiency virus-infected patients with continual unexplained diarrhea: prevalence and scientific and biologic options. Coinfection with Giardia lamblia and Enterocytozoon bieneusi in a patient with acquired immunodeficiency syndrome and chronic diarrhea. Human immunodeficiency virus 1-associated necrotizing cholangitis attributable to an infection with Septata intestinalis. Microsporidiosis of the mandible in a patient with acquired immunodeficiency syndrome. Detection of Septata intestinalis in stool specimens and coprodiagnostic monitoring of profitable remedy with albendazole. Microsporidia an infection of the cornea in a man seropositive for human immunodeficiency virus. Improved light-microscopal detection of microsporidia spores in stool and duodenal aspirates. A new trichrome-blue stain for detection of microsporidial species in urine, stool, and nasopharyngeal specimens. A new and improved "quick-hot Gram-chromotrope" approach that differentially stains microsporidian spores in clinical samples, including paraffin-embedded tissue sections. Luna stain, an improved selective stain for detection of microsporidian spores in histologic sections. Detection of microsporidian spores in medical samples by indirect fluorescent-antibody assay using whole-cell antisera to Encephalitozoon cuniculi and Encephalitozoon hellem. Identification of the microsporidian Encephalitozoon hellem utilizing immunoglobulin G monoclonal antibodies. Encephalitozoon intestinalis-specific monoclonal antibodies for laboratory diagnosis of microsporidiosis. Production of monoclonal antibodies directed against the microsporidium Enterocytozoon bieneusi. Production and characterization of monoclonal antibodies in opposition to Enterocytozoon bieneusi purified from rhesus macaques. Sensitivity and specificity of a monoclonal antibody-based fluorescence assay for detecting Enterocytozoon bieneusi spores in feces of simian immunodeficiency virus-infected macaques. Short-term in vitro culture and molecular analysis of the microsporidian, Enterocytozoon bieneusi. Serial propagation of the microsporidian Enterocytozoon bieneusi of human origin in immunocompromised rodents. Comparison of polymerase chain reaction with gentle microscopy for detection of microsporidia in scientific specimens. In vitro model to assess effect of antimicrobial agents on Encephalitozoon cuniculi. Analysis of the beta-tubulin genes from Enterocytozoon bieneusi isolates form a human and rhesus macaque. Analysis of the beta-tubulin gene from Vittaforma corneae suggests benzimidazole resistance. Urethritis related to disseminated microsporidiosis: medical response to albendazole. Blanshard C, Peacock C, Ellis D, et al Treatment of intestinal microsporidiosis with albendazole. Fumagillininduced aseptic meningoencephalitis in a kidney transplant recipient with microsporidiosis. Investigations into microsporidian methionine aminopeptidase kind 2: a therapeutic goal for microsporidiosis. Microsporidial keratoconjunctivitis handled efficiently with a short course of fumagillin. Microsporidial keratoconjunctivitis attributable to Septata intestinalis in a patient with acquired immunodeficiency syndrome. The efficacy of corneal debridement within the therapy of microsporidial keratoconjunctivitis: a prospective randomized clinical trial. Clinical features, risk factors, and coverings of microsporidial epithelial keratitis. The protozoans identified to infect people are a various group, as indicated by phylogeny (Table 271. Protozoa could additionally be divided, for convenience, into four distinct groups based mostly on methodology of locomotion: Mastigophora (flagella), Sarcodina (pseudopodia), Apicomplexa (microtubule advanced, generally referred to as sporozoa), and Ciliophora (ciliates) (see Table 271.
Usage: gtt.
Mycophenolate mofetil treatment 3rd degree hemorrhoids albenza 400 mg discount visa, permitted in 1995 symptoms 5 months pregnant albenza 400 mg generic, is a cytotoxic drug with an antiproliferative effect on T and B lymphocytes and has changed azathioprine in triple-drug regimens medications known to cause weight gain 400 mg albenza generic with mastercard, comprising a calcineurin inhibitor agent and corticosteroids medications japan travel albenza 400 mg discount free shipping. Its use has been related to decrease rates of biopsy-proven rejection compared with azathioprine, with similar threat of infections. The effects of immunosuppressive brokers have turn out to be more apparent as surgical techniques have improved, and antimicrobial prophylaxis has come to be used more broadly. The aim is to optimize immunosuppressive regimen such that it prevents rejection but preserves antimicrobial immunity and minimizes long-term metabolic problems and the risk of malignancy. Corticosteroids Although inadequate as sole brokers to sustain graft survival, corticosteroids remain a key component of most immunosuppressive regimens. Corticosteroids broadly inhibit immune responses, including innate inflammatory responses, phagocytic perform, cellular immunity, and, to a lesser extent, antibody formation. In an effort to obviate undesirable unwanted aspect effects of corticosteroid therapy, more transplantation centers follow early withdrawal and use steroid-free regimens. Meta-analyses of trials 3672 the calcineurin inhibitor agent cyclosporine is a cyclic peptide derived from Tolypocladium inflatum and was approved for scientific use in 1983. Concentrations of the drug as little as a hundred ng/mL effectively inhibit blended lymphocyte reactions. Patients handled with cyclosporine alone for various autoimmune illnesses show low rates of scientific an infection, which demonstrates the significance of corticosteroids and other cofactors for infection in transplant recipients. Tacrolimus, accredited in 1994, is a macrolide produced by Streptomyces tsukubaensis. Although a significant part of the immunosuppressive effects of cyclosporine and tacrolimus is accounted for by the antagonism of calcineurin exercise, tacrolimus also inhibits steps distal to calcineurin activation in the T-cell activation cascade. Clinical trials have demonstrated that tacrolimus-based immunosuppression ends in lower rates of acute rejection and graft loss than cyclosporine-based therapy, notably in kidney and liver transplant recipients, with no convincing proof that it enhances the chance for an infection. Major opposed effects of calcineurin inhibitor agents are nephrotoxicity, thrombotic thrombocytopenic purpura/hemolytic uremic syndrome, neurotoxicity, hypertension, and diabetic mellitus. In comparability with cyclosporine, tacrolimus is related to less hypertension however larger rates of diabetes mellitus and neurotoxicity. Mammalian Target of Rapamycin Inhibitors Rapamycin, also called sirolimus, was launched in 1999. They have additionally been linked to delayed wound healing, oral ulcerations, and a uncommon drug-induced interstitial pneumonitis that may mimic Pneumocystis pneumonia. Everolimus is a hydroxyethyl by-product of rapamycin that differs from sirolimus in its pharmacokinetics, nevertheless it has an analogous side-effect profile and infectious danger. For example, persistent renal dysfunction develops in 7% to 21% of the organ transplant recipients and will increase the chance of death by roughly fourfold. The biologic agents used for immunosuppression in transplant recipients are proven in Table 308. Allograft might transmit an infection or be more susceptible to an infection on account of ischemic harm or allograft reactions. These agents can generally be divided into T-cell nondepleting and depleting medication. Antithymocyte globulins, corresponding to Thymoglobulin, are polyclonal antibodies prepared in rabbits or horses by immunization with human thymocytes. They end in profound immunosuppression as a outcome of T-cell depletion, which lasts for 3 to 6 months. It is increasingly used with transplant recipients for both induction remedy or for the therapy of acute rejection unresponsive to corticosteroids. The infectious danger of alemtuzumab is considerably greater when used as salvage remedy for acute rejection than when used as induction remedy. Rituximab is approved to treat a selection of B-cell malignancies and autoimmune ailments. In organ transplantation it has been primarily used to deal with antibody-mediated rejection. Current medicines ought to be reviewed, specifically immunosuppressants corresponding to corticosteroids, which may predispose the affected person to opportunistic infections earlier than transplantation. All related microbiology and hospital medical information must be examined for proof of latent or energetic infection and colonization with drug-resistant micro organism. Pretransplantation serologic screening is pivotal in mitigating the risk of infection posttransplantation, as outlined in Table 308. A few observational studies have demonstrated that pre�liver transplant rectal colonization with extended-spectrum -lactamase-producing or carbapenem-resistant Enterobacteriaceae is a risk factor for posttransplant colonization and infection. Rapamycin interferes with cell-cycle proliferation and blocks intracellular signaling mechanisms by inhibiting a regulatory kinase, mammalian goal of rapamycin. Belatacept is a novel fusion protein that avidly attaches to receptors on antigen-presenting dendritic cells. It selectively inhibits costimulation signaling, thereby interfering with effective T-cell activation. Strongyloides stercoralis can additionally be endemic throughout the southeastern United States, where screening ought to be considered. Screening for Coccidioides antibodies must be routinely performed in recipients from areas of endemicity of this fungus. However, evolving medical practices and preventive methods have led to modifications within the threat and timeline of several infections, as discussed later. Nevertheless, infections in transplant recipients must be evaluated in the context of time elapsed since transplant. Bacterial infections, together with these due to antimicrobial resistant pathogens, are by far the most regularly occurring infections; vascularcatheter infections, health care�associated pneumonia, Clostridioides difficile (formerly Clostridium difficile) colitis, and surgical web site infections being most typical. Invasive fungal infections are unusual in the first month, aside from invasive candidiasis, which usually manifests as candidemia or surgical site infections. In the absence of mold-active prophylaxis, invasive aspergillosis can occur in lung transplant recipients with prior mildew colonization. Certain donor-transmitted infections (discussed later) can also manifest during this era. Infections Between 30 to one hundred eighty Days Although nosocomial infections proceed to pose a threat in patients requiring prolonged hospitalization, rates of surgical infections usually decline after 1 month, and opportunistic infections associated with immunosuppression emerge. Notably, in lung transplant recipients Aspergillus infections happen after 12 months; the median time to onset posttransplantation was 357 days in a single report15 and 33 � 19. Infections greater than 6 months after transplantation are mostly group acquired and just like those seen in the common inhabitants. However, up to date data from the Spanish consortium for the study of infections in transplant recipients present that though the rate of infections declined from three. A variety of tumors associated to viral an infection can also happen late, probably the most frequent being cutaneous malignancies. Infections because of mycoses, such as cryptococcosis or histoplasmosis, often manifest late and without an obvious inciting event or change in immunosuppression. Finally, though the chance for classic opportunistic infections declines, it by no means disappears fully. In this regard, treatment of rejection, particularly with T-cell�depleting agents resets the timeline and renders the affected person vulnerable to opportunistic pathogens noted earlier, the risk of which declines in the late posttransplantation period (see Table 308. Most infections, together with bacteremia in these patients, come up from the urinary tract. Although asymptomatic bacteriuria is frequent in kidney transplant recipients, a randomized, controlled trial in kidney transplant recipients confirmed no benefit of routine screening and therapy for asymptomatic bacteriuria. Mycoplasma hominis might trigger a breakdown of the ureterovesical anastomosis with subsequent graft loss. Presence of struvite stones, encrusted cystitis, alkaline urine, and obvious sterile pyuria is suggestive of Corynebacterium urealyticum. This bacterium may be missed in routine cultures in commonplace media as it requires incubation for more than forty eight to seventy two hours or requires particular media for isolation. Historically, pneumonia occurred in 25% to 30% of kidney transplant recipients and was the commonest infectious explanation for demise. Currently, nevertheless, these opportunistic brokers have come beneath better management, and standard bacterial pathogens have become way more widespread in transplant populations. Wound infections are rare (4%�5%) but may be a major problem, particularly if they contain the perinephric area. Body mass index 30 kg/m2, urinary leak, reoperation through the transplant incision, mycophenolate mofetil use, and diabetes mellitus are threat components for infection. These sufferers have typically acquired extreme immunosuppression or have chronic dysfunction of the allograft or different main organs. Kidney transplant recipients have the lowest variety of episodes of infection per patient, whereas liver and coronary heart transplant recipients have intermediate charges.
Tags: albenza 400 mg order without prescription, buy albenza 400 mg without a prescription, order albenza 400 mg, generic albenza 400 mg fast delivery, albenza 400 mg order overnight delivery, buy albenza 400 mg with amex, discount albenza 400 mg on line, purchase 400 mg albenza with visa, albenza 400 mg mastercard, albenza 400 mg cheap visa, albenza 400 mg buy cheap, 400 mg albenza discount fast delivery, albenza 400 mg on-line, buy discount albenza 400 mg, albenza 400 mg buy generic, purchase albenza 400 mg free shipping
10 of 10
Votes: 325 votes
Total customer reviews: 325
Customer Reviews
Tempeck, 54 years: Primary and secondary construction of the pore-forming peptide of pathogenic Entamoeba histolytica. Risk factors for early-onset, ventilator-associated pneumonia in crucial care sufferers: chosen multiresistant versus nonresistant bacteria. The finish factors utilized in scientific trials include clinical, parasitologic, and immunologic cure. Seroprevalence of Babesia infections in people uncovered to ticks in midwestern Germany.
Ballock, 43 years: The catheter should be eliminated if problems develop or if bacteremia or fungemia persists after 72 hours of acceptable antibiotic remedy. Serious bacterial infections throughout remedy of patients given a diagnosis of continual Lyme disease-United States. Immunization with the most important surface glycoprotein of Pneumocystis carinii elicits a protective response. After mucositis has cleared and oral alimentation has resumed, oral remedy is the popular route for antiinfective prophylaxis.
Spike, 65 years: Giardia lamblia and other intestinal parasitic infections and their relationships with dietary status in youngsters in Brazilian Amazon. Discontinuation of antimicrobial remedy for febrile, neutropenic children with most cancers: a potential study. Background to hematopoietic cell transplantation, including submit transplant immune recovery. Semicritical gadgets minimally require high-level disinfection with chemical disinfectants.
Nerusul, 33 years: Sterilization technologies could be relied on to produce sterility only if cleaning-to remove organic and inorganic materials and microbial load-precedes therapy. In such cases, two doses of oral ivermectin, 200 �g/kg/dose, taken with meals, one dose on day 1 and a second dose between days eight and 15, could offer a more acceptable and equally effective alternative. Tracking a hospital outbreak of carbapenem-resistant Klebsiella pneumoniae with whole-genome sequencing. The hydrogenosome appears to have a standard ancestry with mitochondria primarily based on similarities in protein import.
Jerek, 37 years: Human parvovirus B19 in younger male patients with hemophilia A: associations with remedy product exposure and joint range-of-motion limitation. Effect of nitazoxanide in persistent diarrhea and enteritis related to Blastocystis hominis. In immunocompetent hosts, Cystoisospora infection is indistinguishable from different noninflammatory intestinal infections. Whereas most cancer patients would expertise self-limited upper respiratory illness, these with a extreme immune deficit, similar to those treated for leukemia, are at increased risk for development from higher respiratory tract infection to pneumonia, with attainable respiratory failure and deadly outcome.
Sven, 61 years: Both dapsone and pyrimethamine moreover shield towards Toxoplasma gondii however not towards bacterial infections. It is also necessary to think about infections brought on by uncommon pathogens, similar to M. Takeuchi and colleagues demonstrated that mice could be rescued from a deadly infection by type I macrophages. Human herpesvirus 6 infection after hematopoietic cell transplantation: is routine surveillance needed
Ismael, 45 years: Catheter-related bloodstream infections caused by rapidly rising nontuberculous mycobacteria: a case sequence including uncommon species. Other research conducted in areas of high endemicity have demonstrated breakthrough an infection amongst vaccine responders marked by the development of antibodies in opposition to hepatitis B core protein. Cryptosporidium parvum attachment to and internalization by human biliary epithelia in vitro: a morphologic study. Adoptive transfer of lymphocytes sensitized to the main floor glycoprotein of Pneumocystis carinii confers protection within the rat.
