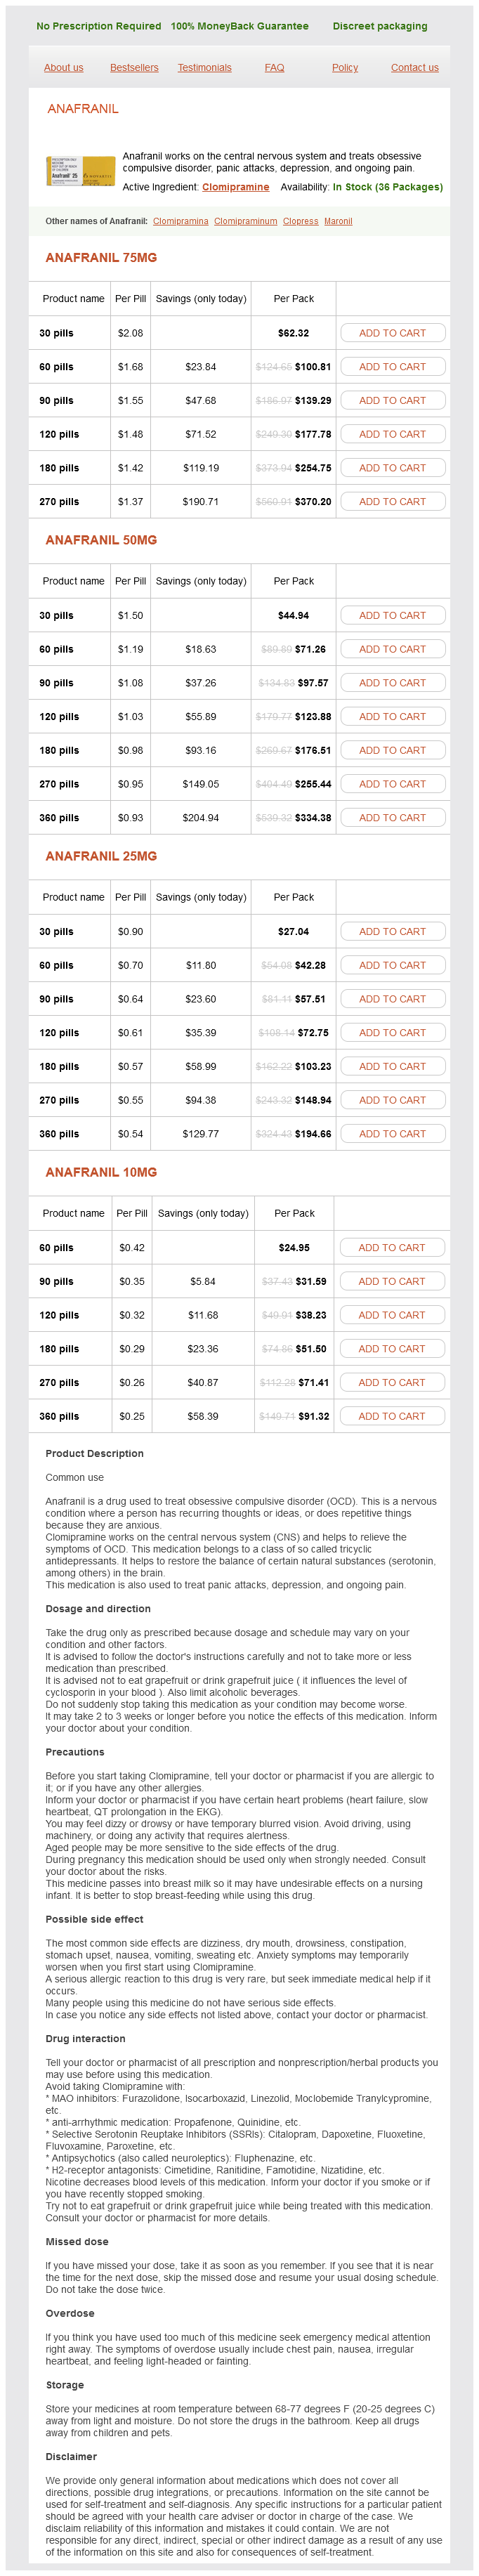
Anafranil 75mg
- 30 pills - $62.32
- 60 pills - $100.81
- 90 pills - $139.29
- 120 pills - $177.78
- 180 pills - $254.75
- 270 pills - $370.20
Anafranil 50mg
- 30 pills - $44.94
- 60 pills - $71.26
- 90 pills - $97.57
- 120 pills - $123.88
- 180 pills - $176.51
- 270 pills - $255.44
- 360 pills - $334.38
Anafranil 25mg
- 30 pills - $27.04
- 60 pills - $42.28
- 90 pills - $57.51
- 120 pills - $72.75
- 180 pills - $103.23
- 270 pills - $148.94
- 360 pills - $194.66
Anafranil 10mg
- 60 pills - $24.95
- 90 pills - $31.59
- 120 pills - $38.23
- 180 pills - $51.50
- 270 pills - $71.41
- 360 pills - $91.32
Anafranil dosages: 75 mg, 50 mg, 25 mg, 10 mg
Anafranil packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 745
Only $0,27 per item
Description
Systemic scleroderma (progressive systemic sclerosis) zero Compact granulomas along neurovascular bundles and dense peripheral lymphocytes depression diagnosis definition buy anafranil 25 mg with amex, Langhans large cells are absent mood disorder questionnaire for children purchase anafranil 10 mg mastercard. Hardening of the skin can be seen in genetic depression test dansk anafranil 10 mg purchase overnight delivery, metabolic depression sous jacente definition order anafranil 50 mg with amex, neurologic and immunologic dysfunction. Morphea is split into six varieties based on morphology and distribution of the lesions 1. Differential Diagnosis zero Tuberculoid leprosy 0 Sarcoidosis Biopsy should embrace subcutaneous tissue. Early inflammatory stage: zero Reticular dermis reveals interstitial lymphoplasmacytic infiltrate with barely thicl<ened collagen bundles. Laie Scleroiic Stage 0 Cutaneous syphilis zero Granuloma annulare zero Xanthomas zero Disappearance of the inflammatory infiltrate besides within the subcutis, epidermis is normal. Differential Diagnosis 0 Elastosis zero Eosinophilic fasciitis 0 Lichen sclerosis et atrophicus. Case History: A l5-year-olol boy with pores and skin cove- red firm papule alongside the nasolabial fold. Five clinical types are zero Superficial dermal lesions, nicely circumscribed, small and symmetric. Flat lesions Slightly elevated lesions Papillomatous lesions Dome-shaped lesions Pedunculated lesions zero Horn cysts are most characteristic histologic function abrupt and full l<eratinization. Histopathological types zero Lentigo simplex zero Junctional nevus 0 Next essential characteristic is tumor islands composed of basophilic cells, with peripheral palisading and surrounded by stroma. Microscopy zero Irregular lobular formation, nice variation in the size of the lobules. Immunofluorescence Two types ofchondroid syringomas are acknowledged 0 Tubular, cystic partially branching lumina. Case History: A 50-year-old feminine with nodular lesion over the outer canthus of eye. Special Stains Shadow cells may have calcium deposits which may be demonstrated by von Kossa stain. Case History: A 28-year-old male with pink to purple scaly papules and plaques over the complete body. Clinical Issues 0 Solitary lesion, face and higher extremities are most typical sites. Two forms of cells are seen within the strong portions: 0 Polyhedral cells with rounded nucleus and basophilic cytoplasm. Microscopy zero the tumor consists of 1 giant, sharply demarcated lobule, may display a fibrous capsule. Microscopy zero Malignancy in the lesion exhibits glandular formation, squamous differentiation and sarcomatous change with excessive mitotic rate. Differential Diagnosis 0 It is an oval, thick-walled spherule surrounded by a polysaccharide capsule. Single lesion develops on the site of infection Solitary nodules that may ulcerate Cellulitis Ulcers Subepidermal blistering which may persist for weeks to months. Microscopy zero Subepidermal non-acantholytic unilocular blisters with festooning of dermal papillae, mebooksfree. Linear IgG and C3 antibodies to hemidesmosomes at the lamina lucida of the basement membrane. Differential Diagnosis zero Dermatitis herpitiformis 0 Epidermolysis bullosa acquisita zero Bullous lupus erythematosus. Case History: A 55-year-old female with large and flaccid bullae in oral cavity and scalp. Differential Diagnosis zero Bowenoid actinic l<eratosis single row of keratinocytes hooked up to basement membrane. Microscopy Sheets of monoclonal population of lymphocytes exhibiting atypia and mitosis. Macular: Focal/ small amount of eosinophilic faceted deposit within the papillary dermis also pigment incontinence. Deposits are prominently 0 Macular: Common in women lesions seem as flat dusky brown or grayish coloured spot distributed symmetrically over the higher again and the shoulder blades, often presenting within the early adult life. Nodular: Very uncommon present as a single or a quantity of firm pinl<ish brown nodules in the seen even in the walls of small blood vessel and particular person lipocytes with adjoining inflammatory tissue exhibiting predominantly plasma cell. Microscopy 0 Lymph node infarction 0 Systemic lupus lymphadenitis zero Necrotizing granulomatous lesions of tuberculosis. Case History: A 20-year-olol feminine with mass on left aspect of the neck for two months. Clinical Syndrome 0 the lymph node architecture is partially maintained and residual follicles have reactive germinal facilities. Hyaline Vascular Variant 0 the variant happens over a broad age vary and, in most research, males and females are equally affected. The follicles include germinal centers with polarization, mitoses, and histiocytes with nuclear particles. Differential Diagnosis Hyaline Vascular Variani two or extra small germinal centers (socalled "twinning"). Ancillary Tesis Case History: A lO-year-olol male wiih hisiory of lump in the righi axilla of axillary lymph nodes-firm, discreie. Diagnosis-Sinus histiocytosis with huge lymphadenopathy (Syn: Rosai-Dorfman disease). Clinical Issues 0 Special stains: Reticulin stain reveals poor reticulin fibers, no condensation. Differential Diagnosis Florid follicular hyperplasia must be differentiated from follicular lymphoma. Reaciive Lymphoid Hyperplasia- Paracoriical/Mixed zero the age of sufferers ranged from new child to 74 years (mean, 20. Microscopy Paracortex expanded with high endothelial venules, lymphocytes, activated T cells, histiocytes, plasma cells, immunoblasts. Differential Diagnosis zero Dermatopathic lymphadenitis zero Interfollicular Hodgkin lymphoma zero Peripheral T cell lymphoma. Reaciive Lymphoid Hyperplasia-Sinus Hisiiocyiosis Microscopy 0 Involved lymph nodes are giant and matted and exhibit fibrosis of the capsule and pericapsular fibro fatty tissues. Microscopy and Special Stain Diagnosis-sinus histiocytosis (Syn: Sinus hyperplasia). Site Rarely occurs in pelvic nodes of prostate most cancers and axillary nodes of breast cancer zero In lymph nodes, the lesions consist of scattered or confluent noncaseous granulomas. Microscopy Dilated and prominent sinuses, often containing increased macrophages or sinus lining cells and polygonal histiocytes with rounded nuclei. Differential Diagnosis zero Large numbers of degenerating yeasts launch abundant gelatinous fluid that accumulates and types cystic spaces surrounded by collagenous tissue. Case History: A 3-year-old lady baby with fever and skin rashes since 1 week, biopsy cervical lymph node. Clinical Issues in immunosuppressed may present necrosis with suppuration, teaming with acid-fast bacilli. Molecular Description zero Multinucleated large cells, independently described by Warthin and Finkeldey, normally seem in the prodromal part of measles in numerous hyperplastic lymphoid tissues, together with tonsils, adenoids, lymph May be clonal rearrangement of T cell receptor delta gene. Case History: A 28-year-old male with a single asymptomatic enlarged cervical lymph node. Case History: A 20-year-old male with historical past of painless mass within the submandibular area. Clinical Issues Often subcutaneous mass of head and neck (including salivary glands), related to regional lymphadenopathy however regular overlying skin. Laboratory 0 Germinal centers are markedly bigger than normal, with indistinct margins; are composed of follicular mantle lymphocytes and in depth follicular dendritic cells. Microscopy 0 Germinal middle hyperplasia with polykaryocytes, fibrosis and proteinaceous materials in germinal facilities. Follicular lymphoma Hyaline vascular Castleman disease Nodular lymphocyte predominant Hodgkin lymphoma. Diagnosis-intranodal palisading myofibroblastoma Clinical Features 0 Bland spindle cells with areas of nuclear palisading, intraparenchymal hemorrhage and pink blood cell extravasation. Gross Ancillary Stains 0 Spindle cells: Smooth muscle actin, Vimentin, Well circumscribed, gray-white with hemorrhage and peripheral nodal tissue.
Sarsaparillae radix (Sarsaparilla). Anafranil.
- Are there any interactions with medications?
- Dosing considerations for Sarsaparilla.
- Psoriasis, rheumatoid arthritis, kidney problems, fluid retention, digestive problems, syphilis, gonorrhea, and other conditions.
- What is Sarsaparilla?
- How does Sarsaparilla work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96393
Twenty-four yr single-center expertise of hepatitis B virus an infection in heart transplantation anxiety zone breast cancer order anafranil 50 mg overnight delivery. Symptoms such as stomach pain depression symptoms during menopause anafranil 75 mg with visa, bleeding depression symptoms nimh anafranil 25 mg order on-line, and diarrhea are highly non-specific depression young adults anafranil 25 mg order mastercard, and should instead suggest a noninfectious cause such as peptic ulceration, pancreatitis, or drug toxicity somewhat than an infectious trigger. Patients should bear endoscopy/colonoscopy with biopsy to aid in identification of the responsible pathogen, if any. Preventive Measures In addition to antimicrobial prophylaxis and applicable vaccination previous to transplantation, which have been mentioned above, the standard an infection management measures ought to be enacted post-transplantation. While an inpatient, the standard hand-washing precautions by each employees and guests alike is necessary. Healthcare providers with air-transmissible illnesses must also chorus from direct contact with the affected person. As outpatients, warning ought to be exercised to minimize the chance of environmental or occupational exposures to potential pathogens, in addition to pet-related exposures; certain types of food should be averted, and the patient ought to pay consideration to potential travelrelated exposures. There is disagreement in the need for antibiotic prophylaxis when present process dental procedures however normally, antibiotic prophylaxis is supported by many programs [3]. Phenotypic and genotypic characterization of Rhodococcus equi isolated from sputum. A comparative research of Legionella micdadei and different nosocomial acquired pneumonia. Cytomegalovirus an infection is associated with cardiac allograft rejection and atherosclerosis. Co-infections with cytomegalovirus and human herpesvirus kind 7 in grownup Polish allogeneic haematopoietic stem cell transplant recipients. Disseminated varicella zoster virus an infection in adult renal transplant recipients: outcome and risk elements. Epstein barr virus and post transplant lymphoproliferative dysfunction in stable organ transplant. Outcome of remedy with pegylated interferon and ribavirin in heart transplant recipients with chronic hepatitis C. Complement-fixing antibodies against cytomegalovirus in numerous parts of the world. Human immunodeficiency virus an infection in patients with solid-organ transplants report of five instances and evaluation. Toxoplasma gondii exposure within the coronary heart transplant recipient: good, bad, or detached Infectious issues among 620 consecutive heart transplant patients at Stanford University Medical Center. Impact of enterococcal colonization and an infection in stable organ transplantation recipients from the Swiss transplant cohort research. Cytomegalovirus infections in heart transplant recipients: relationship to immunosuppression. Diagnosis, remedy, and prevention of clostridium difficile infection in stable organ transplant recipients. Cardiac Allograft Rejection, Surveillance and Treatment David Chang and Jon Kobashigawa 12 Clinical Pearls � Cardiac allograft rejection is most typical in the first 6 months after transplantation, and if left unchecked is related to elevated mortality and improvement of cardiac allograft vasculopathy. This chapter intends to discuss the main types of cardiac allograft rejection, strategies of prognosis, surveillance and its treatment. Pathology and Diagnosis of Cardiac Allograft Rejection the Endomyocardial Biopsy the endomyocardial biopsy, first described by Caves in 1973 [2], remains the gold normal method for detection of rejection following heart transplantation. Introduction Since the early days of cardiac transplantation, allograft rejection has remained the primary barrier to favorable long-term outcomes until the introduction of effective immunosuppression, as detailed in Chap. With the introduction of calcineurin inhibitors rejection rates have sharply declined and improvement in survival charges has permitted cardiac transplantation to turn into an increasingly sensible therapeutic option for endstage coronary heart disease. While rejection charges proceed to decline, the danger of rejection remains vital notably in the early period following transplantation, necessitating routine surveillance for both acute mobile and antibody-mediated rejection. Biopsies ought to be taken from the interventricular septum, provided that the right ventricular free wall is skinny, and scraping too hard might trigger perforation. Procedural Limitations Due to its invasive nature, the test could provoke anxiety and discomfort for the affected person and stays significantly challenging in the pediatric population, often requiring the use of general anesthesia. A main downside to the endomyocardial biopsy is that it samples only a limited space of the endocardium. Inflammatory modifications may be sporadic via the myocardium, or might predominantly have an result on the subendomyocardium; in these instances, the biopsy might miss the analysis. Thus, prognosis of rejection also relies on the scientific presentation and echocardiographic findings, which can or may not be supported by 12 Cardiac Allograft Rejection, Surveillance and Treatment 159. Furthermore, biopsy utilizes important assets together with physician time and is associated with substantial prices. Such reported problems embody transient proper bundle branch block, tricuspid regurgitation, access site hematoma, transient arrhythmias and occult pulmonary embolism [5]. Generally speaking, only those who undergo repeated biopsy are at risk of long-term issues, which may embrace extreme tricuspid regurgitation and coronary artery to proper ventricular fistula. Scheduling of Endomyocardial Biopsy As the transplanted heart is denervated, symptoms ensuing from graft rejection could remain silent and is most likely not recognized until late in the course of the course of a rejection episode. Consequently, surveillance biopsies are traditionally carried out at commonplace intervals from the time of transplantation. The recommended frequency for performing surveillance proper ventricular biopsy varies by middle. There has been a recent pattern in direction of a discount in the variety of procedures being carried out as improvements in immunosuppressive therapy and post-transplant management proceed to show a decline in the number of rejection episodes. The growth of other, noninvasive surveillance methods has further decreased the use of biopsy at some facilities. A typical biopsy schedule consists of performing the process weekly in the course of the first month, each 2 weeks for one more month and monthly till 6 months and then every two or 3 months till the tip of the first post-operative year, with yearly biopsies thereafter in higher-risk sufferers. This schedule is meant to reflect the final risk of allograft rejection which is highest within the first 6 months post-transplant. After the primary yr, any extra protocol biopsies are doubtless not to be of clinical significance given the very low 160 D. However, biopsies are performed anytime in cases of clinically suspected rejection. Repeat biopsies are performed 7�14 days after treatment of rejection to find a way to confirm resolution. Clinical Features of Allograft Rejection Histologically talking, acute rejection is observed as an inflammatory response of the host to the transplanted organ. As rejection is a histological diagnosis, there are tons of cases the place the patient could remain asymptomatic, especially with milder types of rejection. In circumstances the place there are medical features, signs of rejection may embody palpitations, tachycardia, arrhythmias, edema, dizziness or blackout spells, dyspnea, and a fever of one hundred �F or higher. Antigen recognition activates the complement system, together with an influx of neutrophils. Endothelial cells and platelets are induced to shed lipid particles from their membrane that promote coagulation; the resulting inflammation prevents vascularization of the graft, which suffers irreversible harm from ischemia. While this is probably the most drastic consequence of preformed antibodies to the graft, the presence of donor-specific antibodies is also associated with opposed outcomes even after profitable engraftment [9]. The development of the possible cytotoxic crossmatch, and subsequently the virtual crossmatch (mentioned in Chap. Such advances in perioperative administration and improvements in immunosuppression in latest times have led to a common decline in the rates of allograft rejection, although it still stays a big problem post-transplant. Hyperacute rejection is mediated by preformed antibodies to the allograft within the recipient. It sometimes presents following surgical engraftment and restoration of native circulation as an virtually immediate, aggressive and inevitably lethal immune assault on the organ. It is characterised by thrombotic occlusions and hemorrhage of the graft vasculature that begins minutes to 12 Cardiac Allograft Rejection, Surveillance and Treatment 161 variability of interpretation and discordance between pathologists remains, significantly for higher grades of rejection [13]. Panel (b) Grade 1R: Low power view of endomyocardial biopsy showing three focal, perivascular infiltrates without myocyte harm (H&E). Panel (c) Grade 2R: Low energy view showing three foci of damaging mono- nuclear cell infiltrate with regular myocardium intervening (H&E).
Specifications/Details
Gatifloxacin administration could be associated with extreme dysregulation of glucose homeostasis and can lead to either severe hypo- or hyperglycemia depression symptoms dsm 5 anafranil 10 mg visa. In mixture with other agents that impact repolarization anxiety 9 dpo anafranil 75 mg purchase otc, moxifloxacin has often been associated with life-threatening cardiac arrhythmias depression landform definition anafranil 25 mg without a prescription. Ciprofloxacin mood disorder unspecified icd 9 75 mg anafranil generic fast delivery, levofloxacin, and gatifloxacin are cleared primarily by the kidneys. Moxifloxacin can be partially metabolized by the liver, and gemifloxacin is metabolized primarily by the liver. All quinolones demonstrate comparable tissue penetration, being concentrated in prostate tissue, feces, bile, and lung tissue. As a result of a superb gram-negative spectrum, ciprofloxacin is certainly one of the primary antibiotics really helpful for remedy of urinary tract infections. It is the drug of alternative for Salmonella typhi (typhoid fever), and it is also recommended for treatment of Salmonella gastroenteritis when antibiotic therapy is critical. Ciprofloxacin is the really helpful remedy of cat scratch illness brought on by Bartonella henselae. With the exception of gemifloxacin, these brokers may additionally be used in gentle tissue infection during which a combination of gram-positive and gram-negative organisms is suspected. Given the worse toxicity profiles of the three newer agents (moxifloxacin, gatifloxacin, and gemifloxacin), levofloxacin ought to most likely be the fluoroquinolone of alternative for these infections. Gatifloxacin and moxifloxacin reveal moderate in vitro exercise in opposition to anaerobes and may be thought-about for the remedy of combined infections thought to embody anaerobes. Fear of selecting for resistant pathogens has led to their use being restricted in some hospitals. Also covers many different gramnegative organisms together with Escherichia coli, Salmonella, Shigella, Neisseria, and Legionella. Levofloxacin, gatifloxacin, moxifloxacin, gemifloxacin: a) Greater exercise against Streptococcus pneu-moniae, covers highly penicillin-resistant strains. These agents bind to the 50S ribosome at a site similar to that utilized by chloramphenicol. The oxazolidinones are bacteriostatic in opposition to staphylococcal species and enterococci. Reversible thrombocytopenia has been reported in association with prolonged remedy, and monitoring of platelet depend is beneficial for sufferers receiving two or extra weeks of linezolid. Because this agent is a weak inhibitor of monoamine oxidase, hypertension has been reported in affiliation with ingestion of enormous amounts of tyramine. Pseudoephedrine and selective serotonin reuptake inhibitors should be prescribed with caution. Like chloramphenicol, binds to the 50S ribosome subunit; inhibits the initiation of protein synthesis. Thrombocytopenia frequent with treatment exceeding 2 weeks; inhibitor of monoamine oxidase; avoid tyramine, pseudoephedrine, and serotonin uptake inhibitors. A combination of 30:70 quinupristin:dalfopristin has synergistic activity and has been named Synercid. These two brokers inhibit bacterial protein synthesis by binding to the 50S bacterial ribosome. Quinupristin inhibits peptide chain elongation, and dalfopristin interferes with peptidyl transferase exercise. It binds to bacterial membranes and causes rapid depolarization of the membrane potential. Synergy with aminoglycosides, -lactam antibiotics, and rifampin has been observed. Less generally, daptomycin administration has resulted in neuropathy related to a slowing of nerve conduction velocity. More lately, daptomycin remedy has also been associated with eosinophilic pneumonia. This antibiotic is accredited for the treatment of difficult skin and soft tissue infections by prone strains and for S. Toxicities embrace muscle ache and weakness related to creatine phosphokinase leak; no coadministration of statins. Within a bacterium, this antibiotic acts as an electron acceptor and is quickly decreased. Antabuse-like response can happen; mutagenic effects not confirmed in mammals, but the drug must be averted in pregnancy. Metronidazole is the drug of choice for remedy of pseudomembranous colitis attributable to overgrowth of C. Alterations within the sulfonyl radical decide lots of the pharmacokinetic properties of the compounds. Trimethoprim consists of two 6-member rings, considered one of which has two nitrogens and two amino teams, the opposite having three methoxybenzyl teams. Maculopapular drug rashes, erythema multiforme, Steven�Johnson syndrome, vasculitis (including drug-induced lupus), serum sickness-like syndrome, and anaphylaxis have been reported. Sulfonamides should be averted within the final month of being pregnant because they displace bilirubin bound to plasma albumin and enhance fetal blood ranges of unconjugated bilirubin. Competitively inhibit para-aminobenzoic acid incorporation, blocking folic acid synthesis; trimethoprim inhibits dihydrofolate reductase, potentiating sulfonamide exercise. Broad spectrum of exercise for gram-positive and gram-negative organisms, however resistance is widespread. Trimethoprim-sulfamethoxazole combination is the drug of alternative for Pneumocystis prophylaxis and treatment. All are metabolized by the liver, present process acetylation and glucuronidation, with the metabolites being excreted within the urine. Trimethoprim is excreted primarily by the renal tubules, and really excessive concentrations of lively drug are found within the urine. The half-life of trimethoprim is 9-11 hours matching the half-life of sulfamethoxazole. Sulfonamides are the therapy of alternative for Nocardia asteroides, and are helpful together with different brokers for the treatment of M. It can be utilized to treat a selection of other gram-positive and gram-negative pathogens. However, plasmid-mediated resistance is common, and therapy of most pathogens must be initiated solely after sensitivity is confirmed by microbiologic testing. Colistin this antibiotic was found within the 1980s, but abandoned due to fears of undue nephrotoxicity. Because of the progressive improve in multiresistant Gram-negative bacilli, the usage of colistin has been revisited. Complex combination of polymyxins and pure polypeptides that bind to bacterial lipopolysaccharide and disrupt the membrane barrier 2. Narrow spectrum, used to treat multiresistant Pseudomonas aeruginosa, Acinetobacter baumannii, Stenotrophomonas maltophilia, and Klebsiella pneumoniae. The polymyxins all have a robust positive charge and a hydrophobic acyl chain that binds with excessive affinity to the lipopolysaccharide bacterial membrane. Upon binding, colistin acts as a cationic detergent that disrupts the membrane barrier causing leakage of cell contents and eventual death of the bacterium. Risk elements for this complication include older age, preexisting renal insufficiency, low serum albumin, and coadministration of nonsteroidal antiinflammatory drugs or vancomycin. The onset of renal dysfunction often happens throughout the first week of administration and is reversible upon discontinuation in practically 90% of patients. In cystic fibrosis sufferers, colistin may be less nephrotoxic than aminoglycosides. Other rarer neurological manifestations related to administration embody seizures, vertigo, muscle weak point, confusion, hallucinations, partial deafness and visible loss. These neurological unwanted facet effects have been reported to shortly resolve upon discontinuing the drug. The half-life of the drug is approximately 14 hours and as quickly as per day therapy could also be preferable; nevertheless until medical research demonstrate no enhance in toxicity once per day administration, q12h dosing is the popular dosing interval. Colistin is cleared completely by the kidney, and dosing must be adjusted for renal failure (see Table 1. It demonstrates activity in opposition to most Gram-negative bacilli excluding Proteus, Pseudomonas mallei, B.
Syndromes
- Limb removal
- Calcium oxalate
- Throat swelling (may also cause breathing difficulty)
- If you cannot stop taking the medication because of disease, your high blood sugar, high cholesterol levels, and bone thinning or osteoporosis should be closely monitored.
- Occurs with other symptoms, such as headache, weakness, abnormal tongue movements, muscle tightening, or other movements that you cannot control.
- Headache
- Excessive bleeding
- You cannot get a deep breath or your breathing is getting harder, or faster.
- In organs, tissues, and cells
- Blood and urine tests
Related Products
Additional information:
While there have been advances in immunosuppression within the last 20 years chronic depression definition 10 mg anafranil cheap mastercard, improvements in long-term survival have plateaued [1] anxiety 34 weeks pregnant anafranil 25 mg purchase otc. Future enchancment in post-cardiac transplant survival is extra more likely to depression test channel 4 anafranil 75 mg generic fast delivery be achieved by concentrating on the mechanisms liable for long-term mortality anxiety 504 accommodations anafranil 10 mg buy mastercard. This includes cardiac allograft vasculopathy, which is actually a type of continual rejection and could probably be targeted successfully by theoretical induction of tolerance. Furthermore, complete tolerance would reduce the need for immunosuppression, and thus cut back malignancy-related problems. In order to obtain the holy grail of acquired tolerance, one should perceive the mechanisms behind persistent rejection and utilize novel methods to abrogate them; much work is ongoing in this area. Furthermore, present pharmacologic brokers demonstrated to reduce rejection also increase T-reg frequencies [4]. Thus, these alloantigen-induced T-reg cells are in a position to prevent acute as nicely as chronic graft rejection. Interestingly, whereas these T-regs can be induced by alloantigen pretreatment [5, 6], the presence of the allograft as the source of donor alloantigen is important for maintaining the unresponsive state [7]. The ability to generate and maintain these particular alloantigen reactive T-regs may theoretically induce tolerance in future, stopping rejection while remaining immunosuppression-free. While B-cells are recognized more as antibodysecreting cells within the pathogenesis of rejection, they also function as antibody-presenting cells that interact with T-cells [8], leading to antibody mediated rejection, and specific complement receptors through which adaptive immunity is regulated [9]. However, like T-regs, the function of B-regs in the potential induction of tolerance stays to be absolutely defined; how these findings can subsequently be exploited to preserve tolerance stays to be seen. In current years, researchers have tried to establish central tolerance by way of transplantation of donor bone marrow. However, all stories of this technique have resulted in loss of blended chimerism within months of transplantation [15], probably as a end result of inflammatory responses [16]. Thus far, 12 of the 19 patients have been effectively weaned off immunosuppression, with intact grafts and upkeep of stable blended chimerism. A new scientific trial entitled "Bone Marrow Transplant to Induce Tolerance in Heart Transplant Recipients" is presently happening on the University of Louisville [18] and outcomes are keenly anticipated. Further toleranceinduction research will depend on two completely different elements: additional investigation of the mechanism of tolerance, and additional research to increase safety and broaden the applicability of preliminary research utilizing enhanced stem cell transplantation. Thus, minimizing immunosuppression and immunosuppression-associated Strategies to Achieve Chimerism Chimerism, defined because the existence of two allogeneic cell lines, which might enable specific toler- 18 the Future of Heart Transplantation 239 complications while sustaining efficacy remains the goal of post-transplant administration. During the past few a long time, new medicine have been added into post-transplantation scientific practice. From the event of more powerful and particular immunosuppressants, especially helpful for sensitized sufferers (see Chap. A sustained T-cell response following antigen recognition requires costimulatory signals to be delivered through accent T-cell floor molecules. This highly particular mechanism of immunosuppression may also negate the undesired opposed results seen in different immunosuppressants. Eculizumab, a humanized monoclonal antibody directed towards the terminal complement protein C5, can be being investigated in a pilot trial in coronary heart transplant recipients. By inhibiting the cleavage of C5, it prevents the formation of the membrane assault complex [21]. Currently, therapeutic drug monitoring, medical evaluations, endomyocardial biopsy, echocardiography, and the T-cell immune assay are used as the principal instruments for rejection monitoring throughout drug weaning. However, pharmacogenetic polymorphisms could have the potential to predict future antagonistic occasions from certain immunosuppressants and more particularly, particular person dosages of different immunosuppressants. Further explication of those pharmacogenetic mechanisms would possibly lead to targeted dosing based mostly on genetic profiling. Hopefully with further explication of these pharmacogenetic mechanisms [28, 29], dosing equations that use genotype and relevant scientific variables could be developed, instead of dosing primarily based on weight. These equations can also have the flexibility to present transplant physicians more personalised targets of immunosuppression for patients (rather than the present instructed "range"). Genomics for Rejection Monitoring and Outcome Prediction the primary focus of care in organ transplant recipients has at all times been to prevent rejection. Kobashigawa together with monitoring of serum immunosuppressant levels, clinical assessments, echocardiography, tissue endomyocardial biopsy stays the gold normal. Most interesting is that most genomic testing can be done in the type of a laboratory test without requirement for invasive procedures or hospitalization. Further retrospective cohort studies have subsequently demonstrated associations between Allomap rating variability and threat of subsequent mortality [30, 31]. These plasma samples were collected longitudinally and compared to concomitant endomyocardial biopsy samples assessed by pathologists for grading of rejection over the course of the first 12 months post-transplant. These outcomes have been duplicated in a prospective 65-patient examine by De Vlaminick et al. In future, this software might have potential with regard to assessing clinically deteriorating sufferers in whom the analysis of rejection vs. Based on this, the probability of both the donor and recipient having a different allele was calculated to be approximately 12. Kobashigawa objective of genomic purposes in transplantation is to avoid invasive biopsy procedures. Notably, miR-155 is encoded within an exon of the gene B-cell integration cluster (bic), and B-cell and T-cell receptor activation as properly as toll-like receptor activation leads to elevated bic expression, suggesting a task of these processes in acute rejection [44]. Tissue and plasma samples were collected from 60 coronary heart transplant recipients, 30 of whom had acute rejection and 30 of whom were matched controls (matched on recip- ient and donor age, cold ischemic time, time from transplant to first biopsy, immunosuppression). Specifically, serum levels of miR-31, miR-92a and miR-155 had been considerably larger in the sera of sufferers with rejection in comparability with normal and the level of miR-10a was significantly lower. Both acute mobile and antibody mediated rejection, in addition to acute and persistent types of rejection have been detected with high accuracy using this modality. This avenue of genomic drugs provides thrilling potential, as they are ready to 18 the Future of Heart Transplantation 243 assist scale back or eventually replace the invasive endomyocardial biopsy for the screening of graft rejection. Furthermore, with the traditional histopathological criteria, there are many "borderline" or ambiguous cases. Based on preliminary outcomes, expression of transcript units reflecting T cell and macrophage infiltration, and gamma-interferon results correlated strongly with one another and with transcripts indicating tissue/myocardium damage. Regenerative Medicine Stem Cell Therapy Central to the donor coronary heart shortage is the excessive demand for donor hearts in the face of an growing prevalence of end-stage coronary heart failure necessitating transplant. Thus, a therapy that might cause the diseased coronary heart to regenerate and regain operate would be a panacea in this field. Over the final twenty years, intense investigations into the injured coronary heart and potential for cardiac regeneration have taken place, intersecting the fields of developmental biology, stem cells and biomaterials. The area of stem cell biology is of particular interest and is the area by which greatest strides have been made in current years. A crucial question in stem cell remedy is the relevance of various cell types which may result in cardiovascular cell era if transplanted. However, additional analysis has since elucidated a more oblique mechanism involving downstream paracrine effect through angiogenesis and left ventricular reworking [55]. Skeletal muscle stem cells, or myoblasts, have also been trialed, with some profit, however there have been security concerns with regard to arrhythmic occasions attributable to the non-integrated skeletal muscle cells [56]. Recently, cardiosphere-derived cells rising from percutaneous endomyocardial biopsy right ventricular samples, which combine the heart-derived stem cell property along with mesenchymal stem cells, have additionally shown promising therapeutic benefits in animal models [61� 63]. Unfortunately, long-term cell engraftment rates after transplantation of stem cells remains low [64], and it could be that the benefits noticed from these therapies are because of downstream paracrine results exerted quite than direct regeneration of tissue from the transplanted cells. Overall, while the sphere of regenerative drugs is both intriguing and promising, the mechanisms of enchancment are at present beyond our complete understanding. Organ Engineering the sphere of tissue engineering applies bioengineering rules with the purpose of constructing biological substitutes for failing or absent tissues and organs. The bioartificial tissue would then be used as a "patch" on the diseased organ, whereas a bioartificial organ can be transplanted to replace the failing organ (or to take the place of an absent one). Traditionally, the engineering of a viable coronary heart has been considered infeasible, given the advanced nature of myocardium as a contractile tissue with particular structural and physiological specs. Regarding cardiac tissue patches for the diseased coronary heart, quite a few new approaches have been explored. In rat models, neonatal rat cardiomyoctyes were cultured on Poly (N-isopropylacrylamide)-grafted polystyrene dishes and indifferent as a square cell sheet at 20 �C temperature. These sheets have been stacked collectively via induction of a hydrophobic/hydrophilic surface switch to make thicker contractile sheets, eventually achieving a one-centimeter-thick engineered tissue layer.
Usage: q.3h.
Azithromycin: Dose-Children � 6 months � 12 years 10 mg/kg as quickly as every day for three days up to depression symptoms online quiz generic 50 mg anafranil with mastercard a maximum of 200 mg/dose in 3�7 years depression group activities 25 mg anafranil cheap with amex, 300 mg/dose in 8�11 years 400 mg/dose in 12�14 years and 500 mg/dose in more than 14 years boiling point depression definition chemistry generic anafranil 75 mg line. Magnesium salts: 5�10 mL bedtime every day depression relationships 10 mg anafranil generic, lowering dose gradually till constipation is relieved. Malathion: Topical: medical supervision is required for kids lower than 6 months of age. Scabies-apply to entire body excluding head and neck, enable to dry, wash off after 24 hours. Children lower than 2 years ought to have a thin film utilized to scalp, face and ears, avoiding eyes and mouth. Mannitol: A test dose could additionally be given to assess renal operate � 200 mg/kg (maximum 12. Commonly used pressure is the Edmonston Zagreb strain grown in human diploic cell tradition. Hytatid illness 200�400 mg bid or tid for 3�4 weeks, less effective than albendazole. Mebeverine hydrochloride: Oral-3�4 years seventy five mg/day, 4�8 years a hundred and fifty mg/day, 9�10 years 300/day and greater than 10 years 450 mg/day in three divided doses 10�20 min before meals. Mefloquine: Treatment-Oral 15 mg/kg adopted by 10 mg/kg 8�12 hours later (maximum 1. Prophylaxis-Oral first dose 1 week earlier than coming into malarious space (may be started earlier to make certain drug is tolerated) and given weekly on similar day for six weeks and continued for four weeks after return from malarious space. Melphalan: Always seek the advice of the present remedy protocol for particulars of dosage and scheduling. When given as main immunization-3 doses at 4 weeks intervals beginning at 6�8 weeks, if began after sixteen weeks age-2 doses at 4 week intervals and if began more than 1 12 months age-only 1 dose is required. Mercaptamine (cysteamine): Oral Initially less than 12 years 2�3 mg/kg/dose and more than 12 years 100 mg four instances daily adopted by maintenance of 12. Mercaptopurine: Always seek the guidance of the current remedy protocol for particulars of dosage and scheduling. Meropenem: Newborn � forty mg/kg/day in 2 divided doses lower than 7 days and in three divided doses more than 7 days. Pneumonia, peritonitis, neutropenia, septicemia � 60 mg/kg/day in three divided doses (maximum 1 g/dose). Meningitis and life threatening infections-120 mg/kg/day in three divided doses (maximum 2 g/dose). Mesalazine [5-aminosalicylic acid (5-asa)]: Acute cases-15�20 mg/kg/dose 3 times every day adopted by upkeep of 10 mg/kg/ dose 2�3 occasions daily. Mesna (sodium mercaptoethane sulfonate): Uroprotectant- Injection: Mesna doses range however in follow doses higher than 100 percent (mg:mg) of the whole every day oxazaphosphorine dose are used. May be given in 5 divided doses, 15 min before and 3, 6, 9 and 12 hours after alkylating agent dose. Always seek the guidance of the current therapy protocols for particulars of dosage and scheduling. Methionine: Oral less than 6 years 1 g 4th hourly (maximum 4 g/day) greater than 6 years 2. Severe uncontrolled psoriasis unresponsive to conventional therapy-oral-child 2�18 years-initially 200 �g/kg (maximum 10 mg) as quickly as weekly increased according to response to 400 �g/kg (maximum 25 mg) as soon as weekly. Vitiligo-Adolescent-Vitiligo is reversible but not equally reversible in every affected person. Repigmentation happens more rapidly in fleshy areas such because the face, stomach, and buttocks and less quickly over much less fleshy areas such as the dorsum of the hands or toes. Initial exposure time must be conservative and not exceed that which is predicted to be onehalf the minimal erythema dose. Determine the remedy interval by the erythema response; usually once a week remedy or less is recommended. Pigmentation might begin after a couple of weeks, but important repigmentation could require 6�9 months of treatment. Methylene blue: Methemoglobinemia-1�2 mg/kg or 25�50 mg/m2; could also be repeated after 1 hour if needed. Methylprednisolone: Dosage might have to be reduced in sufferers with hepatic impairment. If a affected person is receiving oral steroids then these are usually stopped on the days that methylprednisolone is given. Intermittent doses of metolazone may help to overcome diuretic resistance which may happen due to fluid overload, mesenteric congestion (inadequate absorption) and low renal blood move. Patients with hepatic impairment: no specific dosage adjustment is specified because of restricted knowledge. Use with warning in sufferers with hepatic disease since minor alterations of fluid and electrolyte stability might precipitate hepatic coma. Patients with renal impairment: no dosage adjustment is required; however, higher doses could also be wanted to achieve medical targets in some sufferers with end-stage renal illness. Increase dose interval to 12 hours in renal impairment (CrCl less than 20 mL/min/1. Miconazole: Topical on skin apply on affected space 2 times daily for 10 days after lesions have healed. Androgenic alopecia � Apply 12 hourly not exceeding 2 mL/day for no much less than forty five days � often more than 4 months to arrest hair fall. To enhance fats absorption in cystic fibrosis-2�18 years 400 �g/day in 4 divided doses. Mitoxantrone (Mitozantrone): Always seek the assistance of the current therapy protocol for particulars of dosage and scheduling. Careful supervision is beneficial when treating patients with extreme hepatic insufficiency. Montelukast: Oral 2�5 years four mg, 6�14 years 5 mg and greater than 14 years 10 mg once day by day in the evening. Mupirocin: Dosage description: topical cream -apply to affected space three times every day for up to 10 days; nasal ointment apply to the internal floor of each nostril 2�3 times a day for 5�7 days; ointment apply to affected area 2�3 times every day for up to 10 days. Renal-Oral 600 mg/m2/dose 2 occasions daily-first dose within 72 hours after transplant (maximum 2 g/ day). Liver-Oral 10 mg/kg/dose 2 instances every day rising to 20 mg/ kg/dose 2 instances daily-first dose within 72 hours after transplant (maximum 1 g/day). Patients with hepatic impairment: Exercise warning when using nalidixic acid in sufferers with liver illness; nonetheless, no specific dosage changes are indicated. Patients with renal impairment: Decrease the dose by half in sufferers with a CrCl lower than or equal to 20 mL/min. Naloxone: Newborn infant-Do not administer to newborns whose mother is suspected of narcotic abuse as a withdrawal syndrome could also be precipitated. Ensure institution and maintenance of enough air flow earlier than administering naloxone. Specifically indicated for reversal of respiratory depression on new child of mother who has obtained narcotics inside four hours of supply. For maintenance therapy in the therapy of gentle to average chronic bronchial asthma: Oral inhalation dosage (metered dose inhaler): Adolescents and children greater than or equal to 6 years: 2 sprays (1. Dosage may be decreased to 2�3 times per day once desired medical response obtained. Prevention of exercise-induced bronchospasm: Oral inhalation dosage (metered dose inhaler): Adolescents and kids greater than 12 years: A dose of two sprays (1. Allergic conjunctivitis: Ophthalmic dosage: Adolescents and youngsters greater than 3 years: 1�2 drops in each eye twice daily at common intervals. Children lower than 6 years: Dependent on route of administration and indication for remedy. Patients with renal impairment: Specific tips for dosage changes 1200 vip. Eye drops-Superficial eye infection-1 drop 2�4 times day by day, severe an infection 1 drop every 15�20 min initially then reducing frequency as infection will get managed. Neostigmine: Newborn myasthenia gravis-Oral 1�2 mg initially half hour before feed adopted by 1�5 mg/dose (adjusted based on response) 6 instances day by day. This will ship the initial beneficial nesiritide maintenance infusion fee of zero.
Tags: anafranil 25 mg effective, cheap anafranil 10 mg without a prescription, anafranil 10 mg online, anafranil 50 mg order line, buy anafranil 75 mg low price, discount anafranil 10 mg otc, anafranil 50 mg order with amex, order 25 mg anafranil visa, anafranil 75 mg order line, anafranil 10 mg with amex, generic anafranil 10 mg visa, 75 mg anafranil buy with amex, 10 mg anafranil buy fast delivery, purchase anafranil 10 mg on-line, cheap anafranil 25 mg with amex, 10 mg anafranil cheap free shipping
10 of 10
Votes: 175 votes
Total customer reviews: 175
Customer Reviews
Milok, 62 years: While older studies looking at obstruction from all causes show low technical success charges [13,14], more modern data and information looking at stones particularly indicate a more favorable end result, probably as a outcome of more trendy instrumentation. Coadministration of zidovudine and acyclovir increases the danger of creating lethargy. A variety of different virulence elements contribute to the flexibility of urinary pathogens to survive and develop within the urinary tract. Fluidics Analyze 500-5000 cells / second Simultaneous illustration of a number of antigens Sheath pressure Sheath tum A narrow stream of cells flowing in a core inside a wider sheath stream.
Silvio, 51 years: Types Columnar cell variant Cribiform morular variant Encapsulated follicular variant Encapsulated variant Follicular variant Macrofollicular variant Microcarcinoma variant Nodular fasciitis lil Cobryn, 41 years: Hypotension can develop with both an infection and mimic different forms of gram-negative sepsis. Such an analysis is cumbersome and the profit of this classification in routine clinical care is unclear. Less commonly, catheters may be contaminated by hematogenous unfold attributable to a primary an infection at one other site. The biatrial technique was the standard until the mid-to-late 1990s till the bicaval methodology predominated. Kippler, 58 years: It can also be the only criticism, hepatic abscess being one of the common infectious causes of fever of undetermined origin (see case three. We usually use a narrow strip of anesthesia tape with cut up ends to enable easy removing when the patient is in the prone position. It is crucial that all necrotic tissue be resected and that the margins of resection include bleeding healthy tissue. First, the pediatric ureter is shorter, extra elastic, and extra distensible than that of an grownup [37] and these options can promote simpler fragment passage and prevent ureteral impaction. Bengerd, 38 years: Psychiatric evaluation also needs to be incorporated into the general analysis process for coronary heart transplant itemizing. Loss of high-frequency hearing occurs in 3-14% of patients treated with aminoglycosides. Diarrhea varies in volume and consistency: a) Watery with enteropathogenic, enterotoxigenic, enteroaggregative, and Vibrio b) Mucousy with Shigella c) Bloody with Shigella, Campylobacter, entero-hemorrhagic, and enteroinvasive E. Validity implies that a query evokes a response that correlates with the end result measure. Kayor, 63 years: Worldwide entry to holmium laser technology has not been achieved largely as a outcome of cost. Alternatively, transmission may occur via blood transfusions throughout transplant or even endomyocardial biopsy (through an contaminated probe), as has been reported. This virus can be the most common reason for recurrent Mollaret aseptic meningitis. A second method for controlling viral infection is to modify the host immune response.
