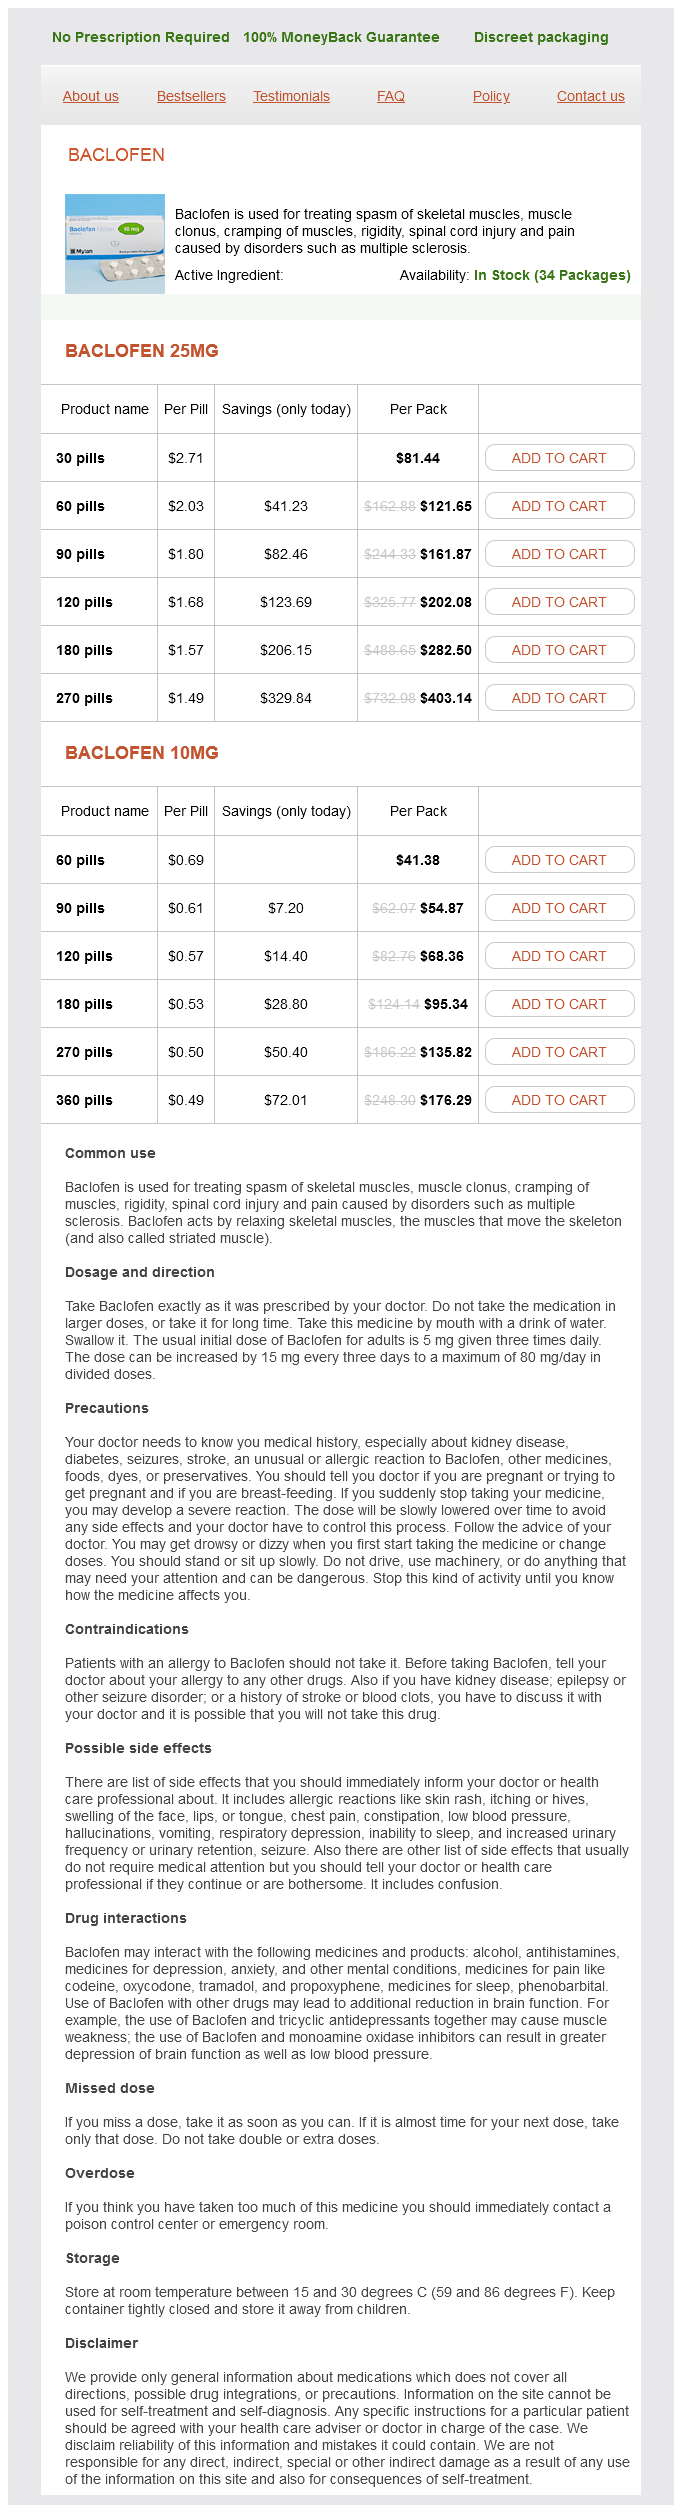
Baclofen 25mg
- 30 pills - $81.44
- 60 pills - $121.65
- 90 pills - $161.87
- 120 pills - $202.08
- 180 pills - $282.50
- 270 pills - $403.14
Baclofen 10mg
- 60 pills - $41.38
- 90 pills - $54.87
- 120 pills - $68.36
- 180 pills - $95.34
- 270 pills - $135.82
- 360 pills - $176.29
Baclofen dosages: 25 mg, 10 mg
Baclofen packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 715
Only $0,52 per item
Description
Achieving an intact tympanic membrane eliminates the need for sufferers to maintain strict water precautions muscle relaxant and painkiller 10 mg baclofen cheap with mastercard. Pain ought to elevate concern for other processes within the head and neck and prompt a thorough evaluation muscle relaxant use in elderly baclofen 25 mg without prescription. Vertigo must be thoroughly investigated previous to muscle relaxant trade names baclofen 25 mg quality surgery to avoid working on an ear with an ongoing vestibulopathy muscle relaxant rocuronium baclofen 25 mg purchase mastercard. History of cleft palate surgery ought to elevate concern for Eustachian tube dysfunction and continual or recurrent infections. Physical Examination Physical examination with a microscope enables thorough inspection of the canal and center ear space. Location of perforation: Central versus marginal 1) Marginal perforations with a "path sign," or keratin migrating from the sting, recommend squamous epithelium within the center ear. Evaluate status of middle ear mucosa, if possible: Cholesteatoma, mucosal hypertrophy, or in depth granulation tissue suggest the necessity for concurrent mastoidectomy. Look for signs of previous surgery and/or chronic Eustachian tube dysfunction, similar to retraction of the tympanic membrane and negative center ear strain (atelectasis), otitis media with effusion, and/or tympanosclerosis, which may point out continual infections. Evidence of otitis media with effusion or unfavorable middle ear pressure (atelectasis) in the contralateral ear demonstrated to be poor prognostic findings in a research of pediatric sufferers by Collins et al. Audiogram Not all tympanic membrane perforations are accompanied by conductive listening to loss. Small perforations may be associated with normal listening to, whereas a near-total perforation may cause a 35- to 40-dB conductive listening to loss. This quantity of listening to loss in the setting of a small perforation should raise concern for a disrupted or fixed ossicular chain. The potential want for ossicular chain reconstruction should be anticipated prior to surgical procedure. Hearing loss: Sudden versus gradual 880 Myringoplasty and Tympanoplasty 881 Patients with combined listening to loss require a different strategy. If, however, a severe combined loss precludes sufficient achieve and comfort from a listening to help, surgical correction of the conductive part may higher facilitate aural rehabilitation. With a Lempert speculum, native anesthetic is injected in a four-quadrant style into the external auditory meatus. The needle tip is placed just lateral to the bone-cartilage junction, and the answer is infiltrated until the pores and skin blanches. Unless vital active illness exists, despite maximal medical remedy, aural amplification should be recommended. General anesthesia: We perform the overwhelming majority of our cases underneath common endotracheal anesthesia to be sure that the affected person stays still for the whole process. Additional injection behind the ear must be infiltrated for harvesting fascia or a deliberate postauricular strategy. An attempt ought to be made to achieve a dry ear previous to surgical procedure with otic drops and/or systemic antibiotics. Preoperative medical clearance prior to anesthesia is really helpful for all patients. Preoperative testing (laboratory tests, electrocardiogram, chest radiograph) per hospital tips four. Risks: Worsening of listening to or full hearing loss, vertigo, short-term or permanent changes in taste due to disruption of the chorda tympani nerve, facial paresis or paralysis, an infection, failure of the graft to heal causing persistent or recurrent perforation, and/or numbness of the superior auricle if undergoing a postauricular approach 5. Reminder: After a quantity of procedures, local tissue for grafting may not be readily available and various sources must be thought-about, similar to perichondrium, periosteum, and even tissue from the contralateral ear. Positioning � Bed turned 180 degrees with feet towards anesthesia � Supine with head turned to the contralateral facet Perioperative Antibiotic Prophylaxis � Generally not indicated for routine tympanoplasty or myringoplasty � For grossly infected ears or if a prosthesis will be placed, one dose of Ancef, or clindamycin if the affected person is allergic to penicillin, may be given. Monitoring � We use facial nerve monitoring for nearly all otologic instances being carried out underneath basic anesthesia; nevertheless, nerve monitoring is elective and not considered the standard of take care of myringoplasty or tympanoplasty. The edges of a contemporary stellate perforation are everted from the medial floor of the tympanic membrane. When squamous epithelium is now not present in the center ear, the sides are reapproximated. Operative Risks � � � � � Worsening of hearing or full listening to loss Tinnitus Vertigo, normally short-term Taste disturbance due to injury to the chorda tympani nerve Facial paresis or paralysis: Allow local anesthesia to wear off earlier than continuing with further testing and/or exploration. Ossicular chain reconstruction and mastoidectomy particulars can be present in Chapters 132 and 134, respectively. Alternatively, use compressed and dehydrated free areolar tissue or fascia from the postauricular area. Then place a fascia graft medial to the perforation and place Surgicel or Gelfoam lateral to the grafted perforation to additional secure the graft. Surgical Technique Surgical technique for tympanic membrane repair can be categorized as inlay, underlay (medial), and overlay (lateral) procedures. Lateral grafts are preferred in circumstances of prior failed surgical procedures, total or near-total perforations, or in patients with severely diseased tympanic membranes with myringosclerotic plaques or remnants that must be resected prior to reconstruction. Myringoplasty by definition addresses only the tympanic membrane, whereas tympanoplasty incorporates inspection of the center ear and reconstruction of the ossicular chain when essential. If restricted mobility of the lateral chain and/or fixation of the incus-stapes complex is noted, then separation of the incudostapedial joint or additional inspection for malleal head fixation may be necessary. A, Myringoplasty of the right tympanic membrane with a posteroinferior perforation. The edges of the perforation are freshened, Gelfoam is placed within the middle ear, and an areolar or compressed adipose tissue graft (stippled area) is positioned by way of the perforation, positioned medial to the tympanic membrane, and supported by the Gelfoam. The edges of the stellate perforation are approximated and supported with a cigarette paper patch or a Steri-Strip. The fringe of the perforation is circumferentially freshened to take away epithelium from the medial margin and promote native bleeding. The inset emphasizes that the medial edge of the perforation should be eliminated to remove squamous epithelium from the center ear. This step might slightly enlarge the perforation; be careful not to enlarge it beyond transcanal visualization. Tragal cartilage is harvested with perichondrium preserved on one or both surfaces. The graft size and form are reproduced utilizing the identical right-angled hook previously used to measure the perforation but intentionally exaggerated by 1 to 2 mm. A blade scores the complete cartilage edge circumferentially, and the perimeters curl apart, creating an appearance just like butterfly wings. Use the same instrument that was used to measurement the perforation to size the cartilage. Prep and drape in ordinary sterile fashion and inject local anesthesia as described beforehand. The graft in place viewed transcanal with one edge elevated for functions of illustration. Vascular strip incisions are made alongside the tympanomastoid and tympanosquamous suture lines. The inferior extent of the incision is just inferior to the lobule; all the time watch out to not extend beyond the mastoid tip and threat harm to the facial nerve. The periosteum and canal skin are elevated from medial to lateral beginning on the annular ligament. Use a Freer elevator to elevate the fascia off the underlying muscle; then reduce a 2 � 2 cm piece of true fascia to use for grafting. Reflect the vascular strip out of the ear canal and place it throughout the self-retaining retractor. The canal skin is kept connected at the bony-cartilaginous junction and gently folded laterally out of the canal. A drill and continuous suction-irrigation are used to enlarge the bony canal and remove the anterior and inferior canal wall bulges. Care should be taken when drilling posteriorly to avoid the facial nerve and anteriorly to avoid drilling into the temporomandibular joint. For small perforations in which the drum remnant surrounds the manubrium, both the surgeon can separate the remnant from the manubrium, or the graft can be placed lateral to the manubrium in a "lateral patch" technique. Sheehy describes putting the graft such that the apex of the slit comes into contact with the tensor tendon. Alternatively, place a properly sized piece of thick Silastic sheeting lateral to the graft to hold it in good place during the therapeutic course of. We recommend then putting one suture to shut the postauricular periosteal flap and stabilize the auricle. The dehydrated fascia is trimmed to an oval shape, and a slit is cut to permit for placement medial to the manubrium.
Rhizoma Coptidis (Goldthread). Baclofen.
- Are there any interactions with medications?
- Digestive problems and other uses.
- How does Goldthread work?
- What is Goldthread?
- Are there safety concerns?
- Dosing considerations for Goldthread.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96480
The esophagus is a muscular conduit extending from the inferior portion of the pharynx to the superior portion of the stomach muscle relaxant oral 10 mg baclofen buy with amex. At the approximate stage of the sixth cervical vertebra infantile spasms 2 year old 25 mg baclofen order with visa, the esophagus begins at the pharyngoesophageal junction in the hypopharynx and descends to the level of the eleventh thoracic vertebra spasms in your stomach 10 mg baclofen purchase fast delivery, the place it enters the cardia portion of the abdomen spasms hiatal hernia baclofen 25 mg purchase overnight delivery. A second leftward curve of the esophagus can be appreciated because it crosses the descending aorta previous to getting into the esophageal hiatus of the diaphragm; nevertheless, some sources have additionally noted the thoracic esophagus to have a proper curvature because of the principle stem bronchus. Approximately 16 cm from the upper incisors, the primary and narrowest constriction happens on the cricopharyngeal sphincter. At 23 to 27 cm from the higher incisors, the second constriction happens on the degree of the left main stem bronchus. The last constriction happens at the gastroesophageal sphincter, 38 to forty cm from the upper incisor enamel. The esophagus lacks a serosa, a novel attribute that differentiates it from the rest of the gastrointestinal tract. Transnasal endoscopy exhibiting a cervical osteophyte (O) displacing the epiglottis anteriorly (E). Oftentimes, patients could also be referred for a swallow evaluation with a speech-language pathologist to identify salient options of the dysphagia not reported by the affected person. This analysis may additionally be useful to establish the potential location of pathology, in addition to to start swallowing remedy for the patient if wanted. A modified barium swallow also can shed light on the dynamic means of swallowing and level to areas of concern. B, Barium esophagram of a patient with dysphagia and a large anterior cervical osteophyte (black arrow). Esophagoscopy and Hypopharyngoscopy 319 an inflammatory response with extravasation, which can be seen with barium. Rigid instrumentation also confers the advantage of permitting bigger suction cannulas and larger caliber devices to be used for retrieval of international bodies. In some circumstances a cardiology clearance could additionally be wanted for sufferers with important cardiopulmonary history. Flexible esophagoscopy permits for visualization of the gastroesophageal junction and improved instrumentation in sufferers with limited vary of movement at the neck or obstructing osteophytes. Transoral esophagoscopy is typically performed underneath sedation and topical anesthesia, whereas transnasal esophagoscopy is performed with topical anesthesia only. Transnasal esophagoscopy is nicely suited for the office setting, is of minimal danger, and permits for sufferers to return residence without need for statement. This procedure could be carried out with comparatively little affected person discomfort and is associated with mostly minor problems, corresponding to epistaxis. It is imperative that prior to any procedure, a full dialogue of the risks and benefits be mentioned with sufferers in a way suited to their stage of understanding. According to recent research, transnasal esophagoscopy could be helpful in altering the course of management in male patients, overweight patients, and particularly these sufferers with a history of dysphagia related to head and neck most cancers. Rigid esophagoscopy is more advantageous in evaluating the hypopharynx, cricopharyngeal sphincter, and cervical esophagus. Oftentimes, redundant mucosal folds can disguise Surgical Technique � the patient is positioned into the sitting place either upright or slightly reclined. After decongestion, cotton pledgets with tetracaine are positioned for further anesthesia. The decrease esophageal sphincter and gastroesophageal junction ought to be assessed before getting into the stomach. A, Esophagoscopes and long suction cannulas; devices obtainable in variety of sizes. From high to bottom are forceps with serrated edges, cup forceps, and alligator forceps. A cup forceps is most suitable for biopsies, whereas the other two are most useful for the retrieval of overseas bodies. The thumb of the left hand is used as a fulcrum for the instrument to stop strain over the incisors and is used to advance the instrument whereas the best hand is used only to information the esophagoscope by altering the angle of entry. The nondominant hand all the time stays on the scope to stabilize it whereas the dominant hand can be utilized to change angle of motion. Care should be taken to never advance the scope when pressure is encountered because this might increase the chance of perforation. Common Errors in Technique � Inadequate anesthesia resulting in affected person discomfort and poor cooperation � Passing the scope via narrow parts of the nasal cavity, causing the affected person vital pain � Failure to consider the esophageal mucosa whereas withdrawing the scope Rigid Esophagoscopy � Anesthesia: General anesthesia with endotracheal intubation � Positioning: Neutral place with out head extension. The base of the tongue and the larynx are displaced anteriorly till the axis of the endoscope is parallel to the longitudinal axis of the lumen. Gastrografin esophagogram, lateral view, demonstrating an esophageal perforation (arrow) with extravasation of distinction materials into the mediastinum. Complications � Dental trauma � Chipped tooth, avulsion of tooth � With a tooth fracture or avulsion, urgent consultation with a dentist or oral surgeon is warranted. Esophageal perforation is a doubtlessly devastating complication after both inflexible or flexible esophagoscopy. According to the literature, the speed of esophageal perforation is roughly 1%; however, this fee can increase to as a lot as 6% if sufferers are undergoing concurrent procedures, such as dilation of a stricture or removal of a overseas body. Most research counsel the next price of perforation for inflexible esophagoscopy in contrast with flexible procedures. The authors recommend that patients for whom esophagoscopy was performed by junior residents could also be most susceptible to injury and perforation. Editorial Comment Endoscopy of the aerodigestive tract is a vital element within the analysis of sure sufferers with issues within the head and neck. Ruling out synchronous main cancers and different lesions of the esophagus can be essential when evaluating patients with cancer of the hypopharynx and cervical esophagus. Kadakia and Chai have given the essential particulars for the different strategies of esophagoscopy. Flexible esophagoscopy is both safer and simpler than inflexible esophagoscopy for this function. In addition, many sufferers with cancer of the hypopharynx or cervical esophagus require prolonged enteral access, and careful placement of the flexible esophagoscope to facilitate percutaneous endoscopic gastrostomy is required. Some particular issues to bear in mind are that use of assorted laryngoscopes to displace the endotracheal tube anteriorly will help in visualizing the postcricoid space and esophageal inlet. These areas and the anterior, lateral, and medial walls and apex of the pyriform sinus are tough to visualize with versatile scopes unless the larynx is displaced. Telescopic visualization along with microlaryngoscopy for the better assessment of the mucosal extent of the cancer and documentation of the stage of the most cancers for each early and superior cancers is necessary for cancers in both surgical websites. Laryngoscopes may additionally be used to facilitate publicity of the esophageal inlet for esophagoscopy when this entry is troublesome. In some circumstances the angle of approach or the most cancers or perhaps a cervical osteophyte will make access troublesome. It is commonly helpful to have the surgeon place the laryngoscope and advance it while an assistant does the air insufflation, suction, and maneuvering. It is important to remove the air within the stomach on removing the scope, and the mucosa is greatest evaluated on the best way out rather than on the way in which in. For cancers of the hypopharynx and cervical esophagus, determination of the inferior extent of the cancer is necessary in determining resectability, notably with reference to placement of vascularized tissue for circumferential reconstruction. For cancers that reach past the cervicothoracic inlet, consideration of complete esophagectomy and gastric pullup quite than free tissue transfer is advisable to avoid lifethreatening leaks of saliva or gastric contents into the higher mediastinum. Unexpected ache and fever should be warnings of an unrecognized complication postoperatively. An exception is percutaneous endoscopic gastrostomy, when prophylactic antibiotics are indicated. The operator must be cautious to not push the scope aggressively against areas of resistance b. The operator ought to change the angle of the scope with the nondominant hand and guide the scope on the oral entry point with the dominant hand c. Esophagoscopy can be a versatile software for therapeutic and diagnostic intervention 2. If esophageal perforation is suspected postoperatively, which of the following are necessary measures to take Prospective multi-institutional transnasal esophagoscopy: Predictors of a change in management. The cricopharyngeus muscle is innervated by the pharyngeal plexus, which is composed of contributions from the vagus and glossopharyngeal nerves.
Specifications/Details
Speech therapy to start instructing with electrolarynx previous to muscle relaxant trade names generic baclofen 25 mg with visa discharge if indicated 13 muscle relaxant menstrual cramps 10 mg baclofen safe. Barium swallow on postoperative days 5 to 7 to consider for small fistula; if unfavorable muscle relaxant valium baclofen 25 mg free shipping, begin a liquid diet and advance as tolerated 14 muscle relaxant 2265 25 mg baclofen buy. Otalgia is a common criticism in patients with laryngeal most cancers as a result of referred pain from a. The more than likely cause of fever, elevated white depend, and erythema of neck skin postoperatively is a. Survival of T4aN0 and T3+ laryngeal cancer patients: a retrospective institutional study and systematic review. Salvage complete laryngectomy after exterior beam radiotherapy: a 20-year expertise. Early feeding after complete laryngectomy results in shorter hospital stay without increased threat of problems: a retrospective case-control examine. Tumor quantity as a prognostic factor for local management and overall survival in superior laryngeal most cancers. The hypopharynx forms the inferior a half of the pharynx and is positioned instantly behind the larynx. It has three subsites-that is, postcricoid, posterior pharyngeal wall, and pyriform sinuses bilaterally. Total laryngopharyngectomy may also be carried out for primary laryngeal tumors with extension to the aforementioned websites. Total laryngopharyngectomy includes removal of the larynx as properly as the hypopharynx and posterior pharyngeal wall, leading to a circumferential defect. More intensive cancers involving the cervical esophagus require complete laryngopharyngoesophagectomy. Options embody myocutaneous flaps (pectoralis major or latissimus dorsi) or fasciocutaneous free flaps (anterolateral thigh, radial forearm), jejunal free flaps, and gastric pull-up procedures. Contralateral nodal metastases may occur in cancer of the medial wall of the pyriform sinus and bilateral nodal metastases might happen with most cancers of the postcricoid area. Referral to a nutritionist or dietician may be indicated preoperatively, as properly as placement of enteral feeding access. Reconstructive choices have to be evaluated prior to placement of feeding entry, as stomach and jejunum are potential donor sites. Physical Examination � Evaluation of the larynx and pharynx with flexible laryngoscopy is obligatory. Evidence of restrictive lung disease must be noted, as this may be a relative contraindication for pectoralis major flap reconstruction with a large pores and skin paddle. This syndrome consists of iron deficiency anemia, esophageal webs, dysphagia, weight reduction, angular stomatitis, and atrophic glossitis. Prealbumin, albumin, thyroid stimulating hormone, and 124 Total Laryngopharyngectomy a hundred twenty five Indications (Table 17. In sufferers with a big obstructive cancer, awake tracheostomy under native anesthesia may be the most secure choice. Tumor mapping allows for better prediction of deliberate most cancers resection and coordination with the reconstructive surgeon. Key Anatomic Landmarks � the hypopharynx consists of the pyriform sinuses, the postcricoid mucosa, and the posterior pharyngeal wall. The postcricoid area is from the arytenoid cartilages to the inferior border of the cricoid cartilage and varieties a connection between the bilateral pyriform sinuses. The pyriform sinuses lengthen from the pharyngoepiglottic folds to the superior facet of the cervical esophagus and are sure medially by aryepiglottic fold, the arytenoid cartilages, and the cricoid cartilage and bound laterally by the thyroid cartilage. An apron incision is deliberate with incorporation of the tracheostomy web site with extension laterally to allow for bilateral neck dissection. Subplatysmal flaps are elevated to the level of the hyoid bone superiorly and laterally, exposing both sternocleidomastoid muscle tissue. The cervical fascia is incised along the anterior border of the sternocleidomastoid muscle tissue. The fascia on the inferior border of the submandibular gland is incised to identify the posterior belly of the digastric muscle and related to the fascial incision at the superior border of the sternocleidomastoid muscle. Outer tunnels are developed between the strap musculature and the sternocleidomastoid muscle tissue. Neck dissection could additionally be carried out individually or left in continuity with the main specimen. Arterial stumps together with lingual, facial, superior thyroid, and transverse cervical arteries are preserved to enable for microvascular anastomosis. Venous stumps including exterior jugular, anterior jugular, and inside jugular branches corresponding to widespread facial and transverse cervical veins ought to be maintained, until oncologic resection requires sacrifice of the inner jugular vein. Strap muscular tissues are divided superior to the tracheostoma, if current, or above the manubrium. In these instances, the thyroid isthmus is divided and the lobes are free of their attachment to the trachea. Certain cancers might require removing of one or both lobes of the thyroid gland with the principle specimen. Inner tunnels are developed between the carotid sheath and larynx along the prevertebral fascia. The hyoid bone is uncovered and the suprahyoid musculature is incised and dissected off of the superior aspect of the hyoid bone. The central portion could additionally be grasped with a towel clamp and retraced laterally in either course to expose the lateral cornua. Each cornu is retracted medially to rotate the hyoid away from the hypoglossal nerve and lingual artery. Dissection is sustained bilaterally alongside the hyoid till each cornu could be freed utilizing the finger loops of a hemostat for retraction. Depending on the location of the cancer, the larynx may or may not be skeletonized as in a total laryngectomy. If limited circumferential resection is indicated, the larynx may be rotated and the pharyngeal constrictor muscles incised alongside the lateral border of the thyroid cartilage contralateral to the most cancers. The pyriform sinus mucosa is reflected off the thyroid lamina utilizing a Freer elevator. Alternatively, the deep cervical fascia could also be divided medial to the carotid artery alongside the prevertebral fascia and the pharynx bluntly mobilized off the prevertebral fascia, assessing for tumor extension previous the buccopharyngeal fascia. If circumferential mobilization is carried out, the pharynx may be entered above the hyoid contralateral to the positioning of most superior extent of the cancer. Pharyngeal mucosal incisions are made horizontally along the posterior pharyngeal wall to free the upper pharynx and full larynx. Large cancers of the pyriform sinus could require resection of a portion of the base of the tongue as a superior margin. Tracheal incisions are carried out next, typically between the primary and second tracheal rings. The anterior tracheal wall is sutured to the skin to prevent retraction of the distal trachea into the mediastinum. If cervical esophageal resection is indicated, incisions are made below the cancer. Wide margins must be taken, as hypopharyngeal cancers might have submucosal spread with diffuse local spread a common finding at surgical procedure. Some cancers could necessitate mediastinal tracheotomy or manubrial resection for removal of superior mediastinal lymphadenopathy. The inferior facet of the tracheal stoma could additionally be accomplished previous to reconstruction. Half-vertical mattress sutures are placed, taking care to drape the skin over exposed cartilaginous rings. Circumferential pharyngeal reconstruction is then accomplished by the reconstructive group (Table 17. Nasogastric tubes are positioned previous to pharyngeal reconstruction in the absence of gastrostomy or jejunostomy tubes.
Syndromes
- Aneurysm
- If your child tries to climb into your bed at night, unless he is afraid, return him to his bed as soon as you discover his presence. Avoid lectures or sweet conversation. If your child simply cannot sleep, tell him he may read or look at books in his room, but he is not to disturb other people in the family.
- Serum ferritin
- Nephritis
- Blood clot
- Changes in the vagina (prolapsed vagina)
- Hepatitis
- Pregnancy
Related Products
Additional information:
Early ligation of the superior and inferior thyroid pedicles will diminish blood loss muscle relaxant metabolism baclofen 10 mg buy discount on line. Hemorrhage from the posterior side of the thyroid bed following Massive and Substernal Goiter 553 supply of the substernal component is managed by strain or packing and cautious identification and ligation of the bleeding websites muscle relaxant egypt 25 mg baclofen overnight delivery. Injury to the recurrent laryngeal nerve often outcomes from extreme traction on the nerve throughout mobilization muscle relaxer zoloft discount 25 mg baclofen with mastercard. The use of steady laryngeal nerve monitoring identifies this sort of injury and allows the surgeon to modify the method muscle relaxant in pediatrics cheap 10 mg baclofen overnight delivery. If a loss of sign is encountered, deferring administration of the contralateral lobe should be thought-about. A Penrose or suction drain could help to stop the buildup of subcutaneous air. Thyroidectomy is efficient in relieving positional dyspnea in 82% of sufferers with goiter and 88% of sufferers with substernal goiter. Substernal thyroidectomy has been related to resolution of pulmonary hypertension and heart failure. Dysphagia related to compression of the esophagus or pharynx can also be attributable to other processes. Patient-reported outcomes have detected improvements in swallowing-related signs 1 yr after surgical procedure, however recurrent laryngeal nerve harm negates any profit from surgical procedure on outcome. Substernal goiters are regularly found as an incidental finding on routine imaging for another downside, corresponding to metastatic workup or motorized vehicle accident. Some sufferers could have significant compression of the trachea, esophagus, or nice vessels. The majority of symptomatic sufferers can count on reduction of symptoms after surgical elimination of the goiter. A new classification system for retrosternal goitre based mostly on a scientific evaluate of its problems and administration. Electrophysiological neural monitoring of the laryngeal nerves in thyroid surgery: review of the present literature. Spread of goiters outside the thyroid bed: a review of 190 instances and an analysis of the incidence of the varied extensions. Postoperative vocal fold palsy in patients undergoing thyroid surgical procedure with steady or intermittent nerve monitoring. Hemorrhage Hoarseness/voice change Hypoparathyroidism Stridor Wound infection Suspected hemorrhage after surgery must be managed with surgical exploration and evacuation of the hematoma. If hemorrhage is associated with fast enlargement of a hematoma and dyspnea, the wound should be opened on the bedside to relieve stress on the airway. Formal exploration may be undertaken within the working room after the patient is safely intubated. Patients present process surgical procedure must be extubated within the operating room when potential. Reintubation may be needed, but an evaluation of vocal cord mobility should be undertaken, if possible. Wound infection after thyroidectomy is rare and normally represents a small unrecognized tracheal or esophageal perforation. This could be managed with antibiotics and placement of a drain into the wound; typically a Penrose drain will suffice. Preoperative surgical analysis of a patient suspected of having a substernal goiter consists of the entire following except: a. Potential instant problems of a total substernal thyroidectomy embody all of the following besides: a. Contraindications for substernal thyroidectomy include the entire following except: a. Of the following preoperative components, which is least associated with an improvement of symptoms after thyroidectomy History of previously handled thyroid most cancers 1) Central neck recurrence after thyroidectomy is often invasive because of anatomic proximity, in addition to disruption of natural tissue planes. Thyroid most cancers is a curable disease with growing incidence and therapy methods. This corresponds with the widespread use of screening modalities and improved well being care availability. With more instances being detected in early levels, the incidence of invasive thyroid cancer is comparatively low, starting from 5% to 25%. Patients with a excessive danger of invasive thyroid most cancers should be recognized and have cross-sectional imaging preoperatively. Conversely, efforts must be made to spare the nerve if preoperatively it was decided to be useful. Shave resection could also be acceptable for restricted invasion into the larynx, trachea, and esophagus however with elevated rates of native recurrence. Transmural invasion into the viscera of the neck typically requires more aggressive margin-negative resection. Examine the thyroid for fixation to underlying structures and overlying skin and assess motion with swallowing. Preoperative ipsilateral vocal fold paralysis is very predictive of invasive thyroid cancer, and these patients ought to obtain superior cross-sectional imaging. Regional metastases and recurrent plenty should be biopsy-proven prior to surgical remedy. Rising thyroglobulin or thyroglobulin antibodies may point out recurrent or metastatic illness. Ultrasound 1) Performed routinely for all thyroid most cancers evaluations 2) May establish invasion into surrounding constructions, though research have proven a wide range of sensitivity and specificity 3) Operator dependent 4) May be helpful for surgical planning if performed by the working surgeon b. Major organ resection should be prevented, if possible, in the case of incidental finding of invasion if affected person has not been recommended preoperatively. Limiting morbidity and surgical danger in broadly metastatic or unresectable, poorly differentiated thyroid carcinoma Preoperative Preparation 1. Discussion/informed consent with affected person concerning treatment objectives and extent of resection a. Many research fail to show survival distinction between aggressive and conservative surgical procedure. Local management rates range and conservative surgical procedure might require repeated surgical procedure and eventual salvage. The surgeon must be prepared for the wide range of surgical resections and reconstructions that could be required. When transmural invasion is suspected, reconstructive choices should be obtainable, together with microvascular surgery and thoracic surgical procedure support. Surgical resection remains the hallmark of treatment for thyroid most cancers, invasive or otherwise. Optimal resection ought to end in adverse margins with extensive resection of tumor and involved constructions a. Surgery for invasive thyroid cancer typically requires general anesthesia with endotracheal intubation. Reverse Trendelenburg or elevated head of mattress to promote venous drainage away from the neck Perioperative Antibiotic Prophylaxis 1. Major head and neck surgery warrants a preincisional antibiotic dose, sometimes a first-generation cephalosporin for gram-positive protection. If upper aerodigestive tract breach is anticipated, protection for anaerobic bacteria should be added with metronidazole or clindamycin. May present info relating to functional standing of the nerve intraoperatively within the case of surgical procedure of invasive illness and may help to information extent of surgical procedure and treatment of the contralateral facet c. Should not substitute direct identification and preservation by the surgeon Key Anatomic Landmarks 1. Extension into the hypopharynx might happen via the piriform sinus, which is intently associated with the lateral fringe of the thyroid cartilage. Invasion occurs from direct extension from the thyroid or paratracheal lymph node metastases. Adherence and superficial invasion into the peritracheal fascia and perichondrium occur first. Transmural invasion sometimes happens between the cartilaginous rings with feeding vessels that traverse the soft tissue. The esophagus is generally resistant to invasion and invasion sometimes includes outer muscular layers with out intraluminal invasion.
Usage: t.i.d.
Local flaps: the palatal island flap for reconstruction of palatal lesions is a single-stage mucoperiosteal flap that could be a dependable supply of regional vascularized delicate tissue that obviates the necessity for prosthetic rehabilitation spasms body buy generic baclofen 25 mg online. The temporalis muscle is a gorgeous option for reconstruction for the next causes: 1) the donor website and the defect are throughout the identical operative field and therefore the necessity for more advanced free tissue transfers could be avoided spasms esophagus purchase 25 mg baclofen mastercard. Microvascular free tissue switch: Reconstruction of defects after inferior maxillectomy are nicely summarized under the theme of useful palatomaxillary reconstruction spasms mid back generic 10 mg baclofen. Horizontal classification: a-palatal defect only muscle relaxant injections neck order baclofen 25 mg mastercard, not involving the dental alveolus; b-less than or equal to � unilateral; c-less than or equal to � bilateral or transverse anterior; d-greater than � maxillectomy. Letters check with the rising complexity of the dentoalveolar and palatal defect and qualify the vertical dimension. Patient with a detachable denture that restores good oral-nasal separation and supplies for an excellent beauty appearance. Transfer to a devoted head and neck most cancers unit with nurses educated within the care of head and neck sufferers. There is normally no need for intensive care unit�level of care for this surgical procedure except microvascular reconstruction is employed. If microvascular reconstruction is carried out, the reconstructive surgeon dictates the extent of care. Pain medication: Opioid ache medicine corresponding to oxycodone 5 to 10 mg every 4 hours as needed ought to present adequate analgesia in the perioperative interval. Meticulous oral hygiene with chlorhexidine mouthwash swish-and-spit after each meal is essential to help stop an infection. Prosthetic rehabilitation and native or regional flap 1) Full liquid or pureed diet starting on postoperative day 1 c. This is used in the interim while the ultimate prosthesis is delayed until the maxillectomy cavity matures. If there are plans for adjuvant radiation therapy, the ultimate prosthesis might have to be delayed until after completion of radiation to guarantee a correct fit. Early ambulation with or with out bodily therapy is essential for postoperative rehabilitation. Patients with bone invasion (T4 lesions) or with highgrade salivary gland cancers are referred for postoperative radiation remedy. B, After total inferior maxillectomy, the defect was reconstructed with a temporalis muscle flap, which shortly turned mucosalized. Perforation of soppy tissue on the nasal aspect of the palate with removal of palatal bone as a deep margin b. Repair intraoperatively with soft tissue via a prosthesis, local, regional, or microvascular free flap. Meticulous oral hygiene and perioperative antibiotic prophylaxis will forestall most infections. Treat with postoperative antibiotics covering for oral flora (gram-positive, gram-negative, and anaerobic bacteria) similar to ampicillin-sulbactam or clindamycin for penicillin-allergic patients with pus and systemic indicators of an infection (fever or leukocytosis) Alternative Management Plan 1. The palliative care physicians discuss points such has symptom administration (pain, starvation, thirst) and the main points of hospice care. Editorial Comment: Inferior Maxillectomy the exhausting palate and alveolar ridge give rise to a broad variety of conditions starting from necrotizing sialometaplasia, a benign situation, to squamous cell carcinoma, which is the most frequently encountered malignant tumor. Malignant tumors and most benign conditions are treated surgically because radiation utilized to bone structures can lead to osteoradionecrosis. When I was first introduced to the inferior maxillectomy it was carried out through a lateral rhinotomy strategy, which offers wide publicity but at the value to the patient of a conspicuous scar. I soon realized that most tumors arising in the space of the palate might be eliminated successfully through a transoral strategy, and I abandoned the lateral rhinotomy incision. Loss of oronasal separation, which is fundamental to each swallowing and talking, was managed with a prosthesis besides in circumstances of a complete inferior maxillectomy, which was reconstructed with a temporalis muscle flap. Reconstruction of the palate with free tissue transfer introduced extra lately was not embraced fearing that closing the defect would preclude cancer surveillance. Another major step ahead within the administration of patients with squamous cell carcinoma is the administration of the neck. It was believed that cancers of the onerous palate and alveolar ridge, which occurred much less regularly than most cancers in different sites such as the tongue and the ground of the mouth, had a different pattern of metastasis. I grew to become conscious of a study carried out at the University of Virginia during which the members of the Department of Otolaryngology noticed a price of metastasis of approximately 35%, which is the same as in other sites within the oral cavity. A subsequent examine performed in our department7 validated the findings of the aforementioned study. Based on this examine, we tailored using the selective neck dissection, bilateral or unilateral primarily based upon the location and extent of the primary. Cancer of the onerous palate and maxillary alveolar ridge: approach and functions. Cervical metastasis from squamous cell carcinoma of the maxillary alveolus and exhausting palate. Management of the neck in a affected person with squamous cell carcinoma involving the left maxillary alveolus extending to midline contains which levels According to the Brown and Shaw maxillary defect classification, a maxillary defect involving the orbital rim, but preserving the eye and involving larger than half of the palate falls into which of the next courses A maxillary defect not involving the orbit and fewer than half of the onerous palate is finest reconstructed with which of the next Combined intraoral and lateral temporal method for palatal malignancies with temporalis muscle reconstruction. Thoracodorsal artery scapular tip autogenous transplant: vascularized bone with an extended pedicle and versatile soft tissue. Scapular angle osteomyogenous flap in postmaxillectomy reconstruction: defect, reconstruction, shoulder function, and harvest technique. Versatility and donor web site morbidity of the lateral higher arm flap in intraoral reconstruction. The palatal island flap for reconstruction of palatal and retromolar trigone defects revisited. Iliac crest inside oblique osteomusculocutaneous free flap reconstruction of the postablative palatomaxillary defect. The epidemiology of oral cavity, pharyngeal and esophageal most cancers outside of North America and Western Europe. In addition, this minimally invasive surgical procedure might avoid opposed consequences of chemoradiation with comparable end result. This could be accomplished both by way of transoral robotic surgical procedure or endoscopy-based transoral laser microsurgery. The transoral method has been expanded with the development of transoral robotic surgery. This technological enchancment supplies threedimensional visualization for exact dissection and safety of margins. There are some advantages of robotic surgery, together with shorter hospitalization, rapid useful recovery, avoidance of tracheostomy, and reduced need for nasogastric tube feeding. In the previous, oropharyngeal cancers have been treated with surgical procedure followed by radiation. Surgical resection normally required mandibulectomy or mandibulotomy and elimination of pharyngeal musculature, which resulted in significant morbidity. Because of the practical and beauty impairments and current growth of organ preservation regimens, chemoradiation has turn into the therapy of alternative in many sufferers with cancer of the oropharynx. There are rising data that much less aggressive remedy may be performed on this group of patients with out sacrificing the nice cure price. The oropharynx is the middle part of the throat that extends from the junction of the delicate and exhausting palate superiorly to the superior fringe of the epiglottis and the hyoid bone inferiorly, circumvallate papillae of the tongue anteriorly, and pharyngeal wall posteriorly. It includes the base of the tongue, the taste bud, the lateral and posterior pharyngeal partitions, the tonsils, and tonsil pillars. It is noteworthy that the swallowing operate is adversely affected each by surgical resections and chemoradiation. Dysphagia and poor talking might lead to social issues, however aspiration may cause lifethreatening issues. Therefore applicable number of the type of surgical strategy is sort of essential within the administration of cancer of the oropharynx. The prognosis and remedy of most cancers of the oropharynx are strongly associated to the involvement of cervical lymph nodes. The incidence of lymphatic metastasis is relatively excessive, relying on the subsite. Even in patients with no adenopathy on the time of prognosis, elective ipsilateral or bilateral neck treatment is required either through a neck dissection or by radiation therapy.
Tags: generic baclofen 10 mg free shipping, generic baclofen 25 mg on line, cheap 25 mg baclofen overnight delivery, 10 mg baclofen sale, purchase 25 mg baclofen free shipping, 10 mg baclofen generic overnight delivery, buy baclofen 25 mg online, baclofen 10 mg purchase mastercard, 25 mg baclofen cheap overnight delivery, 25 mg baclofen purchase mastercard, generic baclofen 10 mg line, baclofen 10 mg effective, quality 25 mg baclofen, baclofen 10 mg without prescription, baclofen 10 mg without a prescription, baclofen 25 mg buy fast delivery
9 of 10
Votes: 38 votes
Total customer reviews: 38
Customer Reviews
Fraser, 41 years: With the patient positioned supine with the top turned away, the medial half of the ear canal is filled with the predetermined anesthetic agent.
Lukjan, 30 years: Most lesions are located anterior to this line because about 10%�30% of patients have anterior compartment pneumatization; in contrast, the posterior petrous bone (osseous labyrinth) hardly ever pneumatizes.
Merdarion, 33 years: It can be a dynamic examine and may be done with concurrent salivary stimulation with food.
Carlos, 43 years: Master Techniques in Otolaryngology-Head and Neck Surgery: Skull Base Surgery Wolters Kluwer Philadelphia.
Tufail, 31 years: Dissection of the posterior stomach may generally facilitate identification of the hypoglossal nerve.
