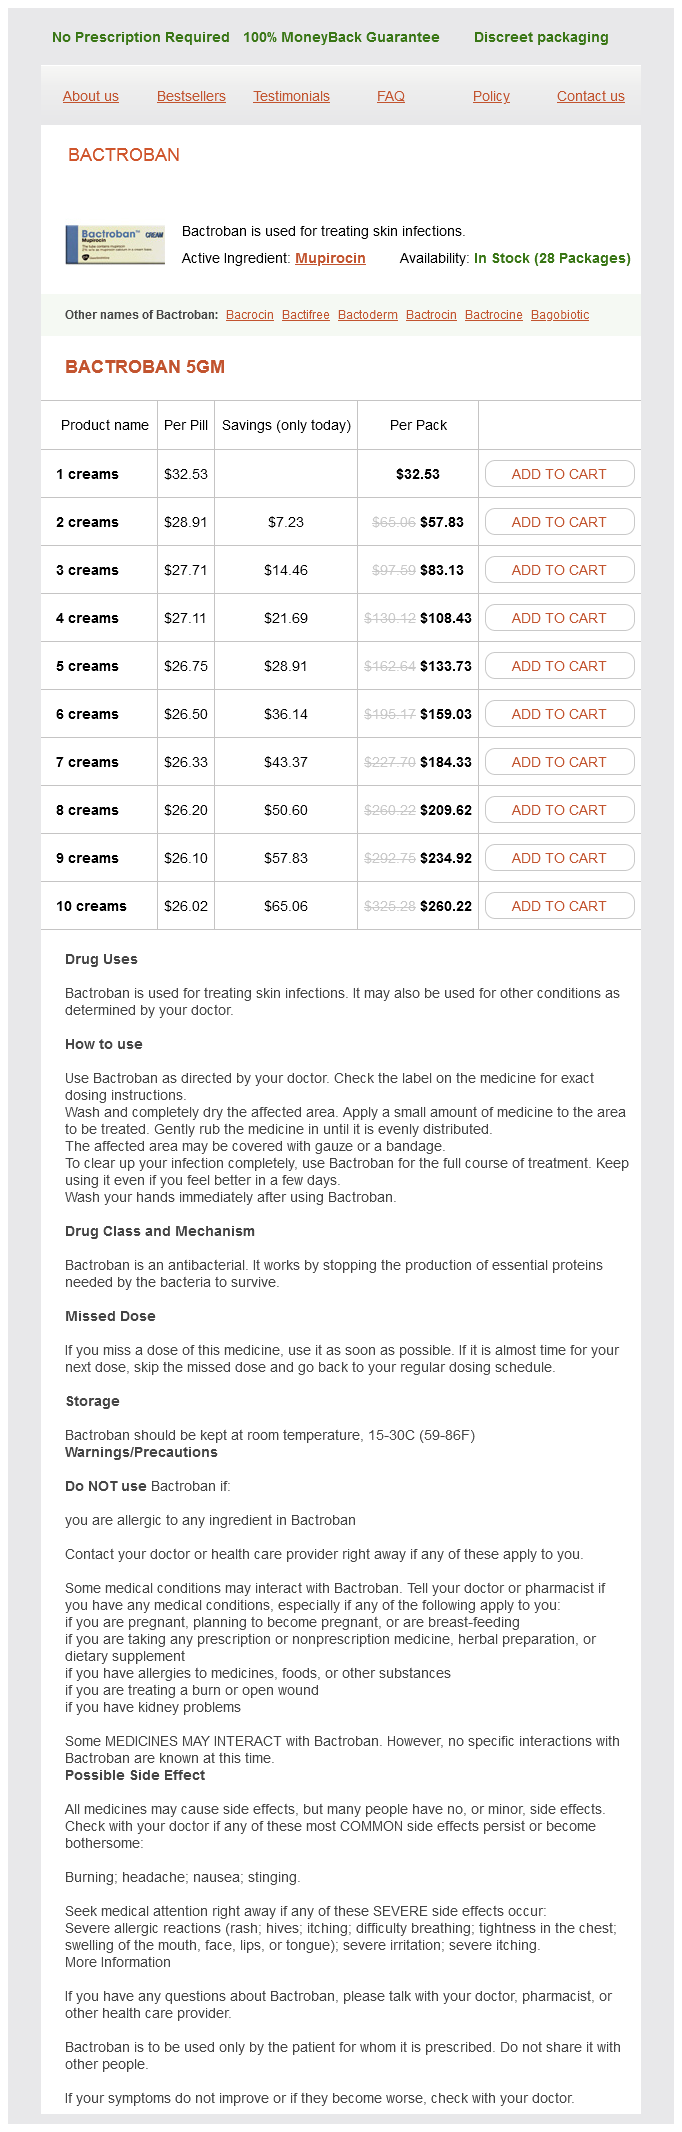
Bactroban 5gm
- 1 creams - $32.53
- 2 creams - $57.83
- 3 creams - $83.13
- 4 creams - $108.43
- 5 creams - $133.73
- 6 creams - $159.03
- 7 creams - $184.33
- 8 creams - $209.62
- 9 creams - $234.92
- 10 creams - $260.22
Bactroban dosages: 5 gm
Bactroban packs: 1 creams, 2 creams, 3 creams, 4 creams, 5 creams, 6 creams, 7 creams, 8 creams, 9 creams, 10 creams
In stock: 590
Only $27,65 per item
Description
Prognosis is dependent upon the pace of therapy and the quantity of small bowel affected acne quistes 5 gm bactroban generic overnight delivery. Diagnostic pearls: Inhomogeneous wall thickening of the cecum and ascending colon; occasionally skin care urdu tips buy bactroban 5 gm with mastercard, spreading to the distal ileum and/or appendix acne and hormones generic bactroban 5 gm visa. Clostridium difficile�induced acute inflammation of the colonic mucosa with or with out submucosa acne inversa images 5 gm bactroban order otc. Diagnostic pearls: Pancolitis with nodular circumferential wall thickening (15 mm). Histologically, an inflammatory strategy of the mucosa with deep ulcerations and necrosis due to native ischemia. Usually a complication of antibiotic therapy with copious nonbloody diarrhea, stomach cramps, and tenderness. Dilation of the descending colon and segmental wall thickening with "goal" sign (a). Restriction of changes to the left-sided colon is indicative of ischemic origin (b). Oval to round pericolonic fatty mass (arrow) in the left lower stomach with hyperattenuating ring, surrounded by stranding of mesenteric fatty tissue. Pancolitis with nodular circumferential wall thickening ("accordion" sign) (a) and targetlike appearance of colonic wall (b). Diagnostic pearls: Actinomycosis: Predominantly within the ileocecal and rectosigmoid colon. Salmonellosis/yersiniosis: Predominantly ileum, however can also unfold to cecum and proper colon. Schistosomiasis: Multiple polypoid filling defects within the sigmoid colon or rectum. Worm infestation (Ascaris and Trichuris): Bolus of ascariasis might trigger a solitary filling defect. Trichuriasis might induce excessive mucus production and numerous irregular filling defects. Inflammation and subsequent infection of the appendix because of an acute luminal obstruction. Diagnostic pearls: Dilated appendix (6 mm), hyperattenuation and thickening of appendicular (and generally additionally cecal) wall, and periappendicular fats stranding. Inflammation with or with out perforation of saccular outpouchings within the antimesenteric colon wall. Schistosomiasis: Filling defects (granulomas) are a late manifestation of heavy infestation and persistent exposure to Schistosoma. Worm infestation: Trichuris trichiura is a relatively common inhabitant in the cecum and appendix. An appendicular abscess seems as a well-demarcated fluid collection in the proper decrease quadrant of the pelvis. Occurs in 10% to 25% of patients with diverticulosis due to obstruction of the diverticular neck and subsequent diverticular distention and perforation. Staging and administration per Hansen and Stock: Stage zero: Asymptomatic diverticulosis Stage I: Inflammation restricted to bowel wall. A partially cystic mass with fluid layers may be noticed in cases of anticoagulation-induced bleeding. Extraluminal/intra-abdominal gasoline not specific for colon perforation (alternative causes may be barotraumas and mechanical ventilation). Diagnostic pearls: Thickening of the bowel wall and "sandwich" signal of bowel wall (edematous submucosa between hyperattenuating mucosa and serosa). Idiopathic persistent inflammation affecting primarily the colorectal mucosa and submucosa. Diagnostic pearls: Pancolitis with thickened targetlike colonic wall (10 mm), luminal narrowing, stranding of pericolonic fat, and fibrofatty perirectal proliferation (presacral house 2 cm). Iatrogenic-induced injury to the bowel wall as a result of therapeutic belly irradiation. Diagnostic pearls: Acute adjustments: Nonspecific wall thickening, goal signal Chronic changes: Bowel wall thickening, fibrosis, and luminal narrowing Perirectal fats proliferation (10 mm) with accompanying pararectal fibrosis (halo sign). Rare concomitant bowel affection in patients who underwent bone marrow transplantation. Diagnostic pearls: Diffuse nonspecific mural thickening involving the entire intestine from the abdomen to the colon, as properly as stranding of mesenteric fat and lymphadenopathy. Diagnostic pearls: Multiple, up to 2-cm submucosal low-density cystic lesions within the rectum with or without sigmoid. Initial irritation is confined to the mucosa; thus, barium study and endoscopy are extra delicate for detecting these modifications. Ulcerative colitis Chronic irritation confined to the mucosa and exclusively progressing retrograde and continuous from the rectum to the cecum. Radiation enteritis might occur up to 20 y after remedy, radiation colitis inside 2 y after radiation. Clinical symptoms are profuse secretory diarrhea, cramping, and malabsorption attributable to immunocompetent T cells of the donor reacting in opposition to host tissues. The cysts are full of thick mucinous materials and lined by a cuboidal flattened epithelium. Diagnostic pearls: Normal or thickened rectal wall with small hypoattenuating polypoid lesions. Comments May be idiopathic, associated with chronic obstructive pulmonary illness, or secondary to surgical procedure or ischemia. Diagnostic pearls: Large, strongly enhancing gentle tissue mass within the bowel wall which will contain necrosis and ulceration. Diagnostic pearls: Multiple strongly attenuating tumors characteristically positioned on the mesenteric aspect of the colon. Colonic wall hematoma due to anticoagulation remedy seems as partially cystic submucous mass with fluid layers (arrow). Diagnostic pearls: Attenuating infiltrating mass with a cauliflower-like floor look and subcutaneous tissue/perirectal fat infiltration. Diagnostic pearls: Polypoid delicate tissue mass is discovered in the appendix or proper colon, less commonly within the rectum. Diagnostic pearls: Intraluminal or intramural mass, usually no or only distinct attenuation; extracolonic development, necrosis, and perforation. Large, broad-based intraluminal tumors in elderly sufferers suggest a much less frequent malignant carcinoid. Histologic subtypes are mucinous (signet ring cells), mucin-producing, and colloid. Modified Dukes staging: Stage A (T1N0M0): Restricted to (sub)mucosa Stage B (T2or3N0M0): Limited to serosa/pericolonic tissue Stage C (T2or3N1M0): Lymphatic spread Stage D (any T, any N, M1): Distant metastases Primary tumors of the uterus, ovary, prostate, bladder, pancreas, kidney, and stomach might immediately invade nearby colonic segments or induce distant seeding via ascites. Diagnostic pearls: Features often are indistinguishable from these of major colonic most cancers. Diagnostic pearls: Simple obstruction: Dilated fluid-filled, thin-walled loops of small gut with or without air�fluid levels. One or several grossly distended fluid-filled U-shaped loops with two adjoining limbs exhibiting a zone of abrupt transition. Strangulating obstruction: Slight circumferential wall thickening and enhancement (target sign), in addition to engorgement of mesenteric vessels, indicate mild ischemia. Typical intrinsic causes are intraluminal lesions, neoplasms, inflammations, and infections. Colonic pseudo-obstruction Pseudo-obstruction could additionally be induced by ischemia, inflammation (toxic megacolon), impaired neuromuscular function (diabetic neuropathy, uremia, and hypokalemia), postoperative paralytic ileus, and iatrogenic causes (vagotomy and irradiation). However, perisigmoidal fats stranding on axial scan signifies stadium Dukes B (b), however native lymphadenopathy led to a ultimate stage Dukes C. Segmental wall thickening and luminal narrowing within the descending colon as a outcome of a metastasis from adenocarcinoma of the pancreas head, which can be visible. Incidental finding throughout preoperative digital colonography (b) in a affected person with a nonpassable sigmoid cancer (same affected person as in. The right triangular ligament types from the coalescence of the superior and inferior plica of the proper coronary ligament and separates the proper subphrenic area from the Morison pouch.
Matricaria eximia (Feverfew). Bactroban.
- Rheumatoid arthritis.
- Are there any interactions with medications?
- Preventing migraine headache.
- Dosing considerations for Feverfew.
- How does Feverfew work?
- Are there safety concerns?
- Fever, menstrual irregularities, arthritis, psoriasis, allergies, asthma, dizziness, nausea, vomiting, earache, cancer, common cold, and many other conditions.
- What is Feverfew?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96896
Note the spigelian hernia on the right aspect with presence of belly fat between the interior and external indirect muscular tissues acne antibiotics bactroban 5 gm purchase overnight delivery. On the proper facet acne 4 days before period buy generic bactroban 5 gm line, the inguinal canal accommodates solely stomach fats; on the left skin care experts buy generic bactroban 5 gm online, it incorporates gentle tissue acne 2 weeks before period bactroban 5 gm cheap on-line, representing herniated bowel. Note the inguinal ligament, a thin gentle tissue�equivalent linear structure dorsal to the hernia. A femoral hernia is seen on the left facet protruding medially to the femoral vessels, anteriorly to the pubic ramus, and posteriorly to the inguinal ligament. Diagnostic pearls: Bowel loop interposed between obturator (posteriorly) and pectineus (anteriorly) muscle. Comments Typically occurs in elderly girls because of a laxity in or defect of the pelvic floor. Obturator hernias have a right-sided preference, thus predominantly include small bowel loop, such because the ileum. Lumbar hernia Rare acquired hernia within the flank region, often between ages 50 and 70 y. Diffuse however localized inflammation of the subcutaneous fatty tissue with or without involvement of muscle sheets and/or peritoneal fascia. Diagnostic pearls: Ill-defined localized hyperdensity of the subcutaneous fatty tissue in patients after surgical procedure or skin damage. Diagnostic pearls: Diffusely increased density of fatty tissue and subtle subcutaneous gasoline collections (lung window). May end result from a direct route of an intraabdominal process similar to Crohn illness, diverticulitis, appendicitis, and perforated neoplasms. The muscular layers of the stomach wall are separated by low-attenuation pus with discrete nodular fuel collections. Ill-defined localized stranding of ventral subcutaneous fatty tissue in a affected person a couple of days after laparoscopic appendectomy. Diffuse muscular atrophy often is related to congenital or acquired neuromuscular illness. Focal atrophy usually is a delayed complication of transverse or subcostal stomach incision, in all probability due to a denervation harm. Trauma Hematoma Round or spindle-shaped mass, usually in the rectus sheath or subcutaneous tissue. Density of the lesion decreases and approaches that of plain serum after 2 to four weeks. May occur spontaneously because of muscle strain or secondary to trauma, surgical procedure, or anticoagulation. Seat-belt injuries could lead to abdominal wall disruption, resulting in a transverse tear of the rectus muscle. May result from penetrating injury of the abdominal wall, thoracic accidents, pressured ventilation, or aerogenous germs. Trapped air Rhabdomyolysis Typical causes embody extreme delicate tissue harm, surgical interventions, and compartment syndrome. Other causes are medications (neuroleptica, statins, cocaine, and propofol), malignant hyperthermia, alcohol intoxication, autoimmune reactions, inflammation, and muscle an infection. Benign neoplasms Lipoma Smooth encapsulated fatty mass within subcutaneous fatty tissue, belly muscles, or adjacent tendon sheaths. It is commonly attainable to indirectly visualize lipomas throughout the subcutaneous fatty tissue by contemplating the space-occupying impact of the lesions in the form of facet differences in the outer shape of the stomach wall. Usually a number of round delicate tissue lots within the subcutaneous tissue of the belly wall. Comments Histologically, a benign neoplasm of thin, fibrous stroma that surrounds a number of vascular channels lined by a single layer of endothelial cells. Large hemangiomas appear heterogeneous and may include a central fibrotic cleft of low density. Neurofibroma Neurofibromas primarily lie within the subcutaneous fatty tissue of patients with neurofibromatosis. Abdominal wall musculature and spinal muscular tissues are atrophic and hardly identifiable due to fatty alternative. The affected person reveals important spinal stenosis (arrow), which can have triggered muscular atrophy of the trunk. Diagnostic pearls: Ill-defined heterogeneous mass with inhomogeneous distinction enhancement. Diagnostic pearls: Well-defined, spherical, strongly enhancing delicate tissue mass, restricted to one facet of the abdomen. Diameter of metastases characteristically already measures several centimeters at the time of analysis. Desmoid tumor Rare, locally invasive fibroblastic proliferation arising from the aponeurosis of belly muscular tissues. Twenty-nine p.c of sufferers with Gardner syndrome develop desmoid tumors of the abdominal wall. Characteristic locus for metastases of malignant melanoma, however main tumor itself may look alike. Diagnostic pearls: If malignant melanoma is suspected major, check mesentery (originates from ectoderm) for further metastases. Tumor extension per continuitatem Neoplasms originating from superficial stomach organs are susceptible to prolong in to the belly wall. Likely primaries embrace malignancies of the transverse colon, gallbladder, urinary bladder, liver, and omentum. Tumorlike calcifications throughout the subcutaneous tissue of the right stomach wall (arrow). A giant inhomogeneously attenuating mass bulges the peritoneal cavity without infiltrating. The major part of the tumor lies inside the stomach cavity, however it also infiltrates muscle layers of the left abdominal wall. However, in skilled palms, barium research still have the next diagnostic accuracy in identifying related pathology and will even be better than endoscopy in detecting scirrhous carcinoma. The thickness of the well-distended abdomen wall ranges from 2 to 5 mm, as measured at the depth of a rugal fold. The wall of usually distended contrast-filled small bowel loops measures 3 mm in thickness. Jejunal and ileal folds could additionally be visible however normally measure at most 2 to 3 mm in thickness. Healthy bowel loops usually present a well-defined, homogeneous, hyperattenuating wall on postcontrast scans and no seen locoregional lymph nodes or stranding of surrounding mesenteric fats. A basic thickening of small bowel folds may be due to hypoproteinemia, radiation enteritis, ischemia, or an adjacent inflammatory process and thus be nonspecific. However, infectious diseases, similar to tuberculosis, cryptosporidiosis, and cytomegalovirus infections, may also trigger thickening of small gut and colonic mucosa. However, instruction and preparation play an important role in correctly displaying the gut. Optimal opacification of the stomach and small intestine is achieved by slowly and continuously consuming 1500 mL of both a 2% mixture of Gastrografin or a 1% combination of barium sulfate suspension (contraindication is suspected perforation due to a excessive threat of barium-induced peritonitis) over a interval of 60 minutes previous to the examination. Optimal colonic opacification is achieved by rectal instillation of 300 mL of 2% water-soluble distinction medium. Although the tactic presents excessive diagnostic accuracy in experienced arms, its clinical relevance is often nonetheless restricted to evaluation of sufferers in whom typical colonoscopy is either not attainable. However, when assessing arterial or portal venous abdominal vessels, higher flow charges (5 mL/s) and proper timing of contrast injection are important; use of the bolus-triggering approach is due to this fact highly beneficial. Normal-sized rugal folds in the contrast-filled abdomen (arrows) of a affected person with a biliary obstruction. Note the streaks of contrast media slowly penetrating in to the viscous contents (arrow). The descending colon is collapsed-which is common-and subsequently has a thicker wall. The colon is sharply outlined by surrounding pericolonic fats; thus, stranding of pericolonic fats is indicative of a pathologic process. Local mural thickening could also be caused by surgical anastomosis, however apart from this is always extremely suspicious of a malignancy. The jejunum, ileum, cecum, transverse colon, and sigmoid are intraperitoneal buildings; the distal duodenum and ascending and descending colon lie within the retroperitoneal area. The ascending colon is situated in the far proper lateral stomach, reaching from the cecum up to the right hepatic flexure just under the liver.
Specifications/Details
Cephaloceles may be congenital or acquired secondary to surgery skin care books 5 gm bactroban discount, trauma skin care 77054 cheap bactroban 5 gm line, or as a result of skin care gift baskets buy 5 gm bactroban with amex spontaneous causes acne 7 weeks pregnant 5 gm bactroban purchase amex. Associated abnormalities are callosal hypogenesis, interhemispheric lipoma, dermoid, neuronal migration anomalies, colloid cyst, midline craniofacial dysraphisms, hypertelorism, microcephaly, microphthalmos, and hydrocephalus. Nasal dermoid/epidermoid Dermoid cysts are the most common midline congenital nasal plenty. Nasal dermoids could additionally be situated anywhere from the glabella to the nasal tip and will extend intracranially. They could current with a nasal pit, dimple, or fistula containing a hair over the dorsum of the nose. Dermoids are barely more frequent in male sufferers, whereas epidermoids have equal prevalence in both genders. They commonly turn into infected, might distort nasal growth, and are cosmetically unacceptable. Rare, developmental mass of dysplastic neurogenic tissue sequestered and isolated from the subarachnoid space ("encephalocele" that has lost its intracranial connection). Usually recognized at birth as a congenital subcutaneous blue or pink mass alongside the nasal dorsum. Nasal obstruction may be current with intranasal glioma due to firm, polypoid submucosal nasal cavity mass. One of the frequent anatomical variations of the sphenoid sinus, which can pose an endoscopic sinus surgical hazard if not acknowledged preoperatively. Protrusion of other neighboring buildings (optic, maxillary, and vidian nerves) in to the sphenoethmoid sinus lumen may additionally be seen. Nasal glioma Protrusion of the interior carotid artery in to the sphenoid sinus (continues on page 279) Lesions in the Nasal Cavity and Paranasal Sinuses 279 Table 7. If contaminated, there could also be a rim of distinction enhancement across the cyst and enhancing inflammatory adjustments in surrounding delicate tissues. Comments A dacryocele (lacrimal sac mucocele) is a cystic enlargement of the nasolacrimal sac or a diverticulum of the sac brought on by a distal block of the lacrimal drainage system combined with a one-way valve impact on the proximal finish of the system. Dacryoceles are thought-about an unusual congenital anomaly of the lacrimal drainage system and are normally present as a tense or fluctuant mass slightly nasal and inferior to the inner canthus within the first few days of life. Most instances of congenital nasolacrimal duct cysts resolve spontaneously inside 12 months. Secondary dacryocystitis, dacryopyocele, periorbital cellulites, and septicemia could ensue. Adult nasolacrimal sac mucocele is an uncommon mass arising within the medial canthal area of the orbit of middle-aged sufferers with a history of prior trauma, surgery, and postinflammatory or neoplastic stenosis. The cystic expansion is related to distal nasolacrimal duct obstruction and proximal obstruction on the junction of the common canaliculus and sac. Nasolacrimal duct orifice cysts of the inferior nasal meatus are also rare acquired lesions. An in depth nasopalatine duct cyst (C) shows remarkable nasolabial protrusion after penetration of the maxillary cortex. The bones between the maxillary sinus and the ground of the orbit and the roof of the orbit and the ground of the frontal fossa are depressed. Comments the maxillary sinus develops in the fourth month of intrauterine life as a mucosal evagination in the center of the middle nasal meatus. If development is arrested at this stage, aplasia or hypoplasia happens with incomplete pneumatization in to the malar eminence and maxillary alveolar ridge. Conditions similar to extreme infection, trauma, tumor, irradiation, and congenital first arch syndrome arrest the expansion of the maxilla, leading to a small (hypoplastic) antrum. Imaging might reveal problems of sinusitis, such as secondary osteomyelitis, orbital complications, subcutaneous abscess (Pott puffy tumor), meningitis, epidural abscess, subdural empyema, and brain abscess. Signs of persistent rhinitis, together with mucosal thickening, inflammatory polyps, and hyperplasia of the turbinates, may also be evident. This pattern may be observed in the presence of benign or malignant neoplasms arising from the lateral nasal wall. The bacteria most often involved are Haemophilus influenzae and Streptococcus pneumoniae. Predisposing elements embody upper respiratory infections, systemic disease, nasal masses, trauma, anatomical variants, dental infections, and allergic mucosal edema. Manifests clinically as headache, local tenderness, facial pain, and purulent nasal drainage. All however one pattern of continual rhinosinusitis (sporadic pattern) are primarily based on the obstruction of different mucus-drainage pathways. Often associated situations are underlying anatomical variations and first ciliary dysmotility. Common signs are facial ache and stress, nasal obstruction, nasal discharge, hyposmia, and anosmia. Presents with a focal polypoid mass inside a partially or completely opacified sinus lumen with central areas of high density and/or fine, round to linear matrix calcifications. Chronic allergic hypersensitive aspergillus sinusitis presents with normally asymmetrical pansinusitis, hypodense contrast-enhancing mucoperiosteal thickening, polyps, and hyperdense sinus contents, sinus expansion, and facial deformity. Acute invasive fungal sinusitis is most typical within the maxillary and ethmoid sinuses, followed by the sphenoid sinus. The fulminant progressive disease presents with complete or partial soft tissue opacification of affected sinus, fungal colonization with increased density, absence of fluid levels, and a number of areas of focal bony destructions of sinus partitions. Spread of sinus can extend in to adjacent delicate tissues and current with rhinoorbitocerebral disease. Comments Aspergillus fumigatus and Mucoraceae are the most typical offending organisms. Acute invasive fungal sinusitis most often happens in diabetic or immunocompromised sufferers with predisposing conditions. Noninvasive steady forms could happen in an in any other case wholesome affected person after change in local sinus microenvironment (sinus surgery, postradiation, marijuana smoking). The wall between the nasal fossa and the hypoplastic sinus is displaced laterally. Also noted are hypodensity of secretions and sclerosis and thickening of the affected maxillary sinus walls. Comments Bacterial infections with granulomatous lesions of the sinonasal cavities embrace actinomycosis, nocardiosis, tuberculosis, syphilis, leprosy, and glanders. Rhinoscleroma is a tumorlike expansion of the nostril and upper lip, seen more generally in Africa, Central and South America, and Eastern Europe. It also can contain the nasopharynx, larynx, trachea, bronchi, middle ear, and orbit. Infectious granulomatous sinonasal illness Cocaine nostril Granuloma of the nasal septum, which eventually could also be eroded. Nonspecific mucosal inflammation of the nasal cavity and/or paranasal sinuses may be associated. The nasal septal destruction, lack of the structural integrity of the nasal cavity, and hard palate defect are acknowledged as a local complication. Presents with normally bilateral, irregular mucosal thickening and delicate tissue nodules with contrast enhancement. As the disease becomes continual, the partitions of the residual paranasal sinuses (particularly the maxillary sinus) become markedly thickened, while the sinus quantity is progressively reduced, and the nasal septum may completely disappear. A persistent rim of air and lack of sinus enlargement distinguish the retention cyst from a mucocele. Multiple polypoid mucoid or gentle tissue lots inside the nasal fossa and paranasal sinuses. Polyps may be hyperdense with elevated protein and decreased water content material or colonization with fungal agent. Deossification of bony septa in ethmoid and nostril, nasal cavity and sinus wall reworking and enlargement, enlargement of the infundibulum, lamina papyracea bulging in to orbits, and even intracranial extensions are famous in extreme instances (may have mucoceles associated). A well-defined, homogeneous, low-density, mucuslike mass may be seen occupying the maxillary sinus, ipsilateral nasal cavity, and nasopharynx. Central elevated density may be associated to chronicity of polyp or fungal colonization. The maxillary ostium and infundibulum are considerably enlarged by passage of the dumbbellshaped, nonenhancing polypoid lesion in to the nose. Nasal manifestations of allergic granulomatosis and angiitis (Churg�Strauss syndrome) are just like Wegener granulomatosis.
Syndromes
- Blood (such as CBC or blood differential) and urine tests (such as urinalysis)
- A heart transplant is another option for this condition. But finding a donor heart for an infant is very difficult. Infant heart transplants can be done at only a few medical centers.
- Fever
- Infections such as tuberculosis, HIV, or fungal infections
- Trauma that injures the heart such as a car accident
- Serratia marsescens
- Allergic reactions: Such reactions are rare and are usually to some part (component) of the vaccine.
- Malnutrition
- Holes (necrosis) in the skin or tissues underneath
- Spleen infections or pus (abscess)
Related Products
Additional information:
Thus acne home remedies bactroban 5 gm order on line, the foundation of the small bowel mesentery interconnects the higher abdomen and the right decrease abdomen skin care quiz products buy bactroban 5 gm line, which in turn connects with the extraperitoneum of the stomach and pelvis acne on buttocks buy bactroban 5 gm without prescription. The small intestinal arteries come up from the left facet of the superior mesenteric artery skin care quiz cheap bactroban 5 gm line. Those arising above the ileocolic artery course in the jejunal mesentery, those distal to the ileocolic artery within the ileal mesentery. The transverse mesocolon is identified by the branches of the middle colic artery and vein. The middle colic vein joins the best gastroepiploic vein in the fused transverse mesocolon and gastrocolic ligament, and drains in to the superior mesenteric vein anteriorly as the gastrocolic trunk. It is recognized by its position between these organs and the contained center colic vessels. On the left, lateral extension of the transverse mesocolon is to the side wall at T11, constituting the phrenicocolic ligament. The ileocolic vessels course near the bottom of the small intestine mesentery anterior to the third portion of the duodenum near the midline to the right iliac fossa. The proper middle colic vessels branch from the superior mesenteric vessels to the best and course within the ascending mesocolon. The left colic artery and vein lengthen from the marginal vessels of the descending colon and identify the descending mesocolon. These parts of the subperitoneal house are depicted in continuity with the root of the small intestine mesentery identified by the superior mesenteric vein (V). Fluid throughout the peritoneal cavity outlines the small gut mesentery (large arrow) and the transverse mesocolon (small arrow). Note the infiltrated larger omentum extending caudad from the transverse colon (T). The distal sigmoid mesocolon and upper mesorectum are recognized by the superior rectal vessels. The subperitoneal house inside the cardinal ligaments blends laterally beneath the parietal peritoneum overlying the pelvic muscles and continues to follow the course of the major pelvis vessels anteriorly. The broad ligament encloses the subperitoneal area that surrounds the suspended feminine pelvic organs and interconnects them with the lateral pelvic wall. Central and Lateral Continuity the lateral pathways of communication of the subperitoneal area between the abdomen and the pelvis are shaped by the convergence of the pararenal areas to form the infrarenal space, caudal to the perirenal area, which descends in to the extraperitoneum of the pelvis. On the proper side, the junction of the basis of the small gut mesentery in the best lower quadrant with the subperitoneal space at the proximal ascending colon supplies continuity with all of the abovedescribed connections of the foundation of the small gut mesentery in addition to the continuity with the right lateral abdomen and right lateral pelvis. On the left aspect, there are two major avenues of communication within the subperitoneal space between the left lower abdomen and the pelvis: the central pathway and the lateral pathway. Attention can also be focused on the continuity of the decrease stomach and pelvic organs created by the subperitoneal house. Thus, continuity is provided from the left stomach to the pelvis centrally as properly as the suspended sigmoid colon. The aorta also interconnects laterally with the pelvis because it bifurcates, forming the common iliac arteries that course to the lateral pelvis. Thus, the central and lateral pathways of the subperitoneal area interconnect alongside the scaffolds of the most important arterial pathways. The anterior pelvic extraperitoneum is subdivided by the umbilicovesical Thoracoabdominal Continuum fascia in to the perivesical and prevesical areas. The umbilicovesical fascia defines the perivesical area because it extends cephalad to the umbilicus and caudad in to the pelvis, encasing the urachus, the obliterated umbilical arteries, and the urinary bladder. The infrarenal house is in continuity with paravesical spaces of the pelvis, which is in continuity with the anterior and posterior extraperitoneal areas of the pelvis. The paravesical area is in continuity with the broad ligament, the sigmoid mesocolon, and the mesorectum. Thus, the subperitoneal continuity persists via the confluence of the extraperitoneum and the suspended pelvic organs. This provides potential pathways for bidirectional spread of illness between the stomach and the pelvis. The splanchnic mesoderm forms the visceral layer that covers the thoracic and abdominal organs and features the stomach ligaments and mesenteries. The parietal and visceral layers are in continuity and enclose the extrapleural and subperitoneal spaces. It is through this subserous continuum that vital constructions course between the thorax and the abdomen. This hiatus permits the thoracoabdominal continuation of the esophagus, the vagus nerves, the esophageal branches of the left gastric vessels, and the lymphatics coursing from the gastrohepatic ligament to the middle mediastinum. The esophagus (E) and aorta (A) are shown traversing that portion of the subserous house (stippled area) interconnecting the thorax and abdomen. These three putting circumstances clearly point out potential for bidirectional unfold of illness processes throughout the abdomen and pelvis, and indicate the continuity of the abdomen with the mediastinum. There is a steady anterior density at the degree just above the inferior phrenic arteries, the median arcuate ligament, which identifies the aortic hiatus. The wall of the cava is adherent to the margins of the foramen and thus interrupts continuity of the subserous area. In offering the most important continuity of the thoracoabdominal continuum, the esophageal hiatus and aortic hiatus provide the potential pathways for bidirectional illness unfold between the thorax and the abdomen. The smaller anterior openings are also potential pathways for thoracoabdominal spread of disease. The only time the recesses of the peritoneal cavity are imaged is when they comprise abnormal amounts of fluid (ascites), gas (pneumoperitoneum), or tumor. The subperitoneal house lies subjacent to the visceral and parietal peritoneum; the potential area of the peritoneal cavity is between the peritoneal and the visceral peritoneum. The move is directed by intraabdominal strain gradients, the positioning and nature of origin of the fluid, body position, and the anatomy of the mesenteric partitions and peritoneal recesses. The anatomy of the peritoneal recesses is set by the ventral and dorsal parietal attachments of the ligaments and mesenteries. Subperitoneal gasoline is seen diffusing throughout a significant portion of the subperitoneal area. The process originates from the mediastinum within the first case and from the rectum within the second instance. Gas not only extends in to the transverse mesocolon and small intestinal mesentery but additionally dissects alongside the renal vasculature to both kidneys and descriptions an anterior communication across the midline. Central diffusion may be traced along the decrease stomach aorta to its bifurcation. Note gas (arrow 2) as it programs via the diaphragmatic hiatus and on either side of the diaphragmatic crura. Gas has subtle caudally in the left lateral stomach within the subperitoneal area (arrow 5). Gas programs in left lateral pelvis (arrow 6) and diffuses in to the sigmoid mesocolon (arrow 7a). This recess is posterior to the spleen and anteriorly to the left kidney, and extends anteriorly and medial behind the tail the Peritoneal Cavity of the pancreas. The lesser sac is the subhepatic recess on the left; its only communication with the peritoneal cavity is through the foramen of Winslow. The organs surrounding the lesser sac are the spleen on the left, the stomach and duodenum anterior and right, the transverse colon anterior, and the pancreas posterior. The connecting ligaments and mesenteries include the splenorenal ligament, the gastrosplenic ligament, 35 the gastrocolic ligament, the larger omentum, the lesser omentum (gastrohepatic ligament and hepatoduodenal ligament), and the transverse mesocolon. The lesser sac is subdivided in to a superior recess and inferior recess by the left gastric artery as it programs from the celiac artery within the gastropancreatic plica to the gastrohepatic ligament. The superior recess is to the proper of the left gastric artery and is the smaller recess. Gas originating from a perforated sigmoid diverticulum diffusing by way of the pelvis and stomach via the subperitoneal area and in to the mediastinum. Positive contrast within the pelvic portion of the peritoneal cavity reveals the ventral recesses (arrowheads) merging with the paravesical recesses (black arrow) and the cul-de-sac dorsally (white arrow). Positive contrast in the best paravesical recess (small arrow) merges ventrally to the junction with the proper paracolic recess (small arrowhead). Positive distinction in the right peritoneal cavity in the lateral portion of the perihepatic recess (large arrow) after merging with the subhepatic recess.
Usage: p.r.n.
Verify that electrical capture (seen on the monitor) is related to mechanical seize (verified by palpable pulses) skin care face buy bactroban 5 gm cheap. Transvenous pacing - Transvenous pacing refers to the delivery of a pacing stimulus to the center through a vein (transvenous approach) acne 40 years discount bactroban 5 gm otc. For significant unresolved rhythm or conduction problems acne vulgaris bactroban 5 gm purchase on line, everlasting pacing is required skin care 3-step discount bactroban 5 gm mastercard. Temporary pulse generators are externally managed by manipulating dials on the face of the unit. Insert a brand new 9-volt battery in to the battery compartment; set pacing price at one hundred beats per minute, the mA to 5, and the sensitivity knob to most clockwise place for demand (synchronous) pacing. Insert the tip of the bridging cable in to matching terminals on the heartbeat generator, and turn pulse generator on to verify proper functioning of the battery and unit. The preferred routes of access for transvenous pacing are the right inner jugular vein, the best subclavian, and the best femoral vein. The pacing lead is inserted in to the vein of selection and guided in to the guts using fluoroscopy. Once the wire is visualized in the proper atrium, a balloon at the tip of the pacing catheter is inflated and the wire is floated by way of the tricuspid valve in to the apex of the proper ventricle for single-chamber ventricular pacing. Even though single-chamber atrial pacing and dual-chamber pacing could be accomplished, single-chamber ventricular pacing is probably the most dependable and most well-liked selection for transvenous pacing. The distal tail of the pacing catheter is connected to the adverse connection of the bridging cable and the proximal tail is linked to the constructive connection of the bridging cable. Using the dials on the exterior pulse generator, regulate the pacemaker settings: 1. While watching the cardiac monitor, steadily flip down the mA till capture is misplaced (usually zero. Epicardial pacing - Epicardial pacing refers to the delivery of a pacing stimulus to the heart through wires positioned on the epicardial surface of the atrium, ventricle, or both, throughout cardiac surgery. Two wires are attached to the atrium for single-chamber atrial pacing (one wire serves as ground) or to the ventricle for single-chamber ventricular pacing, or two wires are attached to both chambers for dual-chamber pacing. Increase mA by turning dial clockwise to greater number; lower mA by turning dial counterclockwise to lower quantity. Determines the heart fee in beats/minute at which the stimulus is to be delivered. Increase sensitivity (mV) by turning mV dial clockwise to decrease quantity; lower sensitivity by turning dial counterclockwise to higher number. Atrial wires usually exit to the proper of the sternum and ventricular wires exit to the left. Epicardial pacing is used after cardiac surgery to deal with symptomatic bradyarrhythmias, as a prophylactic measure for high-risk patients, and to treat tachyarrhythmias utilizing overdrive pacing techniques. The implant process is relatively easy, usually carried out under native anesthesia and aware sedation, and lasts about 1 hour. After satisfactory placement of the pacing lead is confirmed, the lead is connected to the pacemaker generator. The generator is placed in the subcutaneous tissue just below the left or proper clavicle. The main cause for implanting a pacemaker is the presence of a symptomatic bradycardia. Permanent pacemaker technology has undergone main advances since pacemakers have been first launched in the Fifties. Studies have proven that pointless pacing of the proper ventricle can lead to coronary heart failure and an elevated incidence of atrial fibrillation. The newer dualchamber gadgets can maintain the quantity of right ventricular pacing to a minimal and thus stop worsening of the center disease. Once the pacemaker is implanted, the following data is useful to share with the patient: 1. Periodic pacemaker checkups - the pacemaker is periodically checked to make sure the device is operational and performing appropriately. Most pacemakers are programmable, enabling the doctor to adjust pacing therapy. Pacemaker safety - Built-in filters defend pacemakers from electrical interference from most gadgets encountered in every day life, together with microwave ovens. Any exercise that entails intense magnetic fields (such as arc welding) must be avoided. Pacemakers have a built-in indicator to signal when the battery is approaching depletion. The pacemaker is designed to function for several months to allow adequate time to schedule a replacement procedure. Because the batteries are permanently sealed contained in the pacemaker, the complete pacemaker is replaced when the battery runs down. Permanent pacemaker identification codes A common coding system is used to describe the function of single- and dual-chamber pacemakers (Table 10-1). Various letters are used for every place to describe a pacemaker operate or attribute. Only one letter is used per place: First place - Identifies the chamber paced. Second position - Identifies the chamber where intrinsic electrical exercise is sensed. Third place - Indicates how the pacemaker will reply when it senses intrinsic electrical exercise. Fourth place - Identifies programmable functions, the capability for transmitting and receiving information (communication), and the supply of rate responsiveness. Antitachycardia pacing (overdrive pacing) - this function paces the heart faster than the intrinsic fee to convert the tachycardia 2. Five-letter pacemaker identification code First letter Chamber paced O = None A = Atrium V = Ventricle D = Dual (A and V) Second letter Chamber sensed O = None A = Atrium V = Ventricle D = Dual (A and V) Third letter Response to sensing O = None I = Inhibits pacing T = Triggers pacing D = Dual (I and T) Fourth letter Programmable capabilities O = None P = Simple programmable M = Multiprogrammable C = Communication R = Rate responsive Fifth letter Antitachycardia capabilities O = None P = Antitachycardia pacing S = Shock D = Dual (P and S) Pacemaker terms Pacemaker firing A pacemaker produces a programmed present (stimulus) at a set rate to the myocardium. This energy travels from the pacemaker generator by way of the lead wires to the myocardial muscle. Basic pacemaker operation consists of a closed-loop circuit in which electrical present flows between two metal poles (one negative, the other positive). Unipolar pacing has one pole (electrode) inside the heart, with the other pole being the metal case of the heart beat generator. The circuit travels between the electrode on the distal tip of the pacing lead in touch with the myocar- dium (the unfavorable pole) to the pacemaker generator situated in soft tissue (the positive pole). The current travels between the electrode on the distal tip of the pacing lead (negative pole) to the proximal electrode situated a couple of millimeters above the distal tip (the positive pole). Capture the time period capture refers to the profitable stimulation of the myocardium by a pacemaker stimulus, resulting in depolarization. Atrial depolarization from a pacing stimulus results in a pacing spike followed by atrial exercise (P wave). Automatic interval (pacing interval) the automatic interval refers to the heart fee at which the pacemaker is ready. This interval is measured from one pacing spike to the following consecutive pacing spike. This is called the A-A interval, analogous to the P-P interval of intrinsic waveforms. This is identified as the V-V interval, analogous to the R-R interval of intrinsic waveforms. The pacing stimulus has no impact for the rationale that ventricle is already being depolarized. The fusion beat has traits of each pacemaker and affected person forces, although one usually dominates the Pacemaker rhythm Stimulation of the atria for one beat is identified as an atrial paced beat. The identical ideas apply to permanent pacemakers, however correction of malfunctions requires the utilization of a pacemaker programmer or an precise surgical procedure to reposition the pacing lead or exchange the generator. Disconnection within the system - Check the connections between the generator, bridging cable, and lead; reconnect or tighten connections. Fracture of lead or lead insulation - Do an overpenetrated chest X-ray to detect fractures; have the physician replace the lead. Most malfunctions could be traced to issues with the generator (parameter settings, battery failure), the lead (problems at the interface between the catheter tip and the endocardium, fracture in the lead or its insulating surface), or to a disconnection in the system.
Tags: 5 gm bactroban, 5 gm bactroban buy overnight delivery, bactroban 5 gm, generic bactroban 5 gm overnight delivery, buy bactroban 5 gm cheap, order 5 gm bactroban mastercard, cheap 5 gm bactroban with visa, generic 5 gm bactroban visa, 5 gm bactroban purchase visa, buy discount bactroban 5 gm on line, bactroban 5 gm buy online, 5 gm bactroban cheap mastercard, purchase bactroban 5 gm overnight delivery, 5 gm bactroban discount amex, buy discount bactroban 5 gm, order 5 gm bactroban amex
10 of 10
Votes: 85 votes
Total customer reviews: 85
Customer Reviews
Darmok, 33 years: Cervical Cancer Symptoms of cervical most cancers turn into evident when cervical lesions are of moderate size. The differential diagnoses of benign breast plenty: Fat necrosis is often a result of trauma to the breast with subsequent bleeding in to the breast tissue. Malignant tumors of the nasal cavity and paranasal sinuses are comparatively rare (3% of all head and neck tumors).
Tukash, 43 years: Diagnostic pearls:The neck of a direct hernia lies medially and the neck of an oblique hernia lies laterally to the inferior epigastric vessels. Fifty p.c of adrenal cortical carcinomas are hormonally lively (twice as frequent in women), and patients may develop Cushing syndrome. Associated symptoms/relieving elements: Pain may be related to positional adjustments, fever, or nausea/vomiting.
Basir, 25 years: Renal halo sign refers to inflammatory infiltration of the pararenal area with sparing of the perirenal space. Axial scan identifies infiltrating retroperitoneal lymphoma because the underlying trigger. Some describe a multilaminar fusion,forty three whereas others have documented ready communication towards the iliac fossa.
Vasco, 60 years: The entity of the fluid collections could be assessed primarily based on a wide selection of completely different criteria. Psoas Abscess and Hematoma Spontaneous dissection from a primary web site in the retrofascial area deep to the transversalis fascia in to the extraperitoneal compartments is uncommon. An enlarged right kidney depicting intensive streaky to mottled gasoline collections all through the renal parenchyma with extension in to the perirenal space is seen.
Mason, 62 years: A massive inhomogeneous soft tissue mass with calcifications (arrow) is seen in the proper subhepatic region with extension in to the retroperitoneum. A hematoma within the distensible perirenal compartment can develop to an infinite size before pressure turns into sufficient to cause tamponade of the bleeding site. Nodular or combined varieties are less frequent, low attenuating, and thus extra distinguishable from normal liver parenchyma.
