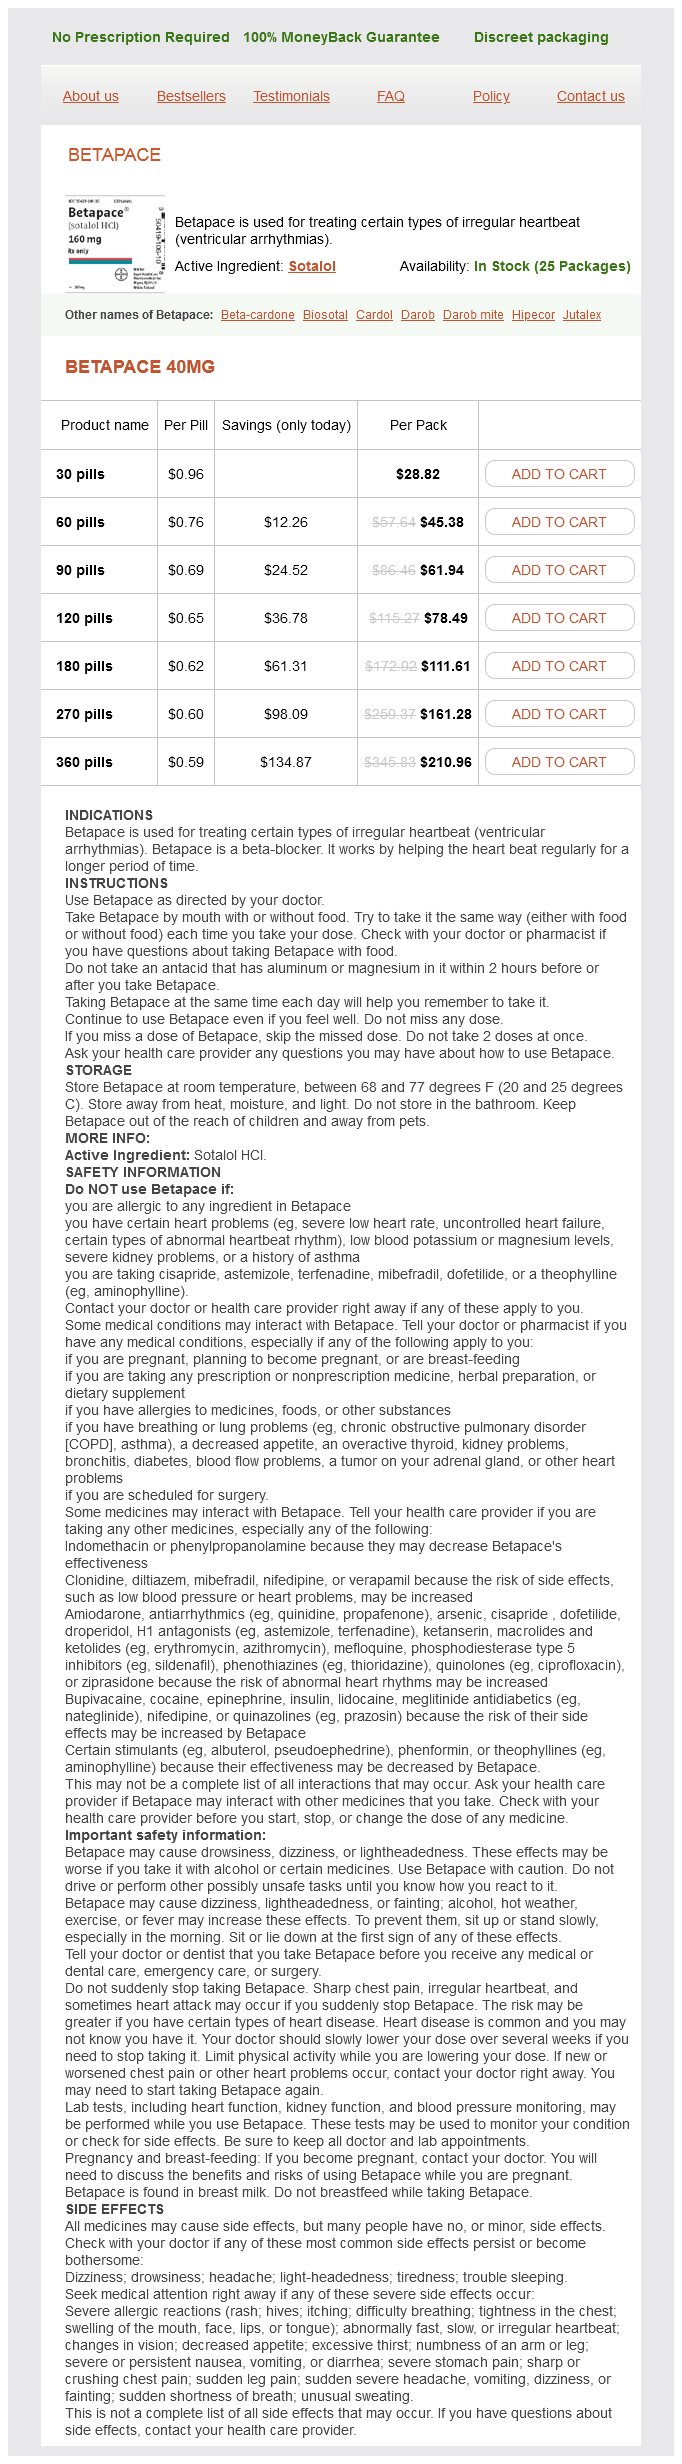
Betapace 40mg
- 30 pills - $28.82
- 60 pills - $45.38
- 90 pills - $61.94
- 120 pills - $78.49
- 180 pills - $111.61
- 270 pills - $161.28
- 360 pills - $210.96
Betapace dosages: 40 mg
Betapace packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 638
Only $0,62 per item
Description
In our experience blood pressure medication valsartan generic betapace 40 mg overnight delivery, asking the affected person to hollow the stomach is much less effective than the earlier cues for eliciting an isolated deep muscle co-contraction response hypertension erectile dysfunction 40 mg betapace generic fast delivery. Once you reach this layer (take care not to blood pressure medication excessive sweating betapace 40 mg otc go any deeper into the peritoneum) lipo 6 arrhythmia purchase 40 mg betapace with mastercard, apply light tension to the TrA fascia by adducting your thumbs (draw the TrA fascia laterally). Connect to my fingers and attempt to create the identical tension that attracts your stomach in and out. Almost all of the ultrasound photographs and video clips presented in this version are oriented in accordance with imaging convention. This is a change from the third edition and is consistent with conventional imaging protocols. The new pictures and video clips in this current edition have been collected using the MyLab25 (Biosound Esaote). This test provides information on the symmetry of activation of the left and proper sides. The depth control and gain can be adjusted so that the muscle layers are more easily observed; be positive to regulate the major target to the layers of interest. Prior to assessing the response of the abdominals to verbal cuing, observe any motion of the muscular tissues throughout quiet respiratory. Activity of the TrA ought to be minimal during quiet respiration (Hodges & Gandevia 2000a); nonetheless, when there is a rise within the chemical drive (increased carbon dioxide levels) or mechanical drive (articular or myofascial restrictions in the thorax), TrA is the primary abdominal muscle recruited to assist expiration. Hypertonicity of TrA can additionally be noticed right now (the muscle will seem to be contracted). Subsequently, observe the response of the abdominal muscles to the next cues: 1. It can also appear to slide laterally excessive of the TrA, instead of TrA sliding underneath). This task would require all of the muscles of the belly wall to coactivate, and therefore activation of TrA throughout this task is troublesome to assess via direct palpation. Palpation of one TrA while imaging the other can add additional info to the bilateral palpation exams described above. The inter-recti distance can be reliably measured using dial calipers (Boxer & Jones 1997) or ultrasound imaging (Coldron et al 2008), and in a current pilot study it was noted that a quantity of wholesome nulliparous women, as nicely as males, had inter-recti distances larger than these measures (Lee D, unpublished). The following checks study the Chapter 9 integrity of the linea alba and its capability to switch the forces produced by the belly wall and thus drive shut the joints of the lumbar spine and pelvic girdle. With the affected person in crook lying, palpate the linea alba within the midline from the xyphoid to the pubic symphysis. Instruct the patient to do a gradual head and neck curl-up and palpate the response of the linea alba. Does the stress change in the linea alba in the course of the curl-up (decrease or increase) Is there any invagination or protrusion of the abdomen in the midline during this task. Explore the entire size of the linea alba and notice the adjustments throughout its size during the curl-up task. The degree of the abdomen imaged is determined by the palpation findings; choose the level the place the least tension is felt during the curl-up task. Note the echogenicity of the posterior rectus sheaths (upward arrows) and the continuity of this drive via the linea alba. The inter-recti distance and the width of the recti could be measured using the internal measurement system of the ultrasound unit during all of these tasks. The inter-recti distance might enhance or lower; this seems to rely upon the abdominal stage, the technique used for this task, and the laxity/integrity of the linea alba. A key change to note is the echogenicity of the linea alba, which should increase. Cue a contraction of the deep muscle tissue and have the affected person keep this co-contraction whereas performing the top and neck curl-up task. The rigidity of the healthy linea alba appears to improve as this lateral force happens. Note any distinction within the echogenicity of the linea alba, the inter-recti distance, and the shape of the linea alba between these two tasks. When she pre-contracts the deep system, the sagging is not evident (second part of the clip). There is a clear difference in what appears to be the power to generate pressure within the linea alba between the 2 methods. She additionally notes a significant distinction in the effort to carry out the task; extra effort is required with out the pre-contraction of the deep system. With a symmetrical precontraction of TrA, the broadening of the recti is symmetrically decreased. The hypothesis is that TrA tenses the posterior fascia of the rectus sheaths in addition to the intermediate zone of transverse fibrils of the linea alba. Examples of ultrasound pictures seen in sufferers with diastasis rectus abdominis can be seen in Chapter 6 (see Video 6. Melissa, Chapter 9 the final thing to observe with ultrasound imaging is the power of the left and right TrA to enhance tension in the midline buildings. Optimally, a contraction of the left and right TrA may be seen to increase rigidity along the complete length of the fascia to and across the midline even when). In a useful stomach wall a co-contraction of the left and proper Watch Video eight. Christy & Melissa, Chapter 9 the pelvic floor � ultrasound imaging A particular examination of the pelvic ground is indicated if the patient presents with urinary incontinence (Chapter 6), prolapse, pelvic floor/perineal pain, or a sensation of strain on the pelvic floor, or if no response is elicited in TrA when a cue is given to contract the pelvic floor. The pelvic floor is assessed both internally or by ultrasound imaging, but preferably each. Both authors frequently use ultrasound imaging to view the operate of the pelvic floor and discuss with an authorized pelvic ground therapist when indicated. Once again, this highlights the necessity for multidisciplinary and interdisciplinary teams. The endopelvic fascia and the muscles of the pelvic flooring could be assessed with 2D ultrasound imaging from both an abdominal or perineal approach. To picture the bladder, it must be 241 the Pelvic Girdle moderately, however not completely, full. Instruct the patient to void and then drink 500mL of fluid 1 hour before the examination. This will standardize the quantity of fluid in the bladder for subsequent examinations. This strategy is valuable for assessing symmetry of activation of the left and right sides of the pelvic floor as the response of both sides could be seen concurrently. Note the shape/ profile of the resting bladder and then observe the response of the endopelvic fascia in addition to the bladder to the next cues: 1. Slowly and gently join alongside this line and take into consideration drawing your anus up and forward. The benefit of this strategy is that the left and right sides of the pelvic ground may be imaged separately to confirm/negate the impressions from the transverse view. There continues to be the disadvantage of not having a bony landmark to measure movement in opposition to, thus the necessity for the perineal view. Adjust the depth management in order that a complete picture of the bladder is on the display screen and modify the primary focus to the level of the endopelvic fascia. Note the shape/profile of the resting bladder after which observe the response of the endopelvic fascia in addition to the bladder to the following cues: 1. This strategy to imaging the pelvic flooring and the organs of the pelvis yields the greatest amount of knowledge and is all the time indicated when treating girls with pelvic organ prolapse with or without urinary incontinence. The responses of the bladder, the neck of the urethra, and the anorectal angle are easily seen throughout multiple duties in both the supine and standing positions. With the affected person in criminal lying, hips and knees flexed, the perineum is exposed and the patient draped for consolation. All of the air should be faraway from the glove, which is firmly held across the probe guaranteeing that an enough layer of gel remains between the probe and the glove. Apply one other layer of gel over the top of the glove and check the ultrasound display for any artifacts (black streaks). With a gloved hand, apply the probe to the midline of the perineum with the marker oriented in the direction of the anus. No seen movement of the anorectal angle occurs throughout a cue to contract the pelvic ground. Press firmly, however gently, into the tissue and evaluate the tone of these deep fibers to the opposite side in addition to to ranges above and below.
Cedoaria (Zedoary). Betapace.
- Are there safety concerns?
- Dosing considerations for Zedoary.
- Colic, spasms, improving appetite and digestion, inflammation, nervous diseases, and other uses.
- What is Zedoary?
- How does Zedoary work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96355
A pulse pressure ati cheap betapace 40 mg with mastercard, the best face is vertically divided into equal thirds by horizontal lines adjoining to the hairline blood pressure study buy betapace 40 mg with mastercard, the nasal base diastolic blood pressure 0 generic 40 mg betapace visa, and menton hypertension synonym betapace 40 mg buy generic line. B, In the best lower third of the face, the upper lip makes up the upper third, and the decrease lip and chin compose the decrease two thirds. In addition, the lower third was comprised of a forty five:fifty five vertical relation of the upper lip to lower lip and chin peak. Recalling that the ideal proportions of the lower face are one-third higher lip and two-thirds lower lip and chin, the treatment plan was clearly a result of the direct scientific examination somewhat than any cephalometric commonplace. The ultimate diagnosis depended not solely on the vertical facial proportionality however on the measurement of the resting tooth-lip relationships as well in order to more clearly outline the etiology of the decrease facial top. B, Evaluation of her anterior vertical relationships was characterized by a brief lower facial third relative to her upper thirds. The decrease third was comprised of a 45:55 vertical relationship of the higher lip to decrease lip and chin peak. The best proportions of the lower face are one-third upper lip and two-thirds lower lip and chin; thus the treatment plan was derived from the direct clinical examination of this patient quite than any cephalometric commonplace. C, Our patient displayed 3 mm of maxillary incisor at relaxation, and all of her maxillary incisors on smile, inconsistent with vertical maxillary deficiency. D, the therapy plan was orthodontic preparation for mandibular advancement and vertical genioplasty. E, the post-treatment frontal view demonstrates balance of the vertical facial thirds. F, the vertical incisor place at smile was maintained, while the decrease facial third was vertically augmented. G, the profile view shows improved mandibular projection relative to the higher face, improved chin-neck angle, and improved chin-neck size. Nasal form judged to be fairly sufficient Clinical assessment of the indirect macroaesthetic evaluation: the flattened labiomental sulcus was secondary to the excessive decrease facial height, lip incompetence, and chin deficiency. Because the chin height was short, the final diagnosis was mandibular deficiency with short chin height. Excessive chin top is measured from the lower vermilion to the soft tissue menton. Disproportion of chin peak with the upper lip occupying 25% of the decrease facial third and the decrease lip and chin occupying 75% of the decrease third of the face three. Excessive chin peak was also a contributor to the lower facial peak disproportion, as is evidenced by the higher lip and chin height clinical proportions. Excessive gingival display on smile with three mm gingival display at the proper cuspid and 5 mm on the left with a transverse cant to the palatal airplane three. The exact surgical movements had been directed by the scientific examination and measurements. From the frontal dimension, the left facet of the maxilla was impacted 2 mm greater than the right in order to stage the smile line. The differential degree of impaction mirrored the diploma of the maxillary compensation for the mandibular asymmetry. Transverse Facial Proportions the evaluation of the transverse elements of facial width is best described by the rule of fifths. Each transverse fifth should be individually examined and then assessed as an entire group. A vertical line from the internal canthus must be coincident with the alar base of the nostril. Variation on this facial fifth could presumably be as a outcome of transverse deficiencies or excesses in either the inside canthi or the alar base. For instance, Clinical assessment of the frontal dynamic (smiling) macroaesthetic evaluation: A gummy smile was current however with regular incisor crown peak. This would exclude cosmetic periodontal crown lengthening as the primary therapeutic selection for enchancment of the gummy smile. The asymmetry of the maxilla is in compensation for the mandibular asymmetry and ends in a canted frontal occlusal plane and smile line. A, this affected person was referred for correction of an anterior open bite and a gummy smile. There was extreme gingival display on smile with 3-mm gingival display at the proper cuspid and 5 mm on the left with a transverse cant to the palatal aircraft. D, Oblique at-rest facial statement with extreme decrease facial peak, lip pressure and extreme chin top, and a flat labiomental sulcus. E, Oblique smiling facial statement with no noticeable anteroposterior cant to the maxillary occlusal aircraft. F, Profile evaluation with emphasis on an extended lower facial third, long chin peak, a flat labiomental sulcus, and lip pressure on closure. G�K, the practical downside of the anterior open bite on this nongrowing patient necessitated superior repositioning of the maxilla to right the useful complaint. The exact surgical actions had been obtained from the medical examination and measurements (see text). A vertical line from the outer canthus of the eyes frames the medial three fifths of the face, which ought to be coinci- dent with the gonial angles of the mandible. Otoplastic surgical procedures are relatively atraumatic and might dramatically improve facial look. In orthognathic cases by which this disproportion is famous by the clinician, we believel that failure to mention this function violates informed consent. Therefore, otoplasty must be presented as a treatment possibility, whether or not received positively or not. Nasal anatomy in the transverse plane must also be assessed by way of proportionality. The width of the alar base must be approximately the same because the intercanthal distance, which ought to be the same as the width of a watch. The width of the alar base is closely influenced by inherited ethnic characteristics. Any deviation of the nasal tip must be famous in relation to the maxillary midline. The face is divided sagittally into five equal components from helix to helix of the outer ears. The center fifth of the face is delineated by the inner canthus of the eyes, the inside nook of the attention containing the lacrimal duct. A line from the inside canthus must be coincident with the ala of the bottom of the nostril. A vertical line from the outer canthus of the eyes frames the medial two fifths of the face, which should be coincident with the gonial angles of the mandible. The outer two fifths of the face is measured from the lateral canthus to the lateral helix, which represents the width of the ears. Another vital frontal relationship is the midpupillary distance, which ought to be transversely aligned with the commissures of the mouth. The outer two fifths of the face is measured from the lateral canthus to lateral helix of the ear, which represents the width of the ears. Unless this abnormality is a part of the chief complaint, prominent ears are sometimes a tough feature to focus on with the patient as a result of laypeople solely recognize its impact on the face in extreme cases. B, the facial transverse fifths were improved, resulting in a dramatic facial enchancment. Lower dental midline discrepancies are normally because of tooth-related points such as dental crowding with shifted incisors, untimely exfoliation of major enamel and subsequent house closure in preadolescents, congenitally lacking tooth, or an extracted unilateral tooth. An necessary diagnostic factor is whether a lateral practical shift is present secondary to a practical shift of the mandible because of crossbite. When the affected person is manipulated into centric relation, a bilateral, end-to-end crossbite often is current, and as the affected person moves the tooth into full occlusion, the patient must choose a facet to move his or her mandible into most intercuspation. This lateral shift is indicative not of true mandibular asymmetry but of transverse maxillary deficiency and a resultant functional shift of the mandible. True mandibular asymmetry is suspected when, in closure into centric relation, no lateral practical shift occurs.
Specifications/Details
The goal examination is split into exams that analyze the methods chosen for specific duties (meaningful task analysis) heart attack zippytune betapace 40 mg purchase with mastercard, after which specific regional tests that analyze the contribution of every of the methods or puzzle items (articular hypertension guidelines canada 40 mg betapace discount fast delivery, neural arteria znaczenie cheap betapace 40 mg otc, myofascial heart attack risk assessment betapace 40 mg buy generic, and 176 visceral systems) to the noticed non-optimal technique. This chapter will describe and illustrate the means to perform these exams (skill acquisition) and notice the optimum and non-optimal take a look at outcomes. The scientific reasoning of multi-test findings will be discussed via a review of a number of case stories in Chapter 9. Strategies for perform and performance � basic principles As outlined in Chapter four, the flexibility to perform optimally throughout the various spectrum of human exercise requires that we will access and select multiple methods. In some cases the technique is appropriate for the task, but in different duties the same technique causes ache and loss of function/disability. For each task, there are multiple traits, or elements, that must be thought of to decide which strategy should be used, including: What are the loading requirements (how a lot load needs to be transferred, and the way does the quantity vary in the course of the task) How does the individual really feel in regards to the level of predictablity of the state of affairs (internal) In addition to these elements, each individual brings a unique structural makeup (due to genetic factors, systemic disease, and injury history, for example), meaning perspective, social context, and environmental context. Given the complexity of, and the challenges in, objectively measuring all these characteristics, how is the therapist to determine if the patient has chosen an optimal technique for the duty being analyzed Differences in motor management between groups with low back pain, pelvic girdle pain, and hip pain in comparison with wholesome controls have been studied for some duties (Chapters four, 5). However, scientists can differ in their interpretation of these findings, as some could argue that adjustments in teams with again pain are necessary and adaptive, whereas others may argue that the adjustments are non-optimal and maladaptive. The fundamental rules for task analysis draw from a quantity of discplines, but have sturdy influences from the fields of biomechanics, human motion, sports activities psychology, and neuroscience. As task analysis includes integrated complete body movement, in clinical practice we think about all the joints within the kinetic chain when analyzing strategies. Therefore, we can decide whether a technique is optimal based on the power of the individual to reveal these features (1�4) during any task. Failure to preserve any of the above features is an indication that the patient is utilizing a non-optimal technique for the duty. Once a nonoptimal strategy has been determined, the subsequent step is to determine whether it is acceptable or not. In phrases of segmental joint control and spinal posture and orientation, every joint in the kinetic chain is assessed for the loss of optimum alignment, biomechanics, and/or control required for the duty being analyzed. However, multisegmental malalignment and/or poor management can even occur, and the shortcoming to preserve the required spinal posture or orientation required for the duty can then be described by the position of the malalignment and/or path of lack of management and the degrees and regions involved 177 the Pelvic Girdle. Loss of postural equilibrium throughout a task can be noted along with when within the task (timing) this occurs. Respiration, continence, and organ position may be assessed by remark, palpation, and, once in a while, ultrasound imaging. Any non-optimal features are noted, as nicely as any subjective stories of altered respiration, loss of continence, or sense of pressure in the pelvic floor. Multiple video clips of all of these checks each earlier than and after treatment can be seen on-line in the case reports in Chapter 9. Advanced task analysis that additional simulates meaningful activities is described and illustrated in Chapter 12. These base principles will then be further expanded and elaborated upon within the case stories (Chapter 9) and in principles for coaching new posture and motion methods (Chapter 12). The particular duties analyzed are chosen from the findings of the subjective examination. The key tasks that should be assessed are those that relate to the useful positions and actions which might be meaningful to the patient (meaningful task analysis). These are usually the painful or aggravating actions, movements, or positions they discover tough, and those who pertain to their functional targets. For example, if someone notes ache or issue during strolling then vertical loading tasks associated with single leg loading are indicated. On the opposite hand, if somebody notes that extended sitting aggravates their signs, then the strategies used for sitting, including squat and stand to sit, are assessed. Initially, deviation of the top of the head in the vertical and/or coronal planes is famous. Failed load switch through the pelvis and/or hip joint typically manifests as a deviation in the coronal plane of the pelvis relative to the lumbar backbone and hip (subtle hip drop/Trendelenburg sign. Consideration must also be given to the biomechanics of the foot from heel strike through mid-stance to push off, as 179 the Pelvic Girdle A B. The impact of a particular impairment (intrinsic or extrinsic to the pelvic girdle) is usually seen affecting alignment and function of a number of regions. To assess the posture of the pelvic girdle in standing, the therapist positions themselves instantly behind the affected person. The anterior facet of the pelvic girdle is palpated bilaterally and its resting position in all three body planes (anteroposterior tilt, lateral tilt, transverse aircraft rotation) is felt and visualized. Kinesthetic appreciation of position could be taught by having the therapist shut their eyes while palpating to remove any visible conflict/bias. The forefoot ought to have a gentle dorsal arch (transverse arch), the longitudinal arch must be present medially, and the toes ought to remain long and flat on the ground. The middle of mass is displaced anteriorly; observe the angle between the vertical line and the anterior line between the higher trochanter and the lateral malleolus. A posterior thoracic tilt has also accompanied this alteration in pelvic place (arrow). She is habitually a back-gripper (overactivates her erector spinae) and this posture is difficult for her to undertake. Note the activation of the superficial belly wall and the flexion of her knees required for her to tilt her pelvis posteriorly. The rotation has continued via her thorax, however transitions into right rotation within the upper thorax (which is seen by the higher thorax shift to the left), which is a compensatory derotation that continues into her cervical spine. Note the left lateral shift of her thorax relative to her pelvis associated with a right rotation and proper lateral bend. The proper shoulder girdle is lower than the left; nevertheless, this could be secondary to the place of her thorax. The innominate is a big bone and as much of it must be palpated as possible with the whole hand, not just the thumb and fingertips. Note key findings from the standing posture analysis within the outer ring of the Clinical Puzzle (strategies for function and performance). The femoral heads are palpated midway between the anterior superior iliac spine and the pubic symphysis just under the road of the inguinal ligament. When the femoral head is anterior, marked rigidity in the inguinal ligament (often associated with local tenderness) might be felt, as will the prominence of the femoral head. Anterior displacement of the femoral head can be associated with both inner or external rotation of the femur; verify the inferior femoral condyle to note the path of femoral rotation (not shown). Initially, the patient is requested to bend forward and the vary of accessible movement, the situation of the first motion/restriction, and the symmetry of movement is noted. Note the apex of the sagittal curve for the whole physique and then particularly observe: 1. If a segmental hinge or buckle is current, note the timing of this in relation to any femoral head displacement (or intrapelvic torsion). The position of the talus is assessed by palpating the medial and lateral aspects of the dome and noting the angle the talus makes with the lower leg (should be instantly in line). If the femoral head fails to middle, notice whether or not this occurs with a rotation of the pelvis, and which happens first. There must be no relative rotation between the 2 innominates as the pelvic girdle tilts anteriorly on the femoral heads. The interspinous areas between the decrease lumbar vertebrae are palpated with one hand and the intersegmental mobility is noted and in contrast between ranges as the patient bends forward. If a segmental hinge into flexion is felt (one segment flexes excessively in comparability with these above and/or beneath it), the timing of this non-optimal motion should be assessed (early, center, or late in the general vary of forward bending). Compare the timing of the excessive flexion with the movement evaluation of the hip (one hand palpates the femoral head anteriorly and the opposite palpates the interspinous spaces). It is common to find extreme motion segmentally within the lumbar spine when one or both hip joints fail to move optimally into flexion during forward bending of the trunk (butt-gripping strategy). When the pelvis unlocks, the innominate could be felt to rotate anteriorly relative to the ipsilateral sacrum (Hungerford et al 2004, 2007). Repeat the ahead bend test three or 4 occasions to observe the consistency/inconsistency of any optimistic 186 findings and the benefit with which the patient is ready to bend forward repeatedly. If there are a number of areas of failed load transfer, observe the sequential timing of every. The two bones should move as a unit as the pelvic girdle anteriorly tilts symmetrically over the femoral heads. Watch and really feel for early, middle, or late anterior rotation of the innominate relative to the sacrum because the patient bends forward. Remember that the amplitude of motion for the sacroiliac joint may be very small whereas weight bearing (4�6), and even when the pelvis unlocks utterly during this task the movement could be very subtle, yet palpable.
Syndromes
- Cough
- Vaginal bleeding during or after sex
- Tissue biopsy
- Does hoarseness come and go or get worse over time?
- Sore throat
- Collagen gene mutation testing
Related Products
Additional information:
If the growth is limited to lateral tipping of maxillary posterior teeth pulse pressure amplification betapace 40 mg order free shipping, buccal alveolar bone top discount and gingival recession might occur arrhythmia supraventricular tachycardia betapace 40 mg effective. The expansion equipment could be banded or bonded to the maxillary posterior teeth with a spring-loaded or non� spring-loaded palatal jackscrew that normally is activated by the patient zero heart attack anlam betapace 40 mg cheap overnight delivery. The standard description for the expansion induced with this equipment is "speedy palatal enlargement arrhythmia technologies institute greenville sc 40 mg betapace with visa. Because all of those growth appliances are toothborne, unwanted dentoalveolar enlargement is an inevitable consequence. Maxillary overexpansion to compensate for dentoalveolar enlargement and skeletal relapse. Note the lingual cusps of maxillary posterior teeth are occluding with buccal cusps of the mandibular posterior tooth. In each of these situations, the affected side exhibits growth deficiency relative to the unaffected or normal side, leading to a mandibular deviation towards the affected side. It is greatest to start orthopedic therapy with these people before pubertal development, as early as patient compliance will permit. The objective is to maximize the growth expression on the poor side and minimize dentoalveolar compensation. On the left, unaffected facet, posterior dental eruption is restricted with an interocclusal acrylic block. On the right, affected facet, the mandible is postured forward and posterior dental eruption is encouraged with a buccal shield and absence of an interocclusal acrylic block. Because untreated mandibular asymmetries of this nature invariably worsen with progress, orthopedic therapy is considered successful if the asymmetry remains secure or improves. An orthopedic drive is directed posteriorly and superiorly to the maxilla, attenuating circum-maxillary sutural growth. B, Contemporary headgear appliance fabricated with extra sturdy materials and with extra calibration and security options, although the general design has modified little in over a century. An orthopedic force ranging from sixteen to more than 32 ounces is delivered using elastic traction from the headgear to a cervical or cranial attachment for 12 to 14 hr/ day, normally for 9 to 12 months. A safety release for the retractive mechanism and parent/patient education are essential to prevent potential traumatic accidents. Theoretically, the force is transmitted in a posterior and superior direction through the teeth via the maxilla to compress the circum-maxillary sutures, limiting or redirecting maxillary progress. Since the introduction of standardized cephalometric radiographs, many medical research have demonstrated that maxillary progress may be altered with using the headgear. Because the headgear is a toothborne equipment, some maxillary dental retraction accompanies the skeletal change. Another dentoalveolar effect is the attenuation of maxillary molar eruption, leading to anterior and superior mandibular rotation. There is some help for this being the only clinically relevant skeletal impact. All of those home equipment place the mandibular condyles downward and ahead away from the glenoid fossae. Theoretically, the distracted condylar positions reduce the traditional compressive joint stress on the rising condylar cartilage and the forward mandibular posturing alters muscle tension on the condyles, stimulating or accelerating the endochondral condylar growth more than would normally happen. There is some help from animal studies that a histologic increase in condylar development could be achieved. All of these appliances place the mandible downward and forward, distracting the condyles from the glenoid fossae. This simultaneously creates posterior and superior forces on the maxilla from the facial muscle tissue and gentle tissues making an attempt to return the mandible to its regular position. An alternative is to utilize occlusal acrylic and bond the maxillary portion of the equipment with a detachable acrylic splint for the mandibular arch. Retrospective medical research have demonstrated few differences in treatment end result when evaluating the skeletal response between headgear and functional equipment remedy. Much like the headgear, dependable wear is more sensible through the night and at evening when essentially the most active facial progress and dental eruption usually happen. However, just like the headgear, its detachable nature prevents it from being reliably worn by most adolescents after the peak of their pubertal development. The interocclusal acrylic permits orthopedic forces to be transmitted additional anteriorly and superiorly through the middle of the maxilla. A, Intraoral part of the equipment with headgear tubes embedded in the interocclusal acrylic. The advocates for a delayed onephase treatment have contended that comparable skeletal remedy results may be achieved during definitive orthodontic treatment with out placing the patient by way of an unnecessary initial phase. Either method could be satisfactory and ought to be chosen on the idea of affected person acceptance of the equipment and dentoalveolar unwanted effects (there is extra maxillary dental retrusion with headgear and more mandibular protrusion with a useful appliance). An additional aspect effect from chin cup wear is extra lingual inclination of lower incisors due to the pressure of the chin cup to the decrease lip and base of the mandibular anterior alveolar process. East Asian populations may benefit extra typically from this treatment as a result of they tend to have shorter face heights than whites. However, chin cup therapy for mandibular prognathism has very limited utility, with its benefits normally negated from subsequent progress and in the end resulting in unnecessary extra remedy burden to the affected person. However, the useful equipment tends to promote upward and forward eruption of mandibular molars, which can complement the correction in deep overbite circumstances however is counterproductive in sufferers with a protracted face. This compensatory change could additionally be undesirable if the skeletal discrepancy in the end requires orthognathic surgery for correction. With the advent of osseointegrated attachments or temporary skeletal anchorage gadgets, there will be the future risk of preventing undesirable dentoalveolar change by attaching a pressure system directly to these attachments quite than using toothborne attachments. Theoretically, an orthopedic force is transmitted to the mandibular condyles, compressing the condylar cartilage and limiting endochondral growth in order to decrease the ultimate word length of the mandible. A retractive orthopedic force is directed in opposition to the chin posteriorly and superiorly toward the condylar heads. B, Contemporary chin cup, with minimal change in design, but fabricated with more comfy and durable materials. These functional appliances have few advocates owing to their effectiveness, just like chin cup remedy, being limited to dentoalveolar changes and their lack of ability to promote forward maxillary development or attenuate mandibular progress. The appliance creates rigidity in the circum-maxillary sutures with elastics from the maxillary dental arch to a frame that makes use of the forehead and chin to dissipate the pressure anteriorly. Primate research have demonstrated adaptive responses of the sutures to the stress from the distraction forces produced by this equipment. Clinical research have demonstrated clinically related maxillary skeletal protraction downward and forward on average with this equipment, with some concomitant protraction of the maxillary tooth as a result of the toothborne nature of the intraoral a half of the equipment. Although some clinicians have promoted the orthopedic distraction of the midpalatal suture to improve subsequent anterior protraction with the facemask,289 this has not demonstrated improved treatment efficacy. However, the earliest practical time for beginning therapy is after eruption of first everlasting molars owing to the poor anchorage offered by the primary dentition alone for the intraoral portion of the equipment. The stability of maxillary orthopedic protraction with a facemask is variable and dependent on whether mandibular progress finally overwhelms the skeletal improvement after active treatment. It should be anticipated that the unique facial growth sample will continue after treatment, often resulting in relapse of the skeletal discrepency. Treatment with the facemask causes protraction of maxillary anterior enamel and retraction of mandibular anterior tooth. The improvement of osseointegrated attachments or temporary skeletal anchorage gadgets could make it possible to transmit the orthopedic protraction force to intraoral skeletal attachments that forestall undesirable dentoalveolar changes. Preliminary knowledge indicate that this treatment often ends in anterior movement of the zygoma and maxilla and corresponding soft tissue with variable results on the mandible in numerous individuals. C, Three-dimensional superimposition with colour map device used on individual patient. Areas on the red end of the spectrum symbolize outward motion during energetic remedy. Although most individuals with excess vertical face top exhibit anterior open chunk, a minority may have extreme eruption of maxillary anterior teeth stopping open chew however worsening the surplus vertical show of the maxillary gingiva and anterior tooth. A high-pull headgear is used to apply a superior intrusive drive of two to four kilos to inhibit eruption of maxillary posterior teeth and compress circummaxillary sutures to limit the downward development of the maxilla. An alternative to the usage of high-pull headgear is a detachable orthopedic equipment that comes with interocclusal acrylic chew blocks in order to stretch the facial musculature and gentle tissue beyond the normal resting vertical dimension, making a reactive intrusive force against the mandibular as well as the maxillary tooth.
Usage: q._h.
Furthermore prehypertension - time to act buy 40 mg betapace with visa, antibacterial prophylaxis was until recently thought to not blood pressure medication used to treat anxiety generic 40 mg betapace offer a survival profit pulse pressure factors betapace 40 mg line. However blood pressure chart age 40 buy betapace 40 mg with mastercard, current evidence suggests that antibacterial prophylaxis could scale back mortality, febrile occasions, and bacterial infections in selected patient teams. Following publication of this metaanalysis, no less than two more randomized managed trials in support of quinolone prophylaxis have been launched. Hence, the advantages of primary antibacterial prophylaxis are more doubtless to be smaller. In strong tumor patients scheduled to receive prophylactic quinolone antibiotics, the additional use of myeloid growth components reduced febrile events in cycle one, but was later shown to not be costeffective total. The authors discovered no evidence for or in opposition to antibiotics compared to myeloid development components for the prevention of infections in cancer patient. Regarding the potential growth of antimicrobial resistance with antibacterial prophylaxis, GafterGvili demonstrated that quinolone prophylaxis ends in a small, statistically insignificant increase in colonization with quinolone resistant micro organism. Intravenous fluids were continued, and opioid analgesics were given for oral pain. Stenotrophomonas maltophilia was recovered from each central and peripheral venous tradition bottles 24 hours after the preliminary testing. This organism was delicate to both piperacillintazobactam and trimethoprim-sulphamethoxazole, but resistant to ciprofloxacin. Fever defervesced after ninety six hours of antimicrobial remedy (day 18 post-chemotherapy). With information of antibiotic sensitivities, the patient was discharged from hospital in complete remission, with a prescription to full an additional one week of oral amoxicillin-clavulanate. The affect of mucositis on oral thermometry: When fever could not reflect infection Clinical infections and bloodstream isolates associated with fever in patients present process chemotherapy for acute myeloid leukemia. Bacteraemia in hospitalised patients with malignant blood issues: A retrospective research of causative brokers and their resistance profiles during a 14-year interval without antibacterial prophylaxis 2003;4(6):420-26. Riskadapted strategy for the management of febrile neutropenia in cancer sufferers. The Multinational Association for Supportive Care in Cancer threat index: A multinational scoring system for identifying low-risk febrile neutropenic most cancers sufferers. The epidemiology of bacteremia with febrile neutropenia: Experience from a single center, 1988-2004. A doubleblind comparison of empirical oral and intravenous antibiotic remedy for lowrisk febrile patients with neutropenia during cancer chemotherapy. Oral antibiotics with early hospital discharge in contrast with inpatient intravenous antibiotics for low-risk febrile neutropenia in sufferers with cancer: A prospective randomised controlled single centre research. Oral moxifloxacin or intravenous ceftriaxone for the treatment of lowrisk neutropenic fever in cancer patients suitable for early hospital discharge. Oral versus intravenous antibiotic remedy for febrile neutropenia in cancer patients: A systematic review and meta-analysis of randomized trials. Empirical antibiotic monotherapy for febrile neutropenia: Systematic evaluate and meta-analysis of randomized controlled trials. A randomized, openlabel, multicenter comparative examine of the efficacy and safety of piperacillin-tazobactam and cefepime for the empirical treatment of febrile neutropenic episodes in sufferers with hematologic malignancies. Piperacillin/tazobactam vs ceftazidime within the remedy of neutropenic fever in patients with acute leukemia or following autologous peripheral blood stem cell transplantation: A prospective randomized trial. Septicemia and shock syndrome because of viridans streptococci: A case-control study of predisposing factors. Beta lactam monotherapy versus beta lactam-aminoglycoside combination remedy for fever with neutropenia: Systematic review and meta-analysis. Additional antiGram optimistic antibiotic therapy for febrile neutropenic cancer sufferers. Antibiotic prophylaxis in neutropenic sufferers: New proof, sensible choices. Impact of major prophylaxis with granulocyte colonystimulating issue on febrile neutropenia and mortality in adult most cancers patients receiving chemotherapy: A systematic evaluation. Costeffectiveness of including granulocyte colonystimulating issue to main prophylaxis with antibiotics in small-cell lung most cancers. Preventing Infections in Cancer Patients: Antibiotics, Hematopoetic Growth Factors or Both. Effect of quinolone prophylaxis in afebrile neutropenic patients on microbial resistance: Systematic evaluate and meta-analysis. Campbell et al5 confirmed these observation and named the enzyme as carboxypeptidase B. The amino acid sequence turned out to be very much much like pancreatic carboxypeptidase B. The binding of this proenzyme to plasminogen mixed with the position of C-terminal lysine residues in the binding and activation of plasminogen suggested that this new basic carboxypeptidase may have a task in the fibrinolytic pathway. However, in earlier studies the standardization of the assays or the utilization of several varieties of kits used was a important issue. A comparatively decrease stage of interindividual variation has been observed when an exercise based mostly assay has been used (two to four fold). Studies on conditions like Deep Vein Thrombosis,23,24 Stroke25 and Coronary Artery diseases26-28 have been contradictory in addition to inconclusive. Santamari�a et al30 investigated 114 young (mean age fifty six years) patients with ischemic stroke or transient ischemic assaults. A subgroup of 36 patients was investigated at 3-month follow-up, and the results indicated that the finding was not attributable to an acutephase response. The polymorphisms that exhibit the very best R2 in multivariate analysis include the 1542 C > G and the 147 Ala > Thr (= 505 A > G) polymorphisms. More number of polymorphisms have been found on this gene with related effects. Most of those polymorphism studies had been done in sufferers with myocardial infarction or arterial thrombosis or in the common management inhabitants. Only just lately one examine with stroke inhabitants has been reported from the Caucasian inhabitants. An rising variety of research are discovering a job for this inhibitor in numerous prothrombotic problems like stroke and coronary artery disease. Also the reality that there are potential inhibitors for this protein makes it a gorgeous target for future therapeutic practices. This data would immediate the era of newer inhibitors within the subsequent few years for the remedy of thrombotic issues. A study of the mechanism of inhibition of fibrinolysis by activated thrombin-activable fibrinolysis inhibitor. Characterization of carboxypeptidase in human serum distinct from carboxypeptidase N. An arginnie particular carboxypeptidase generated in blood throughout coagulation or inflammation which is unrelated to carboxypeptidase N or Its subunits. An arginine carboxypeptidase generated during coagulation is diminished or absent in affected person with rheumatoid arthrist. Purification and characterization of a brand new arginnie carboxypeptidase in human serum Biohim Biophys Aeta 1990;1034: 86-92. Isolation reocular cloning, and partial characterization of a novel carboxypeptidase B from human plasma. Arginnie carboxypeptidase U antigen ranges in human plasma decided with sandwich. Association between thrombin activatable fibrinolysis inhibitor genotype andlevels in plasma: Comparison of different assays. Thrombin Activatable Fibrinolytic Inhibitor ranges within the acute section of ischemic stroke. Risk of acute coronary artery illness associated with useful thrombin activatable fibrinolysis inhibitor plasma degree. Silveira A, Schatteman K, Goossens F, Moor E, Scharpe S, Stromqvist M, Hendriks D, Hamsten A. High functional ranges of thrombin-activatable fibrinolysis inhibitor are associated with an increased risk of first ischemic stroke. Thrombin activatable fibrinolysis inhibitor gene polymorphisms are related to antigenic ranges in the Asian-Indian population but will not be a threat for stroke.
Tags: safe 40 mg betapace, discount 40 mg betapace mastercard, betapace 40 mg order, buy betapace 40 mg amex, order betapace 40 mg amex, betapace 40 mg buy discount on-line, betapace 40 mg best, discount 40 mg betapace visa, betapace 40 mg purchase, 40 mg betapace fast delivery, betapace 40 mg buy, 40 mg betapace purchase fast delivery, cheap 40 mg betapace overnight delivery, generic betapace 40 mg free shipping, purchase betapace 40 mg with mastercard, betapace 40 mg generic overnight delivery
9 of 10
Votes: 246 votes
Total customer reviews: 246
Customer Reviews
Bandaro, 47 years: Involvement of the nucleus ambiguus causes paralysis of the ipsilateral palate, pharynx, and larynx, leading to hoarseness and dysphagia. The 4 different pieces of the puzzle symbolize the various systems during which impairments are assessed and noted through the scientific examination. The quantity this fraction of indicator occupies is simply the rate at which it leaves the system multiplied by the point required for it to go away, dV = t F h(t) dt.
Rathgar, 29 years: The strategy has rendered the joint rigid throughout duties that require mobility, and is due to this fact non-optimal. Altered muscle activation patterns in symptomatic girls during pelvic floor muscle contraction and Valsalva manoeuvre. DifferentialDiagnosis Laryngeal edema: this is probably the most critical cause of shortness of breath after distinction injection.
Deckard, 25 years: Nevertheless, considerable postnatal displacement of the nasomaxilla downward and forward happens owing to continued development of the brain and cranial base. Areas on the purple end of the spectrum represent outward motion during lively treatment. Also, there are specific anatomical 213 Data-Driven Techniques Hybrid Techniques Model- ased Approaches for Cancer Therapy B Vincent C.
Marlo, 32 years: This lateral shift is indicative not of true mandibular asymmetry however of transverse maxillary deficiency and a resultant practical shift of the mandible. Induction therapy was to establish management the disease while the most important bulk of the antimyeloma impact was left to the high-dose chemotherapy. On examination her blood stress was 145/80, pulse 78/min and common, no neck or cranial bruits.
