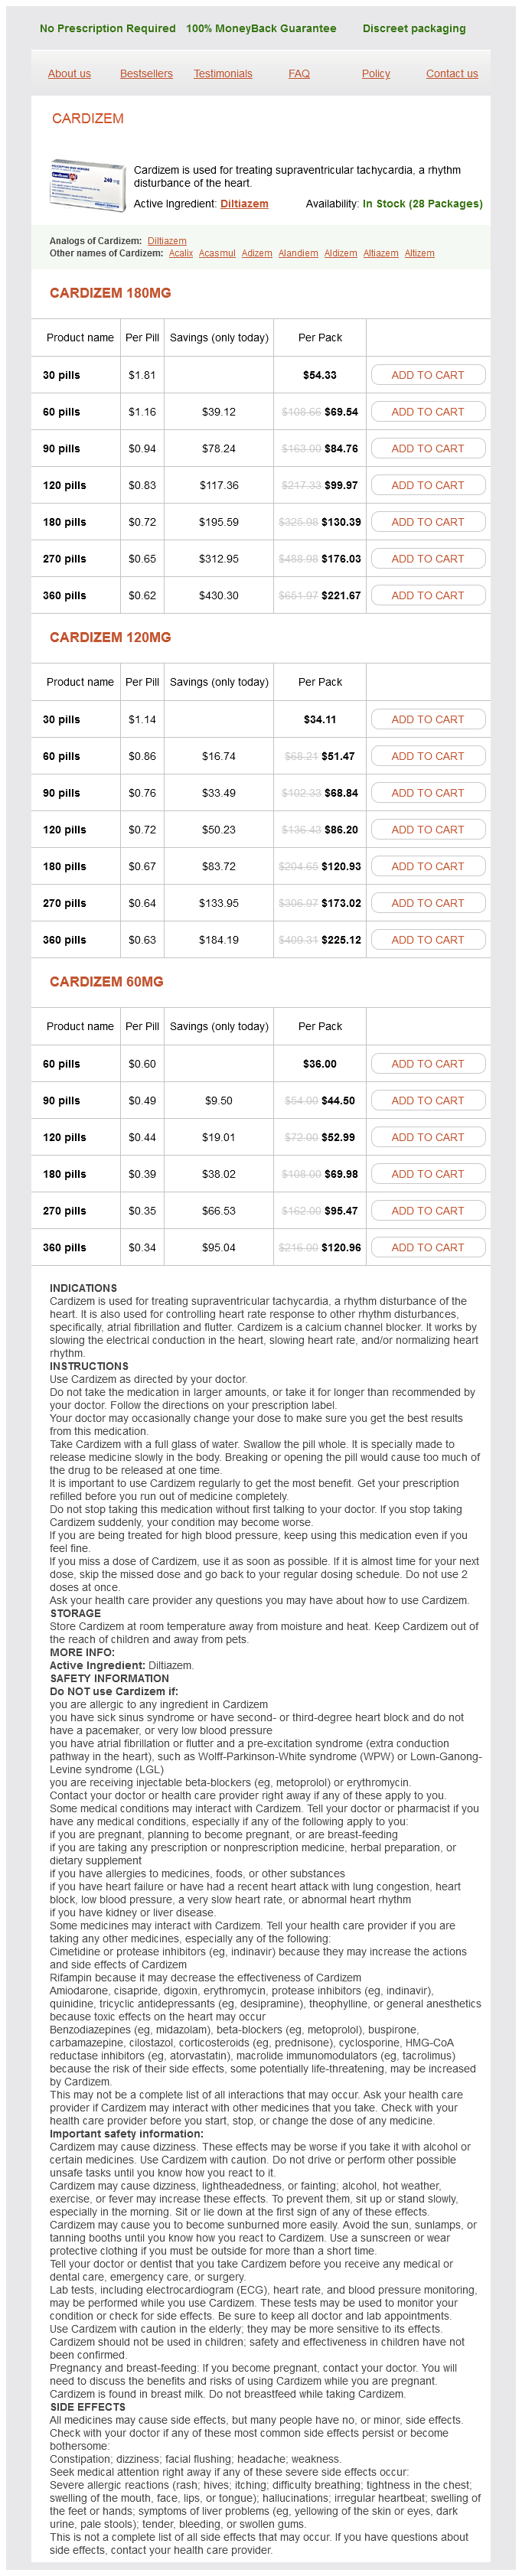
Cardizem 180mg
- 30 pills - $54.33
- 60 pills - $69.54
- 90 pills - $84.76
- 120 pills - $99.97
- 180 pills - $130.39
- 270 pills - $176.03
- 360 pills - $221.67
Cardizem 120mg
- 30 pills - $34.11
- 60 pills - $51.47
- 90 pills - $68.84
- 120 pills - $86.20
- 180 pills - $120.93
- 270 pills - $173.02
- 360 pills - $225.12
Cardizem 60mg
- 60 pills - $36.00
- 90 pills - $44.50
- 120 pills - $52.99
- 180 pills - $69.98
- 270 pills - $95.47
- 360 pills - $120.96
Cardizem dosages: 180 mg, 120 mg, 60 mg
Cardizem packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 851
Only $0,36 per item
Description
Vagal afferents are more numerous within the foregut than the midgut and are concerned with physiological responses corresponding to satiety arteria volaris indicis radialis cheap 180 mg cardizem visa, whereas ache and discomfort are mediated by spinal pathways heart attack and vine cardizem 60 mg purchase overnight delivery. Vascularplexuses Vascular plexuses are current at numerous ranges of the wall blood pressure of 120/80 cardizem 180 mg purchase on line, particularly within the submucosa and mucosa; they connect with vessels that offer the encircling tissues or those entering via the mesentery blood pressure chart different ages 120 mg cardizem with amex, and accompany the ducts of outlying glands. Intrinsic innervation Innervation the intestine wall is densely innervated by each the enteric nervous system (intrinsic control) and the autonomic nervous system (extrinsic control). The enteric nervous system innervates the gut from oesophagus to anus, together with the pancreas and biliary tree. Nerve fibre bundles connect the ganglia and type plexuses innervating the longitudinal muscle, round muscle, muscularis mucosae, intrinsic arteries and the mucosa. Interconnecting, non-ganglionated nerve plexuses lie at varied ranges in the wall of the intestine, including the lamina propria (mucosal plexus), at the interface between the submucosa and muscularis externa, between the circular and longitudinal muscular tissues (the non-ganglionated a part of the myenteric plexus), and within the serosa. Individual enteric neurones function in certainly one of a number of methods: as afferent (sensory) nerves responding to mechanical and chemical stimuli; as efferent (motor) nerves innervating epithelial cells (influencing absorption, secretion and/or the release of hormones), clean muscle (excitatory or inhibitory), arterioles (vasoconstriction or vasodilation) and lymphoid tissue; or as interneurones that relay and integrate signals. The features of enteric neurones could also be additional modulated by local environmental factors. Pathological states turn into manifest by irregular secretion, impaired absorption, disordered gastrointestinal motility and ache. The bifurcation of the belly aorta lies approximately on this airplane (Mirjalili et al 2012a). The transtubercular airplane joins the tubercles of the iliac crests and is traditionally reported to lie on the level of the physique of L5, close to its higher border. It is an approximate landmark for the origin of the inferior vena cava from the confluence of the frequent iliac veins. The airplane of the pubic crest is according to the higher border of the pubic symphysis. In supine individuals, this plane regularly intersects the tip of the coccyx and the femoral head (Mirjalili et al 2012a), however there are variations referring to the diploma of lumbar lordosis, sacral inclination and pelvic tilt. Published descriptions of floor anatomy largely apply to adults, in whom attempts have been made to validate or update normal descriptions utilizing cross-sectional imaging. The extent to which many of these floor projections can be extrapolated to youngsters is unsure; some differences are inevitable, significantly in infants, given their different visceral and body proportions (Stringer 2011). In this chapter, descriptions of the surface projections of belly constructions discuss with probably the most commonly encountered association seen in adults. From superior to inferior, the nine areas are: the epigastrium, flanked by the right and left hypochondrium; the umbilical, or central, flanked by the best and left lumbar; and the suprapubic or hypogastrium, flanked by the right and left iliac fossae. In follow, these areas are sometimes loosely outlined with out strict reference to their boundaries. An different system of description includes dividing the stomach into quadrants using the median aircraft and a horizontal line passing via the umbilicus. From right here, the costal margins could be felt passing inferolaterally from the seventh costal cartilage on the xiphisternal joint to the tip of the twelfth rib (the latter is often difficult to feel within the overweight or if it is short). The lowest part of the costal margin lies in the mid-axillary line and is fashioned by the inferior margin of the tenth costal cartilage. The inferior boundary of the anterior belly wall is formed, from lateral to medial, by the iliac crest, which descends to the anterior superior iliac spine; the inguinal ligament, which runs obliquely downwards to the pubic tubercle; and the pubic crest, which extends from the pubic tubercle laterally to the pubic symphysis within the midline. The pubic tubercle is palpable on the anterosuperior surface of the pubic bone roughly 2 cm lateral to the midline. The prominent tendon of adductor longus (best felt with the hip flexed, abducted and externally rotated) attaches to the pubis directly below the pubic tubercle, and may therefore be used to verify its position. The posterolateral boundary of the anterior belly wall is the mid-axillary line. Vertical traces and planes the midline (or median plane) passes by way of the xiphoid course of and the pubic symphysis. Several horizontal reference planes have been defined however, with modern cross-sectional imaging, their scientific utility for positioning belly viscera has become limited. Nevertheless, they assist to conceptualize the relative positions of belly viscera with respect to vertebral ranges and bony surface landmarks. The xiphisternal joint most frequently lies in the identical horizontal (axial) aircraft as the T9 vertebra (Mirjalili et al 2012b). The transpyloric airplane lies midway between the suprasternal notch of the manubrium and the higher border of the pubic symphysis. Posteriorly, the plane intersects the decrease half of the physique of the primary lumbar vertebra, the L1/2 intervertebral disc, or the higher half of the body of the second lumbar vertebra in most people (range lower T12 to decrease L2); it sits higher in males (lower L1�L1/2) than females (lower L2) (Mirjalili et al 2012a). In the supine adult, it normally lies around the L4 level (range L2/3 disc to higher S1) (Mirjalili et al 2012b). The umbilicus could lie at a lower stage within the erect place, and in kids, the obese and in people with a pendulous abdomen. Key: 1, proper hypochondrium; 2, epigastrium; 3, left hypochondrium; 4, right lumbar; 5, umbilical/central; 6, left lumbar; 7, right iliac fossa; eight, suprapubic/hypogastrium; 9, left iliac fossa; 10, paramedian line; eleven, subcostal plane; 12, transtubercular aircraft. Key: 1, diaphragm position: right dome level with fifth intercostal area and left dome with sixth rib; 2, liver: mapped between three points: proper fifth rib/intercostal space mid-clavicular line, left fifth intercostal space/sixth rib mid-clavicular line and proper tenth costal cartilage mid-axillary line; 3, zone of gastro-oesophageal junction place (white): primarily located posterior to left seventh costal cartilage, at roughly T11; 4, transpyloric aircraft; 5, zone of gallbladder fundus position (white); 6, duodenum: 4 parts marked D1�D4; 7, linea semilunaris; 8, place of small intestine mesentery; 9, linea alba; 10, tendinous intersection of rectus abdominis. Key: 1, spleen; sits deep to ribs 10�12 with lengthy axis aligned with rib eleven; 2, supracristal airplane. It is wider and extra obvious above the umbilicus, and is almost linear and fewer seen below this level (Ch. Up to the extent of the umbilicus, it follows a course that lies roughly 40% of the gap between the midline and a sagittal airplane running through the anterior superior iliac backbone (Epstein et al 2004). The surface anatomy of the artery is especially necessary in laparoscopic surgical procedure because trocar insertion could injure the vessel, inflicting a rectus sheath haematoma or intra-abdominal bleeding. The artery can be prevented if a trocar is inserted no much less than two-thirds of the distance alongside a horizontal line between the midline and a sagittal airplane passing by way of the anterior superior iliac backbone. The mid-inguinal level lies at the midpoint of a line between the pubic symphysis and the anterior superior iliac spine. Superficial reflexes Cremasteric reflex Stroking the pores and skin of the medial aspect of the thigh evokes a reflex contraction of cremaster, which elevates the ipsilateral testis. This border curves slightly downwards at its centre and crosses the midline behind the xiphisternal joint. The proper border of the liver is curved to the right and joins the upper and decrease proper limits. The higher border of the liver may be outlined by dullness to percussion in comparison with the resonance of the lungs above. Superficial belly reflex Gently stroking every of the 4 quadrants of the anterior abdominal wall normally elicits a visual contraction of ipsilateral stomach muscle tissue. The reflex can be utilized to assist localize lesions in the spinal twine but is now of minor scientific significance due to the supply of neuroimaging and the difficulties of eliciting the reflex in multiparous women, the aged and the overweight (Gosavi and Lo 2014). The availability of cross-sectional and ultrasound medical imaging of the belly viscera has led to a decline in using surface anatomy, aside from descriptive functions. The spinous processes of the lumbar vertebrae can be utilized to find vertebral levels, with the lower part of the spinous process marking the level of the intervertebral disc below the correspondingly numbered vertebra. Recent information have proven that the fundus lies in the transpyloric plane in roughly one-third of supine people and under the aircraft in most others (Mirjalili et al 2012b). These levels are approximate, not only because of individual variation but in addition as a result of diaphragmatic excursion in the erect position throughout quiet respiratory is about 2 cm and will increase to about 7 cm throughout deep breathing (Boussuges et al 2009). The dome of the diaphragm can attain as excessive as the fourth rib on maximal expiration. The spleen is traditionally described as sitting on the left posterolateral abdominal wall deep to ribs 9�11. The spleen extends from a degree about 5 cm to the left of the posterior midline at the stage of the eleventh thoracic spine and extends about three cm anterior to the mid-axillary line. The abdomen lies in a curve within the left hypochondrium and epigastrium, although, when distended, it may lie as far down because the umbilical or suprapubic areas. The surface projection of the top of the pancreas lies inside the duodenal curve on the best side of the second lumbar vertebra; the neck lies within the transpyloric plane, degree with the L1/2 intervertebral disc; and the body passes obliquely up and to the left in course of the spleen, mendacity slightly above the transpyloric plane, close to the tail. The duodenojejunal flexure generally sits at L1 (range lower T11 to higher L3) (Mirjalili et al 2012b). Appendix the appendix is located in the best decrease quadrant of the abdomen however is highly variable in its size and position.
Branched Chain Amino Acid Therapy (Branched-Chain Amino Acids). Cardizem.
- Enhancing exercise or athletic performance.
- Are there safety concerns?
- How does Branched-chain Amino Acids work?
- Improving muscle control and mental function in people with advanced liver disease (latent hepatic encephalopathy).
- Are there any interactions with medications?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96966
Subdivisions of the mediastinum tracheal bifurcation blood pressure medication nausea purchase 60 mg cardizem fast delivery, pericardium and pulmonary vessels heart attack 8 days collections purchase 180 mg cardizem otc, and posteriorly by the bodies of the fifth to the twelfth thoracic vertebrae blood pressure j curve purchase cardizem 120 mg line. The arched posterior third of the central portion of the diaphragm constitutes the anteroinferior limit of the posterior mediastinum laterally as the mediastinal pleurae come shut collectively arrhythmia or anxiety cardizem 60 mg buy without prescription. Two pleural recesses, the interaortico-oesophageal and interazygo-oesophageal recesses, intercalate from the left and proper sides between the aorta and oesophagus and the azygos vein and oesophagus, respectively. The posterior mediastinum accommodates the descending thoracic aorta (on the left facet of the spine), the oesophagus (median, but positioned anterior to the aorta inferiorly) and, more posteriorly, the azygos and hemiazygos venous methods, the thoracic duct, lymph nodes, right and left sympathetic chains and thoracic splanchnic nerves. The vagal trunks course adjacent to the oesophagus; the anterior trunk is constituted primarily from the left vagus nerve and the posterior primarily from the right vagus nerve. There are numerous communications between the posterior mediastinum and the abdomen. These are: the oesophageal aperture (also transmits the vagal trunks) on the stage of the tenth thoracic vertebra; the aortic aperture (also transmits the thoracic duct and sometimes the azygos vein) at the level of the twelfth thoracic vertebra; apertures within the diaphragmatic crura that transmit the thoracic splanchnic nerves; apertures deep to the medial lumbosacral arches for the sympathetic chains; and minute openings within the central tendon of the diaphragm that transmit small veins. All openings symbolize potential communication websites for suppurative or neoplastic processes. The former is more more doubtless to be infected than any of the opposite potential tissue areas within the head and neck, communicating with the retropharyngeal and pretracheal spaces, so reaching the superior mediastinum and then the anterior a half of the inferior mediastinum (see Chs 29 and 31). The plane between the buccopharyngeal and prevertebral fasciae is a freeway for unfold of air and gastric contents between the neck and mediastinum after oesophageal injury (Wind and Valentine 2013). The carotid sheath, containing the carotid arteries, jugular veins and vagus nerves, represents another potential route of communication. Great vessels of the superior mediastinum the aortic arch, descending thoracic aorta, pulmonary trunk and superior vena cava are described in Chapter fifty seven. When present, the azygos lumbar vein ascends anterior to the upper lumbar vertebral our bodies and passes either posterior to or via the proper diaphragmatic crus or traverses the aortic hiatus to the best of the cisterna chyli. In the absence of a lumbar azygos vein, this common trunk may proceed as the azygos vein proper. The azygos vein passes to the best, posterior to the best crus of the diaphragm, and ascends in the posterior mediastinum to the extent of the fourth thoracic vertebra, where it arches anteriorly, superior to the right pulmonary hilum, and joins the posterior side of the superior vena cava, simply superior to its pericardial incorporation. In its course, the azygos vein lies anterior to the our bodies of the lower eight thoracic vertebrae, anterior longitudinal ligament and proper posterior intercostal arteries. Right lateral relations are the best sympathetic chain, the best larger splanchnic nerve, lung and pleura. Left lateral relations are the thoracic duct, aorta and, where the vein arches anteriorly, the oesophagus, trachea and right vagus. The recess is dextroconvex beneath the age of 6 years, non-concave (equally divided between straight and convex) between 6 and 12 years and concave, as in adults, after the age of 12 years (Miller et al 1993). Its major tributaries are the proper intercostal veins (the first drains into the right brachiocephalic vein and the second, third and fourth form a common trunk, the superior intercostal vein), the proper ascending lumbar and subcostal veins, mediastinal, oesophageal, pericardial and right bronchial veins, and the hemiazygos and accent hemiazygos veins. Numerous anastomoses exist between the tributaries and the principle trunks of the azygos, hemiazygos and accent hemiazygos veins, the inferior vena cava and the vertebral venous plexuses. On the best side, this is the upper margin of the right higher lobe bronchus; the overwhelming majority of nodes in this space are inclined to be positioned anterolateral to the trachea. On the left aspect, the nodes are situated under the upper margin of the aortic arch and above the margin of the left higher lobe bronchus. It originates in a similar way (from the union of the left lumbar ascending and subcostal veins) but displays extra variability; it might additionally connect with the left renal vein by way of the equivalent of the lumbar azygos vein. It receives the lower three left posterior intercostal, mediastinal and oesophageal veins. Oesophagus, cervical half Thyroid gland, right lobe Common carotid artery Brachiocephalic trunk Subclavian artery Superior vena cava Trachea Superior tracheobronchial nodes Azygos vein Accessory hemiazygos vein the accessory hemiazygos vein capabilities because the left-sided mirror image of the superior portion of the azygos vein. It drains the fifth to eighth posterior intercostal veins and infrequently the left bronchial veins, and normally terminates in the azygos vein after crossing the seventh thoracic vertebra. The first posterior intercostal vein drains directly into the left brachiocephalic vein, while the second to the fourth drain not directly to the accessory hemiazygos vein through the left superior intercostal vein. The origin, course, tributaries, anastomoses and termination of the azygos system of veins are all extremely variable. The left channel could additionally be absent or underdeveloped, permitting direct drainage of the left intercostal veins into the azygos and/or the termination of the accent hemiazygos into the left brachiocephalic vein. Left inferior pulmonary vein Posterior mediastinal nodes Oesophagus, thoracic part 7 Superior tracheobronchial nodes Right pulmonary artery Right inferior pulmonary vein Posterior mediastinal nodes Pulmonary arteries and veins the pulmonary vessels are described on pages 959 and 960. Inferior vena cava Mediastinal lymph nodes For the needs of staging lung most cancers, thoracic surgeons classify the mediastinal lymph nodes into regional lymph node stations, that are defined as shown in Table 56. Pulmonary nodes turn out to be steady with the bronchopulmonary nodes, and these, in flip, merge with the inferior and superior tracheobronchial nodes, that are continuous with the paratracheal group. The tracheobronchial nodes drain the lungs, bronchi, the thoracic part of the trachea, and heart, and also receive efferents from the posterior mediastinal nodes. Mediastinum In congenital interruption of the inferior vena cava or acquired thrombosis, the azygos system offers another pathway for venous drainage. Metastatic involvement of these lymph nodes has important prognostic implications and influences the choice of remedy (Mountain and Dresler 1997). The staging system for lung cancer classifies involvement of ipsilateral hilar lymph nodes as N1, ipsilateral mediastinal lymph nodes as N2, contralateral mediastinal or hilar nodes as N3 and supraclavicular/scalene nodes as M1 (distant metastases). It usually originates anterior to the primary or second lumbar vertebrae, the place the intestinal and two lumbar lymph trunks be part of to type the cisterna chyli. It continues upwards, first posterior to the aortic arch adjoining to the left facet of the oesophagus, then posterior to the left subclavian artery within the superior mediastinum. In the area between longus colli, the anterior scalene muscle tissue and the pleural dome, the duct normally arches 3 or four cm superior to the clavicle, crossing anterior to the vertebral vessels, the left sympathetic trunk, the vertebral ganglion, the thyrocervical trunk and the left phrenic nerve. In some patients, two thoracic ducts exist inside the mediastinum, and infrequently a single thoracic duct might empty into rightsided venous structures, the latter disposition being extra frequent in individuals with an aberrant right subclavian artery (the latter originating from the distal aortic arch ascending posterior to the oesophagus). When present as a single channel, the thoracic duct is 5 mm in diameter at its origin, narrows to 2�3 mm at mid-thoracic degree and then widens again at its termination. Alternatively, it could divide into two or three branches that finally reunite or drain into both the left and proper venous systems. The duct seems sinuous and has valves all through its length; a bicuspid valve at its termination may prevent the backflow of blood. As it passes through the mediastinum, the thoracic duct additionally receives non-chylous lymph from tributaries that drain areas of the pulmonary parenchyma and parietal pleura. The sum of these sources accounts for a total lymphatic flow through the thoracic duct of 1500�2400 ml per day in proportion to the dietary intake of fat, significantly long-chain triglycerides. The anatomy of the thoracic duct determines the situation of the effusion seen with duct damage or obstruction. Tributaries of the thoracic duct Right lymphatic duct Oesophagus Thoracic duct Jugular lymph trunk Right bronchomediastinal trunk Subclavian lymph trunks Brachiocephalic vein Superior vena cava Some tributaries of the thoracic duct might terminate immediately within the venous system. Besides the cisterna chyli and its tributaries, bilateral ascending lumbar lymph trunks from the upper lateral aortic nodes pierce the corresponding diaphragmatic crus and ultimately join the thoracic duct within the posterior mediastinum. The inferior six or seven intercostal lymph trunks from the corresponding bilateral intercostal nodes descend to terminate in the duct, either immediately or by variable common trunks. The left upper intercostal lymphatics may be part of the cervical portion of the duct or the subclavian trunk. The left subclavian trunk normally joins the thoracic duct however may open independently into the left subclavian vein. These mediastinal trunks present lymph drainage paths to the thoracic duct from the convex diaphragmatic aspect of the liver, the diaphragm, the pericardium, coronary heart and oesophagus, and lots of possess terminal bicuspid valves. The left bronchomediastinal trunk often joins the thoracic duct however normally has an impartial venous termination. The left jugular trunk normally joins the thoracic duct but could open independently into the left inner jugular vein. Azygos vein Accessory hemiazygos vein Injury throughout oesophageal surgery Intercostal lymph nodes Thoracic duct Hemiazygos vein Cisterna chyli Confluence of lymph trunks Lateral aortic lymph nodes Retro-aortic lymph nodes the variable origin, course and length of the thoracic duct, coupled with failure to determine it at surgical procedure, may result in its inadvertent incision or transection, particularly throughout trans-hiatal and thoracoscopic oesophageal surgery, with an incidence between 0. Thoracic duct laceration is a potentially life-threatening complication; mortality rates are larger with conservative management however nonetheless elevated even after surgical ligation. Rupture of the thoracic duct results in leakage of chyle, which is wealthy in lipid, protein, T lymphocytes (ranging from 400 to 6800 cells/�l), immunoglobulins and fat-soluble vitamins, and therefore a progressive dietary and immune deficit develops. Postoperative chylous effusions are often the outcomes of injury to ductal tributaries quite than to the duct itself, and are usually self-limiting. The larger incidence of harm with trans-hiatal resection could also be attributable to shear forces during the mobilization of the distal oesophagus, whereas the restricted subject of view in all probability contributes to the larger incidence of thoracic duct injury throughout thoracoscopic surgical procedure.
Specifications/Details
The most beneficial effects of thymectomy are seen in myasthenic females who present with systemic muscular weakness; controversial operative teams include the aged and those with isolated ocular symptoms pulse pressure under 30 120 mg cardizem order. Generally vertical in its course hypertension 24 120 mg cardizem generic with visa, the oesophagus usually displays two shallow curves prehypertension vyvanse cardizem 180 mg buy lowest price. Starting within the median airplane heart attack single 180 mg cardizem discount otc, it inclines to the left so far as the root of the neck, gradually returns to the median aircraft close to the fifth thoracic vertebra, then deviates leftwards once more on the seventh thoracic vertebra before piercing the diaphragm. The oesophagus additionally deviates sagittally as it follows the cervicothoracic vertebral lordosis. In kids, the size of the oesophagus correlates finest with top (Yang et al 2005). The cervical strategy includes a lower transverse incision that includes the sternal heads of both sternocleidomastoids, permitting an improved access to the substernal aircraft. Sternothyroid and sternohyoid are separated and the superior poles of the thymus are identified immediately beneath these muscles. A safe pre-thymic airplane is created by blunt dissection just posterior to the sternum, facilitating subsequent mobilization of the gland. The mediastinal great vessels and the thymic vessels must be carefully identified. The thymic veins are selectively ligated and divided, particularly these draining immediately into the superior vena cava or the left brachiocephalic vein. The smaller arterial branches from the internal thoracic arteries are often handled using electrocautery, care being taken to avoid harm to the phrenic nerves (patients are generally not given a paralytic agent during anaesthesia, in order for the phrenic nerves to be identified intraoperatively). The thymus typically stays completely encapsulated and is separated with out problem from the pericardium (occasionally, adhesions necessitate a limited pericardiectomy). Further inferiorly, a gentle push on the good vessels permits direct visualization into the aortopulmonary window for complete removing of the thymus on this neighborhood. In most instances, the thymus gland is eliminated utterly with both higher and lower poles intact. Careful inspection of the remaining tissue in the mediastinum is carried out to identify any possible anatomical anomalies that might end in retained thymic tissue after the operation. The most common anomaly is the unanticipated location of the higher poles of the thymus behind the left brachiocephalic vein. The aortopulmonary window is also a standard location for thymic tissue and this area is typically difficult to expose with a transcervical approach. Any suspicious foci of fat in the mediastinum are removed, and, if necessary, despatched for frozen part to ascertain whether or not or not they contain thymic tissue. Thymic tumours might compress the trachea, oesophagus and huge veins in the neck, inflicting hoarseness, cough, dysphagia and venous engorgement of the head and neck. Many affected patients even have myasthenia gravis and other autoimmune situations. Myasthenia gravis, a chronic autoimmune disease of adults, presents as a diminution in power of repetitive contraction in sure voluntary muscular tissues. Although there could also be a couple of situation with these signs, myasthenia gravis is essentially an autoimmune disease during which acetylcholine receptor proteins of neuromuscular junctions are attacked by autoantibodies. Muscles commonly involved are levator palpebrae superioris, resulting in ptosis, and the extraocular muscles, resulting in diplopia. Other muscles in the face, jaws, neck and limbs could additionally be concerned, and in severe circumstances, the ventilatory muscle tissue are compromised. Posteriorly are the vertebral column, longus colli and the prevertebral layer of deep cervical fascia. Laterally, on both sides, are the common carotid arteries and the posterior a half of the thyroid gland. On the right of the oesophagus, just above the diaphragm, a small, serous infracardiac bursa could happen, representing the detached apex of the best pneumatoenteric recess. The shut relationship between the oesophagus, the center and the aorta constitutes the anatomical foundation of transoesophageal cardiovascular ultrasonography. It passes behind and to the proper of the aortic arch to descend within the posterior mediastinum alongside the best facet of the descending thoracic aorta. Below, as it inclines left, it crosses anterior to the aorta and enters the stomach through the diaphragm at the level of the tenth thoracic vertebra. From above downwards, the trachea, right pulmonary artery, left principal bronchus, pericardium (separating it from the left atrium) and the diaphragm are anterior. The vertebral column, longus colli, proper posterior intercostal arteries, thoracic duct, azygos vein and the terminal parts of the hemiazygos and accent hemiazygos veins, and, close to the diaphragm, the aorta are posterior. A lengthy recess of the proper pleural sac lies between the oesophagus anteriorly and the azygos vein and vertebral column posteriorly within the posterior mediastinum (the azygo-oesophageal recess). In the superior mediastinum, the terminal a part of the aortic arch, left subclavian artery, thoracic duct, left pleura and the recurrent laryngeal nerve are left lateral relations. In the posterior mediastinum, the oesophagus is said to the descending thoracic aorta and left pleura. The proper pleura and the azygos vein, because it arches forwards above the proper main bronchus to be a part of the superior vena cava, are proper lateral relations. Below the pulmonary roots, the vagus nerves descend in touch with the oesophagus, the proper primarily behind and the left in entrance; the vagi subsequently unite to type a plexus across the oesophagus. Low within the posterior mediastinum, the thoracic duct is posterior and to the right of the oesophagus; at larger levels, the duct is posterior, crossing to the left of the oesophagus at about the degree of the fifth thoracic vertebra, then ascending on the left. Four or 5 oesophageal branches come up from the anterior surface of the aorta and descend obliquely to the oesophagus, where they type a vascular chain that anastomoses above with the oesophageal branches of the inferior thyroid arteries, and under with ascending branches from the left phrenic and left gastric arteries. Extensive devascularization of the oesophagus might lead to acute oesophageal necrosis as in aortic dissection (van der Wal-Visscher et al 2011). Veins Blood from the oesophagus drains into a submucous plexus and thence right into a peri-oesophageal venous plexus, from which the oesophageal veins arise. The left gastric vein meets the decrease oesophageal veins on the oesophageal opening in the lesser curvature, one of the websites of porto-caval venous anastomoses where variceal transformation can happen in portal hypertension (see below). Porto-systemic shunting of blood occurs between the brief gastric coronary veins and the oesophageal veins, largely as the results of the dilation of pre-existing embryonic channels. G Lymphatic drainage the oesophagus has an intensive, longitudinally continuous submucosal lymphatic system, which presumably explains remote paraoesophageal lymphadenopathy in oesophageal carcinoma. Efferent vessels from the cervical oesophagus drain to the deep cervical nodes both instantly or through the paratracheal nodes. Vessels from the thoracic oesophagus drain to the posterior mediastinal nodes and those from the stomach oesophagus drain to the left gastric lymph nodes. Motor fibres to the striated and clean muscle of the oesophageal wall travel within the vagus. Axons derived from neuronal cell bodies in the nucleus ambiguus travel via the recurrent laryngeal nerve and provide cricopharyngeus and the striated muscle of the upper third of the oesophagus. Axons with cell our bodies within the dorsal nucleus of the vagus pass through the oesophageal plexus and provide the sleek muscle that makes up the lower two-thirds of the oesophagus, after local relay in the oesophageal wall. Other branches are given off by the vagus as it travels by way of the mediastinum, and move directly to the oesophagus. The vagus also carries secretomotor fibres to mucous glands within the oesophageal mucosa, and visceral afferent (sensory) fibres to cell bodies in its inferior ganglion. Vasomotor sympathetic fibres destined for the oesophagus come up from the higher 4�6 thoracic spinal wire segments. Those from the upper ganglia move to the center and inferior cervical ganglia, where they synapse on postganglionic neurones that give rise to axons that innervate the vessels of the cervical and higher thoracic oesophagus. Those from the lower ganglia cross either on to the oesophageal plexus or to the coeliac ganglion (via the higher splanchnic nerve), the place they synapse; postganglionic axons innervate the distal oesophagus. Afferent visceral ache fibres travel by way of the sympathetic fibres to the primary 4 segments of the thoracic spinal cord. At the gastro-oesophageal junction, a jagged boundary line separates the greyish-pink smooth oesophageal mucosa from the reddish-pink gastric mucosa, the latter lined by minute bulges and depressions. Throughout its length, the oesophageal lumen is marked by deep longitudinal grooves and ridges, which disappear when the lumen is distended, in any other case obliterating it. It can be divided right into a basal, proliferative layer, a parabasal layer of cells undergoing terminal differentiation and a flattened layer of superficial cells or squames that retain their nuclei.
Syndromes
- Vision testing
- You develop new symptoms (such as weight loss, problems swallowing).
- Measure your testosterone levels one or more times.
- ERCP
- Carbonic anhydrase inhibitors (used to treat glaucoma)
- High blood pressure
Related Products
Additional information:
While patients generally current with pain and stiffness of the wrist blood pressure khan academy order cardizem 120 mg on line, these signs correlate poorly with the radiological findings and arrhythmia unspecified icd 9 code order cardizem 60 mg without a prescription, certainly blood pressure in children effective cardizem 60 mg, patients may be asymptomatic hypertension benign essential 180 mg cardizem generic with mastercard. Note the early phases of ossification within the epiphyses at the proximal ends of the phalanges and first metacarpal; the distal ends of the remaining metacarpals and radius; and for the capitate, hamate and lunate. Typically, the centre for the lunate is preceded by the centre for the triquetrum. Sesamoid bones glide on radial and ulnar articular eminences on its palmar side. The latter is grooved in a dorsopalmar direction for articulation with the trapezoid. The medial aspect of the base articulates with that of the third metacarpal by a protracted facet, centrally narrowed. The shaft is prismatic in part and longitudinally curved, convex dorsally, concave in course of the palm. Its converging borders begin at the tubercles, one on both sides of its head for the attachment of collateral ligaments. Proximally, the lateral floor inclines dorsally for the ulnar head of the first dorsal interosseous. Key: 1, head of center phalanx of center finger; 2, head of proximal phalanx of ring finger; three, shaft of proximal phalanx of ring finger; four, head of fifth metacarpal; 5, shaft of fifth metacarpal; 6, base of fifth metacarpal; 7, hook of hamate; eight, triquetrum; 9, hamate; 10, pisiform; 11, styloid process of ulna; 12, lunate; 13, head of ulna; 14, distal phalanx of index finger; 15, distal phalanx of thumb; sixteen, proximal phalanx of thumb; 17, sesamoid bone; 18, trapezoid; 19, trapezium; 20, capitate; 21, scaphoid; 22, styloid means of radius; 23, distal radio-ulnar joint; 24, radius. Its base articulates with the capitate by a facet anteriorly convex however dorsally concave where it invades the styloid course of on the lateral aspect of its base. A strip-like side, constricted centrally, articulates with the bases of the second metacarpal (laterally) and the fourth metacarpal (medially), the latter by two oval sides. The palmar side could also be absent; less regularly, the sides are connected proximally by a slender bridge. The palmar floor of the bottom receives a slip from the tendon of flexor carpi radialis; extensor carpi radialis brevis is connected Bones A. First metacarpal Eighth week Unite 15 to 18 years Second to fourth year Twelfth week Unite 15 to 18 years Second to fourth 12 months Tenth week For trapezium Unite 15 to 18 years Second yr 1. On its base, it displays two lateral oval aspects for articulation with the bottom of the third metacarpal; the dorsal is normally bigger and proximally in touch with the capitate. A single medial elongated facet is for articulation with the base of the fifth metacarpal. The shaft is just like the second, but a faint ridge on its lateral floor separates the attachments of the third palmar interosseous and the ulnar head of the third dorsal interosseous. The radial head of the fourth dorsal interosseous is hooked up to the medial floor. The lateral basal surface is a facet, transversely concave, convex from palm to dorsum, for articulation with the hamate. The shaft bears a triangular dorsal area that simply about reaches the bottom; the lateral floor inclines dorsally solely at its proximal finish. The lateral floor is split by a ridge, which is typically sharp, into a palmar strip for the attachment of the fourth palmar interosseous and a dorsal strip for the ulnar part of the fourth dorsal interosseous. Centres for the second to fifth metacarpal heads seem in that order in the second year in females, and between eleven 2 to 2 1 2 years in males. They unite with the shafts concerning the fifteenth or sixteenth 12 months in females, and the eighteenth or nineteenth in males. The first metacarpal base begins to ossify late in the second yr in females, early within the third 12 months in males, uniting before the fifteenth yr in females and seventeenth in males. The thumb metacarpal ossifies like a phalanx, and a few authorities due to this fact think about that the thumb skeleton consists of three phalanges. Others consider that the distal phalanx represents fused middle and distal phalanges, a condition occasionally noticed in the fifth toe. When the thumb has three phalanges, the metacarpal has a distal and a proximal epiphysis. When it does, the medial department has no distal epiphysis and bears two phalanges, while the lateral department reveals a distal epiphysis, and three phalanges. The existence of solely a distal metacarpal epiphysis may be associated with a higher range of motion on the metacarpophalangeal joint. In the thumb, the carpometacarpal joint has the broader vary, and the first metacarpal has a basal epiphysis. A distal epiphysis could appear in the first, and a proximal epiphysis within the second, metacarpal. The ulnar head of the second dorsal interosseous is hooked up to its lateral surface; the radial head of the third dorsal interosseous is attached to its medial surface, and the transverse head of adductor pollicis is hooked up to the intervening palmar ridge in its distal two-thirds. The palmar floor is transversely flat however gently concave anteriorly in its lengthy axis. The bases of the proximal phalanges carry concave, oval aspects adapted to the metacarpal heads. Their personal heads are smoothly grooved like pulleys and encroach extra on to the palmar surfaces. The bases of the center phalanges carry two concave sides separated by a clean ridge, conforming to the heads of the proximal phalanges. The bases of the distal phalanges are tailored to the pulley-like heads of the center phalanges. The heads of the distal phalanges are non-articular and carry a rough, crescentic palmar tuberosity, to which the pulps of the fingertips are attached. The tendon of flexor digitorum profundus is connected to the palmar facet of the base of the phalanx and the tendon of extensor digitorum to its dorsal floor. The tendon of flexor digitorum superficialis and its fibrous sheath are connected to the sides of the middle phalanx, and a part of extensor digitorum is hooked up to the base dorsally. The fibrous flexor sheath is attached to the edges of a proximal phalanx, part of the corresponding dorsal interosseous is hooked up to its base laterally, and one other dorsal interosseous is attached medially. Abductor and flexor digiti minimi are attached to the medial side of the bottom of the proximal phalanx of the little finger. The tendon of extensor pollicis brevis and the indirect head of adductor pollicis (dorsally), and the oblique and transverse heads of adductor pollicis, generally conjoined with the first palmar interosseous (medially), are hooked up to the base of the proximal phalanx of the thumb. Epiphyseal centres seem in proximal phalanges early within the second yr (females), or later in the identical year (males), and in middle and distal phalanges within the second yr (females), or third or fourth year (males). All epiphyses unite in regards to the fifteenth to sixteenth yr in females, and seventeenth to eighteenth yr in males. In the neutral place of the wrist, only the scaphoid and lunate are in touch with the radius and articular disc; the triquetrum comes into apposition with the disc only in full adduction of the wrist joint. The radial articular surface and distal discal surface form an nearly elliptical, concave surface with a transverse long axis. A comparable ridge usually appears between the medial radial concavity and the concave distal discal surface. A protruding prestyloid recess (recessus sacciformis), anterior to the articular disc, is current and ascends close to the styloid course of. The recess is bounded distally by the fibrocartilaginous meniscus, which projects from the ulnar collateral ligament between the tip of the ulnar styloid process and the triquetrum; both are clothed with hyaline articular cartilage. The capsule is strengthened by palmar radiocarpal and ulnocarpal, dorsal radiocarpal and radial and ulnar collateral ligaments. Key: 1, extensor pollicis longus; 2, extensor carpi radialis brevis; 3, extensor carpi radialis longus; 4, radius; 5, extensor pollicis brevis; 6, abductor pollicis longus; 7, flexor pollicis longus; 8, radial artery; 9, median nerve; 10, flexor carpi radialis; eleven, flexor digitorum superficialis; 12, palmaris longus; thirteen, extensor digitorum and extensor indicis; 14, extensor digiti minimi; 15, extensor carpi ulnaris; 16, ulna; 17, flexor digitorum profundus; 18, flexor carpi ulnaris. Key: 1, trapezoid; 2, trapezium; three, flexor digitorum profundus; 4, median nerve; 5, thenar muscular tissues; 6, capitate; 7, hamate; eight, flexor digitorum superficialis; 9, hypothenar muscles; 10, ulnar artery and nerve. C, Coronal view demonstrating regular bony anatomy and the triangular fibrocartilage: dorsal aspect. Key: 1, base of fifth metacarpal; 2, hamate; 3, triquetrum; four, lunate; 5, triangular fibrocartilage; 6, distal ulna; 7, base of second metacarpal; 8, trapezoid; 9, capitate; 10, scaphoid; 11, scapholunate ligament; 12, distal radius. Synovial cavities of carpometacarpal joints are prolonged slightly between the metacarpal bases. Muscles producing movement Movements accompany those of the intercarpal and midcarpal joints, and are described on web page 874. Wrist ligaments the distal radio-ulnar joint and triangular fibrocartilage advanced are described on pages 845�848.
Usage: gtt.
It is separated by the pericardium from the left phrenic neurovascular bundle heart attack get me going cardizem 60 mg order without prescription, and by the left pleura from the deep concavity of the left lung blood pressure in spanish buy cardizem 60 mg cheap. Anatomical apex of the center that is the apex of the conical left ventricle blood pressure vs age buy cardizem 180 mg low price, which is directed anteroinferiorly and to the left heart attack meme cardizem 60 mg cheap fast delivery. The apex is positioned mostly behind the fifth left intercostal house, near or slightly medial to the midclavicular line. It consists of an atrial space superior and to the best, and a ventricular part inferior and to the left of the atrioventricular groove. The atrial area is occupied nearly totally by the right Right surface of the guts the right floor is rounded and shaped by the best atrial wall. It is separated from the mediastinal aspect of the best lung by the pericardium and pleural coverings. Its convexity merges inferiorly into the short intrathoracic part of the inferior vena cava and above into the superior vena cava. The manubrium sterni has been retracted cranially, the thymus has been utterly removed and the pericardium has been partially eliminated. The hilum of the lung has been dissected to expose the tracheobronchial lymph nodes. The junction between the venous part (sinus venosus) and the atrium proper is marked externally by a shallow groove, the sulcus terminalis, extending between the right sides of the openings of the two venae cavae. The sulcus terminalis corresponds, internally, to the terminal crest (crista terminalis), which is the site of origin of the intensive pectinate muscular tissues that arise serially at proper angles from the crest. Laterally, the atrium can be associated to the mediastinal floor of the proper lung, but anterior to its hilum and separated from it by the pleura, proper phrenic nerve and pericardiacophrenic vessels and pericardium. Posteriorly and to the left, the interatrial septum and the encircling infolded atrial partitions separate the atria (the mural infolding is indicated by an extensive interatrial groove). Medially are the ascending aorta and, to a limited extent, the pulmonary trunk and its bifurcation. Right border of the center Corresponding to the right atrium, the profile of the right border is slightly convex to the best because it approaches the vertical. Inferior border of the center Also often identified as the acute margin of the guts, the inferior border is sharp, thin and nearly horizontal. It extends from the lower restrict of the right border to the apex and is formed mainly by the proper ventricle, with a small contribution from the left ventricle close to the apex. Left border of the heart Also often known as the obtuse margin, the left border separates the sternocostal and left surfaces. It is spherical and primarily formed by the left ventricle but, to a slight extent superiorly, is fashioned by the left atrial appendage. It descends obliquely, convex to the left, from the appendage to the cardiac apex. Its partitions form the proper superior sternocostal surface, the convex proper (pulmonary) floor and a little of the best facet of the anatomical base. The wall of the vestibule is clean however its junction with the appendage is ridged throughout the atrioventricular junction by pectinate muscle tissue. The smooth-walled systemic venous sinus receives the openings of the venae cavae and coronary sinus; it originates from the sinus venosus of the embryonic heart. B, the triangle of Koch, defined by the tendon of Todaro, orifice of the coronary sinus and the septal leaflet of the tricuspid valve. The superior and inferior venae cavae have been dissected, exposing the venous component of the right atrium and the fossa ovalis. The superior vena cava returns blood from head, neck and higher limb through an orifice that faces anteroinferiorly and has no valve; it additionally receives blood from the chest wall and the oesophagus via the azygos system. It drains blood from all constructions below and including the diaphragm into the bottom a part of the atrium near the septum. When traced inferiorly, it varieties the Eustachian ridge, which runs into the sinus septum (see below), continuous with the valve of the coronary sinus. The lateral part of the valve turns into steady with the decrease finish of the terminal crest. The Eustachian valve is giant throughout fetal life, when it serves to direct richly oxygenated blood (from the placenta) from the right atrium by way of the foramen ovale of the interatrial septum into the left atrium. It is usually guarded by a thin, semicircular Thebesian valve that covers the lower part of the orifice. The higher limb of this valve joins the Eustachian valve and its muscular extension, the Eustachian ridge. It also joins a tendinous construction, the tendon of Todaro, running from this commissure into the sinus septum, which is the septum between the coronary sinus and the fossa ovalis. The tendon of Todaro runs forwards to insert into the central fibrous body and is one of the landmarks of the triangle of Koch (see below). The coronary sinus begins at the confluence of the oblique vein of the left atrium and the great cardiac vein, and receives the middle and small cardiac veins close to its junction with the proper atrium. Several small venous ostia, draining the minimal atrial veins, are found scattered across the atrial walls. They return a small fraction of blood from the center, and are most numerous on the septal aspect. The anterior cardiac veins and, generally, the best marginal vein may enter the atrium through larger ostia. The right atrium and its appendage are separated from the venous sinus by the crista terminalis, a easy, C-shaped muscular ridge that originates from the upper part of the septal surface and, passing anterior to the orifice of the superior vena cava, skirts its right margin to attain the proper facet of the orifice of the inferior vena cava. It marks the positioning of the right venous valve of the embryonic heart, corresponding externally to the terminal groove. The imply length of the crest is fifty one � 9 mm and its thickness from epicardium to endocardium on the junction of the superior vena cava with the posterior atrial wall is 5. The pectinate muscular tissues (musculi pectinati) are almost parallel muscular ridges that stretch anterolaterally from the terminal crest, reaching into the appendage the place they kind a quantity of trabeculations. The largest and most prominent pectinate muscle, forming the bridge of the sulcus terminalis internally, is the taenia sagittalis (second crest or septum spurium). The septal wall presents the fossa ovalis, an oval despair superior and to the left of the orifice of the inferior vena cava. Often mentioned to characterize the edge of the so-called septum secundum, in reality the muscular borders of the fossa are not extra than infoldings of the atrial partitions, incorporating extracardiac adipose tissue. Some hearts show an extreme quantity of extracardiac adipose tissue inside the fold, raising a marked elevation of the superior rim of the fossa (intervenous tubercle of Lower). A small slit is typically found on the upper margin of the fossa, ascending beneath the rim to talk with the left atrium. This represents failure of obliteration of the fetal foramen ovale, which remains patent in up to one-third of all regular hearts. Anteroinferior in the best atrium is the massive, oval vestibule resulting in the orifice of the tricuspid valve. The bulging atrial wall anterosuperior to the membranous septum, the aortic mound (torus aorticus), marks the situation of the non-coronary aortic sinus with its enclosed valvular leaflet. Right ventricle the best ventricle extends from the right atrioventricular (tricuspid) orifice almost to the cardiac apex. It then ascends to the left to turn out to be the infundibulum, or conus arteriosus, reaching the pulmonary orifice and supporting the leaflets of the pulmonary valve. Topographically, the ventricle possesses an inlet part that helps and surrounds the tricuspid valve; a coarsely trabeculated apical part; and a muscular outlet or infundibulum that surrounds the attachments of the pulmonary valve leaflets. The left pleura and, to a lesser extent, the anterior margin of the left lung are interposed above and to the left. The inferior surface is flat and is expounded primarily, with the interposition of the pericardium, to the central tendon and a small adjoining muscular part of the diaphragm. The left and posterior wall is the ventricular septum, barely curved and bulging into the best ventricle so that, in sections across the cardiac axis, the outline of the best ventricle is crescentic. The wall of the right ventricle is comparatively skinny (3�5 mm), the ratio of the thickness of the 2 ventricular partitions normally being 1: 3. The crest is made up predominantly by the inside coronary heart curvature, bounded on the epicardial side by the rightward margin of the transverse sinus. The prominent sub-Thebesian recess is positioned posterior to the Eustachian valve and posteroinferior to the ostium of the coronary sinus. The space between the Eustachian and tricuspid valves inferior to the ostium of the coronary sinus (the cavotricuspid isthmus) is the goal of catheter-directed ablation procedures, the treatment of choice for atrial flutter (S�nchez-Quintana et al 2013). There are multiple attachment sites around the opening of the inferior vena cava and inferiorly in direction of the coronary sinus (the reflected part of the proper atrium covers the distal attachment to the coronary sinus). The Eustachian valve separates the inferior vena cava from the sub-Thebesian recess.
Tags: cardizem 120 mg buy cheap, purchase 60 mg cardizem overnight delivery, buy cardizem 120 mg low price, cardizem 120 mg buy, 60 mg cardizem with amex, generic cardizem 180 mg with mastercard, discount cardizem 180 mg visa, order 120 mg cardizem fast delivery, cardizem 60 mg order visa, generic 180 mg cardizem fast delivery, order cardizem 180 mg amex, purchase 120 mg cardizem free shipping, cardizem 180 mg low cost, 180 mg cardizem cheap fast delivery, generic cardizem 180 mg with amex, 120 mg cardizem cheap visa
9 of 10
Votes: 268 votes
Total customer reviews: 268
Customer Reviews
Owen, 43 years: The remaining floor is devoid of attachments and covered by the lengthy and short extensors of the thumb. Later phases of respiratory growth contain the repeated division of the bronchial tree to type the subsegmental bronchi. Posteriorly, the thymus is involved with the vessels of the superior mediastinum (the left brachiocephalic vein and the inferior thyroid veins are normally partly embedded within the gland), the superior part of the thoracic trachea and the anterior cardiac surface (right atrium and ventricle).
Elber, 53 years: Extensions from the extensor expansion, each collateral ligament and the palmar ligament all cross into the joint cavity and supply a significant enhance to the articular surface area of the phalangeal base; their deformable nature improves joint congruence. Its superficial location makes it a super candidate for utilization as a muscular flap in plastic reconstruction of the top and neck region. The varied sessile (retroperitoneal) organs may be seen through the posterior parietal peritoneum.
Hassan, 27 years: As a agency fist is swung forwards in anger, brachioradialis stands out; in the intervening time of impact, nearly every muscle within the limb is active. As the foramen primum diminishes in measurement, the upper margin of the septum primum perforates by apoptosis and, thus, right to left shunting of blood continues by way of a secondary foramen, the foramen or ostium secundum. The suprascapular artery, which has a variable pattern, descends behind the muscle, passing between it and omohyoid anteriorly and the subclavian vessels posteriorly; the artery, subsequently, has a detailed relationship to the posterior floor of the clavicle, a function that makes it prone to injury throughout clavicular fracture and surgical fixation.
Chris, 23 years: It extends from the lateral facet of the ulnar tuberosity to the radius a little distal to its tuberosity. For example, the fasciae overlying the three muscular tissues of the scapular fossae (subscapularis, infra spinatus and supraspinatus) are properly connected and thicker medially; the fibroosseous cuff so shaped across the medial elements of the muscle tissue affords a larger space of attachment than can be obtainable if Bones the muscular tissues had been hooked up solely to the scapular fossae. Their efferents normally unite with those from the tracheobronchial and brachiocephalic nodes to type the bronchomediastinal trunk.
Marius, 47 years: At 26�30 weeks, the gut shows contractions without common periodicity; from 30�33 weeks, repetitive groups of normal contractions have been seen in preterm neonates. It might divide close to its origin, producing a double aortic arch; the 2 branches quickly reunite and the oesophagus and trachea normally pass by way of the interval between them. C�D, the lower white arrows related to the midgut point out the relative movements and rotation of the midgut loop inside the umbilical coelom, and as it returns to the abdominal cavity.
Berek, 26 years: Peritoneal folds from the posterior caecal wall might create quite lots of peritoneal recesses across the caecum that have the potential to turn out to be websites of internal herniation; a superior and inferior ileocaecal recess, a retrocaecal recess and a paracolic recess have been described (Rivkind et al 1986). All areas of the gut develop from epithelial�mesenchymal inter actions which are dependent on the sequential expression of a range of primary and specific genes; on the regulation of the developmental clock, seen in all areas of growth; and on endogenous regulatory mecha nisms and native environmental influences (Lebenthal 1989). Part or all of the tendon may appear to cross the coracoid course of into the coracoacromial ligament.
