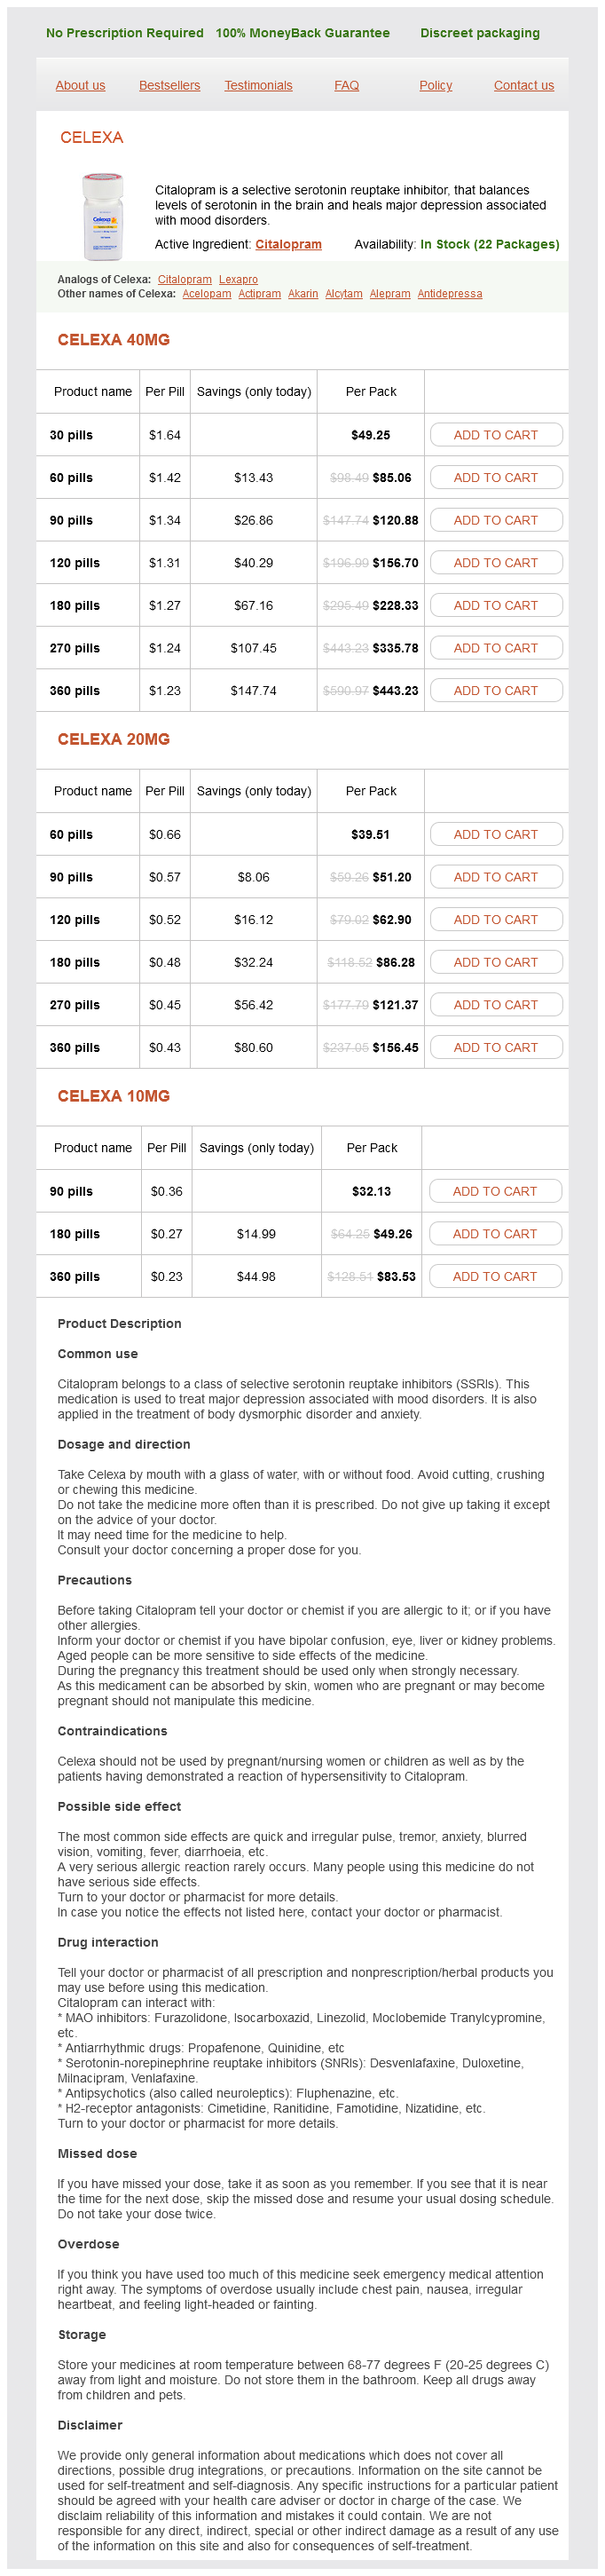
Celexa 40mg
- 30 pills - $49.25
- 60 pills - $85.06
- 90 pills - $120.88
- 120 pills - $156.70
- 180 pills - $228.33
- 270 pills - $335.78
- 360 pills - $443.23
Celexa 20mg
- 60 pills - $39.51
- 90 pills - $51.20
- 120 pills - $62.90
- 180 pills - $86.28
- 270 pills - $121.37
- 360 pills - $156.45
Celexa 10mg
- 90 pills - $32.13
- 180 pills - $49.26
- 360 pills - $83.53
Celexa dosages: 40 mg, 20 mg, 10 mg
Celexa packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 945
Only $0,25 per item
Description
Severe congenital is usually fatal treatment goals and objectives trusted celexa 20 mg, whereas individuals with the adult-onset sort tend to symptoms 6 weeks pregnant celexa 10 mg best be the least affected medicine lux discount celexa 10 mg with visa. Muscle weakness is often most extreme within the face medicine 1950 proven 10 mg celexa, the neck flexors, and the proximal limb muscular tissues. Severe neonatal respiratory disease and the presence of arthrogryposis multiplex congenita are associated with the severe congenital type, and result in death within the first year of life. In distinction, infants affected with the typical congenital kind appear mildly hypotonic, often coming to medical attention only when they fail to achieve motor milestones. This form tends to be slowly progressive, with greater weak spot in proximal than distal muscle tissue. Weakness of facial muscular tissues causes a dysmorphic appearance during which the face appears long and narrow and the palate is excessive and arched. The weak spot is slowly progressive, and affected individuals may be wheelchair confined as adults. The term nemaline myopathy refers to a group of genetically distinct disorders linked by common morphological features noticed on muscle histology. Muscle fibers show a quantity of small rodlike particles, thought to be derived from lateral enlargement of the Z disk. The small fibers are all kind I and contain rodlike bodies in a subsarcolemmal position. Mutations in certainly one of two genes are responsible for virtually all by which a genetic trigger has been established. Central Core Disease Central core illness is a definite genetic entity transmitted primarily by autosomal dominant inheritance, though recessive and sporadic instances occur. Weakness is bigger in proximal than in distal limb muscle tissue and is greater within the arms than in the legs. Because of the tight packing of myofibrils, the cores are poor in sarcoplasmic reticulum, glycogen, and mitochondria. Small research suggest that the beta-agonist salbutamol is useful with symptom management, though not curative. Most instances are sporadic; genetic transmission could also be autosomal dominant, autosomal recessive, or X-linked. The severity of weak point within the new child varies from mild hypotonia to respiratory insufficiency. Many had intrauterine hypotonia and show congenital hip dislocation, dysmorphic features, and joint contractures. Facial weakness, high-arched palate, ptosis, and disturbances of ocular motility may be present. When axial weak point is present in infancy, kyphoscoliosis typically develops throughout childhood. Weakness is most severe during the first 2 years after which turns into comparatively stable or progresses slowly. Physical remedy must be initiated instantly, not only to relieve existing contractures, but additionally to forestall new contractures from developing. The center of every fiber has a central core that seems clear when oxidative enzyme reactions are applied. Multi-Minicore Disease the presence of multiple small zones of sarcomeric disorganization with lack of oxidative exercise defines multiminicore illness. The traditional kind includes 75% of cases and presents congenitally or in early childhood. Affected infants are hypotonic and developmentally delayed, with scoliosis and respiratory involvement, which may lead to coronary heart failure. The antenatal kind with arthrogryposis multiplex congenita accounts for lower than 10% of instances. Other subtypes embody the reasonable kind, with hand involvement, and the ophthalmoplegic form. Affected newborns are hypotonic with a excessive arched palate and pectus excavatum, or other chest deformities. Axial weak spot is typical, as evidenced by scoliosis and neck flexor weak point, though the degree of spinal rigidity is variable. Respiratory insufficiency is the norm; nonetheless, most people are ambulatory regardless of their signs. Infants typically require respiratory assist, and maintenance of good pulmonary toilet is required. Pulmonary infections or progressive respiratory compromise due to scoliosis may be deadly. Myotubular (Centronuclear) Myopathy Several medical syndromes are included within the category of myotubular (centronuclear) myopathy. Transmission of some is by X-linked inheritance, others by autosomal dominant inheritance, and still others by autosomal recessive inheritance. The frequent histological feature on muscle biopsy is an apparent arrest in the morphogenesis of the muscle fiber at the myotube stage. The histological particulars are the identical as for other types of centronuclear myopathies, but the genetic trigger is distinct. Newborns with X-linked myotubular myopathy are hypotonic and require respiratory help. The face has a myopathic appearance, motor milestones are delayed, and most fail to stroll. Those with forms which may be more moderate obtain motor milestones more rapidly and about 40% require no ventilator support. In the mildest varieties, ventilatory assist is just required within the new child interval; delay of motor milestones is delicate, walking is achieved, and facial power is normal. Inheritance of milder forms of centronuclear myopathies may be both autosomal dominant or recessive. Some children with the illness have hypotonia at birth; others come to attention due to delayed motor development. Possible options include ophthalmoplegia, loss of facial expression, and continuing weak point of limb muscular tissues. Muscle biopsy is crucial for prognosis, and the histological features are identical to these of the acute kind. Muscular Dystrophies Congenital Dystrophinopathy Dystrophinopathies occasionally cause weakness at delivery. Immunofluorescence reactions for all three domains of dystrophin are essential for analysis. Transmission is by autosomal recessive inheritance with considerable genetic heterogeneity. Approximately half of affected people are abnormal at start because of some mixture of hypotonia, poor capability to suck, and respiratory distress. Limbgirdle weak spot is the rule, generalized weakness may be current, and about half of the individuals have facial weak point. The phenotypes related to merosin deficiency are generally extra extreme than the phenotypes with merosin current. The toddler has generalized limb weak spot, with proximal muscles affected earlier and extra severely than distal muscle tissue. Tendon reflexes may be present or absent and are sometimes difficult to check because of joint contractures. Contractures at birth might contain any joint, however torticollis and clubfoot are particularly common, and congenital dislocation of the hips is usually an associated function. Chronic hypoventilation leading to respiratory failure is the usual cause of demise. Features embrace a variation in fiber dimension with occasional central nucleation, extensive fibrosis, and proliferation of adipose tissue, fibers undergoing regeneration and degeneration, and thickening of the muscle spindle capsule. A mononuclear infiltrate surrounding muscle fibers is commonly current early in the course. The main feature is a disturbance of mobile migration to the cortex between the fourth and fifth gestational months, leading to polymicrogyria, lissencephaly, and heterotopia. Other abnormalities may embody fusion of the frontal lobes, hydrocephalus, periventricular cysts, optic nerve atrophy, hypoplasia of the pyramidal tracts, reduction in the number of anterior horn cells, and irritation of the leptomeninges.
Surelle (Wood Sorrel). Celexa.
- How does Wood Sorrel work?
- What is Wood Sorrel?
- Are there safety concerns?
- Liver problems, digestion problems, wound healing, scurvy, and gum swelling.
- Dosing considerations for Wood Sorrel.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96259
This mixture is rather more generally seen with a left than with a proper aortic arch symptoms panic attack order celexa 40 mg. This is in contrast to the case forming a vascular ring medicine evolution order celexa 40 mg overnight delivery, which is rather more widespread with a right aortic arch symptoms neck pain order celexa 10 mg without prescription. Minimal-intensity thick part exhibits abnormal branching pattern of the tracheobronchial tree treatment question celexa 20 mg. There is a protracted section narrowing of the distal trachea between the abnormal bronchus to the right higher and middle lobes and the tracheal bifurcation. The upper tracheal bifurcation is simply too high for normal carina, while the decrease bifurcation is simply too low. Some think about the upper bifurcation because the carina, the vertical narrowed half as the left major bronchus, and the bronchus to the proper decrease lobe as a "bridging bronchus. The left aortic arch with aberrant right subclavian artery was reported as the most common aortic arch anomaly in a large autopsy sequence, occurring in 0. Isolated right aortic arch is rare and has no vital associated morbidity or mortality. The left aortic arch with an aberrant right subclavian artery is an rare affiliation with congenital coronary heart illness. Double aortic arch is normally present in isolation but hardly ever may occur in association with other cardiac defects similar to transposition of the good arteries,43 interrupted aortic arch,44 or crossed department pulmonary arteries. Chromosome 22q11 deletion was associated in over 75% of sufferers with conotruncal malformation and subclavian arterial anomaly, whereas it was present in lower than 30% when there was no subclavian artery anomaly. Nonetheless, a double aortic arch may also be discovered incidentally in an asymptomatic child. Management includes surgical division of the buildings contributing to the vascular ring. A massive Kommerell diverticulum could be remodeled, as a end result of it could develop aneurysmal dilatation and continue to compress the trachea and esophagus even after the ring has been launched. There is a right-sided aortic arch with left-sided ductus arteriosus and an aberrant left subclavian that type the vascular ring. Sweeping cephalad, we see the proper and left aortic arches that encircle the trachea. Cardiac Embryology: A Help or a Hindrance in Understanding Congenital Heart Disease. Godfrey and Wayne Tworetzky Background Coarctation (from the Latin for "constriction") refers to a narrowing of the aorta, normally on the isthmus, and usually with a discrete "posterior shelf" of tissue causing the narrowing of the isthmic lumen. This is likely considered one of the more frequent forms of congenital coronary heart illness, constituting 5% of instances, with an incidence of 3�5 circumstances per 10,000 live births. Therefore, the presence of any obstacle to flow will simply trigger a redistribution of flow. Ironically, one of the earliest reviews of fetal analysis in the literature demonstrated a discrete shelf. They appropriately identified an arch abnormality in 18 of these 24 fetuses, though they acknowledged the issue in differentiating between coarctation and interrupted aortic arch (see the following text). Similar to the ventricular disproportion research, many of these research confirmed that relative dimension discrepancies between the left-sided construction. Of note, nevertheless, measurements of the aortic isthmus and transverse arch have been proven to be necessary in this diagnosis. In the mid-nineteenth century, there was debate as to whether or not coarctation was caused by an "inflammation" at some point in postnatal life, or if it was a congenital malformation. The acknowledged difficulty in diagnosing coarctation within the fetus is due partly to the regularly normal four-chamber view,5 as well as the shortage of clinically significant obstruction at the web site of the posterior shelf. The cause of the comparatively small left-sided structures in the fetus with coarctation has not been precisely defined. It has been suggested to be attributable to raised left ventricular end diastolic stress (due to the coarctation), decreasing right to left shunting at the foramen ovale, with an increased volume load on the best ventricle, and concomitant underfilling of the left ventricle. This has led to a quantity of research discovering that the diagnostic accuracy for coarctation is decreased as gestation advances,15,21,32,34 and though there could additionally be sure findings that are extra discriminatory at later gestation than at earlier, the sensitivity and specificity are lowered. The presence of lesions which are commonly related to coarctation ought to increase the index of suspicion and should increase diagnostic accuracy35 (Table 32. Bicuspid aortic valve is current in about 60% of sufferers with coarctation36 and might often be identified by fetal echocardiography. Note the "figure-of-3" look of the insertion of the aortic arch into the ductal arch. The asterisk denotes the posterior shelf, with move disturbance seen at that web site within the colour picture. This 416 Fetal Cardiology supply in a hospital with on-site pediatric cardiology help. If on postnatal examination, after ductus arteriosus closure, the infant is found to not have a coarctation-that is sweet news! If the child certainly has coarctation, then the glorious news is that the baby is in the right place to obtain acceptable therapy. Type B is the commonest, accounting for 52%�84% of cases, with 13%�47% kind A, and solely 1%�3% sort C. Our institutional medical follow is to counsel the mother that we suspect coarctation, and explain our restricted capacity to be sure of the prognosis. This counseling is a dialogue with the mom of the dangers and advantages of various supply plans. Note the hole between the ascending aorta within the circle and the ductal arch to the proper. Interruption of the aortic arch is present in 11%�23% of circumstances of truncus arteriosus,77�80 and conversely, truncus arteriosus represents 11% of instances of interrupted aortic arch. Therefore, the entire blood provide to the decrease body (and, relying on the site of interruption, to portions of the higher body) should undergo the primary pulmonary artery-ductus arteriosus. Imaging of the entire aortic arch is recommended by some,91,92 but not all,ninety three skilled societies. It is our institutional practice to examine the aortic arch in each sagittal (the "candy-cane" view) and axial planes, with each two-dimensional and shade Doppler imaging, in all fetuses every time possible. Pedra Introduction Diseases of the endocardium, myocardium, and pericardium could current with very variable varieties, etiology, and natural historical past. They may outcome from systemic abnormalities, maternal ailments, or some other particular conditions similar to twin-to-twin transfusion syndrome or anemia. In roughly 50% of patients, the mitral and aortic valves are involved, typically leading to marked anatomic deformity and either valvar regurgitation or stenosis. Runs of supraventricular tachycardia and hydrops had been controlled with oral digoxin. Of observe, his earlier sibling had offered with comparable findings and died of uncontrolled arrhythmia after a Blalock-Taussig shunt. Resultant fibroelastotic thickening could also be focal or diffuse, with its severity related to the diploma and time of publicity to the underlying illness. There are multiple situations associated with its etiology: maternal viral infections, hypoxia, vascular and metabolic illnesses, and chromosomal abnormalities. Familial recurrence is well-documented in some case collection,17,18 suggesting a genetic foundation for the pathology. Autosomal dominant transmission has been reported, but there are additionally stories of X-linked inheritance and gene mutations. This disorder, in its primary or secondary kind, may be the cause of congestive coronary heart failure, fetal hydrops, and demise. There was no pulmonary antegrade move (functional pulmonary atresia) because of extreme systolic dysfunc tion. They are defined as dilated and hypocontractile ventricles with ventricular enlargement higher than 2 z-scores for the particular gestational age. Diastolic dysfunction is regularly related, and in accordance with the degree of dysfunction, hydrops could happen. Systolic perform could be assessed by M-mode, two-dimensional echo and Doppler indexes. Diastolic Doppler tracings throughout the atrioventricular valves and within the inferior vena cava, ductus venosus, and umbilical vein are prognostic and will precede fetal hydrops and demise2 (Video 33.
Specifications/Details
In most cases medicine you can take while pregnant 10 mg celexa order free shipping, the spleen is either absent (asplenia) medicine 91360 20 mg celexa sale, or multiple spleens are present on the right or on the left (polysplenia) symptoms e coli celexa 20 mg generic. Generally treatment kitty colds 20 mg celexa generic with mastercard, asplenia occurs with proper bronchopulmonary and atrial isomerism, whereas polysplenia happens with left bronchopulmonary and atrial isomerism. However, polysplenia can happen with right isomerism, and asplenia with left isomerism. There is evidence to suggest that heterotaxy may have a genetic etiology,thirteen,27,forty five,49�53 though genetic anomalies were uncommon diagnoses in our institutional experience46 with heterotaxy patients. Moreover, left isomerism may be found incidentally with none clinical evidence of a cardiac defect. In proper isomerism greater than left isomerism, the atrioventricular septal defect is often characterised by an unbalanced commitment of the atrioventricular Table 17. The pulmonary artery is way smaller than the aorta (A) because of severe pulmonary stenosis. The atrium is a typical chamber with a small strand of remnant atrial septum seen as a dot (central dot sign). In proper isomerism, cardiac lesions are usually complicated and often have an result on the center at a number of ranges. In left isomerism, the pulmonary veins from every lung are probably to separately enter the posterior wall of the ipsilateral atrium. In each situations, the hepatic veins could have separate openings in the floor of the atrium or atria, somewhat than forming a confluence. In a four-chamber view, this strand is seen as a dot within the center of the common atrium (the "central dot signal"), which is pathognomonic for proper isomerism. In left isomerism, the atrial septum is usually better shaped or well developed in two-thirds of cases. The atrioventricular connection is more usually univentricular in proper isomerism (to a dominant chamber of right ventricular morphology) and biventricular in left isomerism. The morphology of the ventricular chambers in univentricular atrioventricular connection could additionally be tough to outline by trabeculations. It is, nonetheless, useful to determine ventricular morphology indirectly by assessing the spatial relationship between the dominant and rudimentary ventricle, respectively. When only one ventricle is recognized, the ventricular morphology is tough to define and referred to as indeterminate. Pulmonary stenosis or atresia is current in approximately 80% of the best isomerism circumstances. In contrast, in as a lot as 70% of instances of left isomerism, the ventriculo-arterial connection is concordant and pulmonary stenosis or atresia far much less widespread (approximately 30% of cases), while left-sided obstructive lesions are present in about 20%�30%. The threat of coronary heart block in left isomerism is much higher in fetal sequence than in postnatal series. When biliary atresia is current, pulmonary arteriovenous malformations could develop later in life. Polysplenia may be related to additional hepatic portosystemic shunt82 and agenesis or hypoplasia of the portal vein. In right isomerism, a part of the stomach may be seen in the thorax,sixteen normally due to a hiatal hernia. Four-chamber view shows the shut proximity of the orifices of the pulmonary veins (asterisks). The department pulmonary arteries are symmetric in preserving with right atrial isomerism. The letter "V" indicates forward move by way of the pulmonary artery peaking throughout ventricular systole. The letter "A" point out reversed move by way of the pulmonary vein during atrial systole. Hydrops has developed secondary to severe bradycardia due to full coronary heart block. Left atrial isomerism with full heart block is usually seen in association ventricular noncompaction. When pulmonary outflow tract obstruction is critical, administration of prostaglandin is critical immediately after supply to preserve patency of the ductus arteriosus. Right isomerism with obstructive whole anomalous pulmonary venous connection is associated with a very poor prognosis because of Abnormal visceral and atrial situs and congenital coronary heart disease the additional lung pathology. Risk factors for mortality other than proper isomerism included whole anomalous pulmonary venous connection with obstruction, underdeveloped pulmonary arterial mattress, functionally single ventricle, and the necessity for early surgical intervention. In addition, complicated anatomy of the systemic in addition to pulmonary venous connections, presence of bilateral superior venae cavae, uncommon spatial relationship of the ventricles, and complex outflow tract pathology are additionally necessary in figuring out the complexity of postnatal surgical restore and long-term need for reintervention. Postnatal outcomes were additionally related to the extracardiac anomalies and their resultant complications, including biliary atresia and intestinal obstruction. There is double-outlet proper ventricle with malposed great vessels with an anterior aorta. In the fetus, the true prevalence is, nonetheless, not identified, since some types, particularly when related to heart block and fetal hydrops, would end as fetal demise, and another more delicate forms of cardiac malposition or isolated situs inversus may be missed even in a toddler. The early prenatal detection of an abnormality of this group has a big impact on counseling the pregnant lady, particularly as a end result of small particulars can radically change the prognosis. There are difficulties in reaching a last fetal prognosis, because the examiner can rely solely on ultrasound, where there are limited prospects for the exact differentiation of structures. Furthermore, some fundamental knowledge is required in order to perceive some definitions in addition to the classification of defects. It is tried, quite, to provide the reader with primary information for a practical approach when abnormal circumstances are suspected. Because this situation is extraordinarily rare, it might be beneficial that earlier than making this prognosis, the examiner checks the fetal place and the transducer orientation. However, there are other situations the place the mirror-image arrangement is partial: both solely affecting the center, as in dextrocardia (with situs solitus); or affecting the visceral organs, as in situs inversus with levocardia. The coronary heart position and axis are important features to check while analyzing the heart. Compared to its regular position in the left chest with a normal base-apex axis of 45� to the left aspect, cardiac malpositions are divided into dextrocardia, levocardia, mesocardia, and ectopia cordis. As already acknowledged, dextrocardia is present when the center is in the proper hemithorax with the axis pointing to the right. Developmental elements and normal body configuration In contrast to other embryological organs, the thoracic and abdominal buildings develop asymmetrically. In Chapter 10, on fetal cardiac anatomy, the focus was on the segmental evaluation of the upper stomach and the guts, showing that beneath regular situations, in situs solitus the stomach and descending aorta are on the left and the liver and the inferior vena cava on the proper. The normal sonoanatomy of the higher abdomen with situs solitus (left) and the heart in levocardia (right). The fetus is in vertex position and in the upper abdomen a mirror-image rotation is discovered with the abdomen (St. Many kids having mesocardia are incorrectly grouped within the dextrocardia group, since on x-ray, the guts appears more on the best facet. Similarly, levoposition (displacement to the left) is seen when the center is shifted into the left thoracic cavity with the axis still pointing to the left, as usually present in right-sided diaphragmatic hernia or some other right-sided thoracic lesions. The descending aorta is on the left, the guts on the right, right and left atria are seen, however the anatomy of the ventricles reveals an atrioventricular discordance characteristic for the congenital corrected transposition, which regularly is related to a dextrocardia. In these situations, the association is identified as situs ambiguus (indeterminate or uncertain situs) and is essentially the most complex form of visceral and atrial arrangement. This group of defects has many synonyms, similar to heterotaxy syndromes, cardiosplenic syndromes, or asplenia-polysplenia syndromes or isomerisms, and the circumstances are regularly associated with advanced cardiac defects. Because the spleen develops as a left-sided organ, it was in the past an indication for classification, asplenia being the earlier name of right isomerism and polysplenia of left isomerism. Knowing that the center develops in accordance with well-defined cardiac segments, Van Praagh5 proposed a classification based on the anatomy and connections of these segments, generally known as the segmental method. Therefore, ailments with isomerism are now divided into right atrial and left atrial isomerism. The identification of these anomalies and their differentiation could also be simpler for the pathologist during necropsy. In the fetus the diagnostic prospects are decreased, and the reliable prognosis or differentiation between proper or left isomerism can be very difficult to be achieved prenatally. The diagnostic method using ultrasound is based on the method proposed by Huhta et al. The central point of diagnosis is the anatomy of the atria defined by their form and their appendages. The left atrial appendage is finger-like and has a slender base, whereas the proper atrial appendage is pyramidal in form and its base is somewhat broad.
Syndromes
- Severe abdominal pain
- Difficulty breathing
- Blood clot in an artery in the lung
- Skin ulcers
- Eye swelling (conjunctivitis)
- Your doctor or nurse will tell you when to arrive at the hospital.
Related Products
Additional information:
The application of instruments to higher grade the degree of cardiovascular derangement will help in figuring out the efficacy of current and to-be-developed therapy methods medicine park oklahoma celexa 10 mg purchase free shipping. Godfrey medicine doctor generic 40 mg celexa amex, and Wayne Tworetzky Introduction Advances in fetal echocardiography have facilitated our understanding of the natural history of cardiac disease in utero severe withdrawal symptoms celexa 20 mg proven. The objective is to alter the pure historical past of fetuses with extreme anomalies that result in 94 medications that can cause glaucoma celexa 10 mg cheap fast delivery important lifelong morbidity and mortality, i. Finally, the emerging chance of maternal hyperoxygenation as a form of fetal therapy is mentioned. The maternal aspects of fetal therapy, that are important to contemplate, are beyond the scope of this chapter. In conjunction with technical modifications to the procedure, greater success was able to be achieved. The presence of four or more of those options had 100 percent sensitivity and 38% positive predictive worth for figuring out patients with a biventricular outcome. Once the epidural is placed, the fetal place is determined and, if necessary, the fetus is manipulated into the optimal position. After cannula elimination, the fetus is monitored for issues within the working room. The commonest problems, which happen in up to 40% of fetuses, are bradycardia, ventricular dysfunction, and hemopericardium. Four of the deaths occurred inside 24 hours of the procedure, and two of the deaths have been due to untimely rupture of membranes leading to delivery of nonviable fetuses. Laparotomy is reserved only for select circumstances by which optimum fetal positioning is unable to be achieved with external model or imaging is restricted. After stylet elimination and evidence of blood return confirming intracardiac cannula position, a zero. The cannula has an unobstructed pathway from the maternal stomach to the left ventricular apex. Once the apex is punctured, the guidewire and coronary angioplasty catheter are positioned for balloon dilation across the aortic valve. The patient depicted within the first row (images [a] and [b]) had a technically unsuccessful fetal aortic valvuloplasty and was managed with staged univentricular palliation after delivery, whereas the affected person within the second row (images [c] and [d]) had a technically profitable process and a biventricular end result. However, biventricular patients had substantial cardiac morbidity: nearly all required postnatal cardiac catheterization and/or surgery, with valve replacements generally carried out. This could also be achieved by perforating and dilating the atretic pulmonary valve in utero (fetal pulmonary valvuloplasty) to facilitate right heart progress throughout the remainder of gestation. On the opposite end of the spectrum are fetuses with only mildly hypoplastic right ventricles in whom postnatal pulmonary valvuloplasty alone is commonly enough to achieve a biventricular circulation. These patients are thought of to have an intermediate circulation, and whether or not 610 Fetal Cardiology a biventricular circulation is in the end achieved is very dependent on postnatal management technique. The degree of proper ventricular hypoplasia correlates with the z-score of the tricuspid valve, and just like postnatal studies, the fetal tricuspid valve z-score may predict eventual postnatal end result. The atretic valve is perforated with the stylet or a 22-gauge Chiba needle, and a zero. Technically successful interventions are characterised by colour Doppler imaging demonstrating antegrade move across the pulmonary valve and pulmonary regurgitation. Complications corresponding to bradycardia, ventricular dysfunction, and hemopericardium may happen, as detailed previously. This results in left atrial and pulmonary venous hypertension with downstream adverse effects on the pulmonary Fetal interventions for congenital heart illness vasculature and developing lungs. Technical elements of the process An 18- or 19-gauge cannula is inserted through either the proper or left atrium, and the stylet or a 22-gauge Chiba needle is used to puncture the atrial septum. A balloon and/or balloon-mounted stent are inflated across the septum, with the objective of creating an atrial communication three mm (Video 45. Bradycardia and ventricular dysfunction are uncommon with atrial access; nonetheless, hemopericardium can occur after the cannula is removed. The administration of supplemental oxygen to pregnant moms was proven to raise the fetal pO2 in the 1950s53 and was initially proposed as a remedy for intrauterine development restriction. Furthermore, the optimum dose and period of maternal hyperoxygenation, in addition to the potential side effects of chronic oxygen remedy to each the mom and the fetus, have yet to be defined. Our ability to explore therapies that will benefit the fetal heart is dependent upon our understanding of the in utero natural historical past and risk factors for essentially the most severe types of disease. It is an thrilling time in our subject; nonetheless, all strategies must be pursued with the well being and safety of the mom paramount. Detection prompts further investigations, corresponding to umbilical artery Doppler research, which has been proven to reduce stillbirth and increase preterm delivery without rising neonatal mortality. A current systematic evaluate and meta-analysis discovered that a genomic chromosomal microarray provides a 4% incremental yield over typical karyotyping. Umbilical artery Doppler discriminated higher than gestational age between two teams with totally different timing, pure historical past, and fee of antagonistic end result. Screening strategies By combining first- or second-trimester uterine Doppler findings with baseline maternal characteristics, detection of early onset progress restriction (needing supply at <34 weeks) nears acceptable ranges. Clinical management an important prognostic think about progress restriction is gestational age at delivery. However, development to extreme fetal deterioration and even fetal death can occur rapidly. This may be explained by reduced tolerance to hypoxia of the term as compared with the preterm fetus and the more widespread presence of uterine contractions. Concerning surveillance, a relevant notion is that the status "low risk" versus "high risk," and consequently, the beneficial administration, can change after an initial analysis, and for these reasons, serial measurements of the biometrics and Doppler are recommended. There is evidence from one randomized trial36 that in comparison with monitoring each 2 weeks, twice a week monitoring ends in more inductions with none enchancment in the perinatal outcomes. One could speculate that the degree of the extension is what accounts for this finding. Normal (b) and irregular (high-diastolic velocities and decreased pulsatility index) (c) waveforms. Normal (b) and irregular (increased impedance to flow with early diastolic notching) (c) waveforms. The finest proof relating to this issue comes from two randomized managed trials. They found negligible variations in perinatal and neonatal outcomes between induction of labor and expectant monitoring. Moreover, follow-up at 2 years of age showed no differences when it comes to neurodevelopment and neurobehavior between each strategies. As discussed, a mixture of biometrical and Doppler parameters allows profiling of a subgroup of fetuses that concentrates most cases of adverse outcomes. The incidence of neonatal composite adverse outcomes was lower after selective induction (9% versus 22%; p < 0. Timing of supply No therapy has been demonstrated to be of profit in progress restriction. The evaluation of venous pulsations4�6 has turn into part of the fetal hemodynamic evaluation. With purpose, we believe that the venous velocity sample is a more instantaneous indicator for hemodynamic efficiency than is the umbilical artery velocity pattern. The implication is an increased diploma of recirculation of deoxygenated blood throughout the fetal body near term. Deoxygenated blood within the abdominal portion of the inferior vena cava is predominantly directed to the proper atrium. This implies that 90% or more recycles inside the fetal physique, leading to lower oxygen saturation and extra demanding oxygen extraction in the fetal tissues. This contributes to keeping up the perfusion pressure each for the ductus venosus and the liver, but also to an additional lowered oxygen content material of the central circulation. An lively distension of the inlet of the ductus venosus (mediated by nitroxide and prostaglandins) enhances this redistribution, significantly throughout hypoxemia. The fetus approaching time period has more developed endocrine and neural regulation mechanisms to respond to hypovolemia and hypoxemia by an initial increase in blood pressure and peripheral resistance. A wave consists of three components- pressure wave, diameter wave, and flow wave-that collectively obey the necessities of preservation of energy in accordance with the Navier-Stoke equations. One such issue is the direction of the strain wave in contrast with that of the blood velocity. However, the most important determinant for wave propagation is described with the phenomenon of wave reflection. The inferior vena cava, ductus venosus, and umbilical vein type one clinically important transmission line for this wave.
Usage: q.3h.
Survival following surgical procedure has improved over time and is negatively affected by associated extracardiac abnormalities/ genetic syndromes medications 73 20 mg celexa cheap overnight delivery. The fee of termination of being pregnant is high if the prognosis is made before 24 weeks of gestation symptoms at 4 weeks pregnant 10 mg celexa generic with visa. Identification of fetal laterality and visceral situs must be part of routine fetal anomaly scans treatment resistant depression 40 mg celexa fast delivery. World Congress of Pediatric Cardiology and Cardiac Surgery; May 11�15 treatment nail fungus buy 10 mg celexa overnight delivery, 1997; Honolulu, Hawaii. Ventricular outflow tract anomalies can be categorized into two categories: (1) as isolated lesions in an otherwise structurally regular coronary heart, and (2) as extra advanced anomalies that happen in association with irregular ventriculo-arterial connections and/or irregular great arterial relationship. The latter group, often recognized as conotruncal or truncoconal anomalies, consists of easy and corrected transposition of the nice arteries, double-outlet ventricle, and common arterial trunk. Interruption of the aortic arch and tetralogy of Fallot are additionally considered conotruncal anomalies and are mentioned elsewhere in this guide. The proper ventricular outflow tract is anterior and then angles leftward of the left ventricular outflow tract. The major distinction is the existence of the crista supraventricularis in the proper ventricle, which is a muscular crest that separates the pulmonary and tricuspid valves within the regular proper ventricle. Only a small a half of the crista, the outlet or infundibular septum, is really a septal structure. The outlet septum is cradled between the two limbs of the trabecula septomarginalis. Once the four-chamber view is obtained, the transducer is moved radially across the maternal abdomen, maintaining the four-chamber aircraft in view, until the ventricular septum is aligned perpendicular to the sonographic beam axis. From this explicit transducer position, the left ventricular outflow tract view may be obtained just by rotating the transducer by way of 40��50� clockwise or counterclockwise towards the cardiac apex. The transducer is then moved barely upward till the proper ventricular outflow tract view is visualized. The basal ventricular short-axis view is the optimum airplane for evaluating the morphology of the infundibular or outlet septum and the best ventricular outflow tract. Opened proper (a) and left (b) ventricles, and the base of the ventricles seen from above (c) and below (d). Notice the deeply wedged place of the aortic valve between the tricuspid and mitral valves in (c). The transducer is moved upward or downward along the fetal thorax with some cranial or caudal tilt until the aortic valve is situated within the middle of the cardiovascular section that visualizes the right atrium, proper ventricle, major pulmonary artery, and proper pulmonary artery. This view could be obtained from the coronal view by displacing the transducer to the left anterior or proper posterior part of the chest wall. Three-dimensional (3D) and four-dimensional (4D) ultrasound enhances two-dimensional (2D) diagnostic approaches to fetal outflow tract abnormalities. From the volume dataset, the photographs described may be reconstructed for ventricular outflow tract evaluation. Doppler interrogation is a vital adjunct to 2D imaging and demonstrates the course and velocity of the blood circulate through the outflow tracts. It additionally demonstrates the move course and velocity through the ductus arteriosus, which is necessary for recognition of a attainable "duct-dependent" pulmonary or systemic circulation after delivery. The transducer is moved radially across the maternal abdomen (arrow 1) until the ventricular septum is aligned perpendicular to the sonographic beam axis. Then the left ventricular outflow tract is obtained by rotating the transducer towards the cardiac apex (arrow 2). By sliding the transducer upward along the fetal thorax, the best ventricular outflow tract view is obtained. When it occurs with discordant atrioventricular connection-that is, the best atrium connects to the left ventricle and the left atrium to the best ventricle-it known as congenitally corrected transposition. Most instances occur with situs solitus, levocardia, and usually positioned ventricles. In this classic setting, the aorta is anterior to and to the proper of the pulmonary artery. Rarely, the aorta may be situated posterior to or to the left of the pulmonary artery. This semicoronal view is equivalent to the angiographic right anterior indirect view. The long-axis cuts of the three vessels are aligned from the left anterior to the best posterior aspect of the fetal thorax. With a greater diploma of overriding of the aortic or pulmonary valve, transposition merges into doubleoutlet left or proper ventricle with malposed nice arteries. Obstruction because of fibrous ridge, fibromuscular tunnel, or accent mitral valve tissue can exist with an intact ventricular septum as nicely as in association with a ventricular septal defect. With a major left ventricular outflow tract obstruction, the primary pulmonary artery is smaller than the ascending aorta. It may be because of anterior malalignment of the outlet septum as described and is usually dynamic. The three vessels are arranged in a triangular style with the right superior vena cava (S), proper anterior aorta (A), and left posterior pulmonary artery (P). There is discrepancy of the sizes of the right and left ventricles, with a smaller however apex-forming right ventricle within the four-chamber view. Systemic arterial oxygenation and thus the diploma of cyanosis depends on the quantity of oxygenated blood that is able to move across an intracardiac (atrial septal defect, ventricular septal defect) and/or extracardiac (ductus arteriosus) communication to the proper coronary heart and aorta. Delay in diagnosis and treatment might result in vital morbidity and mortality. Bidirectional ductal circulate has been related to an elevated danger of persistent postnatal pulmonary arterial hypertension. The presence of a ventricular septal defect together with a left ventricular outflow tract obstruction or arch obstruction requires change in surgical administration, so these lesions are appropriately addressed. This implies that after birth, the best ventricle will function as the systemic ventricle and pump oxygenated blood from the left atrium into the aorta, while the left ventricle will pump deoxygenated blood from the systemic veins into the pulmonary vasculature. In situs solitus, the left-sided ventricle is the morphologically right ventricle that can be recognized by the presence of a moderator band and more apical attachment of its atrioventricular valve to the ventricular septum. The pulmonary valve is in fibrous continuity with the mitral valve in basic circumstances. Most instances of corrected transposition may have further cardiac lesions, with only 10% occurring as an isolated anomaly. It mostly occurs with situs solitus and concordant atrioventricular connections. In situs solitus, the aorta is usually situated to the right of the pulmonary artery, and the nice vessels are most likely to have a side-by-side relationship; however, any great arterial relationship could be found. As the outlet septum is deficient with this defect, a typical right ventricular outflow tract leads to the good arteries. An atrioventricular septal defect is another potential form of a noncommitted intracardiac communication. When the defect is doubly dedicated or non committed, the physiology is determined by the intracardiac streaming of blood flow. It was once thought of that a bilaterally deficient infundibulum is the hallmark of doubleoutlet left ventricle. A subsequent research, nevertheless, verified that any infundibular morphology is found in double-outlet left ventricle and that a subpulmonary or subaortic infundibulum is more frequent than bilaterally poor infundibulum. Left ventricular outflow tract obstruction is another widespread affiliation, occurring in 40%� 50% of cases. The nature of the obstruction may be a fibrous ridge, fibromuscular tunnel, aneurysm of the membranous septum, accessory mitral valve tissue, or stenosis of the pulmonary valve. The most typical pathology is valve dysplasia with a variable diploma of regurgitation. Bradycardia with complete atrioventricular block has been reported to happen in roughly up to 20% of fetuses with congenitally corrected transposition before delivery. Without any associated lesions, surgical repair is in all probability not needed, and patients with this sort of pathology could solely be diagnosed incidentally. Anatomic repair seems to have a better short-term mortality in comparability with physiologic restore. Biventricular anatomic restore with arterial swap (double switch) process is associated with 91% survival quick term, whereas restore with Rastelli-type of repair is associated with 60% survival due to high incidence of residual left ventricle outflow obstruction. The ventricular septal defect is classified based on its location relative to the semilunar valves.
Tags: buy celexa 20 mg cheap, 20 mg celexa buy free shipping, celexa 10 mg generic on-line, celexa 40 mg discount amex, celexa 10 mg visa, celexa 20 mg cheap fast delivery, 20 mg celexa order with amex, buy discount celexa 10 mg online, generic celexa 10 mg line, buy celexa 10 mg on line, order 40 mg celexa with amex, buy cheap celexa 10 mg on-line, order 40 mg celexa, 40 mg celexa sale, celexa 10 mg discount on line, buy cheap celexa 20 mg line
8 of 10
Votes: 50 votes
Total customer reviews: 50
Customer Reviews
Khabir, 62 years: The use of a quantity of polymerase chain response masking 18 exons on the deletion hotspots is able to detect 90%� 98% of deletions.
Inog, 60 years: Certain views may be restricted by the fastened linear axis of the ultrasound probe during the transvaginal examination, and fetal position typically dictates the views that may be imaged.
