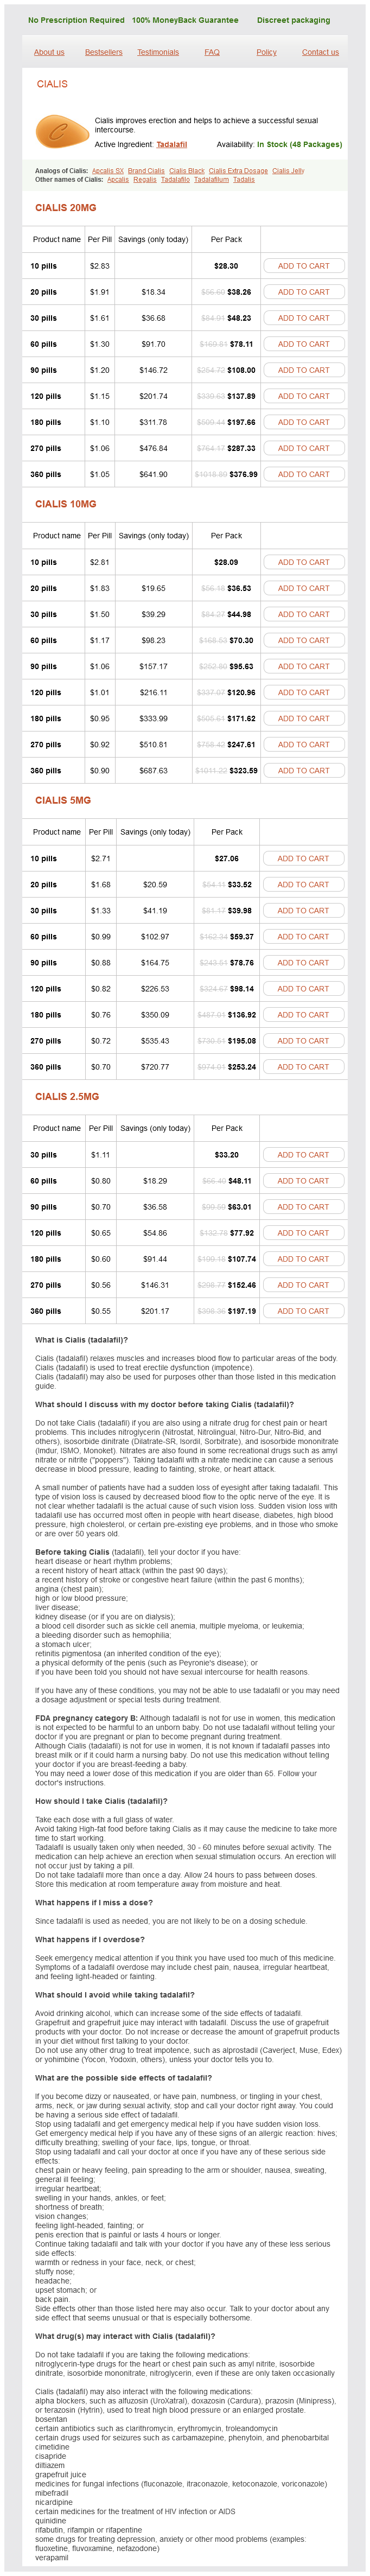
Cialis 20mg
- 10 pills - $28.30
- 20 pills - $38.26
- 30 pills - $48.23
- 60 pills - $78.11
- 90 pills - $108.00
- 120 pills - $137.89
- 180 pills - $197.66
- 270 pills - $287.33
- 360 pills - $376.99
Cialis 10mg
- 10 pills - $28.09
- 20 pills - $36.53
- 30 pills - $44.98
- 60 pills - $70.30
- 90 pills - $95.63
- 120 pills - $120.96
- 180 pills - $171.62
- 270 pills - $247.61
- 360 pills - $323.59
Cialis 5mg
- 10 pills - $27.06
- 20 pills - $33.52
- 30 pills - $39.98
- 60 pills - $59.37
- 90 pills - $78.76
- 120 pills - $98.14
- 180 pills - $136.92
- 270 pills - $195.08
- 360 pills - $253.24
Cialis 2.5mg
- 30 pills - $33.20
- 60 pills - $48.11
- 90 pills - $63.01
- 120 pills - $77.92
- 180 pills - $107.74
- 270 pills - $152.46
- 360 pills - $197.19
Cialis dosages: 20 mg, 10 mg, 5 mg, 2.5 mg
Cialis packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 604
Only $0,58 per item
Description
In the nerve fiber layer erectile dysfunction age 60 cialis 10 mg generic visa, blood is drained directly into the retinal veins erectile dysfunction blood pressure medication cialis 10 mg buy mastercard, which then be a part of to form the central retinal vein impotence australia 10 mg cialis safe. In the prelaminar erectile dysfunction 4xorigional cheap cialis 5 mg overnight delivery, laminar, and retrolaminar regions, venous drainage also happens through the central retinal vein or axial tributaries to the central retinal vein. Histologically, early glaucomatous cupping consists of loss of axons, blood vessels, and glial cells. The loss of tissue seems to start on the level of the lamina cribrosa and is related to transforming of the load-bearing connective tissues. In many cases, though not all the time, structural optic nerve adjustments may precede detectable practical loss. Glaucomatous cupping in infants and children is accompanied by an growth of the whole scleral ring, which can clarify why cupping appears to occur earlier in kids and why reversibility of cupping is extra outstanding with successful remedy in these cases. Cupping may be reversed in adults as nicely, but such reversal is much less frequent and extra refined. A, Glaucomatous optic nerve (anterior optic nerve head and transverse view, proper eye). B, Clinical view of glaucomatous optic nerve head demonstrating intensive loss of the neuroretinal rim. Decreased optic nerve head perfusion and/or disturbance of vascular autoregulation may contribute to optic nerve damage in glaucoma, both immediately or as a consequence of biomechanical effects. Glutamate excitotoxicity, autoimmunity, and neurotrophic deprivation have all been instructed as causes of secondary damage. Current thinking acknowledges that glaucoma is a heterogeneous family of problems mediated, most likely, by many elements. The slit beam, quite than diffuse illumination, is helpful for figuring out refined adjustments within the contour of the nerve head. This system offers excessive magnification, wonderful illumination, and a stereoscopic view of the optic nerve head. This also allows for quantitative measurement of the diameter of the optic nerve head, by adjusting the height of the slit beam. The disc is considered through the handheld lens until the height of the slit is the same as the vertical diameter of the disc. However, this instrument might not provide enough stereoscopic element to detect delicate modifications in optic nerve head topography. The oblique ophthalmoscope can be used for examination of the optic nerve head in young youngsters and in uncooperative sufferers. With the oblique ophthalmoscope, cupping of the optic nerve can be detected, but, generally, optic nerve cupping and pallor seem much less pronounced than with slit-lamp strategies, and the magnification is usually inadequate for detecting delicate or localized details necessary within the analysis of glaucoma. The optic nerve head is usually round or barely oval in form and contains a central cup. The tissue between the cup and the disc margin is recognized as the neural rim or neuroretinal rim. In people with out glaucoma, the rim has a comparatively uniform width and a shade that ranges from orange to pink. The measurement of the physiologic cup is developmentally decided and is expounded to the size of the disc. For a given variety of nerve fibers, the larger the overall disc area, the bigger the cup. Nonglaucomatous black individuals, on average, have larger disc areas and bigger cup�disc ratios than do whites, although a substantial overlap exists. Differentiating physiologic or normal cupping from acquired glaucomatous cupping of the optic nerve head can be troublesome. The early adjustments of glaucomatous optic neuropathy are very refined and include generalized enlargement of the cup, focal rim thinning, superficial disc hemorrhage, nerve fiber layer loss, asymmetry of cupping, and beta (b) zone of peripapillary atrophy (Table 3-2). Diffuse neuroretinal rim thinning related to generalized enlargement of the cup may be an early signal of glaucomatous injury. However, diffuse loss may be difficult to appreciate until previous goal documentation of the optic nerve head (eg, photographs) is out there. Note the generalized enlargement of the cup in the right eye (A) as compared with the left eye (B). An indirect insertion of the optic nerve into the globe of people with excessive myopia may also trigger a tilted appearance to the optic nerve head. Examination of other family members may clarify whether a big cup is inherited or acquired. Localized lack of the neuroretinal rim most typically occurs on the inferior and superior temporal poles of the optic nerve in early glaucomatous optic neuropathy. In regular eyes, the Inferior neuroretinal rim is usually the thickest, adopted by the Superior rim, the Nasal rim, and eventually the Temporal rim. Deep localized notching, the place the lamina cribrosa is seen at the disc margin, is sometimes termed an acquired optic disc pit. Even in the normal eye, laminar trabeculations or pores could also be seen as grayish dots in the base of the physiologic cup. Nasalization of the central retinal artery and central retinal vein is often seen because the cup enlarges. One-third of glaucoma sufferers at some time in the course of the course of their disease might develop hemorrhages, which generally clear over a quantity of weeks to months. Some glaucoma sufferers have repeated episodes of optic disc hemorrhage; others have none. Optic nerve head hemorrhage is a vital prognostic signal for the event or development of visible field loss, and any patient with a disc hemorrhage requires detailed analysis and follow-up. Disc hemorrhages may also be brought on by posterior vitreous detachments, diabetes mellitus, department retinal vein occlusions, and anticoagulation remedy. Axons within the nerve fiber layer of the traditional eye could finest be visualized with red-free illumination. As the nerve fibers lengthen from the peripheral retina to converge at the optic nerve head, they seem as fine striations created by the bundles of axons. In the wholesome eye, the brightness and striations of the nerve fiber layer are more easily visible superiorly and inferiorly. With progressive glaucomatous optic neuropathy, the nerve fiber layer thins and becomes less visible. Early wedge-shaped defects are sometimes visible only at a distance from the optic disc margin. Diffuse nerve fiber loss is more widespread in glaucoma than is focal loss but in addition more difficult to observe. The nerve fiber layer may be visualized clearly in high-contrast blackand-white images, and experienced observers can acknowledge even early illness if good-quality photographs can be found. The combination of red-free filter, wide slit beam, and posterior pole lens on the slit lamp affords the most effective view. Beta zone is more common and in depth in eyes with glaucoma than in wholesome eyes. Other, much less particular, indicators of glaucomatous harm include nasal displacement of the vessels, narrowing of peripapillary retinal vessels, and baring of the circumlinear vessels. It is essential to recognize that glaucomatous optic nerve damage is just one kind of pathologic change of the optic nerve; other etiologies of optic nerve changes must be thought-about in the differential diagnosis. Certain circumstances may cause obvious cupping of the optic nerve that could be confounded with glaucoma, corresponding to congenital pits of the optic nerve head, coloboma, morning glory syndrome, arteritic ischemic neuropathy or compressive optic neuropathies. With uncommon exceptions, glaucoma results in elevated cupping and pallor throughout the cup, however not pallor of the remaining rim tissue. The ophthalmologist should also consider drusen or coloboma as attainable causes of optic nerve change and visual subject loss. Finally, the myopic optic disc represents a challenge when the ophthalmologist is making an attempt to assess possible glaucomatous injury. The size, tilting, and related structural modifications typically preclude the power to definitively determine the presence of glaucomatous injury. Therefore, glaucoma diagnosis regularly requires longitudinal monitoring and detection of progressive injury over time.
Argousier (Sea Buckthorn). Cialis.
- What is Sea Buckthorn?
- Dosing considerations for Sea Buckthorn.
- How does Sea Buckthorn work?
- Are there any interactions with medications?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96747
In association is the elevated danger of arterial ischemic strokes and cerebral venous thrombosis erectile dysfunction drugs boots cialis 2.5 mg discount without prescription. Population studies have proven an increased danger of postpartum stroke in caesarean part deliveries impotence lipitor buy cialis 5 mg without a prescription. Vasculitis has been instructed as a potential etiology for stroke as a result of erectile dysfunction age 75 discount cialis 10 mg with visa the function of tissue transglutaminase in sustaining endothelial integrity erectile dysfunction pills in store purchase cialis 10 mg mastercard. Importantly, mosaicism within the mitochondrial lineage signifies that not all tissues are affected, which leads to a broad vary of clinical manifestations. The explanation for the brain lesions and strokelike episodes is unknown however favored to be because of oxidative metabolic derangement within the mind somewhat than ischemic vascular pathology. The analysis must be based mostly on medical [425], neuroimaging, histochemical, and molecular knowledge. The first scan (lefthand panel) exhibits an infarctlike hyperintensity within the parietooccipital cortex (white arrow). The second scan (righthand panel) was obtained two weeks later and shows a new lesion within the left parietooccipital cortex (open white arrow); the sooner lesion has vanished. Genetic counseling is essential for this chronic and finally deadly situation which often becomes symptomatic and identified after patients have had kids. Strokes can be subcortical or cortical, attributed to small or largevessel disease and cardioembolism. Fabry disease may be responsible for 3�5% of cryptogenic strokes, and approximately 1% of all strokes in the younger [440]. It leads to a multisystemic dysfunction affecting connective tissue, muscular tissues, cardiovascular and central nervous system, usually presenting in childhood or younger adulthood. It is related to cerebral arterial and venous thrombosis, though the mechanism is unclear. Endothelial harm and platelet aggregation leading to atheroma has been hypothesized. Vitamin B6 has been used for therapy; however, no particular treatment has been recognized [441]. Primary oxalosis has been reported to cause thrombotic occlusion of proximal cerebral blood vessels inflicting a moyamoya syndrome, as nicely as cardioembolic infarction [442]. Neurofibromatosis could also be difficult by distal carotid stenosis or occlusion inflicting a moyamoya syndrome. Ectasia and occlusion of cerebral arteries, aneurysmal formation, and tumor compression of cerebral arteries have also been described [444, 445]. Neuroimaging reveals tumorlike lesions with vasogenic edema and focal calcifications. Steroids have been used to reduce cerebral edema; in any other case remedies are limited. Imaging findings additionally consist of microhemorrhages and leukoaraiosis in sufferers without typical cerebrovascular threat factors [438]. Patients can present with persistent headache, altered mentation, seizures, and focal neurologic dysfunction. Papilledema can cause transient visible blurring as nicely as visible field constriction. Seizures and focal neurologic signs develop on account of venous hypertension and cerebral edema, and venous infarction. Thrombosis of the deep venous buildings can cause venous hypertension in bilateral deep constructions such as the hypothalami, thalami, corpus striatum, and medial temporal � occipital lobes, causing coma and abnormal eye actions. Pregnancy and puerperium (see part on pregnancy and puerperium) are related to a transient prothrombotic state that lasts from the beginning of pregnancy through 6�8 weeks postpartum. Poorer prognosis has been seen in older sufferers, men, involvement of the deep venous system or proper lateral sinus, and motor deficits [447, 451, 452]. Lifelong anticoagulation could also be warranted in patients with extreme thrombophilias in whom recurrence threat is excessive. Large and smallvessel disease are seen on this disorder, with intracranial stenoocclusive arterial lesion distinct from different vasculopathies of childhood and agingrelated atherosclerosis. Vascular abnormalities include arterial dysplasia and arteriovenous shunting [466]. Neurologic deterioration including stroke and strokelike episodes are thought to be due to impaired blood move to the mind [463]. Certainly cerebral, cerebrovascular, and cardiac imaging might level to many other, though rare, prospects of the stroke etiology from cerebral venous thrombosis to cardiac tumors. After taking an exhaustive historical past, performing a thorough systemic and neurological examination, and analyzing all appropriate laboratory and imaging knowledge, there are nonetheless some sufferers with no clear stroke mechanism. Longitudinal evaluation should be undertaken to discover treatable sources of stroke. After confirming the prognosis and making certain a unfavorable comprehensive evaluation, a clinician can reassure the affected person with some extent of confidence that although the stroke was sudden, testing has ruled out highrisk options for stroke recurrence, and after taking the suitable precautions, the patient is at relatively low danger of getting another event. Reasonable therapies include a day by day aspirin regimen, lowering cerebrovascular risk factors, and avoiding substances and actions that may predispose to future stroke. Ultrastructural connective tissue abnormalities in patients with spontaneous cervicocerebral artery dissections. Increased incidence of aortic aneurysm and dissection in large cell (temporal) arteritis: a populationbased study. Extracranial and intracranial vertebrobasilar dissections: analysis and prognosis. Risk of stroke and recurrent dissection after a cervical artery dissection: a multicenter study. Carotid and vertebral artery sacrifice with a combination of Onyx and coils: technical observe and case series. Endovascular stenting of extracranial carotid and vertebral artery dissections: a scientific evaluation of the literature. Magnetic resonance angiographic and medical features of extracranial vertebral artery dissection. Dissecting aneurysms limited to the basilar artery: report of two circumstances and evaluate of the literature. Prognosis and safety of anticoagulation in intracranial artery dissections in adults. Fibrocartilaginous embolism: a complete evaluation of an understudied explanation for 31 32 33 34 35 36 37 38 39 40 forty one 42 forty three forty four 45 forty six spinal wire infarction and proposed diagnostic standards. Acute ischemic stroke from fibrocartilaginous embolism to the center cerebral artery. The use of lumbar drains in stopping spinal cord harm following thoracoabdominal aortic aneurysm restore: an up to date systematic evaluate and metaanalysis. Endovascular isolation of intracranial blood blisterlike aneurysms with Willis covered stent. An echocardiographic study of valvular coronary heart disease associated with systemic lupus erythematosus. Detection of cerebral embolic signals in patients with systemic lupus erythematosus. Association of antibodies in opposition to phospholipids with coronary heart valve disease in systemic lupus erythematosus. Clinical and neuropathological findings in systemic lupus erythematosus: the role of vasculitis, coronary heart emboli, and thrombotic thrombocytopenic purpura. The prognosis and clinical administration of the neuropsychiatric manifestations of lupus. Risk of cerebrovascular accidents and ischemic heart disease in cutaneous lupus erythematosus: a populationbased cohort research. Prevalence and correlates of accelerated atherosclerosis in systemic lupus erythematosus. Cerebral small vessel disease burden is increased in systemic lupus erythematosus. Catastrophic antiphospholipid antibody syndrome presenting as acute vascular occlusion in a young feminine affected person. Vertebrobasilar insufficiency in rheumatoid atlantoaxial subluxation: a case report with angiographic demonstration of left vertebral artery occlusion. Cryoglobulinaemias: a multicentre study of the early clinical and laboratory manifestations of primary and secondary illness. Central nervous system involvement and psychiatric manifestations in systemic sclerosis (scleroderma): scientific and neurophysiological analysis. Noninfective endocarditis with systemic embolization and recurrent stroke in systemic sclerosis.
Specifications/Details
Hyperinsulinemic euglycemia remedy for stunned myocardium following subarachnoid hemorrhage impotence vs infertile cialis 10 mg buy discount on-line. Torsade de pointe atypical ventricular tachycardia complicating subarachnoid hemorrhage impotence zargan discount cialis 10 mg fast delivery. Association between electrocardiographic abnormalities and intracranial blood in patients following acute subarachnoid hemorrhage erectile dysfunction due to old age cialis 5 mg order mastercard. Neurogenic pulmonary edema and other mechanisms of impaired oxygenation after aneurysmal subarachnoid hemorrhage erectile dysfunction cialis 2.5 mg generic online. The effects of treating hypertension following aneurysmal subarachnoid hemorrhage. Management of hypertensive emergencies in acute brain disease: evaluation of the therapy effects of intravenous nicardipine on cerebral oxygenation. Prospective randomized comparison of safety and efficacy of nicardipine and nitroprusside drip for management of hypertension within the neurosurgical intensive care unit. Delayed postoperative neurological deterioration from extended sodium nitroprusside administration. Characterization of perioperative seizures and epilepsy following aneurysmal subarachnoid hemorrhage. Anticonvulsant prophylaxis and timing of seizures after aneurysmal subarachnoid hemorrhage. Seizures and epilepsy following aneurysmal subarachnoid hemorrhage: incidence and threat components. Outcome in patients with subarachnoid hemorrhage treated with antiepileptic medication. Phenytoin publicity is related to practical and cognitive incapacity after subarachnoid hemorrhage. Preoperative ventriculostomy and rebleeding after aneurysmal subarachnoid hemorrhage. Acute surgery for intracerebral haematomas attributable to rupture of an intracranial arterial aneurysm. Proposed use of prophylactic decompressive craniectomy in poor grade aneurysmal subarachnoid hemorrhage sufferers presenting with associated massive sylvian hematomas. The notion of "warning leaks" in subarachnoid haemorrhage: are such sufferers in fact admitted with a rebleed Acute subdural haematoma with out subarachnoid haemorrhage caused by rupture of an inside carotid artery bifurcation aneurysm: case report and review of literature. Acute subdural haematoma secondary to ruptured intracranial aneurysm: analysis and administration. Immediate administration of tranexamic acid and reduced incidence of early rebleeding after aneurysmal subarachnoid hemorrhage: a prospective randomized examine. Ultraearly surgery for aneurysmal subarachnoid hemorrhage: outcomes for a consecutive sequence of 391 sufferers not selected by grade or age. Effectiveness of neurosurgical clip utility in patients with aneurysmal subarachnoid hemorrhage. The natural history of intracranial aneurysms: rebleeding charges through the acute and long run period and implication for surgical management. Timing of surgery in sufferers with aneurysmal subarachnoid haemorrhage: rebleeding is still the major reason for poor consequence in neurosurgical items that goal at early surgical procedure. Selection, timing, and technique of aneurysm surgical procedure of the anterior circle of Willis. Timing of aneurysm surgery in subarachnoid hemorrhage: a scientific review of the literature. Timing of aneurysm surgical procedure: the International Cooperative Study revisited within the period of endovascular coiling. Outcome following symptomatic cerebral vasospasm on presentation in aneurysmal subarachnoid hemorrhage: coiling vs. Perioperative measures for treatment and prevention of cerebral vasospasm following subarachnoid hemorrhage. Timing of aneurysm treatment after subarachnoid hemorrhage: relationship with delayed cerebral ischemia and poor outcome. Does remedy of ruptured intracranial aneurysms inside 24 hours improve clinical end result Threedimensional reconstructed pictures after rotational angiography in the analysis of intracranial aneurysms: surgical correlation. Followup screening after subarachnoid haemorrhage: frequency and determinants of latest aneurysms and enlargement of present aneurysms. Analysis of intraoperative rupture in the surgical therapy of 1694 saccular aneurysms. Impact of hospitalrelated components on end result after therapy of cerebral aneurysms. Endovascular remedy of posterior circulation aneurysms by electrothrombosis using electrically removable coils. Combined microsurgical and endovascular administration of advanced intracranial aneurysms. Remodeling method for endovascular treatment of ruptured intracranial aneurysms had a higher price of enough postoperative occlusion than did conventional coil embolization with comparable security. Stentassisted coiling in acutely ruptured intracranial aneurysms: a qualitative, systematic evaluation of the literature. Assessment of acutely unsuccessful makes an attempt at removable coiling in intracranial aneurysms. Procedural problems of coiling of ruptured intracranial aneurysms: incidence and risk factors in a consecutive series of 681 patients. Rupture of intracranial aneurysms during treatment with Guglielmi removable coils: incidence, end result, and threat factors. Association of endovascular remedy of very small ruptured aneurysms with larger charges of procedurerelated rupture. Intracranial aneurysms handled with the Guglielmi removable coil: midterm clinical leads to a consecutive collection of a hundred patients. Retroperitoneal hematoma as a serious complication of endovascular aneurysmal coiling. References 713 106 van der Schaaf I, Algra A, Wermer M, Molyneux A, 107 108 109 one hundred ten 111 112 113 114 a hundred and fifteen 116 117 Clarke M, van Gijn J et al. Endovascular coiling versus neurosurgical clipping for sufferers with aneurysmal subarachnoid haemorrhage. Guglielmi detachable coil embolization of posterior circulation aneurysms: a systematic evaluation of the literature. Endovascular management of intracranial aneurysms: current experience and future advances. Early rebleeding after coiling of ruptured cerebral aneurysms: incidence, morbidity, and risk elements. Clipping versus coiling for ruptured intracranial aneurysms: a scientific evaluate and metaanalysis. Antifibrinolytic treatment in subarachnoid hemorrhage: a randomized placebocontrolled trial. Antifibrinolytic remedy to prevent early rebleeding after subarachnoid hemorrhage. Potential position of NovoSeven within the prevention of rebleeding following aneurysmal subarachnoid haemorrhage. Angiographic vasospasm is strongly correlated with cerebral infarction after subarachnoid hemorrhage. Clot quantity and clearance price as independent predictors of vasospasm after aneurysmal subarachnoid hemorrhage. The angiopathy of subarachnoid hemorrhage: angiographic and morphologic correlates. Occurrence of extreme vasospasm following intraventricular hemorrhage from an arteriovenous malformation. Prognostic worth of cerebral perfusioncomputed tomography in the acute stage after subarachnoid hemorrhage for the event of delayed cerebral ischemia. Initial lack of consciousness and threat of delayed cerebral ischemia after aneurysmal subarachnoid hemorrhage. Prophylactic hyperdynamic postoperative fluid therapy after aneurysmal subarachnoid hemorrhage: a scientific, prospective, randomized, controlled study. Control of hypertension and prophylaxis against vasospasm in circumstances of subarachnoid hemorrhage: a preliminary report.
Syndromes
- Menopause and hormone replacement therapy
- Protecting the delicate skin of the ear canal from getting irritated when water is in the canal
- Sickle cell disease
- DO NOT eat raw honey, only honey that has been heat treated
- Allergic reactions to drugs
- Rheumatoid arthritis
- Haemophilus influenzae vaccine (Hib)
Related Products
Additional information:
The nurses usually have biggest contact with the patients and family and due to this fact have an important position in this space erectile dysfunction treatment duration cialis 2.5 mg buy line. Advising nurses and different carers on one of the only ways to position sufferers to stop unhelpful modifications in muscle tone which will lead ultimately to contractures and further limitation of function (Section eleven impotence at 18 buy generic cialis 2.5 mg on-line. Teaching the nurses and informal carers the best way to handle the affected person to keep away from ache or harm to the patient or carer erectile dysfunction treatment brisbane cheap 10 mg cialis otc. This will usually involve educating correct strategies of transferring erectile dysfunction cycling purchase 2.5 mg cialis free shipping, lifting, standing and walking the patient. Providing remedy to relieve the symptoms associated with painful shoulders or swollen limbs (Sections eleven. Occupational therapist Occupational therapists fulfill several roles in the management of stroke sufferers. These are usually pretty limited in the very early period after a severe stroke, but turn out to be extra important as the affected person recovers and as selfcare turns into extra related. To totally understand the potential of stroke unit nurses requires appreciable investment in specialist training and coaching. An early assessment of patients to learn how each impairment is more probably to limit their function. This includes finding the finest way of achieving a specific activity for that particular person patient. This usually includes wheelchair provision, feeding and kitchen aids, and loo aids, amongst many others (Section eleven. Speech and language therapist Speech and language therapists have several roles within the care of stroke sufferers. They embody the following: Assessment of swallowing safety both initially and as the sufferers enhance, so that their diet and fluid intake matches their swallowing talents (Section 11. Teaching the sufferers workout routines which will improve the rate of restoration of swallowing problems (Section 11. Because issues with communication so often lead to emotional misery, most speech and language therapists additionally take on a counseling role. Teaching sufferers, carers, and even volunteers methods to allow the sufferers to communicate successfully using language (spoken or written), gesture, or communication aids where appropriate. Providing remedy that will improve the recovery of communication difficulties (Section eleven. Following up patients and families after discharge from hospital, to establish any altering needs for help and to make changes to any care package deal. Providing counseling which could be helpful in allowing patients and households to come to terms with the change in circumstances caused by the stroke. Some social staff organize groups of patients, carers, or each to help remedy issues. Social worker the position of the social worker is certain to range in different societies, but might include: Providing patients and their families with practical recommendation and assist in any respect phases of the illness. For instance, arranging subsidized transport for the household to go to the hospital, or extra residence care for a dependent relative if the stroke affected person was the principle carer earlier than admission. Social workers often help with any financial issues that have arisen as a result of the main breadwinner has had a stroke. Social workers usually spend a lot of time figuring out the wishes and wishes of the affected person and household after which, Although organized stroke care improves outcomes, some query the effectiveness of physiotherapy, occupational remedy, speech and language remedy, and social work. They level to the relative lack of analysis evidence to assist the effectiveness of those professionals (but interestingly, without questioning their own effectiveness), or they emphasize explicit research that seem to demonstrate the ineffectiveness of other professions. This has presumably resulted in "falsenegative" studies, leading to rejection of the contribution of priceless group members. All the stroke units included in one systematic review of the randomized controlled trials held at least weekly conferences of the multidisciplinary group, separate from typical ward rounds [62]. These conferences have several important capabilities: the whole team may be informed about new patients and their problems. Existing patients can have their progress reviewed, and if individual group members have noted a change of their situation or a new downside, this can be communicated to the other members. By the time of the assembly, the nursing employees can report on the functional penalties of these impairments. At every subsequent meeting, the affected person is launched briefly with a r�sum� of the date of stroke, medical type, and presumed trigger. The problems are then summarized, as well as targets and actions that have been agreed at the last meeting. The therapists follow: first the physiotherapist, then the speech therapist, and lastly the occupational therapist. Lastly, the social employee stories on any issues which shut contact with the household might have revealed and progress concerning discharge planning. This sequence also has the advantage that the occupational therapist and social employee could make use of the knowledge from the others in formulating their own objectives and actions. Inevitably, groups will include some more assertive people and other much less outgoing members, the previous tending to dominate discussions. The proposed framework lessens the probability of this arising, although after all not every member will necessarily have something useful to contribute in every case. Their views on certain issues should be sought upfront of the assembly, and the character and conclusions of the discussion on the meeting should be communicated again to the affected person and/or family by probably the most appropriate staff member, most often the nurse. Separate staff meetings (case conferences or household meetings) to which the affected person, household and any other people who are concerned � such because the district (community) nurse and home care organizer � are invited are useful in planning hospital discharge in complex circumstances and in resolving differences of opinion between the group members and the affected person or family. Instead, potentially lifesustaining remedy, together with artificial hydration and diet, could additionally be withdrawn or withheld. In addition, the worth that the affected person would place on survival in a given state may be difficult to choose. However, some relations might have their own interests and never just these of the patient to consider. Patients may have written down what they wish to happen within the event of a lifethreatening illness. Although rising incapacity is commonly associated with a reduction in quality of life [64, 65], there are numerous examples of patients reporting a good to good high quality of life despite critical disability [12, 66]. One rationalization for this observation is that patients confronted with extreme incapacity as a consequence of stroke might change their internal requirements, values, and the conceptualization of high quality of life, a course of that has been termed "response shift" [67]. Patients might have a fair to good longterm high quality of life despite extreme disability. Early dietary support is prone to enhance the proportion of patients surviving although not perhaps the useful status of survivors. Few would argue towards giving parenteral fluids to a acutely aware patient to stop dehydration, thirst, and discomfort. Also, if the affected person develops an infection very soon after the onset of the stroke, other than the difficulties talked about above in assessing the severity of stroke, the question arises as to how aggressively one ought to treat the affected person. Are intravenous antibiotics, physiotherapy, and even synthetic air flow and inotropic support appropriate on this situation Apart from worrying about medicolegal points, one has to contemplate the reaction of the family. Effective communication is a core competency in any dialogue with any patient, but this is much more crucial when a affected person or relations are informed a few poor prognosis, and when treatment restrictions are discussed. Practical methods for the care supplier that may be of assist in these discussions are summarized within the American Heart Association/American Stroke Association pointers [68]. In an American examine, most surrogates of critically unwell and incapacitated sufferers wanted physicians to disclose prognostic estimates even when they might not make sure these had been right, and most accepted this uncertainty [12, 69]. A drawback of this approach is that patients could additionally be denied the possibility to die in an early phase, however instead survive in a situation they at all times thought-about unacceptable [12]. Importantly, the position of therapy restrictions within the first few days after stroke has been independently associated with an increased threat of early dying in several observational studies [12]. A statement from the American Heart Association/ American Stroke Association provides useful tools for addressing the wants of sufferers with extreme stroke and a poor prognosis, and people of their households [38]. Contemporary outcome measures in acute stroke analysis: selection of main outcome measure. Characteristic adverse events and their incidence amongst sufferers collaborating in acute ischemic stroke trials. Bias from requiring explicit consent from all individuals in observational research: prospective, population based research. Estimates of outcomes as much as ten years after stroke: evaluation from the prospective South London Stroke Register.
Usage: ut dict.
If these tests fail to show an abnormality and the clinical suspicion is excessive vacuum pump for erectile dysfunction in pakistan cheap 2.5 mg cialis fast delivery, traditional angiography with neuroradiologic intervention (eg erectile dysfunction cvs 2.5 mg cialis buy, coiling of fistula) should be considered when the advantages to the patient outweigh the dangers impotence natural treatments 5 mg cialis generic fast delivery. Topical ocular hypotensive drugs impotence fonctionnelle cialis 10 mg free shipping, significantly people who cut back aqueous production, could also be effective in some sufferers. Due to the etiology of the condition, laser trabeculoplasty is probably going not effective. However, given the chance of a ciliochoroidal effusion or suprachoroidal hemorrhage, prophylactic sclerotomies or scleral windows may be necessary. This elevation tends to be temporary however may be protracted and lead to glaucomatous optic nerve injury. Chemical accidents, significantly those involving alkali, might cause acute secondary glaucoma because of inflammation, shrinkage of scleral collagen, release of chemical mediators corresponding to prostaglandins, direct harm to 104 Glaucoma the anterior chamber angle, or compromised anterior uveal circulation. Recurrent inflammation or injury to the trabecular meshwork may progress to glaucoma over months or years after a chemical injury. The average reported frequency of rebleeding after an preliminary hyphema is 5%�10%, nevertheless it varies significantly with different examine populations. Rebleeding normally happens within 3�7 days of the initial hyphema and could also be related to regular clot retraction and lysis. Careful gonioscopic examination in people with blunt trauma may reveal a delicate hyphema. Topical and oral corticosteroids may cut back related irritation, though their impact on rebleeding is debatable. Oral administration of aminocaproic acid has been proven to reduce rebleeding in some research. However, this has not been confirmed in all studies, and systemic opposed effects, similar to hypotension, syncope, abdominal ache, and nausea, may be significant. It has been advised that patients with sickle cell hemoglobinopathies keep away from carbonic anhydrase inhibitors, because these agents could enhance the sickling tendency within the anterior chamber by further reducing the pH; however, this relationship has not been firmly established. Adrenergic agonists with vital a1-agonist results (apraclonidine, dipivefrin, epinephrine) must also be averted in sufferers with sickle cell disease, because of the potential for anterior segment vasoconstriction with their use. Parasympathomimetic agents should be prevented in all sufferers with traumatic hyphema. In young kids, vision obstruction by the hyphema or corneal blood staining could justify early surgical intervention to cut back the danger of amblyopia. If a total hyphema is present, pupillary block may occur, and an iridectomy is helpful at the time of the washout. Hemolytic and ghost cell glaucoma Hemolytic glaucoma, ghost cell glaucoma, or each could develop after a vitreous hemorrhage. In hemolytic glaucoma, hemoglobin-laden macrophages block the trabecular meshwork. Red-tinged cells are seen floating within the anterior chamber, and the trabecular meshwork might seem reddish brown. These small, khaki-colored cells can become layered, as happens in a hyphema or hypopyon. They achieve entry to the anterior chamber via a disrupted hyaloid face, which can occur from earlier surgical procedure (pars plana vitrectomy, cataract extraction, or capsulotomy) or trauma or spontaneously. On gonioscopy, the angle appears regular aside from attainable layering of ghost cells in the inferior angle. A long-standing vitreous hemorrhage may be present, with attribute khaki coloration and clumps of extracellular pigmentation from degenerated hemoglobin. Hemolytic glaucoma and ghost cell glaucoma generally resolve once the hemorrhage has cleared. Traumatic, or angle-recession, glaucoma Angle recession is a common finding after blunt trauma and entails a tear between the longitudinal and circular fibers of the ciliary body. Examination might reveal findings in keeping with earlier trauma, corresponding to corneal scars, iris damage, abnormalities within the angle, focal anterior subcapsular cataracts, and phacodonesis. Comparing gonioscopic findings in the affected eye to these within the fellow eye could assist the clinician determine areas of recession. More in depth angle recession is associated with a larger discount in outflow facility and an elevated danger of glaucoma. Angle recession occurs when the ciliary body is torn, usually between the longitudinal and circular fibers of the ciliary body, resulting in a deepened angle recess (arrows). Torn iris processes (arrows), a whitened and increasingly seen scleral spur, and a localized despair in the trabecular meshwork are shown. The remedy of traumatic glaucoma is usually initiated with aqueous suppressants, prostaglandin analogues, and a2-adrenergic agonists. If postoperative inflammation is present, prostaglandin analogues could also be deferred till the inflammation has resolved. Attempts to reduce these adjustments with different-sized donor grafts, peripheral iridectomies, and surgical repair of the iris sphincter have solely been partially successful. Intraocular hemorrhage from wound neovascularization years after anterior section surgery (Swan syndrome). Matsuo later demonstrated the presence of photoreceptor outer segments in the aqueous humor of patients with rhegmatogenous retinal detachments. The photoreceptor segments may be mistaken for an anterior chamber inflammatory reaction or pigment. In common, the efficiency of the anti-inflammatory glucocorticoid exercise of a specific drug parallels its ocular hypertensive efficiency. The link between intravitreal antivascular endothelial growth factor injections and glaucoma. Early visible acuity loss was greater in the surgery group, however the differences between groups converged over time. At the 8-year followup examination, substantial worsening (3 dB) of visual field imply deviation from baseline was present in 21. Patients with worse baseline visible fields were less likely to progress if treated with trabeculectomy first. Patients with diabetes mellitus have been more likely to progress if treated initially with surgical procedure. Participants: 1637 patients with ocular hypertension recruited between 1994 and 1996. Study design: Multicenter randomized controlled scientific trial evaluating statement and medical therapy for ocular hypertension. The incidence of glaucoma was decrease within the medicine group than in the observation group (4. Results 2010: Topical ocular hypotensive medication was initiated in the unique remark group after 7. Participants within the original medicine group continued topical ocular hypotensive medicines for a median of 13 years. The major function of the followup examine was to determine whether delaying treatment resulted in a persistently increased danger of conversion to glaucoma, even after the initiation of remedy. Results: At 6 years, 62% of untreated sufferers showed development, whereas 45% of treated patients progressed. Risk elements for sustained decrease in visual acuity included higher baseline visual acuity, older age, and fewer formal schooling. When the variety of confirmatory visual field tests was increased from 1 to 2, the share of eyes that showed a persistent defect elevated from 72% to 84%. Traditionally, angle closure is divided into 2 main classes: major and secondary angle closure. Prevalence charges in European and African populations are usually decrease; nonetheless, genetic heterogeneity may find yourself in broadly various rates within populations of the identical continent. Moreover, the clinical presentation of angle closure varies from the abrupt and dramatic onset of acute angle closure to the insidious and asymptomatic presentation of persistent illness. In both presentation, acute or persistent, the physician should establish the anatomical adjustments within the angle and the underlying pathophysiology that has precipitated these adjustments so as to initiate the suitable remedy. Early prognosis and remedy of most forms of angle closure or narrowing could be invaluable, and generally healing. Accordingly, understanding the pathophysiology is essential if correct therapy is to be initiated.
Tags: cialis 10 mg order with amex, buy generic cialis 20 mg, cialis 10 mg buy amex, 20 mg cialis cheap with mastercard, cialis 5 mg generic visa, buy cialis 5 mg visa, 2.5 mg cialis buy visa, cialis 2.5 mg purchase on line, discount cialis 5 mg online, cialis 20 mg buy amex, cialis 20 mg buy on-line, quality 20 mg cialis, cialis 20 mg discount mastercard, purchase 20 mg cialis amex, cialis 2.5 mg buy without a prescription, cialis 20 mg order mastercard
9 of 10
Votes: 309 votes
Total customer reviews: 309
Customer Reviews
Dawson, 34 years: Amyloid deposition is noted within the basal epithelial layer on transmission electron microscopy. Finally, neither the procedure of electrical cardioversion nor the medicine used for pharmacological cardioversion are freed from risk [384, 385]. Chronic low again ache and fusion: A comparison of three surgical techniques: A potential multicenter randomized research from the Swedish Lumbar Spine Study Group. Transfer for persevering with rehabilitation: Where sufferers have been admitted to one service for acute care but should be referred to a separate institution for 19.
Kaffu, 29 years: Noninvasive carotid imaging to choose sufferers for endarterectomy: Is it really safer than conventional angiography Applying the identical arithmetical strategy used for symptomatic stenosis (Section 17. Thus, one can objectively measure the vary of motion around a joint and repeat the measure to determine whether or not or not an intervention has improved the vary. Organizing stroke services: Finally, Chapter 19 focuses on the organizational issues that are necessary when making an attempt to ship all these varied aspects of treatment to large numbers of stroke patients as efficiently and equitably as potential.
Julio, 62 years: The nonoperative group, in contrast, largely remained at baseline ranges of deformity, ache, and disability. Reduced pharyngeal "peristalsis" or cricopharyngeal dysfunction may allow meals to gather in the pharynx and spill over, previous the vocal cords and into the trachea. Burst fractures have been subdivided into 5 varieties primarily based on the fracture sample, though their clinical importance was not defined. By working closely together and sharing information and skills, some blurring of the boundaries between the roles of the professions turns into potential, and this can provide greater flexibility and effectivity.
Alima, 26 years: Management of depression after stroke: a systematic evaluate of pharmacological therapies. There was one case of leakage of cement into the vena cava, which remained asymptomatic. Treatment algorithms have advanced over previous many years to accommodate differences in fracture sample as properly as affected person age, medical situation, and body habitus. A attribute characteristic of posterolateral thalamic hemorrhages is distortion of the vertical orientation of the physique with a bent to tilt towards the ipsilateral aspect [303].
Topork, 23 years: Topical and oral corticosteroids may reduce associated irritation, although their impact on rebleeding is debatable. Previous angina Previous myocardial infarction Cardiac failure Intermittent claudication Diabetes mellitus Previous epileptic seizures Previous malignancy Dependent before stroke (Rankin >2) 106 (16) 112 (17) fifty two (8) 112 (17) sixty three (9) 19 (3) 74 (11) 103 (15) Functional deterioration months after a stroke is unlikely to be due to the initial stroke and more likely to be caused by a recurrent stroke or the development of a comorbid condition similar to angina, arthritis, or intermittent claudication. In the ischemic penumbra that surrounds the anoxic core, cells may be rescued by fast reperfusion. For sufferers at high risk of venous thromboembolism, maybe because of a historical past of a earlier episode of venous thromboembo lism or the presence of thrombophilia, intermittent pneumatic compression units or lowdose subcuta neous heparin are alternate options, that are discussed intimately in Section eleven.
