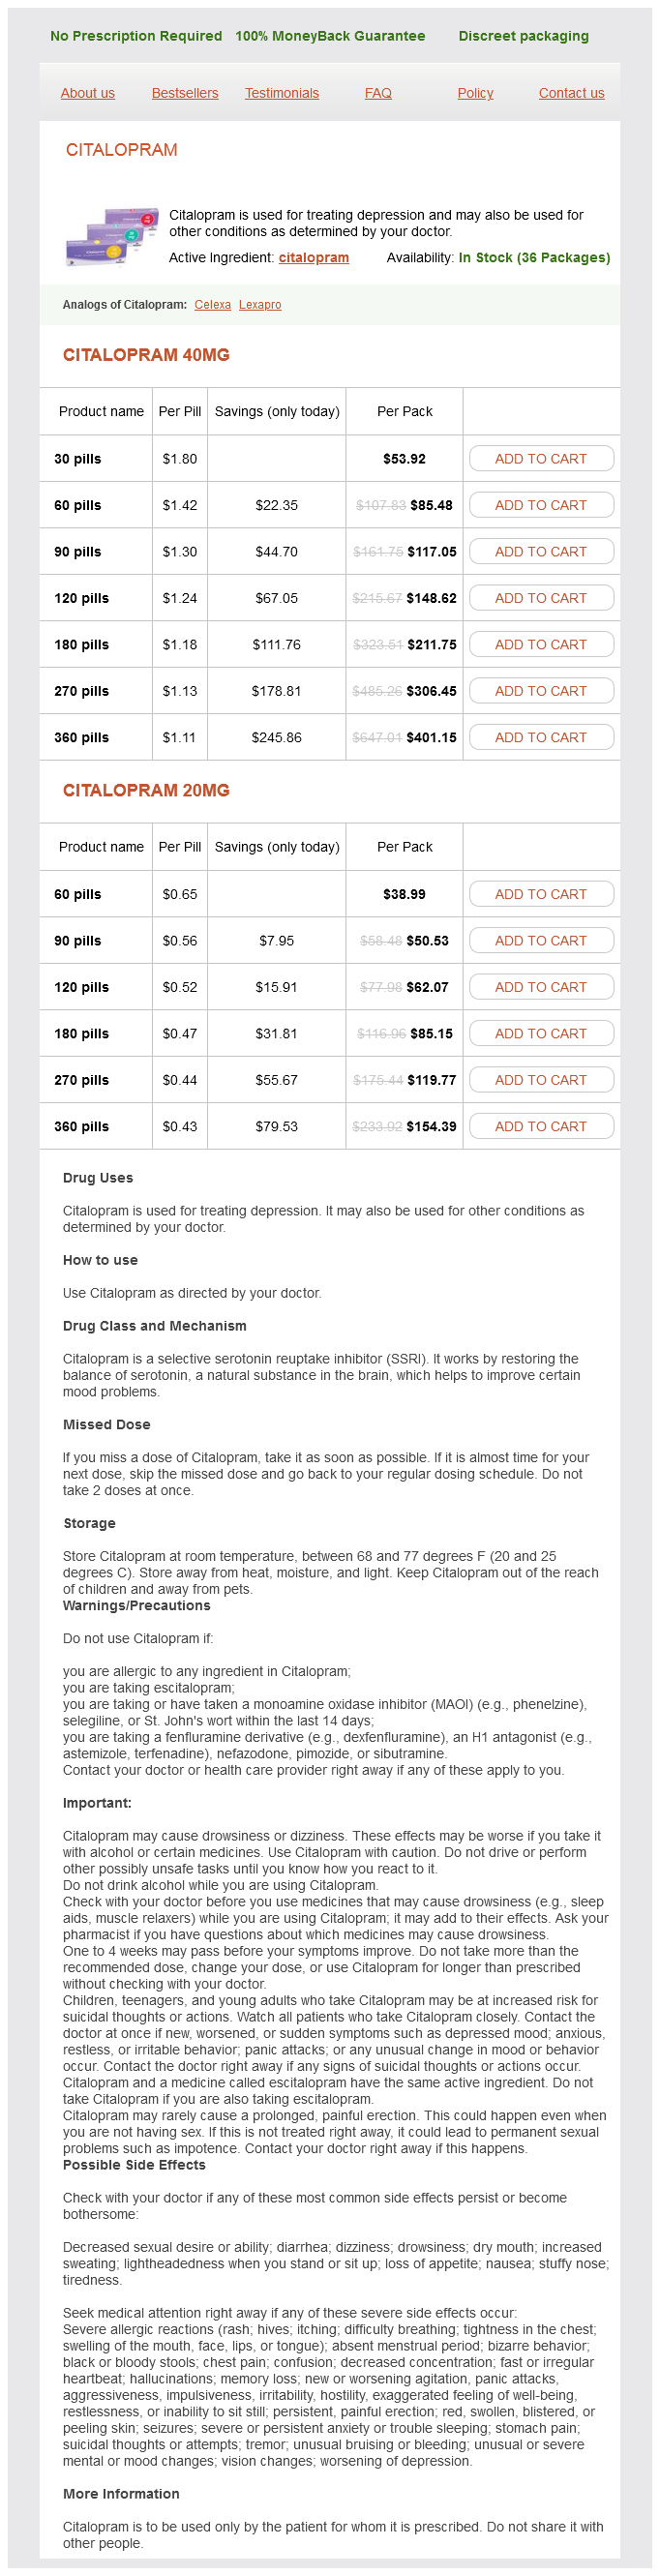
Citalopram 40mg
- 30 pills - $53.92
- 60 pills - $85.48
- 90 pills - $117.05
- 120 pills - $148.62
- 180 pills - $211.75
- 270 pills - $306.45
- 360 pills - $401.15
Citalopram 20mg
- 60 pills - $38.99
- 90 pills - $50.53
- 120 pills - $62.07
- 180 pills - $85.15
- 270 pills - $119.77
- 360 pills - $154.39
Citalopram dosages: 40 mg, 20 mg
Citalopram packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 790
Only $0,46 per item
Description
The rectum itself treatment kidney stones discount 40 mg citalopram, nevertheless treatment abbreviation cheap citalopram 20 mg on line, is normally spared because it has a dual blood supply medications via g-tube buy citalopram 20 mg on line, from the splanchnic and systemic arterial methods medicine 93 3109 purchase 20 mg citalopram free shipping. Most circumstances of ischemic colitis are attributable to atherosclerosis of major intestinal arteries, and recurrent bouts of stomach pain due to ischemic colitis are known as intestinal angina. Increasing age, especially older than 65 years, and feminine gender are danger elements. Thrombophilic states, a number of prescription medicines and the illicit drug cocaine additionally increase the chance of ischemic bowel illness. In more severe cases, necrosis affects deeper layers of bowel and might evolve to full-thickness necrosis. Patients may recover utterly or develop a stricture, by which case surgical elimination of the obstructed section could additionally be necessary. Segments of ischemic stricture show variable mucosal ulceration and irritation, submucosal granulation tissue, fibrosis and hemosiderin-laden macrophages. A trichrome stain highlights the attribute thickening of the collagen table (blue, notice arrows) with entrapment of capillaries. The intercryptal floor epithelium is flattened and incorporates an increased number of intraepithelial lymphocytes. Chronic inflammation of the lamina propria is increased, and typically extra prominent extra superficially. Changes could also be more pronounced in the proper colon, so random biopsies of the whole colon are helpful in evaluating microscopic colitis. In severe cases, mortality exceeds 50%, and pressing removal of the involved bowel may be needed. The parts of the colon most weak to nonocclusive ischemia (usually because of hypotension) are areas between adjacent arterial distributions, so-called watershed areas. A mucosal biopsy shows coagulative necrosis with "ghostly" outlines of the preexisting crypts. The hallmark of solitary rectal ulcer syndrome is smooth muscle proliferation from the muscularis mucosae into the lamina propria typically with accompanying mucosal hyperplastic modifications. Dilated glands can be trapped within the rectal wall, a condition known as colitis cystica profunda. Angiodysplasia (Vascular Ectasia) May Cause Intestinal Bleeding Angiodysplasia (vascular ectasia) is localized arteriovenous malformations, mainly in the cecum and ascending colon. Younger people might have lesions at other websites, including the rectum, stomach and small bowel. It has been advised that angiodysplasia outcomes from continual intestinal circulatory insufficiency, intestinal muscle hypertrophy and consequent venous obstruction. Patients complain of multiple bleeding episodes, but continual bleeding may also be occult. Thus, the diagnosis is difficult and often requires selective mesenteric arteriography or colonoscopy. Colonoscopic interventions are usually adequate to cease the bleeding, but surgical removal of the affected segment may be necessary in some instances. These vessels have attenuated walls, presumably accounting for their propensity to bleed. Lymphoid Polyps Are Solitary Submucosal Lymphoid Accumulations They are normally current in the colorectal mucosa and differ in dimension from pinpoint to up to 5 cm. They are covered by intact mucosa and contain distinguished lymphoid follicles with germinal centers. Nodular lymphoid hyperplasia occurs mainly in children or patients with common variable immunodeficiency syndrome (see Chapter 4) and is characterized by excessive accumulation of normal colonic lymphoid follicles. Lesions differ from reversible intestinal mucosal injury to persistent inflammation, ulceration and fibrosis of the gut. In the quick term, radiation damages epithelium and endothelium, impairs normal bowel mucosal renewal and, in the small bowel, results in villous shortening. Chronic changes happen 9�14 months after radiation remedy, after the mucosa has healed. Complications of radiation enterocolitis embrace perforation and subsequent growth of internal fistulas, hemorrhage and strictures. Inflammatory Polyps Are Elevated Areas of Inflamed, Regenerating Epithelium They are generally present in sufferers with ulcerative colitis and Crohn disease however might result from any reason for colitis. They additionally happen without demonstrable colonic illness and could also be related to prior, resolved acute/infectious colitis. These polyps have variable elements of distorted and inflamed mucosal glands, typically intermixed with granulation tissue. Hamartomatous Polyps Typically Have Both Stromal and Epithelial Elements They are composed of an overgrowth of cells and tissue native to the anatomic location. While usually discovered within the rectum, Juvenile Polyps (Retention Polyps) Juvenile polyps occur most commonly in children younger than 10 years, though 1/3 may be in adults. When sporadic, they usually arise within the rectum and current with rectal bleeding or with the polyp prolapsing through the rectum. These patients develop hamartomas of the pores and skin, gut, breast and thyroid gland. Gastrointestinal polyps in these sufferers are indistinguishable in appearance from juvenile polyps. Thus, the prognosis of Cowden syndrome is made clinically and by figuring out extraintestinal manifestations. Patients with Cowden syndrome are at elevated danger of growing breast, thyroid, ovarian, cervical, uterine and bladder cancers as properly as meningiomas (see Chapter 32). Patients with juvenile polyposis syndrome have an increased risk for gastrointestinal and pancreatic carcinomas. However, unlike juvenile polyposis or Cowden syndrome, these polyps show changes within the mucosa between polyps (edema, cystically dilated glands, elevated inflammatory cells). Such sufferers can develop a protein-losing enteropathy, anemia and electrolyte disturbances. They additionally current with scalp and body alopecia, nail dystrophy and skin hyperpigmentation. Surface epithelial erosion with underlying granulation tissue is common, as is reactive epithelial proliferation. Peutz-Jeghers Syndrome it is a uncommon, autosomal dominant syndrome with variable penetrance. Hyperplastic Polyps Are Benign Serrated Lesions Hyperplastic polyps are small, sessile mucosal protrusions with exaggerated crypt structure. They are extra frequent in colons with adenomatous polyps and in populations with larger charges of colorectal cancer. Hyperplastic polyps are felt to be because of defective proliferation and maturation of regular epithelium. Thus, cell proliferation occurs on the base of the crypt, and upward migration of the cells is slowed. The epithelial cells differentiate and purchase absorptive characteristics lower within the crypts and persist on the floor longer than do regular cells. Traditional Serrated Adenomas Occur Mainly within the Distal Colon and May Be Premalignant these polyps are a lot less widespread than hyperplastic polyps or sessile serrated adenomas. The crypts of hyperplastic polyps are elongated and show comparatively regular crypt bases. Lining epithelial cells have abundant eosinophilic cytoplasm with an elongated nucleus and open or hyperchromatic chromatin. The carcinomas that arise from sessile serrated adenomas are inclined to be bulky, mucinous and proper sided. Serrated Polyposis Syndrome Is Characterized by Multiple Serrated Polyps Also referred to as hyperplastic polyposis syndrome, this uncommon dysfunction is characterized by multiple serrated colorectal polyps, often hyperplastic polyps and sessile serrated adenomas. Risk elements are European descent and increased age, although younger individuals are typically affected. No specific mutation has but been identified, although the disease reveals familial clustering. Any number of serrated polyps proximal to the sigmoid colon in an individual with a first-degree relative with serrated polyposis syndrome three. They show irregular, uneven cell proliferation by which cells could divide wherever alongside the crypt. Microscopically, the irregular proliferation of goblet cells offers the crypts a serrated look down to the bases, inflicting the bases to turn out to be dilated with plentiful mucin and the characteristic formation of boot-, "L"- or inverted "T"-shaped crypts. The most attribute feature of this polyp kind is formation of ectopic crypts, often with a villous structure and lining epithelial cells with abundant eosinophilic cytoplasm.
Bull Balls Extract (Orchic Extract). Citalopram.
- Are there safety concerns?
- How does Orchic Extract work?
- Maintaining healthy testicle function in men and other uses.
- Dosing considerations for Orchic Extract.
- What is Orchic Extract?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96975
These newly synthesized triglycerides are secreted as lipoproteins or are retained for storage treatment 4 water 40 mg citalopram buy amex. Most of the fat deposited in the liver after continual alcohol consumption is from the food regimen medicine 8162 citalopram 40 mg generic mastercard. Within hepatocytes treatment using drugs is called cheap citalopram 20 mg without a prescription, ethanol (1) will increase fatty acid synthesis x medications purchase 40 mg citalopram with mastercard, (2) decreases mitochondrial oxidation of fatty acids, (3) raises triglyceride production and (4) impairs launch of lipoproteins. Alcoholics could have delicate fatty liver for many years and, without any change in drinking habits, suddenly develop acute alcoholic hepatitis. It may be that long-standing, subclinical alcoholic hepatitis precedes clinically overt hepatitis. Nevertheless, the often explosive presentation of alcoholic hepatitis means that some environmental or physiologic cofactor is concerned, although none has been recognized. The cytoplasm of just about the entire hepatocytes distended by fat that displaces the nucleus to the periphery. In the latter case, liver cells may be barely recognizable as such and resemble adipocytes, with their cytoplasm distended by a clear space and their nuclei flattened and displaced to the periphery of the cell. Ultrastructurally, hepatocytes in alcohol-induced fatty livers reflect the cytotoxicity of ethanol rather than an impact of fat. Not solely is the microsomal ethanol-oxidizing system induced, however metabolism of quite so much of medication is also enhanced. Whereas persistent alcohol consumption promotes microsomal capabilities, acute alcohol ingestion inhibits mixed-function oxidases and acutely reduces the rate of clearance of medicine from the physique. Hepatocytes show variable hydropic swelling, giving them a heterogeneous appearance. Isolated necrotic liver cells or clusters of them have pyknotic nuclei and present karyorrhexis. These cytoplasmic inclusions are extra frequent in visibly damaged, swollen hepatocytes and seem as irregular skeins of eosinophilic materials or as stable eosinophilic lots, often perinuclearly. The broken, ballooned hepatocytes, significantly these with Mallory bodies, are surrounded by neutrophils. Collagen deposition is all the time seen in alcoholic hepatitis, especially around central veins (terminal hepatic venules). Chronic alcohol exposure prompts hepatic stellate cells to deposit intrasinusoidal collagen. Some are just about regular, whereas others are enlarged, with a mononuclear infiltrate and proliferated bile ductules. The altered portal tracts usually show spurs of fibrous tissue that penetrate the lobules. In extreme cases, a prolonged prothrombin time usually portends an ominous prognosis. The outlook in sufferers with alcoholic hepatitis reflects the severity of liver cell harm. Most of those who abstain from alcohol after recovery from acute alcoholic hepatitis get well. Necrosis and degeneration of hepatocytes, Mallory-Denk our bodies (eosinophilic inclusions) within the cytoplasm of injured hepatocytes (arrows) and infiltration by neutrophils. The inflammatory infiltrate consists predominantly of neutrophils (N), though a few lymphocytes (L) and macrophages (M) are also present. Dense, interwoven bundles of cytokeratin filaments are in the cytoplasm of hepatocytes. The other lesions of alcoholic liver disease-fatty liver and acute or persistent alcoholic hepatitis-are typically seen at the facet of cirrhosis. Some assert that progression to alcoholic cirrhosis requires a minimum of subclinical alcoholic hepatitis. Activated hepatic stellate cells, which produce perisinusoidal collagen, in all probability contribute to the development of cirrhosis. The prognosis in instances of established alcoholic cirrhosis is much better in those who abstain from alcohol. Nevertheless, many sufferers progress to end-stage liver disease, and alcoholic liver illness is a standard indication for liver transplantation. Autoantibodies bind epitopes associated with the mitochondrial pyruvate dehydrogenase complicated. Other circulating autoantibodies are antinuclear, antithyroid, antiplatelet, antiacetylcholine receptor and antiribonucleoprotein antibodies. Loss of bile ducts results in impaired bile secretion, cholestasis and hepatic damage. Bile duct epithelium is irregular and hyperplastic, with stratification and occasional papillary ingrowths of epithelial cells. Epithelioid granulomas typically occur in portal tracts and will impinge on the bile ducts. Most (85%) patients have no much less than one different autoimmune disease (chronic thyroiditis, rheumatoid arthritis, scleroderma, Sj�gren syndrome, systemic lupus erythematosus), and virtually half (40%) have two or extra such diseases. A portal tract expanded by an inflammatory infiltrate consisting of lymphocytes, plasma cells, eosinophils and macrophages. Collagenous septa extend from the portal tracts into the lobular parenchyma and begin to encircle some lobules. Small bile ducts are scarce, and medium-sized ducts are conspicuously fewer in number. There is little inflammation within either the fibrous septa or the parenchymal nodules. Progressive biliary obstruction typically results in persistent obstructive jaundice, recurrent cholangitis and finally to secondary biliary cirrhosis. Some remain asymptomatic and appear to have an excellent prognosis; others ultimately develop superior cirrhosis and its complications. As the disease advances, serum bilirubin progressively will increase in most patients. Blood cholesterol levels enhance strikingly, and an irregular lipoprotein (lipoprotein-X) seems, a finding in many forms of chronic cholestasis. Cholesterol-laden macrophages accumulate in subcutaneous tissues, the place they type localized lesions termed xanthomas. Impaired bile excretion into the gut often results in severe steatorrhea because of fats malabsorption. Those patients who ultimately develop cirrhosis die of liver failure or complications of portal hypertension. Associations with retroperitoneal fibrosis, lymphoma and the fibrosing variant of persistent thyroiditis (Riedel struma) are additionally reported. Increased colonic permeability to micro organism has been advised as an element, however this chance stays speculative. An inflammed portal tract with a dilated bile duct and "onion skin" periductal fibrosis. Transferrin standing: Fe 1 Unbound Bound to 1 iron: Bound to 2 iron: Similar inflammatory and fibrotic changes may be seen in large intrahepatic and extrahepatic bile ducts, and these modifications can hinder each. The illness tends to be segmental; thus, the intrahepatic biliary tree shows a characteristic beaded appearance with distinction radiography. Clinical displays range from asymptomatic elevations in cholestatic liver exams to symptoms of biliary obstruction, recurrent cholangitis and evidence of end-stage liver illness. There are two main groups of iron overload syndromes, divided on the basis of etiology. It entails parenteral iron overload, by which the iron accrues due to multiple blood transfusions or parenteral administration of iron itself, or is caused by big dietary intake of iron. Several principal proteins management this course of: Hepcidin: this 25 amino acid peptide is manufactured and exported by the liver and is the important thing to iron regulation. Hepcidin blocks transit of iron via enterocytes to the blood and inhibits its secretion from shops in hepatocytes and macrophages. It does this by binding the primary iron export channel in these cells, ferroportin, and selling its degradation. Hepcidin synthesis is stimulated when physique iron stores are sufficient and is downregulated when the body wants more iron. Once in enterocyte cytosol, iron is exported by a selected channel, ferroportin, which mediates iron export in enterocytes and different cells.
Specifications/Details
Patterns of antigenic expression identify the lineage and maturation stage of regular and neoplastic lymphoid cells (see below and Chapter 4) symptoms whooping cough buy generic citalopram 20 mg on line. Larger nodes are considered clinically enlarged and may be abnormal microscopically symptoms rheumatoid arthritis citalopram 40 mg buy line. Sometimes many nodes within a series or group may be enlarged and/or matted collectively 5 medications buy citalopram 20 mg cheap, typically a function of malignancy symptoms 9f diabetes 40 mg citalopram proven. There, they turn into Ig-secreting plasma cells, or they exit the lymph nodes as memory B cells. Plasma cells have eccentric nuclei with clumped chromatin marginated on the nuclear membrane, historically described as "clock-face chromatin. Recombination of T-cell receptor genes generates a diverse population of T cells, each of which may acknowledge a single antigen. Once mature and educated, T cells depart the thymus to lymph nodes, spleen and peripheral blood to turn into postthymic T cells. The antigens presented to T-helper cells are peptide fragments derived from partial digestion of foreign proteins by macrophages and/or different antigen-presenting cells. The T-helper cells in flip interact with B lymphocytes that specific the identical antigenic specificity and induce the latter to proliferate and differentiate into plasma cells. Lymphocytes have diverse morphologies in stained peripheral blood and bone marrow smears, in addition to in tissue sections. Like other blast cells, immature lymphoid cells have excessive nuclear-to-cytoplasmic ratios, fantastic chromatin and visual nucleoli. Following the lymphoid stem cell and precursor stage in the bone marrow, B cells mature into naive B lymphocytes and home to the secondary lymphoid organs (primarily lymph nodes). The germinal-center reaction represents an necessary turntable for immunoglobulin variable-region gene mutations, Ig heavy-chain change and differentiation into plasma cells and reminiscence B cells. B-cell immunoblasts and plasmacytoid immunoblasts reside within the T-cell�rich paracortex and medulla, respectively. In peripheral blood smears, reworked cytotoxic T cells are variant lymphocytes (sometimes referred to as "atypical lymphocytes"). Variant lymphocytes are inclined to have ample blue-gray cytoplasm and a number of nucleoli in Wright-Giemsa�stained smears. The same cells in tissue sections stained with hematoxylin and eosin have spherical to oval nuclei, one to several eosinophilic nucleoli apposed to their nuclear membranes and abundant clear to purple cytoplasm. Precise identification and characterization of lymphoid cells requires flow cytometric or immunohistochemical analysis. The term "variant lymphocytes" covers atypical lymphocytes and large granular lymphocytes. Large granular lymphocytes are medium to large lymphoid cells with some pink cytoplasmic granules. Plasmacytoid lymphocytes have plentiful blue cytoplasm and are seen in some reactive issues. Bone marrow plasmacytosis higher than 10% is typically related to a plasma cell neoplasm. In both reactive and neoplastic plasma cell proliferations, immunoglobulin could accumulate in the cytoplasm to type outstanding eosinophilic globules, known as Russell our bodies. Similarly, benign and neoplastic plasma cells could contain nuclear pseudoinclusions (Dutcher bodies), which represent immunoglobulin invaginated into the nucleus and seen in cross-section. Lymphocytopenia Usually Reflects a Decrease in T-Helper Lymphocytes Peripheral blood lymphocytopenia is outlined as a blood lymphocyte rely lower than 1500/L in adults or lower than 3000/L in youngsters. An absolute lymphocytosis attributable to a heterogeneous population of small and larger lymphoid cells, including atypical lymphocytes, is characteristic of this Ebstein-Barr virus� driven dysfunction. Other less widespread causes of reactive lymphocytosis embody pertussis, chronic bacterial infections such as tuberculosis and brucellosis, stress and cigarette smoking. Persistent absolute lymphocytosis, larger than 4000/L, notably in adults, raises suspicion for a lymphoproliferative disorder and deserves further analysis. Decreased lymphocyte production: Several congenital and acquired immunodeficiency syndromes entail decreased era of lymphocytes. Impaired T-cell manufacturing also happens with some lymphomas, corresponding to classical Hodgkin lymphoma, significantly in superior phases. Loss of lymphocytes: Disorders related to damage to intestinal lymphatics can lead to lack of lymph fluid and lymphocytes into the gut lumen. Such ailments include protein-losing enteropathies, Whipple illness and conditions of increased central venous strain. Immunologic damage to lymphocytes might happen in collagen vascular illnesses, similar to systemic lupus erythematosus. The histology and magnitude of lymph node enlargement in reactive hyperplasia are capabilities of the age of the patient (children are most likely to show higher immunoreactivity than do adults), the immunologic competence of the host and the inciting stimulus. Acute suppurative and necrotizing lymphadenitis occurs in lymph nodes that drain sites of acute bacterial or fungal infections. Such nodes enlarge rapidly because of edema and hyperemia, and are often tender as a result of the capsule turns into distended. Lymph node sinuses and stroma are infiltrated by neutrophils and variable numbers of bland macrophages. Well- or poorly outlined granulomas are common, and necrosis can be focal and Plasma cells in peripheral blood: It is rare to discover plasma cells in the blood. The presence of circulating plasma cells in the blood of an grownup raises suspicion for a plasma cell neoplasm, such as plasma cell myeloma (see below). Reactive bone marrow plasmacytosis: Plasma cells normally account for lower than 3% of hematopoietic cells in the bone marrow. If they make up higher than 3% of bone marrow cells, plasmacytosis is diagnosed, and it could be polyclonal or monoclonal. In children and young adults, most plasmacytoses are brought on by reactive situations similar to continual infections or systemic inflammatory problems. The major patterns of reactive hyperplasia are contrasted with the architecture of a traditional lymph node. Follicular hyperplasia, with an increased number of enlarged and irregularly formed follicles, is attribute of B-cell immunoreactivity. Interfollicular hyperplasia with expansion of the paracortex is typical of T-cell immunoreactivity. This patten is seen in reactive proliferations of the mononuclear�phagocyte system. A combined sample of follicular, interfollicular and sinusoidal hyperplasia is frequent in a wide range of advanced immune reactions. In necrotizing lymphadenitis, variable zones of necrosis are discovered inside the lymph nodes, with or with out the presence of neutrophils. Cohesive clusters of macrophages and occasional multinucleated large cells are attribute of the granulomatous inflammation sample. Although the precise trigger is usually unknown, the situation often resolves promptly. A part of a hyperplastic lymph node reveals distinguished follicles (germinal centers) containing quite a few macrophages with pale cytoplasm. The location of the nodes concerned in reactive lymphadenopathy usually provides a clue to its trigger. For example, posterior auricular lymph nodes are generally enlarged in rubella an infection; occipital lymph nodes in scalp infections; posterior cervical lymph nodes in toxoplasmosis; axillary lymph nodes in infections of the arms or chest wall; and inguinal lymph nodes in venereal infections and infections of the legs. Generalized lymphadenopathy may happen in systemic infections, hyperthyroidism, drug hypersensitivity reactions and autoimmune diseases. Mixed Patterns of Reactive Lymph Node Hyperplasia Some infectious diseases are related to blended patterns of lymphoid hyperplasia, in which a quantity of completely different features are outstanding. Lymphadenitis attributable to lymphogranuloma venereum and tularemia (see Chapter 9) resembles that seen in cat-scratch illness. Follicular Hyperplasia Hyperplasia of secondary follicles (germinal centers) and plasmacytosis of medullary cords point out B-cell immunoreactivity. The activated B cells in these follicles vary from small cells with irregular, cleaved nuclei to massive immunoblasts. Scattered benign macrophages, with ample pale cytoplasm containing pyknotic nuclear and cytoplasmic particles, impart a characteristic "starry sky" sample to benign follicle centers.
Syndromes
- Hallucinations
- Females over 14 years: 3.0 mg/day
- Blood clots in the legs that may travel to the lungs
- Primaquine
- Allergy to spermicides used for birth control
- Severe respiratory infections that keep coming back (recurring)
Related Products
Additional information:
Universal vaccination applications have significantly reduced the incidence of acute hepatitis A in the United States medications online generic citalopram 40 mg fast delivery. It mainly replicates in hepatocytes medications 1 gram citalopram 20 mg order on-line, however gastrointestinal epithelial cells can also be infected symptoms 4 days after ovulation 20 mg citalopram cheap overnight delivery. Epidemics of hepatitis A occur in crowded and unsanitary conditions medicine stick cheap citalopram 40 mg free shipping, similar to exist in warfare, or by fecal contamination of water and meals. In industrialized countries, which have low charges of infection, most instances of hepatitis A are seen in older kids and adults. By contrast, in less developed areas, where the illness is endemic, a lot of the inhabitants is contaminated earlier than 10 years of age. It stays evident for a median of 10 days however might persist for greater than a month. Aminotransferase levels usually return to normal by the time jaundice has disappeared. IgM titers start to decline within a few weeks and are undetectable by 3�5 months. The C gene contains two consecutive open reading frames: the precore and core areas. Mutations are common, each in unmolested infection and beneath the influence of pharmacotherapy. The complete virion, composed of the viral core and its surrounding envelope, is represented by Dane particles (arrows). In endemic areas, excessive provider rates are sustained by vertical transmission from provider moms to newborns. In countries with high endemicity, the excessive chronicity fee is due to vertical transmission and unsafe injection practices. Such contact transmission largely includes direct transfer of virus by way of breaks within the skin or mucous membranes. In some regions the place hepatitis B is endemic, vaccination has considerably reduced the prevalence of the illness. Vaccination of infants is common in most nations (currently 177 of 193 countries). The infectivity of blood from patients with chronic hepatitis B declines with the period of the disease. This is basically due to decreased episomal (extrachromosomal) replication of infectious virions. However, genomic fragments are progressively built-in, after which they produce a quantity of viral antigens, contributing to viral persistence. Symptoms of hepatitis B are largely just like these of hepatitis A, but acute hepatitis B tends to be considerably extra extreme, and its incubation period is for much longer. Typically, symptoms seem 2�3 months after exposure, but incubation durations might range from under 6 weeks to 6 months. As in hepatitis A, many instances, including nearly all infections in infants and children, are anicteric and thus not clinically obvious. Nucleoside and nucleotide analogs have improved outcomes for patients with fulminant hepatitis B compared to historic controls. There is little vital hepatocellular irritation or necrosis: serum aminotransferase levels are normal. However, these people could revert to immune lively disease and thus require long-term follow-up. Such circulating immune complexes could result in extrahepatic problems, including a serum sickness�like syndrome (fever, rash, urticaria, acute arthritis), polyarteritis, glomerulonephritis and cryoglobulinemia. Chronic hepatitis B is associated with a big danger of liver cancer (see below). The virus is genetically unstable, which outcomes in the existence of multiple genotypes and subtypes. Types 1, 2 and three are most common (about 75% within the United States and Western Europe). It is estimated that some a hundred and seventy million folks (3% general prevalence) are infected worldwide. Less environment friendly transmission occurs via smaller percutaneous exposures (needlestick injuries) or mucosal routes similar to vertical and sexual transmission. Much of this decrease probably reflects declining use of injectable illicit drugs. Mortality as a outcome of hepatitis C is growing, as people infected long ago are aging. About 20% of the sufferers with acute hepatitis C have a self-limited an infection that resolves in a couple of months. The remaining patients with hepatitis C develop persistent sickness, with exacerbations and remissions of scientific symptoms. Despite active humoral and mobile immune responses against all viral proteins, most patients have persistent viremia. Acute hepatitis C is quite gentle, or asymptomatic, in most people: only 10%� 20% develop jaundice. Even in the absence of elevated aminotransferases or vital risk factors for progression, patients can present with vital fibrosis and even cirrhosis. Chronic hepatitis is gentle in most patients for a minimal of 10 years and sometimes for 20 or extra years. Hepatitis E Virus Is a Major Cause of Epidemic Hepatitis Hepatitis E is a self-limited, acute, icteric disease much like hepatitis A. It accounts for greater than 1/2 of cases of acute viral hepatitis in younger to middle-aged people within the poorer regions of the world. Large outbreaks have been reported in India, Nepal, Burma, Pakistan, the previous Soviet Union, Africa and Mexico. Most of those epidemics have followed heavy rains in areas with insufficient sewage disposal. Jaundice, hepatomegaly, fever and arthralgias are frequent and usually resolve within 6 weeks, with 1%�12% mortality. Like hepatitis A, scientific sickness from hepatitis E is far extra frequent in adults than in youngsters; within the latter, infection could usually be subclinical. The disease is very dangerous in pregnant girls, in whom mortality could attain 20%�40%. Chronic illness and carrier states are unknown in immunocompetent sufferers, but immunocompromised people could develop continual hepatitis E. Extrahepatic manifestations of hepatitis C are widespread and embody mixed cryoglobulinemia (see Chapter 20), a systemic vasculitis due to deposition of circulating immune complexes within the microvasculature. The skin (leukocytoclastic vasculitis), salivary glands (sicca syndrome), nervous system (mononeuritis multiplex) and kidney (membranoproliferative glomerulonephritis) could additionally be affected. Chronic hepatitis C is usually treated with a combination of injected interferon- and oral ribavirin. Within the hepatic lobule, scattered single cell necrosis or demise of small clusters of hepatocytes is seen. A few apoptotic liver cells appear as small, deeply eosinophilic bodies (acidophilic bodies), typically with pyknotic nuclei. Acidophilic bodies are characteristic of viral hepatitis but are also seen in lots of different liver diseases. In acute viral hepatitis, many liver cells show varying degrees of hydropic swelling and variations in size, shape and marking properties. Concomitantly, regenerative liver cells may have bigger nuclei and basophilic cytoplasm. Mononuclear cells, largely lymphocytes, infiltrate lobules diffusely, surround individual necrotic liver cells and accumulate in areas of focal necrosis. Characteristically, lymphocytes infiltrate between the wall of the central vein and the liver cell plates, an look termed central phlebitis. Swelling and proliferation of the endothelium of central veins (endophlebitis) could develop. Kupffer cells are enlarged, project into sinusoid lumens and comprise lipofuscin pigment and phagocytosed particles.
Usage: a.c.
Many forms of dysplasia are accompanied by other urinary tract abnormalities treatment knee pain cheap citalopram 40 mg fast delivery, particularly ones that trigger obstruction of urine circulate treatment 30th october 40 mg citalopram free shipping. This association means that obstruction to urine circulate in utero may cause dysplasia medications qd citalopram 20 mg quality. Rudimentary glomeruli could also be seen symptoms nausea headache citalopram 40 mg line, and tubules and ducts may be cystically dilated. Renal dysplasia may be unilateral or bilateral, and the affected kidney could additionally be fairly large or very small: Aplastic renal dysplasia results in very small misshapen dysplastic kidneys, which can be troublesome to identify by gross examination. Multicystic renal dysplasia is often unilateral and is characterized by renal enlargement by multiple cysts, ranging from microscopic to a quantity of centimeters in diameter. Diffuse cystic renal dysplasia options extra uniformly sized cysts and preservation of a kidney form. Obstructive renal dysplasia, focal or diffuse, unilateral or bilateral, is attributable to intrauterine obstruction to urine flow, corresponding to posterior urethral valves or ureteropelvic junction stenosis. Unilateral multicystic renal dysplasia is the most common reason for an stomach mass in newborns and is satisfactorily treated by eradicating the affected kidney. Bilateral aplastic dysplasia and diffuse cystic dysplasia trigger oligohydramnios and the resultant Potter sequence and lifethreatening pulmonary hypoplasia. Immature glomeruli (arrow), tubules (arrowhead) and cartilage (C) are surrounded by free, undifferentiated mesenchymal tissue (*). The tubule wall turns into covered by undifferentiated cells with giant nuclei and solely few microvilli. Concomitantly, a defective basement membrane just under the irregular epithelium permits the affected tubule to dilate. Cyst fluid is initially derived from the glomerular filtrate, but ultimately most cysts lose reference to the tubules, by which case fluid accumulates by transepithelial secretion. Thus, elements apart from crowding of normal tissue by expanding cysts doubtless impair practical renal tissue. Apoptotic lack of renal tubules and accumulation of inflammatory mediators have been incriminated in the destruction of normal renal mass. The external contours are distorted by quite a few cysts, as large as 5 cm, full of a straw-colored fluid. Cysts arise from any level alongside the nephron, including glomeruli, proximal tubules, distal tubules and amassing ducts. Areas of normal renal parenchyma between the cysts endure progressive atrophy and fibrosis because the illness advances with age. It affects 1:400�1:a thousand individuals in the United States, 1/2 of whom finally develop end-stage renal failure. The products of these genes, polycystin-1 and polycystin-2, are within the main cilia of tubular epithelial cells and in cell�cell adhesion complexes. These buildings sense the extracellular surroundings including urine flow, resulting in regulation of intracellular calcium and of tubule epithelial proliferation, cell polarity and apoptosis. Defects in these proteins result in dysfunction of major cilia (ciliopathy) that disrupt calcium signaling, trigger disturbed cell polarity and induce tubular epithelial cell proliferation. A small minority of sufferers develop symptoms throughout childhood, and rarely are they symptomatic at start. Symptoms embody a way of heaviness within the loins, bilateral flank and belly pain, and belly plenty. Eventually, hematuria, lowlevel proteinuria and progressive renal insufficiency develop. In the neonatal interval, 1/4 of those infants die, typically because of pulmonary hypoplasia caused by oligohydramnios (Potter sequence) and because the big size of the kidneys impairs lung improvement and performance. Children who survive the neonatal interval have varying onset and rate of progression of renal insufficiency as nicely as hepatic fibrosis with portal hypertension. Nephronophthisis is autosomal recessive, with onset in infancy, childhood or adolescence. Medullary cystic illness is autosomal dominant with onset in adolescence and renal failure in maturity. Atrophic tubules with markedly thickened and laminated basement membranes and lack of tubules out of proportion to glomerular loss are early histologic features of the disease. Eventually, corticomedullary cysts might develop, and the relaxation of the parenchyma turns into increasingly atrophic. Secondary glomerular sclerosis, interstitial fibrosis and nonspecific inflammatory infiltrates dominate the late histologic image. The gene product, fibrocystin, is found within the main cilia of the accumulating ducts of the kidney, biliary ducts of the liver and exocrine ducts of the pancreas, and it seems to be involved in regulation of cell differentiation, proliferation and adhesion. Interstitial fibrosis and tubular atrophy are common, significantly in children in whom disease presents later. The liver is normally affected by congenital hepatic fibrosis, with fibrous expansion of portal tracts with bile duct proliferation (see Chapter 20). Nephronophthisis is seen in three clinical variants: childish, juvenile and adolescent. The dilated cortical and medullary collecting ducts are arranged radially, and the exterior floor is clean. Symptomatic instances are usually found between the ages of 30 and 60 years, presenting with flank pain, dysuria, hematuria or "gravel" within the urine brought on by stone formation in the cysts. Increased glomerular capillary permeability allows loss of protein from plasma into the urine (proteinuria). Proteinuria is brought on by many different glomerular ailments and by a selection of mechanisms. Nephrotic syndrome outcomes from main glomerular illnesses unrelated to a systemic disease, or they may be secondary to a systemic disease that affects other organs as properly as the kidneys. Diabetic glomerulosclerosis is the most typical cause of secondary nephrotic syndrome in adults. Table 22-1 lists the main causes and approximate frequency of the primary nephrotic syndrome in adults and kids. Table 22-2 details selected pathologic options of a few of these illnesses (discussed below). There are necessary variations in the charges of specific glomerular diseases that cause nephrotic syndrome in adults versus these in kids. For instance, minimal-change disease is liable for most (70%) instances of main nephrotic syndrome in children, however only 15% in adults. They could additionally be solitary or a quantity of and are often discovered within the outer cortex, the place they bulge the capsule. After 5 years of dialysis, greater than 75% of sufferers present bilateral cystic kidneys. The cysts are initially lined by flat-to-cuboidal epithelium, however hyperplastic and neoplastic epithelial proliferation might develop inside 10 years of initiating dialysis. Nephritic (Glomerulonephritis) Syndrome Is an Inflammatory Disease with Hematuria, Proteinuria and Decreased Glomerular Filtration Rate Hematuria could also be microscopic or grossly visible, and proteinuria varies. Glomerular illnesses related to the nephritic syndrome are brought on by inflammatory adjustments in glomeruli. Injury to glomerular capillaries results in spillage of protein and blood cells into the urine (proteinuria and hematuria). The inflammatory damage may also impair glomerular circulate and filtration, leading to renal insufficiency, fluid retention and hypertension. Nephritic manifestations may (1) develop rapidly and end in reversible renal insufficiency (acute glomerulonephritis); (2) progress rapidly, with renal failure that resolves only with aggressive therapy (rapidly progressive glomerulonephritis); or (3) persist for years constantly or intermittently and proceed slowly to renal failure (chronic glomerulonephritis). Some glomerular illnesses are probably to trigger the nephrotic syndrome, however others result in the nephritic syndrome (Table 22-3). However, apart from minimal-change disease (which virtually at all times causes nephrotic syndrome), all glomerular illnesses could sometimes trigger combined nephritic and nephrotic manifestations that confound clinical diagnosis. Renal biopsy evaluation is the one technique of definitive diagnosis for most glomerular diseases, although clinical and laboratory knowledge may provide presumptive proof for a particular illness. Immune complexes that deposit from the circulation additionally activate complement and recruit inflammatory cells. Accurate pathologic diagnosis of glomerular ailments requires examination of renal tissue by light, immunofluorescence and electron microscopy, and integration of these findings with scientific data. Resultant immune complexes in glomerular capillary walls attract leukocytes and activate complement and other humoral inflammatory mediators, leading to inflammatory harm. Circulating immune complexes might deposit in glomeruli and incite irritation like that produced when immune complexes form in situ. For instance, circulating antibodies can bind to antigens released into the blood by bacterial or viral infection to produce immune complexes.
Tags: citalopram 20 mg order without a prescription, 20 mg citalopram generic with amex, effective 40 mg citalopram, discount citalopram 20 mg without a prescription, proven citalopram 20 mg, citalopram 40 mg free shipping, generic citalopram 40 mg with amex, buy generic citalopram 40 mg on-line, citalopram 20 mg generic overnight delivery, citalopram 40 mg order overnight delivery, 20 mg citalopram discount amex, 40 mg citalopram cheap with amex, buy cheap citalopram 40 mg on line, 40 mg citalopram generic, buy generic citalopram 20 mg on-line, citalopram 20 mg buy otc
10 of 10
Votes: 84 votes
Total customer reviews: 84
Customer Reviews
Quadir, 39 years: The bleeding diathesis is evidenced by cerebral hemorrhage, ecchymoses and hematuria.
Gancka, 51 years: Prostatic carcinoma normally arises from the peripheral glands, and compression of the urethra is a late clinical event.
Urkrass, 34 years: Complications of Myocardial Infarction the infarct, somewhat than only on the periphery.
Pavel, 41 years: Chronic narrowing of the vessel lumen: As an atherosclerotic plaque grows, it might slender the lumen, progressively decreasing blood move to tissue served by that artery.
Mojok, 29 years: A photomicrograph illustrates the attribute rosettes, formed by small, common, darkish tumor cells organized around a central, pale fibrillar core.
Tyler, 25 years: They are notably efficient in coping with particles with aerodynamic diameters underneath 2 m.
Leif, 58 years: A part of skin exhibits a giant cell in the middle, which accommodates a thick-walled, brown, sclerotic body (copper penny, arrow), representing the fungus.
