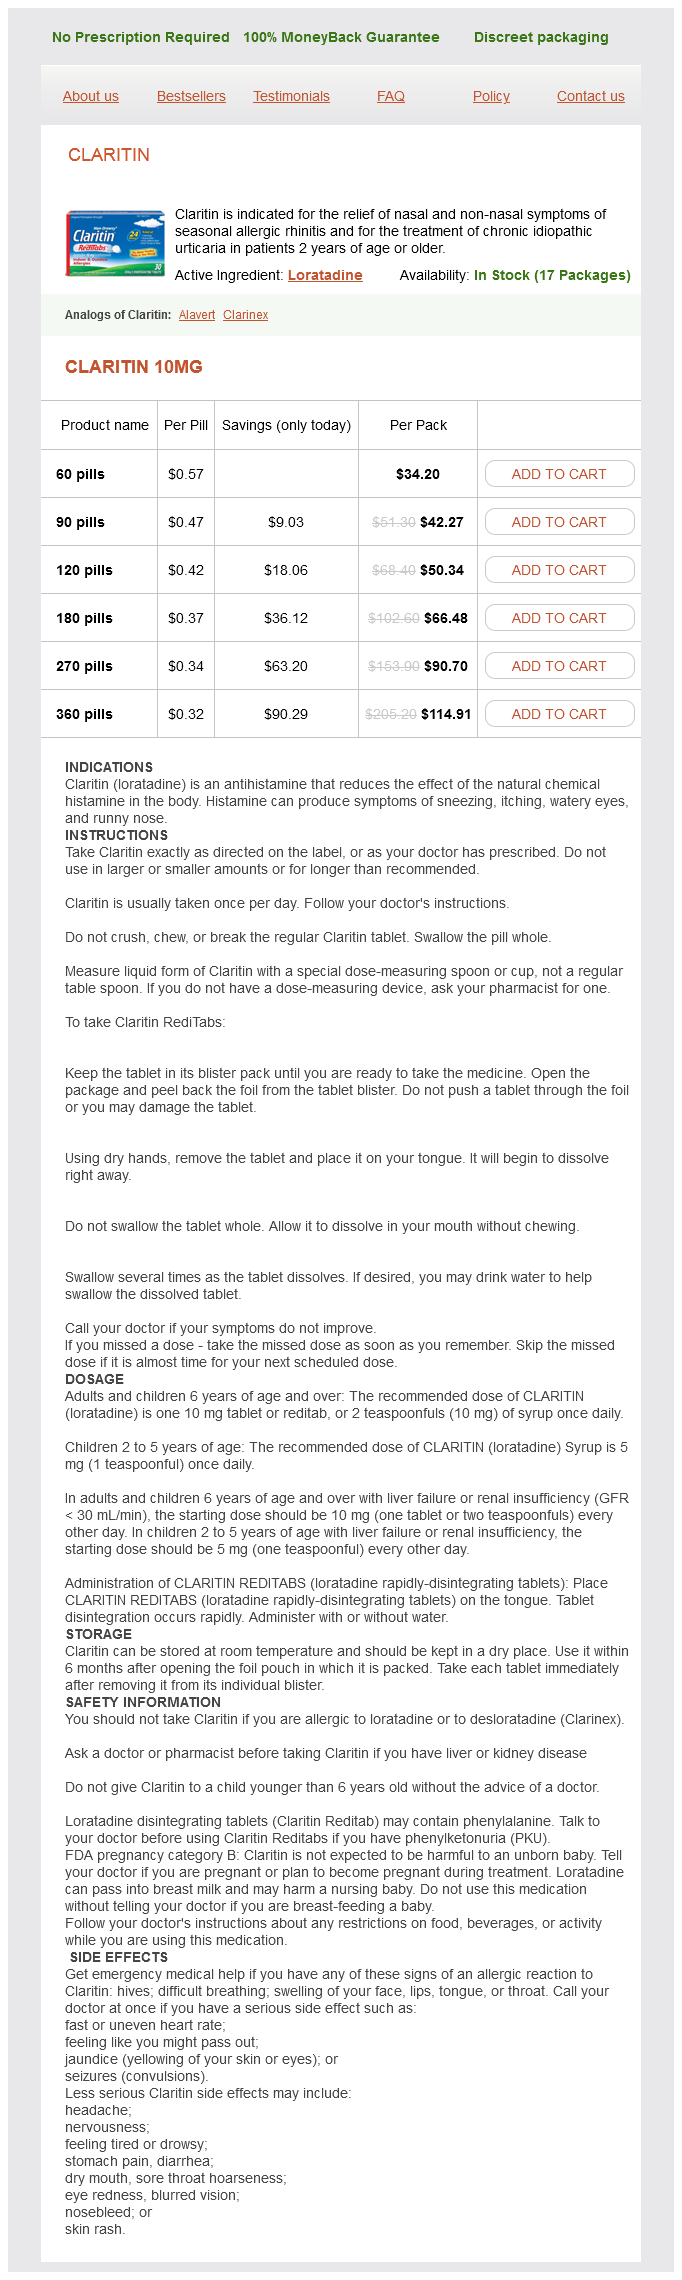
Claritin 10mg
- 60 pills - $34.20
- 90 pills - $42.27
- 120 pills - $50.34
- 180 pills - $66.48
- 270 pills - $90.70
- 360 pills - $114.91
Claritin dosages: 10 mg
Claritin packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 526
Only $0,34 per item
Description
The retromaxillary region is especially troublesome to access allergy symptoms for pollen claritin 10 mg buy generic, requiring a lateral strategy via the temporalis muscle area allergy weight gain generic claritin 10 mg online. In these cases allergy medicine not working for child claritin 10 mg order on-line, the squamous portion could also be attributable to radiation-induced malignancy allergy treatment during pregnancy discount 10 mg claritin with mastercard. In half, this is due to the challenges of treating dental tissues immediately with primary radiation therapy, significantly the maxilla with its limited gentle tissue coverage. Risk of osteoradionecrosis is excessive when main radiation is directed at these tissues. In addition, the relatively quick access to the oral cavity via transoral strategy permits for direct surgical extirpation. The degree and strategy to ablative surgical procedure of the maxilla thus can be highly individualized based on detailed understanding of the complicated three-dimensional structure to be addressed. Of course, margins are also required in all dimensions, taking into account complicated saddle relationships that are troublesome to conceptualize, orient, and catalogue. Surgical strategy must allow adequate publicity of important structures with care taken for ultimate cosmesis after closure. Truitt and coauthors have categorized surgical management of onerous palate malignancies as consisting of alveolectomy, palatectomy, and infrastructure maxillectomy, all feasible via the oral aperature. Hard palate and dental tissues that permit for mastication and forestall sinonasal penetration can be maintained in some instances. Partial maxillectomy with preservation and primary repair of the exhausting palate mucosa has been described for highly select tumors of the maxilla. Sacrifice of the anterior midline maxilla supporting the nasal vomer and septum can 227 Primary Malignancies of the Maxilla cause tip collapse. Orbital floor and rim are important to each appearance of the orbit as properly as ocular function. Surgical strategy may be divided into transoral and transfacial options and could additionally be supplemented with endoscopic endonasal or intrasinus visualization. A number of facial incisions have been designed to allow publicity with maintenance of acceptable cosmesis. These incisions utilize shadows, creases and grooves, or corners to allow scar to disguise or blend while preserving anatomical subunits, muscular continuity and performance, and sensation as a lot as possible. In basic, tumors that approach the orbital rim, lacrimal sac, medial canthus, or anterior ethmoid/frontal recess are more probably to require a transfacial part. Facial incisions can split the higher lip in midline or along a filtrum ridge with acceptable operate and look after restore. A group of oral maxillofacial surgeons from China recently reported satisfactory exposure and cosmesis using a lateral lip-splitting method for access to the maxilla. They preserve that "most of the 36 sufferers thought their results have been good or truthful. Removal of portions of the specimen sequentially requires that the surgeon remember the unique and evolving relationships of tumor and normal borders in order not to miss a element of tumor, whereas speaking clearly with the pathologist as to the true margin edges for sampling and analysis. This method additionally requires consideration to integrity of thorough communication and reporting of margins between the surgeon and pathologist. A transfixion incision between the lower lateral and septal cartilages (a) is connected to an incision just below the higher lateral cartilage (b) and completed with incisions within the pyriform aperture and nasal ground (c). Blunt elevation of sentimental tissue from the nasal dorsum via the incision in the nasal dome and over the higher lateral cartilage frees the dorsal soft tissue on both sides (d). Local injection into the descending palatine foramen of the palate, the posterior facet of the inferior meatus of the nose where the sphenopalatine artery is situated, and in oral and nasal mucosa is also recommended. Options for quick administration include gauze packing, placement of short-term obturator, or instant flap reconstruction. Vaseline and antibiotic-impregnated gauze packing can be conformed to the sinonasal defect and suspended in place with a "spider web" of silk suture placed across the perimeter of the defect. This permits instant oral alimentation with minimal discomfort while the packing is in place. We usually leave the packing for 5 to 7 days, throughout which period prophylactic oral antibiotic is provided. When packing is eliminated, an extra measure for managing the defect have to be in view. A quick and cheap different to gauze packing is the usage of comformable thermoplastic (Aquaplast) substance9 which can be conformed to the remaining skeletal and dental components, and suspended with wire to the zygoma or with suture to soft tissue. If a dental prosthodontist is part of the group, a more formal obturator may be used. The prosthesis could be customary before surgical procedure by taking impressions and planning with the ablative surgeon on how much alveolus and dentition will stay for securing the obturator. The deep positioning of the internal maxillary artery branches necessitates that some bone cuts be made earlier than direct ligation of the distal finish is feasible. The facial tissues have a very rich blood supply, and so blood loss have to be anticipated and prepared for both mentally and practically with blood substitute readily available. Preparation of soppy tissues the place bleeding could also be diminished with vasoconstrictive local injection ought to be undertaken as a lot as possible earlier than starting the osteotomies. Lateral nasal wall cuts may be accomplished with scissors via ethmoid sinus and maxillary fontanelle (c). The obturator is then clipped to remaining teeth with clasps incorporated into its design. Wires to bony parts similar to pterygoid plates or zygoma, or lag screws to remaining hard palate and vomer complete the fixation. After 1�2 weeks, the obturator is eliminated and a sequence of adjustments made by the prosthodontist for comfort and fixing the seal of the gadget. Fabrication of the final obturator is postponed till the cavity has had time to mature and reach its last endpoint of form and measurement. Most authors keep that this remark is opposite to the prevailing sense of danger held by clinicians who choose metastases to be less prone to come from a roof of mouth major. The regional metastases were operable in most (85%) cases, main the authors to opine that "watchful waiting was possible on this cohort. This group who had elective neck surgery experienced a decrease price of subsequent neck recurrence and higher 5-year and total survivals, leading the authors to recommend elective neck dissection at the time of primary therapy in advanced T stage cases. As expected, early stage tumors have a relatively higher probability of 5-year survival (50�82% T1, T2 versus 17�49% T3, T4). Both the Toronto and Memorial Sloan Kettering teams have asserted that voice high quality and consuming function can be fairly good on this circumstance. The soft palate must be ready to create a seal with the prosthetic without irritation of the tissue to stop nasal regurgitation. A longer prosthetic protruding more posteriorly is harder to tolerate with out gagging. The presence of less than half of the hard palate causes issue in retention of the prosthesis during maxillary activity. Implants or wire clasps to remaining enamel might help in this regard, however without some base of assist above the prosthesis on the surgically resected facet, proper positioning of the obturator may be difficult to preserve. Key Points Detailed knowledge of the three-dimensional anatomy of the maxilla is critical to planning and accurately executing illness extirpation. Rehabilitation with restoration of the roof of the mouth requires a multidisciplinary group including free tissue transfer and/or prosthodontist. Frank tumor erosion with extension into the maxillary sinus or nasal flooring identifies sufferers with superior T4 illness and poorest prognosis. Differential prognosis of tumours of the minor salivary glands of the palate by computed tomography. Preservation of palatal mucoperiosteum for oronasal separation after whole maxillectomy. Cervical metastasis from squamous cell carcinoma of the maxillary alveolus and hard palate. Management of the neck and regional recurrence in squamous cell carcinoma of the maxillary alveolus and onerous palate compared with other websites within the oral cavity. Cervical metastasis in squamous cell carcinoma of the exhausting palate and maxillary alveolus. Risk factors have an result on the survival outcome of onerous palatal and maxillary alveolus squamous cell carcinoma: 10-year review in a tertiary referral middle.
Wild Cherry (Sweet Cherry). Claritin.
- Are there safety concerns?
- Dosing considerations for Sweet Cherry.
- What is Sweet Cherry?
- Arthritis, gout, preventing cancer, and preventing heart disease.
- How does Sweet Cherry work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97086
This design merely measures the anteroposterior and dorsoventral defects in the minimally protruded tongue allergy medicine for 8 year old claritin 10 mg order visa. The flaps historically used for this extent of reconstruction are outlined in Table sixteen allergy treatment malayalam claritin 10 mg generic online. This flap is inset from the bottom of the tongue to the anterior mouth allergy forecast huntsville tx proven claritin 10 mg, which varieties a "cash pouch�like" shape allergy gold filter cleaning claritin 10 mg cheap. This design allows for the neotongue to be in contact with the onerous palate when the mouth is closed. This design includes harvesting a skin paddle to reconstruct the neotongue with the harvest of a de-epithelialized second paddle to fold underneath the cutaneous portion to enhance volume. Regardless of the flap choice, the most important consideration with flap design is to produce a protuberant tongue. It was concluded that flaps must be designed 30% larger than the defect and the larynx should be resuspended to prevent flap prolapse and reduce the danger of aspiration. Restoration of tongue bulk and mobility of the tongue is paramount to successful reconstruction of a hemiglossectomy defect. The introduction of the biolobed, sensate radial forearm flap by Urken and Biller with the addition of vascularized subcutaneous fat if necessary primarily based on the scale of the defect provides sufficient bulk, and it has a flooring of mouth part that forestalls tethering of the tongue. A rectangle template for hemiglossectomy defects incorporates the rules of the biolobed flap into a easy design without any concern for partial flap necrosis from devascularization. However, a majority of these sufferers had T1 or T2 lesions, and there was no assessment of swallowing operate. However, a retrospective review of 50 patients that had submental flaps for oral cavity reconstruction demonstrated a 10% occult metastatic node rate in degree 1 with no native recurrences. Although not discovered in this examine, it ought to be famous that peripheral and complete necrosis of the supraclavicular artery island flap has been reported. There is proof that reinnervation of sensory nerves from the flap to the lingual nerve improves sensation. Speech and swallowing function postreconstruction is likely predominately mediated by the amount of native tongue sacrificed and the ultimate volume of the reconstruction somewhat than a return to baseline sensation. It is difficult to extrapolate significant conclusions with such small sample sizes and lack of a control group. Our protocol for freeflap reconstruction is for flap checks each hour for the first 24 hours, every 2 hours for the second 24 hours, and every four hours thereafter. Pedicled regional flaps require no monitoring, and have been proven to have decreased hospital keep in comparison with free-flap reconstruction. Patients with free-flap reconstruction usually are hospitalized for five to 10 days relying on the type of reconstruction and their capacity to safely ingest an oral diet. Subsequent posthospital care involves native wound care to free flap and local flap donor websites and continued work with speech-language pathology for speech and swallow rehabilitation. This is predominately as a outcome of the split-thickness skin graft used to cowl the forearm defect with dehiscence of the graft overlying the flexor carpi radialis tendon. The acceptable reconstructive choice should contemplate functional end result, patient comorbidities in relation to operative time, and potential donor website morbidity. The ideas of oral tongue reconstruction, including restoration of enough volume for premaxilla, palatal, and pharyngeal contact of the reconstructed tissue, must be followed. Reinnervation of flaps improves sensation; nevertheless, the functional implications are yet to be identified. Microvascular reconstruction of the tongue utilizing a free anterolateral thigh flap: three-dimensional evaluation of quantity loss after radiotherapy. A systematic strategy to practical reconstruction of the oral cavity following partial and complete glossectomy. Analysis of the relations between the form of the reconstructed tongue and postoperative capabilities after subtotal or complete glossectomy. Individual design of the anterolateral thigh flap for useful reconstruction after hemiglossectomy: expertise with 238 patients. Functional reconstruction of swallowing and articulation after total glossectomy without laryngectomy: money pouch-like reconstruction method utilizing rectus abdominis myocutaneous flap. Modification of flap design for whole cell tongue reconstruction using a delicate antero-lateral thigh flap. A new flap design for tongue reconstruction after whole or subtotal glossectomy in skinny patients. Quality of life in patients after resection of pT3 lateral tongue carcinoma: microvascular reconstruction versus primary closure. Swallowing function in patients who underwent hemiglossectomy: comparison of major closure and free radial forearm flap reconstruction with videofluoroscopy. Submental island pedicled flap vs radial forearm free flap for oral reconstruction: comparability of outcomes. Oncologic safety of the submental flap for reconstruction in oral cavity malignancies. Functional comparability after reconstruction with a radial forearm free flap or a pectoralis main flap for most cancers of the tongue. Pedicled supraclavicular artery island flap versus free radial forearm flap for tongue reconstruction following hemiglossectomy. Usefulness of supraclavicular flap in reconstruction following resection of oral cancer. Microvascular free tissue switch for tongue reconstruction after hemiglossectomy: a useful evaluation of radial forearm versus anterolateral thigh flap. Radial forearm versus anterolateral thigh flap reconstruction after hemiglossectomy: useful assessment of swallowing and speech. Comparison of morbidity after reconstruction of tongue defects with an anterolateral thigh cutaneous flap compared with a radial forearm free-flap: a meta-analysis. Motor and sensory morbidity related to the anterolateral thigh perforator free flap. True practical reconstruction of whole or subtotal glossectomy defects utilizing a chimeric anterolateral thigh flap with each sensorial and motor innervation. Oral sensation and performance: a comparability of patients with innervated radial forearm free flap reconstruction to healthy matched controls. Its lack of a bodily barrier permits early invasion to lymphatics and adjacent neurovascular structures. The limited surgical access, coupled with the small space enhance the likelihood of optimistic margins, and the propensity for cervical metastases make this area difficult for surgeons. Keywords: ground of the mouth most cancers, oral cavity most cancers, squamous cell carcinoma, method to floor of the mouth, mandibulotomy, mandibulectomy, mandibular invasion 17. This could be readily achieved underneath native anesthetic, adopted by a punch biopsy of the edge of the tumor and normal tissue. A thorough history and examination should be performed in all these sufferers, beginning with an inquiry in regards to the presenting signs including pain, paresthesia, ear pain, dysphagia, odynophagia, voice change, dysarthria, trismus, bleeding, weight loss, lower lip/chin numbness, unfastened dentition, and preexisting dentures. This must be adopted by particular questions about their previous medical historical past and surgical history, allergies, social network and assist, tobacco use, and alcohol consumption. These elements all affect the preoperative counseling and optimization of patients. It is our follow to routinely refer sufferers with 10% weight loss to a dietitian for optimization of diet prior to surgery. These factors additionally significantly influence the postoperative administration of the affected person when it comes to rehabilitation and progression through to adjuvant therapies including radiotherapy and chemotherapy. A thorough examination, specifically, with bimanual palpation of the lesion should be attempted to verify the size. Laterally, fixation of the tumor through involvement of the periosteum may point out underlying involvement of the mandible. The medial extent of the tumor edge must also be evaluated, focusing on the extent of involvement of the oral tongue. Loose dentition, particularly, adjacent to the tumor must be noted for potential invasion of the mandible. Trismus should also be noted as it will influence the selection of surgical access, which shall be mentioned later. The neck ought to then be systematically examined for the medical willpower of regional unfold. Flexible laryngoscopy should be routinely performed to evaluate for potential posterior extension of the tumor, synchronous primaries, and the status of the airway.
Specifications/Details
Reconstruction of the onerous palate using the radial forearm free flap: indications and outcomes allergy season cheap 10 mg claritin amex. Comparison of useful and qualityof-life outcomes in sufferers with and without palatomaxillary reconstruction: a preliminary report allergy treatment 4th claritin 10 mg cheap with amex. Use of the buccal fats pad in the reconstruction and prosthetic rehabilitation of oncological maxillary defects allergy treatment for mold claritin 10 mg order fast delivery. Osseocutaneous radial forearm free tissue switch for repair of complex midfacial defects allergy guidelines 2015 quality 10 mg claritin. The radial forearm osteocutaneous "sandwich" free flap for reconstruction of the bilateral subtotal maxillectomy defect. Zygomaticmaxillary buttress reconstruction of midface defects with the osteocutaneous radial forearm free flap. Functional dental rehabilitation of huge palatomaxillary defects: circumstances requiring free tissue transfer and osseointegrated implants. Maxillary reconstruction can involve a range of options, spanning native and pedicled flaps as well as gentle tissue or composite free flaps. Surgical sequelae of maxillary reconstruction of extensive defects typically ends in suboptimal useful and aesthetic outcomes which require acceptable counseling and infrequently necessitate revision procedures. Microvascular free flap reconstructive choices in patients with partial and complete maxillectomy defects. Structural pillars of the facial skeleton: an strategy to the management of Le Fort fractures. Prosthodontic guidelines for surgical reconstruction of the maxilla: a classification system of defects. A 15-year review of midface reconstruction after total and subtotal maxillectomy: half I. Accuracy and reproducibility of virtual chopping guides and 3D-navigation for osteotomies of the mandible and maxilla. The angular branch of the thoracodorsal artery and its blood supply to the inferior angle of the scapula: an anatomical study. Scapular flap for maxillectomy defect reconstruction and preliminary results utilizing three-dimensional modeling. Scapular angle osteomyogenous flap in postmaxillectomy reconstruction: defect, reconstruction, shoulder perform, and harvest method. Osseointegrated implants: a comparative research of bone thickness in four vascularized bone flaps. Vascularized bone flaps in oromandibular reconstruction: a comparative anatomic study of bone stock from various donor sites to assess suitability for enosseous dental implants. Scapular free vascularised bone flaps for mandibular reconstruction: are dental implants attainable Maxillary reconstruction using the scapular tip free flap: a radiologic comparability of 3D morphology. Successful reconstruction of irradiated anterior cranium base defect using the twin flap technique involving local pericranial flap and radial forearm free flap. Complications of craniofacial resection for malignant tumors of the skull base: report of a global collaborative examine. Reconstruction of lateral skull base oncological defects: the position of free tissue switch. Usefulness of the anterolateral thigh flap with vascularized fascia lata for reconstruction of orbital ground and nasal floor after total maxillectomy. Beavertail modification of the radial forearm free flap in base of tongue reconstruction: method and useful outcomes. Byrne Summary the reconstruction of oral cavity defects following most cancers resection can prove difficult. The shut spatial relationships between distinct tissue varieties found within the oral cavity can allow invasive malignancies to span multiple subsites. In these instances, reconstructive methods that restore anatomic kind in addition to the specialized and coordinated operate of each subsite are important for success. Patient selection, preoperative planning, operative method, and postsurgical care all significantly affect the last word success of multisite reconstruction of the oral cavity. This article will talk about the relevant challenges and potential solutions concerned within the repair of these defects. Keywords: oral cavity, carcinoma, squamous cell carcinoma, lip, tonsil, gingiva, palate, tongue, retromolar trigone, buccal, mucosa, salivary gland, pharynx, alveolus, floor of mouth, free flap, skin graft, native flap Evaluation of the patient by the reconstructive team attempts to assess the extent of the illness, predict the anticipated defect, and create a plan for restore. The guiding ideas described by Millard and Gillies "to switch like with like" and to "consider reconstruction in phrases of models" are notably relevant in instances with multisite involvement. Keeping these tenets in thoughts will help to type through the various reconstructive options and present the sufferers with the most appropriate for their particular needs. A cautious dialog about all choices, including a discussion of the dangers and benefits inherent to each, is crucial for proper informed consent. The associated donor site morbidities, the need for additional procedures, and the timeline for recovery ought to be outlined. The risk of postoperative functional and/or aesthetic deficits ought to be addressed in order that expectations can be managed appropriately. Ancillary testing similar to angiography to assess peripheral vascularity may be thought-about if free tissue transfer is necessary in the setting of peripheral vascular disease. The total nutrition status of the patient can be assessed by way of history, session with a nutritionist, or laboratory values such as albumin and pre-albumin that can indicate malnutrition. A swallow assessment by a speech and language pathologist is important to detect dysphagia that may cause aspiration. Assuming a surgical treatment is indicated and the patient is medically match to withstand an operation, an intensive examination of the oral cavity will help to determine one of the best reconstructive plan. The highly specialized structures and distinct tissue types liable for these features are in close proximity and share tissue planes that reach across subsite boundaries. For this purpose, invasive malignancies are likely to contain multiple oral cavity subsites. Surgical resection can subsequently be expected to produce complicated and multifaceted defects that require careful planning and execution by the reconstructive surgeon. The innovative architect Frank Lloyd Wright wrote in 1949 that "form and performance thus become one in design and execution if the character of supplies and strategies and functions are all in unison. This article will discuss surgical considerations important in the reconstruction of multisite oral cavity defects with this objective in mind. Furthermore, the significance of acquiring adverse surgical margins for oncologic management will essentially result in a defect bigger than the dimensions of the tumor itself. Intraoperative findings corresponding to perineural involvement, metastatic lymphadenopathy, adherence to adjoining structures, or findings of 243 Reconstruction of Multisite Defects surprising development can even result in defects larger than anticipated. The idea of field cancerization represents a situation during which several tumor cells exist over a large mucosal space, with potential segments of normal-appearing tissue in between. Despite these uncertainties, "observation remains the basis of surgical diagnosis," and a scientific and careful examination of each subsite will finest inform the reconstructive plan. It consists of both the first and secondary palate, that are separated by the incisive foramen. Inspection and palpation of the palate is important because though ulcerative or exophytic masses are simply seen, minor salivary gland carcinomas come up submucosally and can be coated by normal-appearing mucosa. Palatal hypoesthesia might point out perineural invasion by way of the sphenopalatine or pterygopalatine fossae. Anterior midline hard palate lesions may appear isolated however lateral or posterior lesions may involve adjacent subsites together with the alveolar ridges, gingiva, maxilla, or pterygoid house. Floor of Mouth the ground of mouth represents a U-shaped mucosal lined house situated beneath the anterior ventral tongue and increasing ahead to the mandibular gingiva. Deep to this house, the mylohyoid muscle varieties a sling which separates the floor of mouth from the submandibular and submental areas. Sublingual folds of redundant mucosa as well as submucosal sublingual veins are discovered lateral to the frenulum. The ground of mouth extends posterolaterally adjoining the inferior lateral tongue and terminating at the anterior tonsillar pillar. Palpation of cellular mandibular segments may recommend pathologic fracture if tumor invasion of the mandible is present. Loose enamel or edentulous areas adjoining to the primary tumor or agency and stuck lesions involving the gingiva or ground of mouth mucosa alongside the mandible are indicators for probable bony invasion. Paresthesia of the chin might suggest tumor infiltration of the inferior alveolar nerve.
Syndromes
- The developing baby to move in the womb, which allows for proper bone growth
- 0 - 6 months: 400 micrograms per day (mcg/day)
- Loss of movement or feeling in the legs or feet
- Short fingers
- Convulsions
- Hematoma (blood accumulating under the skin)
- You constantly feel as though there is a something in your eye
- Diarrhea
Related Products
Additional information:
Failure to progress with a laparoscopic strategy or a vessel damage with uncontrollable haemorrhage requires conversion to an open method allergy symptoms in january claritin 10 mg without prescription. Postoperatively allergy air purifier claritin 10 mg discount otc, the bowel could turn into entrapped within the trocar sites or there may be bleeding from the sheath web site allergy forecast hutto tx quality claritin 10 mg. An acute hydrocele can develop because of allergy shots and xanax order 10 mg claritin mastercard irrigation fluid accumulating within the scrotum. Occasional � Infection, ache, or hernia of the incision, requiring additional treatment. Very uncommon � Recognized (and unrecognized) injury to organs or blood vessels, requiring conversion to open surgery or deferred open surgical procedure. Very rare � Need to take away the kidney at a later time because of harm caused by recurrent obstruction. Alternative therapy Observation, telescopic incision, dilatation of the area of narrowing, momentary placement of a plastic tube through the narrowing, conventional open surgical approach. Laparoscopic simple nephrectomy Occasional � Short-term success charges are just like open surgery, however long-term results unknown. Laparoscopic radical nephrectomy Occasional � Short-term success rates are much like open surgery, however long-term outcomes unknown. Alternative remedy Observation, embolization, chemotherapy, immunotherapy, typical open surgical method. Many stones of <4cm in diameter could be removed endoscopically, but the higher the quantity and size of the stones, the more inclined will the surgeon be to adopt an open approach. Having said this, when you anticipate that the patient is prone to develop recurrent stones, and due to this fact would require multiple future procedures to remove them, then try to keep away from open surgery as a end result of every redo open cystolithotomy might be more difficult (due to the presence of scar tissue). Post-operative care A catheter is left within the bladder for a day or so, since haematuria is common, particularly after fragmentation of large stones. Common post-operative issues and their administration Haematuria Requiring bladder washout or return to theatre is uncommon. Grasping the bladder wall within the jaws of the stone forceps or punch is easily accomplished and might cause perforation. Very rare � Perforation of the bladder, requiring a brief urinary catheter or return to theatre for open surgical repair. If it stays black, take away it, having ligated the spermatic twine with a transfixion sew of absorbable materials. If the testis bleeds actively, it must be salvaged (close the small wound with an absorbable suture). Fixation technique Some surgeons repair the testis throughout the scrotum with suture material, inserted at three points (3-point fixation). Those who use the latter argue that absorbable sutures may disappear, exposing the affected person to the chance of retorsion. The sutures should move via the tunica albuginea of the testis and then via the parietal layer of the tunica vaginalis lining the inner surface of the scrotum. Others say the testis ought to be mounted within a dartos pouch,2 arguing that suture fixation breaches the blood�testis barrier, exposing both testes to the risk of sympathetic orchidopathia (an autoimmune response attributable to the development of antibodies towards the testis). For dartos pouch fixation, open the tunica vaginalis; convey the testis out, and untwist it. Develop a dartos pouch within the scrotum by holding the pores and skin with forceps and dissecting with scissors between the skin and the underlying dartos muscle. Use a number of absorbable sutures to connect the wire close to the testis to the within of the dartos pouch to forestall retorsion of the testes. The dartos may then be closed over the testis, and the pores and skin may be closed in a separate layer. Post-operative care and potential problems and their management As for all procedures involving scrotal exploration, a scrotal haematoma may end result, which may need to be surgically drained. Alternative therapy Observation-risks lack of testis and autoimmune reaction, resulting in subfertility and loss of hormone manufacturing within the remaining testis. Drug administration can due to this fact be controlled by altering the electric current depth. The two main electrokinetic principles are: iontophoresis (transport of ionized molecules into tissue by making use of a present throughout a solution containing the ions. Relative contraindications Active an infection of the decrease genitourinary tract, protrusion of the enlarged median lobe of the prostate into the bladder, urethral stricture, bladder neck stenosis. The urothelium consists of multilayered transitional epithelium, with numerous tight junctions that render it impermeable to water and solutes. The bladder base is called the trigone-a triangular space with the 2 ureteric orifices and the internal urinary meatus forming the corners. Intravesical stress throughout filling is low as a end result of reciprocal relaxation in a bladder with regular compliance. The main excitatory motor enter to the bladder is from the autonomic nervous system and is predominantly parasympathetic innervation (S2�4). Sympathetic innervation (T10�L2) via the hypogastric plexus plays a task in urine storage (see E p. Urethra the bladder neck (and posterior urethra) is often closed during filling. It consists of circular clean muscle (with sympathetic innervation) and can additionally be referred to as the interior sphincter. The clean muscle element of the sphincter has myogenic tone and receives excitatory and inhibitory innervation from the autonomic nervous system. Inhibition of somatic enter relaxes the exterior striated sphincter muscle, and sympathetic inhibition causes coordinated bladder neck smooth muscle (internal sphincter) leisure. Micturition is stimulated by exercise within the parasympathetic (pelvic) nerves and inhibited by activity within the sympathetic (hypogastric) nerves and pudendal nerves. The calyx draining each papilla is named a minor calyx, and a quantity of other minor calyces coalesce to type a significant calyx, a quantity of of which drain into the central renal pelvis (fig. The renal artery, which arises from the aorta at vertebral degree l1/2, branches to kind interlobar arteries which, in turn, type arcuate arteries after which cortical radial (interlobular) arteries, from which the afferent arterioles are derived. The capillaries drain into venous channels which drain into interlobular veins, then arcuate veins, ultimately draining into the renal vein via interlobar veins. Anatomical relations of the kidney � anterior relations of the right kidney are, from prime to bottom, the adrenal (suprarenal) gland, liver, and hepatic flexure of the colon. Medially and anterior to the proper renal pelvis is the second a part of the duodenum. The anterior relations of the left kidney are, from high to backside, the adrenal gland, stomach, spleen, and splenic flexure of the colon. Blood is delivered to the glomerular capillaries by an afferent arteriole and drained by an efferent arteriole. The loh generates hypertonicity; its descending limb is just permeable to water, whereas its ascending limb is just permeable to solutes. The clearance ratio for a substance signifies the amount of energetic reabsorption or excretion. Where a substance is both filtered at the glomerulus and secreted by the renal tubules, its clearance will be higher than the gfR. Where a substance is filtered on the glomerulus however reabsorbed by the renal tubules, its clearance will be less than the gfR. Of observe, serum creatinine is an insensitive marker of early renal impairment, because the gfR must fall below 60�80ml/min earlier than a rise in creatinine is seen. Combined blood flow within the two renal veins is about 1299ml/ min, and the difference in circulate rates represents the urine manufacturing price. The function of the kidney is regulation of the quantity and composition of eCf by constant adjustment of solutes and water to maintain a normal focus. During conditions of water extra Body fluids become hypotonic, and aDh release and thirst are suppressed. During conditions of water deficit Body fluids are hypertonic, and aDh secretion and thirst are stimulated. The capability to concentrate or dilute urine is dependent upon the countercurrent multiplication system within the loh. Children have a circadian rhythm in aDh secretion high at night and low in the course of the day. Conversely, when blood volumes are i, sympathetic activity and aDh secretion are suppressed and NaCl excretion is enhanced (natriuresis).
Usage: t.i.d.
Adjuvant treatment for oral most cancers is covered in additional element in Chapter 35 and 36 allergy testing jersey channel islands claritin 10 mg sale. Treatment is primarily surgical and sometimes requires reconstruction and adjuvant therapy allergy shots diarrhea order 10 mg claritin. Early allergy shots cause rheumatoid arthritis claritin 10 mg low cost, aggressive swallowing rehabilitation is suggested to mitigate late dysphagia allergy relief natural generic claritin 10 mg on line. The global incidence of lip, oral cavity, and pharyngeal cancers by subsite in 2012. Clinicopathologic analysis of prognostic elements for squamous cell carcinoma of the buccal mucosa. Prognostic components in sufferers with buccal squamous cell carcinoma: 10-year expertise. Squamous cell carcinoma of tongue and buccal mucosa: clinico-pathologically totally different entities. Positive surgical margins in early stage oral cavity most cancers: an evaluation of 20,602 cases. Cancer of the buccal mucosa: are margins and T-stage correct predictors of native control Squamous cell carcinoma of the buccal mucosa: outcomes of treatment in the trendy era. Malignant transformation of oral submucous fibrosis: overview of histopathological elements. Malignant transformation of oral lichen planus and oral lichenoid lesions: a meta-analysis of 20095 affected person information. Potentially malignant issues revisited-The lichenoid lesion/proliferative verrucous leukoplakia conundrum. What is the function of elective neck dissection within the treatment of patients with buccal squamous cell carcinoma and clinically unfavorable neck findings Outcome and cervical metastatic unfold of squamous cell most cancers of the buccal mucosa, a retrospective evaluation of the previous 25 years. Carcinoma of the buccal mucosa: analysis of scientific presentation, consequence and prognostic factors. Skin involvement and ipsilateral nodal metastasis as a predictor of contralateral nodal metastasis in buccal mucosa cancers. Predictors of locoregional recurrence in early stage buccal cancer with pathologically clear surgical margins and adverse neck. Head and neck cancer: main modifications within the American Joint Committee on Cancer Eighth Edition most cancers staging handbook. Oral cavity squamous cell carcinoma: position of pretreatment imaging and its influence on management. Patterns of cervical lymph node metastases from squamous carcinomas of the upper aerodigestive tract. Setting the stage for 2018: how the adjustments in the American Joint Committee on Cancer/Union for International Cancer Control Cancer Staging Manual Eighth Edition influence radiologists. Definitive chemoradiation for locallyadvanced oral cavity most cancers: a 20-year expertise. In-continuity neck dissection: long-term oncological outcomes in squamous cell carcinoma of the buccal mucosa. A retrospective evaluation of squamous carcinoma of the buccal mucosa: an aggressive subsite inside the oral cavity. Buccal mucosa elasticity influences surgical margin willpower in buccal carcinoma resection. Clinicopathological examine of surgical margins in squamous cell carcinoma of buccal mucosa. Post-operative radiotherapy in carcinoma of buccal mucosa, a potential randomized trial. Systematic evaluation of the current proof in the use of postoperative radiotherapy for oral squamous cell carcinoma. Surgery versus surgical procedure and postoperative radiotherapy in squamous cell carcinoma of the buccal mucosa: a comparative research. Eisele, and Carole Fakhry Summary Reconstruction of the buccal region following tumor resection poses a unique challenge with important aesthetic and useful issues. The buccal region plays a serious position in mouth opening, chewing, swallowing, speech, as nicely as facial movement. The optimal reconstructive method is largely based on the scale of the first defect. Smaller defects could additionally be closed primarily or with a local flap, whereas bigger defects could require a regional or free flap to preserve function. There are a number of nonoperative in addition to operative therapies for trismus, with microvascular free tissue switch playing an essential position in creating long-lasting enchancment in mouth opening. Keywords: buccal defects, oral vestibular reconstruction the arterial provide of the buccal regions is derived from the buccal department of the inner maxillary artery in addition to the facial artery. Sensory innervation is provided by branches of the maxillary and mandibular branches of the trigeminal nerve. The parotid duct exits from the anterior aspect of the parotid gland and courses superficial to the masseter muscle. In easy terms, the buccal mucosa serves as a passive barrier that helps enclose the oral cavity and, in conjunction with the action of the lips, prevents leakage of saliva and different oral contents. The capability to seal the oral cavity can be necessary to generate a optimistic air stress gradient for plosive speech and a adverse strain gradient for sucking. The muscular tissues of facial features, along with undertaking their namesake, are involved in the transit of food throughout mastication and deglutition. Facial reanimation, because it pertains to the buccal area, is due to this fact an important consideration for reconstruction of buccal defects that involve the facial musculature and nerve branches. Specific techniques for facial reanimation, nevertheless, are beyond the scope of this chapter. One of the most typical useful consequences of surgical resection and reconstruction for buccal cancer is the development of trismus, outlined as a mouth opening limited to 35 mm or less. By itself, trismus might contribute to problem with oral consumption, chewing, swallowing, talking, as properly as dental points from poor oral hygiene. Functionally, the buccal region performs a vital position in oral section swallowing, speech, mastication, and facial motion. Facial expression, together with the contour of the face and look of the oral commissure, can even introduce aesthetic complexities in reconstruction. Successful reconstruction of the buccal area is aimed at restoring a barrier that encloses the oral cavity whereas supporting the practical and aesthetic elements listed above. Each of these elements must be considered in characterizing a defect and planning for an acceptable reconstruction the muscles of facial features in the buccal area embrace the orbicularis oris, risorius, zygomaticus main and minor, buccinator, and depressor anguli oris. Squaquara et al classify the dimensions of intraoral defects into small (4 cm diameter), medium (7 cm diameter), and enormous (> 7 cm diameter). However, with growing defect diameter and soft-tissue involvement, the chance of trismus will increase. However, it offers minimal bulk and can retract considerably, making it unsuitable for medium or massive defects. It is designed simply anterior to the parotid duct and consists of mucosa, submucosa, part of the buccinator muscle, the facial artery, and a wealthy submucous venous plexus. These flaps are usually versatile and reliable, however require a second-stage surgery, because the flap pedicle tethers the tongue and should be divided after the preliminary inset. During the postoperative interval, trauma to the pedicle can happen from the teeth, in addition to excessive motion of the tongue. Dysarthria can additionally be a potential sequela, although this can usually be averted if the mobility of the tongue tip is maintained. The use of a posteriorly based mostly buccinator musculomucosal flap has also been reported. Excessive harvesting of buccal mucosa, nevertheless, might result in trismus in addition to harm to the parotid duct. Both flaps could be harvested either as muscle alone or as a musculocutaneous flap, and are based mostly off of the submental artery. The submental flap is designed throughout the midline in the submental area, and can be utilized to reconstruct full-thickness defects of the cheek. If pores and skin is included, the affected person ought to be counseled on the potential for improvement of intraoral hair. In contrast, the island platysma flap is designed over a hairless space at the distal side of the sternocleidomastoid muscle.
Tags: generic claritin 10 mg visa, 10 mg claritin best, claritin 10 mg cheap without prescription, claritin 10 mg purchase with amex, claritin 10 mg purchase on line, cheap 10 mg claritin, 10 mg claritin discount visa, order claritin 10 mg with amex, order 10 mg claritin visa, buy claritin 10 mg mastercard, claritin 10 mg buy cheap on-line, generic 10 mg claritin otc, buy generic claritin 10 mg line, safe 10 mg claritin, generic 10 mg claritin overnight delivery, discount 10 mg claritin with mastercard
9 of 10
Votes: 254 votes
Total customer reviews: 254
Customer Reviews
Connor, 22 years: If attainable, plating ought to be done earlier than the specimen is eliminated within the ablative portion of the case. Prevention/Avoidance: Little or no traction on the umbilical cord or fundal pressure during the supply of the placenta. Alternatively, main colposuspension is helpful for treating each problems (but carries a 15% risk of posterior wall prolapse).
Abbas, 52 years: Expected Outcome: With early detection, progressive fetal growth can usually be achieved, although many pregnancies may require early supply or other interventions to ensure fetal well-being. Measure urine osmolality: <250mosm/kg = water diuresis, >300mosm/kg = solute diuresis. Specifically, when contemplating the alveolar ridge, reconstructive necessities shall be radically completely different relying upon location and extent of disease.
Thordir, 44 years: Overall, the elevators are much stronger than the depressors and the masseter muscle is the strongest of the elevators. The presence of none of these elements confers beneficial risk-median time to demise 20 months; 1�2 factors carry intermediate risk-median survival 10 months; >3 components carry poor risk-4 months median survival. Use of stone baskets to retrieve stones after ureteroscopy the aim of ureteroscopy (or versatile ureterorenoscopy) is to take away the ureteric (or renal) stone.
Tuwas, 30 years: Contemporary considerations within the therapy and rehabilitation of head and Neck Cancer: Voice, Speech, and swallowing. Treatment choices for hydronephrosis Bypass the exterior sphincter � Indwelling catheter. Encourage the patient to begin these larger calorie/higher protein foods as soon as attainable, ideally previous to remedy.
Farmon, 45 years: The significance of "constructive" margins in surgically resected epidermoid carcinomas. Fine tuning to customize scientific target volume protection versus organ vulnerable to publicity may be achieved using manual tools that permit manipulation of the dose cloud by the radiation oncologist. Suspected most cancers: recognition and referral (published June (2015); up to date July 2017).
