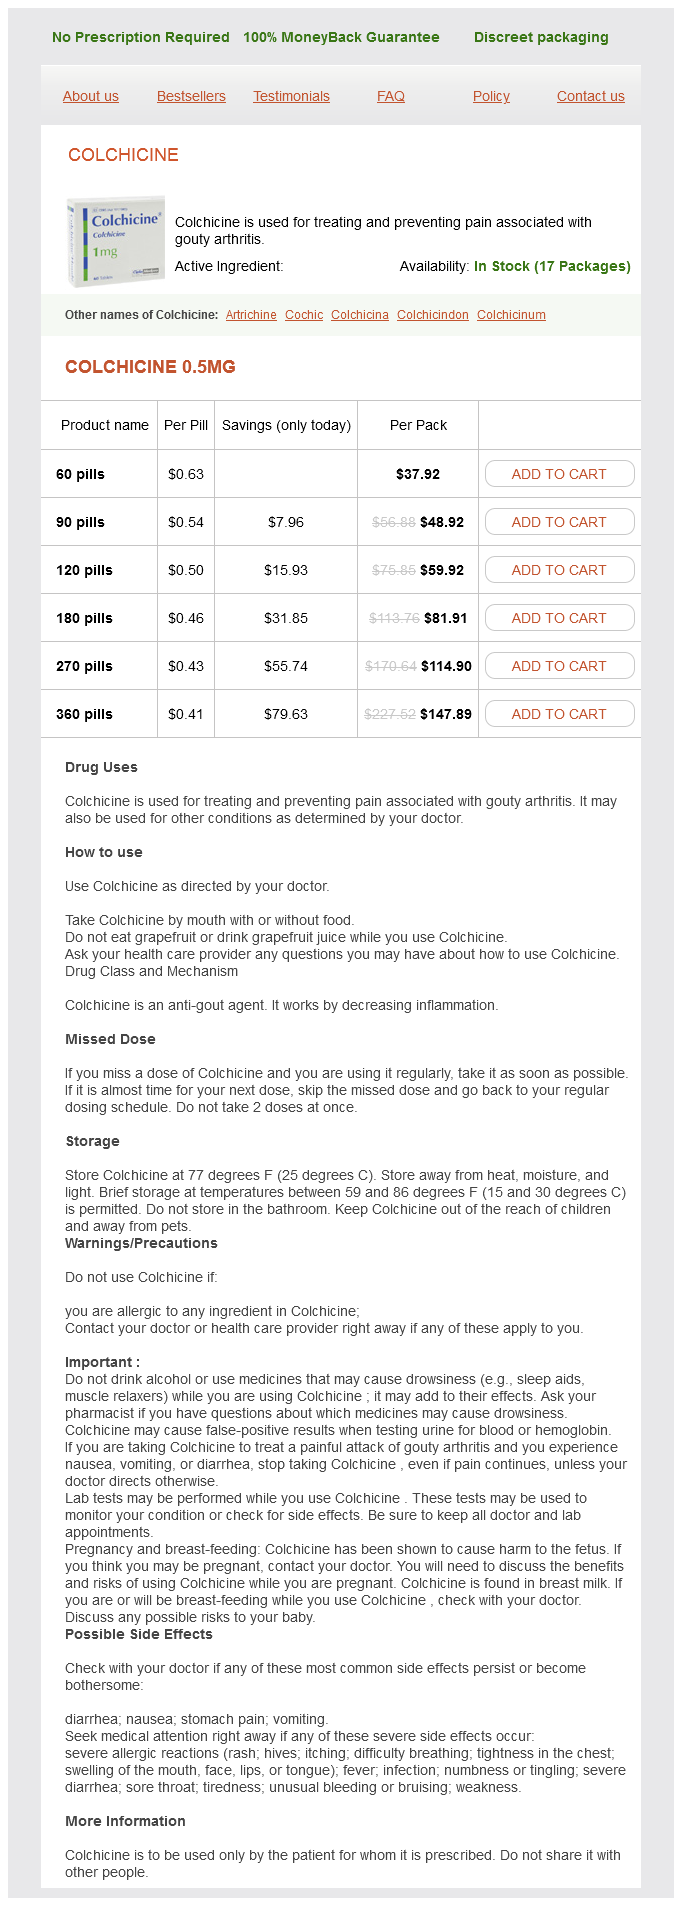
Colchicine 0.5mg
- 60 pills - $37.92
- 90 pills - $48.92
- 120 pills - $59.92
- 180 pills - $81.91
- 270 pills - $114.90
- 360 pills - $147.89
Colchicine dosages: 0.5 mg
Colchicine packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 822
Only $0,44 per item
Description
Recommended screening exams embody fasting plasma glucose degree infection of the cervix colchicine 0.5 mg buy overnight delivery, hemoglobin A 1c infection jobs indeed 0.5 mg colchicine purchase visa, or 2-hour oral glucose tolerance test antibiotic resistant salmonella generic colchicine 0.5 mg amex. The American Diabetes Association recommends screening each 3 years if check results are normal antibiotic ointment colchicine 0.5 mg cheap on line. Grade C recommendations are supplied for selected patients depending on particular person circumstances. Nucleic acid amplification tests can be carried out on first-voided urine or vaginal or endocer vical swabs. Nucleic acid amplification exams could be carried out on first voided urine or urethral swabs from men and vaginal or endocervical swabs from ladies. Using this software, the clinician asks, "During the past 2 weeks, how often have you been bothered by any of the next issues: (1) little curiosity or pleasure in doing issues, or (2) feeling down, depressed, or hopeless Additionally, all adults at high threat (injection and intranasal drug users, per sons who acquired a blood transfusion before 1992, persons on long-term hemodialysis. Appropriate screening exams embrace tuberculin skin take a look at ing or the interferon-y launch assay. The doctor additionally ought to present individuals engaged in risky or hazardous drinking with temporary behavioral counseling. A single-item screening question ("How many occasions in the past 12 months have you used an unlawful drug or used prescription drugs for nonmedical reasons Screening for Substance Use Disorders Breast Cancer Breast cancer screening discussed in this part applies to asymptomatic average-risk girls. Women with significant threat factors for breast most cancers, together with family history of breast or ovarian most cancers or personal history of atypia or lobu lar carcinoma in situ, ought to endure a proper breast most cancers risk assessment. As a end result, guidelines issued by organizations may differ considerably, and some recommendations may be con troversial. This highlights the necessity to understand the proof underlying the different guidelines and to have interaction in shared decision-making when deciding on an appropriate cancer screening technique for a person patient. In general, it is suggested that individuals with fewer than 10 years of high quality life expectancy not receive most cancer screening. Harms can include false-positive screening outcomes, which can lead to unnecessary emotional stress, biopsies, and pointless remedy. As with other most cancers screening exams, research have advised that women should have a life expectancy of a minimum of 10 years to benefit from screening mammography. Most guidelines advocate stopping screening if life expectancy is less than 10 years. Preventive Services Task Force recommends in opposition to using prostate-specific antigen degree to display for prostate most cancers. Preventive Services Task Force, ladies ages 21 to 65 years ought to be screened for cervi cal most cancers each 3 years with a Pap smear. Preventive Services Task Force and the American College of Physicians advocate biennial screening mammography for all ladies aged so to seventy four years to display for breast cancer. Preventive Services Task Force recommends that each one adults be screened for obesity, hypertension, tobacco use, alcohol misuse, and depression (if ade quate sources can be found to provide support and treatment for depression). Evidence suggests that individuals are berter at reporting absence quite than pres ence of illness in relatives. Drawing a pedigree or household tree is commonly useful in recogniz ing patterns of inheritance. Taking a Family History Clinical genetics has traditionally focused on identification of particular disease-causing mutations that observe a mendelian pat tern of inheritance: nevertheless. The understanding of the position of these genetic components in predis posing an individual to sure diseases is rapidly evolving. The growing availability and lowering value of direct to-consumer genetic testing require clinicians to perceive the basics of detecting, diagnosing. Disorders that come up at a youthful age than anticipated could occur due to a genetic predisposition that makes a person more vulnerable to environmental exposures. A disorder that happens within the less widespread intercourse might happen because of a genetic predisposition that overrides other hormonal, developmental, and environmental elements that contribute to its prevalence. Genetic predisposition may result in the occurrence of a disorder within the absence of apparent environmental components. Because relations usually have a tendency to share the same genes, kids from a consanguineous couple related as first cousins or nearer have an elevated danger of having an autosomal recessive condition. Example Three members of the family in two generations with cardiovascular disease Cardiovascular illness occurring within the fourth decade of life Breast most cancers in a male Family history of multiple affected family members with the same or related disorders Earlier age at onset of disease than anticipated Condition within the less-often affected sex Disease in the absence of known danger components Ethnic predisposition to certain genetic disorders Close biologic relationship between mother and father Hyperlipidemia in an individual with a super food regimen and train regimen Lactose intolerance in a person of African ancestry Cystic fibrosis Based on National Coalition for Health Professional Education in Genetics. Giemsa staining of chromosomes produces a banding pattern that enables karyotyping and aids in detecting structural abnormalities, and fluorescence in situ hybridiza tion and microarray evaluation can both be used to detect more refined chromosomal abnormalities. Biochemical testing relies on measuring the levels of metabolites involved in biochemical pathways to assess enzymatic activity. When an enzymatic defect is pre sent, metabolite levels could additionally be either elevated or decreased. Predictive genetic testing uses a genetic check to decide whether or not or not a person will develop a condi tion at some point in his or her lifetime. Direct-to-consumer genetic testing allows patients to obtain testing with out the assistance of a well being care provider. Direct-to-consumer testing is based on figuring out genetic variations between people with a condition and people without the condition. Direct-to-consumer testing has many potential drawbacks, together with the validity of the tests themselves. Because of an absence of pretest counseling, sufferers usually misinterpret check results, resulting in pointless angst. Genetic testing raises many moral questions, because the outcomes affect not only the patient but also different family members. Referral for Genetic Counseling Genetic counseling should all the time happen earlier than any genetic take a look at is carried out. Types of Genetic Testing and Indications Indication Used to confirm or assist a prognosis in a patient with scientific illness (for example, cystic fibrosis, sickle cell disease) Used to establish people in danger for heritable disease: Genetic Testing Type Diagnostic testing Predictive testing Presymptomatic tests evaluate for conditions brought on by single genes with a excessive diploma of penetrance that may doubtless eventually trigger disease (for example, Huntington disease). Susceptibility tests consider for various genetic markers related to advanced ailments (for example, coronary artery disease). Approximately 1 hour of coun seling is taken into account commonplace for each genetic take a look at performed. If a vaccination collection is interrupted, the schedule ought to be resumed at the level of interruption. Multiple vaccinations can usually be given simultaneously to enhance vaccination charges. Vaccination must be supplied as soon because the vaccine becomes out there and will continue until influenza season has ended. There are at present three various sorts of influenza vac cine out there within the United States: inactivated influenza vac cine (! The quadrivalent vaccine contains two influenza A virus antigens and two influenza B virus antigens, whereas the trivalent vaccines include two influenza A virus antigens and one influenza B virus antigen. All vaccine formulations must be prevented in persons who previ ously developed Guillain-Barre syndrome inside 6 weeks of receiving the influenza vaccine. Recommendations relating to influenza vaccination of persons who report allergy to eggs. Birth within the United States earlier than 1980 is taken into account to serve as evidence of immunity in opposition to vari cella, besides in well being care professionals, pregnant girls, and immunocompromised people, all of whom require serologic confirmation. For individuals born after 1980, evidence of immunity to varicella includes written documentation of age-appropriate vaccination, serologic confirmation of immu nity, or verification of either varicella or herpes zoster diagno sis made by a doctor. Women must be assessed for varicella immunity during being pregnant, and if not immune, they need to be vaccinated following preg nancy. The herpes zoster vaccine is similar to the varicella vac cine but is significantly stronger. It is beneficial for individuals aged 60 years and older regardless of whether or not they have had a earlier zoster episode, however vaccination must be averted in immunocompromised sufferers. Vaccination is efficient for reducing the prevalence of each herpes zoster and postherpetic neuralgia. Vaccinations Recommended for Some Adults Varicella and Herpes Zoster Although tetanus and diphtheria infections are extremely unusual, the incidence of pertussis has recently increased, presumably as a outcome of waning immunity with age. A single booster dose of the tetanus toxoid, decreased diphtheria toxoid, and acellular pertussis (Tdap) vaccine is also beneficial for youngsters between the ages of eleven and 12 years.
Inositol Hexaniacinate (Inositol Nicotinate). Colchicine.
- Blood disorders of the brain, migraine headaches, a disorder of fibrous connective tissue deposits in the skin and organs (scleroderma), sleeplessness (insomnia), lowering blood pressure, restless leg syndrome, acne, skin inflammation (dermatitis), inflammation of the tongue (exfoliative glossitis), psoriasis, schizophrenia, and other conditions.
- Are there any interactions with medications?
- How does Inositol Nicotinate work?
- Dosing considerations for Inositol Nicotinate.
- Are there safety concerns?
- What other names is Inositol Nicotinate known by?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96724
Agent Commonly Used Pharmacologic Therapies for Smoking Cessation Mechanism Prevents nicotine withdrawalb Effectiveness Increases cessation charges about 1 antibiotic drug classes purchase colchicine 0.5 mg with mastercard. Max dose: 24 pieces/d Advantages Less costly than other forms of nicotine alternative virus encrypted files 0.5 mg colchicine otc. Nicotine gum� Nicotine patch (24 h)a antibiotic 3 times a day colchicine 0.5 mg buy generic line, c Prevents nicotine withdrawalb Increases cessation charges about 1 xeno antibiotics buy generic colchicine 0.5 mg on line. Most patients: 21-mg patch for 4-8 wk (remove and exchange every 24 h), then 14-mg patch for 2-4 wk, followed by 7-mg patch for 2-4 wk. Nicotine nasal spray� Prevents nicotine withdrawalb Increases cessation rates about 1. Nicotine inhaler� Prevents nicotine withdrawalb Increases cessation rates about 1. Nicotine lozenge� Prevents nicotine withdrawalb Increases cessation charges about 1. Alcohol withdrawal happens with persistent heavy alcohol use inside how-s to days after alcohol cessation. Early withdrawal signs occur inside a couple of hours of abstinence and include agitation, anxiety. Generalized tonic-clonic seizures might happen usually L 1 lozenge (2 mg or four mg) each 1-2 h during weeks 1-6 then 1 lozenge every, 2-4 h throughout weeks 7-9, then 1 lozenge every 4-8 h throughout weeks 10-12. Patients who smoke within 30 min of waking require 4-mg lozenge; those who have first cigarette later in the day require 2-mg lozenge. Delirium tremens is characterized by fluctuating ranges of consciousness, confusion, and agitation with marked auto nomic overdrive and is related to a 5% mortality fee. Agent Commonly Used Pharmacologic Therapies for Smoking Cessation (Continued) Bupropion Unclear Mechanism Increases cessation charges about 2 occasions at 1 y. Effectiveness Initial Prescription Begin 1-2 wk before stop date; start with one hundred fifty mg once every day for 3 days, then a hundred and fifty mg twice day by day by way of end of remedy (7-12 wk max). Some antidepressant exercise; could additionally be a good choice for patients with a history of depression. Dosing pointers are for patches designed to stay in place for 24 h and that are available doses of 21 mg, 14 mg, and seven mg. Clinicians ought to examine prescribing information on nicotine patches that are available other doses or which are designed to be used <24 h/d. Benzodiazepines must be given as wanted, somewhat than by scheduled dosing or steady infusion. Prevalence of co-occurring critical mental diseases with substance abuse, high-risk sexual behav ior, and polysubstance abuse is increased amongst illicit drug users. Any illicit drug use ought to be considered harmful given potential health and authorized conse quences of even rare use. Asking about illicit drug use and prescription drug misuse is recommended throughout preliminary medical visits and when clinically related (see Routine Care of the Healthy Patient). The method to treatment is similar to that for tobacco and alcohol misuse, consisting primarily of Drugs � For people who smoke not able to stop, motivational interview ing, with emphasis on nonconfrontational methods and dialogue of patient selections, has proven greater cessation charges than use of transient advice or usual care. These issues are entrenched, rigid, and secure over time, and result in substantial impairment and misery. There are 10 specific persona issues, which are grouped into three clusters based on symptoms (Table 73). Patients with personality issues often Personality Disorders require extra time than the primary care physician can realis tically provide and may profit from referral to a psychological well being skilled. More generally encountered in nonpsychiatric settings, these issues may be seen in as a lot as 20% of patients in major care settings. Such sufferers have very high utilization of health care regardless of general dissatisfaction with their medical care. Diagnostic criteria for somatic symptom disorder are as follows: no much less than one somatic symptom causing misery or interference with daily life; excessive ideas, behaviors, and emotions related to the somatic symptom(s) (dispropo1iionate or persistent concern about seriousness of symptoms, persis tent excessive degree of tension about health, or excessive focus of time and energy on health concerns); and chronic somatic symptoms for at least 6 months (does not have to be the same symptom for six months). When this disorder has pain as the primary symptom, the specifier "with predominant pain" should be used as a outcome of this diagnosis has replaced ache dysfunction. Illness anxiousness dis order (previously generally known as hypochondriasis) is characterised by extreme worry about common health and preoccupation with health-related actions (such as measuring pulse). Factitious disorder is a deliberate falsi fication of symptoms or infliction of injury on oneself or one other, even within the absence of clear exterior benefit. Prior to diagnosing any of the somatic symptom and associated disorders, excluding or optimizing therapy of natural illness or other psychiatric issues (such as despair and generalized anxiety) is indicated. The symptoms are often continual in nature and sufferers incessantly undergo repetitive and pointless diagnostic testing, which regularly leads to unnecessary invasive medical and surgical inter ventions. Management begins with an open discussion of the analysis, scheduling of standard follow-up visits, and coordi nation of care with a psychiatrist. Personality Disorders Cluster A: Odd or Eccentric Thinking and Behaviors Paranoid: pervasive distrust of others; unjustified suspicion of others; unjustified suspicions concerning their companions or spouses; overly hostile reactions to perceived insults Schizoid: prefer to be alone and lack interest in relationships; appear indifferent, cold, and unresponsive to social cues; benefit from few actions Schizotypal: manifest odd pondering, beliefs. Bone density measurement is commonly advised after 6 to 12 months of continued signs. Common options embrace consuming more rapidly than normal, feeling uncomfort ably full, consuming large amounts when not hungry. Physical examination might reveal erosion of dental enamel, parotid gland swelling, xerosis, and Russell sign (scar ring or calluses on the dorsum of the hand if used to induce vomiting). It is characterised by persistent caloric consumption restriction leading to significantly low body weight, a distorted physique image, and an intense fear of gaining weight or becoming fats. Subtypes embody limit ing type (no binge eating or purging behaviors) and binge eating/purging sort (purging with or with out binging). It primarily impacts adolescent girls and young women however can even affect males and older ladies. Physical examination could reveal ema ciation, brittle hair and nails, lanugo, xerosis, yellow skin especially of the palms (from hypercarotenemia), and edema. Types Eating Disorders � Management of sufferers with somatic symptom and associated problems begins with an open iliscussion of the diagnosis, scheduling of standard follow-up visits, and coordination of care with a psychiatrist. The primary remedy of eating disorders is restoration of normal weight and consuming behaviors. This can be done in a mix of outpatient, residential, or inpatient settings involving a multidisciplinary group, including a major care physician, dieticians, and psychological health specialists. Treatment of anorexia nervosa entails psychotherapy (including family remedy, particularly in adolescents) and nutri tional restoration (supervised meals, medical monitoring, and hospitalization in severe cases). Intense psychological assist is usually needed in the course of the strategy of regaining weight. Olanzapine has shown recent promise in reducing obsessive-compulsive tendencies and improving weight gain in anorexia nervosa. Other laboratory abnormalities embody anemia, leu kopenia, and elevation of liver chemistry checks. Bulimia nervosa also can cause electrolyte derangements resulting in arrhythmias but additionally includes gastrointestinal related problems, together with esophagitis, Mallory-Weiss tears, and esophageal rupture. Purging and misuse of laxatives, diuretics, and enemas can cause electrolyte abnormalities. Both anorexia nervosa and bulimia nervosa also impart an increased risk of melancholy, nervousness, substance abuse, and suicide danger. Schizophrenia often begins in late adolescence and is charac terized by a minimal of two of the following signs: delusions, hallucinations, disorganized speech, disorganized or catatonic habits, and negative symptoms (affective flattening, alogia, or avolition). These symptoms must have an effect on a number of major areas of functioning (work, interpersonal relations, or self care) and have been present for six months (including a minimal of 1 month of lively symptoms). Schizophrenia � Cognitive-behavioral therapy has been persistently proven to be useful in the treatment of bulimia ner vosa and binge eating disorder. Rates of hypertension, dyslipidemia, diabetes mellitus, weight problems, smoking, and metabolic syndrome are sig nificantly elevated. Furthermore, schizophrenia is often associated with undertreatment of persistent medical problems and low charges of obtaining screening and preven tive care. Typical antipsychotics have a higher danger of seda tion, anticholinergic results, extrapyramidal symptoms, and hyperprolactinemia. Second-generation antipsychotics have fewer extrapyramidal signs and are simpler than typical antipsychotics. Clozapine has proved simpler than other antipsychotics but requires routine blood monitor ing because it can trigger agranulocytosis.
Specifications/Details
The time period "rim lease tear" describes an articular-sided partial-thickness tear involving the insertional fibers ("footprint") of the tendon antibiotics japan over counter colchicine 0.5 mg. Complete Tears Complete (full-thickness) tears are transtendinous in at least one portion of the involved tendon and lead to virus yahoo email generic colchicine 0.5 mg with mastercard communication between the glenohumeral joint and the subacromial/subdeltoid bursa antibiotic resistance methods buy colchicine 0.5 mg mastercard. According to their dimension antibiotic hip spacer discount 0.5 mg colchicine, fullthickness tears may be categorised as small (<1 cm), intermediate (1-3 cm), giant (3-5 cm), or huge (>5 cm). According to Patte and coworkers, tendon retraction in full-thickness tears could be quantified as follows: � Grade 1: tendon retracted however lateral to humeral equator � Grade 2: tendon medial to humeral equator however lateral to glenoid � Grade three: tendon medial to glenoid Rotator cuff tears induce muscle atrophy and with time irreversible fatty degeneration of the muscle bellies. Supraspinatus Tendon Tears the supraspinatus tendon represents the most commonly torn portion of the rotator cuff. Degenerative tears sometimes develop on the most anterior aspect of the supraspinatus tendon from where they propagate in a posterior direction and might prolong into the infraspinatus tendon. Larger supraspinatus tendon tears can also involve the rotator interval and the superior portion of the subscapularis tendon. In athletes, supraspinatus tendon lesions are inclined to be located extra posteriorly, particularly if attributable to posterosuperior glenoid impingement. The fracture was invisible on plain radiographs (not shown) a b Supraspinatus tendon tears may result in reactive bone marrow changes and cyst formation at the higher tuberosity of the humeral head. Subscapularis Tendon Tears Subscapularis tendon tears more usually occur together with supraspinatus tendon tears than in isolation. Isolated subscapularis tears are commonly traumatic and may develop throughout anterior shoulder dislocation in association with lesions of the inferior glenohumeral ligament. Contributing to the reality that tears of the subscapularis tendon typically progress in a craniocaudad direction, a selected classification system has been proposed by Fox and Romeo: � Grade 1: partial tear � Grade 2: complete tear of higher 25% of subscapularis tendon � Grade three: complete tear of higher 50% of subscapularis tendon � Grade 4: complete rupture (100%) of subscapularis tendon Intramuscular "Cysts" Intramuscular fluid collections can develop from leakage of fluid by way of a rotator cuff defect. These so-called "cysts" are most frequently observed within the supraspinatus muscle in association with a delaminating tear. They sometimes originate from the region of the myotendinous junction of the affected muscle. Differential Diagnosis the scientific symptoms of a rotator cuff tendon tear may be mimicked by several different circumstances that might have an result on the shoulder. Fractures of the higher tuberosity of the humeral head can happen with direct or oblique trauma or as a sequel of shoulder dislocation. Greater tuberosity fractures are commonest in people youthful than 40 years of age and are typically not associated with a rotator cuff tear. Muscle strains of the rotator cuff are often seen in youthful adults after indirect trauma. As in different locations, the myotendinous junction represents the everyday website of damage. Suprascapular nerve palsy can develop as a end result of traumatic harm, neural compression or irritation. The nerve could be compromised by acute (scapular fracture) or chronic traumatization (overhead sports) or throughout shoulder surgical procedure (rotator cuff restore, tumor surgery). Ganglia originating from the glenoid labrum ("paralabral cysts") and lengthening into the spinoglenoid notch represent the commonest explanation for suprascapular nerve entrapment. The ParsonageTurner syndrome (neuralgic shoulder amyotrophy) is a postviral form of neuritis that usually impacts the suprascapular nerve, but additionally would possibly involve the axillary and, rarely, the subscapular nerve. Compromise of the suprascapular nerve usually results in denervation of the infraspinatus alone or the infra- and supraspinatus together. Bone involvement with cortical erosion and marrow extension on the larger tuberosity of the humeral head might also be observed. Sagittal T1-weighted magnetic resonance arthrogram of the shoulder demonstrates regular anatomy of the rotator interval. The intertubercular sulcus and transverse ligament characterize the apex of this triangle, the coracoid course of its base. The time period "rotator interval lesion" is an umbrella time period for various accidents that may occur at this anatomic website. Horizontally oriented capsular tears at the rotator interval are sometimes seen following anterior shoulder dislocation. This lesion might progress to complete detachment of the subscapularis tendon, thus allowing the biceps tendon to dislocate intra-articularly. However, nearly all of degenerative lesions are related to impingement and rotator cuff pathology. Although these indicators have a excessive sensitivity, their specificity is comparatively low. Spontaneous rupture due to this fact normally happens with minor trauma and even throughout a standard movement. Partial tears can present with thickening and increased T1- and T2-weighted sign intensity as properly as thinning of the tendon. Radiology 240:501-507 Gerber C, Sebesta A (2000) Impingement of the deep floor of the subscapularis tendon and the reflection pulley on the anterosuperior glenoid rim: a preliminary report. Clin Orthop Rel Res 304:78-83 Habermeyer P, Magosch P, Pritsch M et al (2004) Anterosuperior impingement of the shoulder because of pulley lesions: a potential arthroscopic study. The proximal ulna articulates with the trochlea and functions as a hinge joint, while the proximal radioulnar joint provides for rotational movement of the forearm. Together, these permit for flexion and extension of the arm and, along side the distal radioulnar joint on the wrist, pronation and supination. The elbow is subjected to the same forms of articular pathology as other joints, but additionally demonstrates distinctive injuries related to the complex forces that occur during throwing and different overhead actions. The bigger medial epicondyle is the positioning of attachment of the frequent flexor/pronator tendon along its anteromedial side in addition to the ulnar collateral ligament alongside its undersurface. The lateral epicondyle provides rise to the frequent extensor/supinator tendon from its superolateral surface, whereas the extensor carpi ulnaris tendon originates on its posterior-inferior aspect [2]. The radial collateral and lateral ulnar collateral ligaments additionally arise from the lateral epicondyle. The distal articular floor of the humerus is split into the trough-like trochlea that articulates with the proximal ulna and the rounded capitellum that articulates with the radial head. In the proximal ulna, the deep, concave trochlear notch lies between the coronoid and olecranon processes and forms a hinge joint with the trochlea. A second concave articular surface, the radial notch, lies along the lateral aspect of the coronoid process and articulates with the radial head to type the proximal radioulnar joint. The slightly concave fovea of the radial head articulates with the capitellum and the small radial tuberosity along the medial facet of the proximal radius provides the attachment web site for the tendons of the brief and long heads of the biceps muscle. It is also necessary to recognize that the articular cartilage of the capitellum is found alongside its anterior convexity solely, and never along its irregular, posterior nonarticular facet. Also, the cartilage alongside the margins of the radial head on the proximal radioulnar joint covers roughly 60 degrees of the circumference of the radius where it articulates with the ulna on the proximal radioulnar joint. Other osseous variants which will mimic pathology involve the trochlear notch of the ulna [5]. A transverse bony ridge within the mid-trochlear notch is frequent and should mimic a loose physique or osteophyte on sagittal images. Similarly, small cortical notches alongside the margins of the mid-trochlear groove may mimic osteochondral defects, again when seen on sagittal photographs. Bones: Pathology Acute Trauma In a patient presenting with elbow pain after an acute damage, often the only radiographic finding is that of an effusion (elevation of the posterior and/or anterior fats pads). A bone contusion is most easily recognized by its edema-like signal intensity on fat-saturated T2weighted pictures. T1-weighted images are useful for anatomic definition and to additional consider abnormalities seen on T2-weighted images. For instance, a fracture line is commonly easier to see on a T1-weighted picture if the surrounding edema obscures it on a fat-saturated T2-weighted picture. Articular cartilage should be evaluated in all three planes using as excessive a resolution method as possible. Osteochondral Lesions Osteochondral lesions of the elbow are thought to result from repetitive impaction or shear forces that result in focal injury to the articular cartilage and underlying subchondral bone. Formerly generally identified as osteochondritis dissecans, these accidents occur most often in adolescent throwing athletes or gymnasts [14]. The repetitive valgus forces that occur at the elbow during the late cocking and early acceleration phases of the throwing movement may find yourself in tensile forces throughout the medial joint that will produce laxity or tearing of the ulnar collateral ligament and/or the common flexor tendon. As these medial stabilizers fail, impaction and shear forces occur across the lateral aspect of the joint leading to injury to the cartilage and subchondral bone of the capitellum and radial head [15]. This is frequent in throwing athletes between the ages of 11 and 15 years (often members of Little League Baseball) [16], and in gymnasts because of axial loading of the joint during actions involving weight-bearing on their arms. These osteochondral lesions most commonly contain the anterolateral capitellum, but have additionally been described within the trochlea in young athletes.
Syndromes
- Last 6 - 48 hours
- Name of the product (ingredients and strengths, if known)
- What type of cancer or illness you have
- Disorders that affect the amount of oxygen in the blood (such as abnormal heart anatomy and lung diseases including cancer or infection) may cause clubbing.
- Pain
- The Michael J. Fox Foundation - www.michaeljfox.org
- How many times have you coughed up blood?
- Convulsions
Related Products
Additional information:
Corneal ulcers could cause everlasting visible loss and require referral to an ophthalmologist virus vs virion cheap colchicine 0.5 mg with visa. Physical exam ination requires eversion of the lid for inspection and removing of international bodies virus 4 free order 0.5 mg colchicine otc. The cornea can be examined by applying fluorescein dye and examining with a Wood lamp or slit lamp household antibiotics for dogs 0.5 mg colchicine trusted. A follow-up examination in 24 hours should be organized to ensure that the corneal abrasion has healed bacteria zombie plants colchicine 0.5 mg safe. Corneal Disorders � Episcleritis is painless and includes no imaginative and prescient modifications, whereas scleritis is painful and related to visual impairment. Cataracts are quite common and occur in over 50% of people older than 80 years within the United States. Risk elements include getting older, household history, smoking, diabetes mellitus, ultraviolet B radia tion exposure, and use of systemic glucocorticoids. Ophthalmoscopic examination reveals opacification of the lens and diminished or absent light reflex. Surgery is indicated when signs interfere with actions of daily dwelling; nevertheless, not all patients with cataracts would require surgery. Risk fac tors are age older than forty years, family history, and race (inci dence in blacks is roughly 4 occasions higher than in whites). Ophthalmoscopic examination reveals a mid-dilated (4-6 mm), nonreactive pupil and! Additionally, patients with continual angle closure glaucoma should avoid sure medica tions that cause pupillary dilatation, including decongestants, anticholinergic brokers, adrenergic brokers, antidepressants, antipsychotic agents, and motion-sickness medications. Because the onset is gradual and asymptomatic, it usually goes unnoticed by the patient. Other interventions include laser remedy and surgical remedy, corresponding to iridectomy or trabeculectomy. Eye Disorders � Primary open angle glaucoma presents with bilateral peripheral visual loss that happens progressively and painlessly. If the drusen turn out to be confluent within the macula, visible acuity will lower however hardly ever beneath 20/40. Bleeding and exudation end in sudden (or rapid onset over weeks), painless blurring or warping of central vision. The dry kind (left), is characterised by distinct yellow-white lesions (drusen) surrounding the macular region and areas of pigment mottling. The moist type (right), is characterised by clumps of hyperpigmentation, hypopigmentation, and evidence of subretinal hemorrhage. Symptoms are floaters, flashes of light (photop sias), and squiggly lines, adopted by a sudden, peripheral visible field defect that resembles a black curtain and pro gresses across the entire visible field. Emergent ophthalmol ogy referral is crucial, as prognosis is determined by the time to surgical therapy. Retinal detachment occurs when the retina separates from the underlying retinal pigment epithelium and choroid and could also be brought on by a tear within the retina, leakage or exudation from beneath the retina, or vitreous traction pulling on the retina. The mechanisms of dry eye embrace disruption of tear secretion and increased tear evaporation. Decreased tear secretion often results from irritation of the lacrimal glands and may be associated to systemic diseases, corresponding to Sjogren syndrome and rheumatoid arthritis. Increased tear evapora tion can be brought on by increased measurement of the paJpebral fissure, as seen in Graves ophthalmopathy, or by meibomian gland dys perform, which reduces the tear movie. Sjogren syndrome, Graves disease, and Bell palsy could cause persistent dry eye that leads to corneal damage. Treatment focuses on lowering inflammation and proper ing lid pathology that disrupts the tear film. Topical cyclosporine and glucocorticoid drops are reserved for patients with dry eye from systemic sickness. Punctal or canali cular plugs, very small devices that are inserted into the tear ducts to lower tear evaporation, may be utilized in patients Dry Eye � Emergent ophthalmology referral is crucial for patients with suspected retinal detachment, as prognosis is decided by the time to surgical treatment. Patients are usually aged and current with profound and sudden painless imaginative and prescient loss. Severe visible impairment at presentation signifies the risk of permanent visual loss. Risk components for retinal vein occlusion are superior age, smoking, diabetes mellitus, hypertension, hyperlipidemia, weight problems, glau coma, retinal arteriolar defects, and hypercoagulable states. Occlusion of the central retinal artery (arrow) characterized by the looks of an opalescent retina, retinal pallor, and "cherry-red spot" defining the fovea. Central retinal vein occlusion characterized by optic disk swelling, dilated and tortuous veins, flame-shaped retinal hemorrhages, and cotton-wool spots ("blood and thunder"). Herpes zoster involving the Lrigeminal nerve distribution and particularly the lip of the nostril (Hutchinson sign) correl,1tes with sight-threatening herpes zoster ophlhalmicus. The eye must be handled with al least half-hour of eye irrigation whereas awaiting ophthalmologic evaluation. Disease Conductive Cerumen impaction Otosclerosis Tympanic membrane perforation Cholesteatorna Symptoms are eye swelling. Hearing loss is usually categorized as conductive or sensori neural, although patients can have blended listening to disorders (Table 68). Conductive listening to loss outcomes from a mechanical drawback in the ear canal, tympanic membrane, or ossicles that prevents the transmission of sound to the cochlea. Patients with conductive problems will describe basic hearing loss, fre quently with related pain or drainage. Preventive Services Task Force concludes that the current proof is insufficient to assess the steadiness of advantages and harms of screening for hearing loss in asymptomatic adults Hearing Loss Common Causes of Hearing Loss Notes Cerumen could completely impede ear canal, inflicting conductive hearing loss. Refer for attainable repair if related to important hearing loss or possible middle ear pathology. An expanding mass composed of keratinizing squamous epithelial cells which will comprise ldl cholesterol crystals. Although histologically benign, it may erode extensively into local constructions, together with the cochlea, ossicles, tympanic membrane, and facial nerve. Sensorineural Presbycusis Sudden sensorineural listening to loss Meniere disease Age-related hearing loss; typically symmetric high-frequency hearing loss. Benign neoplasm, usually causing sensorineural hearing loss, tinnitus, and generally vertigo. A household or private histo ry of neurofibromatosis sort 2 places patients at excessive danger for these tumors, typically bilaterally. Prevention is mainstay of remedy; hearing aids if condition is already superior. Acoustic neuroma Noise-induced Drug-induced Both Conductive and Sensorineural Infection Middle ear an infection may impair motion of the tympanic membrane or ossicles, producing reversible conductive listening to loss. May produce a conductive hearing loss from ossicular disruption and hemotympanum or a sensorineural listening to loss from cochlear fracture or auditory nerve damage. Head trauma 112 Ear, Nos e, Mouth, and Throat Dis or d ers aged 50 years or older. If undertaken, screening could be com pleted by simply asking the patient if she or he has difficulty hearing. Self-reported hearing loss has been shown to have 90% agreement with audiometric assessment in sufferers older than age 50 years. Validated screening questionnaires, such as the Hearing Handicap Inventory for the Elderly, have been shown to have excessive positive chance ratios for listening to loss. The examiner whispers six units of three let ter or quantity combos to the patient. Failure to repeat no much less than three of the six units appropriately constitutes a constructive result. A optimistic take a look at outcome occurs when the patient fails to identify the rubbing in three of six attempts. Physical examination for hearing loss should give attention to differentiating between conductive and sensorineural causes utilizing the Weber and Rinne tests (Table 69). During physical examination, visualization of the ear canal is essential to decide if a mechanical obstruction or tympanic membrane disorder exists.
Usage: p.c.
Full-thickness tissue loss in which the base of the ulcer is covered by slough or eschar antibiotics for acne canada 0.5 mg colchicine cheap with visa. Purple or maroon localized area of discolored however intact skin or a blood-filled blister as a end result of antibiotics in first trimester 0.5 mg colchicine order fast delivery injury of underlying delicate tissue from strain or shear antibiotic resistance the need for global solutions 0.5 mg colchicine cheap free shipping. Prevention of pressure ulcers ought to begin with a help surface that ensures strain redistribution virus cleaner 0.5 mg colchicine purchase visa, shear discount. There is moderate evidence that the usage of advanced static mattresses and overlays (such as foam. No one advanced static mattress or overlay has been proven to be superior to one other. Treatment of stress ulcers is aimed at addressing the elements that predisposed the affected person to the development of the ulcer. Air-fluidized beds have been proven to enhance healing of pressure ulcers in contrast with commonplace hospital mattresses. Debridement of nonviable tissue by way of surgical or nonsurgical methods (for example, wet-to-dry dressings) is also indicated. Nutritional supplementation to enhance wound therapeutic stays controversial; however. There is insufficient proof to sup port vitamin supplementation or zinc supplementation, though these interventions are thought of very low threat. There is low-level proof supporting electrical stimulation and vacuum wound gadgets in lowering wound dimension. Multiple research have demonstrated low yield and poor risk correlation of routine preoperative diagnostic exams. In most circumstances, patient-specific ri1ctors decide diagnostic testing wants. Pregnancy testing ought to be provided to ladies of" child bearing age, and preoperative urinalysis must be carried out in patients undergoing urologic procedures. It can be necessary to contemplate specific medicine and their potential effect in certain scientific circumstances. This complica tion increases the danger or retinal detachment and endophthal mitis; therefore. Lhe managemenl of this agent in sufferers being evaluated for a cataract process should be mentioned with the attention surgeon preoperatively. Table seventy seven lists other medications with potential surgery related threat and recommended time frames for withholding them. Perioperative medicine management begins with willpower of treatment indications. Unless particular surgery associated dangers are identified, medicines with a transparent indica tion ought to be continued uninterrupted. Suggested Perioperative Medication Management Recommendation Continue for minor surgery. Medication Class Anticoagulant Comments Bridging with heparin indicated for high-risk sufferers and presumably moderate-risk patients. AntipIateIet Clopidogrel: discontinue 5-7 d before surgical procedure; patients with cardiac stent may require continuation. Aspirin and clopidogrel use in patients with cardiac stent and/or at excessive threat is controversial. Cardiovascular Continue -blockers, calcium channel blockers, nitrates, antiarrhythmia agents. Continue controller and rescue inhalers as nicely as systemic glucocorticoids (if used). Oral hypoglycemic agents: discontinue 12-72 h earlier than surgical procedure relying upon half-life of the drug and danger of hypoglycemia. Short-acting insulin: withhold morning of surgical procedure; might have dose discount preoperatively if modified food plan. Lipid lowering Pulmonary Gastrointestinal Hypoglycemic agents Hypoglycemia is more dangerous than hyperglycemia; warning to always have some basal insulin current in sufferers with sort 1 diabetes. Thyroid Glucocorticoids Estrogen Continue thyroid replacement, propylthiouracil, methimazole. Discontinue several weeks before surgery if feasible; if continued, enhance stage of deep venous thrombosis prophylaxis. Can proceed lithium, though some experts taper and discontinue a number of days before surgery. May continue antiparkinsonian brokers, though some experts may discontinue the night earlier than surgery. Medication Class Suggested Perioperative Medication Management (Continued) Recommendation For transplant recipients, continue all except sirolimus without interruption. For non-transplant sufferers, discontinue for at least 4 half-lives before and a pair of weeks after surgery. Comments Paucity of data; danger of illness flare balanced towards risk of opposed response from medication. Risk of perioperative wound complications may be decrease for methotrexate, hydroxychloroquine, and sulfasalazine. Revised Cardiac Risk Index and Predicted Rate of Major Cardiac Complications Perioperatively High-risk surgery (intrathoracic, intraperitoneal, suprainguinal vascular) Risk Factor (1 level for each) Chronic kidney disease (serum creatinine >2. Derivation and prospec tive validation of a easy index for prediction of cardiac danger of main noncardiac surgical procedure. The Revised Cardiac Risk Index within the new millennium: a single centre potential cohort re-evaluation of the unique variables in 9,519 consecutive elective surgical patients. Prior to continuing with pharmacologic stress testing in an asymptomatic palient present process noncardiac surgery. Echocarcliography may also be useful in specific circum stances lor assessment of left ventricular perform or valvular coronary heart illness. Statins can also present perioperative cardiac threat reduc tion, and limited information suggest this profit could be seen even when initiated sh011ly before surgery. Stalins should also be continued perio peratively in sufferers already taking them. This recommendation is based upon the dearth of information supporting specitk risk discount measures for sufferers with perioperative asymptomatic myocardial infarction or isolated cardiac biomarker elevation. In common, these situations should be medically optimized as a lot as attainable prior to sur gery and want careful attention to postoperative hemodynamic management. Several models and danger calculators have been developed for predicting pulmonary threat. Although these calculators might provide a reasonably reliahle estimate of general pulmonary compli cations. Therefore, clinical assessment of danger factors without a validated threat calculator is probably going surticient in most medical conditions. Arterial blood gas analysis and chest radiograph outcomes rarely alter perioperative administration when obtained in clinically stable sufferers. Smoking ces sation ought to be strongly inspired; the best benefit comes from quitting greater than 8 weeks earlier than surgical procedure. Selective use of nasogastric intubation can be efficient at stopping pulmo nary complications. Regional and neuraxial anesthesia and analgesia, intraoperative protecting Jung ventilation. Perioperative Management of Anticoagulant Therapy Surgical patients on chronic anticoagulant therapy confront the problem of balancing their baseline thrombotic threat with the added thromboembolic and bleeding risks related to invasive procedures. Anticoagulation administration should aclclress the next: (l) want for momentary anticoagulant cessation, (2) potential advantage of bridging anticoagulation if cessation is critical. If momentary cessation is warranted, therapy ought to be with held for a sufficienl time period to depart minimal residual anticoagulant activity. Much less information can be found for the perioperative administration of target-specific oral anticoagulants. Most specialists suggest a conservative strategy to ensure elimi nation by the point of surgical procedure (Table 83).
Tags: purchase colchicine 0.5 mg free shipping, discount 0.5 mg colchicine with mastercard, cheap colchicine 0.5 mg with mastercard, cheap 0.5 mg colchicine overnight delivery, 0.5 mg colchicine order with amex, colchicine 0.5 mg effective, cheap colchicine 0.5 mg overnight delivery, buy 0.5 mg colchicine, colchicine 0.5 mg on-line, discount colchicine 0.5 mg overnight delivery, 0.5 mg colchicine buy free shipping, purchase colchicine 0.5 mg free shipping, colchicine 0.5 mg order fast delivery, 0.5 mg colchicine buy with amex, discount 0.5 mg colchicine fast delivery, buy colchicine 0.5 mg low cost
8 of 10
Votes: 321 votes
Total customer reviews: 321
Customer Reviews
Bradley, 60 years: Pancreatitis-associated thrombosis might not require anticoagulation therapy either, particularly as a end result of the risk for intra-abdominal bleeding with such therapy may be excessive. Neurosurgery 66(3 Suppl):48-55 Pratt H, Davies E, King L (2008) Traumatic injuries of the c1/c2 complicated: computed tomographic imaging appearances. Bibliography � Type 1 (hypokalemic distal) renal tubular acidosis results from a defect in urine acidification within the distal tubule with impaired excretion of hydrogen ions. The term clumped refers to enhancement in a focal, linear or linear-branching, segmental or regional distribution.
Kayor, 62 years: He drinks two to three alco holic beverages per day on weekends, and he usually eats quick meals. On bodily exan1ination, she is afebrile, blood strain is 128/76 mm Hg at relaxation, pulse fee is 72/min, and respiration rate is 15/min. A follow-up skeletal survey is typically obtained 10-14 days after the initial survey and could additionally be limited to the lengthy bones and ribs, additionally together with other areas of radiologic or scientific concern from the time of the preliminary survey. When genitourinary signs are the primary con cern in a menopausal lady, low-dose vaginal estradiol is the therapeutic normal.
