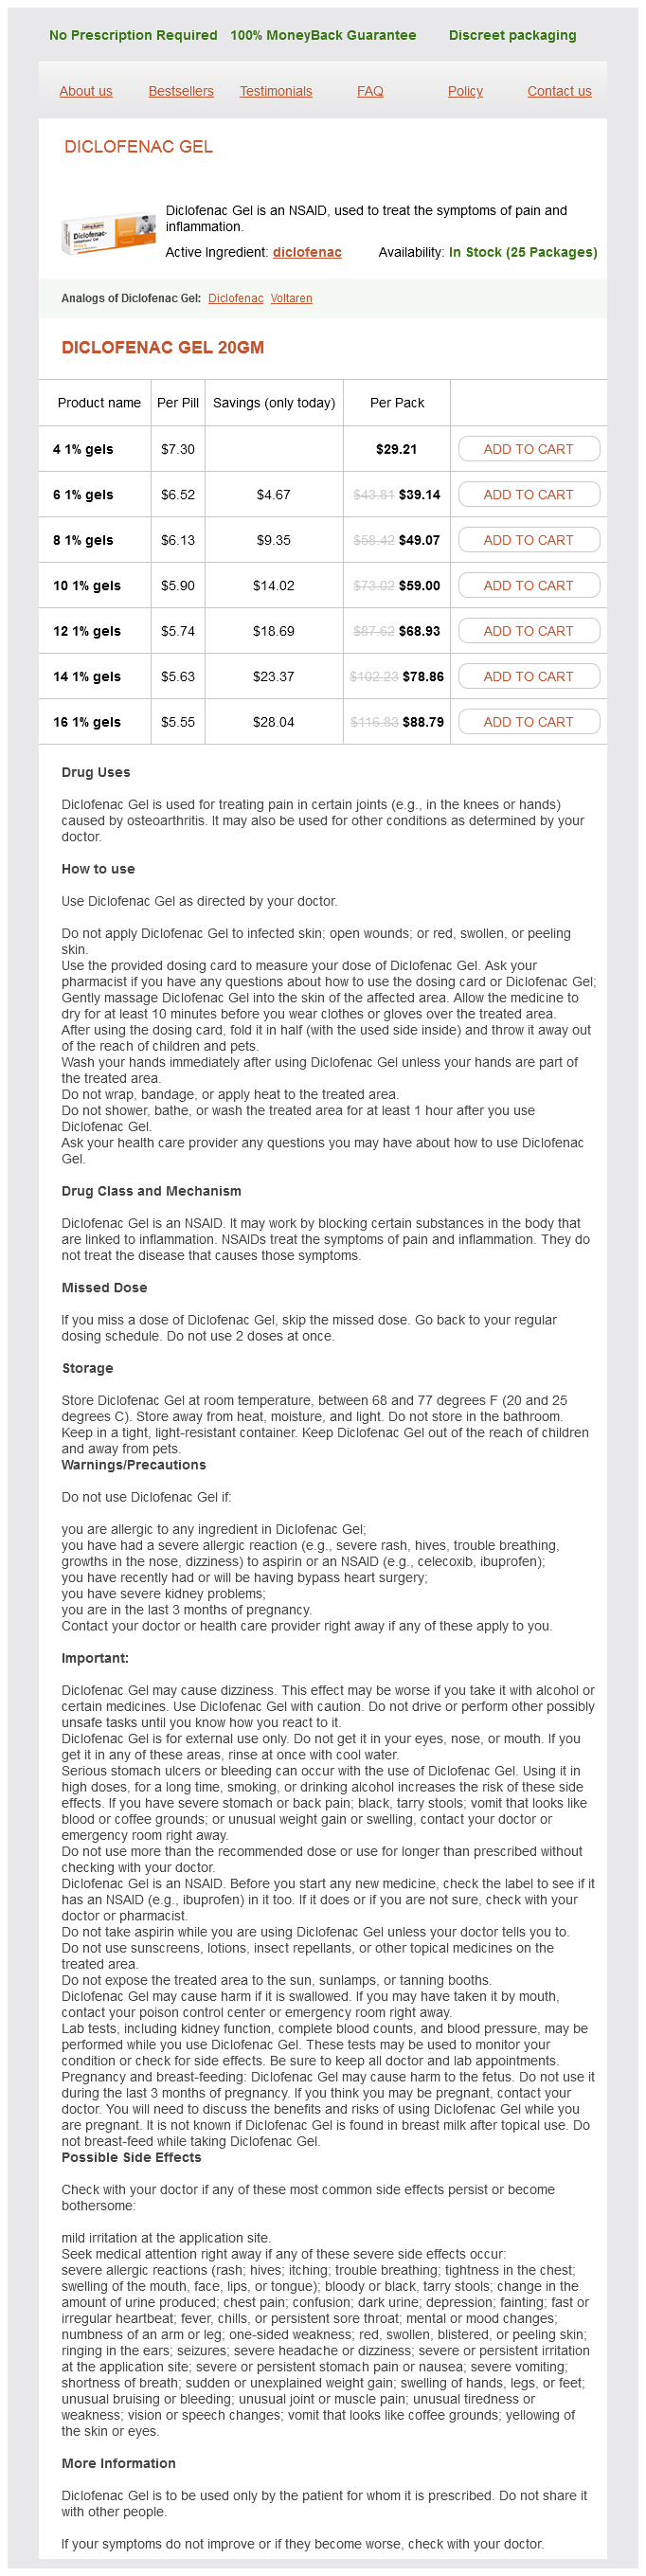
Diclofenac Gel 20gm
- 4 1% gels - $29.21
- 6 1% gels - $39.14
- 8 1% gels - $49.07
- 10 1% gels - $59.00
- 12 1% gels - $68.93
- 14 1% gels - $78.86
- 16 1% gels - $88.79
Diclofenac Gel dosages: 20 gm
Diclofenac Gel packs: 4 1% gels, 6 1% gels, 8 1% gels, 10 1% gels, 12 1% gels, 14 1% gels, 16 1% gels
In stock: 723
Only $5,9 per item
Description
In addition arthritis cats buy diclofenac gel 20 gm cheap, amiodarone toxicity might current with more neutrophils and fewer conspicuous steatosis arthritis treatment great danes buy diclofenac gel 20 gm without a prescription. In the meantime arthritis pain back of hand diclofenac gel 20 gm purchase otc, the results of the longitudinal research to date point out that remedy endpoints in scientific trials should be redefined arthritis diet cookbook order diclofenac gel 20 gm without prescription, giving more weight to enchancment of fibrosis stage and evaluating the improvement of hepatocellular ballooning and portal, along with lobular, inflammation. Bardet�Biedl, Alstr�m, Prader-Willi) could present with steatosis and steatohepatitis that hardly ever can progress to advanced fibrosis and cirrhosis. Despite this, there are well-defined evidencedbased therapeutic interventions that cut back morbidity and mortality. Current recommendations give attention to way of life change (diet and exercise) to achieve weight loss and management of cardiovascular threat components. To achieve this, a calorie-restricted food regimen (600 kcal/day lower than required to keep body weight) may be followed, focusing on 0. Such adjustments are troublesome to sustain in an setting of cheap poor-quality meals, restricted time and assets for exercise and communities oriented towards automotive transportation. Steatohepatitis could be very uncommon, and necroinflammatory exercise and fibrosis are the outcome of different concurrent liver disease. Hepatic steatosis of variable extent might develop in consuming disorders similar to anorexia nervosa, bulimia nervosa, cachexia, large weight reduction and poorly controlled inflammatory bowel disease. Steatohepatitis and progressive fibrosis are extraordinarily uncommon in these issues. In early Wilson illness the liver typically exhibits patchy steatosis and many glycogenated nuclei. The general sample of damage in Wilson illness is that of persistent hepatitis, not steatohepatitis. Lipoprotein metabolism problems similar to abetalipoproteinaemia, familial hypobetalipoproteinaemia, Dorfman�Chanarin syndrome and pseudoneonatal adrenoleucodystrophy have all been related to the event of macrovesicular steatosis of the liver. Other inherited metabolic disorders are related to microvesicular steatosis (see Table 5. Vitamin E has additionally been evaluated as a therapeutic agent due to its antioxidant properties. It is likely that further, liver-directed therapies will turn into obtainable within the subsequent few years. Paradoxically, portal persistent inflammation could additionally be elevated in otherwise improved biopsies. B, the identical affected person was rebiopsied 2 years later; there had been no interventional therapy in the interim, but lack of steatosis. Bruchst�ck Med Jahrb des kaisl, k�nigl �sterr Staates 1839; Bd 29 oder neueste Folge Bd 20 Wien: 557. Nonalcoholic fatty liver disease/nonalcoholic steatohepatitis: histological diagnostic standards and scoring systems. Post-jejunoileal-bypass hepatic disease: its similarity to alcoholic hepatic illness. Amiodarone hepatotoxicity: prevalence and clinicopathologic correlations amongst 104 patients. Non-alcoholic steatohepatitis: Mayo Clinic experiences with a hitherto unnamed disease. Patterns of chemotherapyinduced hepatic damage and their implications for sufferers undergoing liver resection for colorectal liver metastases. Similarities and variations within the pathogenesis of alcoholic and non-alcoholic steatohepatitis. Biochemical evaluation of hepatic lipid in alcoholic and diabetic and management topics. A staining method for the detection and measurement of fats droplets in hepatic tissue. Determinants of development to cirrhosis or fibrosis in pure alcoholic fatty liver. Accumulation of nascent lipoproteins in rat hepatic Golgi during induction of fatty liver by orotic acid. Impaired mitochondrial operate in microvesicular steatosis: results of drugs, ethanol, hormones and cytokines. Lactic acidosis and hepatic steatosis associated with use of stavudine: report of 4 cases. The liver in ferrous sulphate poisoning: a report of three deadly instances in children and an experimental study. Focal glycogenosis of the liver in disorders of ureagenesis: its incidence and diagnostic significance. Familial Reye-like syndrome: a presentation of medium-chain acyl-coenzyme A dehydrogenase deficiency. Microvesicular steatosis and steatohepatitis: function of mitochondrial dysfunction and lipid peroxidation. Multiple hepatic mitochondrial deletions suggest untimely oxidative ageing in alcoholic sufferers. Focal fatty change of the liver: a review and a case related to steady ambulatory peritoneal dialysis. Fatty macroregenerative nodule in non-steatotic liver cirrhosis: a morphologic research. Histopathological algorithm and scoring system for analysis of liver lesions in morbidly overweight patients. Ballooned hepatocytes in steatohepatitis: the worth of keratin immunohistochemistry for analysis. The position of hepatocyte enlargement in hepatic pressure in cirrhotic and noncirrhotic alcoholic liver disease. Correlation between liver morphology and portal stress in alcoholic liver disease. Expression of perilipin and adipophilin in nonalcoholic fatty liver illness: relevance to oxidative injury and hepatocyte ballooning. Indian childhood cirrhosis: the nature and significance of cytoplasmic hyaline of hepatocytes. Focal nodular hyperplasia of the liver with alcoholic hyalin bodies and cytologic atypia. Hepatocellular hyalin (Mallory bodies) in long term griseofulvin-treated mice: a model new experimental model for the study of hyalin formation. In vitro demonstration of Mallory physique formation in liver cells from rats fed diethylnitrosamine. Mallory bodies: isolation of hepatocellular hyalin and electrophoretic resolution of polypeptide elements. Pathology of cytoskeleton of liver cells: demonstration of Mallory bodies (alcoholic hyalin) in murine and human hepatocytes by immunofluorescence microscopy utilizing antibodies to cytokeratin polypeptides from hepatocytes. Mallory our bodies: immunohistochemical detection by antisera to distinctive non-prekeratin elements. Hepatocyte cytokeratins are hyperphosphorylated at a number of sites in human alcoholic 87. Mallory bodies in alcoholic and non-alcoholic liver disease comprise a typical antigenic determinant. The genetic background modulates susceptibility to mouse liver Mallory�Denk body formation and liver damage. Gender dimorphic formation of mouse Mallory�Denk our bodies and the function of xenobiotic metabolism and oxidative stress. A cell tradition system for the induction of Mallory bodies: Mallory our bodies and aggresomes symbolize various varieties of inclusion bodies. Ubiquitin: an immunohistochemical marker of Mallory bodies and alcoholic liver disease. Hepatocyte apoptosis and fas expression are outstanding options of human non-alcoholic steatohepatitis. In vivo evaluation of liver cell apoptosis as a novel biomarker of illness severity in non-alcoholic fatty liver disease. Circulating and tissue ranges of the neutrophil chemotaxin interleukin-8 are elevated in severe acute alcoholic hepatitis, and tissue levels correlate with neutrophil infiltration. Cirrhosis mortality and per capita consumption of distilled spirits, United States, 1949�94: pattern evaluation. Liver cirrhosis mortality rates in Britain from 1950 to 2002: an analysis of routine data.
D-Pantothenyl Alcohol (Pantothenic Acid (Vitamin B5)). Diclofenac Gel.
- What is Pantothenic Acid (vitamin B5)?
- Skin problems, alcoholism, allergies, attention deficit-hyperactivity disorder (ADHD), rheumatoid arthritis, osteoarthritis, hair loss, asthma, heart problems, carpal tunnel syndrome, lung disorders, colitis, conjunctivitis, convulsions, kidney disorders, dandruff, depression, diabetic problems, enhancing immune function, headache, hyperactivity, low blood pressure, inability to sleep, irritability, multiple sclerosis, muscular dystrophy, muscle cramps, improving athletic performance, and other conditions.
- Treating or preventing skin reactions from radiation therapy.
- Are there safety concerns?
- What other names is Pantothenic Acid (vitamin B5) known by?
- Dosing considerations for Pantothenic Acid (vitamin B5).
- Treating or preventing pantothenic acid deficiency.
- How does Pantothenic Acid (vitamin B5) work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96826
The clinical and biochemical features are highly suggestive of extrahepatic biliary obstruction how does arthritis in the knee feel like diclofenac gel 20 gm overnight delivery. Perivenular fibrosis is usually current rheumatoid arthritis dmards purchase diclofenac gel 20 gm otc, as is a small amount of perisinusoidal fibrosis rheumatoid arthritis exhaustion purchase diclofenac gel 20 gm amex. Electron microscopy confirmed widespread harm or loss of organelles arthritis knee new treatment order diclofenac gel 20 gm line, significantly mitochondria and endoplasmic reticulum. Many subsequent studies have shown that a wide variety of clinical options and biochemical abnormalities may accompany the same morphological sample of liver harm. A liver biopsy research of sufferers presenting for treatment of alcoholism revealed alcoholic hepatitis in 17%. Histological alcoholic hepatitis is said to happen much less usually in Japan than in different parts of the world. Occasionally, nonetheless, liver biopsies from patients with a history of reasonable to heavy alcohol consumption show a nonspecific sample of damage characterised by gentle to average hepatocyte injury-necrosis and/ or apoptosis-with minimal or absent ballooning degeneration, and accompanied by a mononuclear cell infiltrate with few or no polymorphs. In absolutely developed alcoholic hepatitis, hepatocyte necrosis is more widespread and typically confluent. Features indicating liver regeneration include mitotic figures in hepatocytes, microregenerative nodules and a ductular reaction. Sclerosing hyaline necrosis Sclerosing hyaline necrosis, described by Edmondson et al. A marked degree of liver cell necrosis is apparent, and a few massive fat droplets are seen. The terminal hepatic venules might become occluded, and portal hypertension can happen within the absence of cirrhosis. More extreme bridging necrosis between adjoining terminal hepatic venules or between terminal hepatic venules and portal tracts leads to condensation of pericellular fibrosis tissue and the formation of septa. Lymphocytic phlebitis was noted in 16% of patients with alcoholic hepatitis and in 4% of these with cirrhosis. Portal hypertension correlated considerably with diploma of phlebosclerosis and veno-occlusive change. In biopsy materials, Burt and MacSween296 confirmed that phlebosclerosis was a universal discovering in alcoholic hepatitis and cirrhosis, but they found veno-occlusive lesions in solely 10% of 256 biopsies and lymphocytic phlebitis in 4%. These occlusive venous lesions might contribute to the atrophy of hepatic parenchyma and practical impairment. This course of happens in early alcoholic liver harm and is seen first within the perivenular zone. This phenomenon is usually accompanied by structural changes in the liver sinusoidal endothelial cells (see Chapter 1). The means of defenestration has been associated with elevated vascular resistance in the sinusoidal mattress, which suggests that alterations within the hepatic sinusoidal lining may be concerned in the pathogenesis of portal hypertension. Perivenular fibrosis Baboons fed alcohol chronically have been observed to progress from the fatty liver stage to cirrhosis, with out an intermediate stage of alcoholic hepatitis. Serial liver biopsy studies have proven that sufferers with perivenular fibrosis at the steatosis stage are likely to have progressive liver injury if consuming continues. Mild fatty change, gentle alcoholic hepatitis and a quantity of other Mallory-Denk bodies are obvious within the region of a hepatic venule. Increased amounts of fibrous tissue are seen in the parenchyma adjoining to the venule. Note the marked intimal proliferation producing considerable narrowing of the lumen of a hepatic vein department. An abnormally thick rim of fibrous tissue surrounds the terminal hepatic venule; fibrous tissue additionally extends focally into the encompassing liver in a pericellular sample. Since only 20% of the heavy drinkers had cirrhosis, the authors advised that factors along with the dose and length of alcohol consumption should contribute to the development from early perivenular fibrosis to cirrhosis. Perivenular fibrosis is believed to be the first lesion in a sequence of occasions which leads in the end to the development of cirrhosis. Prominent tough endoplasmic reticulum is seen in the cell, but fat droplets are absent. Bundles of collagen are seen in the area of Disse closely apposed to the outer floor of the cell. Micronodular cirrhosis, which is the most common type of cirrhosis seen in affiliation with alcohol,309 is characterised by remarkably uniformsized regenerative nodules, most of which are <3 mm in diameter. Biopsies of cirrhotic livers can also show options of alcoholic hepatitis; the hepatocyte injury happens predominantly on the periphery of the regenerative nodules. A variable combination of neutrophil polymorphs, lymphocytes, plasma cells and macrophages is seen within the fibrous tissue. The presence of alcoholic hepatitis often means continued ingesting, despite the precise fact that there may be little or no fatty change. There is full loss of the traditional structure and alternative by small regenerative nodules which may be utterly surrounded by broad bands of fibrous tissue. Explanted liver reveals numerous small epithelial cells and ductules within the portal tracts and at the periphery of regenerative nodules. Large regenerative nodules could often have medical and radiological features suggestive of hepatocellular carcinoma. Again, a potential interaction between the two aetiological elements could lead to cirrhosis at a relatively early age. Portal tract changes Portal fibrosis has not been thought-about to result from traditional alcohol harm. In their experience, portal and septal fibrosis was extra frequent than perivenular fibrosis. Furthermore, portal fibrosis appeared to contribute to a greater proportion of total fibrosis than did perivenular scarring. Also, macrophages greatly enhanced lysosomal enzyme launch in contrast with regular liver, suggesting that cytotoxic mediators launched by these activated cells may be contributing to liver injury. Other morphological options of alcoholic liver harm Cholestatic syndromes Alcoholic liver illness might current with medical and biochemical options that are strongly suggestive of extrahepatic biliary obstruction. This contrasts with the zonal distribution of iron, with a periportal predominance, and infrequently a pericanalicular distribution within the hepatocytes in hereditary haemochromatosis. Both major and secondary hepatic iron overload seem to potentiate liver damage in humans. Similarly, dietary iron overload potentiated alcohol/hepatotoxin-mediated fibrosis and cirrhosis in an animal mannequin. This 58-year-old man had a previous history of heavy drinking however had abstained for a number of years. Recent epidemiological research have demonstrated an elevated prevalence and incidence of intrahepatic cholangiocarcinoma and a relationship to the presence of cirrhosis. With emerging methodologies for noninvasive measurement of fibrosis by surrogate markers366 and elastography,367 in addition to the inherent invasive nature of the biopsy procedure, its use in apply has declined. Proponents of its use level to the dual or a number of pathologies or unsuspected diagnoses; in a research by Levin et al. The other 20% had various types of non-alcohol-related liver disease, including cholangitis, viral hepatitis, granulomatous hepatitis, passive venous congestion and nonspecific adjustments. Biopsy may be used to assess the patient for potential therapeutic intervention and to monitor the effects of assorted remedy modalities. Biopsy can be utilized to verify or refute alcohol abstinence, though as noted earlier, some histological features. A biopsy can be of value in establishing the stage and grade of the illness; this will likely contribute to an evaluation of prognosis. It has been demonstrated, for instance, that in patients with hepatic decompensation, transjugular biopsies can be utilized to identify a subset of patients with superimposed alcoholic hepatitis who might profit from a trial of therapeutic intervention. These include persistent alcohol misuse, feminine gender, tobacco use, concomitant obesity and type 2 diabetes or viral hepatitis. Clinical scoring systems have been developed to predict mortality in acute alcoholic hepatitis. Seven developed fibrosis, and another nine grew to become cirrhotic; nonetheless, eight of the 9 have been recognized to have continued to drink closely. A mixed macro- and microvesicular pattern and large mitochondria in the authentic biopsies have been found to be unbiased histological predictors of progression. Continued alcohol consumption by patients with these histological options on biopsy is associated with a 47�61% danger of progressive liver illness.
Specifications/Details
Evolution of nonalcoholic fatty liver illness recurrence after liver transplantation arthritis in knee weather change buy diclofenac gel 20 gm overnight delivery. Total parenteral diet therapy and liver harm: a histopathologic research with scientific correlation arthritis dogs laser therapy diclofenac gel 20 gm discount visa. Increased danger of nonalcoholic fatty liver illness after prognosis of celiac disease what does arthritis in back feel like purchase 20 gm diclofenac gel fast delivery. Celiac disease-related hepatic injury: insights into associated situations and underlying pathomechanisms psoriatic arthritis diet treatment buy discount diclofenac gel 20 gm. Association of cardiorespiratory fitness, body mass index, and waist circumference to nonalcoholic fatty liver illness. Role of leisuretime bodily activity in nonalcoholic fatty liver illness: a populationbased research. Effect of vitamin E on aminotransferase levels and insulin resistance in children with non-alcoholic fatty liver illness. Lifestyle intervention and antioxidant therapy in kids with nonalcoholic fatty liver disease: a randomized, controlled trial. Independent results of bodily activity in sufferers with nonalcoholic fatty liver disease. Aerobic train training reduces hepatic and visceral lipids in overweight people without weight loss. A pilot trial of body weight reduction for nonalcoholic fatty liver disease with a home-based way of life modification intervention delivered in collaboration with interdisciplinary medical staff. Randomized controlled trial testing the effects of weight loss on nonalcoholic steatohepatitis. Diet and exercise interventions reduce intrahepatic fats content material and enhance insulin sensitivity in obese older adults. Weight loss reduces liver fat and improves hepatic and skeletal muscle insulin sensitivity in obese adolescents. Lifestyle intervention in individuals with normal versus impaired glucose tolerance. Diet, weight loss, and liver well being in nonalcoholic fatty liver illness: pathophysiology, proof, and apply. Importance of changes in adipose tissue insulin resistance to histological response during thiazolidinedione therapy of sufferers with nonalcoholic steatohepatitis. Randomized, placebo-controlled trial of pioglitazone in nondiabetic subjects with nonalcoholic steatohepatitis. Non-alcoholic steatohepatitis: rising molecular targets and therapeutic methods. Outcomes of liver transplantation for nonalcoholic steatohepatitis: a systematic review and meta-analysis. Lifestyle interventions for the treatment of nonalcoholic fatty liver disease in adults: a scientific evaluation. Vitamin E and vitamin C remedy improves fibrosis in patients with nonalcoholic steatohepatitis. Prospective research of the long-term results of bariatric surgery on liver harm in sufferers with out advanced illness. The effects of discontinuing pioglitazone in sufferers with nonalcoholic steatohepatitis. Ursodeoxycholic acid for treatment of nonalcoholic steatohepatitis: results of a randomized trial. Incidence and natural course of fatty liver in the common population: the Dionysos examine. Transmission of illness is often by the faecal-oral route via contaminated food or water. Alternatively, transmission may be through sexual contact or parenteral publicity, corresponding to by intravenous drug use, blood transfusion or occupational needlestick publicity. If present, signs may be nonspecific and not readily identifiable as resulting from viral hepatitis. Typical signs embrace fatigue, anorexia and nausea within the early levels, adopted by darkish urine and jaundice with growing severity and length. Right higher quadrant belly pain or discomfort, arthritis, urticaria, pruritus and lowgrade fever could also be present. In sufferers with acute viral hepatitis, the surviving parenchyma could additionally be characterised by various degrees of regeneration. Nodular hyperplasia, two-cell-thick hepatocyte plates between sinusoids and mitotic figures inside hepatocytes could indicate liver cell regeneration and a possible for recovery. Serum markers of affected person prognosis in fulminant hepatic failure embody alpha fetoprotein,3 Gc-protein4 and troponin levels. Death may end result from issues of an infection or renal failure somewhat than from hepatic artificial dysfunction directly. The subject of this chapter is the pathological penalties of an infection with hepatotropic viruses. These infections are responsible for hepatitis, which is usually classified by viral type (Table 6. Viral hepatitis can be identified by the duration of infection and the clinicopathological syndrome that develops (Table 6. Although some pathological features are unique to the kind of virus liable for an infection, many aspects of the pathological injury and medical development are common to multiple kinds of hepatotropic viral infection. These complications, when they do occur in acute illness, could additionally be the outcomes of hepatocyte loss and consequent collapse of the sinusoidal community. Increases in serum transaminase values precede an increase in bilirubin and may peak before the event of jaundice. Jaundice, in the presence of serious elevation of transaminase values, signifies a severe diploma of liver damage. Cholestatic hepatitis is a clinical variant of acute viral hepatitis in which biliary dysfunction predominates. The prognosis of this sample of hepatic harm is mostly beneficial when not related to distinguished hepatocellular necrosis. Cholestatic viral hepatitis must be distinguished clinically from biliary obstruction by biliary imaging studies and from drug/ toxin-induced liver damage by scientific history (see Table 6. Pathological options Acute viral hepatitis is characterized morphologically by a combination of inflammatory cell infiltration, macrophage exercise, hepatocellular injury and regeneration. The proportion and detailed nature of those elements differ extensively according to the actual virus accountable, the host response and the passage of time. For example, the liver in acute viral hepatitis is swollen and tender, its capsule is tense, and blood vessels are engorged. Initially the liver is swollen and purple, its capsule oedematous and tense; exuded tissue fluid may be seen on the capsular floor. In patients with severe cholestasis, the color of the liver is bright yellow or green. In fulminant hepatitis the organ shrinks and softens as a result of intensive necrosis, and the capsule turns into wrinkled. The tan nodular zones represent regenerative foci, and the pink zones represent huge necrosis with no residual hepatocytes. Patients dying of acute liver failure usually have injury to other organs, which can significantly contribute to the quick explanation for demise. Such lesions assist to clarify death when liver cell harm is limited in extent or there has already been substantial regeneration. This kind is finest explained as necrosis of zone 3 of the easy acinus, as described by Rappaport,thirteen as a end result of this zone touches each terminal hepatic venule and portal tract. Light microscopy look: types of necrosis the histological classification of acute hepatitis in this chapter relies on completely different patterns of hepatocellular necrosis. These patterns due to this fact are briefly reviewed before the microscopic modifications of acute hepatitis are described intimately. More than one of many patterns of necrosis described next could additionally be seen in different parts of the identical liver and even inside a single biopsy specimen. Spotty (focal) necrosis and apoptosis In the focal form of necrosis, which represents the basic lesion of acute viral hepatitis, individual hepatocytes inside otherwise intact parenchyma die and are removed. The mode of dying of hepatocytes probably includes each lytic necrosis and apoptosis (see Chapter 1), however the relative contribution of every might vary. In the case of apoptosis (or formation of acidophilic bodies), T lymphocytes probably play a task.
Syndromes
- Graves disease
- Nausea
- Endoscopy -- camera down the throat to see burns in the esophagus and the stomach
- Poor healing
- Large amounts of protein in the urine
- Spine
- Esophagitis
- Low-fat dairy products
Related Products
Additional information:
The cells present anisonucleosis arthritis in feet and toes diclofenac gel 20 gm generic without prescription, nuclear contour irregularities arthritis in outside of knee diclofenac gel 20 gm cheap without a prescription, nuclear moulding arthritis treatment knee joints buy diclofenac gel 20 gm cheap, distinct nucleolus arthritis relief elbow diclofenac gel 20 gm generic online, chromatin clumping and excessive nuclear/cytoplasmic ratio. The most difficult scenario is distinguishing orderly, low-grade adenocarcinoma from inflammatory or reactive epithelial atypia. A, Strip of columnar epithelium with basally oriented oval nuclei and supranuclear mucin secretion. There is nuclear overlapping with nuclear contour irregularities, hyperchromasia and excessive nuclear/cytoplasmic ratio. B, Three-dimensional cluster of pleomorphic epithelial cells shows nuclear overlapping, anisonucleosis, nuclear contour irregularities, hyperchromasia, excessive nuclear/cytoplasmic ratio and distinct nucleolus. C, Three-dimensional cluster of pleomorphic epithelial cells exhibits cell-in-cell grouping. Extrahepatic metastases are discovered at autopsy in about 75% of patients, with lymph nodes andlungs(74%),peritoneumandadrenals(20%),kidney(15%) andbone(13%)asthemostcommonsites. The most important prognostic elements for resectable tumours are lymph node metastasis and status of surgical margins. Other adverse prognostic components embody bilobar distribution, poor differentiation, histological variants such as signet ring and sarcomatous carcinomas, perineural invasion and vascular invasion. Correlation with the clinical setting, endoscopic findings and imaging is critical to confirm the diagnosis. Vascular tumours Cavernous haemangioma Clinical options Cavernous haemangioma is the most common primary liver tumour and is most frequently found as an incidental finding at surgery or post-mortem. The stretching of Glisson capsule secondary to recurrent intralesional haemorrhages and organizing thrombosis has been suggested as a explanation for pain. Rarely,lesionsmaybediffusewithinthe liver,594,595 or might even be related to similar-appearing cavernous haemangiomasinadjacentorgans. This lesion concerned the whole right lobe and extends in an irregular method into the left lobe. Smaller haemangiomatous foci (bottom centre), in addition to isolated minute clusters of haemangioma-like vessels represented by multiple small, dot-like foci, are intensive in quantity inside the adjoining liver (right). The vascular spaces in these lesions have the same morphology as those inside cavernous haemangioma. The vascular channel walls are composed of an admixture of clean muscle and fibrous stroma. Haemorrhagic smear exhibits a compact coil of elongated spindle cells with bland nuclear options. These organizing thrombi might ultimately end in extensive scarring over time and the so-called sclerosed haemangioma. In end-stage sclerosed and calcified haemangiomas, an underlying vascular sample may be a clue to the prognosis. These extremely sclerotic lesions can even comprise mast cells, which in flip may play a role in the organizing course of. Mostcases are recognized in infants youthful than 6 months,132,602�604 and this tumour is twice as widespread in ladies as in boys. Surgical resection may not at all times be possible because of multifocality and enormous size with extensive arterialization, so othertreatments. A question has been raised as to the true nature of the big lesions related to massive irregular vessels and cardiac failure or different extreme signs. This argues in opposition to the prognosis of true childish haemangioma in no much less than a few of these lesions, suggesting that the large lesions with abnormal large vessels might instead represent vascular malformations with a peripheral capillary reaction. The tumour consists of variably sized vascular channels lined by a single layer of flat to considerably plump endothelial cells with out significant atypia. Pathology Infantile haemangiomas are typically poorly circumscribed, haemorrhagic lesions that are variably stable and cystic. Cystic areas are typically caused by the vascular parts and thus are sometimes purple to brown in look, whereas the strong areas outcome from fibrosis and are white to tan. The general microscopic options thought of to be diagnostic are just like the capillary haemangiomas of infancy usually seen within the skin, and similarly, these lesions can undergo numerous stages of proliferation, maturation and involution. In addition, the endothelial cells at this advancing border may appear plumper and mitotically energetic. Regression within the tumour leads to variable zones of necrosis, haemorrhage, scarring and calcification. Small tubular to ductular-like epithelial constructions can typically been seen throughout the stroma of the tumour, notably near the periphery of the tumour. These could represent metaplastic change of entrapped hepatocytic and/or progenitor cells. A, At periphery of tumour, the vascular buildings and/or tumour endothelium encroach on the structure of the surrounding regular liver, causing dilation of sinusoids and/or entrapment of hepatocytes (left) and ductular buildings (right). B, Tumour vascular channels can also be seen within the instantly adjoining parenchyma. In addition, multiple foci of extramedullary haematopoeisis are current in both A and B. Single and small teams of tumour cells in a fibromyxoid (mucopolysaccharide-rich) stroma. Calcifications could additionally be current, which might impart a gritty consistency to the tumour. The dendritic tumour cells are elongated, usually irregularly formed, or stellate cells with lengthy branching processes. The tumour tends to grow around, and depart intact, pre-existing buildings, including portaltracts,hepatocytesandbileducts. This area has a small-vessel element, some containing epithelioid vascular endothelial cells or tufts of tumour cells. The edge of the tumour could also be more mobile, with extra outstanding or atypical epithelioid endothelial tumour cells. The tumour cells can develop alongside the sinusoids, replacing normal endothelium and entrapping hepatocytes. Remnant of a medium-sized central (hepatic) vein now crammed with tumour cells, as recognized by a mix of trichrome and elastic (elastochrome) stain. Scatteredinflammatorycells,suchaslymphocytes and neutrophils, are often seen as properly. Caremustbetaken,nonetheless, to not mistake focal keratin positivity in trapped hepatocytes or bile ducts as evidence of a carcinoma. The atypical cells are polygonal with plentiful, dense cytoplasm and occasional tailing. The nuclei are round to reniform with nice chromatin and occasionally distinguished nucleoli. Intranuclear cytoplasmic inclusions and binucleated or multinucleated large cells can also be seen. Vascular shunting via the tumour can happen, causing problems that will embrace congestive coronary heart failure, microangiopathic haemolytic anaemia and consumptive coagulopathy. Pathology Angiosarcomas are sometimes massive haemorrhagic tumours with poorly defined borders and with variably stable to cystic areas. Thetumourcells are normally elongated in appearance, however epithelioid transformation can be present. Thesinusoidal pattern is often finest seen at the periphery of the tumour and thus might symbolize an early outgrowth. The stable pattern doubtless results from piling of the tumour cells and will have a fascicular, whorled or fibrosarcoma-like appearance. More intensive scaffold pattern of growth along sinusoids, with focal piling of spindly endothelial tumour cells, associated with atrophic changes of liver cell plates (right). Focal congestion and haemorrhagic change (top) and a few dilation of the former sinusoidal areas (right) is also present. Usually, spindled or some epithelioid endothelial cells are seen interspersed with hepatocytes. Thin-walled vascular areas are composed of scant collagenous tissue and lined by small, bland endothelial cells. Note that entrapped ductular constructions and hepatocytes could be current, especially near the periphery of the lesion. Higher magnification of tumour demonstrating anastomosing tumour channels lined by the crowded, spindly, tumour endothelial cells. This centre of a lesion has small vascular channels with scant stromal component and bland endothelial cells. Variable numbers of scattered inflammatory cells can also be seen; on this case, some focal clusters of eosinophils.
Usage: q._h.
Lipid accumulations consisting of amorphous materials in addition to stacks of lamellar leaflets could also be seen in hepatocytes arthritis research back pain diclofenac gel 20 gm buy lowest price, Kupffer cells and portal tract macrophages is arthritis in neck common diclofenac gel 20 gm buy visa. This method has potential for the investigation of other glycolipid and glycoprotein storage ailments rheumatoid arthritis in upper back order diclofenac gel 20 gm otc. Electron micrograph displaying multiple dense and sometimes laminated inclusions in hepatocytes and in a Kupffer cell arthritis medication ulcers 20 gm diclofenac gel cheap with visa. Electron micrograph displaying concentric lamination of inclusion material, with periodicity of 5�6 nm. Sphingolipid storage ends in progressive demyelination and severe neurological signs. Signs of neurological deterioration embrace progressive psychological retardation, optic atrophy, loss of speech, hypertonic quadriplegia, ataxia and absent tendon reflexes. In the terminal phases of the illness the affected person loses sensory contact with the environment. Progressive neurological abnormalities develop during the course of the illness and embody incoordination, ataxia, spastic paresis, visible issues, tremors, skeletal muscle rigidity, athetotic actions and spastic dysuria. Ultrastructurally, prismatic lysosomes are found in epithelial cells of the gallbladder and are composed of periodic leaflets which appear tubular in cross section. A triad of symptoms, together with joint disease, erythematous subcutaneous nodules (particularly at the wrists) and a hoarse cry, has been described. Aphonia might end result from swelling and granuloma formation within the epiglottis and larynx. Other signs embrace poor feeding and difficulty breathing, which end in poor weight gain, fever and pneumonia. Nerve involvement is widespread notably within the decrease motor neurons, and cerebrospinal fluid protein could also be elevated. Postmortem examination revealed huge histiocytic infiltration of the liver, spleen, lymph nodes, thymus and lungs. The Farber our bodies have additionally been reproduced experimentally in mice by injection of ceramides and related sphingolipids. [newline]The clear vacuoles, which had been also famous in cells lining intrahepatic bile ducts, resembled those seen within the mucopolysaccharidoses. Physical findings include hepatosplenomegaly, lymphadenopathy, opisthotonic posturing, spasticity and cranial nerve involvement. Glycosyl ceramide lipidosis (Gaucher disease) Gaucher disease, the most common lysosomal dysfunction, is attributable to deficiency in acid -glucosidase (glucocerebrosidase) leading to lysosomal accumulation of glucosylceramide (glucocerebroside), primarily in macrophages. Initial proof of neurological involvement could not present until maturity with supranuclear oculomotor deficits. More than 50% of sufferers have delicate haemorrhagic phenomena related to thrombocytopenia. According to knowledge from the International Gaucher Registry, Gaucher sufferers have an increased threat of growing a number of myeloma, however no other tumours. A full surface marker study of the splenic storage cells in a case of Gaucher illness has largely substantiated the monocyte/histiocyte nature of Gaucher cells. The distribution may be focal or zonal, with the perivenular zone being mainly affected. They additionally compress hepatocytes with progressive atrophy and disruption of the hepatic plates. Mutations in each type A and B have been documented and will bear some correlation with phenotype. Perisinusoidal fibrosis and mechanical blockage of sinusoidal areas are presumed to be the cause of portal hypertension, but the pathogenesis of tissue damage in Gaucher disease may be complex and could also contain activation of stellate cells. In cross part the inclusions comprise numerous small tubules, 13�75 nm in diameter. The multisystemic involvement and scientific variability are highlighted in a broad, prospective, crosssectional survey. The discovering of large, foamy macrophages in bone marrow, liver or spleen could be the preliminary clue to the diagnosis. Numerous mutations have been recognized,1705 with the latest finding that the Q775P mutation may correlate with a extreme infantile neurological form and the C177Y mutation with a late infantile clinical phenotype. Rarely, an infant presents with chronic-pattern neonatal liver failure (near-normal serum aminotransferases low serum albumin, coagulopathy). Other manifestations embrace cerebellar involvement (ataxia, dystonia, dysarthria), cataplexy with or with out narcolepsy and studying difficulties. Late modifications include mental regression, seizures and neurological pyramidal indicators. In infants, rectal biopsy might disclose abnormalities in the ganglion cells according to neuronal storage. By this method, lysosomal cholesterol will not be deemed abnormal in 15% of circumstances. The attribute finding is the presence of large macrophages with a foamy or microvesicular cytoplasm. A single, small, eccentric or centrally placed nucleus is usually found in each cell. Hepatocytes additionally include sphingomyelin, and their cytoplasm reveals progressive loss of eosinophilia with growing vacuolization, until they become indistinguishable from affected Kupffer cells. The foam cells are autofluorescent however have a nodular sample, in distinction to the uniform fluorescence of Gaucher cells. Peroxisomal issues Peroxisomes could type by synthesis of their membranes, adopted by importation of enzymes synthesized elsewhere within the cell, or by budding from pre-existing peroxisomes. They perform quite a few capabilities, including catabolism of glyoxylate, -oxidation of phytanic acid, biosynthesis of bile acids, biosynthesis of ether phospholipids (plasmalogens), biosynthesis of docosahexaenoic acid and -oxidation of fatty acids; peroxisomes are essential for -oxidation of very-longchain (C:24 or C:26) fatty acids. The peroxisomal disorders are often subdivided into the next two subgroups1732: � Peroxisomal biogenesis problems. Electron micrograph exhibiting electron-opaque laminated inclusions densely packed within the cytoplasm of a Kupffer cell (�7900). The problems described on this section embrace X-linked adrenoleucodystrophy, di- and trihydroxycholestanoic acidaemia, mevalonate kinase deficiency and grownup Refsum illness. Peroxisomal biogenesis problems Diseases of the Zellweger spectrum symbolize a continuum of scientific disorders with Zellweger syndrome having essentially the most extreme phenotype and neonatal adrenoleukodystrophy, infantile Refsum disease and Heimler syndrome having progressively milder phenotypes. Severity at the two ends of the Zellweger spectrum correlates broadly with mutation sort and impression. Prenatal diagnosis in affected families is feasible utilizing techniques to assess sufficient peroxisomal function. Whereas much progress has been made in biochemistry and genetics of peroxisomal problems, dedication of the pathophysiology and remedy has been gradual. Portal irritation, periportal fibrosis, focal necrosis with development to parenchymal fibrosis, cholestasis and haemosiderosis have been recorded. Patients with extreme fibrosis and disruption of the parenchyma1759�1763 and even cirrhosis1750,1764,1765 have been described. Numerous angulate lysosomes have additionally been famous in Kupffer cells in this disorder. Serum IgD levels (>100 U/mL) stay elevated during the attack, most frequently associated with raised IgA ranges. Disease severity is very variable, as are the time of presentation and rate of disease progression. Many of those disorders affect the neuromuscular system with no identified hepatic involvement. This part focuses on mitochondrial problems in which liver disease is a outstanding medical function. Acquired hepatic mitochondrial disorders, for example, associated with toxicity of nucleoside analogue retroviral medicine or with persistent viral hepatitis, are mentioned in other chapters. Inherited hepatic mitochondriopathies tend to current clinically in infancy or childhood; late hepatic involvement is much less common. Classification of the mitochondriopathies can be difficult, especially as the variety of known mitochondrial cytopathies continues to increase. Diseases can be classified by the genetic defect (autosomal or mitochondrial) or by the affected enzymatic system (oxidative phosphorylation or fatty acid oxidation). A comprehensive classification of mitochondrial illness has been proposed,1801 as well as one specializing in liver involvement. Mitochondria are derived nearly completely from the ovum, since sperm include only a few mitochondria. Gene localization and determination of particular genetic defects are available for a few of the mitochondriopathies.
Tags: 20 gm diclofenac gel generic otc, 20 gm diclofenac gel with mastercard, cheap 20 gm diclofenac gel visa, order diclofenac gel 20 gm with amex, purchase 20 gm diclofenac gel fast delivery, 20 gm diclofenac gel quality, diclofenac gel 20 gm buy, discount diclofenac gel 20 gm line, diclofenac gel 20 gm buy otc, diclofenac gel 20 gm fast delivery, quality diclofenac gel 20 gm, cheap diclofenac gel 20 gm visa, cheap diclofenac gel 20 gm online, cheap diclofenac gel 20 gm on line, diclofenac gel 20 gm lowest price, diclofenac gel 20 gm cheap line
8 of 10
Votes: 210 votes
Total customer reviews: 210
Customer Reviews
Hamlar, 57 years: Increases in hepatitis C virus infection associated to injection drug use amongst persons aged 30 years-Kentucky, Tennessee, Virginia, and West Virginia, 2006�2012. Hyperplasia of small interlobular bile ducts and ductules results in an elevated number of apparently tortuous structures within the portal tracts. Positive staining may be seen in pulmonary adenocarcinomas and fewer usually in adenocarcinomas from other sites, such as abdomen, oesophagus and biliary tree.
Yorik, 42 years: Neonatal liver failure, continual liver illness an essential etiology for neonatal liver failure. Cholesterol gallstones Cholesterol stones are shaped when the bile is supersaturated with cholesterol, which can end result from decreased bile acid manufacturing, increased ldl cholesterol output in bile or both. Iron storage in relations of sufferers with haemochromatosis and in relatives of sufferers with alcoholic cirrhosis and haemosiderosis: a comparative research of 27 families.
Gelford, 35 years: Siderosis of Kupffer and endothelial cells signifies secondary iron overload or ferroportin disease. Diagnosis primarily based on a mix of biochemical, immunological and histological findings. Tall, skinny, dark pencillate cells are scattered among the columnar epithelial cells.
