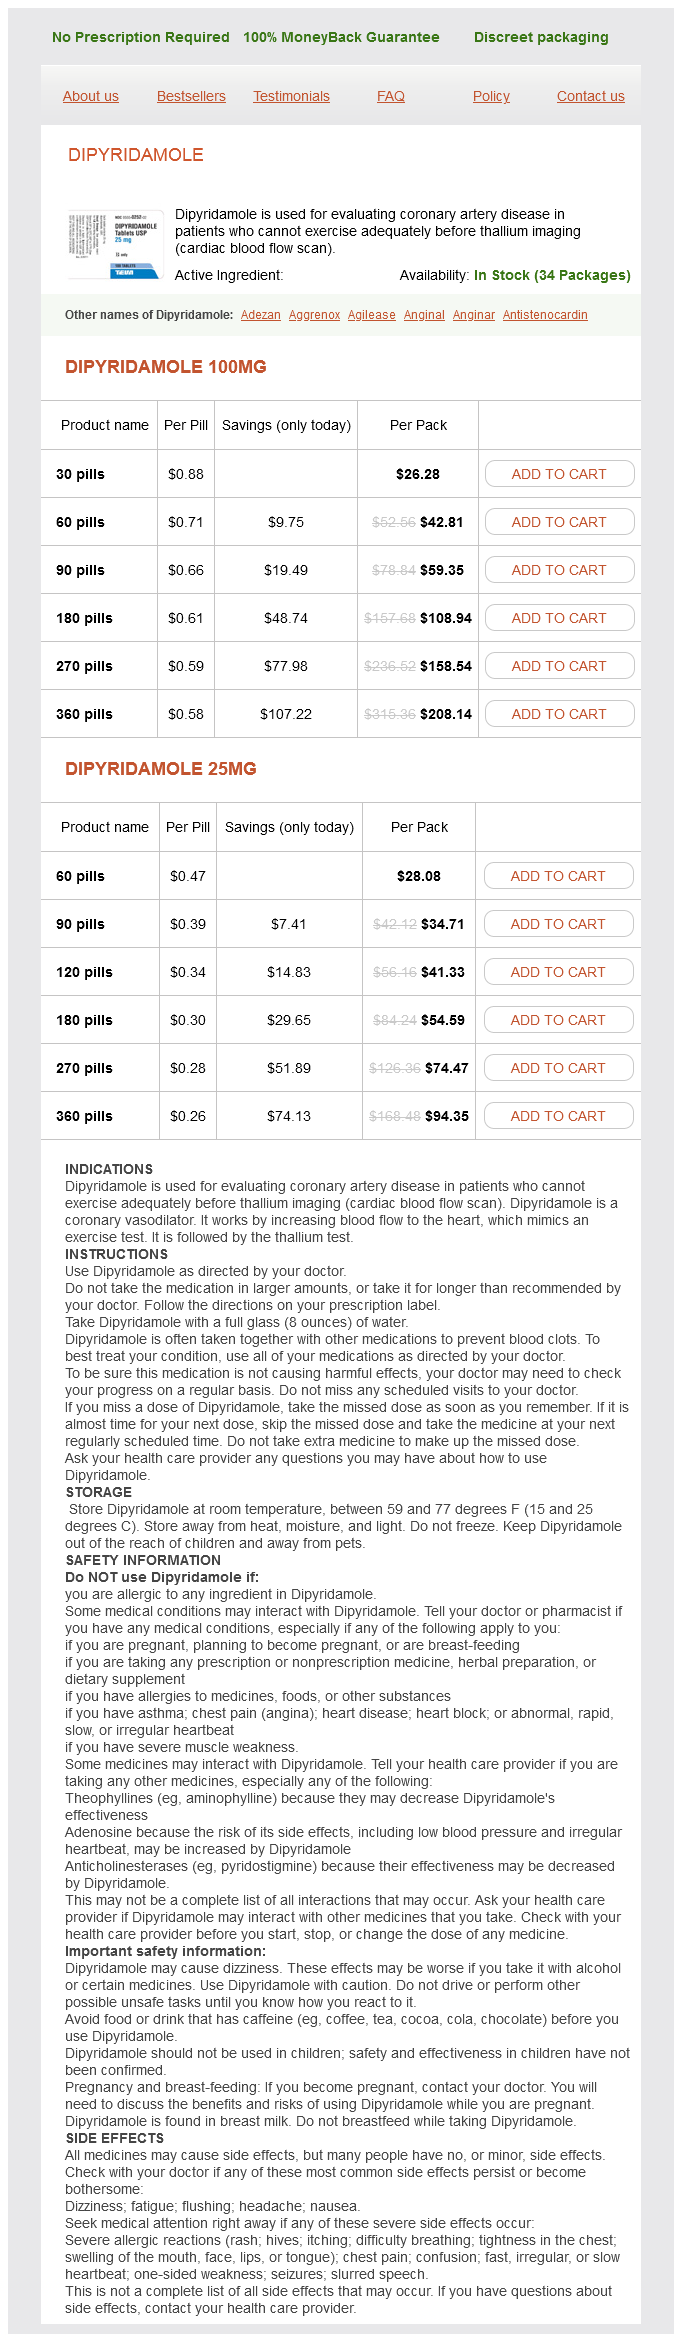
Dipyridamole 100mg
- 30 pills - $26.28
- 60 pills - $42.81
- 90 pills - $59.35
- 180 pills - $108.94
- 270 pills - $158.54
- 360 pills - $208.14
Dipyridamole 25mg
- 60 pills - $28.08
- 90 pills - $34.71
- 120 pills - $41.33
- 180 pills - $54.59
- 270 pills - $74.47
- 360 pills - $94.35
Dipyridamole dosages: 100 mg, 25 mg
Dipyridamole packs: 30 pills, 60 pills, 90 pills, 180 pills, 270 pills, 360 pills, 120 pills
In stock: 639
Only $0,28 per item
Description
Early signs are cramps blood pressure chart health canada 25 mg dipyridamole buy, bloating arteria jugularis externa discount 100 mg dipyridamole with mastercard, and constipation blood pressure medication enalapril side effects dipyridamole 25 mg buy generic, often adopted by blood in the stool blood pressure tracker purchase 25 mg dipyridamole visa. Surface epithelium containing goblet cells (G) and enterocytes (En) invaginates to form an intestinal crypt. Enterocytes have an apical striated border of microvilli that project into the lumen. The crypts, sectioned transversely, seem as often oriented, circular profiles surrounded by lamina propria. The deep straight intestinal glands (or crypts) indenting its floor, at about 0. The layer of cells lining the surface and crypts types a easy columnar epithelium much like that seen elsewhere within the small intestine. The ratio of goblet cells to enterocytes, nevertheless, is larger within the colon than in the small gut, and this ratio slowly will increase from the cecum to the rectum. The extremely cellular lamina propria incorporates many lymphoid nodules that will pierce the muscularis mucosae to reach the submucosa. Paneth cells are seen in the cecum and appendix however are usually lacking from crypts of the remainder of the colon. Crypts comprise stem cells for epithelial renewal, in addition to enteroendocrine cells; these are scattered among enterocytes and goblet cells. The submucosa has the standard tissue components including large quantities of adipose tissue. Other parts of the colon, nonetheless, are invested by an incomplete serosa and suspended by mesentery. Ileocolic artery Superior mesenteric artery Posterior cecal artery Appendicular artery Anterior cecal artery Cross part of appendix. It initiatives from the blind end of the cecum about 2 cm beyond the ileocecal junction. A short mesentery, the mesoappendix, attaches to the mesentery of the terminal ileum. It serves as a conduit for blood vessels, autonomic nerves, and lymphatics that supply the appendicular wall. The histology resembles that of different elements of the colon with some adjustments, such as the distinctive multiple, confluent lymphoid nodules that are a half of thirteen. The nodules, within the lamina propria, protrude into the lumen, thereby narrowing it so it has a slit-like, stellate look. The lumen is wide and patent in early childhood however with age might become partly or utterly obliterated. Lymphoid nodules in the mucosa pierce the muscularis mucosae to occupy the submucosa. The appendix has been assumed to be vestigial, but plentiful lymphoid tissue in its wall and manufacturing of B-lymphocytes in germinal facilities of nodules indicate an immunologic defense perform. As in other parts of the digestive tract, the serosa is made of straightforward squamous epithelium-a mesothelium (Me). These nerve cell our bodies (arrows) and related pale-stained nerve fibers are elements of the enteric nervous system. Obstruction of lumen (often after fecal stasis) causes elevated intraluminal strain adopted by venous hypertension, ischemia of the appendicular wall, and subsequent bacterial proliferation, tissue edema, necrosis, and rupture. Acute appendicitis Gangrenous appendicitis Fecal concretions in inflamed appendix Inflamed retrocecal appendix with adhesions 13. The easy columnar epithelium consists largely of combined enterocytes and goblet cells. M (or membranous) cells are additionally in the epithelium overlying many lymphoid nodules within the lamina propria. These cuboidal to columnar antigen-processing epithelial cells, greatest seen by electron microscopy, have brief microvilli, or microfolds, on their apical floor. The muscularis externa lacks taenia coli and consists of complete outer longitudinal and internal round layers of easy muscle. As in other components of the digestive tract, elements of the enteric nervous system are seen: the myenteric plexus between the two smooth muscle layers, and the submucosal plexus in the submucosa. Acute appendicitis first impacts the mucosa, where edema and leukocyte infiltration happen. Penetration of other layers might result in abscess, necrosis, perforation into the peritoneal cavity, and a complication- peritonitis (inflammation of the peritoneum). The transition from rectum to anal canal is close to the serrated pectinate line (arrows), which shows a color change on the surface. Three transverse semilunar mucosal folds project into the rectal lumen and assist assist of feces earlier than defecation. The 2- to 3-cm-long anal canal ends at the anus, the place its epithelial lining turns into continuous with epidermis of pores and skin. The mucous membrane of the anal canal has 5-10 everlasting longitudinal folds referred to as anal columns of Morgagni. This space of the mucosa appears serrated and is called the pectinate line as a result of it resembles a comb. In the submucosa at the base of each anal column are terminal branches of the superior hemorrhoidal artery and vein. The veins kind an extensive hemorrhoidal venous plexus, which may develop varicosities and lead to inner hemorrhoids. An abrupt transition (double arrows) from simple columnar (left) to stratified columnar (right) epithelium happens in this a half of the pectinate line. Mucus-secreting goblet cells predominate on the mucosal surface and in rectal crypts. In connective tissue underneath the epithelium is a plexus of thin-walled hemorrhoidal veins. In this area, easy columnar epithelium changes abruptly to an intervening transitional zone of stratified columnar epithelium, which turns into nonkeratinized stratified squamous. The arterial provide, venous return, lymphatic drainage, and innervation have different sources on the 2 sides of the road. The pectinate line corresponds to the fetal anal membrane, which marks the boundary between hindgut endoderm and the ectodermal part of the anal canal. The inside round smooth muscle layer in the muscularis externa is thickened-the involuntary inside sphincter. Beyond this sphincter, skeletal muscle fibers of the levator ani form the voluntary exterior sphincter. At the lower finish of the anal canal, the epithelium turns into keratinized and is steady externally with epidermis of skin. Internal hemorrhoids are above the pectinate line and originate from superior hemorrhoidal veins; external hemorrhoids, beneath the road, are from the inferior hemorrhoidal plexus. Causes may embody genetic predisposition and increased pressure within the veins ensuing from repeated straining from constipation or throughout being pregnant. Chronic congestion of the veins, which lack valves, results in thrombosis and bleeding. Intensely eosinophilic parenchyma makes up the Round ligament (ligamentum teres) bulk of the normal liver, which is permeated by many vascular channels (arrows). Twenty % of patients develop cirrhosis (scarring of the liver) within 20 years. It sits slightly below the diaphragm in the higher proper quadrant of the belly cavity and is protected fully by the rib cage. It includes two main lobes of just about equal size-right and left-separated by a falciform ligament and a spherical ligament (ligamentum teres). Two smaller lobes-caudate and quadrate-are seen on the inferior (visceral) surface however are poorly demarcated. Under a peritoneal serous masking, a thin connective tissue (Glisson) capsule surrounds the lobes. On the visceral floor is the porta hepatis, the gateway for the hepatic ducts, portal vein, hepatic artery, lymphatics, and nerves. Parenchymal cells proliferating from this diverticulum cross into mesenchyme of the septum transversum and occupy meshes of a network of capillaries related to vitelline and umbilical vessels. The liver is an accessory gland-both exocrine and endocrine- of the digestive tract and plays a central position in three broad useful categories: metabolism of carbohydrates, proteins, and fats; modification of exogenous substances similar to medication and alcohol; and formation and exocrine secretion of bile, which is crucial for fat digestion. Caused by hepatotropic viruses (A to G), viral hepatitis encompasses a broad array of acute or persistent inflammatory liver problems.
Carthamus Tinctorius (Safflower). Dipyridamole.
- Are there any interactions with medications?
- Dosing considerations for Safflower.
- How does Safflower work?
- What is Safflower?
- Reducing LDL cholesterol.
- What other names is Safflower known by?
- Are there safety concerns?
- Fever, tumors, coughs, bronchial conditions, blood circulation disorders, pain, menstrual disorders, chest pain, traumatic injuries, constipation, inducing sweating, causing abortion, and other uses.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96138
Within lung lobules arrhythmia yahoo generic 100 mg dipyridamole fast delivery, lymphatics typically run within the septa prehypertension foods to avoid purchase dipyridamole 100 mg mastercard, not with the airways or interalveolar walls blood pressure kiosk machines dipyridamole 25 mg generic. Advances in surgical methods blood pressure medication how quickly does it work dipyridamole 100 mg generic on line, improvement of immunosuppressive therapies, and rising public consciousness of organ donor applications have led to its useful remedy for end-stage organ failure by enhancing quality of life and lengthening life expectancy. Although long-term survival charges continue to improve, possible postsurgical problems are organ rejection, infection, renal dysfunction, posttransplant lymphoproliferative dysfunction, and bronchiolitis obliterans syndrome. Novel remedies to handle them are directed to cut back morbidity and mortality in lung transplant recipients. Very slender partitions-the interalveolar septa- demarcate and separate adjoining alveoli. Features of these septa are tough to distinguish by standard gentle microscopy. Two forms of pneumocytes make up this epithelium: sort I cells are flattened and possess a big surface area to facilitate gas trade. Their attenuated cytoplasm, except for the a part of the cell containing the single, elongated, darkly 15. Type I pneumocytes cowl about 95% of the alveolar floor, although they constitute solely 40% of all the epithelial cells. However, due to their shape-more cuboidal-they account for less than 5% of the liner cells. Alveolar macrophages (dust cells) defend alveolar spaces by scavenging the surface. Interalveolar septa are supported by a fragile connective tissue stroma- pulmonary interstitium-that is wealthy in elastic fibers. The major element of the septa is an intensive community of anastomosing pulmonary capillaries that undertake a convoluted course. Most cells within the septa are endothelial cells of capillaries; scattered fibroblasts, macrophages, and occasional mast cells additionally occur. The attenuated endothelium of the capillary, the slender strategy of a type I pneumocyte, and their fused basal laminae represent the primary components of this barrier. A few scattered organelles, together with cytoplasmic vesicles, are within the cytoplasm of each the endothelial cell and pneumocyte. It contains the attenuated endothelium of pulmonary capillaries, kind I pneumocytes lining the alveolus, and their fused basal laminae. In the realm of minimal thickness, sort I pneumocytes have a thin rim of cytoplasm with few organelles besides for so much of cytoplasmic vesicles, which suggests an lively position in fluid and solute transport. Adjacent pneumocytes are sealed by tight junctions, which stop leakage of fluid and solutes. Ultrastructurally, endothelial cells are arranged as an interlocking, contiguous mosaic. Cytoplasm of endothelial cells accommodates (near the nucleus) mitochondria, Golgi complicated, microtubules, microfilaments, Weibel-Palade our bodies, and rough endoplasmic reticulum. Organelles are virtually entirely absent in slender extensions of endothelial cells, which in some areas may be quite thin-only 0. The most putting function of those cells is the presence of quite a few vesicles, which are free within the cytoplasm or intently associated with luminal and abluminal cell surfaces and whose primary operate is to transport fluid and proteins between blood and surrounding interstitium. Short, stubby microvilli project from other elements of the cell surface (small arrows). Profiles of pulmonary capillaries (Cap) and portions of alveolar areas (*) are additionally visible. In this optimally preserved specimen, the fingerprint construction typical of surfactant is obvious. They have a single, centrally placed, rounded nucleus, which is usually euchromatic, with one or two distinguished nucleoli. Short stubby microvilli project from the cellular surface into the alveolar lumen. Their cytoplasm incorporates a well-developed Golgi complex, profiles of rough and smooth endoplasmic reticulum, scattered mitochondria, and peroxisomes. Large, pleomorphic membrane-bound multilamellar our bodies, a singular characteristic of these cells, can be noticed extruding their contents into alveolar spaces. The bodies are crammed with electron-dense lamellar materials and represent secretory vesicles. They are derived from the Golgi complex and are ultimately discharged by exocytosis on the cell floor. This replicative potential is necessary for healing after lung harm, as a outcome of the massive surface area of kind I cells makes them particularly susceptible to harm. Primary and secondary lysosomes are a notable function of its cytoplasm, and its nucleus has an indented margin. Also seen are thin processes of sort I pneumocytes (arrows) lining the alveolus (*), and lumina of two pulmonary capillaries (Cap). They are normally seen bulging into the alveolar house, typically located at junctions between adjoining interalveolar septa. Their cytoplasm accommodates varied organelles, including many main and secondary lysosomes. Their main operate is to ingest mud and other foreign particles that have entered alveolar spaces throughout inspiration. Electron microscopy has shown that the cells have an irregular shape and a surface studded with pseudopodia and short microvilli. These motile cells are derived from blood monocytes whose precursors arise in bone marrow. They migrate throughout the partitions of pulmonary capillaries to the interalveolar septa. They endure maturational division in the interstitium of the lung and then enter alveolar areas to lie free in the lumina. In certain kinds of coronary heart illness, similar to congestive coronary heart failure, erythrocytes from the bloodstream might escape into pulmonary alveolar spaces, where alveolar macrophages may phagocytose them. These swollen macrophages with ingested hemosiderin could additionally be seen in sputum and are known as heart failure cells. Signs embody labored respiration and cyanosis, which are attributable to incapability of pulmonary alveoli to increase or stay open after inspiration. Treatment options depend upon illness severity and prematurity of the infant and include supply of O2 to assist respiration, mechanical air flow, corticosteroid remedy, and delivery of synthetic surfactant to the lungs. Developing respiratory tract (Top) at 4-5 weeks and bronchi and lungs (Bottom) at 5-6 weeks. At 20 weeks Terminal bronchiole Alveolar ducts Terminal sacs (future alveoli) Simple cuboidal epithelium Oropharyngeal membrane Mandibular (1st branchial) arch Ventral aorta Ventricle of heart Pulmonary artery Esophagus Laryngotracheal ridge Trachea Bronchial buds At 24 weeks Respiratory bronchiole Alveolar duct Connective tissue Terminal sacs (future alveoli) Ventral view of pharynx. At this pseudoglandular developmental stage, the lung has a glandular appearance with many thinwalled tubes (arrows) and sacs (*) of varied shapes and sizes lined by simple squamous to cuboidal epithelium. The future larynx develops from the upper a half of the tube; the trachea, from the caudal half. Two knob-like thickenings at its most distal finish turn out to be the bronchial buds, which endure about 20 successive divisions earlier than delivery, followed by continued postnatal growth. Growth of endodermal epithelium is accompanied by invasion and condensation of surrounding splanchnic mesenchyme, which envelops the tube. The mesenchyme offers rise to connective tissue, easy muscle, and cartilage of the airways; endoderm is the supply of the epithelium 15. Bronchi and lungs develop like an exocrine gland: Bronchi are equal to extralobular ducts, whereas bronchioles are counterparts of intralobular ducts. Five phases of lung improvement embrace the embryonic interval from 26 days to 6 weeks, with initial development of lobar bronchi. In the pseudoglandular section between 6 and sixteen weeks, terminal bronchioles, which appear as blind tubules lined with cuboidal or columnar epithelium, develop further. The canalicular period, 1628 weeks, contains growth of acini accompanied by invasion of capillaries from surrounding mesenchyme. The saccular period, 28-36 weeks, is followed by the alveolar interval, from 36 weeks to delivery. Kidney Lateral border Anterior surface of right kidney Fibrous capsule (cut and peeled back) Medial border Hilum Renal artery Ureter Renal vein Renal pelvis Psoas major m. Fibrous capsule Cortex Minor calyces Renal sinus Major calyces Renal pelvis Pelvic ureter Rectum Bladder Medulla (pyramids) Renal papilla Urethra Prostate Renal column Medullary rays Regional anatomy of the urinary system. The kidneys, embedded in fats, lie in a retroperitoneal place (behind the peritoneum, outdoors the stomach cavity), simply anterior to muscular tissues of the posterior abdominal wall.
Specifications/Details
Thus blood pressure form 25 mg dipyridamole cheap fast delivery, when the physique needs to helvetic nerds - blood pressure dipyridamole 100 mg order visa withdraw calcium from its mineral reserves arteriosclerotic cardiovascular disease dipyridamole 100 mg discount mastercard, it could do so solely by resorbing bone (mineral component plus natural matrix) arteria etmoidal anterior dipyridamole 100 mg buy visa. Through the process of coupling, bone formation increases and osteoblasts are stimulated to fill in the resorption defect, though this restore may not be complete within the elderly. Endocrine-mediated bone formation and bone resorption contain more than the stimulation of current differentiated bone cells; these processes are depending on the transformation of undifferentiated stem cells in each osteoblast and osteoclast lineages. Thus, bone formation and bone resorption are contingent not only on the metabolic activity of every cell but in addition on the recruitment of new cells to the job. The main operate of calcitonin, a hormone secreted by the parafollicular cells of the thyroid gland, is to inhibit osteoclastic bone resorption in response to elevated serum calcium ranges. Bone Stimulates recruitment of preosteoclasts Strongly stimulates osteoclastic resorption of bone Inhibits osteoclastic resorption of bone Efficient gastrointestinal absorption of calcium depends totally on daily calcium consumption, vitamin D standing, and age. With the vitamin D axis intact, efficiency of calcium absorption will increase if calcium intake decreases. Some calcium secreted into the gut is absorbed, but a lot of it passes into the stool as unabsorbed calcium. For each additional gram of calcium ingested, solely about 50 mg of additional calcium appears in urine. Thus, the urinary calcium level is better determined by the speed of calcium absorption by the gut than by the quantity of calcium ingested. In the traditional adult skeleton, bone formation and resorption processes are balanced in a state referred to as coupling, in order that web bone formation equals internet bone resorption. Unless a significant metabolic insult occurs to bone early in life, the height grownup bone mass will exceed the brink for spontaneous fracture. Noninvasive techniques to measure bone density have provided a helpful definition of osteoporosis: a mass-per-unit volume of normally mineralized bone that falls under a populationdefined threshold for spontaneous fracture. If net bone resorption exceeds net bone formation, bone mass declines with time (see Plate 2-30). Under these situations, with a speedy fee of bone turnover, the decrease of bone mass is rapid. Conversely, with a slow price of bone turnover, the decline in mass is correspondingly sluggish. Similarly, if web bone formation exceeds web bone resorption (as in regular bone progress and even after longitudinal progress ceases), bone mass will increase with time. Some attainable combos of bone formation/ resorption are shown in the desk in the higher half of Plate 2-30 and graphically offered within the lower half. Example eight represents regular bone turnover: bone formation and bone resorption are appropriately coupled, leading to a stable bone mass with no internet change (black bar on center line). This state of bone transforming is seen in the lively stage of Paget illness (see Section three, Metabolic Diseases, Plates 3-44 to 3-46). Example 11 reveals decreased bone turnover fee, however right here, too, bone formation and resorption are appropriately coupled, with no net change in bone mass. Example 1 depicts a state of severe uncoupling (decreased bone formation and elevated bone resorption), which causes a web decline in bone mass over time. Such an imbalance in formation and resorption occurs in persistent glucocorticoid excess, which may be endogenous (Cushing syndrome) or iatrogenic (see Section three, Metabolic Diseases, Plate 3-26). Example 2 illustrates increased bone turnover rate with a standard price of bone formation but an increased fee of bone resorption. This state is represented in the lower half of Plate 2-30 by the black bar under the zero line and by the red dot above the green column, indicating resultant osteoporosis. Mild Normal bone turnover Decreased bone turnover hyperthyroidism, gentle hyperparathyroidism, and a continual dietary calcium deficiency may cause elevated bone turnover, with resorption exceeding formation. In severe hyperthyroidism and hyperparathyroidism, remodeling charges could be even higher than those shown in example 3, with a correspondingly greater distinction between formation and resorption and infrequently a greater net loss of bone mass. Stimulation of deposition Weight-bearing exercise Growth Fluoride Electricity More (or more active) osteoblasts (B) 2. In a pathologic context, a localized (focal) phenomenon of increased bone formation and resorption with formation exceeding resorption happens in the osteoblastic stage of Paget illness. Example 6 illustrates regular bone resorption paired with an increase in the rate of bone formation, which leads to a web improve in bone mass with time. This is typical during regular progress and growth, particularly between late adolescence (when longitudinal progress ceases) and approximately age 35 (when peak adult bone mass is reached). Example 7 reveals the extremely uncoupled state of increased bone formation and decreased bone resorption that result in a web enhance in bone mass. Such a state of reworking is seen within the grownup, or autosomal dominant, type of osteopetrosis (see Section three, Metabolic Diseases, Plate 3-43). In this disorder, the lowered rate of bone resorption is due to the relative decline in osteoclastic bone resorption; the speed of bone formation could additionally be regular or elevated. This form of uncoupling can also be induced by pharmacologic doses of fluoride administered to stimulate bone formation and stabilize bone apatite crystal and render it more proof against breakdown. Example 9 reveals a state of regular bone resorption with decreased bone formation, which leads to reduced bone mass and osteoporosis. This can happen after exposure to a poison or toxin that affects the osteoblasts, as with use of certain chemotherapeutic agents and continual alcohol abuse. In example 10, both bone formation and resorption are decreased however bone resorption nonetheless exceeds bone formation. This is seen when calcium and vitamin D supplementation helps to diminish age-related bone loss. Example 13 exhibits a positive bone balance ensuing from a normal fee of bone formation and a decreased rate of bone resorption. This occurs in women receiving replacement therapy with calcium and estrogen or calcium and calcitonin soon after menopause. These agents, administered independently or together, act to lower bone resorption. The coupling process then causes bone formation charges to modify downward accordingly (example 12); eventually, bone mass stabilizes at a much decrease fee of bone transforming (example 11). In a more extreme instance, administration of bisphosphonates to sufferers with osteoporosis nearly eliminates bone resorption rates and, as a consequence of coupling, bone formation charges also considerably decline over remedy time. Inhibition of withdrawal Weight-bearing activity Estrogen Testosterone Calcitonin Adequate vitamin D consumption Adequate calcium intake (mg/day) Child: 400�700 Adolescent: 1,000�1,500 Adult: 750�1,000 Pregnancy: 1,500 Lactation: 2,000 Postmenopause: 1,500 Level of bone mass stays constant when fee of deposition equals fee of withdrawal (osteoblastic exercise equals osteoclastic activity), whether each rates are high, low, or regular. However, in many circumstances, early adjustments shall be checked by concomitant stimulation of the opposing bone cell population-stimulation of osteoclasts (resorption) leads to a coupled stimulation of osteoblasts (formation). However, enough calcium can be tough to get hold of in many reasonable diets and has led to fortifying meals merchandise with supplementary calcium. On the opposite hand, phosphate is current in almost all foods and dietary deficiencies are uncommon. Accessory elements selling absorption of calcium from the intestine embody an acid pH, a low serum phosphate concentration (to keep away from exceeding the critical solubility product talked about within the first axiom above), and the absence of chelators similar to phytate, oxalate, or excessive free fatty acids. The mechanism of phosphate absorption is less selective than that of calcium absorption but additionally appears to be a minimum of partly dependent on the vitamin D metabolites. Because dietary intake of phosphate varies extensively and absorption is kind of unrestricted, the primary axiom would possibly suggest that people stand poised getting prepared to metastatic calcification and ossification due to a excessive, uncontrollable intake of phosphate. In fact, the renal excretory mechanisms exert a fine-tuned control over phosphate ion ranges. Acting on the level of the intestine lining cell (with vitamin D) to increase absorption of calcium 3. Acting at the level of the renal tubule (with vitamin D) to improve tubular reabsorption of filtered calcium four. Acting on the degree of bone (with vitamin D) to increase the inhabitants of activated osteoclasts, which destroy not only the hydroxyapatite crystals but also segments of organic bone matrix, thus releasing both calcium and phosphate ions 5. This is achieved principally by diminishing the osteoclast inhabitants and exercise and, to some extent, by lowering gastrointestinal absorption. However, it ought to be clearly noted that although the second mechanism may be nicely developed in avian species and though administration of exogenous, non� species-specific calcitonin could have a profound impact on the skeleton, the natural mechanism in humans seems to be too limited to defend the body from hypercalcemia. Hyperphosphatemia, or elevated focus of serum phosphate, might lead to metastatic calcification, significantly in renal failure, since the important solubility product could be exceeded even when calcium levels are normal. Also, gastrointestinal absorption and tubular reabsorption of calcium, and even bone breakdown, are initially lowered, thus diminishing the focus of calcium. The basic axioms and the interactions of the various hormonal and mineral supplies mentioned listed here are important in understanding the principles that govern and management the homeostatic mechanisms and the alterations that lead to the rachitic syndrome (see Plates 2-28 and 2-29, and Section three, Metabolic Diseases, Plates 3-13 to 3-23). These axioms are distinct, representing chemical, physiologic, and biologic information. In truth, on the pH of physique fluids and the concentrations of calcium and phosphate ions found in extracellular fluids, the important solubility product is approached and sometimes exceeded.
Syndromes
- Large scars that take a long time to heal
- Posterior urethral valves
- You had chickenpox before age 1
- Bleeding time
- Enlarged spleen or liver
- Slurred speech
- You are very sensitive to light.
- Medicines to relieve pain
- The Compassionate Friends - www.compassionatefriends.org
Related Products
Additional information:
Other nerves which could be anesthetized embody the phrenic nerve (which is why bilateral deep cervical plexus blocks should be carried out with caution blood pressure 45 year old male dipyridamole 100 mg cheap on line, if at all) blood pressure 800 25 mg dipyridamole for sale, and the recurrent laryngeal nerve prehypertension in young adults discount dipyridamole 25 mg overnight delivery. Some local anesthetic might unfold exterior the deep cervical fascia and may produce blockade of the sympathetic chain pulse pressure 58 25 mg dipyridamole discount mastercard, producing Horner syndrome. The accessory nerve comes out cephalad to the injections (Barash: Clinical Anesthesia, ed 7, pp 946�947; Hebl: Mayo Clinic Atlas of Regional Anesthesia and Ultrasound-Guided Nerve Blockade, ed 1, pp 179�185). The ciliary ganglion (deep within the orbit and lateral to the optic nerve) and ciliary nerves are additionally blocked, offering anesthesia to the conjunctiva, cornea, and uvea. All of the muscular tissues of the larynx are innervated by the recurrent laryngeal nerve except for the cricothyroid muscle. The superior laryngeal nerve divides into the interior and external laryngeal branches. The vertebral artery lies anterior to the ganglion, because it has just originated from the subclavian artery. Under these circumstances, injection of a local anesthetic or narcotic could produce stress that might presumably result in ischemia and neurologic injury. The posterior department of the tibial nerve offers rise to the medial and lateral plantar nerves, which supply the plantar surface of the foot (Barash: Clinical Anesthesia, ed 7, pp 990� 991; Hebl: Mayo Clinic Atlas of Regional Anesthesia and Ultrasound-Guided Nerve Blockade, ed 1, pp 444�448). In the overwhelming majority of these instances (80%), phantom limb sensation persisted till the block receded. Accordingly, the only acceptable choice on this query could be basic anesthesia with propofol, succinylcholine, nitrous oxide, and fentanyl. With complete bilateral transections of the recurrent laryngeal nerve, each the abductor and adductor muscles are affected, and the vocal cords will undertake an intermediate place. Acute complete injury to the recurrent laryngeal nerves may find yourself in stridor and respiratory distress requiring remedy. If a affected person sustained a partial bilateral paralysis of the recurrent laryngeal nerve that affected solely the abductor muscular tissues, then the unopposed adductor muscle tissue would deliver the cords collectively. When the head is elevated, the headache may be severe, is bilateral, and could also be related to diplopia, nausea, and vomiting. Typically the onset of the headache is 12 to 24 hours after a dural puncture and lasts several days if untreated (rarely it could possibly final for months). The different complications listed hardly ever have a major postural element (Barash: Clinical Anesthesia, ed 7, pp 926�927; Miller: Basics of Anesthesia, ed 6, pp 271�272). The block is performed by walking off the inferior fringe of the rib with the needle, usually about 5 to 7 cm from midline. The two principal risks are pneumothorax and intravascular injection of native anesthetics. Because of the close proximity of the vein and artery to the nerve, intercostal blocks have comparatively high blood levels as in comparison with different blocks. The degree of absorption from the positioning of injection is decided by the blood provide to that web site. The impartial (non-ionized) type of the molecule is prepared to cross through the lipid nerve cell membrane, whereas the ionized (protonated) form really produces anesthesia. Despite this truth, 3% chloroprocaine has a more speedy onset than 2% lidocaine, presumably because of the greater variety of molecules (concentration). A pneumothorax ought to be thought-about if the patient begins to complain of chest ache or shortness of breath or begins to cough throughout placement of supraclavicular brachial plexus block. The anterior division provides motor innervation to the sartorius muscle and cutaneous sensation to the anterior and medial aspects of the thigh. The posterior division innervates the quadriceps muscle and cutaneous sensation to the anterior, medial, and lateral features of the knee in addition to the articular elements of the knee joint. The nerve passes underneath the inguinal ligament and lies simply lateral to the femoral artery and vein. Proper needle placement will elicit quadriceps muscle contraction with patellar elevation that disappears with native anesthetic injection (Hebl: Mayo Clinic Atlas of Regional Anesthesia and Ultrasound-Guided Nerve Blockade, ed 1, pp 347�362). An obturator nerve block is achieved by placement of the needle 1 to 2 cm lateral to and 1 to 2 cm below the pubic tubercle. After contact with the pubic bone, the needle is withdrawn and walked cephalad to establish the obturator canal. The most typical complication is a phrenic nerve block, which is normally mild and relatively frequent (30%-60% of blocks). These roots at the level of the scalene muscle turn into the three trunks: superior, middle, and inferior. The trunks then divide into the dorsal and ventral divisions on the lateral fringe of the primary rib. When the divisions enter the axilla, they turn out to be the cords: posterior, lateral, and medial. At the lateral border of the pectoralis muscle, they turn into the five peripheral nerves: radial, musculocutaneous, median, ulnar, and axillary. The interscalene block is on the degree of the roots/trunks (but spares the inferior trunk); the supraclavicular block is on the degree of the trunks/divisions; the infraclavicular block is at the degree of the cords; and the axillary block is at the degree of the branches (Barash: Clinical Anesthesia, ed 7, pp 959�966; Hebl: Mayo Clinic Atlas of Regional Anesthesia and Ultrasound-Guided Nerve Blockade, ed 1, pp 225�226; Miller: Basics of Anesthesia, ed 6, pp 287�292). Alcohol 247 causes pain when injected and sometimes is mixed with bupivacaine, whereas phenol is relatively painless. Alcohol has a barely longer duration of analgesia (3-6 months) compared to phenol (2-3 months). Therefore, higher-frequency ultrasound is typically used for shallower constructions, and lower frequencies are used for deeper structures. Usually the depth is adjusted so the construction in question is in the middle, top-to-bottom, of the image. Increasing the acquire increases, or amplifies, the mirrored sign power and increases the brightness of the image (Hebl: Mayo Clinic Atlas of Regional Anesthesia and Ultrasound-Guided Nerve Blockade, ed 1, pp 99�112). The timing of ambulation relative to dural puncture has not been shown to have an result on the incidence of postspinal headache. Visceral ache is brought on by any stimulus that excites nociceptive nerve endings in diffuse areas. In this regard, distention of a hole viscus causes a larger sensation of ache than does the highly localized damage produced by transecting the gut. When bupivacaine with epinephrine (1:200,000) is used, epidural anesthesia might final one hundred eighty to 350 minutes; infiltration anesthesia may final a hundred and eighty to 240 minutes; and major nerve blocks similar to axillary block could last 360 to 720 minutes. Spinal bupivacaine with out epinephrine might last 90 to 200 minutes; if epinephrine (0. Remembering that the femoral nerve (which innervates the quadriceps muscles) is a distal branch helps one to understand why quadriceps muscle contraction is useful in finding the plexus with a stimulating needle (1-1. If the hamstring muscles are stimulated, the needle is too caudally positioned, and the 248 Part 2 Clinical Sciences needle should be aimed in a more cephalad direction. Continuous psoas catheters are commonly used for postoperative analgesia (Barash: Clinical Anesthesia, ed 7, pp 978�980; Hebl: Mayo Clinic Atlas of Regional Anesthesia and Ultrasound-Guided Nerve Blockade, ed 1, pp 333�345). The sciatic nerve distally becomes the tibial and peroneal nerves, which may be blocked at the popliteal fossa for surgery below the knee. This complication can be avoided by quantity loading the patient with lactated Ringer answer. By blocking the sympathetic chain, unopposed parasympathetic exercise may result in elevated gastrointestinal exercise and transient diarrhea. Paraplegia may result from spasm of the lumbar segmental arteries that perfuse the spinal wire, direct vascular or neurologic damage, or retrograde unfold of drug to the nerve roots and spinal wire. Since the paravertebral area is steady with the epidural house medially, epidural unfold may outcome if large volumes of local anesthetic are injected into the paravertebral. Typically 5 mL are injected at each of three sites for unilateral paravertebral blocks, and three mL per every of six sites (three on each side) if bilateral paravertebral blocks are carried out. If the needle is directed too medially, then the intrathecal area may be entered (dural sleeves extend to the level of the intervertebral foramina) with the potential of a complete spinal if 5 to 10 mL is injected. Blockade of the sympathetic fibers (T1-L2) produces hypotension, notably if the affected person is hypovolemic. Respiratory arrest is as a outcome of of hypoperfusion of the respiratory centers as well as paralysis of the phrenic nerve (C3-C5). Cauda equina syndrome has occasionally developed when the epidural dose was unintentionally administered into the subarachnoid house (most generally with chloroprocaine). Anatomy, Regional Anesthesia, and Pain Management Central pain states might embrace encephalization, psychogenic ache, or malingering. Because local anesthetics are either amino esters or amino amides, decreasing the pH permits extra binding of hydrogen ions to the amino group, making it more ionic or protonated, which traps the local anesthetic inside the cells.
Usage: q.i.d.
This flat pulse pressure is calculated by dipyridamole 25 mg buy on-line, almond formed organ sits beneath the mucous membrane within the floor of the mouth heart attack 51 effective 100 mg dipyridamole. Minor salivary glands are small blood pressure chart hypertension 25 mg dipyridamole otc, isolated glands in the lips blood pressure medication beginning with a dipyridamole 25 mg buy cheap on line, cheeks, tongue, and palate. They are mainly blended seromucous glands, however purely serous or mucous glands are found in isolated sites. These glands have a parenchyma (of glandular epithelium) and connective tissue stroma. The parenchyma derives from oral cavity ectoderm: at about 6 weeks of gestation, strong buds kind from oropharyngeal epithelium. The buds purchase a lumen and develop into tubuloacinar secretory end items and a branching duct system. Mesenchyme around the parenchyma offers rise to the stroma and capsule of the glands. Adipocytes (Ad) occur mainly in the parotid, not typically seen in the two other major salivary glands. Serous cells in every acinus have round basal nuclei and are organized round a small central lumen. Simple columnar epithelium strains the bigger lumina of striated ducts, so named because of striations within the basal cytoplasm of the lining cells. The septa are a sup portive framework for the gland and a conduit for blood vessels and autonomic nerves. The parotid, a branched tubuloacinar gland, is composed of clusters of elongated, branched serous acini. A basement membrane surrounds every acinus and encloses a number of flat myoepithelial cells which might be onerous to see in typical preparations. Intercalated ducts, the preliminary a half of the duct system, are slender conduits formed of 1 layer of squa mous or cuboidal epithelial cells. They drain into striated ducts, that are lined by columnar cells with basal striations. Both inter calated and striated ducts are intralobular and are secretory ducts due to their metabolic activities. A delicate, richly vascularized stroma surrounds secretory acini and intralobular ducts. Initial segments of interlobular ducts are lined by stratified cuboi dal epithelium, which steadily becomes stratified columnar after which pseudostratified as duct diameters improve. Near the main outlet of the most important (Stensen) duct, the epithelium turns into strati fied squamous as it opens into the oral cavity vestibule. Before the vaccine, it was a typical childhood communicable disease affecting both sexes equally. It causes swollen and painful parotid glands (both glands or one), plus headache, malaise, and fever. The parenchyma of the gland is diffusely infiltrated by plasma cells and macrophages, followed by degeneration of acini and vacuolation of ductal epithe lium. Inflammation of the testes (orchitis) happens in 25%30% of contaminated males, but infertility is rare. Serious issues, similar to pancreatitis, encephalitis, and meningitis, could develop. A few myoepithelial cells (My) are related to acini and share a basement membrane with the mucous cells. Lightly eosinophilic columnar cells with basal striations (arrows) line a central lumen (*). The intercalated duct empties into a larger striated duct lined by tall columnar cells with basal striations. Unlike the parotid, nevertheless, the submandibular has both serous and mucous acini, the bulk being serous. The gland also has combined seromucous acini, during which lighter staining, bigger mucous cells around a central lumen are capped by cres centshaped serous demilunes of flattened serous cells. The basal nuclei of mucous cells are often flattened, not rounded, and apical cytoplasm appears washed out because of large mucin droplets. Unlike the parotid and submandibular glands, the sublingual gland lacks a transparent fibrous capsule. Both submandibular and sub lingual glands have intralobular and interlobular ducts like those within the parotid, in addition to a conspicuous characteristic distinctive to salivary glands-striated ducts. Basal striations in the easy columnar epithelial cells in these ducts set them apart from different parts of 12. Hematoxylin and eosin (H&E) staining reveals cells as intensely eosinophilic, indicating many mitochondria. Unlike the parotid, with variable amounts of adipose tissue in its stroma, and the sublingual gland, which has adipocytes, the submandibular gland often lacks adipocytes. Symptoms are dryness and discomfort of the oral cavity, cracked lips, and halitosis (bad breath). By promoting bacterial development, it might result in tooth decay, elevated plaque formation, gum disease, and oral candidiasis. In addition to radiation and chemotherapeutic agents for cancer remedy, problems such as Parkinson illness and the autoim mune Sj�gren syndrome may trigger it. Surrounding the duct are scattered connective tissue cells, venules, and capillaries (Cap). Many of the ample mitochondria (Mi) are oriented vertically to the base of each cell. Deep infoldings (arrows) of plasma membrane invaginate the basal side and interdigitate extensively with these of adjoining cells. Long slender mitochondria (Mi), oriented in parallel, are within cytoplasmic compartments shaped by the infoldings and have many carefully packed cristae. The ducts modify the composition of saliva via resorption of Na+, which makes saliva hypotonic. Basal striations, which are perpendicular to the bottom of the cells, are the attribute function. Apical sur faces, which are in contact with the duct lumen, bear short stubby microvilli. These areas additionally comprise small secretory granules that store kallikrein, a vasoactive substance, and secretory immunoglobulins. Lumen Stratified squamous epithelium Muscularis mucosae Submucosa Circular clean muscle Trachea Arch of aorta Bronchus Thoracic (descending) aorta Thoracic part of esophagus Esophageal branches of thoracic aorta Diaphragm Abdominal a part of esophagus Stomach Longitudinal part: Upper third. Stratified squamous epithelium Muscularis mucosae Deep (submucosal) glands with duct Two layers of easy muscle Longitudinal skeletal muscle Transverse section: Middle third. It propels partly digested meals by peristalsis from the laryngopharynx to the stomach. Like other parts of the digestive tract, it has 4 primary layers: mucosa, submucosa, muscularis externa, and adventitia. But not like the other elements, its muscularis externa consists of two types of muscle tissue. The upper third of the esophagus has skeletal muscle fibers; the center third, a mix of easy and skeletal muscle; and the decrease third, solely smooth muscle. The upper sphincter is an anatomically distinct construction of skeletal muscle fibers of the cricopharyngeus muscle. At the lower end (distal 5 cm), in contrast, is a physiologic sphinc ter, less properly outlined histologically, that normally prevents reflux of gastric contents. During passage of a food bolus, the distensible esophageal wall permits the folds to flatten out because of its excessive content material of elastic tissue. When portal blood flow is obstructed, these veins function collateral vessels between portal and systemic cir culations. Increased endo thelin1 (a vasoconstrictor) and decreased nitric oxide (a vasodilator) have been implicated in pathogenesis of portal hypertension and esophageal varices. The muscularis externa has inside (In) and outer (Ou) clean muscle layers; the adventitia, nerves (Ne) and lymphatic channels (Ly). The multilayer epithelium is 300500 mm thick; is nicely suited to shield in opposition to friction, abrasion, and damage; and has basal, inter mediate, and superficial layers. Basophilic cuboidal cells type the basal layer, which, as in different stratified epithelia, is mainly a mitotic and regenerative zone. Continuous renewal of epithelial cells normally takes 1421 days as cells slowly migrate to the floor and desquamate. Above the basal layer, maturing cells turn out to be flatter and accumulate glycogen, which is seen as washed out areas in conventional preparations.
Tags: dipyridamole 100 mg quality, dipyridamole 100 mg purchase with visa, 100 mg dipyridamole generic overnight delivery, buy dipyridamole 100 mg low price, 100 mg dipyridamole generic with amex, purchase dipyridamole 25 mg fast delivery, dipyridamole 25 mg on line, dipyridamole 25 mg cheap online, 100 mg dipyridamole otc, dipyridamole 25 mg generic without prescription, buy 25 mg dipyridamole fast delivery, generic dipyridamole 100 mg, buy dipyridamole 25 mg without a prescription, dipyridamole 100 mg discount free shipping, 100 mg dipyridamole buy with amex, dipyridamole 100 mg cheap with visa
9 of 10
Votes: 176 votes
Total customer reviews: 176
Customer Reviews
Brant, 26 years: Anteroposterior radiograph reveals large cell tumor of epiphysis and metaphysis of distal femur extending into however not penetrating subchondral plate. Larger lesions could be handled surgically with split-thickness skin grafting; often, major skin closure is accomplished by mobilization of adjoining skin flaps.
Finley, 24 years: Phenylephrine, an -adrenergic receptor agonist, is the drug of alternative for remedy of hypercyanotic assaults, because presumably phenylephrine will increase systemic vascular resistance, which reduces the intracardiac right-to-left shunt and improves arterial oxygenation. Pooling of local anesthetics in dependent areas of the backbone inside the subarachnoid house has been identified because the causative think about instances of cauda equina syndrome.
Bozep, 48 years: It is normally trans mitted as a part of an autosomal dominant phenotype with slight variation. Physical examination reveals tenderness, ache and crepitation with joint movement, and, normally, a restricted vary of movement.
Khabir, 27 years: Testes include small convoluted seminiferous tubules, whose germinal epithelium produces male germ cells often recognized as spermatozoa, and interstitial connective tissue. Muscles can reply to exercise patterns by an applicable shift in their metabolic traits.
Kliff, 32 years: Provitamin D2 (ergosterol) is ingested or provitamin D3 (7-dehydrocholesterol) is synthesized from ldl cholesterol by the liver, and each are saved within the skin. The cell types are classed according to particular secretory product, but all conform to the same ultrastructural plan.
