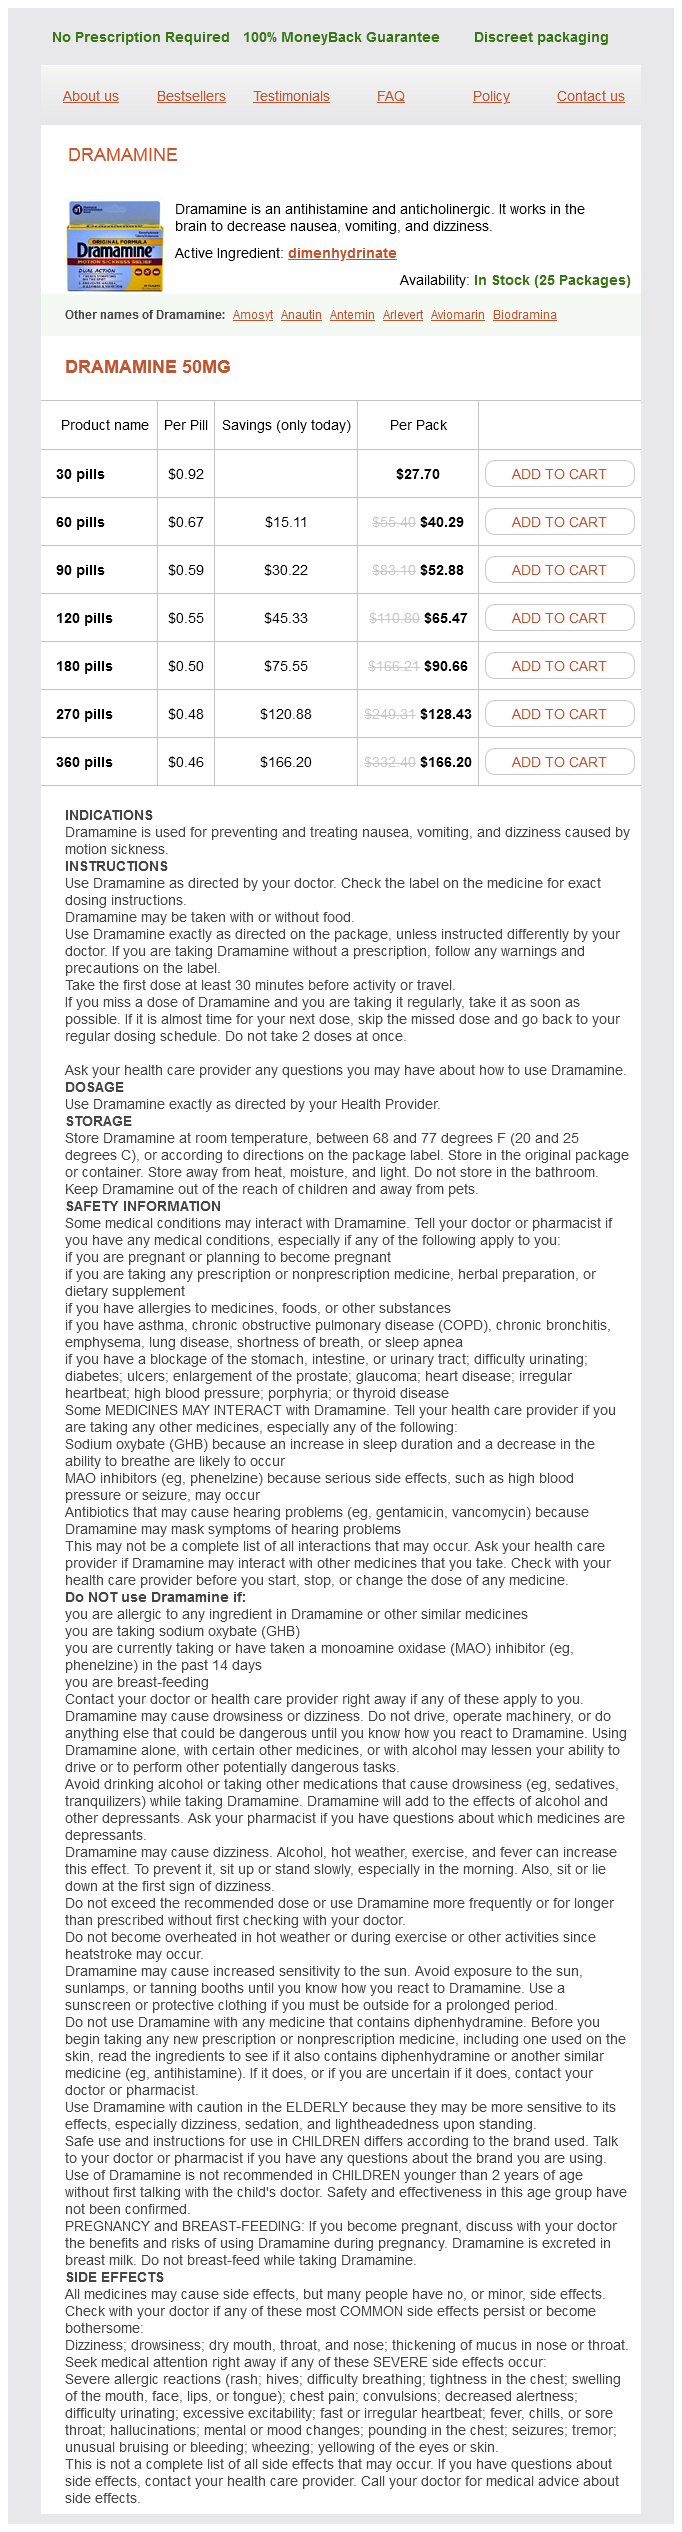
Dramamine 50mg
- 30 pills - $27.70
- 60 pills - $40.29
- 90 pills - $52.88
- 120 pills - $65.47
- 180 pills - $90.66
- 270 pills - $128.43
- 360 pills - $166.20
Dramamine dosages: 50 mg
Dramamine packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 529
Only $0,49 per item
Description
If cardiac output continues to decrease from insufficient circulating blood volume (>15% reduction) symptoms at 4 weeks pregnant dramamine 50 mg purchase overnight delivery, the baroreceptor reflex triggers an increase in the coronary heart rate to preserve cardiac output medications with acetaminophen discount dramamine 50 mg fast delivery. Sympathetic stimulation through the discharge of endogenous catecholamines from the adrenal glands produces vasoconstriction of nonessential organs facial treatment dramamine 50 mg purchase online. Blood is redirected away from the pores and skin medicine uses dramamine 50 mg on line, skeletal muscle, and the splanchnic circulation to maintain perfusion of important organs. If circulating quantity loss continues (>40% reduction) in the absence of adequate resuscitation, compensatory mechanisms might not be ready to maintain cardiac output and decompensated hypovolemic shock follows. Treatment Hypovolemic Shock Hypovolemic shock occurs following an acute, decompensated lower in circulating blood quantity (also see Chapters 42 and 45. Decreases in intravascular volume reduce cardiac preload (left ventricular end-diastolic volume), which is a major determinant of cardiac output. Hypovolemia mostly occurs throughout massive blood loss from trauma, surgical procedure, or gastrointestinal Adequate intravascular quantity resuscitation and supply control are key to the treatment of hypovolemic shock. Ideal access involves brief, large-bore intravenous peripheral catheters, preferably 16-gauge or greater. Balanced salt solutions, corresponding to lactated Ringer answer or Plasma-Lyte, may be preferable, as their composition and osmolality more carefully resemble that of human plasma. If important signs improve in response to resuscitation, then laboratory measurements (especially hemoglobin values) may be obtained to guide the necessity for blood merchandise (also see Chapter 24). In trauma patients (also see Chapter 42), permissive hypotension may need to be employed till bleeding is managed in sufferers requiring emergent surgical intervention. In the event of average to severe hypovolemic shock due to acute blood loss, the empiric administration of blood merchandise could also be needed prior to acquiring laboratory measurements. Additionally, an preliminary hematocrit worth could additionally be misleading if compensatory mechanisms or crystalloid resuscitation has not led to the dilution of the remaining purple blood cell mass. During large transfusion, outlined as the need for 10 models packed red blood cells in 24 hours or 4 units in 1 hour, contemporary frozen plasma and platelets should be administered in a 1:1:1 ratio to packed red blood cells11 (also see Chapter 24). Treatment Cardiogenic Shock Cardiogenic shock outcomes when both the left or right ventricle is unable to contract effectively to generate an sufficient stroke quantity. Ventricular end-diastolic quantity rises leading to distention of the ventricle and the development of pulmonary edema in left-sided failure or distended neck veins, peripheral edema, and hepatic congestion in right-sided failure. Biventricular failure may finish up when the pulmonary congestion from left ventricular failure leads to pulmonary artery hypertension and concomitant right ventricular failure. Clinical Manifestations Causes of cardiogenic shock embrace acute myocardial infarction, extreme cardiomyopathy, myocarditis, arrhythmia, valvular rupture, or ventricular septal defect. To maintain systolic blood stress, compensatory tachycardia happens to offset the decreased stroke quantity. This often worsens myocardial oxygen stability because the tachycardia increases oxygen consumption by allowing much less time for diastolic subendocardial perfusion. Increasing end-diastolic pressure additional reduces subendocardial blood move, worsening oxygen delivery to the failing ventricle. As ventricular operate continues to fail, the compensatory tachycardia is unable to maintain cardiac output and hypotension follows. Patients typically develop poorly perfused extremities as sympathetic outflow results in peripheral vasoconstriction. Invasive screens, together with arterial and central venous traces, assist to guide therapy. In severe cardiogenic shock with hypotension, the administration of inotropic and vasopressor support helps to increase perfusion to the myocardium and different important organs, however may improve myocardial oxygen demand. For severe hypotension, administration of norepinephrine as compared to dopamine improves outcomes with fewer arrhythmias. As an inodilator, dobutamine typically decreases arterial blood pressure but improves ahead circulate and perfusion of important organs. Often norepinephrine and dobutamine are administered together to enhance cardiac output while maintaining adequate coronary artery filling pressures. Diuresis is key to enhancing cardiac filling pressures however ought to be undertaken judiciously if the hemodynamics are tenuous. In sufferers with proof of cardiogenic shock accompanied by hypertension, vasodilators such as nitroprusside or nitroglycerin could help to decrease afterload and preload and improve ahead circulate. For sufferers with cardiogenic shock complicating an acute myocardial infarction, early revascularization improves mortality rate. In the case of tachyarrhythmias precipitating cardiogenic shock, the popular antiarrhythmic is amiodarone as it possesses much less adverse inotropic impacts than -adrenergic blockers or calcium channel blockers. Vasodilatory Shock Vasodilatory shock encompasses an array of well-defined medical entities that embrace septic, anaphylactic, and neurogenic shock. Capillary leakage of intravascular quantity into the extracellular space further worsens the hemodynamics and leads to tissue hypoperfusion, which outcomes in anaerobic metabolism and lactic acidosis. If the underlying course of continues to evolve, multiorgan ischemia and failure develop. Clinical Manifestations Hemodynamic Monitoring Appropriate monitoring of patients with shock performs a key role in therapy. Intensive care settings not only allow for more frequent monitoring but in addition for the position of steady, invasive screens. Arterial Pressure Vasodilation occurs by way of completely different mechanisms in septic, anaphylactic, and neurogenic shock. Anaphylaxis is due to launch of mediators from white blood cells triggered by immunologic mechanisms. Neurogenic shock generally follows a traumatic harm to the mind or spinal twine during which sympathetic outflow to the periphery is interrupted. However, with illness development, the pores and skin can turn into cool and cyanotic as a result of poor end-organ perfusion. Central Venous Pressure Treatment first involves substitute of the effective circulatory volume initially lost owing to pooling of venous blood or capillary leakage. When resuscitation of intravascular volume is unable to restore circulation, vasopressors must be given. In neurogenic shock, adequate perfusion to the injured spinal twine must be maintained to restrict secondary ischemic injury, so the objective is to institute early applicable fluid resuscitation. Anaphylactic shock is handled initially with epinephrine because the vasopressor of choice. Clinical care has shifted more towards the utilization of noninvasive hemodynamic monitoring that provides dynamic measures of intravascular fluid responsiveness. The goal is to perform a focused examination to reply a selected clinical question. With coaching in centered point-of-care echocardiography, important care physicians are in a position to correctly identify ventricular dysfunction greater than 80% of the time. However, measurements should be taken during positive-pressure ventilation, the tidal volume should be no much less than 8 mL/kg, and the guts should be in sinus rhythm. Bedside ultrasonography can also provide procedural steering for placement of peripheral intravenous catheters, arterial strains, and central venous catheters. Use of realtime ultrasound for inner jugular central line placement has been associated with fewer complications, fewer failed attempts, and shorter process times. There are fewer research of ultrasound steerage for placement of arterial traces or subclavian central traces, however use of ultrasonography could enhance the success charges of these procedures as nicely. For example, when alveoli are full of fluid, reverberation artifacts can be seen on the pleural surface, which are called "B-lines" or "lung rockets. However, the fundamental method of early recognition, fast cardiorespiratory resuscitation, quick antibiotic administration, and identification and treatment of the infectious supply has withstood the check of time. Early antibiotic administration and supply management are essential components to sepsis administration. Perhaps the ultimate lesson from all these research is that management ought to be based on clinical examination findings and patient necessities versus absolute numbers obtained by invasive monitors. The workup should embrace cautious bodily examination and assessment of intravascular quantity standing to have the ability to differentiate hypovolemia leading to prerenal azotemia versus hypervolemia from oliguria. Laboratory evaluations should include serum and urine electrolytes, urinalysis, and examination of urinary sediment. Urine sodium focus and fractional excretion of sodium may help determine prerenal azotemia.
Huang Lian (Goldthread). Dramamine.
- Are there any interactions with medications?
- Digestive problems and other uses.
- What is Goldthread?
- Are there safety concerns?
- How does Goldthread work?
- Dosing considerations for Goldthread.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96480
Induction of Anesthesia and Tracheal Intubation � Anticipate exaggerated systemic arterial blood strain adjustments symptoms quivering lips order 50 mg dramamine visa. Maintenance of Anesthesia � Use a volatile anesthetic and vasoconstrictors to management systemic arterial blood stress treatment nerve damage dramamine 50 mg buy discount on line. Changes in surgical stimulation might lead to medications excessive sweating dramamine 50 mg without a prescription adjustments in arterial blood pressure and coronary heart rate symptoms xanax abuse purchase 50 mg dramamine with mastercard. Additional doses of narcotics, -adrenergic blockers, and modifications in the dose of unstable anesthetics can be utilized to management hemodynamics. Heart rate control is probably the most critical component for preventing cardiac morbidity and fatality. Volatile anesthetics are helpful for attenuating exercise of the sympathetic nervous system, which is responsible for these pressor responses. The ability to quickly increase the alveolar concentration of sevoflurane (because of its low solubility) makes this volatile anesthetic uniquely efficacious for treating sudden will increase in systemic arterial blood pressure (see "Maintenance of Anesthesia" underneath "Coronary Artery Disease"). Rapid modifications in desflurane focus might result in tachycardia, hypertension, pulmonary hypertension, and myocardial ischemia and must be prevented. Total intravenous anesthesia (combinations of dexmedetomidine, propofol, narcotics, and benzodiazepines) can also be used with effect. Continuous intravenous infusions of phenylephrine, nitroprusside, nitroglycerin, or esmolol can be used to maintain normotension during the intraoperative interval. Combinations of narcotic, benzodiazepine, and inhaled anesthetics are generally used. Hypotension that occurs throughout maintenance of anesthesia is usually treated by reducing the concentrations of unstable anesthetics while infusing fluids intravenously to increase intravascular fluid volume. Sympathomimetics, corresponding to ephedrine, or vasoconstrictors corresponding to phenylephrine could additionally be essential to restore perfusion pressures till the underlying explanation for hypotension may be corrected. The alternative of intraoperative displays for patients with coexisting essential hypertension is influenced by the complexity of the surgical procedure. Whatever the selection of anesthetic, -adrenegic blockers and sedatives can be utilized to scale back sympathetic nervous system stimulation. The evening earlier than surgical procedure is annoying, and prophylactic -adrenergic blockade can reduce the chance of sympathetic stimulation resulting in tachycardia and subsequent myocardial ischemia. Patients scheduled for ophthalmic surgery, a minor outpatient process, generally have sympathetic stimulation ensuing Chapter 25 Cardiovascular Disease in preoperative hypertension. Prophylactic therapy with -adrenergic blockers can reduce the preoperative hypertensive episodes and myocardial ischemia. Appropriate dosing of all drugs is crucial and inappropriate dosing might lead to hypotension, bradycardia, and elevated morbidity and mortality rates. Withholding antihypertensive medications might lead to withdrawal phenomena and improve the morbidity and mortality charges. Optimal cardiac output can be obtained when the impedance of the vasculature (preload and afterload) matches the impedance of the heart and may be achieved by cautious preload and afterload administration. Small doses of unstable anesthetics can maintain anesthesia, however should be used fastidiously to avoid cardiac despair. Invasive monitoring of intra-arterial blood strain is useful for hemodynamic administration of patients present process each regional and general anesthetics. Use of pulmonary artery catheters could be useful in hemodynamic management, but no proof exists to counsel that they reduce operative danger or enhance outcome. Maintenance of arterial blood stress with vasoconstrictors (phenylephrine) ought to precede increasing myocardial contractility with steady intravenous infusions of inotropic drugs similar to epinephrine, dopamine, and dobutamine. If the surgical procedure precludes such a alternative, common anesthesia with careful hemodynamic control with intra-arterial stress monitoring, infusions of vasoconstrictors, and presumably inotropic medication, with the cautious avoidance of tachycardia, must be used. Postoperative Management Hypertension in the early postoperative interval is a frequent occurrence in patients with a preoperative diagnosis of essential hypertension. Prophylactic or therapeutic administration of -adrenergic blockers can cut back these episodes of hypertension and scale back danger of perioperative ischemia and demise. Tachycardia within the postoperative interval should be actively averted as it increases morbidity and mortality charges (also see Chapter 39). Clearly the arterial blood strain must be managed during the entire perioperative period. The affected person wants preoperative, intraoperative, and postoperative hemodynamic and autonomic control to prevent associated cardiac morbidity and demise. Anesthesia take care of sufferers with cardiac disease actually needs to be perioperative for optimum outcomes. If medication is needed to control arterial blood pressure and heart price while at residence, the patient will probably want it during surgical procedure and postoperative care. Withdrawal of antihypertensive and anti-ischemic medications within the perioperative period increases cardiac threat. Cardiology session is frequently helpful in sufferers with congestive failure as consideration of surgical or interventional revascularization and optimization of medical remedy can enhance cardiac perform. Preoperative initiation of -adrenergic blockers and vasodilator remedy with angiotensin-converting enzyme inhibitors can enhance ventricular perform and reduce operative threat. Volatile anesthetics are useful for stress-free vascular easy muscle and attenuating airway responsiveness to stimuli produced by a tracheal tube. Pulmonary vasodilation with prostaglandins (epoprostenol, treprostinil, iloprost, beraprost), endothelin receptor antagonists (bosentan, sitaxentan, ambrisentan), inhaled nitric oxide, inhaled milrinone, type 5 phosphodiesterase inhibitors (sildenafil, vardenafil), or soluble guanylate cyclase activators (cinaciguat, riociguat) have been tried with variable success. Patients with pulmonary hypertension have important increased risk and must be handled with extreme care. Monitoring of pulmonary arterial or right atrial stress (or both) may be useful to detect any opposed effect on pulmonary vasculature. In extreme cor pulmonale, inotropic support with -agonists can enhance cardiac operate. In extreme right ventricular failure, mixtures of -agonists and phosphodiesterase inhibitors (amrinone or milrinone) can provide synergistic enhancements in ventricular perform and vasodilation (amrinone or milrinone), thus improving cardiac output. Despite these opposed modifications, the stroke volume stays normal or increased owing to the hypercontractile state of the myocardium. This disease is usually hereditary, and the genetic defect seems to be an elevated density of calcium channels manifesting as myocardial hypertrophy. Management of Anesthesia the goal throughout management of anesthesia for sufferers with hypertrophic cardiomyopathy is to lower the pressure gradient throughout the left ventricular outflow obstruction (Box 25. Decreases in myocardial contractility and increases in preload (ventricular volume) and afterload will lower the magnitude of left ventricular outflow obstruction. Volatile anesthetics are useful for upkeep of anesthesia, providing mild melancholy of myocardial contractility. Rapid increases in desflurane could trigger sympathetic stimulation with tachycardia, hypertension, bronchospasm, and pulmonary hypertension and ought to be averted. High potency opioids stimulate the vagus nerve, lower coronary heart fee, and can lower sympathetic stimulation bettering hemodynamics. Combinations of unstable medication (sevoflurane or isoflurane) with an opioid are commonly chosen. Intraoperative hypotension is generally handled with intravenous fluids or an -agonist corresponding to phenylephrine. When hypertension happens, an elevated delivered focus of isoflurane or sevoflurane can be used. A frequent signal of cardiac tamponade is hemodynamic collapse and cardiogenic shock unresponsive to fluids and inotropes. Once the pericardium is drained, venous return can enter the heart and hemodynamics will rapidly normalize. A dissecting aneurysm denotes a tear in the intima of the aorta that allows blood to enter and penetrate between the partitions of the vessel, producing a false lumen. Ultimately, the dissection could reenter the lumen through one other tear within the intima or rupture through the adventitia. Elective repair of an belly aneurysm is often really helpful when the estimated diameter of the aneurysm is more than 5 cm. The incidence of spontaneous rupture will increase dramatically when the dimensions of the aneurysm exceeds this diameter. Extension of the abdominal aneurysm to embrace the renal arteries occurs in about 5% of patients.
Specifications/Details
This restricted availability can increase levels of the unbound symptoms 9f diabetes dramamine 50 mg purchase line, pharmacologically lively fraction of medicine medicine for runny nose dramamine 50 mg buy generic line, corresponding to thiopental and alfentanil medicine you take at first sign of cold dramamine 50 mg on line. Increased drug sensitivity as a end result of decreased protein binding is more than likely to be manifested when plasma albumin concentrations are decrease than 2 symptoms 0f food poisoning cheap 50 mg dramamine with visa. Ascites Ascites is a common complication of cirrhosis affecting up to 50% of cirrhotic patients. The growth of ascites is related to vital morbidity and heralds the tip stages of cirrhosis. Complications associated with ascites include marked stomach distention (leading to atelectasis and restrictive pulmonary disease), Chapter 28 Renal, Liver, and Biliary Tract Disease spontaneous bacterial peritonitis, and circulatory instability due to compression of the inferior vena cava and proper atrium. Although the precise mechanism of ascites is unclear, excess sodium retention by the kidney, decreased oncotic pressure as a result of hypoalbuminemia, and portal hypertension appear to play a central role. Initial remedy consists of restriction of fluid administration, discount of sodium intake, and administration of diuretics. In extreme instances, belly paracentesis could be effective at transiently decreasing abdominal distention and restoring hemodynamic stability. Renal Dysfunction and Hepatorenal Syndrome Renal dysfunction can develop in a good portion of patients with cirrhosis. A variety of etiologic factors together with diuretic therapy, reduced intravascular quantity secondary to ascites or gastrointestinal hemorrhage, nephrotoxic medicine, and sepsis can provoke acute renal failure and finally acute tubular necrosis in cirrhotic sufferers. A mild kind occurs in as much as 20% of sufferers and is associated with minimal sequelae. Risk components for growth of this situation embrace prior publicity to halothane, age older than 40 years, obesity, and feminine gender. Isoflurane and desflurane are also capable of causing hepatic dysfunction, however the incidence of hepatitis after exposure to these unstable anesthetics is extraordinarily uncommon, mainly due to the decreased magnitude of metabolism in comparison to halothane. Given its rare incidence and the disappearance of halothane in fashionable clinical apply in North America, volatile anesthetic�induced hepatic dysfunction stays a prognosis of exclusion in the affected person presenting with hepatitis within the perioperative period. These changes mirror drug- or technique-induced effects on hepatic perfusion strain or splanchnic vascular resistance, or each. For instance, decreased hepatic blood move from risky anesthetics, as properly as regional anesthesia (T5 sensory level), is in all probability going as a outcome of decreased hepatic perfusion stress. Autoregulation (increased hepatic artery blood flow offsetting decreases in portal vein blood flow) of hepatic blood flow could also be greatest maintained with isoflurane. However, hepatic blood move through the administration of desflurane and sevoflurane is maintained by a similar mechanism. Volatile Anesthetic�Induced Hepatic Dysfunction Finding Serum bilirubin (mg/dL) Serum albumin (g/dL) Prothrombin time (seconds prolonged) Ascites Encephalopathy A <2. Postoperative liver dysfunction is extra doubtless within the presence of coexisting liver disease. Furthermore, the massive reserve of the liver implies that considerable hepatic damage could be present before liver function test outcomes turn into altered. It might take further stressors, corresponding to anesthesia and surgery, to reveal the underlying liver illness. Inadequate hepatocyte function throughout anesthesia and surgical procedure could be manifested as metabolic acidosis intraoperatively. Intraoperative Management Induction and Maintenance of Anesthesia Most sufferers have well-preserved cardiac function and no significant systemic or pulmonary hypertension. Induction of anesthesia can be achieved with an intravenous anesthetic corresponding to propofol, thiopental, or etomidate, together with opioids and short- or intermediate-acting neuromuscular blocking drugs. Intravenous anesthetics have minimal impact on hepatic blood move provided arterial blood pressure is satisfactorily maintained. Thus, arterial blood pressure ought to be preserved and sympathetic stimulation averted, which also has an adverse effect on hepatic blood flow. A rapid-sequence or modified rapid-sequence induction of anesthesia is warranted if patients have vital ascites or delayed gastric emptying. Hypotension after induction of anesthesia occurs generally as a outcome of the low systemic vascular resistance and relative hypovolemia. This can usually be handled with small doses of vasoconstrictors corresponding to phenylephrine. With the exception of halothane, all unstable anesthetics are suitable for sufferers with extreme liver illness. No optimum anesthetic technique has been established for the maintenance of anesthesia. Most main operations in sufferers with important liver illness involve the use of general anesthesia. Major operations during which blood loss is likely require steady technique of monitoring arterial blood pressure (arterial line) and filling strain (central venous line). Patients with important comorbid circumstances (including cardiac diseases) present process procedures involving large anticipated blood loss might require placement of a pulmonary artery catheter. Correction of extreme coagulopathy before vascular line placement ought to be considered. Ultrasound steering might reduce the danger of issues related to vascular access. Communication with the blood bank (also see Chapter 24) earlier than surgery is essential to ensure sufficient availability of purple blood cells, platelets, and clotting components, together with recent frozen plasma and cryoprecipitate. Additional information, unavailable through typical laboratory checks, such as clot strength, platelet perform, and hyperfibrinolysis, can be assessed quickly at the bedside with these newer strategies. Hemostatic algorithms that utilize point-of-care coagulation testing and issue concentratebased therapy are showing considerable promise within the administration of patients with coagulopathy related to liver illness. In some sufferers, grand mal seizures may be the first indication of alcohol withdrawal syndrome. When seizures occur, hypoglycemia and other potential causes, including brain harm, must also be dominated out. Treatment Postoperative Jaundice Halothane or different unstable anesthetics are sometimes implicated as the cause for postoperative jaundice, however there are numerous other and doubtless more likely causes (see Table 28. A surgical explanation for postoperative jaundice is probably going if the operation involved the liver or biliary tract. Similarly, multiple blood transfusions and resorption of surgical hematoma can lead to jaundice in the perioperative interval. Drugs, including antibiotics, and other metabolic or infectious causes such as sepsis, should also be thought-about in the differential diagnosis of postoperative jaundice. Treatment of delirium tremens must be aggressive and typically consists of benzodiazepine administration at regular intervals. If psychological standing declines considerably, airway protection may be achieved by endotracheal intubation. Correction of fluid, electrolyte (magnesium, potassium), and metabolic (thiamine) derangements is necessary. These sufferers often have regular liver perform check outcomes, aside from increased serum bilirubin or alkaline phosphatase concentrations as a result of choledocholithiasis (common bile duct stone) or chronic cholangitis. Gilbert syndrome, a benign disorder causing elevation in unconjugated bilirubin, is probably certainly one of the most typical causes of jaundice and should occasionally be mistaken for postoperative hepatobiliary dysfunction. Conversely, Dubin-Johnson and Rotor syndromes are congenital disorders leading to elevated conjugated bilirubin ranges that can be exacerbated by surgery. Intoxicated sufferers are more susceptible to regurgitation of gastric contents and aspiration pneumonia as a result of alcohol slows gastric emptying and reduces the tone of the decrease esophageal sphincter. Management of Anesthesia Anesthesia for cholecystectomy or exploration of the common bile duct, or both, is influenced by the effect of the medication used for anesthesia on intraluminal strain within the biliary tract. Specifically, opioids can produce spasm of the choledochoduodenal sphincter, which increases frequent bile duct strain. Such spasm may impair the passage of distinction medium into the duodenum and erroneously counsel the necessity for sphincteroplasty or the presence of frequent bile duct stones. However, opioids have been used in many situations without adverse effect, which emphasizes the reality that not all patients reply to opioids with choledochoduodenal sphincter spasm. Laparoscopic Cholecystectomy Alcohol Withdrawal Syndrome Initial symptoms of alcohol withdrawal, including agitation, tachycardia, and signs of elevated sympathetic stimulation, could also be subtle and mistaken for different common perioperative complications similar to pain and delirium.
Syndromes
- When did this problem develop?
- Certain foods
- DuoFilm patch
- Name of the product (ingredients and strengths, if known)
- Skin tumors
- Amount swallowed
- Nasal packing
- Malnutrition
Related Products
Additional information:
Prolonged prone positioning has resulted in pres certain ulcers on the face symptoms 6 days after conception purchase dramamine 50 mg, especially the chin and brow keratin intensive treatment dramamine 50 mg generic with amex, and different areas treatment hepatitis c 50 mg dramamine cheap visa. When possible medicine 93 2264 discount dramamine 50 mg otc, periodic repositioning of the pinnacle throughout prolonged procedures might minimize the risk of such accidents. Pressure and stretch on nerves are prevented by correct padding and avoiding any extension over ninety levels. The stomach needs to be hanging free to avoid increased venous pressure and thereby elevated venous bleeding. The susceptible position alters pulmonary dynam ics, so pulmonary perform should be reassessed in this place. Intraoperative Spinal Cord Monitoring Monitoring spinal cord perform is an important com ponent of major surgical procedures involving distrac tion and rotation of the spine similar to occur with major anteroposterior spinal fusions and scoliosis surgery (also see Chapter 20). Spinal twine monitoring is employed in order to detect and hopefully reverse, in a well timed method, any opposed results famous through the operative period. The anesthetic technique should be adjusted appropriately when spinal twine monitoring is employed. Some anesthetics intrude with acquisition of the wave types which are obtained intraoperatively and utilized to analyze spinal wire integrity. An increase in latency of more than 10% or a decrease in amplitude of 60% or extra, in addition to lack of ability to acquire a proper waveform or signal, could also be indicative of spinal twine dysfunction or disruption. Surgically unrelated causes may embody hypotension, hypothermia, high concentrations of unstable anesthetics, benzodiaz epines, hyper or hypocarbia, and anemia. Midazolam and other benzodiazepines are averted as a result of they may intrude with acquiring a waveform. Some anesthesia suppliers avoid nitrous oxide and use a mix of air in oxygen. Distraction, rotation, excessive bleed ing, and severing or clamping of arterial blood supply can result in ischemia to the twine and neurologic injury. Some areas of the spinal wire are extra vulnerable and due to this fact more prone to ischemia as their blood supply relies on watershed blood circulate. Surgical intervention on account of either direct contact or stretching might impair blood sup ply and thus render the twine ischemic. In addi tion, on account of distraction there could additionally be inadequate blood supply to the spine, and subsequently, the mean arterial blood strain should be increased in an effort to restore enough blood circulate. Note how the newly acquired waveforms (purple) are flattened when compared to baseline tracings (red) as amplitude of tracings are decreased and latency increased. Stimulation over the motor cortex of the mind generates a waveform, which is propagated down the motor pathways and detected distally in the arm or leg. Importantly, it must be understood that the electrical Chapter 32 Orthopedic Surgery current causing the stimulus over the motor cortex additionally stimulates muscular tissues instantly within the area of the electrodes placed in the scalp-the masseter muscle and muscles of mastication. Placing a chunk block made of tongue depressors and gauze behind the mouth alongside the teeth line bilaterally will assist forestall injury. In the susceptible (facedown) place, any motion might allow for the tongue to slip and fall between the enamel, render ing it weak to laceration. Each stimulus is associated with a masseter muscle contraction so the patient is in danger as long as waveforms are being generated. A rapidacting anesthetic corresponding to propofol should be ready to be administered as soon because the assessment is complete, so the affected person can rapidly be reanesthetized. If a low milliampere (mA) current can stimulate the nerve root, then the screw is merely too near the nerve root. Wake-Up Test the wakeup test was traditionally utilized to assess spi nal twine integrity in plenty of scoliosis circumstances. Development of refined spinal twine monitoring is now normal in many hospitals, and the wakeup take a look at is generally reserved for those situations by which monitoring is unobtain in a position or a big intraoperative change in spinal twine monitoring waveforms is famous. During the wakeup test the anesthetic is discontinued and the patient is asked to move the extremities. Potential issues of this approach embody elevated bleeding, venous air embo lism, and even inadvertent extubation of the trachea within the prone position with the wound exposed. The wakeup test is carried out as follows: Turn off all inhaled anesthet ics, reverse any neuromuscular blocking druginduced paralysis, and cease infusions corresponding to dexmedetomidine, propofol, or ketamine. Then, whereas someone is observing the toes, ask the patient At the conclusion of the operation, the affected person is placed within the supine place. Carefully reassess the patient for hemodynamic status, intravascular volume status, hematocrit, blood loss, diploma of fluid and blood substitute ment, temperature, and the potential for airway edema. Also, facial edema, respiratory effort, the amount of pain medicine, and the presence of splinting and pain ought to be evaluated previous to extubating the trachea. Postoperative pain management (also see Chapter 40) may show difficult after backbone surgery as some sufferers may be taking vital amounts of ache drugs, significantly opioids, prior to surgery. In fact, the ache administration pathway should think about utilizing pre operative oral ache medicines, intraoperative infusion of pain drugs, and use of postoperative medica tions to provide a multimodal pain routine with the aim of maximizing ache reduction whereas contemplating methods to lower narcotic related respiratory melancholy. Applying individual consideration to a standard pain pathway, pre operative ache drugs might embody acetaminophen, gabapentin, or different antiinflammatory ache medications. Some centers utilize ketamine as an analgesic adjunct, both intraoperatively or postoperatively. Other oral drugs are helpful in the perioperative period and may be considered for administration preop eratively and postoperatively. Patients who may be at elevated threat are those having lengthy procedures or substantial blood loss or each. In addition, when possible, the pinnacle should be maintained in a neutral ahead position. From American Society of Anesthesiologists Task Force on Perioperative Visual Loss. Practice advisory for perioperative visual loss associated with spine surgery: an up to date report by the American Society of Anesthesiologists Task Force on Perioperative Visual Loss. Perioperative elements such as anemia, hypotension, pro longed surgery, blood loss, elevated venous pressure from positioning within the prone place, edema, a compartment syndrome throughout the orbit, and resistance to blood move such as direct strain on the eye, as well as systemic dis eases such as diabetes, hypertension, and vascular disease have all been considered possible etiologic factors. The headdown place permits edema to develop within the orbit and this improve in venous stress may influence arterial blood circulate. Most sufferers in the registry had been wholesome and positioned within the inclined position for backbone surgery. Blood loss greater than 1 L and procedures of 6 hours or longer had been current in 96% of instances. Anesthesia on this posi tion is associated with uncommon but significant and devastat ing neurologic issues together with stroke, ischemic mind damage, and vegetative states. This is due to the arte rial blood strain gradient that develops between the center and mind in this position. Chapter 32 Orthopedic Surgery Measurements obtained at the degree of the heart should be recalculated. Therefore, vital hypotension must be avoided in these sufferers particularly these aged, hyper tensive sufferers whose autoregulatory curve is undoubt edly compromised (also see Chapter 35). Factors predispos ing to fracture include medical comorbid circumstances, osteoporosis, decrease limb dysfunction, visual impair ment, growing age, Parkinson illness, previous frac ture, stroke, feminine gender, dementia, institutionalized patients, extra alcohol or caffeine consumption, cold climate, and use of psychotropic medications. One example is the number of preexist ing comorbid circumstances from which the affected person suffers. For instance, the presence of 4 to six comorbid con ditions is associated with increased mortality price when in comparability with patients with fewer comorbid conditions. Also, sufferers admitted to the hospital instantly after fracture did better than these admitted greater than a day later. A fractured hip usually prevents the affected person from undergoing a normal exercise stress test. The execs and cons of each spinal and basic anesthesia have to be thought of when choosing the approach for a given patient (also see Chapter 14). Intertrochanteric fractures are related to bigger blood losses and lon ger operations, as a outcome of a plate and screw are inserted, than intracapsular fractures that could be repaired with cannulated screws or a hemiarthroplasty relying on the viability of the femoral head. Advantages of regional anesthesia, similar to provided by a spinal anesthetic, are that (1) it avoids endotracheal intubation and airway manipulation and the drugs that have to be administered to accomplish this, (2) it decreases the entire amount of systemic medication the affected person receives all through the process, and (3) it may play a job in reducing the chance of thromboem bolism. An further concern is the period of time the patient should lay on the fracture table, especially within the aged, as even small quantities of sedation may find yourself in important respiratory depression. Chayen and coworkers demonstrated the effectiveness of lumbar plexus blocks in fractured hip sufferers. Intraoperative issues for sufferers undergoing fractured hip repair embrace correct positioning and pad ding on the fracture table, maintaining sufficient intra vascular quantity standing as blood is misplaced, and adequately sustaining physique temperature. Observation for hemody namic alterations, and different unanticipated responses within the aged patient, is very important because the proce dure progresses.
Usage: p.o.
Epidural block failure rates for cesarean delivery following use of a labor epidural are identified to be greater within the pressing setting in comparability with medicine used to treat bv order 50 mg dramamine with visa elective instances and range between 1 treatment vs cure dramamine 50 mg generic on line. During typical common anesthesia for cesarean supply symptoms 9 days after embryo transfer cheap 50 mg dramamine free shipping, opioids and benzodiazepines are administered after the infant is delivered to avoid placental transfer of those drugs to the neonate treatment yellow tongue dramamine 50 mg buy discount online. If intubation makes an attempt fail, the cesarean supply may proceed if the anesthesia supplier communicates that he or she can reliably ventilate the mother with either face masks or laryngeal masks airway68. Halogenated anesthetics are often partially replaced with other anesthetics following delivery to lower uterine atony. This permits titration of the block level or extension of the block period if the procedure lasts for a longer period. A number of drugs are used by anesthesia providers to quickly induce common anesthesia. Propofol General Anesthesia General anesthesia is utilized in obstetric follow for cesarean delivery, typically when neuraxial anesthesia is contraindicated or for emergencies because of its fast and predictable action. Based on knowledge from 1997 by way of 2002, the relative danger of general anesthesia is 1. Approximately two thirds of the deaths associated with basic anesthesia were brought on by intubation failure or induction problems. A multi-institutional database of adverse obstetric anesthesia events indicates that current charges of failed intubation are approximately 1:533, although not considered one of the 10 failed obstetric intubations in the database resulted in maternal fatality. After administration of a nonparticulate antacid, preoxygenation, and affirmation of surgical readiness, a rapidsequence induction is often carried out and a cuffed endotracheal tube positioned. Surgical incision is made after confirmation of tracheal intubation and enough ventilation. Anesthesia is maintained by administration of a mix of a unstable anesthetic, in addition to benzodiazepines, 568 this extremely lipid-soluble drug ends in speedy onset of action that renders the affected person unconscious inside roughly 30 seconds. It is preservative free and have to be drawn up only hours earlier than use, decreases the incidence of nausea and vomiting, and is presently not a controlled substance. Propofol administration has no vital impact on neonatal habits scores with induction doses (2. Etomidate Like propofol, etomidate has a rapid onset of motion because its high lipid solubility and fast hydrolysis lead to a comparatively short length of action. Anxiolytics the active metabolites, use of diazepam has been associated with neonatal respiratory depression. Midazolam is a shorter performing anxiolytic but in addition quickly crosses the placenta, and huge induction doses have been related to profound neonatal hypotonia. Anxiolytic use has been controversial; however, in specific obstetric conditions, lower doses could additionally be helpful maintaining in thoughts their amnestic properties. Because neonates have a limited capacity to excrete Maintenance of anesthesia for cesarean delivery often contains the inhalation of a low concentration (<0. If excessive concentrations of unstable anesthetics are administered for extended periods, neonatal effects of those drugs, as evidenced by flaccidity, cardiorespiratory depression, and decreased tone, may be anticipated. It is necessary to acknowledge that if neonatal depression is due to transfer of anesthetic medicine, the infant is merely anesthetized and should respond easily to simple therapy measures corresponding to assisted ventilation of the lungs to facilitate elimination of the risky anesthetic. A dialogue of the operative and anesthetic plan by the neonatologist, obstetrician, and anesthesia provider is essential for optimizing the end result of neonates in these conditions. Neuromuscular Blocking Drugs (Also See Chapter 11) all agree that cricoid stress is efficacious or required in every affected person. Fetal concentrations rely upon the focus and period of anesthetic administered to the mother. During a typical common anesthetic for cesarean delivery, opioids are administered after the baby is delivered to avoid placental switch to the neonate. There could also be confusion concerning the presence of fetal misery, the use of basic anesthesia, and subsequent supply of a depressed neonate. A Cochrane review of sixteen studies evaluating neuraxial blockade versus common anesthesia in otherwise uncomplicated cesarean deliveries found that "No vital difference was seen in terms of neonatal Apgar scores of 6 or less and of four or much less at one and 5 minutes or the need for neonatal resuscitation. A prolonged period between induction to supply may result in a lightly anesthetized, however not an 570 Succinylcholine (1 to 1. If large doses are given (2 to 3 mg/kg) it ends in detectable ranges in umbilical cord blood. However, extreme doses (10 mg/kg) are needed for the switch to end in neonatal neuromuscular blockade. If the hydrolytic enzyme is current both in low focus or in a genetically decided atypical kind, extended maternal paralysis can occur and the return of neuromuscular energy ought to always be decided earlier than further muscle relaxants are given or extubation of the trachea. It supplies sufficient tracheal intubating situations in roughly 90 seconds at doses of zero. Unlike succinylcholine, it has a much longer length of motion, reducing maternal safety within the occasion the anesthesia supplier is unable to intubate the trachea or ventilate the affected person. Under normal circumstances, the poorly lipidsoluble, extremely ionized, nondepolarizing neuromuscular blockers. This placental impermeability is just relative and when giant doses are Chapter 33 Obstetrics given over lengthy durations, neonatal neuromuscular blockade can occur. A paralyzed neonate may have normal cardiovascular operate and good color but no spontaneous ventilatory movements, no reflex responses, and skeletal muscle flaccidity. Treatment consists of respiratory support until the neonate excretes the drug, which may take up to 48 hours. Antagonism of nondepolarizing neuromuscular blocking drugs with cholinesterase inhibitors may be attempted, but sufficient respiratory support is the mainstay of therapy. Multiple pregnancies account for a major threat to both the mom and the fetuses. These complications embrace the next price of preterm labor, preeclampsia, gestational diabetes, preterm premature rupture of membranes, intrauterine development restriction, and intrauterine fetal demise. Pregnancies with multiple gestations account for 9% to 12% of the perinatal deaths. If the second twin is breech, you will need to focus on the mode of supply with the obstetricians. In circumstances of vaginal supply, women are strongly suggested to undergo placement of an epidural to facilitate delivery and extraction of the second twin. In instances of breech extraction of the second twin, the epidural provides both analgesia and optimum perineal rest in the course of the supply of the fetal head of the second twin. Relaxation of the uterus improves delivery situations of the second twin and reduces the risk of head entrapment. At the late second stage of supply a extra concentrated local anesthetic will optimize the perineal anesthesia and relaxation during this important portion of the delivery. At this time, the potential for head entrapment or fetal bradycardia is highest and a denser block permits for attainable transition to cesarean supply. The process includes rotating the fetus via external palpation and strain of the fetal components. Only just lately (2006) have obstetric apply guidelines allowed particular person obstetricians the flexibility of performing these deliveries primarily based on their expertise and luxury level. Women ought to endure pelvimetry, an ultrasound to decide fetal weight, and counseling by the obstetrician to review the dangers of the process. The patient is strongly inspired to have an epidural placed during labor as the anesthetic management and risks are just like a breech extraction of the second twin. The prognosis is made after the supply of the fetal head when additional expulsion of the infant is prevented by impaction of the fetal shoulders with the maternal pelvis. Risk elements embrace macrosomia, diabetes, obesity, history of dystocia, labor induction, and instrumented supply. Among deliveries with shoulder dystocia, the chance of postpartum hemorrhage is elevated 11% and fourth-degree laceration elevated three. Cases of shoulder dystocia 7 minutes or longer have a significant improve in threat of neonatal brain damage. The ultimate maneuver in a failed shoulder dystocia supply requires pushing the fetus back up and proceeding to emergent cesarean delivery. Among the fetal injuries and sequelae of shoulder dystocia are brachial plexus harm, neurologic harm from asphyxia, and damaged clavicle. Often these neurologic accidents enhance over time with roughly lower than 10% leading to permanent Erb palsy. The definition of hypertensive disorders in being pregnant have been updated and altered in 2013. Gestational hypertension is new-onset elevated arterial blood pressures occurring after 20 weeks of gestation most frequently near term with the cause unclear, however with the need for increased surveillance during pregnancy.
Tags: buy 50 mg dramamine fast delivery, dramamine 50 mg buy fast delivery, order 50 mg dramamine, 50 mg dramamine purchase mastercard, dramamine 50 mg cheap free shipping, buy dramamine 50 mg line, cheap 50 mg dramamine mastercard, buy 50 mg dramamine fast delivery, discount dramamine 50 mg visa, dramamine 50 mg buy low price, buy 50 mg dramamine with mastercard, buy cheap dramamine 50 mg, dramamine 50 mg cheap on line, generic 50 mg dramamine overnight delivery, discount dramamine 50 mg on line, purchase dramamine 50 mg amex
8 of 10
Votes: 125 votes
Total customer reviews: 125
Customer Reviews
Osko, 35 years: Plasma oncotic stress is about 25 mm Hg on the afferent arteriole and with filtration increases to about 35 mm Hg on the efferent arteriole. The morbidity, mortality, and costs related to these infections are preventable to a considerable diploma.
Hassan, 60 years: Hypothermia can result in significant negative results corresponding to slowed metabolism of medicines, shivering with subsequent increased oxygen demand, and potential myocardial ischemia, as well as impaired coagulation. General elements of myofibrillar myopathy Besides the frequent distal scientific presentation, many myofibrillar myopathies are associated with cardiomyopathy and a few with respiratory failure [11�13].
