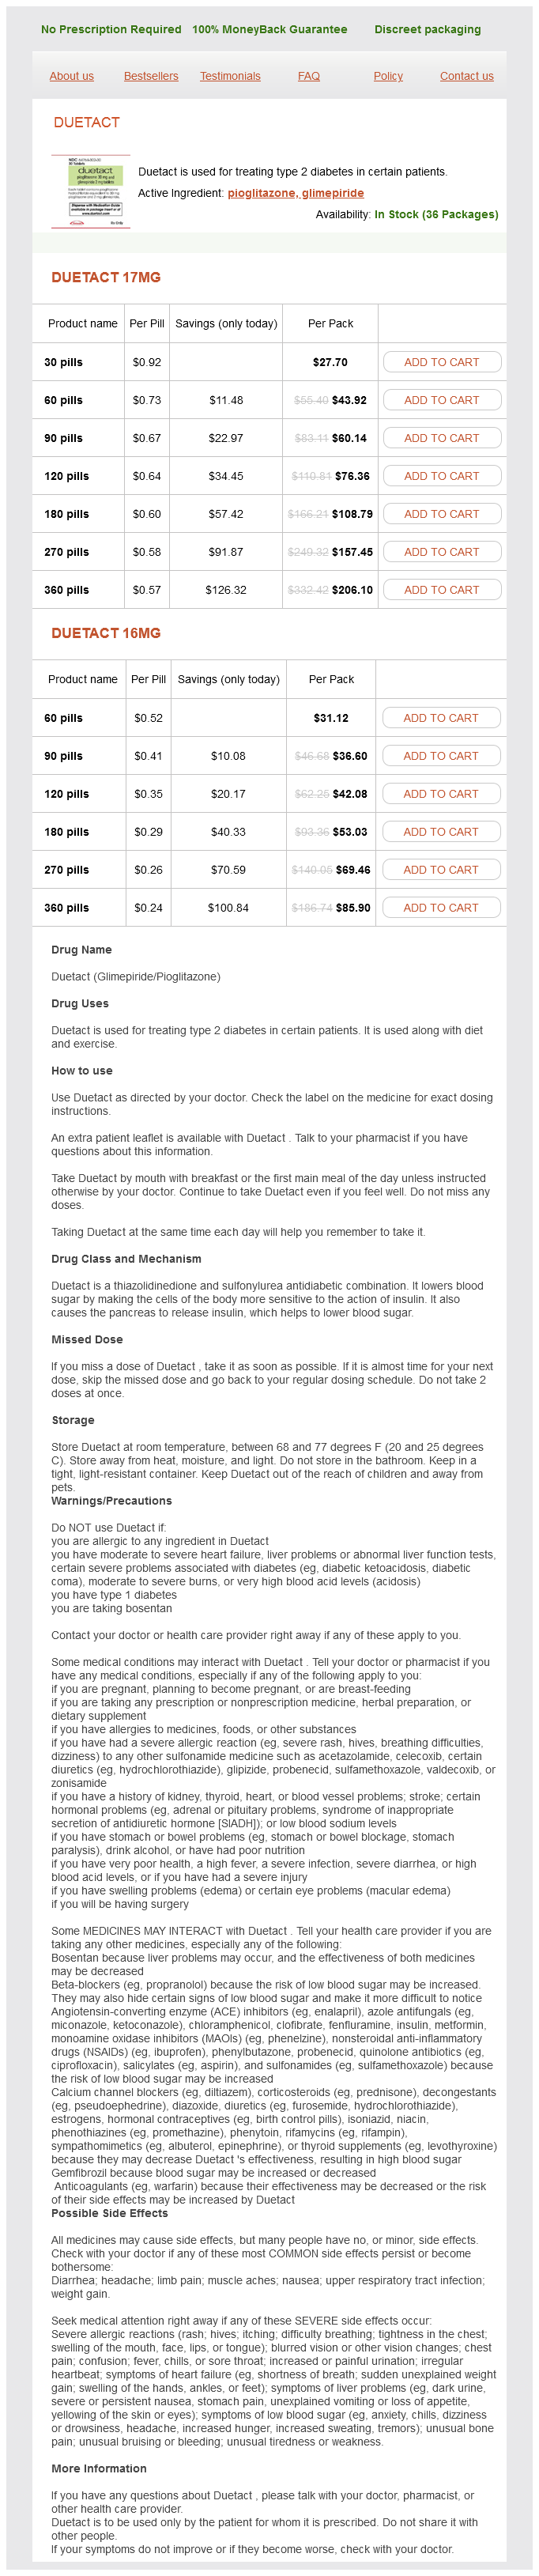
Duetact 17mg
- 30 pills - $27.70
- 60 pills - $43.92
- 90 pills - $60.14
- 120 pills - $76.36
- 180 pills - $108.79
- 270 pills - $157.45
- 360 pills - $206.10
Duetact 16mg
- 60 pills - $31.12
- 90 pills - $36.60
- 120 pills - $42.08
- 180 pills - $53.03
- 270 pills - $69.46
- 360 pills - $85.90
Duetact dosages: 17 mg, 16 mg
Duetact packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 659
Only $0,25 per item
Description
Kinetic characterization of the reconstituted carnitine provider from rat liver mitochondria diabetes symptoms journal order duetact 17 mg fast delivery. Carnitineacylcarnitine carrier deficiency: identification of the molecular defect in a patient diabetes test free cheap duetact 16 mg with visa. Identification of the molecular defect in a extreme case of carnitine acylcarnitine service deficiency metabolic disease 71 generic duetact 17 mg with mastercard. Identification of the molecular defect in patients with carnitine-acylcarnitine provider deficiency managing diabetes gestational duetact 17 mg buy otc. Inhibition by propionyl coenzyme A of N-acetylglutamate synthetase in rat liver mitochondria. A attainable explanation for hyperammonemia in propionic and methylmalonic academia. Mitochondrial acetylcarnitine offers acetyl groups for nuclear histone acetylation. Carnitineacylcarnitine translocase deficiency: case report and review of the literature. They documented poor carnitine acyl transferase exercise in a biopsied liver. In the reaction catalyzed, fatty acyl CoA esters are transformed to carnitine esters. A defect wherever within the pathway can be anticipated to result in insufficient formation of ketone bodies in response to fasting along with insufficient gluconeogenesis and hypoglycemia. Confirmation of the leukocyte analysis is achieved by assay of the enzyme in fibroblasts. Fatty acid synthesis in the central nervous system is implicated in the control of meals consumption and energy expenditure. Elevated concentrations of nonesterified fatty acids in plasma are thought to be essential mediators [11]. This has implications for remedy of problems of fatty acid oxidation as it promotes export of acylcarnitines from the mitochondria and finally urinary excretion. Rodents fed a high-fat diet accumulate acylcarnitine esters and have decreased expression of carnitine biosynthetic genes [13]. Supplementation with carnitine reversed these abnormalities and improved glucose tolerance. Episodes tend to be recurrent till diagnosis and the institution of avoidance of fasting. In the first household [2], a previous sister had had three hypoglycemic episodes and had died at 15 months after a 16-hour quick. She presented with typical Reye syndrome with hepatomegaly, hypoglycemia, and hyperammonemia and very excessive transaminases, in addition to liver failure. The household underwent preimplantation genetic diagnosis, and they have had regular youngsters. Genetics and pathogenesis 287 had been related to abnormal serum hepatocellular enzymes, prothrombin time, and partial thromboplastin time. She was thought to have disseminated intravascular coagulation and sepsis, consistent with an earlier Klebsiella sepsis at two days of age. At 14 months, she developed seizures and was found to have hypoglycemia with no ketonuria. This illness has been notable for its absence of cardiac symptomatology, together with arrhythmias [17]. The neonatal death [19] was attributed to cardiac disease, but the only manifestations of bradycardia and arrest could mirror major systemic sickness, and there were no abnormalities in cardiac or skeletal muscle at post-mortem. It could additionally be transient, or associated with myopathy and elevated creatine deficiency [23]. A patient displayed distal renal tubular acidosis, by which there was failure to acidify the urine throughout spontaneous acidosis [24]. In general, fasting over 15 hours is required to exhaust glycogen stores and call on fatty acid oxidation. Cognitive deficit, or its absence, typically depends on the severity of the initial hypoglycemic episode, but many patients described have been neurologically impaired [18]. In one affected person, there have been recurrent Reye-like episodes with out hypoglycemia, although there was improvement in lethargy on the administration of glucose [22]. Organic acid analysis of the urine is notable for the absence of dicarboxylic aciduria and hydroxydicarboxylic aciduria [2, 6, 18], in addition to the absence of elevation of 3-hydroxybutyric and acetoacetic acids within the urine at times of fasting and hypoglycemia. Fractionation of the esterified carnitine of the urine reveals only acetylcarnitine. Tandem mass spectrometry of the blood reveals an absence of longchain acyl carnitines (C16, C18, C18:1) [18, 27]. In three patients, the ratio ranged from a hundred seventy five to 2000, a spread of 2�32 was observed in management infants. Higher values had been present in older infants, but there was no overlap of sufferers and controls. The histologic examination of the liver has revealed microvesicular and macrovesicular steatosis [6, 26]. Muscle biopsy might show sarcolemmal and interfibrillar accumulation of glycogen, as nicely as the presence of lipid [6]. This hemophagocytic syndrome has additionally been noticed in propionic acidemia and lysinuric protein intolerance. In one prolonged inbred Hutterite kindred, a brother and sister and their second cousin had been affected [24]. The dysfunction is uncommon [18], but there have been nine patients in the Paris expertise of Saudubray et al. Similarly, the conversion of 3H-palmitate to 3H2O in fibroblast monolayers was markedly poor [33]. The hepatic isoform approximates 88 kDa in size, whereas that of muscle is roughly 82 kDa; each variants are present in heart. Regulation of mitochondrial fatty acid oxidation is especially related during the metabolic demands of muscle contraction. The first mutation described [15] was a missense (D454G) change, which when expressed, had 2 % of wild-type exercise. Other mutations identified [16] include Q100X, which would predict an early truncation of the protein, H414V, and Y498C, which have an result on highly conserved sequences within the catalytic core of the enzyme. The rarity of the disease and the overall severity of phenotype have made genotype� phenotype correlations tough, however the mutation resulting in P479L resulted in a late onset disease in which there was proximal myopathy. Four novel mutations have been found [40] in sufferers with severe illness: G405W, R316R, and F343V. Greenberg and colleagues [41] have addressed the high frequency of the P479L variant in Canada among the many Inuit and First Nation households [42]. Studies of fatty acid oxidation in fibroblasts revealed residual exercise of the enzyme which must be sufficient to allow flux by way of the mitochondrial oxidation system. It has been advised that the polymorphism might protect towards atherosclerosis. The very high free carnitine and virtually absent lengthy chain acylcarnitines (peaks 456�484) are illustrated. The peaks in the profile are the molecular ions (M+) of the free carnitine peak 218 and acylcarnitine butyl esters (peaks 260�484). A dysfunction of muscle lipid metabolism and myoglobinuria: absence of carnitine palmitoyl transferase. Hepatic and muscular presentations of carnitine palmitoyl transferase deficiency: two distinct entities. The brain-specific carnitine palmitoyltransferase-1c regulates power homeostasis. Enhanced susceptibility of Cpt1c knockout mice to glucose intolerance induced by a high-fat food plan involves elevated hepatic gluconeogenesis and decreased skeletal muscle glucose uptake. Carnitine insufficiency brought on by aging and overnutrition compromises mitochondrial performance and metabolic management.
Uva De Raposa (Herb Paris). Duetact.
- Headache; living longer; nerve pain; sore and painful muscles and joints; genital tumors; rapid fluttering or throbbing of the heart; muscle spasms; use as a medicine to cause vomiting, or cleansing and emptying the intestinal tract.
- Dosing considerations for Herb Paris.
- Are there safety concerns?
- How does Herb Paris work?
- What is Herb Paris?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96200
The initial plasma concentrations of bicarbonate were under 16 mEq/L in 5 sufferers [4] free diabetes test las vegas generic duetact 16 mg with amex. Persistent infantile hypoglycemia in the presence of metabolic acidosis is an indication for natural acid evaluation diabetes symptoms drunkenness 17 mg duetact purchase with mastercard. In three sufferers what causes diabetes type 2 yahoo purchase 17 mg duetact amex, concentrations ranged from 388 �M/L to 1370 �mol/L [4] and in one patient the plasma focus of ammonia was larger than 2000 �mol/L [3] blood sugar imbalance cheap duetact 17 mg overnight delivery. In fact, the provisional analysis was Reye syndrome in the first four sufferers reported. Despite noncompliance with dietary treatment and multiple acidotic attacks she was growing normally. By follow-up at seven years of age, she was doing higher than average in school though attacks had been persevering with. She had extreme lactic acidotic episodes in the neonatal period and at 5 and 14 months, in the latter of which she developed shock and convulsions together with an unmeasurable blood glucose. On follow-up at 7 years-of-age, she had no attacks for three years and was growing normally. His first acidotic episode was at 6 months-of-age following herpangina and refusal to eat. At 6 years-of-age, he had not had an attack in three years and was doing very well in school. There was in depth enhance in sign in the subcortical white matter consistent with dysmyelination. None of these patients had ketonuria at times of acute illness, and in some low levels of acetoacetate and 3-hydroxybutyrate have been documented within the blood [7, 17, 18]. Levels of acetoacetate and 3-hydroxybutyrate within the urine are disproportionately low [22]. This serves to distinguish these sufferers from those with other natural acidurias, such as propionic acidemia (Chapter 2) or methylmalonic acidemia (Chapter 3). Ketone our bodies decrease proteolysis in muscle and preserve muscle protein throughout starvation [23]; so, impairment of ketogenesis could be related to the hyperammonemia. The illness is uncommon except in Saudi Arabia [3], the place it was documented in sixteen p.c of natural acidemias. Defective activity of the enzyme has been demonstrated in cultured fibroblasts [25, 26], leukocytes [27], and liver [11] of affected patients. Activity in 10 patients was reported to be undetectable; in 16 others, it ranged from 0. In addition, the defect can be recognized by measuring the incorporation of 14C-isovaleric acid into trichloroacetic acid perceptible macromolecules [29] or by monitoring metabolism of 14C-leucine [30]. Mutation at Arg41 was present in a affected person with extreme deficiency of the enzyme [31] which is according to a job for interplay of Arg41 with the acylCoA carbonyl, selling product enolization. Substrate binding involves asparagine 311 and lysine 313 and the institution of polar contacts with phosphate and ribose teams of adenosine [32]. A G-loop construction would facilitate a disulfide bond between cysteine 266 and cysteine 323 [31]. These findings are consistent with the incidence of pancreatitis in this disease. The striatum has been seen as particularly susceptible to oxidative harm by 3-hydroxy-3-methylglutarate which is a robust pro-oxidant [35]. Prenatal diagnosis has been achieved by the evaluation of metabolites in maternal urine at 23 weeks of gestation [36]. A variety of mutations have provided interesting info on the nature of the enzyme. Five mutations in the extremely conserved R41 and D42 codons had been found in 23 percent of the mutant alleles in 41 probands. In three Czech patients, two recognized missense mutations had been discovered along with a novel one base deletion 27 delG in exon 1 [40]. Among main alterations within the gene were two massive deletions [41] and three frameshift/premature terminations [38, 39]. Particular frequency was noted in Saudi Arabia and the Iberian Peninsula the place two mutations (122G>A and 109G>A) have been recognized in 87 p.c and ninety four %. In Brazil, two mutations have been predominant in ethnic Portuguese/Spanish (E37X and V168fs (-2)) [45]. In acute crisis, ranges could reach 10,000 to 20,000 mmol/mol creatinine and between crises may be 200�4000. Normal individuals excrete in urine less than a hundred mmol/mol creatinine [49]; ranges are somewhat greater in young infants. The addition of H2O across the double bond in this compound yields 3-hydroxy3-methylglutarylCoA, which is ultimately cleaved to kind acetoacetic acid and acetylCoA. The response could be catalyzed by the enzyme that catalyzes the reverse dehydrogenation of 3-methylcrotonylCoA to isovalerylCoA. In the acute episode a big elevation of 3-hydroxyisovaleric acid may be found, along with 3-methylcrotonylglycine [19, 51�53]. Glutaric acid and adipic can also be elevated within the urine within the acute disaster [54]. Lactic acid levels could additionally be elevated at these occasions [55], together with hyperammonemia. This permits the incorporation of this disease into packages of neonatal screening. References 347 the excretion of acylcarnitine esters is elevated on this condition, and there could also be a secondary deficiency of free carnitine [60]. The latter is an emergency, and care should be devoted first to measures of basic support such as assisted ventilation and restore of deficits of fluid and electrolytes and elevation of the blood concentration of glucose. In an toddler with or with out hyperammonemia, trade transfusion, or peritoneal dialysis may be needed. Sodium benzoate or phenylacetate and L-arginine are helpful in administration of the hyperammonemia [61]. Hypoglycemia and acidosis usually respond readily to the parenteral administration of 20 percent glucose with intravenous insulin to maintain blood sugar between 6 and 8 mmol/L, fluid and electrolytes. Parents must be instructed to convey the patient in early, each time the oral route is compromised by vomiting or anorexia. Long-term management rests largely on the avoidance of hypoglycemia, and the avoidance of lengthy fasting, particularly during intercurrent sickness. A excessive carbohydrate diet with added cornstarch is advisable; and supplementation with glucose polymers is handy, particularly throughout intercurrent sickness. Restriction of the consumption of protein has been employed, and it appears prudent to limit the amounts of leucine ingested. Restriction of the consumption of fats may reduce the levels of metabolites within the urine [12]. Neurometabolic diseases at a nationwide referral middle: Five years experience on the King Faisal Specialist Hospital and Research Centre. Lethal hypoglycemia in a child with a deficiency of 3-hydroxy-3-methlyglutarylcoenzyme A lyase. Gas chromatographic/ mass spectrometric detection of 3-hydroxy-3-methylglutarylCoA lyase deficiency in double first cousins. Dizygotic twins with 3-hydroxy-3-methylglutaric aciduria: uncommon presentation household research and dietary management. Atypical presentation and neuropathological studies in 3-hydroxy-3methylglutaryl-CoA lyase deficiency. Biochemical and molecular analyses in three patients with 3-hydroxy-3methylglutaric aciduria. Molecular evaluation of Taiwanese patients with 3-hydroxy-3-methylglutaryl CoA lyase deficiency. Urinary and plasma natural acids in dizygotic twin siblings with 3-hydroxy-3methylglutaric aciduria studied by gasoline chromatography and mass spectrometry utilizing fused silica capillary columns. The urinary organic acid profile related to 3-hydroxy-3-methylglutaric aciduria. Genetic complementation analysis of 3-hydroxy-3-methylglutarylcoenzyme A lyase deficiency in cultured fibroblasts.
Specifications/Details
They are characteristically coarser and sparser than those seen in Hurler illness diabetic ulcer antibiotics duetact 17 mg discount on line. Chondrocytes in cartilage biopsied from the iliac crest and the ribs have been reported to be vacuolated [32] diabetes symptoms teenagers 17 mg duetact with amex. The diagnosis of a mucopolysaccharidosis is first made by the findings of increased portions of mucopolysaccharide in the urine diabetes type 2 symbol generic duetact 16 mg. Patients with this disorder accumulate gangliosides in the mind [34 diabetes medications newest 17 mg duetact buy amex, 35] including Gm2 and Gm3 [34], or there might increased amounts of Gm1 [35]. The electron microscopic look of the neurons could also be like these of Tay-Sachs illness [34] (Chapter 88). There can also be zebra bodies, and mucopolysaccharide might accumulate in the mind, as properly as in the peripheral tissues. Multiple affected siblings have been noticed in several households, and consanguinity has been documented [18]. The frequency of the illness has been estimated at one in 24,000 within the Netherlands [18, 36]. The amino nitrogen of the glucosamine moiety may be both sulfated or acetylated, and the 6-hydroxyl may be sulfated. The stepwise degradation of heparan sulfate supplies the websites for the defects in the numerous types of Sanfilippo disease. Heparan-N-sulfatase, the location of the defect in Sanfilippo illness type A [6, 41], catalyzes the breakdown of the molecule by splitting off the sulfate groups linked to the amino group of glucosamine. The enzyme has been isolated and purified [42] and is formally a sulfamate sulfohydrolase. This enzyme has been purified from human liver and urine, and the biosynthesis of the mature lysosomal enzyme has been elucidated [43�45]. In the sequential catabolism of heparan sulfate, elimination of the sulfate in the response catalyzed by heparan-N-sulfatase exposes a terminal glucosamine moiety. This is a two-step reaction by which the enzyme is first acetylated on the cytoplasmic side of the membrane and then transfers this acetyl group now inside the lysosome to a glucosamine. Some sufferers with sort C disease are faulty within the second step and others in both steps [48�50]. The defective enzyme in sort D Sanfilippo illness is in -N-acetylglucosamine-6-sulfatase [50, 51]. Glucosamine residues in heparan sulfate may be both N-sulfated or O-sulfated, and there are particular sulfatases for each residue. Defective activity of both leads to accumulation and to the Sanfilippo syndrome. Immunoprecipitation studies have demonstrated cross-reactive material within the Sanfilippo B-syndrome [53]. Detection of heterozygotes has been achieved via enzyme assay [57] and by 35S accumulation, which may be more reliable in distinguishing heterozygotes. Positive identification by enzyme assay is correct, however there could also be overlap, making identification of the traditional noncarrier individual unreliable. When the mutation is thought, molecular methods could additionally be used for the detection of carriers. Intrauterine analysis of the affected fetus has been accomplished in varieties A and B illness by way of assay of the related enzyme in amniotic cells in tradition [58]. It may be useful to verify the assay by evaluation of 35S accumulation, because some heterozygotes have very low levels of enzyme in the traditional assays. Chorionic villus materials has abundant enzyme exercise and is on the market for the prenatal analysis of every of the types of Sanfilippo illness [58�61]. Some different deletions have been reported, however most mutations have been missense [15, 16, 63�66]. Among Australian, Dutch, and German sufferers, the most typical mutation was R245H [17, 64]. Other widespread mutations are Q380R, S66W, and 1080delC, all with the severe phenotype. Among Polish patients, it was R74C [65], S66W in Sardinians [65], and 1091delC in Spaniards [66]. The gene for N-acetylglucosamine 6-sulfatase, on chromosome 12q14, the location of the defect in Sanfilippo kind D, has been cloned and encodes a protein of 52 amino acids. The first mutation to be found in a consanguineous Pakistani household was a homozygous single base pair deletion c. Enzyme alternative remedy has been attempted utilizing References 587 partially purified enzyme, leukocytes, and cultured fibroblasts [73], after which there could have been some changes in urinary mucopolysaccharides, but scientific benefit has not been evident except in soft tissues [74]. Outcome measures have been studied in a seek for useful screens for evaluating medical trials [76]. The Mullen and Leiter scales of cognitive development and the parental report of adaptive behavior were judged greatest. Mental retardation related to acid mucopolysacchariduria (heparitin sulfate type). Biochemical heterogeneity of the Sanfilippo syndrome: preliminary characterization of two deficient elements. Sanfilippo syndrome: profound deficiency of alphaacetylglucosaminidase activity in organs and skin fibroblasts from kind B sufferers. Sanfilippo syndrome type C: deficiency of acetyl-CoA: -glucosaminide N-acetyltransferase in skin fibroblasts. Sanfilippo illness type D: deficiency of N-acetylglucosamine 6-sulfate sulfatase required for heparan sulfate degradation. Cloning of the sulphamidase gene and identification of mutations in Sanfilippo A syndrome. Genetic heterogeneity and scientific variability within the Sanfilippo syndrome (types A, B and C). A recessively inherited lethal disease in a Caribbean isolate � a sulfamidase deficiency. Intrafamilial variability in Hurler syndrome and Sanfilippo syndrome kind A: implications for analysis of new therapies. The Sanfilippo syndrome: a scientific and genetical examine of 75 patients within the Netherlands (doctoral thesis). Sanfilippo A syndrome: sulfamidase deficiency in cultured skin fibroblasts and liver. Purification and partial characterization of a-N-acetylglucosaminidase from human liver. Biosynthesis and maturation of a-N-acetylglucosaminidase in regular and Sanfilippo B fibroblasts. New biochemical subtype of the Sanfilippo syndrome: characterization of the storage material in cultured fibroblasts of Sanfilippo C patients. Sanfilippo disease kind D; deficiency of N-acetylglucosamine-6-sulfatase required for heparan sulfate degradation. Sanfilippo illness sort B: presence of material cross reacting with antibodies against a-N-acetylglucosaminidase. Intralysosomal formation and metabolic fate of N-acetylglucosamine 6-sulfate from keratan sulfate. Clinical variability in Sanfilippo B disease: a report of six patients in two related sibships. First trimester prenatal analysis of metabolic diseases: a survey of countries from the European Community. Sanfilippo syndrome sort D: a spectrophotometric assay with prenatal diagnostic potential. Identification of molecular defects in Italian Sanfilippo A sufferers together with 13 novel mutations. Mutation 1091delC is extremely prevalent in Spanish Sanfilippo syndrome type A sufferers. Sanfilippo syndrome kind D: identification of the first mutation in the N-acetylglucosamine-6sulphatase gene. Neuropsychological outcomes of a number of storage diseases with and without bone marrow transplantation. The excretion of keratan sulfate within the urine is the defining biochemical feature of sufferers with this disease, and keratan sulfate has been documented to accumulate in tissues [3�5].
Syndromes
- Infection (a slight risk any time the skin is broken)
- Tiny organisms that can cause disease (microorganisms)
- Abdominal x-ray
- Collapse
- Recent exercise
- Pierre-Robin syndrome
- Poor blood supply to the legs
- Fainting or feeling lightheaded
- Spinal tap, and examination of spinal fluid
Related Products
Additional information:
Organic acid evaluation revealed the buildup of all kinds of natural acids diabetes symptoms mouth buy duetact 16 mg otc, including lactic diabetic diet for 8 year old 17 mg duetact discount mastercard, isovaleric diabetes mellitus quais os sintomas duetact 16 mg generic line, and ethylmalonic acids diabetes diet menu pdf 16 mg duetact effective, in addition to glutaric acid. There is generalized defect within the activity of at least 9 acyl CoA dehydrogenases [3]. The elementary molecular defect is within the mitochondrial transport of electrons from the acylCoAs to ubiquinone (CoQ10) of the main electron transport chain [5�7]. There appears to be a much greater incidence in the Turkish population, > 1:20,000 [33]. The first affected person was described as having a "very unpleasant sweaty-feet odor" [1]. This is the consequence of an excess of a number of short-chain, unstable natural acids. A number of these patients have been described as pale [1, 34, 35] and one had macrocytic anemia and a hemoglobin focus of 9. Many have had convulsions consistent with the diploma of melancholy of the blood glucose. They embody a excessive forehead, depressed nasal bridge, and a short anteverted nose. Muscular defects of the abdominal wall have occurred, as well as genital defects, similar to hypospadias and chordee. He had a excessive forehead, depressed nasal bridge, quick nostril with anteverted nares, an extended philtrum and micrognathia. He had a low, incompletely rotated, low-s ears with a decreased anthelix, semilunar folds under the eyes and three umbilical vessels. One of our sufferers also had an interventricular septal defect and three umbilical vessels. Polycystic kidneys could also be current in infants without dysmorphic features and could also be discovered first at autopsy [38, 42]. Ultrastructural changes have been described within the glomerular basement membrane [43]. Other pathologic abnormalities include cerebral gliosis and heterotopias giving a warty dysplastic look to the cortex [37]. Electron dense membrane limited bodies have been reported in the brain and kidneys [41]. Hepatic periportal necrosis has been reported [43], and more generally hepatic microvesicular lipid. Recurrent pancreatitis may occur later in milder circumstances, and this possibility should be investigated when belly signs of unknown origin happen [44]. Infants without dysmorphic options and irregular organogenesis have additionally presented early in life with tachypnea, acidosis, hypoglycemia, and an irregular odor. Some of these have survived the preliminary episode and died a few months later, often with cardiomyopathy. A small number have survived a bit longer and had episodic illness paying homage to Reye syndrome [45�47]. Sudden life-threatening illness in infancy was reported [48] in three infants with this illness, two of whom died. One had documented arrhythmia and the authors attributed the episode to myocardial dysfunction within the others. The later onset a quantity of acyl CoA dehydrogenase deficiency, or ethylmalonic-adipic aciduria has introduced with a considerable variety. The first patient reported [49] had episodic vomiting, hypoglycemia, and acidosis from seven weeks of age. Another [50] presented first as a 19-yearold in hypoglycemic coma and continued to have episodes of nausea, vomiting, hypoketotic hypoglycemia, and hepatic dysfunction with elevated bilirubin and transaminases, however normal ammonia. Others have had such episodes starting in the first yr of life [51�53], however one girl presented at 25 years with a history of episodic muscle weakness and vomiting [54]. During acute episodes, these patients have had hypoketotic hypoglycemia, acidosis and sometimes, especially early in life, hyperammonemia. Transaminase levels in blood may be elevated, and there could also be prolongation of prothrombin or partial thromboplastin times. At one excessive, a ten-year-old girl developed progressive weak point of proximal muscle tissue and died of cardiopulmonary failure, acidosis, hypoglycemia, and hyperammonemia; then again, a 27-year-old woman with train intolerance since childhood had episodes of pancreatitis, elevated creatine kinase, and lipid droplets in biopsied muscle. Uziel and colleagues described a boy with steadily progressive spastic ataxia and leukodystrophy without ever having experienced episodic metabolic crises [59]. One grownup patient presented for a quantity of years with cyclic vomiting and was initially recognized with cyclic vomiting syndrome [60]. Brain magnetic resonance imaging of this affected person confirmed disseminated high-intensity areas within the periventricular white matter and in the splenium of the corpus callosum on T2-weighted images and fluid-attenuated inversionrecovery photographs earlier than beginning the remedy. Roentgenograms of the chest could reveal cardiomegaly, and echocardiography may be according to cardiomyopathy. A macrocephalic patient was found to have symmetric hypoplasia of the temporal lobes of the mind within the first week of life [63]. He had normal psychomotor development for 11 months when he died of a sudden cardiac arrest. Autopsy confirmed hypomyelination and systemic hypoplasia of temporal lobes with lack of axons and focal subcortical ganglionic heterotopia, according to aberrant intrauterine developmental origin. This is especially true within the extreme neonatal onset type during which the portions found are monumental. The most outstanding of those are lactic acid and glutaric acid, but a massive quantity of other dicarboxylic acids and hydroxy acids are discovered. Among the previous are ethylmalonic, adipic, suberic, and sebacic acids, as well as unsaturated suberic acids. Among the latter are 2-hydroxybutyric, 2-hydroxyglutaric, and 5-hydroxyhexanoic acids. Volatile acids are demonstrable in the plasma by evaluation with gas liquid chromatography. The concentrations of isovaleric, acetic, isobutyric, 2-methylbutyric, butyric, and propionic acids could all be elevated to values 60�4800 occasions regular. In others, irregular quantities of natural acids are discovered only throughout acute episodes of sickness. This contrasts with glutaryl-CoA dehydrogenase deficiency (Chapter 9) during which 3-hydroxyglutaric acid is the hydroxy acid discovered. In the neonatal onset illness, the concentrations of the amino acids, citrulline, lysine, ornithine, and proline are elevated in plasma and urine. Hydroxyproline excretion may be high, consistent with a generalized amino aciduria. In the later onset disease, there could also be elevated concentrations of sarcosine in blood and urine [37, forty, 45]. The pattern of elevation of many acylcarnitine esters follows a curve with the utmost at C10. Prenatal diagnosis has been completed by the demonstration of enormous amounts of glutaric acid in amniotic fluid [64]. It has additionally been done by documenting impaired oxidation of [46, forty seven, 65] substrate and by immunochemical assay [66] in cultured amniocytes. In some, this has correlated with medical severity [6], however in others it has not. In one, the - and -subunits have been each poor, and the -subunit was of smaller measurement. In the opposite affected person, the -subunit was also small, while the -subunit was of normal dimension. The biosynthesis of the -subunit precursor in the first cell line was just about absent; in the second an -subunit was made that was about 1 kDa smaller than usual. Complementation research clearly distinguished cells of this disease from these of isovaleric acidemia [73] and supplied proof of two groups of sufferers with severe a quantity of acylCoA dehydrogenase deficiency. The most common was a substitution of methionine for threonine at codon 266, which was present in four unrelated patients. A valine 157 to glycine change has also been reported in two sufferers [30, 31], and a glycine 116 to arginine [30].
Usage: q._h.
Biochemical and histologic pathology in an infant with cross-reacting materials (negative) pyruvate carboxylase deficiency diabetes insipidus thiazide diuretic discount 17 mg duetact otc. Amino acid profile in pyruvate carboxylase deficiency: comparison with some other metabolic problems diabetes mellitus type 2 and exercise duetact 17 mg order. Pyruvant carboxylase deficiency: Metabolic traits and new neurological elements blood sugar effect on blood pressure order duetact 17 mg on-line. The molecular basis for the two totally different medical displays of classical pyruvate carboxylase deficiency diabetes insipidus with head injury duetact 17 mg discount visa. A case of pyruvate carboxylase deficiency with atypical clinic and neuroradiological displays. Amerindian pyruvate carboxylase deficiency is associated with two distinct missense mutations. Intron retention and frameshift mutations end in severe pyruvate carboxylase deficiency in two male siblings. Biotin-dependent carboxylase deficiencies (propionyl-CoA and pyruvate carboxylase). A mutation of pyruvate carboxylase in fibroblasts from a patient with severe continual lactic acidemia. Thiamineresponsive lactic acidosis in a affected person with deficient low Km pyruvate carboxylase activity in liver. A case of pyruvate carboxylase deficiency with later prenatal analysis of an unaffected sibling. Transport of reduced nicotinamide adenine dinucleotide into mitochondria of white adipose tissue. Treatment of pyruvate carboxylase deficiency with high doses of citrate and aspartate. Pyruvate carboxylase deficiency: scientific and biochemical response to anaplerotic diet remedy. Unsuccessful treatment of extreme pyruvate carboxylase deficiency with triheptanoin. In subsequent stories in 1971 by Baerlocher and colleagues [2] and by Hulsmann and Fernandez [3], there were multiple affected siblings of consanguineous matings. The enzyme catalyzes the irreversible conversion of fructose1,6-diphosphate to fructose-6-phosphate. The enzyme is most energetic in liver and kidney; and the liver enzyme is very regulated [4]. The frequent mutation in Japanese folks is an insertion, 960�961insG [6], which was also probably the most frequent mutation in a non-Japanese population [7, 8]. This mutation causes a frameshift and premature chain termination, as does 966del, and expression research have shown each to be pathogenic. The illness is clearly genetically heterogeneous and a wide selection of different mutations has been discovered. The conversion of fructose-6-phosphate to fructose1,6-diphosphate in glycolysis is catalyzed by one other enzyme, 6-phosphofructose-1-kinase. A history of a previous sibling who died in acidosis has usually been the alerting episode that led to early prognosis and survival within the subsequent affected toddler [1, 2]. There may be irritability, however development is normally rapid to somnolence, coma, apnea, and cardiac arrest [2]. Laboratory analysis reveals hypoglycemia, extreme acidosis, and lactic acidemia [10]. The episode often responds properly to vigorous remedy with parenteral fluids containing glucose and sodium bicarbonate. Subsequent episodes often comply with fasting, normally precipitated by intercurrent infections. Onset could also be with vomiting and anorexia; attendant fasting results in hypoglycemia and metabolic acidosis. In one affected person, episodes of hyperventilation started when the toddler was weaned and child foods have been begun at six months [10]; on admission, she was hypoglycemic and the lactic acid concentration was 20 mmol/L. Patients have been described as ketotic and the urinary test for ketones is usually constructive in the course of the acute episode, but the illness has been categorised amongst hypoketotic causes of metabolic acidosis and coma [11]. In the absence of gluconeogenesis, ketones would be anticipated to accumulate as soon as hepatic glycogen is depleted, and the usual disaster is related to ketosis. Nor do they develop proximal renal tubular dysfunction after fructose, as do those former patients. Hepatomegaly develops regularly in infancy, however there are often no signs of liver illness [11, 12]. Neonatal hyperbilirubinemia of a severity requiring exchange transfusion was reported in three infants [13]. Fast spindle-shaped bursts on a gradual amplitude sample have been described [2], in addition to a slow-wave sample [16]. Of course, impaired psychological development, in addition to demise might accompany neonatal or early infantile hypoglycemic crises, however fasting tolerance improves with age, and patients regular by childhood usually develop normally. In addition to the lactic acidemia, evaluation of the blood reveals elevated concentrations of alanine and uric acid [17]. Most reviews have been of Europeans, however there have been reports from the United States, Japan, and Lebanon [10, 20�25], and among the many European families in one sequence a majority were Turkish [25]. Among 9 patients from six households in Israel, two families had been Jewish, three Arabic, and one Druze [26]. Testing for heterozygosity by assay of the enzyme in leukocytes could also be unreliable. Prenatal analysis and heterozygote detection could be completed if the mutation is known. The defective enzyme in sufferers has normally been identified within the assay of biopsied liver [1�3, 29]; a majority of sufferers have little or no activity. The enzyme can also be energetic in kidney [3, 15] and jejunum [30], and the defect has been recognized in each these tissues. Assay of leukocytes is controversial and the activity in regular people is quite low. The defect has been documented in tissues obtained at autopsy, however the outcomes should be interpreted with warning due to rapid inactivation of the enzyme with autolysis [31]. Diagnosis has generally required the assay of the enzyme in biopsied liver, however mutational analysis might allow its avoidance. Culture of monocytes in media rich in calcitriol has been reported [32] to allow the prognosis by enzyme assay. A radiochemical methodology has developed that detects faulty (absent) enzyme activity in isolated monocytes before and after incubation with calcitriol in tissue tradition media [33]. The insG960-961 accounted for forty six p.c of 22 mutant alleles in Japanese and 14 of 28 mutant alleles in non-Japanese [7]. The fasting that standard infants often endure within the first days of life makes for a neonatal presentation in patients with little residual enzyme exercise [35]. If examined with a provocative fast, sufferers turn out to be hypoglycemic when saved glycogen is exhausted. This could happen in a couple of hours in an infant [15] or after 14�20 hours in an older patient [1, 2, 15, 34]. Depletion of glycogen previously synthesized from glucose by injection of glucagon early in the fast ensures that gluconeogenesis is being examined adequately (Chapter 49) [10]. Administration of glucagon after the event of hypoglycemia leads to no glycemic response. Hypoglycemia can also be generated by a food regimen low in carbohydrate and excessive in protein and fat [10]. This test has been employed in sufferers judged on the premise of the response to fasting to have lactic acidemia, as a outcome of a defect in gluconeogenesis (Chapter 49), in order to counsel that the enzyme be assayed on biopsied liver. Following fructose, the blood sugar drops to hypoglycemic ranges within quarter-hour; lactic acidemia and elevated ranges of alanine and uric acid accompany systemic acidosis. Glycerol loading results in a response much like that with fructose [1, 7, 30, 38].
Tags: generic 17 mg duetact, duetact 17 mg discount mastercard, duetact 16 mg order with visa, 17 mg duetact discount otc, duetact 16 mg buy without prescription, duetact 17 mg for sale, duetact 17 mg fast delivery, duetact 16 mg order free shipping, duetact 16 mg generic otc, duetact 16 mg proven, duetact 16 mg discount overnight delivery, duetact 16 mg buy lowest price, duetact 17 mg with mastercard, duetact 16 mg purchase online, purchase 17 mg duetact mastercard, duetact 17 mg discount overnight delivery
10 of 10
Votes: 22 votes
Total customer reviews: 22
Customer Reviews
Ernesto, 35 years: First administration could result in respiratory arrest in responders, and thus therapy must be carried out with support of respiratory management [4].
Lars, 63 years: Among this population of sufferers with severe disease, deletions or rearrangements seen in Southern blots happen in about 20 % [7, eleven, 70�72].
Steve, 53 years: What the fate of these bacteria-laden Schwann cells is and whether or not these cells retain or change Schwann cell id have been unknown till recently.
Jensgar, 23 years: Myoclonic epilepsy in Gaucher disease: genotype�phenotype insights from a rare patient subgroup.
Harek, 54 years: Identification and quantitation of adenine deoxynucleotides in erythrocytes of a patient with adenosine deaminase deficiency and extreme combined immunodeficiency.
Basir, 55 years: The stratum basale or stratum germinativum is the deepest epidermal layer, and underneath it lie the layers of the dermis.
Stan, 42 years: This creates a dilemma for the pathogen between dependence on virulence issue expression and recognition of these factors by the immune system of the host.
Berek, 44 years: The initial step consists of clearly defining the biological query and applicable design of the screening assay, together with exercising explicit care in choosing the mannequin and the knockdown/ knockout library.
