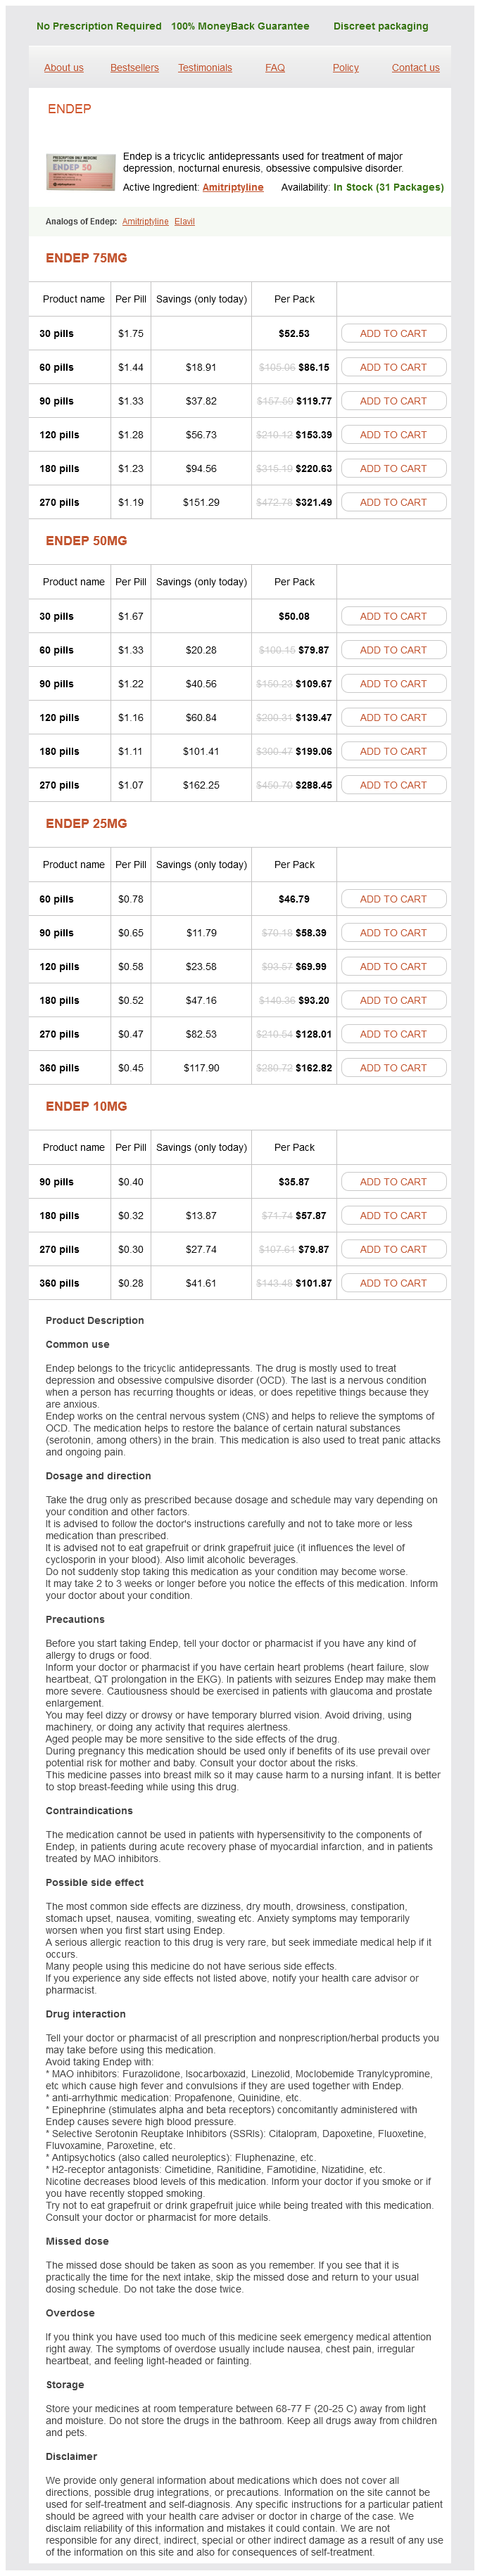
Endep 75mg
- 30 pills - $52.53
- 60 pills - $86.15
- 90 pills - $119.77
- 120 pills - $153.39
- 180 pills - $220.63
- 270 pills - $321.49
Endep 50mg
- 30 pills - $50.08
- 60 pills - $79.87
- 90 pills - $109.67
- 120 pills - $139.47
- 180 pills - $199.06
- 270 pills - $288.45
Endep 25mg
- 60 pills - $46.79
- 90 pills - $58.39
- 120 pills - $69.99
- 180 pills - $93.20
- 270 pills - $128.01
- 360 pills - $162.82
Endep 10mg
- 90 pills - $35.87
- 180 pills - $57.87
- 270 pills - $79.87
- 360 pills - $101.87
Endep dosages: 75 mg, 50 mg, 25 mg, 10 mg
Endep packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 913
Only $0,3 per item
Description
Elderly patients have a high incidence of drug interactions as a outcome of they generally take a number of drugs and they typically have age-related changes in drug clearance medications kidney disease endep 75 mg best. Interactions Based on Absorption Absorption from the gastrointestinal tract could additionally be influenced by brokers that bind medication (eg symptoms 0f yeast infectiion in women 10 mg endep cheap overnight delivery, resins medicine interactions buy cheap endep 10 mg online, antacids medications known to cause pancreatitis endep 50 mg cheap online, calcium-containing foods), by brokers that enhance or lower gastrointestinal motility (eg, metoclopramide or antimuscarinics, respectively), and by medicine that alter the P-glycoprotein and organic anion transporters within the intestine. Concomitant use of antacids, which enhance gastric pH, can lower gastrointestinal absorption of digoxin, ketoconazole, quinolone antibiotics, and tetracyclines. Compounds in grapefruit juice and a few drugs inhibit the P-glycoprotein drug transporter in the intestinal epithelium and may improve the web absorption of drugs that are normally expelled by the transporter. Absorption from subcutaneous websites could be slowed predictably by vasoconstrictors given simultaneously (eg, native anesthetics and epinephrine) and by cardiac depressants that lower tissue perfusion (eg, blockers). Interactions Based on Distribution and Binding Distribution of a drug could be altered by other medicine that compete for binding sites on plasma proteins. This is because warfarin has such a narrow therapeutic window and since its metabolism is dependent upon cytochrome P450 exercise. How does this important anticoagulant work, how is its motion monitored, and if a drug interaction results in an extreme impact, how is its motion reversed Interactions Based on Additive Effects Additive interplay describes the algebraic summing of the effects of two medicine. The combination of tricyclic antidepressants with diphenhydramine or promethazine predictably causes extreme atropine-like results because all these medication have important muscarinic receptor-blocking actions. Tricyclic antidepressants could enhance the pressor responses to sympathomimetics by interference with amine transporter techniques. Similarly, the patient with average to extreme hypertension maintained on one drug is susceptible to excessive reducing of blood stress if another drug with a different site of action is added at excessive dosage. In the case of warfarin, the potential for such opposed effects is enhanced by aspirin (via an antiplatelet action), thrombolytics (via plasminogen activation), and the thyroid hormones (via enhanced clotting issue catabolism). Supra-additive interactions and potentiation seem to be a lot less widespread than antagonism and the simple additive interactions described previously. Supra-additive (synergistic) interaction is said to happen when the end result of interplay is larger than the sum of the medication used alone; the most effective example is the therapeutic synergism of sure antibiotic mixtures similar to sulfonamides and dihydrofolic acid reductase inhibitors corresponding to trimethoprim. Interactions Based on Renal Function Excretion of medicine by the kidney could be changed by drugs that scale back renal blood move (eg, blockers) or inhibit specific renal transport mechanisms (eg, the action of aspirin on uric acid secretion within the proximal tubule). Drugs that alter urinary pH can alter the ionization state of drugs that are weak acids or weak bases, resulting in modifications in renal tubular reabsorption. Interactions Based on Opposing Actions or Effects Antagonism, the best type of drug interplay, is often predictable. For instance, antagonism of the bronchodilating results of 2-adrenoceptor activators utilized in asthma is to be anticipated if a blocker is given for an additional situation. Likewise, the action of a catecholamine on coronary heart price (via -adrenoceptor activation) is antagonized by an inhibitor of acetylcholinesterase that acts by way of acetylcholine (via muscarinic receptors). Herbal Medication Dong quai Garlic, ginkgo Ginseng Kava Liquorice root Ma huang, different ephedra preparations St. Many different herbs, or edible vegetation, also comprise compounds with anticoagulant or antiplatelet potential, including anise, arnica, capsicum, celery, chamomile, clove, feverfew, garlic, ginger, horseradish, meadowsweet, onion, passion flower, turmeric, and wild lettuce. If he makes use of diphenhydramine for allergic rhinitis, a drug interplay is prone to happen because (A) Both drugs block muscarinic receptors (B) Both drugs block reuptake of norepinephrine released from sympathetic nerve endings (C) Diphenhydramine inhibits imipramine metabolism (D) Imipramine inhibits the metabolism of diphenhydramine (E) the medication compete with each other for renal elimination 4. If phenelzine is run to a patient taking fluoxetine, which of the following is most likely to occur The antihypertensive results of captopril may be antagonized (reduced) by which of the next A 55-year-old affected person currently receiving a drug for a psychiatric condition is to be began on diuretic therapy for mild heart failure. Consideration should be given to the fact that thiazides are known to reduce the excretion of which of the next A hypertensive patient has been using nifedipine for some time without untoward effects. Which drug has resulted in severe hematotoxicity when administered to a patient being treated with azathioprine The following section consists of an inventory of lettered options adopted by several numbered objects. This drug enhances the toxicity of methotrexate by reducing its renal clearance. In the case of phenelzine and fluoxetine, the interaction has resulted in a fatal outcome. Pioglitazone is a hypoglycemic drug used in patients with type 2 diabetes mellitus and has no vital impact on blood pressure. Azathioprine is transformed to mercaptopurine, which is answerable for each its immunosuppressant action and its hematotoxicity. Allopurinol inhibits xanthine oxidase, the enzyme that metabolizes mercaptopurine. The antagonistic results of methotrexate, together with its hematotoxicity, are predictably increased. In distinction, the herb decreases the effectiveness of other medicine (including cyclosporine, estrogens, and protease inhibitors) by way of its induction of drugmetabolizing enzymes. Compounds in grapefruit juice can increase the speed and extent of bioavailability of several dihydropyridine calcium channel blockers, including felodipine and nifedipine. This is a good instance of an additive drug interaction resulting from 2 medicine appearing on the same kind of receptor. Most tricyclic antidepressants, phenothiazines, and older antihistaminic medicine (those obtainable without prescription) are blockers of muscarinic receptors. Used concomitantly, any pair of those agents will demonstrate a predictable enhance in atropine-like adverse results. Because warfarin inhibits the synthesis of coagulation factors and never the perform of preformed elements, it has a comparatively gradual onset and offset of activity. Excessive anticoagulation could be reversed by administration of vitamin K or by transfusion with contemporary or frozen plasma, which contains practical clotting components. Describe how the pharmacodynamic characteristics of different drugs administered concomitantly could lead to additive, synergistic, or antagonistic results. However, though fundamental examine guidelines could additionally be utilized to any learning train, test-taking methods rely upon the type of examination. For those excited about test-writing methods, the Case and Swanson reference is strongly really helpful (see References). When finding out dense textual material, cease after a few pages to write out the details of it from memory. These are all energetic learning techniques; mere studying is passive and much much less effective until you occur to have a photographic memory. Your notes should be legible or typed on a computer, and saved for ready access when reviewing for exams. Some regular, day-by-day studying and digestion of conceptual material is normally needed to avoid last-minute indigestion. If the examination has a number of elements, allot time to each part in proportion to its length and difficulty. Students are often suggested to avoid altering their first guess on multiple-choice questions. Note that this may not be true for some native examinations; some scoring algorithms do penalize for incorrect solutions. Lists of these methods are widely obtainable (eg, in the descriptive materials distributed by the National Board of Medical Examiners to its candidates). Many of the newer "medical correlation" questions on the Board examination have an extremely lengthy stem that provides a nice deal of clinical data. One technique for rapidly narrowing the search, especially when confronted with a long stem, is to first learn the final sentence of the stem, then scan the answer list. If 2 statements are contradictory (ie, only 1 can be correct), chances are good that 1 of the two is the correct answer (ie, the opposite 3 choices could also be distracters). In the pair of the proper reply with a contradictory distractor (choices A and C), the teacher revealed what was being tested and then used the opposite three as "filler. Note that this technique is legitimate only if you should guess; many instructors introduce contradictory pairs as distracters.
Gypsy Weed (Veronica). Endep.
- How does Veronica work?
- Dosing considerations for Veronica.
- What is Veronica?
- Are there safety concerns?
- Loss of appetite; arthritis; gout; itching; kidney, liver, lung, skin, spleen, stomach, and urinary problems; wound healing; and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96175
Retained placenta is related to accent placental lobe or irregular uterine invasion symptoms 7 dpo bfp discount endep 10 mg line. Placenta accreta/increta/percreta is the analysis when the examination exhibits placental villi infiltration medicine woman order endep 75 mg visa. Placental villi may be infiltrated to the deeper layers of the endometrium (accreta) ad medicine endep 25 mg discount with mastercard, myometrium (increta) symptoms 0f diabetes endep 50 mg generic visa, or serosa (percreta). It can also be associated with severe preeclampsia, amniotic fluid embolism, or extended retention of a useless fetus. Most Common Cause the most typical cause of unilateral nonbloody nipple discharge is intraductal papilloma. Breast Mass Fibrocystic Disease this classically presents in a lady age 20�50 with cyclical, bilateral painful breast lump(s). A simple cyst may have sharp margins and posterior acoustic enhancement on ultrasound. Fibroadenoma this classically presents as a discrete, firm, nontender, and extremely mobile breast nodule. Diagnostic Testing the steps in prognosis of any affected person (including pregnant women) with a breast mass are as follows: 1. A 30-year-old lady complains of bilateral breast enlargement and tenderness, which fluctuates together with her menstrual cycle. A 47-year-old lady completes her yearly mammogram and is informed to return for analysis. Excision biopsy Core needle biopsy Repeat screening mammogram in 6 months Repeat screening mammogram in 12 months Ultrasound Mammogramshouldbe donebeforebiopsy. A cluster of microcalcifications are principally benign; nevertheless, roughly 15�20 % symbolize early most cancers. Invasive Breast Diseases Invasive ductal carcinoma is the most common type of breast most cancers (85 % of all cases). It tends to be multifocal (within the same breast) and is bilateral in 20 p.c of instances. Established threat elements for breast most cancers: Breastcancerscreening guidelinespertheU. Treatment Primary remedy of invasive carcinoma when tumor dimension < 5 cm is lumpectomy + radiotherapy � adjuvant therapy � chemotherapy. Lumpectomy plus radiotherapy Modified radical mastectomy Modified radical mastectomy plus radiotherapy Neoadjuvant chemotherapy plus lumpectomy plus radiotherapy Tamoxifen and radiotherapy Answer: A. Breast-conserving surgical therapy (lumpectomy) plus radiotherapy is the usual of take care of invasive illness. Adenomyosis 460 Gynecolog y Leiomyoma Three layers type the uterus: endometrium (inner layer), myometrium (middle layer), and perimetrium (outer layer). The myometrium is made up of clean muscle, composed mainly of the proteins myosin and actin. Leiomyoma of the uterus is a easy muscle growth of the myometrium and is the most typical benign uterine tumor. The case will describe an AfricanAmerican lady (the disease is 5 instances more frequent in African Americans) of childbearing age with an enlarged, firm, uneven, nontender uterus. Look for elevated tumor progress and symptoms during pregnancy (growth corresponds to estrogen stimulation) and tumor shrinkage in menopause. Leiomyoma is mostly asymptomatic (intramural location), but when symptomatic, it presents as one of many following: Intermenstrual bleeding and menorrhagia (submucosal location) with distortion of the uterine cavity seen on saline ultrasound (see image). Adenomyosis Leiomyoma Symptoms Secondary dysmenorrhea and menorrhagia � symptoms of bladder, ureter, or rectal compression 1. Histology Large intramural or subserosal myomas; saline infusion can show submucosal myomas Direct visualize tumors Diffusely enlarged uterus with cystic areas within the myometrial wall N/A Definitive analysis Adenomyosis Secondary dysmenorrhea and menorrhagia Management of Leiomyoma vs. Physical examination is normal with a normal-sized uterus and with no vulvar, vaginal, or cervical lesions. Begin progestin remedy Begin estrogen and progestin remedy Perform an endometrial biopsy Perform a Pap smear and endocervical sampling Prescribe topical estrogen cream Nevergiveestrogenalone toawomanwithauterus. The commonest reason for postmenopausal bleeding is vaginal or endometrial atrophy, however an important diagnosis to rule out is endometrial carcinoma (the most typical gynecologic malignancy). Endometrial biopsy is the first step in management of any affected person with postmenopausal bleeding. The most necessary danger components for endometrial carcinoma are unopposed estrogen states (obesity, nulliparity, late menopause/early menarche, continual anovulation) and a historical past of tamoxifen use. All postmenopausal bleeding is suspected endometrial carcinoma till confirmed in any other case. Simple Cyst: Physiologic Cysts (Luteal or Follicular Cysts) that is the commonest cyst that occurs during the reproductive years. Management Laparoscopic/laparotomy removal, either - cystectomy (to retain ovarian function); or - oophorectomy (if fertility is no longer desired). Appendectomy Give high-dose estrogen and progestin Laparoscopic evaluation of ovaries Observation Perform oophorectomy Answer: C. Sudden onset of severe lower stomach ache within the presence of an adnexal mass is presumed to be ovarian torsion. A 9-year-old woman presents with right adnexal ache and sophisticated cystic mass on ultrasound. Answer: Germ cell tumor: these are most typical in young girls and current in early-stage illness. They endure mitosis, meiosis, and mobile differentiation to turn into mature gametes (sperm or eggs). Answer: Epithelial tumor: this is the most typical ovarian most cancers in postmenopausal girls. Answer: Granulosa-theca (stromal tumor): this ovarian tumor secretes estrogen and may trigger endometrial hyperplasia. Tumor markers: Estrogen A 48-year-old lady complains of elevated facial hair and deepening of her voice. Answer: Sertoli-Leydig cell (stromal tumor): this ovarian tumor secretes testosterone. This is a mucin-producing adenocarcinoma from the abdomen that has metastasized to the ovary, most commonly to each ovaries. The patient states that her final Pap smear, accomplished approximately 1 year in the past, was adverse. She has been sexually energetic, using combination oral contraception tablets for the last 4 years. Management of Abnormal Histologyp Step in Management Observation and follow-up Ablative modalities When is that this step the answer Diagnostic Testing Cervical biopsy: the commonest prognosis is squamous cell carcinoma. Colposcopy and biopsy Cone biopsy Endocervical curettage Hysterectomy Repeat Pap after being pregnant Answer: A. Sonogram 470 Gynecolog y Cervicitis that is the analysis when cervical discharge is found on routine exam, usually with out other symptoms. The affected person may also have a history of ectopic being pregnant or abnormal vaginal bleeding. Secondary Dysmenorrhea Secondary dysmenorrhea presents related signs as primary dysmenorrhea however is due to another disorder. However, other pathology (such as adenomyosis or leiomyomas) can be the underlying pathology. It classically presents in women over 30 with dysmenorrhea, dyspareunia, dyschezia (painful bowel movements), and infertility. Itis alsoelevatedin: Cirrhosis Endometriosis Peritonitis Pancreatitis Vaginal Bleeding and Its Absence Premenarchal Vaginal Bleeding this is bleeding that happens earlier than menarche. The affected person states that she started menstruating at age thirteen and that she has had regular menses till the previous 6 months. Irregular bleeding in reproductive age should all the time be evaluated first for pregnancy. If being pregnant is dominated out, workup for anatomical causes of bleeding or anovulation may be began. Primary Amenorrhea Primary amenorrhea is identified with absence of menses at age 14 with out secondary sexual growth or at age 16 with secondary sexual improvement. Diagnostic Testing Physical exam and ultrasound: - Are breasts present or absent She stories that her daughter has good grades, research hard but appears stressed out most of the time which is why she believed her period was delayed.
Specifications/Details
The affected person complains o gentle unsteadiness or light-headedness medicine 93 5298 purchase endep 75 mg on line, particularly with a change o head place symptoms for pneumonia endep 10 mg buy free shipping. As the e ects o the concussion reverse treatment 2 prostate cancer best 25 mg endep, the signs and objective ndings additionally transfer toward normal symptoms 9f diabetes discount endep 25 mg mastercard. Vascular Insu ciency and Its Syndromes Vascular insu ciency is often a widespread trigger o vertigo amongst individuals over the age o 50 as properly as patients with diabetes, hypertension, or hyperlipidemia. The ollowing syndromes have been recognized amongst sufferers with vascular insu ciency. Cha pter 1: Syndromes and Eponyms 49 Labyrinthine Apoplexy Labyrinthine apoplexy is because of thrombosis o the internal auditory artery or one o its branches. Wallenberg Syndrome Wallenberg syndrome is also referred to as the lateral medullary syndrome secondary to in arction o the medulla, which is supplied by the posterior in erior cerebellar artery. Loss o the sense o pain and temperature sensations on the ipsilateral and contralateral physique D. Ipsilateral Horner syndrome Subclavian Steal Syndrome Subclavian steal syndrome is characterized by intermittent vertigo, occipital headache, blurred imaginative and prescient, diplopia, dysarthria, pain in the higher extremity, loud bruit or palpable thrill over the supraclavicular ossa, a di erence o 20 mm Hg in systolic blood pressure between the 2 arms, and a delayed or weakened radial pulse. A gradual recovery ollowed by months o positional vertigo o the benign paroxysmal sort C. Drop attacks with out loss o consciousness and precipitated by neck motion are attribute o vertebrobasilar insu ciency. Cervical Vertigo Cervical vertigo could be brought on by cervical spondylosis in addition to by other etiologies. Cervical spondylosis may be brought about by degeneration o the intervertebral disk. With mobility, the bulging o the annulus is elevated, causing increased traction on the periosteum to which the annulus is connected and stimulating proli eration o bone along the margins o the vertebral our bodies to produce osteophytes. Barre believed that the symptoms o cervical spondylosis (including vertigo) are due to irritation o the vertebral sympathetic plexus, which is in close proximity to the vertebral artery. It is claimed that spondylosis irritates the periarterial neural plexus in the wall o the vertebral and basilar arteries resulting in contraction o the vessels. Others claimed that the loss o proprioception in the neck may give rise to cervical vertigo. Emotional pressure, rotation o the top, and extension o the pinnacle may cause the neck muscle (including the scalenus anticus) to be drawn tightly over the thyrocervical trunk and subclavian artery, compressing these vessels in opposition to the proximal vertebral artery. In elderly individuals, 50 Pa rt 1: General Otolaryngology a change rom the supine to the upright position could give rise to postural hypotension, which in turn may trigger vertebrobasilar insu ciency. The aortic arch syndrome and subclavian steal syndrome may cause cervical vertigo. Symptoms embrace the ollowing: Headache, vertigo Syncope innitus and loss o listening to (usually low requencies) Nausea and vomiting (vagal response) Visual symptoms, corresponding to ashing lights (not uncommon), because of ischemia o the occipital lobe, provided by the posterior cerebral artery, a department o the basilar artery F. Supraclavicular bruit seen by physical examination in one-third o the patients Each o these symptoms normally seems when the top or neck assumes a certain position or change o position. Proper posture, neck workout routines, cervical traction, heat massage, anesthetic in ltration, and immobilization o the neck with a collar briefly are all good therapeutic measures. I traction is required, it can be given as a ew kilos horizontally or several hours at a time. For cervical spondylosis with out acute root signs, heavy traction (100 lb) or 1 to 2 minutes constantly or 5 to 10 minutes intermittently is considered by some to be extra e ective. The second is the momentary, nearly petit mal seizure whose whole brie moment is skilled as dysequilibrium. Cortical vertigo both can be as severe and episodic as M�ni�re illness or it could maniest itsel as a gentle unsteadiness. The affected person may exhibit daydreaming and purpose ul or purposeless repetitive movements. The patient could experience an unusual sense o amiliarity (d�j� vu) or a way o strangeness (jamais vu). Should the seizure discharge unfold beyond the temporal lobe, grand mal seizures might ensue. Vertigo as a outcome of Whiplash Injury Patients o en complain o dizziness ollowing a whiplash damage. The onset o dizziness o en happens 7 to 10 days ollowing the accident, significantly with head actions toward the side o the neck most involved in the whiplash. Vestibular examination can reveal spontaneous nystagmus or positional nystagmus with the top turned within the course o the whiplash. Vertigo With Migraine Vertebrobasilar migraine is due to impairment o circulation o the mind stem. The signs include vertigo, dysarthria, ataxia, paresthesia, diplopia, di use scintillating scotomas, or homonymous hemianopsia. The initial vasoconstriction is ollowed by vasodilatation giving rise to Cha pter 1: Syndromes and Eponyms 51 an intense throbbing headache, normally unilateral. Vestibular Neuronitis Occasionally re erred to as viral labyrinthitis, vestibular neuronitis begins with a nonspeci c viral illness ollowed in a variable period o as much as 6 weeks by a sudden onset o vertigo with nausea, vomiting, and the sensation o blacking out accompanied by extreme unsteadiness. The remission may be hastened by the e ective use o vestibular suppressant medication or a period o up to 6 weeks. A er the acute episode has subsided, which may take weeks, the affected person continues to experience a slight sensation o light-headedness or a while, notably in connection with sudden actions. The acute episode may be ollowed by a period o positional vertigo o the benign paroxysmal sort. In these patients, an analysis or metabolic, otosclerotic, or autoimmune actors is indicated. I these different actors are identi ed and the appropriate treatment initiated, the symptoms could disappear. I a er an acceptable therapy and statement period, and i incapacitating signs persist, a retrolabyrinthine vestibular nerve section is indicated. Nonsyphilitic interstitial keratitis and progressive listening to loss with vestibular symptoms is characteristic o A. Which o the ollowing syndromes is characterized by cerebellar, medullary, and spinal hemangioblastoma, pheochromocytoma, and bilateral papillary adenocarcinoma o the temporal bone Primary Snoring this de ned as sn ring with ut c nc mitant ar usals r sleep ragmentati n. Once an apnea ccurs the cardiac utput decreases, triggering elevated ring the sympathetic nerv us system and ass ciated increased systemic vascular resistance. This cycle occurs repeatedly thr ugh ut the apneic sleep time and ultimately persists thr ugh ut the day t. In the midst apneic events there can be increases in the intracranial pressure leading t decreased cerebral per usi n, Cha pter2: Obstructive Sleep Apnea fifty five which c rresp ndingly increases str ke risk. Vari us 58 Degree of Obstruction a Pa rt 1: General Otolaryngology Con guration c A�P Lateral Concentric Structure Velum Oropharynx lateral wallsb Tongue Base Epiglottis For each construction, there must be a classi cation as to the diploma of obstruction and con guration of obstruction. Open bins re ect the potential con guration that could be visualized related to a speci c structure. There are als questi ns as t validity the examine in that patients requently rep rt that their sleep in the lab was di erent than that which they d at h me. Patients have a tendency t believe the diagn sis m re i the check takes place in their wn bed, and this in flip will increase therapeutic adherence. As demand will increase r sleep diagn stics and techn lgy c ntinues t impr ve, level 3 ambulat ry sleep research are likely t gr w in imp rtance. Practice requirements r ambulat ry sleep studies have been devel ped based n American and Canadian T racic S ciety tips, and practiti ners in sleep medication and surgery sh uld amiliarize themselves with these d cuments. Patients wh are eeling sleepy als c mm nly eel the necessity t take stimulants (eg, excess ca eine) that can urther alter sleep hygiene. [newline]In the past the air pumps had been cumbers me and l ud, however m dern gadgets are b th trendy and ar quieter. Newer machines have built-in c mpliance m nit rs in addition to sel -diagn stics t verify r air leak as properly as aut -titrati n the air pressure. H wever, numer us studies indicate that generally nly appr ximately 50% patients are still ready t use the system at this fee. Sof Palate Implants Palatal implants made p lyethylene terephthalate have been develped r inserti n utilizing a prel aded hand-piece (Medtr nic). The implants are inserted in the midline and laterally, just distal t the hard/s palate juncti n. Implant rejecti n rates have c nsistently h vered at 1% ver the years since intr ducti n. The ensuing scar sti ens the t ngue and als ver time reabs rbs, thus v lumetrically reducing the t ngue measurement. P tential c mplicati ns include ulcerati n, style change, reign b dy sensati n, and in ecti n.
Syndromes
- Narrow bifrontal skull
- Bloody stools
- Swelling
- Body -- tinea corporis
- There are no risks associated with external monitoring. Some people believe the test, however, may lead to early delivery, unnecessary cesarean section, and other more invasive forms of delivery. Talk to your health care provider about the use of external monitoring.
- Is it only on one side?
Related Products
Additional information:
The pericranial ap is positioned under the dural reconstruction and wedged between the healthy dura and beyond the posterior extremity o the de ect and the residual anterior ossa oor at this web site treatment 0f osteoporosis discount 75 mg endep mastercard. A dacryocystorhinostomy may be thought of with placement o sialastic stent by way of the lacrimal pucta i the duct has been severed treatment 002 purchase endep 75 mg free shipping. Free microvascular aps are reserved or cases requiring a total maxillectomy medications that cause hyponatremia 75 mg endep discount visa, acial skin or an in depth resection o the in ratemporal ossa resulting in a big cavity medicine to reduce swelling endep 75 mg buy generic online. Orbital exenteration is normally indicated with gross invasion o the periorbital at, extraocular muscular tissues, or optic nerve. Y Orbital exenteration: periorbita is incised over the superior and lateral orbital rims. Lidocaine is injected round these constructions to prevent autonomic-induced cardiac arrhythmias. The medial and in erior orbital wall must be eliminated en bloc in sufferers with sinonasal carcinoma. Expanded Endonasal Endoscopic Approach to Anterior Skull Base � Bene ts embody the avoidance o giant trans acial and scalp incisions, higher visualization through magni cation and angled scopes as nicely as avoidance o mind retraction. Can use dural gra matrix within the subdural space ollowed by ascia gra ollowed by nasoseptal ap. In certain cases tracheotomy can be used to divert the ow o air and forestall pneumocephalus. Meningioma, craniopharyngioma, plasmacytoma, arachnoid cyst, and craniopharyngeal stulae v. C-shaped incision rom the temporal area extending 4 cm postauricularly then down into the neck. A mastoidectomy removing the mastoid tip, whole bony auditory canal, medial canal pores and skin, tympanic membrane and middle ear contents is per ormed. The inside carotid artery is dissected rom the neck to the cranium base to its place below the cochlea. The posterior and center ossa dura can be opened to expose the cranial cavity when intracranial extension is present. Can sacri ce the labyrinth and/or cochlea to entry the internal carotid artery, the petrous apex, the clivus or the anterior brain stem. Several methods can be applied or reconstruction including recontouring with allogenic tissue matrix, temporalis muscle- ascia ap or microvascular ree ap. It is carried in eriorly in ront o the ear or parotid, sinus and neck lesions or behind the ear or lesions o the temporal bone or clivus. The ap is elevated orward to the level o the lateral orbital rim and angle o the mandible. The temporal department o the acial nerve is protected by elevating a patch o temporal ascia deep to the branch through the pores and skin elevation. The temporalis muscle is elevated through and incision made in the pericranium about 2 cm outdoors the periphery o its origin. Under magni cation, the tympanomeatal ap is raised and the middle ear is entered anteriorly, exposing the opening o the Eustachian tube. The superior cut is directed superiorly into the middle ear, c c throughout the tensor tympani canal anterior to the cochleari orm process into the superior half o the protympanum. The in erior minimize is made throughout the hypotympanum into the mouth o the Eustachian tube. The external canal is then drilled all the method down to the extent o the dura into the squamosal part o the temporal bone superiorly and in eriorly by way of the thickness o the exterior canal into the glenoid ossa. The cut by way of the glenoid ossa is simply about 2 mm deep and is directed towards the oramen spinosum the place the middle meningeal artery is ligated. Neurosurgery per orms small craniotomy by way of greater wing o the sphenoid and squamous temporal bone connecting the cut within the exterior auditory canal posteriorly to the pterygoid plates anteriorly. When bone ap is removed a greenstick racture occurs so that the protympanum is ractured across and the interior carotid artery is uncovered because it enters the posterior wall o the bony Eustachian tube. The internal carotid artery can be dissected rom the brous ring at the opening o the carotid canal by way of the vertical and horizontal parts all the means in which to the cavernous sinus i involved with tumor. The tumor is removed en bloc and rozen sections are checked to ensure margins are negative. The carotid artery may be gra ed i sacri ce essential to clear margins versus leaving microscopic illness on the carotid adventitia. Dura is closed with ascia gra s and nasopharynx is separated rom cranial cavity with both a pedicled temporalis muscle ap or a rectus abdominis ree ap. Appropriate or tumors originating rom clivus, upper posterior neck or extending posteroin eriorly rom the temporal bone. Incision is a question mark beginning excessive in the occiput and coursing around the postauricular space descending to the upper neck. The bone o the spinous processes o the cervical backbone is care ully drilled with care not to injure the vertebral artery. I vertebral artery sacri ce is anticipated, a preoperative balloon occlusion check should be per ormed to set up the sa ety o sacri cing the artery. I not sacri ced the artery is mobilized to the oramen magnum and the atlantooccipital joint is exposed. The lateral mass o the atlas is drilled away with care to not injure the occipital emissary vein and the hypoglossal canal. Can lengthen resection up to the temporal bone with a mastoidectomy to expose the jugular bulb. Neurosurgeon can per orm an occipital-spinal usion i concern or spinal instability. The occipital bone gra is replaced and the muscles are reapproximated be ore closure. Presence o tachycardia, arrhythmias, ushing or liable hypertension ought to prompt analysis o 24 hour urine specimen or vanillylmendelic acid, metanephrine and normetanephrine levels. It includes an extensive in ratemporal ossa dissection with mobilization or resection o the petrous carotid artery and middle and posterior ossa craniotomy. Cha pter forty three: Skull Base Surgery 761 umors of the Internal Auditory Canal and the Cerebellopontine Angle � 90% o tumors on the cerebellopontine angle are acoustic schwanommas. The sigmoid sinus is skeletonized and only a really skinny wa er o bone is le covering the sinus (Bill island). Dura is exposed anterior and a pair of cm posterior to the sinus permitting compression o the sinus or improved exposure. All bone covering the dura rom the sigmoid sinus to the porus acousticus is eliminated as nicely as the bone covering the middle ossa dura. The epitympanum is lled with temporalis ascia and open air cell tracts are occluded with bone wax. A 4-cm-by-4 cm craniotomy is per ormed instantly posterior to the sigmoid sinus. The cerebellum is roofed with a cottonoid and retracted posteriorly with a at blade retractor. At this point, tumor could be excised, vestibular nerve sectioned, or the trigeminal, acial, or vestibular nerve may be decompressed. The operculum is a vital landmark, which identi ed the entry level o the endolymphatic duct. The craniotomy de ect is lled with bone chips or a cranioplasty is per ormed, with hydroxylapatite cement and the wound closed. Retrolabyrinthine Approach Originally described by Hitselberger and Pulec in 1972 or part o the h nerve, use o this approach has been expanded. Presently its use is limited to vestibular nerve sections and administration o hemi acial spasm by microvascular decompression. There are minimal benefits to this method and a signi cant drawback o restricted visualization. The dura is skeletonized along posterior ossa and superiorly along the middle ossa dura. The sigmoid sinus is decorticated and retrosigmoid air cells are eliminated to expose the retrosigmoid dura. [newline]A dural ap is made parallel to the sigmoid sinus (behind the endolymphatic sac) up to the level o the superior petrosal sinus. The cerebellum is retracted and the arachnoid incised, exposing the seventh to eighth nerve complex.
Usage: q.h.
This methodology is utilized in digital hearing aids and allows or more com ortable listening in ears with sensorineural listening to loss with a lot recruitment (narrowed dynamic range) medicine man dispensary generic endep 10 mg with mastercard. Many listening to aids permit the person to swap between directional and omnidirectional microphones medicine for high blood pressure buy 75 mg endep fast delivery. These units can suppress eedback and ampli y speech selectively whereas suppressing ambient noise medicine 751 endep 50 mg buy cheap line. Patients with word recognition scores o no less than 50% and a wide dynamic range are normally success ul listening to help customers medications causing hair loss endep 50 mg buy generic on line. Large venting makes a listening to aid extra com ortable by eliminating the occlusion e ect and enhancing listening to in noise. Large venting un ortunately is contraindicated in ears with signi cant low- requency hearing loss. This design takes benefit o the overall principle that sound is perceived as more pure i delivered closer to the tympanic membrane. This eature is frequent right now and could be recognized by the slim acoustic tube with a wire inside. When the battery must get replaced, the device is removed and changed by the audiologist. Implantable Hearing Devices � Implantable hearing systems have been used primarily or rehabilitation o sensorineural hearing loss, but in addition or conductive and blended hearing loss. A piezoelectric crystal modifications form (bends) in response Cha pter 19: Hearing Rehabilitation: Surgical and Nonsurgical 347 to a altering electric eld. A driver containing a piezoelectric crystal can convert electrical alerts into mechanical vibrations o the ossicular chain. Some systems require an iatrogenic ossicular discontinuity to cut back eedback problems. The titanium implant/abutment complicated is surgically placed within the bone behind the a ected ear, near the temporal line, and is allowed to osseointegrate or 6 weeks to three months. The advantage o this technique over standard hearing aids is that any conductive listening to loss element is e ectively bypassed whereas amplication is supplied solely or the sensorineural element. The higher the conductive component o listening to loss, the larger the benefit o this bone conduction system over conventional listening to aids. The exterior processor has a magnet as properly, attaching to the inner parts much like a cochlear implant. These strategies rely upon varied mechanisms to trans er acoustic power rom the dea ear to the contralateral healthy cochlea where sound is perceived. Sound in ormation is trans erred to the receiver worn on the normal ear, traditionally through a wire behind the neck or extra recently via radio waves. Sound is processed within the ordinary manner and delivered to the bony portion o the external auditory canal through an extended earmold. From that time, sound power is delivered through bone conduction to the contralateral wholesome cochlea. Smaller ear canals are di cult to t and a long earmold is usually uncom ortable. Acoustic signals are collected rom the dea side, processed, and delivered through bone conduction to the contralateral wholesome cochlea. First, the ratio o the dimensions o the physiologically energetic portion o the tympanic membrane and oval window is about 20, leading to a 26-dB gain. Cha pter 19: Hearing Rehabilitation: Surgical and Nonsurgical 349 � Actual experimental measurements o center ear pressure gains average solely about 23 dB. This prosthesis spans the gap between the stapes superstructure and the tympanic membrane. The native incus is removed, turned, and changed to reestablish continuity between the malleus and stapes. Generally good listening to results are obtained in experienced hands, with 66% o ears dropped at within 20 dB o the bone conduction line, with listening to results remaining stable over time. Stapes De ect � When the stapes become xed because of otosclerosis, it can be changed with a prosthesis to restore mobility to the ossicular chain. I listening to is similar in both ears, the patient is asked to identi y which ear is better and again, stapedectomy is perormed on the worse-hearing ear as identi ed by the affected person. While stapedectomy can improve listening to, care have to be taken to not racture the tympanic ring whereas curetting the scutum or racture the incus whereas crimping the prosthesis. Similarly, a patient with contralateral peripheral vestibulopathy may not tolerate even minor vestibular complications. I peripheral vestibulopathy is suspected, caloric testing is indicated be ore contemplating stapedotomy. A f oating ootplate can occur during e orts to take away it and can make the task near impossible. Options include enestrating the f oating ootplate utilizing a laser, or aborting the procedure, permitting the ootplate to re xate, after which attempting the surgery again at a later date. Mild dehiscence and overhang o the acial nerve could be managed by bending the prosthesis wire. Surgery may proceed only i this artery appears vestigial, in any other case surgery is aborted. Historically, incidence is about 1% to 2% a er main stapedectomy and higher a er revisions. This sort o postop labyrinthitis normally resolves within a ew days with out permanent sequelae. The bucket handle is just f ipped over the distal incus or stability, and the piston prosthesis has to be mechanically crimped to the incus. Stapes pistons made o nitinol can be crimped utilizing a specialized heating software or a laser. Air-bone hole closure within 10 dB is expected within the majority o major stapedectomies, and closure within 20 dB in almost all cases. Ossicular Chain Reconstruction in a Modif ed Mastoid Cavity � Same principles are typically utilized to ossicular reconstruction in a modi ed mastoid cavity. Practical use o complete and partial ossicular alternative prostheses in ossiculoplasty. All o the ollowing are benefits o behind-the-ear (B E) fashion hearing aids in comparison with different styles, besides A. It is easy to manipulate controls and easy to incorporate switches and volume management. It is pre erred in children because solely the earmold has to be replaced because the child grows. Large venting improves listening to in noise however is contraindicated in ears with signi icant low- requency hearing loss. Methods or rehabilitation o single-sided dea ness depend on trans erring sound vitality rom the dea ear to the contralateral healthy cochlea. Patients with implantable listening to devices typically report increased sound idelity (compared to their conventional hearing aids), reduced eedback issues, and no occlusion e ect. Footplate shoe can be utilized to stabilize the entire prosthesis on the stapes ootplate. In stapedectomy, closure o the air-bone hole within 10 dB can be expected in a majority o circumstances, without signi icant widening o the air-bone hole over time. Electronic devices which offer listening to to patients with severe to pro ound listening to loss. Replace non unctional internal ear hair cell transducer system by changing mechanical sound energy into electrical indicators. Damaged or missing hair cells o cochlea are bypassed and signal is delivered to mind. Di erent electrical alerts despatched to di erent websites within the cochlea (high pitches heard at cochlear base and low pitches at apex). Incoming speech alerts ltered into requency bands which correspond to a given electrode in the array (spectral in ormation trans erred). Ampli ed and compressed to match narrow electrical dynamic range o ear (typical response range o dea ear to electrical stimulation is on the order o only 10-20 dB, even less in excessive requencies). Spiral ganglion cells or axons seem to be the critical residual neural components that are stimulated. Electrode array: current emphasis on small, so, exible arrays o various lengths to shield cochlear structures. T ree exceptions: (i) Michel deformity, congenital agenesis o the cochlea; (ii) slender inside auditory canal syndrome, cochlear nerve may be congenitally absent; and (iii) neuro bromatosis type 2, bilateral vestibular schwannomas.
Tags: endep 25 mg mastercard, 10 mg endep order with amex, 25 mg endep discount mastercard, effective endep 10 mg, buy 25 mg endep visa, discount 25 mg endep fast delivery, 75 mg endep cheap with amex, 25 mg endep order, endep 75 mg discount on line, cheap endep 50 mg without prescription, endep 75 mg order visa, 50 mg endep generic fast delivery, purchase endep 50 mg without a prescription, endep 25 mg order, endep 25 mg cheap free shipping, endep 10 mg buy overnight delivery
10 of 10
Votes: 146 votes
Total customer reviews: 146
Customer Reviews
Yokian, 55 years: Recurrent parotitis o childhood-more frequent in boys, age 3 to 10, recurs weekly or month-to-month, no pus rom duct, imaging exhibits ectasia o ducts, Rx: antibiotic or Staphylococcus aureus, dilation o Stensen duct, and sialendoscopy. Chronic publicity to the ion, particularly in excessive concentrations, might improve new bone synthesis.
Ali, 47 years: Do not intubate previous to visualizing or lesion may turn into compressed and go unnoticed. A current comparison o surgical outcomes in patients who underwent both canal plugging or resur acing (without plugging o the canal lumen) revealed that full resolution o vestibular symptoms and indicators is extra generally obtained with canal plugging than with resur acing alone.
Avogadro, 44 years: A regular individual with metabolic acidosis will take up the entire bicarbonate, and there should still be a low urine pH in a traditional affected person. Secondary Dysmenorrhea Secondary dysmenorrhea presents similar symptoms as major dysmenorrhea but is as a end result of of one other disorder.
Marik, 23 years: This is responsible for irritant results on mucous membranes of the eye, the oropharyngeal cavity, and the respiratory tract. Movement o odors rom the air section o the nasal cavity into the aqueous phase o the ol actory mucus.
Snorre, 40 years: Pupillary examination: assess or af erent pupillary de ect, anisocoria, and peaked/ irregular pupil. Basic Science Correlate Hereditary spherocytosis is the genetic lack of each ankyrin and spectrin in the purple cell membrane.
Will, 26 years: Noniatrogenic Extratemporal Injury � The extracranial nerve is prone to trauma, particularly penetrating injuries, and a direct evaluation should be carried out to consider the status o nerve unction, the extent o so tissue injury, and the quantity o contamination. However, should the second ear turn into involved, it often happens inside 36 months.
Mazin, 21 years: Absence o onset o medical recovery 6 months a er onset o paralysis, progressive paralysis beyond three weeks, and the presence o acial twitching also constitute medical indicators or imaging o the acial nerve. Practical use o complete and partial ossicular replacement prostheses in ossiculoplasty.
