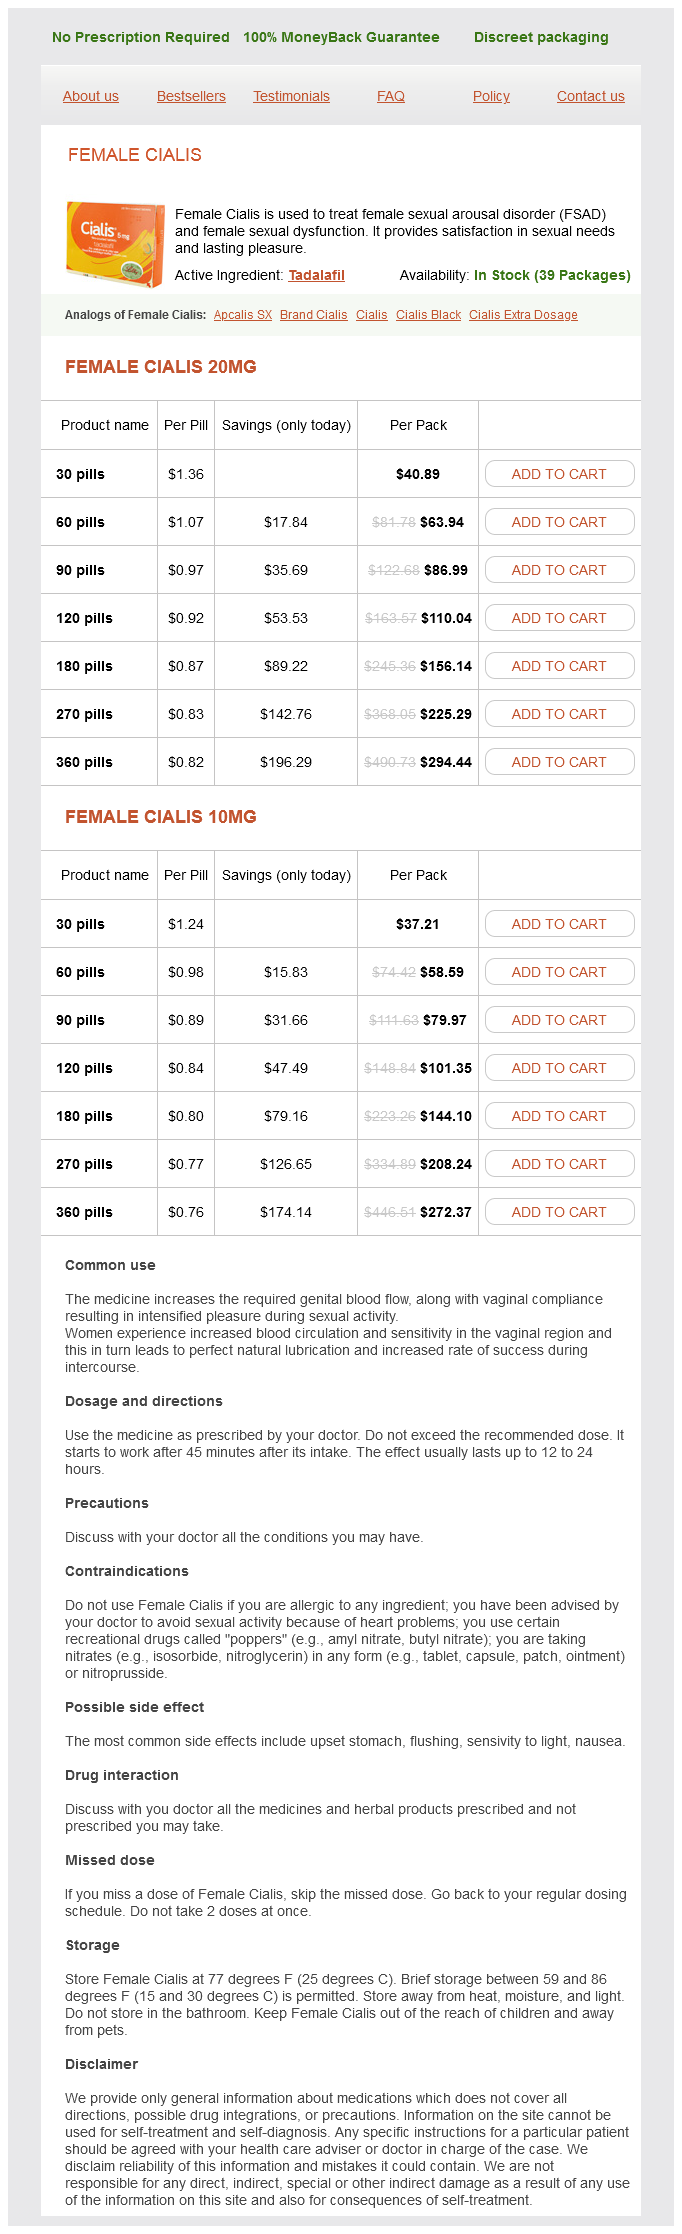
Female Cialis 20mg
- 30 pills - $40.89
- 60 pills - $63.94
- 90 pills - $86.99
- 120 pills - $110.04
- 180 pills - $156.14
- 270 pills - $225.29
- 360 pills - $294.44
Female Cialis 10mg
- 30 pills - $37.21
- 60 pills - $58.59
- 90 pills - $79.97
- 120 pills - $101.35
- 180 pills - $144.10
- 270 pills - $208.24
- 360 pills - $272.37
Female Cialis dosages: 20 mg, 10 mg
Female Cialis packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 587
Only $0,8 per item
Description
Hyperglycemia is regularly observed in hospitalized sufferers receiving specialized nutritional support pregnancy brain female cialis 20 mg discount visa. The glycemic methods should also comply with frequent sense in choosing acceptable therapeutic approaches that not solely management hyperglycemia but additionally have low hypoglycemia threat grants for women's health issues discount 10 mg female cialis. Common causes of hyperglycemia in hospitalized sufferers embrace insufficient insulin dosing breast cancer 9mm purchase 10 mg female cialis free shipping, overfeeding menopause and depression female cialis 20 mg purchase with visa, medicines, in addition to stress, irritation, and infection. In addition, excessive supply of glucose and gluconeogenic substrates through the enteral or parenteral route in hospitalized sufferers can also contribute to hyperglycemia. In common, diabetic sufferers experiencing inpatient hyperglycemia are at higher risk of issues and mortality (3), although evidence is missing if interventions designed to reduce hyperglycemia do improve scientific outcomes, at least in non-critically unwell patients (4). This is especially essential for sufferers with type 1 diabetes mellitus who ought to continue a minimal of basal insulin remedy. Standard enteral formulation comprise 1� 2 cal/ml and, normally, consist of protein, lipid in the type of long-chain triglycerides, and carbohydrates. Current proof and opinions in the subject argue for delayed and permissive underfeeding. Often, continuous feeding is utilized in critically ill patients and intermittent (gravity) feeding is used in medically steady patients. By distinction, jejunal feeding ought to all the time be continuous (nocturnal or 24-hour infusion). The format of the feeding routine has a significant impact on the design of insulin administration packages. Increases within the tube feeding infusion rate ought to be averted until sufficient glucose control has been achieved by applicable insulin management. For patients with hyperglycemia without prior diagnosis of diabetes and no prior use of insulin or oral diabetic agents, initially suggest treatment with short-acting insulin till tube feeding is well tolerated. Once the tube feeding infusion rate has reached 30�40 ml/hr, the usage of intermediate-acting insulin is generally protected. Although some patients receiving gravity feedings can be managed with a few times day by day intermediate-acting insulin alone, others will need mixed intermediate and short-acting insulin therapy. Most patients will require only a once-daily administration of intermediate-acting insulin (alone or mixed with a short-acting insulin preparation) previous to the onset of tube feeding. Continuous feeding over 24 hours: Scheduled administration of intermediate-acting insulin, normally given every 8 hours, could also be required. If the feeding tube is removed or dislodged, the potential for extended hypoglycemia is bigger if long-acting insulin is used. Also, reliance on intermediate insulin requires a more frequent dose-adjustment than use of long-acting insulin, resulting within the potential for more rapid achievement of glucose management. For sufferers on tube feeding, the commonest cause of hypoglycemia is sudden discontinuation of tube feedings. The incidence of hypoglycemia reported in these retrospective research varied between zero. The rationale for the conservative method to insulin intensification in these sufferers is justified by the reality that it might take several days to achieve the specified vitamin goals because of the potential gastrointestinal intolerance throughout early optimization of enteral feeding. Significant diabetic gastroparesis is commonly present in patients with long-standing kind 1 diabetes. Demonstration of delayed gastric emptying establishes the diagnosis of gastroparesis. Accurate prognosis of diabetic gastroparesis is important, because it avoids the misguided attribution of gastrointestinal symptoms to tube feeding or to different elements capable of slowing intestine motility. Most patients with diabetic gastroparesis intolerant of gastric feedings are able to tolerate isoosmolar jejunal tube feedings when initiated at a low fee and advanced slowly. Parenteral vitamin should be used provided that patients fail an affordable trial of tube feeding. Due to its high content material of linoleic acid, soybeanbased lipid emulsions may promote the generation of arachidonic acid-derived eicosanoids and exaggerate the inflammatory response during stress and trauma (25). The initiation of remedy by including insulin on the ratio of 1 unit of insulin per 10�15 grams of dextrose. Furthermore, in some instances, the diabetes history is unknown and it might be troublesome initially to rule out the presence of actually insulin-dependent diabetes in the hospital setting. Gosmanov Management of Hyperglycemia in (Total) Parenteral Nutrition Patient has diabetes The majority of diabetic sufferers require insulin protection when dextrose is infused. The advantage of this method is that the infusion of dextrose and insulin are linked; if the infusion is interrupted for any cause, the administration of insulin can be stopped. If the patient develops hypoglycemia, management ought to be as per hypoglycemia remedy protocol. Hospital Discharge Diabetes Management Options for Patients Receiving Specialized Nutrition Support Following recovery from an acute illness, a quantity of sufferers should still require the continuation of specialised vitamin even after discharge from the hospital. This is especially true for the sufferers who were transitioned from continuous enteral feedings to bolus feeding 3� 4 occasions a day. Metformin therapy supplies many benefits to kind 2 diabetes patients; particular liquid or powder metformin formulations to enable supply via the enteral feeding tube could be tried however can be costly (30). Dextrose 10% or 20% equal doses can be given as an alternative of 50% (less irritant to veins). Hypoglycemia in Patients Receiving Specialized Nutrition Support the event of hypoglycemia has been shown to be related to the elevated danger of complications, the size of hospital stay, and mortality. In addition, worry of hypoglycemia in hospitalized patients stays a major barrier in attaining the optimum glycemic control in the inpatient setting. Hypoglycemia can develop because of an extra of insulin dose, the abrupt discount or discontinuation of diet help, recovery from an acute illness, the titration of glucocorticosteroids or vasopressors, and progressive organ failure. Strategies that would prevent and handle hypoglycemia in sufferers during specialized nutrition assist contain approaches that are pertinent to the administration of hypoglycemia in general as well as would mirror the specifics of potential comorbidities on this patient inhabitants (Table 36-3). Case Study A 70-year-old man with a latest history of total pancreatectomy for continual painful pancreatitis was admitted to a surgical ward for management of intractable nausea and vomiting. Laboratory evaluation was important for normal white blood cell depend, random plasma glucose of 189 mg/dL (10. During the course of the hospitalization, the insulin glargine dose was not changed and his blood glucose levels ranged between 100 and 200 mg/dL (5. Are There Any Specific Glycemic Targets for Hospitalized Patients with Diabetes Receiving Specialized Nutritional Support Hyperglycemia is widespread in sufferers receiving specialised dietary help (Table 36-4). There have been only some small potential trials that have addressed glycemic targets and outcomes on this affected person population; these trials mostly focused on hospitalized patients with diabetes. Future research are wanted to decide safe and beneficial glycemic targets in patients receiving specialised diet support as properly as to determine optimum therapeutic strategies. Current information suggest that the optimum daily carbohydrate necessities in hospitalized patients with diabetes, who obtain specialised nutritional support, is a hundred and fifty grams. Until such evidence turns into available, routine therapeutic methods to management diabetes in hospitalized sufferers must be used as described elsewhere. Similarly, glycemic goals in these sufferers must be in accord with the widespread Acknowledgments the present authors wish to acknowledge the contributions to the earlier edition by Molly McMahon and John Miles, upon which parts of this chapter are based. Glycemic control in non-critically ill hospitalized patients: a scientific evaluation and meta-analysis. Hyperglycemia throughout total parenteral diet: an important marker of poor end result and mortality in hospitalized sufferers. American Association of Clinical Endocrinologists and American Diabetes Association consensus assertion on inpatient glycemic management. Targeting the usage of specialised nutritional formulation in surgical procedure and significant care. Hypocaloric vs normocaloric diet in critically unwell sufferers: a potential randomized pilot trial. High-protein hypocaloric vs normocaloric enteral vitamin in critically unwell patients: a randomized medical trial. Diabetes-specific enteral nutrition formula in hyperglycemic, mechanically ventilated, critically unwell patients: a prospective, open-label, blind-randomized, multicenter examine.
Cappero (Capers). Female Cialis.
- Are there any interactions with medications?
- How does Capers work?
- Diabetes, skin disorders, improving the function of enlarged capillaries, and dry skin.
- What is Capers?
- Dosing considerations for Capers.
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96711
Sodium bicarbonate use and the risk of hypernatremia in thoracic aortic surgical patients with metabolic acidosis following deep hypothermic circulatory arrest menstruation after menopause female cialis 10 mg generic amex. Increased prognosis of main aldosteronism women's health center brookline 10 mg female cialis best, including surgically correctable types women's heart health tips discount female cialis 10 mg fast delivery, in centers from five continents women's health clinic epworth female cialis 10 mg discount mastercard. Renal 11-beta-hydroxysteroid dehydrogenase: a mechanism guaranteeing mineralocorticoid specificity. Cerebral bleeding, infarcts, and presumed extrapontine myelinolysis in hypernatraemic dehydration. Diffuse demyelinating lesions of the brain after the fast development of hypernatremia. Detrimental impact of hyperosmolality on insulin-stimulated glucose metabolism in adipose and muscle tissue in vitro. Dural sinus thrombosis with severe hypernatremia creating in a affected person on long-term lithium therapy. Emergency Management of Acute and Chronic Hypernatremia Berneis K, Ninnis R, Haussinger D, Keller U. Effects of hyper- and hypoosmolality on entire body protein and glucose kinetics in humans. Acute glucocorticoid deficiency and diabetes insipidus are common after acute traumatic mind damage and predict mortality. Hyponatremia following mild/moderate subarachnoid hemorrhage is as a end result of of siad and glucocorticoid deficiency and never cerebral salt losing. Mortality in hyperglycemic disaster: a excessive association with infections and cerebrovascular illness. Intensive care-acquired hypernatremia after major cardiothoracic surgery is related to elevated mortality. Mild hyponatremia, hypernatremia and incident cardiovascular disease and mortality in older males: a population-based cohort research. Lateral pontine and extrapontine myelinolysis related to hypernatremia and hyperglycemia. Central pontine myelinolysis complicating therapy of the hyperglycaemic hyperosmolar state. Extra-pontine myelinolysis secondary to hypernatremia induced by postpartum water restriction. Preventing a drop in effective plasma osmolality to decrease the probability of cerebral edema during remedy of kids with diabetic ketoacidosis. Pituitary dysfunction following traumatic brain injury or subarachnoid haemorrhage. Obesity is related to a plethora of different sequelae, including cancer, hypertension, obstructive sleep apnea, pulmonary thromboembolism, pulmonary hypertension, non-alcoholic fatty liver illness, cholelithiasis, degenerative joint disease, oligomenorrhea/infertility, erectile dysfunction, and cognitive impairment. Increasing evidence additionally indicates the value of metabolic surgical procedure in treating sufferers with sort 2 diabetes, with many patients freed from diabetes drugs and some postoperative sufferers rendered non-diabetic. By far essentially the most profitable of the therapeutic methods has been using statins. In the recent Global Burden of Disease study, data from more than 195 nations have shown that the prevalence of obesity has more than doubled worldwide since 1980 and is now 5% in children and 12% in adults (1). The best therapy of weight problems is prevention and an elevated effort in pediatrics and first care is needed. With dietary intervention techniques aimed toward lowering day by day energy intake by no less than 500 kCal daily, a spread of 4�12 kg at 6 months is typical with a gradual weight regain to follow. For weight loss upkeep, faceto-face or telephone-delivered weight lossmaintenance programs that provide regular contact (monthly or more frequent) with a trained interventionist are evidence-based, and a excessive degree of physical exercise. In this setting, an obsessive/compulsive habits with frequent weighing predicts a more profitable consequence. Increasing evidence also indicates the value of metabolic surgical procedure in treating sufferers with kind 2 diabetes, with many sufferers freed from diabetes medications and a few postoperative sufferers with regular levels of glycosylated hemoglobin A1c rendered non-diabetic. Nevertheless assist for a fibrate such as fenofibrate along with a statin has been instructed when fasting triglycerides are >200 however <500 mg/dL (>2. Two trials with remedy of patients who exhibit this identical vary of triglycerides with omega-3 fatty acids are ongoing. This threat utilizes a danger estimator that now includes assessments for African-Americans in addition to Caucasians. For this group, individualization of statin therapy needs necessary consideration and adverse effects must be rigorously mentioned. The prevalence of overweight/obesity has elevated considerably over the past many years in all parts of the world. Overweight and weight problems are essential modifiable danger components for quite a few related disorders. Bariatric surgical procedure (also termed "metabolic" surgery) has turn out to be recognized as essentially the most definitive and successful means for the remedy of obesity and obesity-associated medical circumstances. Bariatric surgery alters the anatomy of the gastrointestinal tract to restrict caloric intake. Benefits of surgical procedure embody weight reduction and both important enchancment or complete amelioration of metabolic derangements, which must be balanced towards the dangers of every process. Many of the acute emergencies that generally happen on account of bariatric surgical procedure are metabolic in nature, and are associated to both hormonal adjustments or malabsorption induced by the procedure. Acute Emergencies Related to Bariatric Surgery Introduction Overweight and obesity are characterised by an excess of body fat. The prevalence of obese and weight problems has increased significantly over the past many years in all parts of the world. Bariatric Procedures Bariatric surgical procedure (also termed "metabolic" surgery) has become recognized as the most definitive and profitable means for the treatment of weight problems and obesity-associated medical circumstances (1�3). The stomach remnant is allowed to drain through the bypassed portion of the small gut till it reconnects with the distal ileum. This could additionally be by way of reduced gastric acid manufacturing, in addition to a bunch of different helpful hormonal and metabolic effects. A subcutaneous reservoir can be accessed to inflate or deflate the band, as wanted based mostly on medical response. Benefits of surgery embrace weight reduction and both vital improvement or complete amelioration of metabolic derangements, which should be weighed against the risks of each process. Postoperatively, sufferers will want lifelong follow-up that should include recognition of widespread acute emergencies as nicely as the adjustment of medical therapies as comorbid situations improve/evolve. Bariatric Surgery-Related Issues Surgical Emergencies Over the previous decade, both the establishment of high-volume metabolic surgical centers and using laparoscopic method have led to dramatic improvements in surgical outcomes following bariatric procedures (5). Adverse outcomes and observed advantages also depend on the sort of bariatric process undertaken. The most typical causes for hospital readmission after surgery are summarized in Table 43-1 and embody intestinal obstruction, an infection, bleeding, and anastomotic leak (8. While unusual, medical evaluation for these circumstances must be undertaken in appropriate patients. Nausea and Vomiting Due to anatomic changes, sufferers could expertise a major quantity of nausea and vomiting following bariatric surgical procedure. Additionally, the laparoscopic method increases intraabdominal strain throughout every procedure, which can improve threat of thrombus formation (10). Cases of portal or mesenteric venous thrombosis have also been reported, which most frequently current between postoperative days 3 and 30 (11). Symptoms include vague belly ache, and may manifest as liver cirrhosis or bowel ischemia. The routine administration of lowmolecular weight heparin and using compressive stockings have been advised to reduce threat postoperatively (10). Diarrhea and Dumping Syndrome Obesity-related pelvic floor dysfunction ends in fecal incontinence in as high as 20�35% of sufferers with weight problems (13). Following bariatric surgical procedure, the prevalence of fecal incontinence is decreased by approximately 10�15% (14). Patients with dumping syndrome expertise sudden and enormous quantity diarrhea secondary to fast passage of chyme from the stomach to the small intestine (16). Delivery of incompletely digested meals from the stomach can contribute to the associated signs, which include stomach ache Michael A. Treatment of dumping syndrome includes dietary restriction of carbohydrates, especially simple sugars. If signs persist, the administration of acarbose with meals may provide symptomatic relief (19).
Specifications/Details
An extra purpose to deal with even asymptomatic hyponatremia successfully is to stop a lowering of the serum [Na+] to more symptomatic and dangerous levels throughout remedy of underlying conditions women's health center kalgoorlie female cialis 20 mg order on-line. Currently Available Therapies for Treatment of Symptomatic Hyponatremia Conventional management methods for hyponatremia vary from saline infusion and fluid restriction to pharmacologic measures to modify fluid balance women's health lemon zucchini bars female cialis 20 mg buy generic. Consideration of treatment choices should always include an analysis of the benefits as well as the potential toxicities of any therapy breast cancer markers purchase 20 mg female cialis free shipping, and must be individualized for every affected person (37) pregnancy online test buy female cialis 20 mg line. Hypertonic Saline Acute hyponatremia presenting with severe neurological signs is life-threatening, and should be handled promptly with hypertonic solutions, typically 3% NaCl ([Na+] = 513 mmol/L), as this represents the most reliable methodology to quickly increase the serum [Na+]. A continuous infusion of hypertonic NaCl is usually utilized in inpatient settings. Various formulae have been suggested to calculate the preliminary rate of infusion of hypertonic options (33), however till now there was no consensus Emergency Management of Acute and Chronic Hyponatremia concerning optimal infusion charges of 3% NaCl. Because the brain can solely accommodate a mean improve of roughly 8% in mind quantity earlier than herniation occurs, quickly increasing the serum [Na+] by as little as 2�4 mmol/L in acute hyponatremia can effectively cut back brain swelling and intracranial strain (40). This initial therapy is appropriate for sufferers who both have scientific indicators of hypovolemia, or in whom a spot urine Na+ concentration is <20�30 mmol/L (1). Although isotonic saline may enhance the serum [Na+] in some sufferers with hypervolemic hyponatremia, their quantity status will usually worsen with this therapy, so unless the neurological symptoms are extreme, isotonic saline must be avoided. Fluid Restriction For sufferers with persistent hyponatremia, fluid restriction has been the preferred and most generally accepted therapy. Because fluid restriction increases the serum [Na+] largely by under-replacing the excretion of fluid by the kidneys, some have advocated an preliminary restriction to 500 ml lower than the 24hour urine output (44). Restricting fluid intake can be efficient when properly utilized and managed in chosen sufferers, however serum [Na+] are typically elevated solely slowly (1�2 mmol/L/d) even with extreme fluid restriction (41). In addition, this remedy is often poorly tolerated because of an related improve in thirst leading to poor compliance with long-term remedy. This and different identified predictors of failure of fluid restriction are summarized in Table 41-3; the presence of any of these elements in hospitalized patients with symptomatic hyponatremia makes this lower than ideal as an initial therapy. Consequently, such patients are candidates for simpler pharmacological or saline therapy methods. Arginine Vasopressin Receptor Antagonists Conventional therapies for hyponatremia, though efficient in specific circumstances, are suboptimal for a lot of completely different reasons, together with variable efficacy, sluggish responses, insupportable unwanted effects, and severe toxicities. Generally, the 20-mg continuous infusion is used for the primary 24 hours to gauge the initial response. If the correction exceeds 10�12 mmol/L in the first 24 hours, the infusion ought to be stopped and the affected person monitored intently. The commonest side effects of conivaptan embrace headache, thirst, and hypokalemia (50). Similar to conivaptan, tolvaptan therapy have to be initiated in a hospital setting in order that the speed of correction can be monitored rigorously. The starting dose of tolvaptan is 15 mg on the primary day, and the dose could be titrated to 30 mg and 60 mg at 24-hour intervals if the serum [Na+] stays < 135 mmol/L or the rise in serum [Na+] has been < 5 mmol/L within the previous 24 hours. One extra issue that helps to avoid overly speedy correction with tolvaptan is the recommendation that fluid restriction not be used through the active part of correction, thereby allowing the Joseph G. Common side effects of tolvaptan include dry mouth, thirst, elevated urinary frequency, dizziness, nausea, and orthostatic hypotension (51,52). Furthermore, inducing increased renal fluid excretion through either a diuresis or an aquaresis may cause or worsen hypotension in such sufferers. This chance has resulted within the labeling of those medication as contraindicated for hypovolemic hyponatremia (37). Importantly, clinically important hypotension was not observed in both the conivaptan or tolvaptan medical trials in euvolemic and hypervolemic hyponatremic sufferers. The mode of motion is to appropriate hypoosmolality not solely by growing solute-free water excretion but also by decreasing urinary sodium excretion. Doses of 15�60 g/d are typically effective; the dose could be titrated in increments of 15 g/d at weekly intervals as essential to achieve normalization of the serum [Na+]. It is advisable to dissolve the urea in orange juice or another strongly flavored liquid to camouflage the bitter taste. Furosemide and NaCl the use of furosemide (20�40 mg/d) coupled with a high salt intake (200 mmol/d), which represents an extension of the treatment of acute symptomatic hyponatremia (58) to the continual management of euvolemic hyponatremia, has also been reported to be successful in small collection of sufferers (59). Efficacy of Different Treatments to Correct Hyponatremia There have been no adequately powered randomized managed trials to evaluate the efficacy and security of various treatments utilized to appropriate hyponatremia. In this study, "success" was outlined by three different standards: (a) the least stringent was an increase in serum [Na+] of a minimal of 5 mmol/L; (b) the next was correction to a serum [Na+] of a hundred thirty mmol/L; and (c) probably the most stringent was correction to a standard serum [Na+] of one hundred thirty five mmol/L. Of explicit note, fluid restriction, probably the most frequently prescribed remedy within the Hyponatremia Registry sufferers, achieved a correction of serum [Na+] in only 44% of patients treated with this remedy, and isotonic saline in only 36% of sufferers. In this algorithm, patients are divided into three groups primarily based on their presenting signs (Table 41-2): gentle, reasonable, and extreme: Hyponatremia Treatment Guidelines Based on Symptom Severity Although various authors have revealed recommendations on the treatment of hyponatremia (1,2,33,35,37,62�64), no standardized remedy algorithms have yet been universally accepted. This algorithm is based primarily on the neurological symptomatology of r Level three signs embody coma, obtundation, seizures, respiratory misery or arrest, and unexplained vomiting, and often imply a extra acute onset or worsening of hyponatremia requiring instant energetic remedy. Therapies that will quickly elevate serum [Na+] are required to cut back cerebral edema and reduce the risk of probably deadly brain herniation. Level 2 signs, which are more average, embrace altered mental status, disorientation, confusion, unexplained nausea, gait instability, and falls. These symptoms could be both persistent or acute, but allow extra time to elaborate a deliberate approach to selection of treatment. Level 1 symptoms vary from minimal symptoms corresponding to difficulty concentrating, irritability, altered mood, despair, r r Joseph G. The arrows between the symptom bins point out motion of patients between totally different symptom ranges. These signs necessitate a cautious method, particularly when sufferers have underlying co-morbidities. Patients with extreme signs (Level 3) must be handled with hypertonic (3%) NaCl as first-line therapy, adopted by fluid restriction with or without vaptan remedy. For this cause, some authors have proposed simultaneous therapy with desmopressin to reduce the rate of correction to solely that produced by the hypertonic NaCl infusion itself (66,67). Whether adequate clinical knowledge eventually show that this approach is both efficient and secure in bigger numbers of sufferers remains to be decided. Consequently, no active hyponatremia remedy ought to be administered until no much less than 24 hours following profitable will increase in serum [Na+] utilizing hypertonic NaCl. Hypovolemic sufferers ought to be treated with solute repletion, either via isotonic NaCl infusion or oral sodium replacement (1). Although reasonable neurological signs can point out that a patient is in an early stage of acute hyponatremia, they extra often point out a chronically hyponatremic state with enough mind volume adaptation to stop marked symptomatology from cerebral edema. A particular case is when spontaneous correction of hyponatremia occurs at an undesirably fast fee as a outcome of the onset of a water diuresis. If the beforehand mentioned correction parameters have been exceeded and the correction is proceeding more quickly than planned (usually due to continued excretion of hypotonic urine), the pathological events leading to demyelination may be reversed by administration of hypotonic fluids, with or without desmopressin. Efficacy of this strategy is typically recommended each from animal studies (69) as well as case stories in people (35,70) even when patients are overtly symptomatic (71). In addition, some sufferers with minimal symptoms are prone to develop extra symptomatic hyponatremia during periods of increased fluid ingestion. In assist of this, approximately 70% of 31 patients presenting to a college hospital with symptomatic hyponatremia and a mean serum [Na+] of 119 mmol/L had pre-existing "asymptomatic" hyponatremia as the most typical risk factor identified (72). Consequently, remedy of hyponatremia also needs to be thought-about to prevent progression from lower to greater ranges of symptomatic hyponatremia, particularly in patients with a past history of repeated displays for symptomatic hyponatremia. Verbalis Case examine A 75-year-old feminine was admitted for symptomatic hyponatremia with a serum [Na+] = 123 mmol/L. She has a a number of years history of delicate continual hyponatremia, but just lately has experienced confusion and dizziness. She was euvolemic on scientific exam, and was not taking antidepressants or diuretics. After three days on a confirmed 1,000 ml/d fluid restriction, the affected person is still symptomatic and complains of thirst. Laboratory data on day three are: serum [Na+] = 126 mmol/L (normal 135�145), serum [K+] = four. However, she has three parameters that predict doubtless failure of her current fluid restriction: (a) urine osmolality >500; (b) a urine:plasma electrolyte ratio = 0. While tightening the fluid restriction to 500� 800 ml/d would probably end in an improved serum [Na+]. In all hyponatremic sufferers, neurological symptomatology must be rigorously assessed very early within the diagnostic evaluation to outline the symptomatic severity of the hyponatremia and to determine whether the affected person requires extra pressing remedy.
Syndromes
- Hematoma (blood accumulating under the skin)
- The woman is not aware of warm fluid entering her body (important to some women, not to others).
- Nausea
- Rheumatoid arthritis
- Obstructive uropathy
- Increase energy and sex drive
- Change in menstrual patterns
- Chronic liver disease
Related Products
Additional information:
One of the most typical and feared effects is free water shift resulting in menstrual art purchase 20 mg female cialis mastercard brain shrinkage women's health clinic saskatoon purchase female cialis 20 mg overnight delivery, which can causes vascular rupture and permanent cognitive deficits (8) menstrual vs pregnancy best female cialis 20 mg. Cerebral demyelination has additionally been reported in extreme hypernatremia (44) women's health center lynchburg va 20 mg female cialis effective, significantly in liver illness (45). Hypernatremia additionally leads to muscle weak point (46), impaired glucose utilization and insulin function (47) which can lead Emergency Management of Acute and Chronic Hypernatremia to hyperglycemia within the critically ill (48), an increase in venous thromboembolism risk (49), and decreased left ventricular contractility (2). The cellular shrinkage induced by hypernatremia can have catabolic effects and induce proinflammatory cytokine responses (50), which can impair lactate clearance (51). In the intensive care setting, even delicate hypernatremia has been shown to double mortality (53). Hypernatremia has additionally been related to a doubling of mortality and extended length of stay within the intensive care unit following cardiac surgery (57). Propspective knowledge in men with no definable heart problems has additionally linked hypernatremia to extra frequent cardiovascular events and death (61). Although hypernatremia is frequent within the Emergency Department, data have proven that no corrective motion was taken in 18% of these with hypernatremia on presentation, even within the presence of extreme, symptomatic hypernatremia (62). Understanding the issues which cause hypernatremia is important to enable immediate, appropriate administration. It is extremely necessary to note that the severity of signs is strongly influenced by the rapidity of the development of hypernatremia: these with acute hypernatremia are at far higher threat than these with persistent hypernatremia (2,43). Management of Acute Hypernatremia Because of the excess mortality related to hypernatremia, remedy is indicated to scale back mortality and to reverse neurological signs. Rapidly developing hypernatremia (<48 hours) is especially related to the event of neurological sequelae. The majority of instances of acute hypernatremia are simply as a outcome of water depletion, normally precipitated by an intercurrent illness, and occasionally exacerbated by poor thirst response. When hypernatremia is acute or when severe neurological signs are current, quick remedy is indicated; a up to date evaluate has recommended normalization of plasma sodium inside 24 h of commencement of remedy for acute hypernatremia (64). If hypernatremia is continual and only barely symptomatic, then correction ought to take place gradually. The quantity and price of fluid substitute needed to achieve a sure price of decline in Aoife Garrahy and Christopher Thompson plasma sodium focus may be calculated using the Adrogue-Madias formulation (8). Nevertheless, there are anecdotal reviews of extrapontine myelinolysis related to over-correction of hypernatremia (68). It is tough, however, to make sure that the connection between over-correction of hypernatremia and osmotic demyelination is causal, as demyelination has also been reported in affiliation with hypernatremia itself (69�73). In reality, as many of the instances within the literature are related to a rise, rather than a fall in plasma sodium concentration, the risk of osmotic demyelination might fairly be considered a cause for extra speedy reversal of hypernatremia. More information on the causality of osmotic demyelination is required to be sure. Patients who develop severe hypernatremic dehydration have an elevated hematocrit and are in danger subsequently of thrombotic issues as a end result of the hypercoagulable state. We subsequently recommend the use of prophylactic anticoagulation with low molecular weight heparin in patients with vascular illness, within the elderly and in very severe dehydration. Hypernatremia may impair affected person consciousness and slow down recovery and hospital discharge. Case Study A 64-year-old man was transferred from a common hospital to the endocrine unit. He was handled with aggressive insulin remedy and isotonic fluids, with a fall in blood glucose to eleven mmol/L (200 mg/dL) over 36 hours. Despite switching to isotonic fluids, his plasma sodium concentration rose to 174 mmol/L, related to decreased acutely aware stage, and the affected person was transferred Emergency Management of Acute and Chronic Hypernatremia to the university hospital. Osmotic demyelination syndrome associated to hypernatremia and over-rapid correction of the hyperosmolar state is the prognosis. Management of Chronic Hypernatremia Elderly sufferers in long-term care are at danger of growing chronic hypernatremia, which can worsen during acute illness. Prevention is the key, and the significance of sufficient fluid consumption should be emphasised to carers and nursing staff. All probably work through a mix of reducing glomerular filtration price and interference with the diluting capacity of the distal nephron. Episodes of dehydration are sometimes sophisticated by thrombotic issues, together with pulmonary thromboembolism. Many patients die prematurely, because of postsurgical issues, electrolyte abnormalities or sleep apnea. Formal food regimen and train applications if used erroneously in sufferers with hypovolemic hyponatremia. As clinical evaluation of blood quantity status is troublesome (80), vaptans ought to solely be prescribed by these with experience on this area (28,81). In chronic hypernatremia of any cause, the mainstay of therapy is encouragement of water intake, common measurement of plasma sodium focus, and regular medical or nursing review. It is usually seen in aged sufferers with a comorbid condition which further affects cognition and thirst, and/or insensible fluid losses. However, if the affected person is hemodynamically unstable, isotonic saline ought to be used initially. Symptomatic hypernatremia may be corrected relatively rapidly; the rate of correction can reach a maximum of 1 mmol/L/hr to a most of 10�12 mmol/L/day; the place the development of hypernatremia is understood to have occurred rapidly, over 48 h or much less, quicker charges of correction could also be thought-about with normalization of plasma sodium inside 24 h of graduation of therapy. Chronic hypernatremia should be corrected more steadily as cerebral edema could develop if correction is over-rapid. In patients at threat of thrombotic episodes, prophylactic anticoagulation also needs to be considered. Fluid and electrolyte homeostasis within the aged: physiological modifications of ageing and clinical consequences. Impact of diuretic therapy-associated electrolyte disorders present on admission to the emergency division: a cross-sectional analysis. Acute suppression of plasma vasopressin and thirst after consuming in hypernatremic people. Hypernatraemia due to a reset osmostat for vasopressin launch and thirst, sophisticated by nephrogenic diabetes insipidus. Abnormal plasma sodium concentrations in sufferers handled with desmopressin for cranial diabetes insipidus: outcomes of a long-term retrospective examine. Exaggerated vasopressin secretion and attenuated osmoregulated thirst in human survivors of hyperosmolar coma. Nephrogenic diabetes insipidus: important insights into the molecular background and potential therapies for remedy. Risk components for hypernatremia in sufferers with short- and long-term tolvaptan therapy. The syndrome of inappropriate antidiuretic hormone: present and future management options. Exertional dysnatremia in collapsed marathon runners: a critical role for point-of-care testing to guide appropriate therapy. Tonicity stability in sufferers with hypernatremia acquired in the intensive care unit. Prevalence, danger components and prognosis of hypernatraemia throughout hospitalisation in inner medicine. Normal saline to dilute parenteral medicine and to maintain catheters open is a major and preventable supply of hypernatremia acquired in the intensive care unit. In extreme circumstances, the therapeutic use of somatostatin analogs (octreotide, lanreotide, or pasireotide) delay abdomen emptying and enhance the situation (16,20). This phenomenon can also be associated with a sudden significant improve in incretin activity (21). In some instances, the pancreatic -cell response is exaggerated after bariatric Acute Emergencies Related to Bariatric Surgery surgery, leading to elevated variety of -cells and/or overactive -cell operate in a situation known as nesidioblastosis (21,22). In these instances, patients experience hypoglycemia approximately 1�3 hours following meals, especially after the ingestion of a excessive carbohydrate load. Following either a combined meal test, or oral glucose tolerance take a look at, measured serum insulin and C-peptide levels are inappropriately elevated throughout these hypoglycemic durations. Calciumstimulated selective mesenteric venous sampling can also affirm diffuse hyperactivity of pancreatic -cells on this condition (22). In most cases, strict adherence to a low carbohydrate food plan mitigates the exaggerated insulin response in nesidioblastosis. For refractory cases, the use of -glucosidase inhibitors such as acarbose or miglitol, or calcium channel blockers, can scale back the rate of hypoglycemia (23).
Usage: q._h.
Incidence of hospitalized rhabdomyolysis in patients treated with lipid-lowering drugs menopause 2 periods in one month buy 10 mg female cialis visa. Reference values for 27 clinical chemistry checks in 70-year-old women and men pregnancy levels buy female cialis 10 mg. Myolysis and acute renal failure in a heart-transplant recipient receiving lovastatin [letter] women's health clinic uf female cialis 10 mg cheap without a prescription. Rhabdomyolysis in patients receiving lovastatin after cardiac transplantation [letter] pregnancy signs and symptoms cheap female cialis 20 mg on-line. A multicenter comparison of lovastatin and cholestyramine remedy for extreme primary hypercholesterolemia. Erythromycin and verapamil considerably increase serum simvastatin and simvastatin acid concentrations. Statin-associated muscle signs: impact on statin remedy: European Atherosclerosis Society Consensus Panel Statement on Assessment, Aetiology and Management. What proportion of symptomatic unwanted facet effects in sufferers taking statins are genuinely attributable to the drug Systematic evaluate of randomized placebo-controlled trials to aid particular person patient alternative. Comparative security of atorvastatin eighty mg versus 10 mg derived from evaluation of 49 completed trials in 14,236 sufferers. Intensive lipid reducing with atorvastatin in sufferers with steady coronary illness. Beyond muscle destruction: a systematic review of rhabdomyolysis for scientific practice. Rhabdomyolysis: historic background, clinical, diagnostic and therapeutic options. Acute kidney injury as a result of rhabdomyolysis and renal replacement remedy: a crucial review. Early and vigorous fluid resuscitation prevents acute renal failure in the crush victims of catastrophic earthquakes. Preventing renal failure in patients with rhabdomyolysis: do bicarbonate and mannitol make a difference Interaction between amlodipine and simvastatin in sufferers with hypercholesterolemia and hypertension. A drug can have a minimal of three different names: chemical, generic, and trade; and drugs that have a reliable medical use could additionally be marketed under a selection of commerce names. In this guide, commerce names start with a capital letter, whereas chemical or generic names are in lowercase. The most incessantly used drug in this class is alcohol; the most incessantly used illegal drug is the opiate by-product heroin. Other depressants, all of which have some medical use, include morphine, codeine, methadone, oxycodone, barbiturates, and tranquilizers. These substances could cause bodily and psychological dependence-a craving-and withdrawal leads to bodily and psychological stress. Opiate derivatives (heroin, morphine, and codeine) and opium-like medicine such as methadone and oxycodone are often referred to as narcotics. The most frequently used medicine on this class are caffeine and nicotine; probably the most regularly used illegal stimulant is cocaine that, along with amphetamines, has some limited medical use. The term hallucinogen rather than, for instance, psychoactive or psychedelic, is a value-laden one. There are additionally organic hallucinogens, corresponding to mescaline, which is found in the peyote cactus, and salvia, a mint-family plant native to Mexico. Cannabis reveals a number of the characteristics of hallucinogens, depressants, and even stimulants. Inhalants include a wide selection of available merchandise routinely saved in the residence, corresponding to glue, paint thinner, hair spray, and nail polish remover. There is a growing list of artificial substances-designer drugs-that seemingly mimic the consequences of the principal medication in each of those categories with colorful names similar to "Bath Salts," "Spice," "Dragon Fly," and "EightBallZ. Nicotine is a drug that meets the rigorous criteria for abuse legal responsibility and dependence potential, and "cigarettes are one of many main drugs of addiction within the United States and on the earth and are liable for more premature deaths than all of the other medicine of abuse mixed" (Schuster 1992: 40). Nicotine seems to have a dependence potential at least equal to that of different medication. For example, amongst individuals who experiment with alcohol, 10 to 15 p.c will meet criteria for alcohol dependence sooner or later of their life. Among individuals who experiment with cigarettes, 20 to 30 percent will meet criteria for nicotine dependence of their lifetime (American Psychiatric Association 1995). A 2015 research revealed While statutes distinguish between lawful medicine such as nicotine and alcohol and unlawful medicine similar to heroin and cocaine, biology recognizes no such distinction. Distinctions between alcohol and other psychoactive medication reflect neither actuality nor science (Miller 1995). Indeed, heroin users have usually used marijuana and alcohol while they had been adolescents, and from-heavy-alcohol-use-to-injecting-heroin is a typical sequence for many compulsive drug customers (Inciardi, McBride, and Surratt 1998). The value of alcohol abuse is twice the social cost of all unlawful drug abuse, greater than $200 billion annually because of lost productivity, health care bills, criminal justice costs, and different results corresponding to those associated to fetal alcohol syndrome and related issues. And alcohol disturbs habits in a means that "threatens the safety of others even when used occasionally and not compulsively" (Goldstein 2001: 5). About 80,000 Americans die yearly from alcohol-related causes, with practically two-thirds of these deaths attributable to automotive accidents and homicides and the rest caused by illnesses like cirrhosis. Young people use alcohol more than illegal drugs, and the youthful a person is when alcohol use begins, the higher the risk of creating alcohol abuse or dependence later in life. But alcohol for recreational use is legally manufactured, imported, sold, and possessed. Because of this actuality, whereas it has been associated with a myriad of social problems, because the repeal of Prohibition in 1933 (discussed in Chapter 2), trafficking in alcohol has not been related to rampant violence and corruption. Indeed, the repeal of Prohibition resulted in a dramatic lower within the murder price within the United States. Similarly, as a end result of the that means of the word drug differs so widely in therapeutic and social contexts, the basic public is conditioned to imagine that "street medicine" act according to totally totally different ideas than "medical drugs," alcohol, and nicotine do, with the end result that the risks of the previous are exaggerated and the risks of the latter are underrated (Uelmen and Haddox 1983). In this guide, the term drug will discuss with substances which have mood-altering, psychoactive results. This definition includes caffeine, nicotine, and alcohol, in addition to illegal chemical substances similar to cocaine and heroin. Drug abuse "implies willful, improper use because of an underlying disorder or a quest for hedonistic or immoral pleasure" (Miller 1995: 10). Numerous definitions of drug abuse replicate social values, not scientific perception: "One cause for the prevalence of definitions of drug abuse that are neither logical nor scientific is the strength of Puritan moralism in American tradition which frowns on the pleasure and recreation provided by intoxicants" (Zinberg 1984: 33). Such definitions sometimes discuss with the "use of temper modifying chemical compounds outside of medical supervision, and in a way which is harmful to the individual and the community" (American Social Health Association 1972: 1). Other definitions, such as these supplied by the World Health Organization and the American Medical Association, include references to bodily and/or psychological dependency (Zinberg 1984). The ethical definition is similar, however larger emphasis is placed on the motivation or purpose for which the drug is used. The medical model opposes unsupervised utilization however emphasizes the bodily and mental consequences for the consumer, and the social definition stresses social responsibility and opposed results on others" (Balter 1974: 5; emphasis added). At the far end of the drug use continuum is the compulsive user whose life typically revolves round acquiring, maintaining, and utilizing a provide of medicine. For the compulsive person, failure to ingest an adequate supply of the specified drug results in psychological stress and discomfort, and there can also be physical withdrawal symptoms. Along the continuum is experimental use; socially endorsed use, which includes the use of drugs- wine or peyote, for example-in spiritual ceremonies, weddings, christenings, or at social capabilities such as "cocktail events"; and recreational use. Understanding the use of psychoactive substances as a continuum permits the drug concern to be placed in its proper perspective: There is nothing inherently evil or virtuous about using psychoactive substances. For some-actually many-people, they make life more enjoyable; hence, the widespread use of caffeine, tobacco, and alcohol without severe social problems. In between these two extremes are quite so much of drug users, such because the underage adolescent utilizing tobacco or alcohol on occasion, as is fairly common in our society.
Tags: buy female cialis 10 mg amex, female cialis 10 mg generic overnight delivery, 20 mg female cialis discount visa, female cialis 10 mg cheap free shipping, discount female cialis 10 mg, cheap female cialis 10 mg on line, purchase female cialis 20 mg with visa, female cialis 10 mg generic without a prescription, buy cheap female cialis 10 mg on-line, buy female cialis 10 mg amex, 20 mg female cialis for sale, purchase 20 mg female cialis amex, buy female cialis 20 mg online, female cialis 20 mg with visa, purchase 10 mg female cialis with mastercard, order female cialis 20 mg fast delivery
9 of 10
Votes: 33 votes
Total customer reviews: 33
Customer Reviews
Trompok, 27 years: It must be emphasised that acutely unwell patients in danger for central hypoadrenalism should be presumed to be adrenally insufficient and treated with stress doses of glucocorticoids (preferably after drawing a blood specimen to assay cortisol and corticotropin) with out awaiting the results of diagnostic testing.
Cobryn, 48 years: The incision is continued along the lateral border of the tibialis anterior muscle.
Inog, 58 years: Pheochromocytoma in pregnancy manifesting hypertensive disaster induced by metoclopramide.
Anog, 36 years: In all conditions with a identified thrombotic threat, anticoagulation (usually with subcutaneous heparin) during being pregnant and the post-partum interval must be considered.
