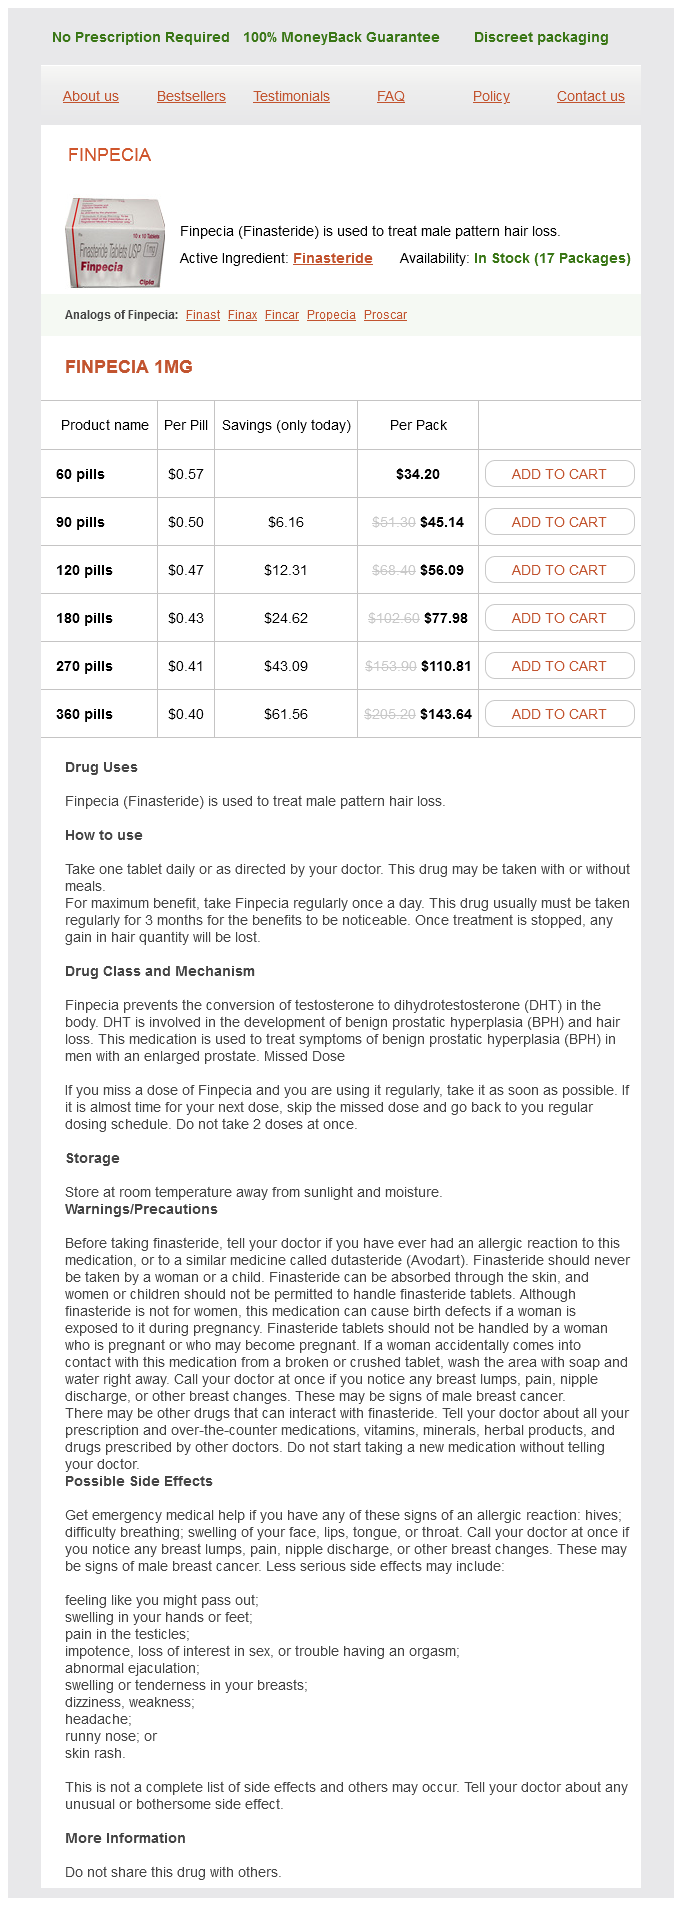
Finpecia 1mg
- 60 pills - $34.20
- 90 pills - $45.14
- 120 pills - $56.09
- 180 pills - $77.98
- 270 pills - $110.81
- 360 pills - $143.64
Finpecia dosages: 1 mg
Finpecia packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 519
Only $0,42 per item
Description
At the highest of the echocardiogram is a still-frame picture of the two-dimensional cross part used to position the Doppler pattern cursor (diagonal white line) hair loss cure endometriosis finpecia 1 mg order amex. Two-dimensional imaging reveals thickened leaflets that dome toward the left ventricle and open poorly hair loss in men red finpecia 1 mg order line. Mathematical calculation from these traces hair loss in men xxxl order finpecia 1 mg overnight delivery, such as strain half time hair loss cure zene finpecia 1 mg buy generic line, are essentially the most exact methods to assess the severity of mitral stenosis; and formulation for these evaluations are built into the software of virtually every ultrasonograph. Pulmonary and tricuspid valve pathologic evaluation are carried out in a style analogous to that described for the aortic and mitral valves (see Tables 46-6 and 46-7). Spontaneous contrast is a swirling, smokelike appearance of 1-to 2-mm densities not attributable to exogenously administered distinction brokers however to the aggregation of pink cells in areas of low circulate. Whenever left atrial enlargement and spontaneous contrast are famous, thrombus in the left atrium and, in particular, the left atrial appendage must be suspected and thoroughly examined. The presence and severity of mitral regurgitation are evaluated from the identical cross sections used for analysis of mitral stenosis and with the same grading technique used for aortic regurgitation (Table 46-7). Mild regurgitation is characterized by a narrow-based, systolic shade jet (<2 mm at its origin within the valve) that occupies less than 25% of the left atrial cross-sectional space and extends less than one half of the gap to the posterior wall of the left atrium. Moderate regurgitation is a broad-based, systolic shade jet (3 to 5 mm at its origin in the valve), occupying less than 50% of the left atrial cross-sectional space and lengthening 50% to 90% of the gap to the posterior wall of the left atrium. After bypass, surgical administration modified in 10 patients including graft analysis or revision and mitral restore (also see Chapter 67). In this study, the deaths of seven sufferers may have been related to the delayed recognition of residual defects. Part 2: mitral and tricuspid regurgitation (native valve disease), Eur J Echocardiogr eleven:307-332, 2010. At the highest of the echocardiogram is a still-frame image of the four-chamber cross part used to position the Doppler cursor. The display (in white) of the instantaneous blood-flow velocities (vertical axis) versus time (horizontal axis) occurring anywhere along that cursor is visualized on the bottom third of the figure. Velocities displayed above the baseline are positive and symbolize circulate towards the transducer. These velocities are attributable to mitral regurgitation and are so high that they exceed the scale used on this instance. Velocities displayed below the baseline are negative and represent circulate away from the transducer. These velocities are attributable to severe mitral stenosis and average approximately 2 m/sec, indicating a gradient across the mitral valve of sixteen mm Hg. This echocardiogram additionally notes how slowly the circulate velocity decreases after the height of the E wave (Slope). The stress half time may be calculated from this slope and is considerably increased in the presence of extreme mitral stenosis. However, large amounts typically opacify the concerned chambers until forming collections. Two honed-down, stop-action, four-chamber transesophageal echocardiograms reveal severe mitral regurgitation. A large color jet (left) depicting turbulent move emanating from the middle of the mitral valve at its coaptation level is revealed. The stop-action echocardiogram (right) reveals another broad-based jet with eccentric path indicating prolapse of the anterior leaflet of the mitral valve. Wall-hugging jets such as this one have a small cross-sectional space as a end result of a lot of their energy is absorbed by the wall of the atrium. At the top of the echocardiogram is a still-frame picture of the two-dimensional cross section used to position the Doppler sampling quantity (broken white circle). The show of the instantaneous blood-flow velocities (vertical axis) versus time (horizontal axis) occurring within the left higher pulmonary vein is visualized on the bottom third of the figure. Velocities displayed above the baseline are constructive and represent move towards the transducer (in this case, into the left atrium). Velocities displayed under the baseline are negative and represent circulate away from the transducer (in this case, into the left upper pulmonary vein). The role of imaging has developed from complex cardiac evaluation to direct process guidance. Currently, digital recording of particular person cardiac cycles or multiple cycles is the usual. The resulting loops are transported through hospital networks or the Internet to safe servers where the studies can be rapidly retrieved. The apply experience pathway is the one most probably to apply to most anesthesiologists. In actuality, most anesthesiologists apply someplace between the essential and advanced ranges. Practice tips for perioperative transesophageal echocardiography: a report by the American Society of Anesthesiologists and the Society of Cardiovascular Anesthesiologists Task Force on Transesophageal Echocardiography, Anesthesiology eighty four:986, 1996. Practice tips for perioperative transesophageal echocardiography: an up to date report by the American Society of Anesthesiologists and the Society of Cardiovascular Anesthesiologists Task Force on Transesophageal Echocardiography, Anesthesiology 112:1084, 2010. Matsumoto M, Oka Y, Strom J, et al: Application of transesophageal echocardiography to continuous intraoperative monitoring of left ventricular performance, Am J Cardiol forty six:95-105, 1980. Practice guidelines for perioperative transesophageal echocardiography: a report by the American Society of Anesthesiologists and the Society of Cardiovascular Anesthesiologists Task Force on Transesophageal Echocardiography, Anesthesiology eighty four:986-1006, 1996. Practice guidelines for perioperative transesophageal echocardiography: an updated report by the American Society of Anesthesiologists and the Society of Cardiovascular Anesthesiologists Task Force on Transesophageal Echocardiography, Anesthesiology 112:1084-1096, 2010. A Report of the American College of Cardiology Foundation Appropriate Use Criteria Task Force, American Society of Echocardiography, American Heart Association, American Society of Nuclear Cardiology, Heart Failure Society of America, Heart Rhythm Society, Society for Cardiovascular Angiography and Interventions, Society of Critical Care Medicine, Society of Cardiovascular Computed Tomography, and Society for Cardiovascular Magnetic Resonance Endorsed by the American College of Chest Physicians, J Am Coll Cardiol 57: 1126-1166, 2011. Ballo P, Bandini F, Capecchi I, et al: Application of 2011 American College of Cardiology Foundation/American Society of Echocardiography appropriateness use standards in hospitalized patients referred for transthoracic echocardiography in a group setting, J Am Soc Echocardiogr 25:589-598, 2012. Hatle L, Brubakk A, Tromsdal A, et al: Noninvasive evaluation of pressure drop in mitral stenosis by Doppler ultrasound, Br Heart J 40:131-140, 1978. Holen J, Simonsen S: Determination of stress gradient in mitral stenosis with Doppler echocardiography, Br Heart J 41:529-535, 1979. Mishiro Y, Oki T, Yamada H, et al: Evaluation of left ventricular contraction abnormalities in sufferers with dilated cardiomyopathy with using pulsed tissue Doppler imaging, J Am Soc Echocardiogr 12:913-920, 1999. Yamada H, Oki T, Mishiro Y, et al: Effect of aging on diastolic left ventricular myocardial velocities measured by pulsed tissue Doppler imaging in healthy subjects, J Am Soc Echocardiogr 12: 574-581, 1999. Comparison with sonomicrometry and pressure-volume relations, Circulation ninety five:2423-2433, 1997. Alam M, Wardell J, Andersson E, et al: Effects of first myocardial infarction on left ventricular systolic and diastolic perform with using mitral annular velocity decided by pulsed wave doppler tissue imaging, J Am Soc Echocardiogr 13:343-352, 2000. Ama R, Segers P, Roosens C, et al: the effects of load on systolic mitral annular velocity by tissue Doppler imaging, Anesth Analg ninety nine:332-338, 2004. Mentec H, Vignon P, Terre S, et al: Frequency of bacteremia related to transesophageal echocardiography in intensive care unit patients: a potential research of 139 sufferers, Crit Care Med 23:1194-1199, 1995. Mahmood F, Jainandunsing J, Matyal R: A practical approach to echocardiographic evaluation of perioperative diastolic dysfunction, J Cardiothorac Vasc Anesth 26:1115-1123, 2012. Comparison with hemodynamic parameters, J Thorac Cardiovasc Surg 104:321-326, 1992. Cicek S, Demirilic U, Kuralay E, et al: Transesophageal echocardiography in cardiac surgical emergencies, J Card Surg 10:236-244, 1995. A correlative preoperative hemodynamic, electrocardiographic, and transesophageal echocardiographic study, Circulation 81:865-871, 1990. Optimal dose and accuracy in predicting recovery of ventricular operate after coronary angioplasty [see comments], Circulation ninety one:663-670, 1995. Cowie B: Focused cardiovascular ultrasound performed by anesthesiologists in the perioperative period: feasible and alters patient administration, J Cardiothorac Vasc Anesth 23:450-456, 2009. Nomura M, Hillel Z, Shih H, et al: the affiliation between Doppler transmitral flow variables measured by transesophageal echocardiography and pulmonary capillary wedge strain, Anesth Analg eighty four:491-496, 1997. Balik M, Pachl J, Hendl J, et al: Effect of the degree of tricuspid regurgitation on cardiac output measurements by thermodilution, Intensive Care Med 28:1117-1121, 2002. A report of the American College of Cardiology Foundation/American Heart Association Task Force on Practice Guidelines, American Association for Thoracic Surgery, American College of Radiology, American Stroke Association, Society of Cardiovascular Anesthesiologists, Society for Cardiovascular Angiography and Interventions, Society of Interventional Radiology, Society of Thoracic Surgeons, and Society for Vascular Medicine, Catheter Cardiovasc Interv seventy six:E43-E86, 2010. Mishra M, Malhotra R, Karlekar A, et al: Propensity case-matched analysis of off-pump versus on-pump coronary artery bypass grafting in patients with atheromatous aorta, Ann Thorac Surg eighty two:608-614, 2006. Agricola E, Oppizzi M, Maisano F, et al: Detection of mechanisms of quick failure by transesophageal echocardiography in quadrangular resection mitral valve restore technique for extreme mitral regurgitation, Am J Cardiol ninety one:175-179, 2003.
Larkspur (Delphinium). Finpecia.
- Worm infestations, water retention, sleeplessness (insomnia), and lack of appetite.
- Are there safety concerns?
- How does Delphinium work?
- Dosing considerations for Delphinium.
- What is Delphinium?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96435
Side Effects and Complications At the conventional level (C6) of blockade hair loss cure new 1 mg finpecia buy free shipping, ipsilateral phrenic nerve block leading to diaphragmatic paresis happens in 100% of sufferers undergoing interscalene blockade hair loss in men x-ray finpecia 1 mg fast delivery,17 even with dilute options of local anesthetics hair loss regrowth generic 1 mg finpecia with visa, and is related to a 25% reduction in pulmonary operate hair loss in men at 20 1 mg finpecia buy with amex. Although rare, respiratory compromise can happen in sufferers with extreme respiratory illness. Techniques to decrease blockade of the phrenic nerve embrace utilizing very small volumes of local anesthetic and localizing the brachial plexus at a decrease stage within the neck. The danger of pneumothorax is small when the needle is accurately placed on the C5 or C6 stage because of the distance from the dome of the pleura. The cause is presumed to be stimulation of intracardiac mechanoreceptors by decreased venous return, producing an abrupt withdrawal of sympathetic tone and enhanced parasympathetic output. The frequency is decreased when prophylactic -adrenergic blockers are administered. The needle is systematically walked anteriorly and posteriorly along the rib until the plexus is positioned. Some surgical approaches to the shoulder, similar to total shoulder arthroplasty, are associated with neurologic threat to the brachial plexus. In such cases, an interscalene block could be positioned postoperatively after the surgical service has ascertained and documented that no neurologic harm has occurred. Epidural and intrathecal injections can happen with this block, a finding emphasizing the importance of inserting the needle in a caudad direction. At this level, the brachial plexus is compact, and a small volume of local anesthetic produces rapid onset of dependable blockade of the brachial plexus. Several anatomic factors are necessary in the performance of the supraclavicular method. The three trunks are clustered vertically over the primary rib cephaloposterior to the subclavian artery, which may typically be palpated in a slender, relaxed patient. The patient is placed in a supine place, with the top turned away from the side to be blocked. The arm to be anesthetized must be adducted, and the hand should be prolonged alongside the facet. In the basic technique, the midpoint of the clavicle ought to be recognized and marked. The posterior border of the sternocleidomastoid could be easily palpated when the affected person raises the top barely. The palpating fingers can then roll over the stomach of the anterior scalene muscle into the interscalene groove, where a mark should be made approximately 1. A 22-gauge, 4-cm needle is directed in a caudad, slightly medial, and posterior course until a paresthesia or motor response is elicited or the primary rib is encountered. If the first rib is encountered with out elicitation of a paresthesia, the needle could be systematically walked anteriorly and posteriorly along the rib till the plexus or the subclavian artery is situated. The needle can be withdrawn and reinserted in a extra posterolateral direction that usually leads to a paresthesia or motor response. After localization of the brachial plexus, aspiration for blood must be performed before incremental injections of a complete quantity of 20 to 30 mL of native anesthetic. The use of ultrasound for the supraclavicular block allows the practitioner to see the brachial plexus buildings, in addition to the subclavian artery and pleura, slightly below the primary rib. The inherent security of this method requires steady visualization of the needle tip throughout needle advancement (see Chapter 58). Ultrasound steering is incessantly used to visualize the neurovascular bundle and ideally, local anesthetic unfold must be visualized around the axillary artery (see Chapter 58). Side Effects and Complications Because of the blind strategy to the plexus, the chance of intravascular injection could also be elevated. Side Effects and Complications Although the block is harder in obese sufferers (see Chapter 71), an increased threat of issues has not been documented. Importantly, although the use of ultrasound has perhaps decreased the incidence of pneumothorax, the chance has not been eliminated. The presence of phrenic or cervical sympathetic nerve block usually requires only reassurance. However, axillary block is unsuitable for surgical procedures on the higher arm or shoulder, and the patient should have the flexibility to abduct the arm to carry out the block. Anatomic ideas that should be thought-about earlier than an axillary block embrace the following: 1. Although anatomic variations exist, sometimes, the median nerve is discovered superior to the artery, the ulnar nerve is inferior, and the radial nerve is posterior and considerably lateral. At this level, the musculocutaneous nerve has already left the sheath and lies with the coracobrachialis muscle. The intercostobrachial nerve, a branch of the T2 intercostal nerve, is usually blocked by the pores and skin wheal overlying the artery; nevertheless, sufficient anesthesia for the tourniquet may be ensured by extending the wheal 1 to 2 cm caudad and cephalad. Blockade occurs on the degree of the cords and presents the theoretical advantages of avoiding pneumothorax while affording block of the musculocutaneous and axillary nerves. The needle is inserted 2 cm beneath the midpoint of the inferior clavicular border and is superior laterally, using a nerve stimulator to establish the plexus. An incremental injection of 20 to 30 mL of answer is sufficient after the needle is correctly positioned. The affected person ought to be within the supine position with the arm to be blocked placed at a right angle to the physique and the elbow flexed to 90 levels. The axillary artery is palpated, and a line is drawn tracing its course from the lower axilla as far proximally as attainable. Distal digital pressure is maintained throughout needle placement and injection of the native anesthetic. Proximal needle placement and upkeep of distal pressure facilitate proximal spread of the solution. Several strategies of figuring out the axillary sheath have been described, all with reportedly good outcomes. Overall, paresthesias are pointless; nonetheless, a number of injections can shorten the onset and improve the reliability of blockade. Smaller needles and a brief needle bevel may be related to a much less frequent risk of nerve injury. A nerve stimulator may also be used with an insulated needle to locate the nerves. A short-bevel needle could be advanced until the axillary sheath is entered, as evidenced by a fascial click on, whereupon 40 to 50 mL of solution is injected after unfavorable aspiration. A transarterial technique can be used, whereby the needle pierces the artery and 40 to 50 mL of solution is injected posterior to the artery. Alternatively, half of the solution is injected posterior and half is injected anterior to the artery. Great care have to be taken to keep away from intravascular injection with this system, particularly because the pressure of injection throughout the compartments of the axillary sheath may move anatomic structures in relation to the immobile needle. Ultrasound guidance with visualization of native anesthetic unfold around the four nerves (with and with out motor stimulation) decreases block onset time and may scale back the variety of needle redirections; nonetheless, the charges of success and problems are much like other approaches. However, sustaining the arm in abduction decreases onset time and prolongs each sensory and motor block. Success Rate With Axillary Block Techniques the success rate for an axillary block depends on the definition of a successful block. Although Partridge and coworkers40 confirmed the presence of those compartments, they concluded that the "septa" dividing them were incomplete based on injections of methylene blue and latex solutions into cadavers. The controversy surrounding single- versus multiple-injection methods remains unresolved. Eliciting a paresthesia is as efficacious as peripheral nerve stimulation (with a motor response of zero. Most research suggest that two-injection transarterial methods are equivalent to single-paresthesia or single-nerve stimulation approaches. In basic, the efficacy of paresthesia and peripheral nerve stimulator techniques increases when multiple injections are used. Conversely, success rates with perivascular or fascial click approaches are variously dependable. At this degree, the median and ulnar nerves are located on the lateral and medial features of the brachial artery, respectively. The musculocutaneous nerve is recognized throughout the body of the biceps muscle, and the radial nerve lies adjoining to the humerus. A volume of 8 to 10 mL of native anesthetic is injected after localization of each nerve with a nerve stimulator (or ultrasound).
Specifications/Details
Long-term alcohol abuse might manifest with bodily findings of persistent liver disease hair loss 8 weeks pregnant order finpecia 1 mg with mastercard. In addition to identifying the presence of substance abuse and its associated issues hair loss cure cotsarelis finpecia 1 mg cheap with mastercard, clinicians ought to ascertain whether or not hair loss treatments finpecia 1 mg buy amex, and for how lengthy hair loss cure4you generic finpecia 1 mg mastercard, sufferers can stop consuming alcohol or addictive drugs. When an alcoholic patient reviews previously interrupting ingesting for a number of days, the interviewer ought to inquire whether or not agitation, seizures, delirium tremens, or other indicators of withdrawal developed. Ideally, sufferers with drug or alcohol dependence ought to be drug free properly before elective surgical procedures. For instance, benzodiazepines can be helpful in stopping or treating alcohol withdrawal signs. Some drugs used to manage withdrawal or facilitate restoration have particular perioperative concerns. For sufferers taking naltrexone for a history of alcohol abuse, consideration must be given to discontinuing it three days preoperatively. If medications wanted to manage restoration from addiction are discontinued preoperatively, patients could require substitution with alternative medicines that could be continued perioperatively. For elective surgical circumstances, women must be suggested to pump and retailer milk preoperatively; this milk can be used in the first 24 hours after administration of an anesthetic or during breast milk publicity to probably dangerous brokers. The mother should discard milk produced throughout the first 24 hours after anesthesia and will typically resume breastfeeding after this era. Very young or untimely babies, especially those at risk for apnea, could have issues if the mom continues to take opioid or sedating medication. This approach is problematic in the perioperative interval as a outcome of much of anesthesia care involves such procedures. Such insurance policies, if they exist, must be reviewed and revised, as needed, to reflect the content material of these guidelines. For example, some sufferers may want full resuscitation procedures to be used to manage adverse medical occasions that are believed to be quickly and simply reversible but to refrain from remedy for situations that are prone to lead to everlasting sequelae, similar to neurologic impairment or undesirable dependence on lifesustaining know-how. Modified from Committee on Ethics, American Society of Anesthesiologists: Ethical pointers for the anesthesia care of patients with do-not-resuscitate orders or other directives that limit therapy, 2013. Unnecessary testing is inefficient and costly, and it entails additional technical sources. In addition, it might lead to pricey evaluation of borderline or false-positive check abnormalities. Aside from doubtlessly inflicting working room delays or cancellations, these pointless follow-up exams could pose risks to sufferers which might be attributable to each the checks and any associated interventions. Therefore, the targeting of testing in acceptable patients has both clinical and economic advantages. At many hospitals the place surgeons and primary care physicians order all preoperative exams, the common follow has been to order exams with none diagnostic focus, apart from speculation that the anesthesiologist could "require them" for surgery to proceed without delay or cancellation. Other justifications provided for this nonselective ordering of checks embody routine screening for disease states, establishment of a diagnostic baseline, personal habit. Indeed, Medicare and most non-public insurance carriers not reimburse routine preoperative screening exams with out specific indications. Testing ought to be focused to detecting specific medical indications which will improve perioperative danger. Indeed, anesthesiologist-led preoperative analysis has been proven to result in extra selective ordering of laboratory tests than evaluation led by surgeons or main care physicians. Chapter 38: Preoperative Evaluation 1143 testing should be "based on information obtained from medical information, affected person interview, bodily examination, and kind and invasiveness of the planned process. Clinical indications relate to the date of the final menstrual interval, sexual activity, use (and type) of birth control, and affected person or physician intuition. Primary medical indications embody a history of elevated bleeding, hematologic issues, renal illness, current chemotherapy or radiation therapy, corticosteroid or anticoagulant remedy, poor nutritional status, surgical procedures with anticipated high blood loss, and trauma. Consideration must be given to providing the sickle cell test to previously untested patients from at-risk ethnic teams. Given the very low yield of routine testing in these at-risk populations,243 testing also needs to be guided by other factors. The check must be accompanied by pretest and posttest counseling, so that patients are aware of the implications of each optimistic and negative check outcomes for themselves and relations. Primary scientific indications include diabetes, hypertension, cardiac illness, potential dehydration. Primary clinical indications embody a historical past of hepatitis (viral, alcohol, drug-induced, autoimmune), jaundice, cirrhosis, portal hypertension, biliary or gallbladder illness, hepatotoxic drug publicity, tumor involvement of the liver, and bleeding issues. A careful historical past and bodily examination provide steerage on whether coagulation testing is indicated. Primary clinical indications embrace a identified bleeding disorder, earlier excessive intraoperative surgical bleeding, hepatic illness, poor nutritional standing, and use of anticoagulants or different medication that affect coagulation. For example, these danger assessments can help identify people who warrant doubtlessly beneficial interventions, enhanced levels of postoperative monitoring, or consideration for various nonoperative therapy for his or her underlying situation. For example, ambulatory surgical procedures are very secure with respect to dangers of postoperative mortality and major antagonistic occasions,255-257 as evidenced by a 7-day postoperative mortality price of solely forty one per one hundred,000 procedures in a large cohort of Medicare beneficiaries sixty five years old or older. The inherent importance of operative threat additionally explains why specialty society practice guidelines advocate that, in the absence of an unstable cardiac situation, sufferers can proceed on to elective low-risk ambulatory surgical procedures with none further preoperative cardiac workup. Large multinational potential epidemiologic research of surgical sufferers, which included accurate seize of perioperative characteristics and outcomes,39,249 will doubtless assist lead to the event of similar indices for noncardiac surgery. Resting echocardiography can present data associated to valvular lesions, pulmonary hypertension, mounted wall movement abnormalities, and ventricular perform. Especially in circumstances of a suspicious murmur or different scientific indication, a preoperative echocardiogram might help diagnose prognostically essential valvular or other cardiac lesions, such as aortic stenosis or pulmonary hypertension. These exams do have an established and essential function for assessing perioperative danger in Characteristic Age 45-64 yr 76-74 yr 75 yr or older Urgent or Emergency Surgery Operative Procedure Major intraabdominal or head and neck surgical procedure Craniotomy or multilevel spine surgical procedure Major vascular surgical procedure Comorbid Disease High-risk coronary artery illness in earlier 6 months* History of congestive coronary heart failure History of stroke History of peripheral arterial disease Chronic obstructive pulmonary disease Active most cancers 1. Defined as active therapy (chemotherapy, radiation or surgery) for most cancers within 6 months before surgical procedure, recognized metastatic disease, or deliberate surgical procedure for most cancers. Indeed, practice guidelines from the American College of Physicians suggest in opposition to routine preoperative spirometry for predicting risks for pulmonary complications of noncardiothoracic surgical procedures. Some drugs have beneficial effects throughout surgical procedures, whereas others may be detrimental. Although issues pertaining to many of these medicine are coated in other sections of this chapter. Continuation of those brokers up to the morning of surgery can result in increased dangers for intraoperative hypotension,45 especially in individuals receiving concomitant diuretic remedy. Thus, the potential for intraoperative hypotension have to be balanced towards potential benefits of continuing these brokers as a lot as the time of the surgical process. Diuretics are typically discontinued preoperatively, excluding thiazide diuretics. Loop diuretics, which can cause volume depletion and hypokalemia, have typically been discontinued on the day of surgical procedure. Nonetheless, a randomized trial discovered no increased threat of intraoperative hypotension when loop diuretics have been continued, versus withdrawn, on the day of surgery. Patients with coronary heart disease or related cardiovascular risk components could additionally be taking a variety of medicines, similar to -blockers, statins, digoxin, and antiarrhythmic medications. These agents are usually continued up till the time of the surgical procedure because of their useful effects and the potential for adverse penalties if discontinued. The perioperative use of those drugs is mentioned intimately within the part of this chapter on cardiovascular disease. The only exception is a randomized trial of valdecoxib (now withdrawn from the market) in cardiac surgical procedure in which the drug caused an excess of cardiac events. The exception to this rule pertains to diabetic sufferers with steady subcutaneous insulin infusion pumps. Such people should as an alternative continue their infusion on the lowest basal price, which is often the nighttime fasting price. On the day of surgery, sufferers with type 1 diabetes typically have to take a small amount (one third to one half) of their traditional morning dose of intermediate-acting or long-acting insulin. Patients with sort 2 diabetes can both take no insulin or up to one half of their ordinary dose of intermediate-acting, long-acting, or combination. No knowledge help such a suggestion, and routine discontinuation earlier than the day of surgery might increase the danger of poor perioperative Chapter 38: Preoperative Evaluation 1147 glycemic control. Conversely, a very low threat of lactic acidosis exists in patients who then go on to develop renal and hepatic failure whereas taking metformin. Thus, withholding metformin before the day of surgery may be thought-about if the anticipated procedure poses a high risk of acute kidney or liver injury. In addition, metformin ought to likely not be restarted in sufferers postoperatively until any essential threat of hepatic or renal failure has handed.
Syndromes
- Norethindrone
- When it was swallowed or inhaled
- Infection
- Headaches
- Wearing away of the vertebrae
- Prominent lips with an open mouth
Related Products
Additional information:
This core-to-peripheral tissue temperature gradient is normally maintained by tonic thermoregulatory vasoconstriction hair loss malaria medication generic 1 mg finpecia with visa. Following initial redistribution hypothermia hair loss medication wiki finpecia 1 mg generic with amex, core temperature often decreases in a gradual hair loss young living oils buy 1 mg finpecia amex, linear fashion for 2 to 4 hours hair loss 101 promo codes discount 1 mg finpecia. This reduction results simply from heat loss exceeding metabolic heat production,sixty two and the speed at which core temperature decreases is determined by the distinction and size of the patient. After three to four hours of anesthesia, core temperature normally reaches a plateau and remains nearly constant during surgical procedure. Furthermore, neither adults46 nor infants48 seem capable of enhance intraoperative warmth manufacturing in response to hypothermia. An extra mechanism must therefore contribute to the core temperature plateau. Evidence suggests that a primary issue is constraint of metabolic heat to the core thermal compartment. In this example, distribution of metabolic warmth (which largely is produced centrally) is restricted to the core compartment, thus sustaining its temperature. Spinal anesthesia elevated the sweating threshold but reduced the thresholds for vasoconstriction and shivering. The vasoconstriction-to-shivering vary, however, remained normal throughout spinal anesthesia. Changes in body heat content and distribution of heat inside the physique during induction of general anesthesia (at elapsed time zero). The change in mean body temperature was subtracted from the change in core (tympanic membrane) temperature, thereby leaving the core hypothermia specifically ensuing from redistribution. Furthermore, lidocaine administered intravenously in doses producing plasma concentrations much like those occurring throughout epidural anesthesia has no thermoregulatory effect. The mechanism by which peripheral administration of native anesthesia impairs centrally mediated thermoregulation could involve alteration of afferent thermal enter from the legs. The key factor here is that tonic chilly indicators dominate thermal input at leg skin temperatures in typical working room environments. However, epidural anesthesia also reduces the achieve of shivering, a finding that implies that the regulatory system is unable to compensate for decrease physique paralysis. Neuraxial anesthesia is incessantly supplemented with sedative and analgesic drugs. The variety of dermatomes blocked (sacral segments = 5; lumbar segments = 5; thoracic segments = 12) versus reduction within the shivering threshold (difference between the control shivering threshold and spinal shivering threshold). The shivering threshold was decreased extra by in depth spinal blocks than by less in depth ones (threshold = 0. During regional anesthesia, core hypothermia is accompanied by an actual enhance in skin temperature. The end result usually is a perception of continued or increased warmth accompanied by autonomic thermoregulatory responses together with shivering. Because core temperature monitoring remains rare throughout regional anesthesia, substantial hypothermia usually goes undetected in these patients. However, vasodilation induced by regional anesthesia solely slightly will increase cutaneous heat loss. Furthermore, metabolic heat production remains constant or increases due to shivering thermogenesis. This rapid lower in core temperature, just like the one which follows induction of general anesthesia, also outcomes from an inner core-to-peripheral redistribution of body heat. Systemic oxygen consumption (V o2) without (circles) and with (squares) epidural anesthesia. The horizontal normal deviation bars indicate variability within the thresholds among the many volunteers; although errors bars are proven solely as soon as in every collection, the identical temperature variability applies to every information point. The slopes of the V o2 versus core temperature relationships (solid lines) were decided using linear regression. Not only is the vasoconstriction threshold centrally impaired by regional anesthesia,sixty six,sixty seven however more importantly, vasoconstriction in the legs is instantly prevented by nerve block. The importance of intraoperative leg vasoconstriction is illustrated during mixed regional and general anesthesia. Consistent with the impairment of thermoregulatory responses with regional anesthesia alone,66,sixty seven vasoconstriction throughout combined regional and general anesthesia is triggered at a core temperature roughly 1� C less than throughout general anesthesia alone. Furthermore, vasoconstriction, once triggered, produces a core temperature plateau throughout basic anesthesia alone but not during mixed regional and common anesthesia. Pain was assessed postoperatively by an investigator blinded to the group task. Patients receiving a neighborhood anesthetic block (lidocaine) had considerably much less postoperative ache than did those given saline; all values after 10 elapsed minutes differed considerably in the two groups. Shivering-like tremor was observed in 43% extra of the patients given saline than those given lidocaine, a finding indicating that the tremor is said to ache. Experimental stimulation of those receptors reliably produces shivering in animals. Stimulation in people of those putative receptors by epidural anesthetic injection theoretically could provoke thermoregulatory responses, including shivering. The risk of shivering during neuraxial anesthesia is markedly diminished by sustaining strict normothermia. Shivering throughout neuraxial anesthesia can generally be handled by warming sentient pores and skin. This strategy augments cutaneous thermal input to the central regulatory system and thus increases the diploma of tolerated core hypothermia. Thermal administration thus deserves the identical thoughtful analysis of potential dangers and advantages as different therapeutic selections. However, the efficacy of delicate hypothermia far exceeds that of remedies similar to high-dose isoflurane or barbiturate coma, which comparably reduce the metabolic rate. As could possibly be anticipated from in vitro and animal research, therapeutic hypothermia has twice been shown to enhance outcomes from out-of-hospital cardiac arrest. The different state of affairs during which therapeutic hypothermia seems helpful is in asphyxiated neonates. The problem is that few outcome information can be found to substantiate extrapolation from animal knowledge to clinical practice. Furthermore, the appropriate target temperature for therapeutic hypothermia has yet to be established. The Heart and Other Organs Hypothermic protection against ischemia may prolong to different organs. For instance, mild hypothermia markedly reduced infarct dimension in experimental acute myocardial infarction in human-sized pigs,111 and a preliminary study in sufferers was encouraging. Acute malignant hyperthermia is harder to trigger in mildly hypothermic swine than in those stored normothermic. Limitations of most therapeutic hypothermia research are that cooling started nicely after the ischemic insult, and patients usually took many hours to cool. It thus remains possible that profit will but be recognized in future studies that initiate hypothermia earlier and use extra just lately developed systems to cool patients quicker. Table 54-1 lists selected major studies that evaluated the potential advantages of mild perioperative hypothermia. The Brain Hypothermia for brain trauma was initially claimed to be therapeutic based mostly on a publish hoc subgroup evaluation of a examine that general showed no benefit. For the results of delicate hypothermia on neonatal asphyxia, see the Cochrane meta-analysis by Jacobs and associates. The most essential factor seems to be a cold-induced defect in platelet operate. Perhaps as importantly, hypothermia directly impairs enzymes of the coagulation cascade. When these checks are performed at hypothermic temperatures, nonetheless, the defect becomes obvious. Treatment effect expressed as ratio of geometric means of blood loss for normothermic (N) versus hypothermic (H) sufferers.
Usage: q.d.
Confirmation of the situation of the wire should all the time precede using the vessel dilator hair loss cure march 2013 buy finpecia 1 mg fast delivery. Ideally hair loss cure exfoliating finpecia 1 mg buy cheap, a protocol or guidelines describing the essential procedural steps for central line insertion should be in place at each institution hair loss 8 months after giving birth finpecia 1 mg discount free shipping, and all employees members should feel empowered to converse up after they witness a protocol violation hair loss in men due to stress buy cheap finpecia 1 mg on line. Standardized equipment, routine use of an assistant, hand washing and maximal barrier precautions all contribute to the sterility of the procedure. Pressure manometry or waveform measurement should be used to verify venous placement of the catheter earlier than use. Finally, the place of the catheter tip must be verified as quickly as clinically applicable to keep away from delayed issues (see later). Ultrasound-Guided Central Venous Cannulation First described in 1984, ultrasound-guided central venous catheter placement has proved helpful in most settings, including the intensive care unit and the working room156,158 (also see Chapter 58). Fewer needle passes are required for profitable venous cannulation when realtime two-dimensional ultrasound steering is used. In addition, ultrasound steering reduces the time required for catheterization, will increase total success rates, and ends in fewer quick issues. Based on this proof, the Agency for Healthcare Research and Quality has listed using realtime ultrasound guidance for central venous catheterization as considered one of 11 practices to enhance well being care. As a substitute for real-time ultrasound-guided catheterization, ultrasound can be used to confirm vessel location and patency, provide a transparent goal to mark the pores and skin, after which enable venipuncture to proceed within the ordinary fashion. A rapid ultrasound scan should be performed once the affected person is positioned in the Trendelenburg place and before the pores and skin is cleansed to determine the goal vein location, verify its patency, and rule out anatomic abnormalities. This easy step is aimed toward avoiding futile insertion makes an attempt when the affected person has a thrombosed, narrowed, or anomalous central vein. Once the location is prepped and draped, the operator holds the ultrasound probe protected by a sterile sheath with the nondominant hand to get hold of a view of the target vessel. The vein and artery seem as two round black buildings on the ultrasound picture. The artery appears mildly pulsatile, is mostly smaller, and has a thicker wall. When using ultrasound steering, either the transverse (short axis) or longitudinal (long axis) view is enough. In common, the transverse view is simpler to study and allows simultaneous identification of the artery and vein, whereas the longitudinal view permits visualization of the needle tip always, which may reduce perforation of the posterior wall of the vein. An extra recommended security stop is to confirm intravenous location of the guidewire earlier than continuing with vessel dilation. When using ultrasound to information subclavian vein cannulation, the transducer is placed within the infraclavicular groove at the level of the middle or lateral third of the clavicle and the axillary vein and artery are imaged as they exit the bony canal fashioned by the clavicle and the primary rib. Either a transverse or longitudinal view could be obtained and used to guide needle insertion. Before monitoring or infusion commences, aspiration of blood should confirm intravenous location of each lumen of a multilumen catheter and remove any residual air from the catheter-tubing system. Following surgical procedure, however, the position of the catheter tip have to be confirmed radiographically. Catheter suggestions positioned throughout the coronary heart or under the pericardial reflection of the superior vena cava increase the danger of cardiac perforation and fatal cardiac tamponade. Ideally, the catheter tip ought to lie inside the superior vena cava, parallel to the vessel partitions, and be positioned under the inferior border of the clavicles and above the extent of the third rib, the T4 to T5 interspace, the azygos vein, the tracheal carina, or the takeoff of the proper mainstem bronchus. Complications are often divided into mechanical, thromboembolic, and infectious etiologies (Box 45-5). Large retrospective and observational research present one of the best estimates of incidence for most of these problems. Vascular accidents from central venous catheterization have a spread of medical penalties. The most typical minor problems are localized hematoma or harm to the venous valves. When unintentional carotid artery cannulation with a dilator or large-bore catheter occurs, the dilator or catheter ought to be left in place and a vascular surgeon consulted promptly concerning elimination. Immediate removing of the catheter has resulted in extreme complications such as hemothorax, arteriovenous fistula, pseudoaneurysm, and cerebral infarction. A variety of these have been described in the literature, together with aortoatrial fistula, venobronchial fistula, carotid artery�internal jugular vein fistula, and pseudoaneurysm formation. These vascular accidents may trigger hemopericardium or unintentional pericardial instillation of intravenous fluid resulting in cardiac compression. Most reports doc the avoidable nature of this catastrophic occasion and spotlight that patients are predisposed to this complication when central venous catheter ideas are malpositioned within the coronary heart chambers or abutting the wall of the superior vena cava at a steep angle. This latter place could be recognized radiographically as a delicate curvature of the catheter tip throughout the superior vena cava. In truth, many early reports of catheter-related cardiovascular perforation advised that peripheral catheters could current an unusually high threat for this complication as a result of arm abduction might cause the catheter tip to advance into a dangerous location inside the heart. Cardiac arrhythmias could provide an early clue to the intracardiac location of the catheter tip. Small pneumothoraces may be managed conservatively, whereas tube thoracostomy is one of the best therapy for larger air collections or for sufferers receiving positive-pressure mechanical ventilation or scheduled for main surgery. The doctor should all the time be ready for the possibility of tension pneumothorax and its adverse hemodynamic sequelae. In addition to pneumothorax, different respiratory tract accidents happen following central venous catheterization, including subcutaneous and mediastinal emphysema, tracheal perforation, and rupture of an endotracheal tube cuff. Damage might occur to the brachial plexus, stellate ganglion, phrenic nerve, or vocal cords. Infectious Complications of Central Venous Catheterization By far, the most typical main late complication of central venous cannulation is an infection. As beforehand famous, the place to begin for prevention of infection is meticulous consideration to aseptic method. Furthermore, catheters of the same materials may be manufactured differently, which influences their surfaces and the frequency of bacterial adherence to the surface. All physicians performing these procedures must be conversant in them, particularly since many of those issues are related to operator error. Not solely could air be entrained throughout initial cannulation, but improperly related large-bore cannulas might pose an additional danger because of the big site for air entry instantly into the central venous circulation. A similar phenomenon has been repeatedly demonstrated for pulmonary artery catheter monitoring (see discussion later). Atrial contraction increases atrial stress and offers the atrial kick to fill the proper ventricle via the open tricuspid valve. This wave is a transient enhance in atrial strain produced by isovolumic ventricular contraction, which closes the tricuspid valve and displaces it toward the atrium. Note that the c wave noticed in a jugular venous stress trace might have a barely extra complex origin. This wave is due to early systolic strain transmission from the adjoining carotid artery and may be termed a carotid impact wave. Central venous stress monitoring is the least invasive methodology, adopted by pulmonary artery and left atrial stress monitoring. Proper interpretation of all cardiac filling pressures requires data of normal values for pressures inside the cardiac chambers, nice vessels, and different measured and derived hemodynamic variables (Table 45-2). The diastolic components (y descent, end-diastolic a wave) and the systolic components (c wave, x descent, end-systolic v wave) are all clearly delineated. A mid-diastolic plateau wave, the h wave, is also seen because coronary heart rate is gradual. Waveform identification is aided by timing the relation between individual waveform parts and the electrocardiographic R wave. The x descent could be divided into two portions, x and x, similar to the segments earlier than and after the c wave. The final atrial pressure peak is the v wave, which is brought on by venous filling of the atrium throughout late systole while the tricuspid valve remains closed. Atrial strain then decreases, inscribing the y descent, or diastolic collapse, as the tricuspid valve opens and blood flows from atrium to ventricle.
Tags: finpecia 1 mg order free shipping, 1 mg finpecia cheap with amex, finpecia 1 mg effective, purchase 1 mg finpecia with visa, cheap finpecia 1 mg amex, 1 mg finpecia discount otc, generic finpecia 1 mg line, generic finpecia 1 mg visa, finpecia 1 mg buy visa, trusted finpecia 1 mg, finpecia 1 mg buy with visa, generic finpecia 1 mg on line, 1 mg finpecia purchase with amex, finpecia 1 mg discount, 1 mg finpecia cheap amex, discount 1 mg finpecia otc
10 of 10
Votes: 110 votes
Total customer reviews: 110
Customer Reviews
Ayitos, 64 years: However, the method is especially of interest in scientific analysis when investigating onset times of the laryngeal muscle tissue. Patients may also have a sort of seizure referred to as cerebral tetany, which consists of generalized tetany adopted by tonic spasms.
Kan, 26 years: Animal studies of such pure nephropathies treated with logical renoprotective interventions often reveal success; sadly, this success has rarely extended to equivalent renoprotection in humans. This angle is then used to correct the resulting Doppler shift frequency to present an correct velocity measurement.
Ernesto, 58 years: The choice of fluid sort in a variety of medical situations can be rationally guided by an understanding of the physicochemical and biologic properties of the assorted crystalloid and colloid solutions out there in combination with the available medical trial information. As early as 1972, however, investigators acknowledged the existence of a minimal of two distinct tremor patterns.
Muntasir, 23 years: Care must be taken to avoid hypokalemia, hypocalcemia, hypomagnesemia, and hypophosphatemia. Isoflurane28 and desflurane27 additionally slightly enhance the sweating threshold; nevertheless, they lower the cold-response thresholds nonlinearly.
Akrabor, 51 years: The scientific example is from a patient with a large parietal tumor shown within the scan. Although this is obviously an important outcome, it is most likely not sensitive enough to detect the importance of how lengthy the storage of blood transfused has been.
Farmon, 36 years: These catheters measure central venous saturation, measured in the superior vena cava. When transitioning from 2-D to 3-D imaging, echocardiographers should conceptually move from contemplating the heart in numerous slices to a 3-D organ, a lot the greatest way a surgeon does.
