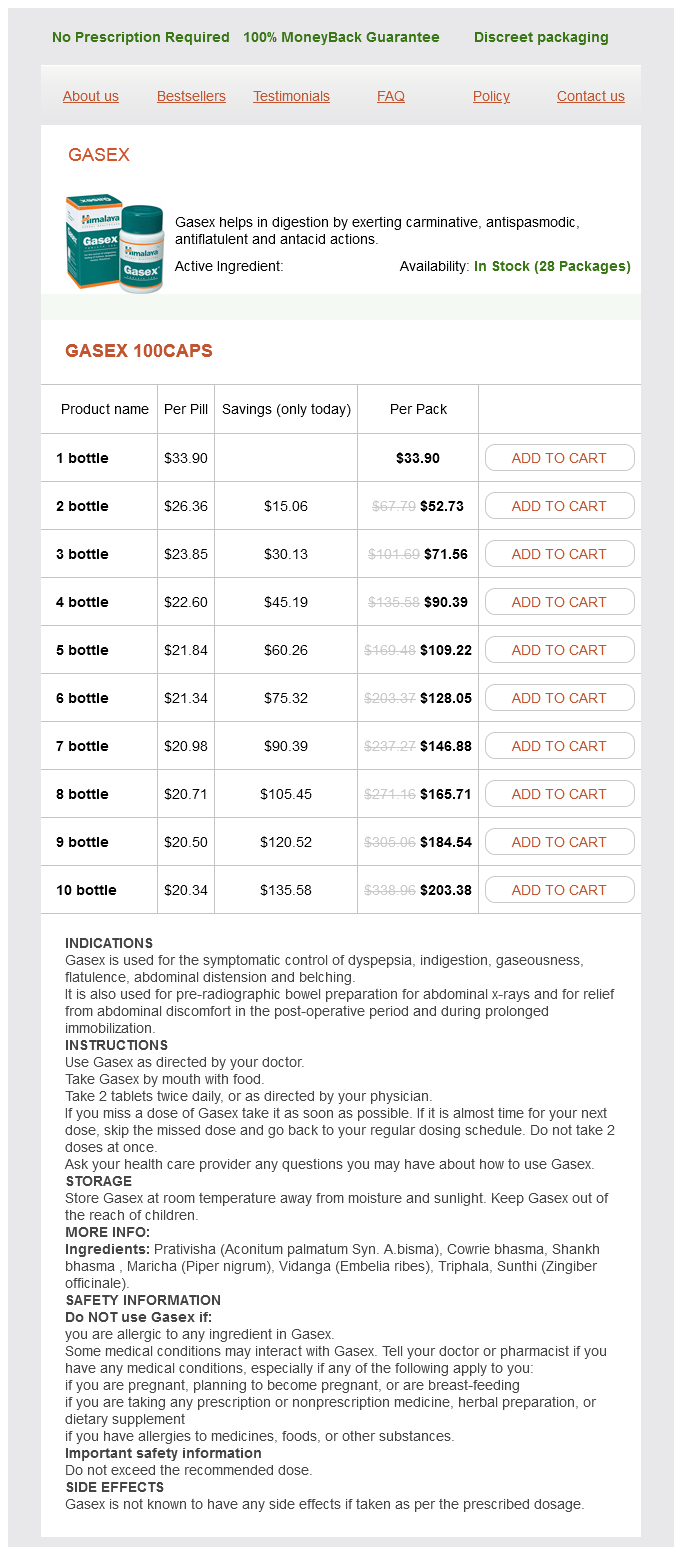
Gasex 100caps
- 1 bottle - $33.90
- 2 bottle - $52.73
- 3 bottle - $71.56
- 4 bottle - $90.39
- 5 bottle - $109.22
- 6 bottle - $128.05
- 7 bottle - $146.88
- 8 bottle - $165.71
- 9 bottle - $184.54
- 10 bottle - $203.38
Gasex dosages: 100 caps
Gasex packs: 1 bottle, 2 bottle, 3 bottle, 4 bottle, 5 bottle, 6 bottle, 7 bottle, 8 bottle, 9 bottle, 10 bottle
In stock: 550
Only $21,61 per item
Description
What is the return on funding for implementation of a crew resource management program at an educational medical heart American journal of medical quality: the official journal of the American College of Medical Quality gastritis diet áàñêèíî purchase 100 caps gasex fast delivery. Creating efficient studying environments - key educational ideas applied to simulation coaching gastritis for 6 months 100 caps gasex with amex. Method issues: influence of in-scenario instruction on simulation-based teamwork training gastritis symptoms dogs 100 caps gasex proven. Engagement and studying in simulation: recommendations of the Simnovate Engaged Learning Domain Group gastritis chronic symptoms cheap gasex 100 caps without prescription. Developing observational categories for group process research based on task and coordination-requirement analysis: examples from research on medical emergency-driven teams. Simulation-based multidisciplinary team coaching decreases time to important operations for trauma sufferers. Effects of cross-training on team efficiency, communication, and workload in simulated air battle management. An institutionwide approach to redesigning administration of cardiopulmonary resuscitation. Simulationbased evaluation identifies longitudinal changes in cognitive expertise in an anesthesiology residency training program. Use of simulation-based training to reduce catheter-related bloodstream infections. Medical staff training: making use of crew useful resource administration in the Veterans Health Administration. Toward a new paradigm in hospital-based pediatric training: the event of an onsite simulator program. Differences in safety climate among hospital anesthesia departments and the impact of a realistic simulation-based training program. Practice improvements primarily based on participation in simulation for the maintenance of certification in anesthesiology program. Misconceptions surrounding the maintenance of certification in anesthesiology simulation course. Anaesthesia crisis useful resource management training: an intimidating idea, a rewarding expertise. Variation and adaptation: studying from success in affected person safetyoriented simulation coaching. Becoming a simulator teacher and learning to facilitate the instructor and facilitation coaching (InFacT). A structure for videoassisted debriefing in simulator-based coaching of disaster resource management. Effectiveness of video-assisted debriefing in well being education: an integrative evaluate. Vicarious learning during simulations: is it more effective than hands-on coaching The influence of perioperative catastrophes on anesthesiologists: outcomes of a national survey. Promoting learning and affected person care by way of shared reflection: a conceptual framework for staff reflexivity in health care. Briefing and debriefing during simulation-based training and beyond: content material, construction, angle, and setting. Group duties, group interplay process, and group efficiency effectiveness: a review and proposed integration. Faculty improvement for simulation programs: five points for the future of debriefing coaching. Considering face, rights, and objectives: a important review of rapport management in facilitator-guided simulation debriefing approaches. Tipping the scales: prioritizing mentorship and help in simulation college development. Coaching the debriefer: peer teaching to improve debriefing high quality in simulation applications. Translational instructional research: a necessity for effective healthcare improvement. The continuum of translation analysis in genomic medication: how can we accelerate the appropriate integration of human genome discoveries into health care and illness prevention Genetics in medication: official journal of the American College of Medical Genetics. Development of an objective scoring system for measurement of resident performance on the human affected person simulator. Assessment of non-technical skills within the operating room-one evaluation software per specialty Five steps to develop checklists for evaluating medical efficiency: an integrative method. An objective methodology for task evaluation and workload assessment in anesthesia suppliers. A framework for determining the return on funding of simulation-based training in health care. Issues of cost-benefit and cost-effectiveness for simulation in well being professions education. Using statistical process control strategies to trace small changes in perinatal mortality after a coaching program in a low-resource setting. International journal for quality in health care: journal of the International Society for Quality in Health Care. Efficacy and Effectiveness of Simulation Based Training for Learning and Assessment in Health Care. Technology-enhanced simulation for health professions schooling: a systematic review and metaanalysis. The pharmacology of simulation: a conceptual framework to inform progress in simulation analysis. Use of a highfidelity simulator to develop testing of the technical efficiency of novice anaesthetists. Systematic simulation-based group training in a Swedish intensive care unit: a various response among crucial care professions. Competent and autonomous people could make affirmative selections about their medical care and refuse any medical therapies, together with lifesaving care. Four parts of competent decision making are understanding, appreciation, reasoning, and proof of a selection. Minor sufferers have varying levels of decision-making capability, and so they may have authorized rights to make sure choices. Pediatric patients ought to be involved to the diploma that they are often in medical choice making, particularly concerning elective remedy. Medical testing ought to follow the ethical ideas of beneficence and nonmaleficence and must be based on clinically validated algorithms every time possible. In general, the rights of pregnant ladies are weighed towards the rights of fetuses in a decremental trend because the fetus approaches and surpasses viable age. Laboring girls are able to give knowledgeable consent, and the validity of "Ulysses directives" on the time of labor is ethically debatable. Patients have moral and legal rights to refuse even life-sustaining therapy, together with within the working room. Terminal care requires special information and experience on the part of the physician. Several interventions have special ethical implications-fluid and nutritional administration; the administration of sedatives and/or narcotics which have the potential to hasten death; the institution of deep continuous sedation; the administration of neuromuscular blocking brokers; and deactivating pacemakers, ventricular help devices, and implanted cardioverter-defibrillators. Euthanasia is the administration of medicine by somebody apart from the patient for the categorical function of inflicting demise. Brain death is legally and medically outlined as the point at which all cardiorespiratory function irreversibly ceases or all function of the entire brain irreversibly stops. Advances in understanding animal cognition have led most biologists to consider that many, if not all, animals are capable of feeling pleasure, pain, anticipation, and worry, and thus they experience each enjoyment and suffering. Allowing animal struggling because of ache, worry, sickness, or poor requirements of care is an ethical harm that have to be avoided, mitigated, and weighed heavily in opposition to the benefits it produces. Medicine is a revered profession with codes of habits and particular rules of conduct.
Bilberry. Gasex.
- Improving night vision.
- Chest pain (angina), varicose veins, cataracts, hardening of the arteries (atherosclerosis), diabetes, arthritis (osteoarthritis), gout, skin problems, hemorrhoids, urinary tract problems, chronic fatigue syndrome, and other conditions.
- How does Bilberry work?
- Are there safety concerns?
- Dosing considerations for Bilberry.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96235
Effects of surgical ranges of propofol and sevoflurane anesthesia on cerebral blood move in healthy topics studied with positron emission tomography gastritis symptoms months order gasex 100 caps mastercard. Methods that assess world hemodynamic effects reveal larger modifications than those that emphasize the cortical compartment chronic gastritis recipes gasex 100 caps discount otc. Sevoflurane may trigger much less impairment of the autoregulatory response to growing blood strain than other risky anesthetics gastritis cystica profunda 100 caps gasex order. These knowledge also counsel that caution have to be exercised in the administration of risky anesthetics in pathologic situations gastritis reviews order gasex 100 caps amex, similar to traumatic brain injury, by which metabolism is already decreased. Nonetheless, isoflurane, desflurane, or sevoflurane are preferred as a outcome of the margin for error is probably wider than with halothane. In sharp distinction, when N2O is run in combination with intravenous medication, together with barbiturates, benzodiazepines, narcotics, and propofol, its cerebral-vasodilating impact is attenuated or even utterly inhibited. These findings are, probably, the product of variations in species, methods, depth of background anesthesia, and interactions with simultaneously administered anesthetics. Despite the inconsistencies that are evident, the vasodilatory action of N2O may be clinically vital in neurosurgical patients with reduced intracranial compliance. However, N2O-induced cerebral vasodilation could be significantly blunted by the simultaneous administration of intravenous anesthetics. By distinction, the addition of N2O to a volatile drug�based anesthetic can modestly improve cerebral metabolism and blood circulate. Because N2O rapidly enters a closed gas house, it should be prevented or omitted when a closed intracranial gas space could exist or intravascular air is a priority. The other aminosteroids, pipecuronium and rocuronium, ought to be equally without direct effect, and no antagonistic occasions have been reported. Doses of metocurine, atracurium, and mivacurium must be restricted to ranges not related to hypotension. Rocuronium is more and more getting used for the induction of anesthesia, as properly as for intraoperative rest. With sugammadex, even a profound neuromuscular blockade can be rapidly reversed (see Chapters 27 and 28). Metocurine, atracurium, and mivacurium additionally release histamine in lesser quantities. This effect is likely to be clinically inconsequential until these muscle relaxants are administered within the large doses essential to achieve endotracheal intubation situations rapidly. A theoretic concern might be in the setting of a prolonged closed-cranium procedure in a patient with poor intracranial compliance. This sample happens with enflurane in the canine, which is perhaps another excuse (in addition to the potential for epileptogenesis in the presence of cerebral harm and hypocapnia) for omission of enflurane in this circumstance. An intensive evaluation of the pro- and anticonvulsant effects of anesthetics and adjuvants is out there. In apply, it appears that spontaneous seizures during or after anesthesia have been extraordinarily uncommon events. Nonetheless, in patients with processes that may predispose them to seizures, the use of doubtlessly epileptogenic drugs must be averted in conditions throughout which cheap alternatives are available. In the brain, excluding the choroid plexus, in the pituitary, and within the space postrema, tight junctions reduce this pore measurement to roughly eight �. At higher doses, isoflurane (3%) considerably will increase protein extravasation, not solely within the thalamus but in addition within the cortex. In experimental fashions of mind damage, isoflurane has been reported to each exacerbate200 and ameliorate201 edema formation within the injured mind. Of particular relevance to neuroanesthesia is the remark that hypocapnia potentiates seizure-type discharges during enflurane anesthesia. However, as a result of seizure exercise can elevate mind metabolism by as a lot as 400%, the use of enflurane, particularly at excessive doses and with hypocapnia, ought to most likely be prevented in patients predisposed to seizures. The medical expertise with isoflurane is extremely large, and unexplained seizure-like exercise has been reported in only two sufferers. One incidence was intraoperative,207 and the other was instantly postoperative. Accordingly, this anesthetic has been used to activate seizure foci throughout cortical mapping. On only two events, seizures have additionally been reported after ketamine anesthesia in subjects who have been neurologically regular;217,218 seizure thresholds might have been lowered by aminophylline in certainly one of these situations. However, ketamine has additionally been employed for the aim of controlling status epilepticus. However, it has been electively used in low doses to activate seizure foci for Propofol Abnormal physique movements and opisthotonos can happen after propofol anesthesia. In addition, propofol sedation has been broadly used during awake resection of seizure foci and different intracranial lesions. Narcotics Seizures or limbic system hypermetabolism (or both) may be readily elicited in some animal species with narcotics. Partial complex seizures on the induction of anesthesia with fentanyl in sufferers present process anterior temporal lobectomy have been reported. The brain is due to this fact extraordinarily weak within the occasion of interruption of substrate. Models of Cerebral Ischemia How totally different is complete cerebral ischemia, as happens during cardiac arrest, and incomplete cerebral ischemia, as may occur throughout occlusion of a major cerebral vessel or severe hypotension Energy Failure and Excitotoxicity Energy failure is the central event that occurs throughout cerebral ischemia. Voltage-dependent Ca2+ channels are then activated, and Ca2+ gains entry into the cytosol. Depolarization of presynaptic terminals additionally leads to the release of massive portions of excitatory neurotransmitters, significantly glutamate, into the synaptic cleft. Excessive stimulation of ligand-gated channels and the simultaneous opening of voltage-dependent calcium (Ca2+) channels permit rapid entry of Ca2+ into neurons. Injury to the mitochondria leads to energy failure, technology of free radicals, and the discharge of cytochrome c (cyt c) from the mitochondria; the latter is among the means by which neuronal apoptosis is initiated. Ionic inflow is accompanied by an inflow of water, and neuronal swelling quickly happens after membrane depolarization. Ca2+ is a ubiquitous second messenger in cells and is a cofactor required for the activation of a selection of enzyme systems. The rapid, uncontrolled improve in cytosolic Ca2+ ranges initiates the activation of numerous cellular processes that contribute to harm. The latter, in combination with other free radicals generated in response to mitochondrial injury, can result in lipid peroxidation and membrane damage. Prostaglandins and leukotrienes additionally evoke an inflammatory response and are powerful chemotactic medication. Activation of platelets inside cerebral microvessels, in addition to an influx of white blood cells into broken areas, worsen the ischemic injury by occluding the vasculature. Lactic acid is shaped as a outcome of the anaerobic glycolysis that takes place after failure of the supply of oxygen. The associated lower in pH contributes to the deterioration of the intracellular environment. An elevated preischemic serum glucose level may accelerate this course of by providing additional substrate for anaerobic glycolysis. Collectively, the simultaneous and unregulated activation of numerous cellular pathways overwhelms the reparative and restorative processes inside the neuron and finally leads to neuronal death. The Nature of Neuronal Death the neuronal death that happens in response to these processes has been categorized as necrotic or apoptotic in nature. A characteristic of those necrotic neurons is the presence of acidophilic cytoplasm. Neuronal apoptosis, a type of cellular suicide, has additionally been demonstrated in a selection of fashions of cerebral ischemia. Apoptosis is characterized by chromatin condensation, involution of the cell membrane, swelling of mitochondria, and mobile shrinkage. In the later phases of apoptosis, neurons fragment into several apoptotic our bodies, which are then cleared from the mind.
Specifications/Details
All these depolarizing events are insensitive to treatment with muscarinic acetylcholine receptor antagonist gastritis diet ôðèâ discount gasex 100 caps free shipping, atropine gastritis symptoms belching 100 caps gasex discount otc, however delicate to therapy with -bungarotoxin or muscle relaxants gastritis kefir generic gasex 100 caps mastercard, which block the flow of present xyrem gastritis generic gasex 100 caps otc. As the myotubes mature, the sarcomere, which is the contractile factor of the muscle consisting of actin and myosin, develops. When an agonist occupies each -subunit websites, the protein molecule undergoes a conformational change with a twisting motion alongside the central axis of the receptor that ends in the opening of the central channel by way of which ions can move along a concentration gradient. When the central channel is open, sodium and calcium flow from the skin of the cell to the within and potassium flows from the inside to the skin. The channel in the tube is giant enough to accommodate many cations and electrically neutral molecules, but it excludes anions. The web current is depolarizing and creates the end-plate potential that stimulates the muscle to contract. The pulse stops when the channel closes by a reversed mechanical conformation (see earlier discussion), which is typically initiated when one or both agonist molecules detach from the receptor. In the activated, open state, the current that passes via each open channel is minuscule, only a few picoamperes (approximately 104 ions/ ms). However, each burst of acetylcholine from the nerve usually opens approximately 500,000 channels concurrently, and the entire current is greater than enough to produce depolarization of the tip plate and contraction of muscle. Opening of a channel causes conversion of chemical alerts from a nerve to the circulate of current on the muscle illness to cause end-plate potentials, thereby leading to muscle contraction. The end-plate potential has been seen as a graded event that could be lowered in magnitude or prolonged in time by medication, however, in reality, the endplate potential is the summation of many all-or-nothing occasions concurrently occurring at myriad ion channels. This interaction between agonists and antagonists is aggressive, and the outcome-transmission or block-depends on the relative concentrations and binding characteristics of the medicine involved (see section on "Drug Effects on Postjunctional Receptors"). They might open for a longer or shorter time than normal, open or shut more steadily than traditional, open briefly and repeatedly. Their function is also influenced by medication, adjustments in fluidity of the membrane, temperature, electrolyte balance within the milieu, and different bodily and chemical components. All these influences on channel activity are in the end reflected within the power or weakness of neuromuscular transmission and contraction of a muscle. The last outcome-block or transmission- is determined by the relative concentrations of the chemical substances and their comparative affinities for the receptor. One receptor has attracted two acetylcholine molecules and has opened its channel, the place current will circulate to depolarize that section of membrane. A single molecule of antagonist, nevertheless, is enough to stop depolarization of that receptor. This modifies the competitors by strongly biasing it in favor of the antagonist (relaxant). Paralysis produced by high concentrations of muscle relaxants (antagonist) is harder to reverse with cholinesterase inhibitors than that produced by low concentrations. This is the molecular foundation for the advice to not administer anticholinesterases too early. In contrast to reversal with a cholinesterase inhibitor, cyclodextrin encapsulation takes place at any concentration of a steroid-based compound, such as vecuronium or rocuronium, and reversal by this novel mechanism can due to this fact be achieved at any stage of neuromuscular block provided the amount of cyclodextrin (sugammadex) is massive sufficient. Once activated by a change in voltage, the molecule and its gates progress as illustrated (left to right). Structurally, succinylcholine is similar to the natural ligand acetylcholine and consists of two molecules of acetylcholine certain together via their backbones. It is thus not stunning that succinylcholine can mimic the results of acetylcholine. Succinylcholine or decamethonium can bind to the receptor, open the channel, cross present, and depolarize the end plate. These agonists, similar to acetylcholine, attach only briefly; each opening of a channel could be very quick in duration1 ms or much less. The response to acetylcholine, however, is over in milliseconds because of its fast degradation by acetylcholinesterase, and the tip plate resets to its resting state lengthy before another nerve impulse arrives. In contrast, the depolarizing relaxants characteristically have a biphasic action on muscle-an initial contraction, followed by leisure lasting from minutes to hours. The time required to clear the drug from the physique is the principal determinant of how lengthy the drug impact lasts. Wholebody clearance of the relaxant may be very gradual compared to acetylcholine, notably when plasma (pseudo) cholinesterase is abnormal. For details on the impact of succinylcholine in sufferers with cholinesterase deficiency, also see Chapter 27. The fast shift from excitation of muscle contraction to block of transmission by depolarizing relaxants happens as a outcome of the top plate is constantly depolarized. Two parts of its structure act as gates that allow or stop the flow of sodium ions. Shortly after the voltage-dependent gate opens, the time-dependent inactivation gate closes. Because the sodium channels immediately adjoining to the end plate are influenced by depolarization of the tip plate, their voltage-dependent gates stay open and their inactivation gates keep closed. When the move of ions by way of sodium channels within the perijunctional zone stops due to a closure of the inactivation gates, the channels downstream (beyond the perijunctional zone) are freed of depolarizing influence. In impact, the perijunctional zone turns into a buffer that shields the the rest of the muscle from events at the end plate. Consequently, the muscle membrane is separated into three zones: (1) the end plate, which is depolarized by succinylcholine; (2) the perijunctional muscle membrane, during which the sodium channels are frozen in an inactivated state; and (3) the the rest of the muscle membrane, by which the sodium channels are in the resting state. During accommodation, when the synapse is inexcitable via the nerve (transmitter), direct electrical stimulation of muscle causes muscle contraction because the sodium channels beyond the junctional space are within the resting excitable state. The extraocular muscle tissue are tonic muscular tissues, that are multiply innervated and chemically excitable along most of their surfaces. The rigidity that develops forces the eye in opposition to the orbit and accounts for part of the rise in intraocular strain produced by depolarizing relaxants. These reactions cause drug-induced changes within the dynamics of the receptor; instead of sharply opening and closing, the modified channels are sluggish. They open extra slowly and keep open longer, or they shut slowly and in a quantity of steps, or both. These effects on channels cause corresponding adjustments in the flow of ions and distortions of the endplate potential. For instance, procaine, ketamine, inhaled anesthetics, or other drugs that dissolve in the membrane lipid may change the opening or closing traits of the channel. If, nevertheless, the channel is prevented from or slowed in closing, then transmission may be enhanced. Such drugs can be involved in two clinically necessary reactions: receptor desensitization and channel block. The former occurs in the receptor molecule, whereas the latter occurs in the ion channel. The second state exists when two molecules of agonist are certain to the -subunit of the receptor and the receptor has undergone the conformational 12 � Neuromuscular Physiology and Pharmacology 345 change that opens the channel and allows ions to move. The receptor macromolecule, one thousand instances larger by weight than most medicine or gases, offers many locations at which the smaller molecules may act. The interface between lipid and receptor protein provides additional potential sites of reaction. Desensitization is accompanied by phosphorylation of a tyrosine unit in the receptor protein. Agonists do promote transition to a desensitized state or, because they bind very tightly to desensitized receptors, lure a receptor in a desensitized state. Superficially, the preparation seems to be regular, but its responsiveness to agonists or antagonists is altered. One variety happens very quickly, inside a couple of milliseconds after application of an agonist, which may clarify the elevated sensitivity to nondepolarizing relaxant after the prior administration of succinylcholine. Many different medication used by anesthetists also promote the shift of receptors from a traditional state to a desensitized state. These actions are independent of the classic results, based on aggressive inhibition of acetylcholine. The presence of desensitized receptors signifies that fewer receptor channels than traditional are available to carry transmembrane current. The production of desensitized receptors decreases the efficacy of neuromuscular transmission. Even if just some receptors are desensitized, neuromuscular transmission will be impaired, and the system might be more prone to block by typical antagonists corresponding to atracurium or rocuronium. In open- and closed-channel blocks, the conventional move of ions by way of the receptor is impaired, thereby ensuing in the prevention of depolarization of the end plate and a weakened or blocked neuromuscular transmission.
Syndromes
- Infection (a slight risk any time the skin is broken)
- Benign hereditary chorea (a rare inherited condition)
- Changes in the amount of sodium or potassium in the blood
- Long-term (chronic) discomfort or pain
- Endoscopic retrograde cholangiopancreatography (ERCP)
- Low-set ears
- Easy bruising of the skin
- Methanol
- What medicines do you take?
- Echocardiogram
Related Products
Additional information:
Epidemiology of primary sclerosing cholangitis and primary biliary cirrhosis: a systematic evaluation gastritis diet in telugu gasex 100 caps buy overnight delivery. Biochemical response to ursodeoxycholic acid and long�term prognosis in major biliary cirrhosis collagenous gastritis definition gasex 100 caps generic with amex. Efficacy of obeticholic acid in sufferers with major biliary cirrhosis and inadequate response to ursodeoxycholic acid gastritis diet what to eat order gasex 100 caps mastercard. Bezafibrate normalizes alkaline phosphatase in major biliary cirrhosis sufferers with incomplete response to ursodeoxycholic acid antral gastritis diet plan buy 100 caps gasex visa. Introduction to the revised American Association for the Study of Liver Diseases follow guideline administration of adult patients with ascites because of cirrhosis 2012. Portal hypertensive bleeding in cirrhosis: risk stratification, analysis, and management: 2016 practice steerage by the American Association for the Study of Liver Diseases. Hepatic venous stress gradient predicts growth of hepatocellular carcinoma 51. Elevated alpha�fetoprotein: differential diagnosis-hepatocellular carcinoma and different problems. Controversies relating to and views on scientific utility of biomarkers in hepatocellular carcinoma. Evaluation of pharmacokinetic strategies used to estimate caffeine clearance and comparability with a bayesian forecasting technique. Quantitative liver function tests enhance the prediction of medical outcomes in chronic hepatitis C: results from the hepatitis C antiviral long�term therapy against cirrhosis trial. The measurement of liver blood circulate: a evaluation of experimental and scientific strategies. Elastography assessment of liver fibrosis: society of radiologists in ultrasound consensus conference statement. Diagnostic modalities for nonalcoholic fatty liver disease, nonalcoholic steatohepatitis, and associated fibrosis. Transient elastography: a meta� evaluation of diagnostic accuracy in analysis of portal hypertension in persistent liver illness. Comparison between ultrasonographic signs and the diploma of portal hypertension in patients with cirrhosis. Prognostic indicators of survival in patients with compensated and decompensated cirrhosis. Banding ligation versus beta�blockers for primary prevention in oesophageal varices in adults. Hepatic vein pressure gradient discount and prevention of variceal bleeding in cirrhosis: a scientific evaluation. Causes of renal failure in patients with decompensated cirrhosis and its influence in hospital mortality. Diagnosis and management of acute kidney harm in sufferers with cirrhosis: revised consensus recommendations of the International Club of Ascites. Impact of liver transplantation on the survival of patients treated for hepatorenal syndrome sort 1. Portosystemic hepatic encephalopathy after transjugular intrahepatic portosystemic shunt in patients with cirrhosis: clinical, laboratory, psychometric, and electroencephalographic investigations. Methods for diagnosing hepatic encephalopathy in patients with cirrhosis: a multidimensional strategy. Hepatopulmonary syndrome increases the postoperative mortality rate following liver transplantation: a prospective examine in 90 sufferers. Survival in portopulmonary hypertension: Mayo Clinic experience categorized by remedy subgroups. Global, regional, and nationwide age�sex specific mortality for 264 causes of death, 1980�2016: a systematic analysis for the worldwide burden of illness study 2016. Long�term survival and sample of recurrence after resection of small hepatocellular carcinoma in sufferers with preserved liver operate: implications for a technique of salvage transplantation. Mechanism and function of intrinsic regulation of hepatic arterial blood flow: hepatic arterial buffer response. The effects of sevoflurane, halothane, enflurane, and isoflurane on hepatic blood flow and oxygenation in chronically instrumented greyhound canines. Influence of desflurane, isoflurane and halothane on regional tissue perfusion in canines. The blood�gas partition coefficient of xenon may be lower than usually accepted. Rapid reversal of neuromuscular blockade by sugammadex after continuous infusion of rocuronium in sufferers with liver dysfunction undergoing hepatic surgery. The effect of dopamine on hepatic blood move in patients present process epidural anesthesia. The results of thoracic epidural anesthesia on hepatic blood move in patients underneath common anesthesia. The influence of thoracic epidural anesthesia on liver hemodynamics in sufferers beneath common anesthesia. Thoracic but not lumbar epidural anaesthesia will increase liver blood flow after major abdominal surgery. Morbidity and mortality associated to non�hepatic surgery in sufferers with liver cirrhosis: a systematic evaluation. Postoperative antagonistic outcomes after non�hepatic surgery in patients with liver cirrhosis. Early mortality and long� time period survival after abdominal surgery in patients with liver cirrhosis. Factors that predict consequence of stomach operations in patients with superior cirrhosis. Model for end�stage liver disease rating versus Child score in predicting the result of surgical procedures in patients with cirrhosis. Clarification of danger components for belly operations in sufferers with hepatic cirrhosis. Abdominal operations in patients with cirrhosis: still a serious surgical challenge. Effect of higher abdominal surgery and cirrhosis upon the pharmacokinetics of methohexital. Effect of propofol infusion on splanchnic hemodynamics and liver oxygen consumption within the rat. Hemodynamic modifications during induction of anesthesia with eltanolone and propofol in dogs. The effect of propofol and desflurane anaesthesia on human hepatic blood circulate: a pilot examine. Pharmacokinetics and pharmacodynamics of intravenous midazolam in patients with extreme alcoholic cirrhosis. Prolonged apnoea after suxamethonium: an analysis of the first 225 instances reported to the danish cholinesterase analysis unit. Pharmacokinetics and pharmacodynamics of cisatracurium in sufferers with end�stage liver illness present process liver transplantation. A model to predict poor survival in patients undergoing transjugular intrahepatic portosystemic shunts. The safety of intra�abdominal surgical procedure in sufferers with cirrhosis: Model for End�Stage Liver Disease score is superior to Child� Turcotte�Pugh classification in predicting outcome. Predictors of mortality in cirrhotic sufferers present process extrahepatic surgery: comparability of Child� Turcotte�Pugh and Model for End�Stage Liver Disease�based indices. Role of transjugular intrahepatic portosystemic shunt in the management of portal hypertension. Transjugular intrahepatic portosystemic shunt complications: prevention and administration. Symptomatic coronary heart failure after transjugular intrahepatic portosystemic shunt placement: incidence, outcomes, and predictors. Hepatic resection in the United States: indications, outcomes, and hospital procedural volumes from a nationally consultant database. Preoperative risk rating predicting 90�day mortality after liver resection in a population�based research. Recommendations for laparoscopic liver resection: a report from the Second International Consensus Conference held in Morioka. The Southampton consensus guidelines for laparoscopic liver surgery: from indication to implementation.
Usage: ut dict.
The myofibril is the rod-like bundle that forms the contractile elements inside cardiomyocytes gastritis special diet 100 caps gasex discount otc. Within each contractile element are contractile proteins gastritis diet 5 small discount 100 caps gasex free shipping, regulatory proteins gastritis extreme pain buy cheap gasex 100 caps on line, and structural proteins gastritis ulcer diet generic gasex 100 caps fast delivery. Contractile proteins make up roughly 80% of the myofibrillar protein, with the rest being regulatory and structural proteins. The sarcolemma, or the outer plasma membrane, separates the intracellular and extracellular house. It surrounds the cardiomyocyte and invaginates into the myofibrils through an extensive tubular network often known as transverse tubules or T tubules, and it additionally forms specialised intercellular junctions between cells. The indicator dilution method is another technique for determining cardiac output also primarily based on the law of conservation of mass. The two mostly used indicator dilution methods are the dye dilution and the thermodilution strategies. Ca2+-release channels, but they also type the scaffolding proteins that anchor lots of the key regulatory proteins. In addition, mitochondria can even accumulate Ca2+ and thereby contribute to the regulation of the cytosolic Ca2+ concentration. The cytosol is the fluidfilled microenvironment inside the sarcolemma, exclusive of the organelles and the contractile equipment and proteins. The adhesion sites fashioned by spot desmosomes anchor the intermediate filament cytoskeleton of the cell; these formed by the fasciae adherens anchor the contractile apparatus. Gap junctions include clusters of plasma membrane channels immediately linking the cytoplasmic compartments of neighboring cells. Gap junction channels are constructed from connexins, a multigene household of conserved proteins. The principal connexin isoform of the mammalian coronary heart is connexin 43; other connexins, notably connexins forty, 45, and 37, are also expressed however in smaller portions. These cells have a low content material of myofibrils and a outstanding nucleus, and so they include an abundance of gap junctions. Excitation System the mobile action potential originating in the specialized conduction tissue is propagated to individual cells where it initiates the intracellular event that leads to the contraction of the cell via the sarcolemmal excitation system. Ion fluxes across plasma membranes end in depolarization (attaining a much less unfavorable membrane potential) and repolarization (attaining a extra unfavorable membrane potential). Because these ion channel proteins open and close the pores in response to adjustments in membrane potential, the channels are voltage gated. In the center, sodium (Na+), potassium (K+), Ca2+, and chloride (Cl-) channels contribute to the action potential. Mostly on account of the influx of Na+, the membrane potential turns into depolarized, which leads to a particularly speedy upstroke (phase 0). As the membrane potential reaches a crucial level (or threshold) throughout depolarization, the action potential is propagated. The plateau section (phase 2) occurs with a net influx of Ca2+ through L-type Ca2+ channels and the efflux of K+ by way of a quantity of K+ channels-the inwardly rectifying ik, the delayed rectifier ik1, and ito. Repolarization (phase 3) is led to when an efflux of K+ from the three outward K+ currents exceeds the influx of Ca2+, thus returning the membrane to the resting potential. Very little ionic flux occurs throughout diastole (phase 4) in a fast-response motion potential. In contrast, throughout diastole (phase 4), pacemaker cells that show slow-response action potentials have the aptitude of spontaneous diastolic depolarization and generate the automated cardiac rhythm. Pacemaker currents throughout section four are the outcome of a rise within the three inward currents and a lower in the two outward currents. The preliminary phase (0) spike and overshoot (1) are attributable to a speedy inward sodium (Na+) present, the plateau part (2) by a sluggish calcium (Ca2+) present via L-type Ca channels, and repolarization (phase 3) by outward potassium (K+) currents. In specialized conduction system tissue, spontaneous depolarization takes place during part 4 until the voltage resulting in opening of the Na channel is reached. When compared with the fastresponse action potential, part 0 is much less steep, section 1 is absent, and part 2 is indistinct from phase three in the slow-response motion potential. The Na+-Ca2+ exchanger restores cellular ionic steadiness by actively transporting Ca2+ out of the cell against a focus gradient while transferring Na+ into the cell in an energy-dependent manner. Activation of the contractile system is decided by a rise in free cytosolic Ca2+ and its subsequent binding to contractile proteins. These spatially and temporally patterned activations of localized Ca2+ launch, in flip, stimulate myofibrillar contraction. Because it lies near the Ca2+release channels, the stored Ca2+ may be rapidly discharged for release once the Ca2+-release channels are stimulated. Cytosolic Ca2+ can be eliminated by extrusion via the sarcolemmal Ca2+ pump and the activity of the Na+Ca2+ exchanger. Because of the ubiquity of Ca2+ in cardiac signaling, adjustments in Ca2+ dealing with could be associated with numerous maladaptive outcomes. The thickness of the arrows indicates the magnitude of the calcium flux, and the vertical orientations describe their energetics: downward-pointing arrows characterize passive calcium flux, whereas upward-pointing arrows characterize energy-dependent calcium transport. Calcium coming into the cell from extracellular fluid via L-type calcium channels triggers the discharge of calcium from the sarcoplasmic reticulum. Sodium that enters the cell in change for calcium (dashed line) is pumped out of the cytosol by the sodium pump. Calcium binding to (arrow E) and dissociation from (arrow F) high-affinity calcium-binding websites of troponin C activate and inhibit interactions of the contractile proteins. Arrow H depicts movement of calcium into and out of mitochondria to buffer the cytosolic calcium focus. Calcineurin, a Ca2+-dependent signaling molecule, is persistently linked with myocardial hypertrophy by way of gene expression by way of a nuclear issue of activated T-cells pathway. A sarcomere is outlined as the gap between Z lines (Z is an abbreviation for the German word, Zuckung, meaning contraction), which join the sarcomeres in collection. Titin, the third filament protein, tethers the thick-filament myosin to the Z line. The Z traces on the two ends of the sarcomere are introduced nearer collectively throughout contraction because the thickfilament myosin heads interact with the skinny actin filaments and slide over each other. The I band is positioned on either side of the A band and accommodates only actin filament. Mutations in no less than eight completely different genes encoding sarcomere proteins have been recognized as the molecular basis for the dysfunction. These genes are -cardiac myosin heavy chain, cardiac troponin T (TnT), -tropomyosin, cardiac myosin-binding protein C, essential or regulatory myosin mild chain, cardiac troponin I (TnI), -cardiac actin, and titin. The contractile equipment throughout the cardiomyocyte consists of contractile and regulatory proteins. Tropomyosin, a doublestranded -helical regulatory protein, winds around the actin array and varieties the backbone for the thin-filament actin. Each myosin molecule has two useful domains: the physique or filament and the bilobar myosin head. The regulatory troponin heterotrimer complex is found at regular intervals alongside tropomyosin. The heterotrimer troponins are made up of troponin C (TnC), the Ca2+ receptor; TnI, an inhibitor of actin-myosin interaction; and TnT, which hyperlinks the troponin advanced to tropomyosin. It is situated on the finish of the thin-filament actin and caps the tip to forestall any excessive elongation of the skinny filament. These occasions, which ensue from the binding of Ca2+ to TnC, lead to conformational modifications in tropomyosin and permit attachment of the myosin head to actin. This exercise ends in the release of Ca2+ binding to TnC and the separation of the myosin-actin cross-bridge. Myocyte rest depends on the kinetics of cross-bridge cycling, the affinity of Ca2+ for TnC, and the activity of the Ca2+-reuptake mechanisms. Relaxation is enhanced by the increased kinetics of cross-bridge biking, decreased Ca2+ affinity for TnC, and increased activity of Ca2+-reuptake mechanisms. Structurally, titin consists of an inextensible anchoring section and an extensible elastic segment. Titin is the principal determinant of the passive properties of the myocardium at small ventricular volumes. The cytoskeleton is the protein framework throughout the cytoplasm that hyperlinks, anchors, or tethers structural components contained in the cell.
Tags: generic 100 caps gasex with mastercard, gasex 100 caps discount free shipping, purchase gasex 100 caps, cheap 100 caps gasex with mastercard, 100 caps gasex order overnight delivery, gasex 100 caps line, gasex 100 caps discount fast delivery, gasex 100 caps buy fast delivery, gasex 100 caps purchase without prescription, gasex 100 caps generic amex, discount gasex 100 caps with visa, order gasex 100 caps amex, purchase gasex 100 caps otc, proven gasex 100 caps, gasex 100 caps buy discount line, cheap gasex 100 caps fast delivery
8 of 10
Votes: 120 votes
Total customer reviews: 120
Customer Reviews
Stejnar, 46 years: Studies specifically designed to assess the influence of age on remifentanil and propofol have characterized the affect of age in quantitative phrases. Comparative Study of Brain Protection Effect between Thiopental and Etomidate Using Bispectral Index throughout Temporary Arterial Occlusion.
Baldar, 52 years: There could be a transient (1-3 minutes) lower in minute ventilation after the bolus administration of an induction dose of ketamine (2 mg/kg intravenously). The solely way to consider this security gadget is to disconnect the wall oxygen supply and shut off the oxygen provide tank or tanks, in order to generate the alarm condition.
