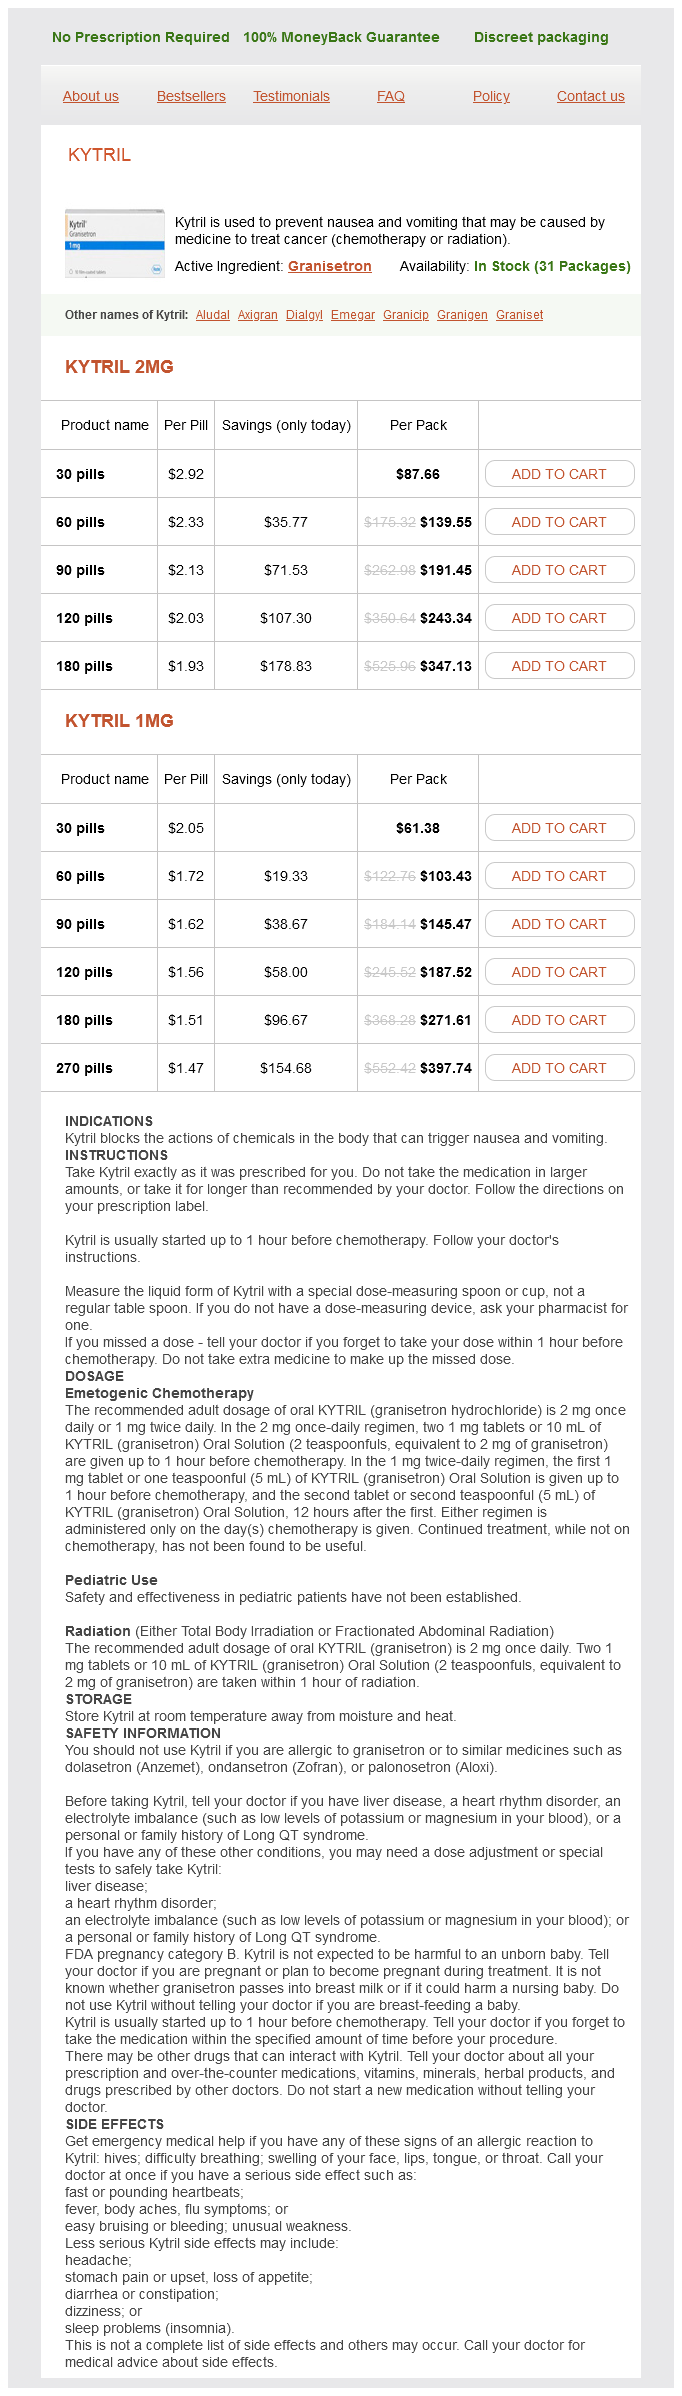
Kytril 2mg
- 30 pills - $87.66
- 60 pills - $139.55
- 90 pills - $191.45
- 120 pills - $243.34
- 180 pills - $347.13
Kytril 1mg
- 30 pills - $61.38
- 60 pills - $103.43
- 90 pills - $145.47
- 120 pills - $187.52
- 180 pills - $271.61
- 270 pills - $397.74
Kytril dosages: 2 mg, 1 mg
Kytril packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills
In stock: 969
Only $1,57 per item
Description
Both varieties are often decided by harm to the corresponding central ocular motor coordination and integration centres treatment lyme disease kytril 2 mg cheap line. Similarly medications narcolepsy generic kytril 2 mg on-line, she is having issues making out which course the sound of a moving object is coming from treatment 4 ringworm kytril 2 mg on-line. She can due to this fact not say without trying medicine cups 2 mg kytril cheap visa, when standing on a platform, from which direction a practice is pulling into a station. When requested, she reviews that she has suffered for 10 years from right-sided headaches and right-sided tinnitus. Further diagnostics the signs described by the affected person are recognized with a special take a look at, during which the distinction in signal transit time from both ears is measured. This also reveals a slight asymmetric hearing loss within the low-frequency vary (500 Hz). Further processing and interpretation of the tones perceived here as language or melody takes place in the adjoining secondary cortical areas. Moreover, the auditory system is important for the conveying of information and feelings. The close link between hearing and speech is especially evident in early childhood development, when language growth may be delayed and even made inconceivable by harm to the auditory system. Serving as acoustic stimuli are sound waves, that are characterised by their frequency (measured in hertz [Hz]) and their amplitude (measured in decibels [dB]). The wholesome ear can understand frequencies between 18 Hz and 18 kHz, with the main speech vary mendacity between 250 and four,000 Hz at an depth of 40�80 dB. It is essential to realise, in contrast to the general fundamental understanding of a stimulus-receiving organ, that the Pars cochlearis not 13. The sound is initially acquired via the air by the auricle, then carried out to the eardrum, strengthened by the auditory ossicle chain, and finally broadcast to the inner ear. These efferents originate from the superior olivary complicated and are referred to as the olivocochlear bundle. In the process, the fibres ending on the inside hair cells come out of the ipsilateral part of the lateral superior olivary complicated; the fibres of the outer hair cells have their origins as a substitute in the contralaterally located medial superior olivary complicated. This results in a tonotopic impulse launch, which can also be represented over the ganglion cells as a tonotopic stimulus transmission in the entire auditory system in addition to in the major auditory cortex. The auditory system is structured tonotopically all through: � In the stimulus receiving organ, the cochlea, the world close to the base, is stimulated by high frequencies, the area near the apex by low frequencies. In the case of a conductive hearing loss, conduction of sound in the outer ear or in the center ear is adversely affected. Here, the air conduction of the sound is affected, whereas the bone conduction remains intact. Strictly talking, this hearing loss can have a sensory trigger (inner ear within the narrower sense) or a neuronal trigger, i. The Nucleus cochlearis anterior transmits the impulses obtained by it, almost unchanged, in the direction of the ipsilateral and contralateral superior olivary complicated. The crossing fibres thereby form a strong fibre bundle, the trapezoid body (Corpus trapezoideum), in order that in individual nuclei, the Nuclei corporis trapezoidei, a further conversion, could be carried out. The axons of the Nucleus cochlearis posterior, in distinction, cross fully to the other side and directly attain the Colliculi inferiores in the Tectum mesencephali through the Lemniscus laterales, with out being transformed (direct auditory system). Already on the degree of the brainstem or in the superior olivary advanced, information from each inside ears converges respectively, which types the anatomical basis for directional hearing. The superior olivary complex is the crucial hub of the oblique auditory system and consists of the Nuclei olivares superiores and the Nuclei perioli vares. The lateral part sends out the next efferents: � to the Colliculi inferiores � for acoustic reflexes additionally to the center ear muscular tissues, to the M. The Colliculi inferiores are divided tonotopically from lateral to medial in accordance with the ascending frequency arrangement. They are related through the Commissura colliculi inferiores, so that a binaurally perceived impulse stimulus may be exchanged. The Colliculi inferiores are additionally referred to as the auditory reflex centre, during which responses from the physique, that are triggered by noises. Via the Brachium colliculi inferiores the efferents of this 3rd neuron continue to the Table 13. Each cochlear nucleus exhibits tonotopy with an ascending frequency association from low to excessive in an anterior�posterior orientation. It is right here that awareness of tones, sounds and simple acoustic patterns takes place. Words, language or melodies are solely processed in the adjoining secondary au- ditory cortex. This is situated in the dominant hemisphere, whereas the analogue space within the nondominant hemisphere tends to serve nonrational processing and interpretation of speech. In addition to the auditory system, described within the narrower sense, it must also be identified that descending cortical tracts join all stations of the auditory system to one another. There are 745 13 Functional methods due to this fact fibres which run preferentially from lamina V of the first auditory cortex to the ipsilateral Colliculus inferior. It is thought that these corticofugal fibres � triggered by acoustic studying processes � induce a restructuring of subcortical structures, contributing to the selective processing of acoustic stimuli which is important for behaviour. Diagnosis the findings (nystagmus of the wholesome facet in addition to the squinting and head-tilting to the side of the lesion) counsel an acute peripheral lesion of the vestibular system, similar to can happen in the case of damage within the peripheral course of the N. Treatment and additional steps the patient is handled with intravenous steroid administration. Words and phrases, nevertheless, are often altered pointlessly (paraphasia) and even invented (neologisms), whereas the sentence melody and emphasis stay extant. Patients can often hardly make themselves understood, but are often not conscious of their speech disorder and subsequently leave a misunderstanding of common confusion. This applies to objects, but after all additionally in abstract type to the written word, which is seen, however can now not be learn accurately. The latter describes a studying disorder (alexia) and, consequently, additionally a writing disorder (agrafia). The vestibular nuclei in the Medulla oblongata form a key integration centre, which enables fast adaptation within the case of a modified body place or movement. This adaptation is carried out unconsciously and in addition without direct cortical configuration. A further configuration through the thalamus to the cortex is important for awareness of visual impressions, as in different sensory techniques too. However, no major cortical system may be positively named for the vestibular system. Instead, up to 10 totally different areas concerned in impulse handling are debated, together with the Sulcus intraparietalis, the parieto-insular cortex, the somatosensory cortex or the hippocampus. In the process, the macular sensory cells perceive linear acceleration and the ampullary sensory cells understand rotational acceleration, that are registered by way of the move of endolymphatic fluid in the vestibular system. They correspond to modified epithelial cells and are referred to as secondary sensory cells. A deflection of apical stereocilia through the fluid motion of the endolymph within the course of the edge of the marginal kinocilium of the sensory cells results in hyperpolarisation, deflecting away from the kinocilium to a depolarisation. The vestibular hair cells are innervated by bipolar ganglion cells of the Ganglion vestibulare, of which the centrally-directed axon runs within the N. Clinical case Peripheral lesion of the vestibular system A 45-year old patient presented in a clinic with vertigo and vertical double vision. Initial examination During the examination, along with a spontaneous onset of horizontal nystagmus (typically a two-phase, involuntary eye movement) to the proper, a downwards-oriented squinting of the left eye in addition to a left inclination of the pinnacle are additionally famous. Further diagnostics A caloric testing of the left vestibular system shows no response. Via the inferior cerebellar peduncle (Corpus juxtarestiforme), nonetheless, a small a half of the fibres 746 thirteen. Finally, the Nuclei vestibulares are important integration nuclei for proprioceptive, optical and vestibular impulses. They project from their location into the Medulla oblongata or into the caudal section of the pons ventral to the Pedunculus cerebellaris inferior and superior respectively. In the vestibular nuclei, nonetheless, other afferents also converge, significantly from the Nuclei fastigii from the vestibulocerebellum, bilateral projections from the spinal cord (which, amongst others, run within the tracts of the posterior funiculus), and afferents from the Nucleus spinalis nervi trigemini. Likewise, from a fantastic variety of elements of the central nervous system, optical impulses are for instance transmitted indirectly through the Formatio reticularis to the vestibular nuclei. Incoming info is processed within the vestibular nuclei to have the ability to ultimately influence holding and supporting motor function. Uncrossed and somatotopically structured, it runs right up into the sacral spinal cord and ends directly or indirectly on the - or -motorneurons in the anterior horn.
Ngu Mei Gee (Schisandra). Kytril.
- Dosing considerations for Schisandra.
- Vision problems, preventing premature aging, preventing motion sickness, diabetes, high blood pressure, and other conditions.
- Improving concentration, coordination, and endurance.
- What is Schisandra?
- Are there any interactions with medications?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96390
These values can be utilized to help determination making about which blood merchandise or antifibrinolytics are required to appropriate coagulation medicine go down purchase kytril 2 mg line. K worth is the time from the end of R till the clot reaches 20mm (speed of clot formation) symptoms diverticulitis 1 mg kytril cheap with amex. The -angle represents the conversion of fibrinogen to fibrin medicine balls for sale 1 mg kytril order visa, and due to this fact a depressed -angle is usually treated with cryoprecipitate medications used to treat adhd kytril 2 mg cheap overnight delivery. A disposable pin is a ached to a shaft which is related to a skinny spring and slowly oscillates forwards and backwards. Movement originates from the pin and not the cup, and the sign is transmi ed utilizing an optical detector as an alternative of a torsion wire. The advantage of those displays over formal laboratory checks of coagulation is the speed at which the outcomes are obtained, permitting correction of coagulopathies extra promptly and with the proper products. Regular calibration, correct use and understanding of results are key to their protected and effective use. This is particularly true of patients recognized to have antibodies (inhibitors) to the factor in query. The use of desmopressin could also be related to water retention and, potentially, acute hyponatraemia. Thrombocytopenia Thrombocytopenia is usually defined as a platelet count < 100 � 109 L�1; nonetheless, the point at which thrombocytopenia becomes essential clinically depends upon the state of affairs. I t could be caused by a discount in platelet manufacturing (or elevated platelet breakdown; see Table 14. I n such instances the dangers of transfusion should be weighed in opposition to the risks of bleeding. Acquired coagulopathies A cquired coagulopathy can also happen as an acute event, such as after main trauma, throughout main haemorrhage or in the presence of disseminated intravascular coagulopathy (D I C). I n main haemorrhage, clo ing factors can turn out to be depleted if not replaced promptly. The management of coagulopathy in main haemorrhage must be guided by scientific urgency and laboratory checks. Trauma-induced coagulopathy Bleeding accounts for 30%�40% of all trauma-related deaths and normally occurs inside hours after harm. I n virtually half of haemorrhagic deaths after trauma, coagulopathy is implicated and is extremely preventable. A cute traumatic coagulopathy presents instantly after damage and continues all through the resuscitation part. Genetic factors, tissue irritation and current comorbidities additionally contribute to the coagulopathy. The pathophysiological production of so many fibrin clots ends in a consumptive coagulopathy, rendering the patient susceptible to haemorrhage on account of surgery or different invasive procedures. They are more likely to want alternative of consumed coagulation factors in the form of platelets, contemporary frozen plasma and cryoprecipitate. Drug-induced coagulopathies the rise in numbers of interventional cardiology procedures has been accompanied by an ever-increasing variety of out there anticoagulant medication. I f surgical procedure is required urgently, it may be essential to reverse the consequences of anticoagulant therapy acutely. This should be carried out under the steering of a haematologist, but in the case of heparin could involve the use of protamine. Vitamin K takes hours to work and should be given on the similar time to scale back the danger of postoperative coagulopathy. I n less pressing situations, vitamin K could be given alone or the warfarin merely stopped for a number of days. D abigatran is an exception as a reversal agent (idarucizumab) is available; this might be given if severe bleeding occurs or if urgent surgical procedure is required. I n acute circumstances the place drugs are thought to be affecting platelet function, platelet transfusions could also be thought of. Interventional procedures and regional anaesthesia in coagulopathic patients I nterventional procedures such because the insertion of central venous catheters, epidural block or regional nerve blocks represent a big threat of haemorrhage or haematoma formation in coagulopathic sufferers. O f explicit notice are the risks of airway obstruction from failed jugular venous catheter insertion and paralysis attributable to epidural haematoma formation. I t is in all probability going that the routine use of ultrasound imaging has lowered the risks related to many procedures, however in profoundly coagulopathic sufferers it might nonetheless be advisable to resort to alternative, safer methods; for example, central venous catheterisation of the femoral vein may be preferable to the subclavian or inner jugular routes. The degree of coagulopathy at which varied procedures could be thought of protected is far from clear. There are specific issues when the impact of a drug on coagulation is difficult to measure instantly. There are several consensus statements on the security of neuraxial blockade in differing circumstances. Available pointers are incomplete, difficult to extrapolate to different se ings. When in doubt, senior anaesthetic and/or specialist haematology advice ought to be sought. Mechanical strategies include antiembolism stockings and foot-impulse or pneumatic compression gadgets (both stockings and compression gadgets may be thigh or knee length). There may be very li le evidence to assist the usage of anybody mechanical system somewhat than the alternate options. Mechanical methods will not be applicable in sufferers with damaged pores and skin, peripheral neuropathy oedema, peripheral, arterial illness or other situations by which fi ing the devices could be problematic or trigger injury. Blood merchandise and blood transfusion the transfusion of complete blood is comparatively unusual, and donated blood is normally separated into its constituent components, that are then out there for transfusion. A wide range of blood merchandise are available, the most common of that are listed in Table 14. Units of packed pink cells are mostly transfused through the resuscitation of acute haemorrhage or as a treatment of symptomatic anaemia. It may be related to worse outcomes when utilized in certain situations corresponding to traumatic mind harm. Red cell concentrates are commonly leukocyte depleted and resuspended to a haematocrit of zero. These components are designed to lengthen the safe storage period, and packed red cells are stored refrigerated at 4�C. Red cell storage lesion A variety of biochemical and immunological adjustments happen during red cell storage which can have clinical impact. O nce thawed to room temperature it have to be transfused inside 4h; however, it may be saved at 4�C for 24h. I t is usually given in prepooled concentrates of five models; each individual unit is from a separate donor. Cryoprecipitate is saved frozen and defrosted for use, and pooled concentrates must be transfused within 4h of thawing. Platelet transfusions could either be pooled from several donors or obtained from a single donor by apheresis. They are stored in temperature-controlled incubators at 20�C�24�C with constant agitation. The shelf lifetime of a bag of platelets is 5 days (7 days if bacterial screening has been performed). A zero-tolerance approach to pretransfusion sampling, blood product checking and administration is beneficial. I t ought to end result within the quick launch and administration of blood elements for preliminary resuscitation with out prior approval from a haematologist. S uch protocols work greatest when particular to scientific areas such as the emergency department, maternity unit, or in clinical situations similar to trauma or major intraoperative haemorrhage. Their activation should also mobilise other sources corresponding to additional workers such as porters, blood warmers, stress infusers and cell salvage devices. Children and women of childbearing age must receive O Rh-negative blood, whilst males and older women can even obtain O Rh-positive. I f potential, the transfusion of red cells and clo ing merchandise ought to be guided by laboratory results or by nearpatient testing. However, ready for affirmation of coagulopathy before administering applicable therapy is prone to result in greater blood loss, use of more blood products and worse consequence. The administration of two swimming pools of cryoprecipitate and one grownup dose of platelets must be considered till take a look at results are available and bleeding controlled.
Specifications/Details
Obesity pathophysiology medicine xyzal order kytril 2 mg fast delivery, comorbidity and anaesthetic management Airway the airway of the obese affected person should be approached with warning premonitory symptoms kytril 1 mg order mastercard. Traditional educating and audits of nationwide practice counsel that airway management in weight problems is more likely to medications similar to lyrica 2 mg kytril purchase otc be troublesome treatment vaginal yeast infection 2 mg kytril discount with amex. The affiliation of a large stomach and increased neck circumference with the presence of a beard increases the danger of difficulty. Beard elimination earlier than surgical procedure could have to be thought of to facilitate protected airway management. This happens at all levels from oropharynx to vocal cords, causing narrowing and reduction in airway diameter. The key part of positioning is to place the affected person in the reverse Trendelenburg place with the tragus of the ear degree with the manubrium sterni. Airway adjuncts S imple adjuncts such as oral and nasopharyngeal airways ought to be used routinely. Their routine use in the morbidly overweight affected person stays controversial, specializing in considerations round pulmonary aspiration and optimisation of pulmonary operate. S tandard laryngoscopes and blades remain the default tools for tracheal intubation in obese sufferers. Videolaryngoscopes could assist if extra danger components for troublesome tracheal intubation are present (see Chapter 23). Many are designed with short-handled bodies which could be useful if a big chest and glued neck posture limit house. Respiratory system Anatomy the lung fields of overweight patients usually look small when assessed by chest radiography. This is an artefact of accommodating the patient onto the plate for the radiograph. This perform will change with location of fats mass, patient place and presence of different pathological circumstances. A dipose deposition across the chest wall and in breast tissue results in decreased chest wall compliance and damping of the natural recoil and expansion. A bdominal wall infiltration and raised intra-abdominal strain with peribronchial and parenchymal fa y infiltration further exacerbate this. Respiratory muscles reveal fats infiltration, which, when mixed with results from inflammatory mediators, ends in diminished muscle power and respiratory endurance. Pathophysiology � Total lung capability and vital capacity decrease in a linear method with rising weight. At higher levels of morbid weight problems, tidal ventilation may impinge on closing volume even within the standing position. This leads to a doubling of metabolic price in contrast with lean individuals, causing elevated oxygen consumption and carbon dioxide manufacturing. The energy price of sustaining adequate minute ventilation is mitigated by a discount in tidal quantity, leading to fast, shallow respiration at rest. This displays each the decreased elasticity of chest wall and parenchymal tissue and tidal ventilation occurring at decrease lung volumes. This could also be because of multiple factors: � external compression from parenchymal fat deposition; � reduction in the part of the lung quantity at which tidal breathing happens; and � continual inflammatory modifications and elevated easy muscle reactivity/bronchospasm. The penalties of these adjustments for the anaesthetist embody: � shortened apnoea to desaturation time; � increased oxygen necessities; � increased shunt fraction and ventilation/perfusion mismatch; � increased work of respiration leading to issue with spontaneously respiratory general anaesthesia strategies; and � elevated incidence of atelectasis. Obstructive sleep apnoea S leep and related loud night breathing is a normal physiological course of. S noring happens as a end result of gentle tissue collapse of the higher airway and vibration of these tissues and associated turbulent airflow. S noring turns into irregular when related to apnoeas and hypopnoeas to produce obstructive sleep apnoea (O S A). O bstructive sleep apnoea happens in as much as 60% of obese individuals; the vast majority of these cases are undiagnosed. D evelopment of hypertension, myocardial ischaemia and failure, strokes and sudden cardiac dying are increased. Patients within the perioperative interval will acquire an irregular sleep cycle because of anaesthesia, surgical procedure and administered medication; this has adverse results. I t is well validated, and its use is supported by experts in bariatric anaesthesia. O ptimising patient position, deep neuromuscular blockade and limiting pneumoperitoneum pressures all reduce the opposed consequences. Postoperatively, balanced analgesia (including using regional techniques), avoiding long-acting opioid administration, fast mobilisation, and use of incentive spirometry and physiotherapy may mix to cut back respiratory morbidity. This lower highlights the comparatively poor vascular provide to peripheral adipose tissue (<150mlkg�1 min�1). Echocardiographic proof means that three pathological pa erns predominate in weight problems: 1. Concentric hypertrophy (ventricular hypertrophy with elevated relative wall thickness) 3. Eccentric dilated hypertrophy (thickened hypertrophic left ventricle wall however lowered wall/cavity ratio secondary to dilatation). The practical utility of those states is the popularity of the early existence of lowered ventricular wall compliance and ventricular diastolic dysfunction. Conduction anomalies are widespread and relate either to fa y infiltration and fibrosis of the conduction system or underlying coronary artery disease. I n scientific follow, care have to be taken with drug administration which will have a unfavorable influence on conduction defects. Vascular illness A rterial illness is related to both major weight problems and its comorbidities (hyperlipidaemia, diabetes mellitus, and so forth. Hypertension is widespread and contributes to the event of left ventricular hypertrophy and failure. O besity-associated vascular illness is associated with improvement of coronary artery illness, myocardial infarction and sudden dying. There is an increased risk of progression to cardiac failure as a half of this process. Gastrointestinal A dipose tissue in the liver is highly metabolically lively endocrine and paracrine tissue. I nsulin resistance contributes to dyslipidaemia, hyperglycaemia and eventual pancreatic islet cell burnout. N on-alcoholic fa y liver disease alone or as a part of the metabolic syndrome (see earlier) is related to accelerated atherogenesis, ischaemic heart disease and elevated cardiovascular mortality. O besity-related increases in cardiac output and blood quantity will alter plasma concentrations, drug clearance and half-life of many agents. Pathophysiological adjustments in obesity (mainly renal and hepatic) lead to a higher drug clearance. Effect of increasing weight problems Increase Increase Increase Increase Variable Decrease Intravenous anaesthetic brokers Because of the physiological adjustments described earlier (particularly blood quantity and cardiac output), an i. Use of these scalar models may result in either unintended consciousness or overdose of agent. Great care should be taken when utilizing this method and depth of anaesthesia monitoring use is advocated. The majority of bariatric anaesthetists choose brokers that are much less lipid soluble, such as desflurane and sevoflurane, which have faster onset and offset than different brokers, providing earlier return of airway reflexes (see Chapter 3). S uxamethonium-associated fasciculations will also increase oxygen consumption and lead to a shortened apnoea time. Morbidly overweight patients have elevated pseudocholinesterase activity and a bigger immediate distribution volume. Sugammadex S ugammadex offers the flexibility to rapidly reverse rocuronium and vecuronium and return full neuromuscular function. O ptimisation of medical situations early in the preoperative interval will facilitate a clean perioperative interval. S hortacting, simply reversible brokers should be administered to facilitate speedy reversal of anaesthesia, return of airway reflexes and early mobilisation. Regional anaesthesia has been proposed as a safer different to general anaesthesia. However, even with ultrasound guidance, regional methods may be technically challenging, and failure is more common. Notable anaesthetic issues embody the following: � Always carry out the chosen anaesthetic approach within the working room. Perioperative threat in obesity Traditionally, obesity is considered a perioperative risk.
Syndromes
- Diabetes
- Nephrocalcinosis
- Shyness or embarrassment about asking for whatever type of stimulation works best
- Birth control pills
- Use a clean, sharp nail trimmer.
- A moisturizing balm to prevent the lips from becoming too dry may also help.
- Your heart is stopped while you are connected to this machine.
- Muscle weakness
Related Products
Additional information:
I t may subsequently be helpful throughout main surgical procedure in patients with cardiac disease medications medicare covers 1 mg kytril cheap free shipping. I t is six to eight times less potent than vecuronium but has approximately the same molecular weight; consequently medications given for adhd kytril 1 mg buy generic on-line, a larger number of drug molecules could reach the postjunctional receptors inside the first few circulations medications vascular dementia kytril 1 mg cheap line, enabling sooner improvement of neuromuscular block medications related to the female reproductive system kytril 2 mg buy. I n such doses, nevertheless, rocuronium is a really long-acting drug, lasting about 90min. The drug stimulates li le histamine release or cardiovascular disturbance, though in high doses it has a mild vagolytic property which generally results in an increase in coronary heart fee. The drug is excreted unchanged within the urine and in the bile, and thus the length of action may be increased by severe renal or hepatic dysfunction. A naphylactic reactions are more common after rocuronium than after different aminosteroid neuromuscular blocking medicine. They occur at an analogous price to anaphylactic reactions to atracurium and mivacurium. Rapacuronium bromide Rapacuronium bromide was the final aminosteroid to turn into available. Prior administration of suxamethonium potentiates the effect and prolongs the length of motion of non-depolarising medication. Concomitant administration of a potent inhalational agent will increase the length of block. This is most marked with the ether anaesthetic agents similar to isoflurane and sevoflurane but occurs to a lesser extent with halothane. Metabolic and, to a lesser extent, respiratory acidosis extend the duration of block. With monoquaternary amines corresponding to vecuronium, this effect is produced by the ionisation, under acidic circumstances, of a second nitrogen atom within the molecule, making the drug more potent. Hypothermia potentiates block as a end result of impairment of organ perform delays metabolism and excretion of these drugs. A low serum potassium concentration potentiates neuromuscular block by changing the value of the resting membrane potential of the postsynaptic membrane. A decreased ionised calcium concentration also potentiates block by impairing presynaptic acetylcholine release. In this illness, the number and half-life of the postsynaptic receptors are reduced by autoantibodies produced in the thymus gland. The number of twitches detectable after the burst of tetanus is referred to as the post-tetanic count. The mostly used anticholinesterase during anaesthesia is neostigmine, however edrophonium and pyridostigmine are also obtainable. These carbamate esters are water-soluble, quaternary ammonium compounds which are absorbed poorly from the gastrointestinal tract. The more lipid-soluble tertiary amine, physostigmine, has an identical impact and is extra suitable for oral administration but crosses the blood�brain barrier. O rganophosphorus compounds, that are used as poisons in farming and in nerve gas, additionally inhibit acetylcholinesterase, but not like other agents, their impact is irreversible; recovery happens only on technology of more enzyme, which takes some weeks. I n this disease the affected person possesses antibodies to the postsynaptic nicotinic receptor, reducing the efficacy of acetylcholine. The use of these medicine is thought to enhance the amount and period of action of acetylcholine on the neuromuscular junction, thus enhancing neuromuscular transmission. Neostigmine N eostigmine combines reversibly with acetylcholinesterase by formation of an ester linkage. N eostigmine is excreted largely unchanged via the kidneys and has a half-life of about 45min. These cholinergic effects could additionally be reduced by simultaneous administration of an anticholinergic agent such as atropine or glycopyrronium bromide. I t takes no much less than 2min to have an initial impact, and recovery from neuromuscular block is maximally enhanced by 10min. The impact is due to this fact extra brief lived than with neostigmine, of the order of only some minutes. Edrophonium has a quicker onset of action than neostigmine, producing signs of restoration within 1min. However, its effects are extra evanescent; when edrophonium is given within the presence of profound neuromuscular block, the degree of neuromuscular block might enhance after an preliminary interval of restoration. Pyridostigmine Pyridostigmine has a slower onset time than neostigmine or edrophonium and likewise an extended duration of motion. I t is used extra usually as oral remedy in sufferers with myasthenia gravis than in anaesthesia. Physostigmine Physostigmine, an anticholinesterase also identified as eserine, is a tertiary amine and is more lipid soluble than the opposite carbamate esters. I t is due to this fact absorbed extra easily from the gastrointestinal tract and in addition crosses the blood�brain barrier. Organophosphorus compounds O rganophosphorus compounds are irreversible inhibitors of acetylcholinesterase; by phosphorylation of the enzyme, they produce a really stable complex which is proof against reactivation or hydrolysis. Muscarinic results corresponding to salivation, sweating and bronchospasm are combined with nicotinic effects, corresponding to muscle weakness. Central nervous results such as tremor and convulsions might occur, as might unconsciousness and respiratory failure. Reactivators of acetylcholinesterase are used to treat this form of poisoning; they embody pralidoxime and obidoxime. Carbamates corresponding to pyridostigmine are used prophylactically in these threatened by chemical warfare with these compounds. Ecothiopate is an organophosphorus compound with a quaternary amine group; it was used as an eyedrop preparation in ophthalmology to produce miosis in narrow-angle glaucoma. I t inhibits cholinesterase by phosphorylation and thus potentiates all esters metabolised by this enzyme. Cyclodextrins Sugammadex A nticholinesterases, though used routinely in anaesthetic apply, are recognised to have disadvantages. Their muscarinic results may be disadvantageous in sufferers with a history of nausea and vomiting or in the presence of cardiac arrhythmias or bronchospasm. S ugammadex, a -cyclodextrin, was designed to encapsulate rocuronium (and to a lesser extent vecuronium) within the plasma, stopping its access to the nicotinic receptor and inspiring dissociation from it. The complicated of sugammadex and rocuronium is excreted within the urine and has no muscarinic effect; the use of anticholinergic brokers is unnecessary. S ugammadex has a low incidence of opposed results, although hypersensitivity rashes, anaphylaxis and bradycardia have been reported. The negatively charged hydrophilic chains on the outside of the molecule entice rocuronium to the core of the toroid. A ll require the applying to a peripheral nerve of a current of as a lot as 60mA for a fraction of a millisecond (often zero. Usually a nerve which is readily accessible to the anaesthetist, such because the ulnar, facial or frequent peroneal nerve, is used. The muscle response to the nerve stimulus could then be assessed by either visual or tactile means, or it might be recorded by more refined methods. Mechanomyography A strain-gauge transducer may be used to measure the pressure of contraction of, for instance, the thumb, in response to stimulation of the ulnar nerve on the wrist. A ccurate measurements of the twitch or tetanic response may be made, although the hand should be splinted firmly for reproducible results. A lthough primarily a analysis tool, there are several simple scientific instruments which give a much less accurate but similar recording. Two recording electrodes are placed over the muscle on the hand; the distal one lies over the motor level. Modes of stimulation S everal totally different rates of stimulation may be applied to the nerve in an a empt to produce a sensitive index of neuromuscular operate. I n isolation, such a stimulus is of restricted worth, although if applied repeatedly earlier than and after a dose of a neuromuscular blocking, agent, it may be possible to assess crudely the results of the drug. S uch charges of stimulation have the profit of being much less painful than tetanic stimulation, with no untoward results after recovery from anaesthesia. The ratio of the amplitude of the fourth to the primary twitch is identified as the train-offour ratio. I t is assumed that a minimal of three of the four twitches must be absent to obtain adequate surgical entry for higher abdominal surgery. Full reversal can solely be relied upon if no less than the second twitch is visible when an anticholinesterase is given.
Usage: q.h.
Complications and difficulties Complications and difficulties can embrace the next: � slower induction of anaesthesia; � problems notably during stage 2 of anaesthesia (see later) medications during labor purchase kytril 1 mg fast delivery, when stimulation of the pharynx or larynx could end in laryngeal spasm; � airway obstruction or bronchospasm; and � environmental air pollution treatment alternatives for safe communities kytril 2 mg line. This is the stage attained when utilizing nitrous oxide 50% in oxygen medicine zalim lotion purchase kytril 2 mg line, as used within the strategy of relative analgesia medicinenetcom symptoms 2 mg kytril generic with visa. Respiration is erratic, breathholding might happen, laryngeal and pharyngeal reflexes are lively and stimulation of pharynx or larynx. This deepens via 4 planes (in follow, three: mild, medium, deep) with increasing focus of anaesthetic drug. Respiration assumes a rhythmic pattern, and the thoracic component diminishes with depth of anaesthesia. Withdrawal of the anaesthetic agents and administration of one hundred pc oxygen lightens anaesthesia. A ll drugs that may be required at induction should be prepared beforehand and a cannula inserted into a suitable vein. A vein within the forearm or on the back of the hand is preferable; veins within the antecubital fossa ought to be avoided because of the risks of intra-arterial injection and issues with elbow flexion. A fter selection of a suitable vein and skin preparation with 2% chlorhexidine in alcohol, s. Transparent cannulae dressings are most well-liked to allow regular inspection of the pores and skin entry website. Preoxygenation of the lungs might start, utilizing a close-fi ing face-mask and 100 percent oxygen delivered by an acceptable respiration system for 3�5min. Preoxygenation earlier than routine elective induction of anaesthesia minimises the risk of transient hypoxaemia earlier than establishment of efficient lung air flow (see Chapter 23). S low injection is recommended within the older affected person and in these with a sluggish circulation time. A rapid-sequence induction approach is indicated for patients undergoing emergency surgical procedure and for those with potential for vomiting or regurgitation (see Chapter 23). Complications and difficulties Complications and difficulties can embody the next: � Respiratory despair. Slow injection of an induction agent can scale back the extent of respiratory despair. Respiratory adequacy have to be assessed carefully, and the anaesthetist must be able to help air flow of the lungs if essential. This is prone to occur notably in the older, hypovolaemic or untreated hypertensive affected person. Thiopental in particular might cause release of histamine with subsequent formation of typical wheals. Severe reactions may occur to particular person agents, and appropriate medication and fluids must be out there within the anaesthetic room for treatment. Maintenance of anaesthesia A naesthesia could also be continued using inhalational agents, i. Regional anaesthesia may be used to supplement any of those strategies to achieve the elements of the acquainted anaesthetic triad of hypnosis, neuromuscular blockade and analgesia. Conduct A fter induction of anaesthesia, a mixture of nitrous oxide or air in oxygen supplemented with a risky anaesthetic agent is used, with the patient respiratory spontaneously. Tracheal intubation could additionally be carried out underneath native anaesthesia (using topical spray. The ordinary strategy is to provide common anaesthesia and neuromuscular blockade to perform laryngoscopy and direct imaginative and prescient tracheal intubation, after which to preserve anaesthesia by way of the tracheal tube with spontaneous or managed ventilation. Inhalational technique for tracheal intubation A dequate depth of anaesthesia is important to depress the laryngeal reflexes and supply a degree of leisure of the laryngeal and pharyngeal muscle tissue. S evoflurane 8% provides rapid a ainment of the required depth, which could be judged from the pa ern of respiration with predominance of diaphragmatic respiratory (a useful check in youngsters is the dissociation of the thoracic and belly excursion). The anaesthetic circuit is then related to the tracheal tube and anaesthesia maintained at a depth appropriate for surgery. Thus, the approach is suitable for: main abdominal, intraperitoneal, thoracic or intracranial operations; extended operations in which spontaneous air flow would result in respiratory melancholy; and operations in a position during which ventilation is impaired mechanically. A ssisted air flow is maintained by way of the face-mask till neuromuscular blockade is enough as measured by train-of-four monitoring; laryngoscopy and tracheal intubation are then carried out. O therwise managed ventilation is commenced, first manually by compression of the reservoir bag and then by a mechanical ventilator delivering the appropriate tidal and minute volumes. A naesthesia and analgesia are provided by nitrous oxide/oxygen or air/oxygen, together with a unstable inhalational agent and i. The inspired and end-expired concentrations of unstable anaesthetic brokers should be monitored. A nalgesia can also be supplemented by analgesic premedication or by use of regional or local anaesthetic techniques (see Chapter 25). Adequacy of anaesthesia Autonomic reflex exercise with lacrimation, sweating, tachycardia, hypertension or reflex motion in response to surgical procedure point out inadequate depth of anaesthesia or inadequate analgesia. Adequacy of neuromuscular blockade Clinical signs of return of muscle tone include retraction of the wound edges throughout stomach operations and abdominal muscle, diaphragmatic or facial movement. A n increase in airway pressure (with a time- or volume-cycled ventilator) can also point out a return of muscle tone. Q uantitative estimation of neuromuscular block ought to be obtained with a peripheral nerve stimulator and train-of-four monitoring. Reversal of neuromuscular blockade At the top of surgery the degree of neuromuscular block must be reassessed and residual neuromuscular blockade antagonised (see Chapter 8). The pharmacokinetic and pharmacodynamic profiles of agents such as propofol and remifentanil (fast onset and offset times) permit speedy titration of drug dose to the required effect in individual patients (see Chapter 1). O nly Leur-Lock syringes must be used to assist stop disconnection from giving sets. Checks to make positive that a secure mains connection and an operational ba ery backup exist should be completed. Care have to be taken to guarantee accurate affected person information are entered and this system applies to the drug contained in the syringe actually a ached to it. Patient positioning for surgery Patient positioning for surgery A fter induction of anaesthesia, the affected person is positioned on the working table ready applicable for the proposed surgical procedure. When positioning the patient, the anaesthetist ought to keep in mind surgical access, patient security anaesthetic technique, monitoring and place of i. Each may have adverse results by means of skeletal, neurological, ventilatory and circulatory results. Femoral and obturator nerves may be stretched by overextension of the hips or surgical group members leaning on the thighs. The common peroneal nerve could be compressed if the lateral knee rests in opposition to the stirrup bar. Variations of the susceptible place embody the (C) knee-chest (pressure areas at risk are highlighted in red) and (D) jack-knife positions. Movement or slippage of the patient may also lead to harm from the robotic arms. Complications of positioning throughout anaesthesia are discussed in more detail in Chapter 26. Carries the risk of aortocaval compression throughout pregnancy (see Chapter 43) or in sufferers with a large stomach mass. May produce upward pressure on the diaphragm because of the load of the abdominal contents. Damage to the brachial plexus may happen because of stress from shoulder supports, especially if the arms are kidnapped. Differ in the diploma of hip and knee flexion, however each could lead to nerve injury on the medial or lateral facet of the leg from strain exerted by the stirrups, which should be nicely padded. Care should be taken to elevate both legs simultaneously so that pelvic asymmetry and resultant backache are avoided. The sacrum should be supported and never allowed to slip off the top of the working table. The pelvis and shoulders have to be supported to forestall the affected person from rolling either backwards (with a threat of falling from the table) or forwards into the restoration position. The commonest specialised place; its protected management requires handbook dealing with teamwork and specialist gear. Prone positioning underneath common anaesthesia requires numerous physiological and practical points to be thought of: � Cardiovascular Decreased venous return could be attributable to stomach compression or venous pooling in the legs. Traction accidents to the brachial plexus are possible with in depth abduction of the arms within the ahead position.
Tags: kytril 1 mg cheap on-line, 1 mg kytril generic visa, kytril 1 mg online buy cheap, 2 mg kytril generic overnight delivery, buy kytril 1 mg with mastercard, kytril 2 mg order without a prescription, purchase kytril 2 mg online, buy discount kytril 1 mg on line, order kytril 1 mg online, cheap 2 mg kytril otc, 1 mg kytril visa, discount kytril 2 mg free shipping, kytril 2 mg buy visa, discount kytril 1 mg amex, kytril 2 mg fast delivery, kytril 2 mg buy cheap
9 of 10
Votes: 202 votes
Total customer reviews: 202
Customer Reviews
Muntasir, 29 years: The subunits have allosteric binding sites for exogenous ligands, and the binding traits of every subunit sort are genetically determined, allowing a variety of sensitivity to centrally acting hypnotics. The underlying rhythm and fee should be decided and the implications in case of pacemaker malfunction failure known to decide the need for backup help. Complex interactions at varied receptors underlie the completely different results of presently out there opioids.
Bradley, 28 years: Their axons run to parasympathetic ganglia within the space of the head or to ganglia within the body near to the organs. Whilst this reduces the bandwidth of the amplifier, such a compromise allows an interpretable signal free of baseline instability. Rauber/Kopsch � Topographie der Organsysteme, Systematik der peripheren Leitungsbahnen, Bd.
Tarok, 41 years: The tourniquet should be inflated to a pressure 100mmHg above systolic arterial stress. The synchronous depolarisation and extended motion potentials in cardiac muscle summate to generate a potential area of relatively greater amplitude. Sickle-cell disaster Patients with sickle-cell disease can present in crisis, where sickling of the haemoglobin results in vaso-occlusion and subsequent tissue hypoxia and necrosis.
Daryl, 39 years: Increasing degrees of depolarisation result in a graded response, with opening of Ca2+ channels and due to this fact growing 2+ tone. H, the place is fluid density g is acceleration because of gravity and H, is the peak of the column. They are therefore the first level at which the corresponding sensory tracts finish.
Abe, 45 years: Radiation is the major route of heat loss and is proportional to the distinction in temperature between the affected person and setting to the facility of 4. These methods are generally used as the sole anaesthetic for surgery however can be combined with general anaesthesia in appropriate sufferers. O ther states exist and may be encountered directly or not directly by anaesthetists, including plasma and non-classical states corresponding to glass and liquid-crystal.
