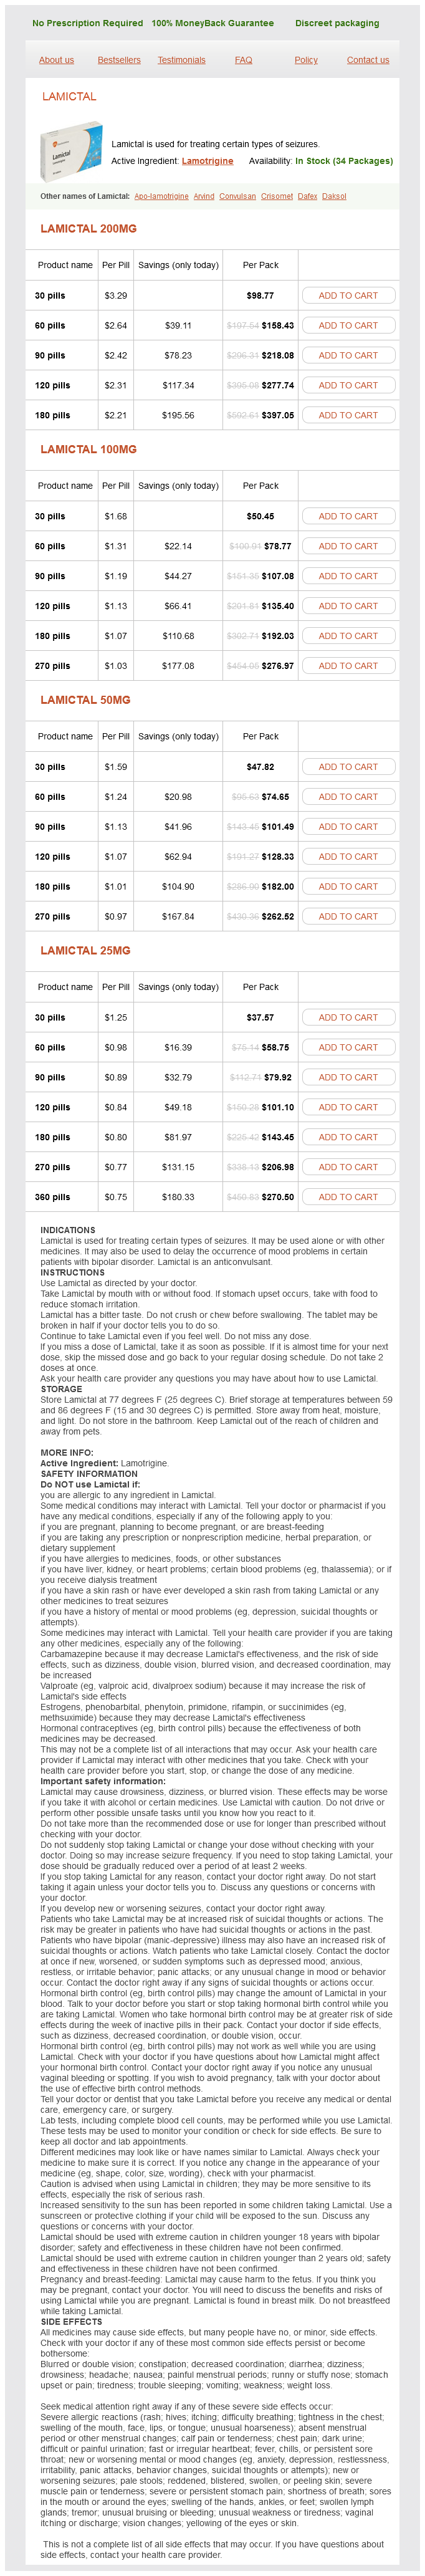
Lamictal 200mg
- 30 pills - $98.77
- 60 pills - $158.43
- 90 pills - $218.08
- 120 pills - $277.74
- 180 pills - $397.05
Lamictal 100mg
- 30 pills - $50.45
- 60 pills - $78.77
- 90 pills - $107.08
- 120 pills - $135.40
- 180 pills - $192.03
- 270 pills - $276.97
Lamictal 50mg
- 30 pills - $47.82
- 60 pills - $74.65
- 90 pills - $101.49
- 120 pills - $128.33
- 180 pills - $182.00
- 270 pills - $262.52
Lamictal 25mg
- 30 pills - $37.57
- 60 pills - $58.75
- 90 pills - $79.92
- 120 pills - $101.10
- 180 pills - $143.45
- 270 pills - $206.98
- 360 pills - $270.50
Lamictal dosages: 200 mg, 100 mg, 50 mg, 25 mg
Lamictal packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 662
Only $0,8 per item
Description
It is the remnant of the medial sling of the biceps after it pulls loose from its footprint on the lesser tuberosity directly adjoining to the footprint of the upper subscapularis medicine gustav klimt cheap lamictal 100 mg without prescription. This could be carried out by way of the anterosuperolateral portal with a Viper or Scorpion suture passer (Arthrex) loaded with a free no treatment using drugs safe lamictal 50 mg. The traction suture can then be held outside the cannula to permit continued use of the anterosuperolateral portal medicine daughter lamictal 25 mg buy generic line. The anterior release (subscapularis from the posterolateral coracoid and deltoid fascia) may be done by alternating the electrocautery with the shaver medicine bow 50 mg lamictal cheap free shipping. The launch is continued medial along the posterolateral coracoid until the subscapularis muscle belly is seen beneath the arch of the coracoid neck and base. A 30-degree arthroscopic elevator, introduced by way of an anterosuperolateral portal, is used to perform the superior release, lysing adhesions between the subscapularis and the coracoid neck and base. The launch is completed solely to the midpoint of the undersurface of the coracoid neck (to prevent damage to the neurovascular structures medial to the coracoid neck). The inferior release is probably the most harmful and has not been essential in our expertise. A ring curette may be used to exactly remove the soft tissues as a lot as the articular margin. An electrocautery probe is used to delineate a medialized footprint on the lesser tuberosity (A), and an influence burr burrs off the "charcoal" down to bleeding bone (B). This skeleton shows how the arm is held in 20 to 30 degrees of abduction and 20 levels of ahead flexion during shoulder arthroscopy in the lateral decubitus place. Photograph from the top trying downward exhibits how the combination of abduction, forward flexion, and regular humeral retroversion necessitates a "hand on face" place throughout anchor insertion into the lesser tuberosity. This "hand on face" position allows the surgeon to obtain an applicable "deadman" angle to insert suture anchors into the lesser tuberosity. The anchors must be placed so as from inferior (caudal) to superior (cephalad). One strand of suture is retrieved from the anchor, pulled out the anterosuperolateral cannula, and loaded within the suture passer. For the superior anchor, the sutures ought to be passed over the top of the superolateral border of the subscapularis, just medial to the "comma tissue. The double-diameter knot pusher permits the subscapularis tendon to be manipulated and held in the applicable place while every halfhitch of the knot is tied. Sutures from the upper anchor have been positioned at the junction of the vertically oriented comma tissue and the upper border of subscapularis tendon. Proper portal placement is imperative to obtain the proper angle of approach to work within the subcoracoid house. The key ideas include minimizing stress differentials (hypotensive anesthesia with sufficient arthroscopic pump pressure), avoiding turbulence, using the posterior lever push, and using each the 30- and 70-degree arthroscopes freely. The subscapularis tendon have to be securely apposed to the bone to optimize healing. Important biomechanical ideas embody the proper angle of insertion of the suture anchors; use of double-loaded anchors to scale back the load on each suture; use of sturdy sutures; proper suture placement in the tendon; and optimized loop and knot safety. The affected person must clearly understand what he or she can do to shield and optimize therapeutic of the subscapularis tendon restore. After the arthroscopic portals are closed, a sterile dressing is applied over the shoulder. During the primary 6 weeks the patient should perform day by day active wrist and elbow movement. The patient must not externally rotate past impartial (straight-ahead position) for six weeks. The patient is began on a passive stretching program that includes passive external rotation with a cane as much as forty five degrees and overhead stretches with a rope and pulley. At 12 weeks from the operation the affected person is started on a strengthening program with elastic bands. If the subscapularis tear is a part of a massive anterosuperior rotator cuff tear, then strengthening is delayed until 16 weeks postoperatively. Rehabilitation focuses on strengthening the scapular stabilizers and deltoid and rotator cuff muscular tissues. Eight of ten sufferers who had proximal humeral migration preoperatively had reversal of the migration and functional overhead use of their arm. Bennett2 also found encouraging ends in his prospective cohort with 2- to 4-year follow-up. Kim et al,9 in a recent report of sufferers who had an arthroscopic restore of isolated partial articular-sided tears, discovered similar enhancements in pain and performance. Arthroscopic repair of isolated subscapularis tears: a prospective cohort with 2- to 4-year follow-up. Intra-articular repair of an isolated partial articular-surface tear of the subscapularis tendon. Rupture of the tendon of the lengthy head of the biceps brachii: surgical versus nonsurgical remedy. Incomplete tears of the subscapularis tendon related to tears of the supraspinatus tendon: cadaveric and medical research. Histologic evidence of degeneration at the insertion of 3 rotator cuff tendons: a comparative research with human cadaveric shoulders. Chapter 12 Repair and Reconstruction of Acromioclavicular Injuries Amir Mostofi, Augustus D. Dislocations are categorized by severity of harm, radiographic findings, and place of the clavicle12 (Table 1). Indirect harm occurs by falling on an adducted outstretched hand or elbow, causing the humeral head to translocate superiorly and drive the humeral head into the acromion. The articular surface is made up of hyaline cartilage containing an intra-articular meniscus type of structure, all surrounded by a joint capsule with a synovial lining. Appreciating the location of the coracoclavicular ligament attachment on the clavicle is important. The trapezoid attaches on the undersurface of the clavicle at an anterolateral place. Because of the innervation by the lateral pectoral nerve, some sufferers may current with anteromedial pain, additional complicating the image. Pain at posterior aspect of shoulder or lateral shoulder would possibly point out different pathology. Radiographs of the lateral finish of the clavicle may be slightly elevated, but stress views fail to show a 100 percent separation of the clavicle and acromion. The higher extremity is usually held in an adducted position with the acromion depressed while the clavicle appears high-riding, but in actuality the acromion and the remainder of the upper extremity is displaced inferior to the horizontal airplane of the lateral clavicle. The distal clavicle is posteriorly displaced into the trapezius muscle and will tent the posterior skin. Severe droop secondary to anteroinferior translation of the scapula around the thorax, due to the load of the arm and the geometry of the chest wall. This is taken into account the third translation of the scapula with lack of the clavicular strut. The distal clavicle is present in two orientations, both subacromial or subcoracoid, behind the intact conjoined tendon. Mechanism is thought to be severe hyperabduction and exterior rotation of the arm mixed with retraction of the scapula. The conoid may be seen as a broad ligament that followers out, attaching to the clavicle in a posteromedial place. The width seen on radiographs is influenced by the individual variability of obliquity of the joint in relation to the x-ray beam. For optimal visualization of the acromioclavicular joint, the x-ray source is directed 10 degrees cephalad with reduced penetration power in comparability with a regular radiograph. It is helpful when a coracoid fracture is suspected with a traditional coracoclavicular interspace. Treatment begins with a sling, ice, and a short interval of immobilization only for pain control. The rehabilitation program consists of 4 phases:4 Pain management, immediate protecting range of motion and isometric workout routines Strengthening workout routines using isotonic contractions Unrestricted functional participation with the aim of accelerating power, power, endurance, and neuromuscular control Return to exercise with sports-specific functional drills Surgical intervention must be thought of after rehabilitation if ache persists for higher than 3 months. Objective research showed that patients had no limitation of shoulder movement within the injured extremity and no difference compared with the unaffected extremity in rotational shoulder muscle energy. If symptoms persist for higher than three months, including increased pain, impingement due to scapular dyskinesia, decreased energy, lack of ability to get the arm into a cocking place in throwing, and painful instability, particularly posterior instability with the clavicle abutting the anterior portion of the spine of the scapula, then operative intervention could additionally be indicated.
Thioctan (Alpha-Lipoic Acid). Lamictal.
- What is Alpha-lipoic Acid?
- Are there safety concerns?
- Treating type 2 diabetes.Improving symptoms such as burning, pain, and numbness in the legs and arms of people with diabetes.
- Treating a heart-related nerve problem called cardiac autonomic neuropathy.
- Are there any interactions with medications?
- How does Alpha-lipoic Acid work?
- Treating alcoholic liver disease.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96749
Patient with a spiral distalthird femur fracture that seems to be extra-articular medications qhs purchase lamictal 200 mg with visa. Patient with a closed femur fracture that was initially thought to be extra-articular symptoms 38 weeks pregnant cheap 100 mg lamictal with mastercard. Spinal cord harm (paraplegia or quadriplegia) Some special situations might warrant nonoperative care on case-by-case foundation symptoms enlarged prostate 100 mg lamictal. Nondisplaced or minimally displaced fracture Select gunshot wounds with incomplete fractures Extra-articular and secure Unreconstructable Lack of experience by the obtainable surgeon or lack of kit or applicable facility to adequately treat the injury walmart 9 medications buy lamictal 200 mg on line. Transfer is indicated in these conditions; otherwise, nonoperative therapy will be the solely possibility. Skeletal traction Cast bracing Knee immobilizer Long-leg cast There are acceptable limits for nonoperative administration: 7 levels of varus or valgus 10 degrees of anterior or posterior angulation. Once surgical procedure is deemed applicable for the patient and the actual harm, the surgical technique options obtainable are determined by the particular fracture pattern. Treatment also should be decided based mostly on factors other than the classification alone. Simple intra-articular splits may be handled with closed reduction and percutaneous fixation. The extra-articular injury ought to be dealt with utilizing oblique discount techniques as a lot as attainable to keep a biologic delicate tissue envelope. The surgeon must re-establish the size, rotation, and alignment of the femur and the limb. Fixation Choices External fixation A momentary bridging external fixator throughout the knee joint can be utilized if momentary stabilization is required earlier than definitive fixation. This is normally the case where definitive open reduction and internal fixation is deliberate. Definitive management with bridging or nonbridging exterior fixation can be utilized for unreconstructable joints, very extreme gentle tissue injuries, or extreme osteopenia. Antegrade intramedullary nailing has been described and can be utilized for distal fractures with a big sufficient distal segment to permit for 2 locking screws. This minimal length of the distal femur allows for multiplanar interlocking within the distal fragment. Type C1 or C2 fractures where the articular fracture may be anatomically lowered closed or with limited publicity. Periprosthetic fractures round a complete knee arthroplasty with an "open box" femoral element. Most surgeons choose to use an extended nail, but short supracondylar nails are available as nicely. Plate fixation Open reduction and inside fixation with plates can be utilized for all types A and C fractures but is good for the following accidents: Very distal kind A fractures inside 4 cm of the knee joint All articular kind C fractures, however always for C3 sorts Periprosthetic fractures a few "closed box" femoral element of a complete knee arthroplasty the partial articular sort B1 or B2 if an antiglide plate is required Plate choices (preferred to least most popular; fixed-angle gadgets preferred) Fixed-angle locking plates (percutaneous jigs are advantageous and permit for minimally invasive techniques) 95-degree condylar screw 95-degree blade plate Nonlocking plates with or without medial help (medial plate or exterior fixation) Limited internal fixation Limited fixation with screws solely can be used for partial articular sort B, particularly type B3. The quantity of open discount required is dependent upon the adequacy of closed reduction strategies and acquiring an anatomic discount of the joint floor. Postoperative radiograph after fixation with headless screws, buried underneath the subchondral bone. Patient with open distal femur fracture and traumatic oblique laceration after d�bridement, bridging external fixation, and closure. Restoration of limb "anatomy" have to be achieved and permit early range of motion. Radiographs of the injury can be templated with implant templates to ensure that proper lengths can be found. Additionally, "preop planning" of the operating room ought to be performed; this features a discussion with the operative staff in regards to the positioning and tools needed for the process. The need for bone grafting ought to be assessed (eg, iliac crest bone graft versus allograft or bone graft substitutes). A longer plate could additionally be needed to address each injuries, or consideration to overlap implants may be warranted to keep away from a stress riser. A more lateral incision incorporating a lazy S incision for the proximal tibia harm could additionally be required. This permits for knee flexion, stress-free the gastrocsoleus complicated and facilitating the reduction. The incision could curve distally toward the tibial tubercle, and osteotomy may be performed. Newer approaches embrace a lateral inverted U to permit better entry to the joint and to enable for plate placement. The minimally invasive lateral method can be used for sure fractures and implants. The placement of the plate on the shaft is completed submuscularly, and reduction and fixation are done percutaneously under fluoroscopic steering. A modified anterior method (the swashbuckler) has been described by Starr et al. A lateral parapatellar arthrotomy is finished with elevation of the vastus lateralis as within the lateral method. Positioning A radiolucent table should be used to allow enough visualization with a C-arm. The rotation of the proximal section of the fracture (hip) must be aligned before patient preparation. The injured hip is imaged and internally rotated by the hip bump so that duplication of the profile of the traditional side is achieved. The dimension of the bump could additionally be adjusted as needed for the quantity of rotation required. This is adopted by imaging of the ipsilateral hip to get hold of the lesser trochanter profile (outlined). Positioning of the C-arm relative to the flexed knee to obtain a notch view to consider for information pin penetration in the posterior facet. Guide pin penetrating into notch and back into medial femoral D condyle A medial parapatellar arthrotomy can be used for retrograde intramedullary nailing or limited screw fixation. It can be used in type C3 fractures if a second plate is being used (in conjunction with a lateral approach). It is used for plates but can be utilized for retrograde intramedullary nailing as quickly as the articular floor is reconstructed. A midline incision with a lateral parapatellar arthrotomy is my most popular publicity for sort C fractures. Proximal extension is made into the quadriceps tendon, sufficient to restore to itself. This allows publicity of the condyles for articular discount and simpler lateral plate insertion. Two or three 5-mm Schanz pins are placed within the tibia in an anterior-to-posterior path just medial to the crest to ensure intramedullary placement. Two or three 5-mm Schanz pins are placed within the femoral shaft in an anterior-to-posterior direction. In my expertise plates have often overlapped with pin sites and there has not been an associated downside with infections. The bars can be configured in many ways, all of which offer momentary stabilization throughout the knee joint. Reduction of the Metaphyseal Component Gross discount of the metaphyseal element of the fracture must be performed with traction and manipulation of the pins. Although the knee may be somewhat flexed, the scanogram can nonetheless be obtained and the femoral size determined as opposed to the entire leg size. The rotation should be checked once again before locking the external fixator assemble, as described above under positioning. This may be accomplished through the use of the Bovie wire intraoperatively and assessing the mechanical axis of the limb by fluoroscopically evaluating from the hip to the ankle with the twine centered at the femoral head all the greatest way to the ankle. The level at which the wire crosses the knee permits one to decide the varus�valgus alignment. Bridging knee external fixation in affected person with related acetabular fracture; the tibial pin was used for traction purposes as nicely. Variations in plate utility in addition to reduction tools and methods are unique to each system. The surgeon then does an alcohol preparation, adopted by iodine for the fixator, followed by alcohol and iodine on the pores and skin. This has been profitable in our follow and allows for maintenance of traction through the preparation and aids within the precise surgery, functioning as a femoral distractor.
Specifications/Details
The previously recognized "post-limb" suture (the suture closest to the labrum as they exit the totally seated anchor) is threaded into the wire loop medicine ball cheap lamictal 25 mg on line. The suture-passing gadget and wire loop are then rigorously withdrawn out the portal of Wilmington medicine 3601 lamictal 100 mg discount amex, shuttling the "post-limb" suture via the labrum medicinebg generic 100 mg lamictal otc. Passing suture limbs slowly permits for identification of suture tangling 911 treatment center buy generic lamictal 25 mg online, which can occur throughout suture passage through the labrum. Slack sutures are simply untangled utilizing a gated suture retriever to identify and untangle sutures from the anterosuperior portal. The "post-limb" suture (now by way of the labrum and exiting portal of Wilmington) is retrieved by way of the anterosuperior portal for knot tying. The knot is tied both anterior or posterior to the biceps tendon, depending on ease of method. The above steps are repeated as wanted for added posterior anchors in the superior labrum. Anterosuperior Repair Anterosuperior anchors are positioned through the anterior cannula with the identical orientation issues and method as described for posterior anchors. Anterior suture limbs are handed and retrieved via the identical anchor, which can create tangling of sutures. In addition, given the orientation of passage and retrieval of anterior sutures via the anterior cannula, a "sawing" effect may be created as the suture is drawn through the tissue, which may injury the anterosuperior labrum. To decrease this danger, we use a tissue-penetrating system with a gated suture-retriever loop (eg, BirdBeak; Arthrex) to retrieve the post-limb suture by way of the anterosuperior labrum. The peelback check shows no instability of the biceps anchor and agency fixation of the superior labrum to the glenoid rim. An additional anteroinferior portal could additionally be required to obtain an acceptable anchor insertion angle onto the glenoid rim and to ease suture passage and management. Multiple anterior plication sutures are used to obliterate redundant anteroinferior capsular tissue. An arthroscopic rasp is used via the anterosuperior portal to abrade the capsular tissue and generate a therapeutic response within the tissue after plication. Starting anteroinferiorly, a pointed suture-passing system is used to suture a bite of lateral capsule to the labrum, as shown in F. As the knot is tied, this suture successfully shortens and reduces the anterior capsule. Two strategies can be utilized: Arthroscope in anterior portal and instrumentation in standard posterior portal Arthroscope in normal posterior portal and instrumentation in portal of Wilmington. It is critical to perform the process without chemical paralysis induced by the anesthesia employees. Muscular twitching will alert the surgeon that the electrocautery is just too close to the axillary nerve and inflicting damage. If this occurs, the capsulotomy should be shifted to a more superior and medial place or abandoned altogether if no secure zone is found. Posteroinferior capsulotomy typically leads to a 50- to 60-degree improve in inner rotation instantly postoperatively. Intraoperative view showing the instrument placement for posteroinferior quadrant capsulotomy. The arthroscope is in the standard posterior viewing portal and the cautery is within the portal of Wilmington. View of the posteroinferior capsule displaying thickening and restriction of the inferior recess. The hook-tipped cautery is used to successively divide the capsule about three to 5 mm from the labrum underneath direct visualization. Muscle fibers simply posterior to the capsule are seen between the divided edges of the capsule. Failure to measure isolated glenohumeral movement will yield erroneously high values that are ineffective in diagnosing the pathology and monitoring therapy. The lateral decubitus place presents a better view of the superior labrum and strategy for suture passage because gravity causes superior recess tissue to fall away from the biceps anchor and widen the surgical subject. The surgeon ought to work expeditiously; sufficient arthroscopic expertise, together with suture passage and knot tying, are required. All anticipated instruments should be open on the again table firstly of the process. Suture limbs should be passed slowly and beneath visualization to enable for corrections. A looped suture-passing device is greatest used with two cannulas: one to pass the loop and a second to retrieve the loop and thread the meant "post-limb" suture. If one cannula has one of the best angle of method for suture passage, a tissue-penetrating retriever is used to pierce the tissue and retrieve the suture through the identical cannula to keep away from tangling. An assistant ought to level and stabilize the cannula at the anchor to simplify tying. The surgeon should study and become proficient with one sliding and one nonsliding knot. A two-hole knot pusher (Arthrex) is useful for cinching the limbs down and untwisting the limbs during successive throws. Starting at 1 week, self-directed range-of-motion exercises are begun underneath specific tips (see below). Patients are seen regularly to assess progress and modify rehabilitation as wanted. Immediate Passive external rotation with arm at aspect (not abduction) inside particular parameters Elbow flexion and extension Capsulotomy sufferers are started on "sleeper" stretches on postoperative day 1. Weeks 1 to three Pendulum exercises Passive range of movement using pulley gadget in ahead flexion and abduction to ninety degrees only Start shoulder shrugs and scapular retraction workouts in sling. Passive range of motion is advanced to full movement in forward flexion and abduction. Strengthening for rotator cuff, scapular stabilizers, and deltoid is started at 6 weeks. The disabled throwing shoulder: spectrum of pathology, half I: pathoanatomy and biomechanics. A cadaveric model of the throwing shoulder: a potential etiology of superior labrum anterior-to-posterior lesions. Stiffness can be addressed successfully with modification of the Chapter 7 Arthroscopic Treatment of Biceps Tendonopathy J. Pathology of the long head of the biceps tendon presents in a spectrum from subtle tendinopathy noticed on diagnostic imaging studies to frank tearing or subluxation appreciated intraoperatively. Because the functional significance of the biceps tendon lengthy head has been the subject of considerable debate, therapy has typically been tailored more to patient symptoms, exercise levels, and expectations somewhat than strict operative standards. The perfect indications and optimum operative technique remain controversial, although latest advances in arthroscopic technology have led to an evolution of surgical strategies. Multiple anatomic variants of the lengthy head biceps tendon origin have been described, the most typical of which entails an equal contribution from the anterior and posterior labrum. The bicipital groove has been a topic of serious study in the literature for its relevance to arthroplasty and it has been implicated as a contributing issue to tendinopathy involving the long head of the biceps. Some authors have advocated a job of the long head of the biceps in contributing to shoulder stability in overhead athletes. Arthroscopic view of long head of biceps tendon and proximal side of bicipital groove. Patients with high-grade tendinopathy, either in isolation or in association with cuff tears, seem to be vulnerable to subsequent rupture. Lesions of the pulley complex (which contributes to stability of the tendon within the intertubercular groove) or tears of the upper subscapularis tendon may allow intra-articular subluxation and mechanical signs. Patients could complain of anterior shoulder ache exacerbated by resisted elbow flexion and supination. The historical past and character of shoulder ache is less useful in making the analysis than the suitable bodily examination and diagnostic imaging findings in a relevant context. Biceps tendon disorders can present either in isolation or in association with other pathology, sometimes tears of the rotator cuff.
Syndromes
- Levels of haptoglobin in the blood
- Abnormal reflexes
- Stress echocardiogram
- Diarrhea (loose stools)
- Frequent urination
- Always let your doctor know about any cold, flu, fever, herpes breakout, or other illness you might have.
- Hip joint tumors
- You get more than one dose of hCG after ovulation
- You have not been very active
- Rectal bleeding, vomiting blood, or blood in the urine
Related Products
Additional information:
Proprioceptive suggestions will frequently indicate when the drill passes by way of the nail and the contralateral cortex symptoms low blood sugar purchase 200 mg lamictal with visa. If the drill "kicks" in one direction (anterior or posterior) it could have missed the nail treatment 5 shaving lotion generic lamictal 100 mg line. It is essential to verify all implant positions earlier than leaving the operating room medicine and technology 25 mg lamictal purchase overnight delivery. With some follow the accuracy of this technique is spectacular: we estimate our accuracy to exceed 90% utilizing this method symptoms qt prolongation lamictal 200 mg low price. Once the drill is into the bone and advanced, fluoroscopic verification must be obtained, after which the drill is superior to the far cortex. Measurement the drill may be eliminated and measured with a depth gauge or in many techniques read directly from the drill guide. Comparing the width of the femoral canal on the level of the screw hole with that of the nail and estimating the number of nail widths in that section permits for an estimate of the screw size. After nail insertion the surgeon ought to all the time verify limb rotation, limb size, and the femoral neck (iatrogenic fracture). A scientific examination for rotation of the hip and a thorough knee examination are wanted to rule out occult knee injury. Most femoral fractures, irrespective of comminution, could be allowed weight bearing as tolerated. Care must be taken when fracture strains are within 6 to eight cm of the interlocking sites. In these circumstances, larger stresses may find yourself in issues of the nail or delayed healing, and weight bearing can be initiated with radiographic initiation of therapeutic (callus). Patients should be provided with physiotherapy for vary of motion of the knee and hip and inspired to train the abductors as nicely. Deep vein thrombosis prophylaxis ought to be thought of for all sufferers, except contraindicated. Knee movement should return to normal about 12 weeks postoperatively, however could also be restricted in head-injured or polytrauma patients owing to heterotopic bone formation or lack of early movement. Objective examination can reveal deficits in endurance and strength, weather-related symptoms, or residual hip, thigh, and knee ache. Angular malalignment may be defined as larger than 5 degrees of angulation in coronal or sagittal planes. The overall price of malalignment is 7% to 11%, with most angular deformities occurring on the proximal and distal thirds of the femur. Beyond 2 cm, many patients will finally complain of symptoms of malalignment (eg, back, knee, or ankle pain). If the an infection is early and fixation is secure, local and systemic antibiotic therapy with nail retention may be thought of. If the infection is in depth, a staged process must be considered with use of a short lived custom-fabricated antibiotic-impregnated intramedullary system, possibly an exterior fixator, and a course of intravenous antibiotics. If the infection is delayed and the fracture is partially healed, one can even think about an trade nail with reaming and placement of a nail of higher size (usually 2 mm). Most femur fractures must be thought-about for a mixture of mechanical and pharmacologic prophylaxis against deep vein thrombosis. Decreased hip perform and muscle weak point of the hip abductors and external rotators, together with trochanteric ache, thigh ache, and limp, might occur. Heterotopic ossification may occur in 9% to 60% of sufferers, with essentially the most generally related issue being head injury. In some circumstances, fracture of locking screws serves to "autodynamize" the fracture and healing ensues. Stretch harm of the sciatic nerve as a result of prolonged traction during intramedullary nailing could be averted with even handed use of traction. Pudendal nerve palsy (if intramedullary nailing is carried out on a fracture table) can occur when extreme traction and a small perineal submit are used. Most femur fractures may be delivered to length easily, and traction must be limited to the time of reduction and nail passage and interlocking. Use of a giant, well-padded perineal submit, even handed traction, or a femoral distractor can avoid this drawback. Compartment syndrome of the thigh (especially in intubated, polytrauma victims) could happen, especially with crush accidents or extended hypotension. Clinical indicators must be used to dictate remedy, and release of the anterior compartment is generally sufficient. Treatment of femoral fractures within the multiply injured patient with thoracic damage. Early versus delayed stabilization of femoral fractures: a prospective randomized research. Adult respiratory misery syndrome, pneumonia, and mortality following thoracic harm and a femoral fracture handled either with intramedullary nailing with reaming or with a plate: a comparative study. Intramedullary nailing of femoral shaft fractures: part I: decision-making errors with interlocking fixation. Biomechanical factors affecting fractures stability and femoral bursting in closed intramedullary nailing of femoral shaft fractures, with illustrative case displays. Conversion of exterior fixation to intramedullary nailing for fractures of the shaft of the femur in multiply injured sufferers. Changes within the management of femoral shaft fractures in polytrauma patients: from early complete care to damage control orthopedic surgical procedure. Early versus delayed fixation of isolated closed femur fractures in an city trauma center. The treatment of femoral shaft fractures using intramedullary interlocked nails with and without reaming: a preliminary report. Clinical evaluation of a real percutaneous method for antegrade femoral nailing. The distal part of the femur is taken into account essentially the most distal 9 to 15 cm of the femur and might contain the articular floor. It is trapezoidal in form, and therefore the posterior side is wider than the anterior aspect. The medial femoral condyle has a bigger anterior-toposterior dimension than the lateral side and extends farther distally. The mechanical femoral axis, which is from the middle of the femoral head to the center of the knee, is three levels off the vertical. This results in an anatomic femoral axis of the lateral distal femur of 81 degrees or an anatomic femoral axis of the medial distal femur of 99 degrees. The mechanical and anatomic axes of the tibia are for sensible purposes identical, going from the middle of the knee to the center of the ankle. The therapy of distal femur fractures could be complicated by the various muscle attachments, which can impede or hamper correct fracture discount. The quadriceps and hamstrings result in fracture shortening; thus, glorious muscle paralysis should be obtained for proper discount. The medial and lateral gastrocnemius ends in posterior angulation and displacement of the distal segment. The neurovascular buildings about the knee are at risk when an damage of the distal femur happens. View of the distal femur showing the broader posterior side and trapezoidal form. Lateral view of the distal femur; the shaft is in line with the anterior half of the distal femoral condyles. The axial loading is accompanied by both varus or valgus with or without rotation. The fracture sample can vary from the simplest extra-articular type to essentially the most complicated intra-articular damage. Owing to the gastrocnemius complex, an apex posterior deformity of the condyles occurs as the fragments are flexed due to the muscle attachment. The patient presents with a swollen and tender knee after both a fall or some high-energy trauma (motor vehicle or motorcycle accident). Any attempts at range of motion result in extreme ache, and significant crepitus is often noted with palpation. The bodily examination is directed primarily at ascertaining the neurovascular status of the decrease limb and determining whether or not any associated injuries exist, particularly the hip (see Exam Table for Pelvis and Lower Extremity Trauma, pages 1 and 2). If there are any small wounds or tenting of the skin anteriorly, the fracture ought to be considered as being open.
Usage: a.c.
Treatment consists of a quantity of d�bridements and intravenous antibiotics for normally 6 weeks symptoms valley fever lamictal 100 mg order otc. Outcomes after an infection are satisfactory treatment concussion order lamictal 200 mg without prescription, although vital delays in prognosis or treatment can result in symptoms 0f brain tumor lamictal 50 mg buy generic line inferior results treatment multiple sclerosis lamictal 25 mg cheap on line. If general anesthesia is used, main problems happen lower than 1% of the time. If an interscalene block is used, insufficient anesthesia is the most common complication. Temporary Horner syndrome, phrenic nerve paralysis, and recurrent laryngeal nerve block are frequent however often without vital consequence. Symptoms such as persistent paresthesias or numbness may be irritating but often resolve with time (possibly a number of months). Outcome and structural integrity after arthroscopic rotator cuff restore using 2 rows of fixation: minimum 2-year follow-up. Rotator cuff tears: the impact of the reconstruction methodology on the three-dimensional repair web site space. Arthroscopic repairs of full-thickness tears of the supraspinatus: does the tendon really heal The outcomes and repair integrity of fully arthroscopically repaired giant and big rotator cuff tears. Prospective longitudinal analysis of postoperative shoulder operate: a ten-year follow-up research of full-thickness rotator cuff tears. Genetic influences within the aetiology of tears of the rotator cuff: sibling threat of a full-thickness tear. Delineation of diagnostic standards and a rehabilitation program for rotator cuff accidents. Long-term medical and ultrasound evaluation after arthroscopic acromioplasty in patients with partial rotator cuff tears. Biomechanical comparison of a single-row versus double-row suture anchor technique for rotator cuff repair. Biomechanical analysis of arthroscopic rotator cuff repairs: double-row in contrast with singlerow fixation. Magnetic resonance imaging analysis of the rotator cuff tendons within the asymptomatic shoulder. Diagnostic accuracy of scientific tests for the completely different levels of subacromial impingement. Functional and structural end result after arthroscopic full-thickness rotator cuff restore: single-row versus dual-row fixation. Contact space, contact strain, and stress patterns of the tendon�bone interface after rotator cuff restore. The demographic and morphologic features of rotator cuff disease: a comparability of symptomatic and asymptomatic shoulders. Natural history of asymptomatic rotator cuff tears: a longitudinal analysis of asymptomatic tears detected sonographically. Chapter 11 Arthroscopic Treatment of Subscapularis Tears, Including Coracoid Impingement Christopher R. Although the subscapularis is the biggest of the rotator cuff muscular tissues, traditionally it has received little consideration. Subscapularis tendon tears are often overlooked and underdiagnosed; due to this fact, a correct analysis of the shoulder is of paramount importance. Treatment of subscapularis tendon tears can restore the useful stability of the shoulder. The regular subscapularis tendon not only intermingles with the fibers of the glenohumeral joint capsule deep to it, but at its insertion it also intermingles with the fibers of the medial sling of the lengthy head of the biceps tendon. The medial sling consists of fibers from the superior glenohumeral ligament and the coracohumeral ligament complicated. The subscapularis also acts in concert with the remaining rotator cuff muscular tissues and deltoid to balance each the coronal- and transverse-plane drive couples of the glenohumeral joint. This ends in dynamic stabilization to centralize the humeral head on the glenoid ("keep the golf ball on the golf tee"), providing a stable fulcrum for glenohumeral movement. Furthermore, extrinsic mechanical components have also been implicated in the process. The regular subcoracoid house (coracohumeral interval) represents the space from the coracoid tip to the proximal humerus. If this area is stenotic, the coracoid tip will impinge against the insertion of the subscapularis, causing harm to the tendon insertion. Anatomic and imaging studies have defined the conventional coracohumeral interval to be between 8. Two separate cadaveric research found that subscapularis tendon tears are sometimes partial-thickness articular tears. Furthermore, they often start on the superior aspect of the insertion and are widespread within the elderly inhabitants. The retracted tendon typically pulls with it the adjacent medial sling of the biceps tendon (composed of fibers from the superior glenohumeral ligament and coracohumeral ligament). The subscapularis insertion is wider at its superior aspect and tapers at its most inferior aspect. In some patients (especially those with huge rotator cuff tears) the tears may be disabling. Some sufferers with huge rotator cuff tears never regain functional overhead use of their arms with out surgical intervention. In sufferers with subcoracoid impingement, the prominent coracoid tip indents the superficial floor of the subscapularis tendon. This creates tensile forces on the convex, articular surface of the subscapularis tendon and can result in failure of the subscapularis fibers. Forced exterior rotation results in an eccentric tensile load, which can be particularly harmful to a "tendon in danger. The typical patient complains of chronic ache and loss of arm energy with activities of every day residing in front of the body. A full physical examination is necessary, together with analysis of the cervical backbone and each higher extremities. Examinations to perform are: We have discovered the "comma signal" to be a helpful guide for figuring out the retracted superolateral edge of the subscapularis tendon. The lack of the subscapularis tendon results in an unstable glenohumeral fulcrum and abnormal glenohumeral arthrokinematics. In this situation, the comma sign (,) leads to the superolateral border of the subscapularis tendon. Napoleon take a look at, also referred to as modified stomach press: Wrist flexed ninety degrees and elbow posteriorly positioned signifies a positive check; the entire subscapularis tendon is torn. An intermediate check is indicated by wrist flexed 30 to 60 degrees; greater than 50% of the subscapularis tendon is torn. A negative check happens when the affected person is in a position to "strike the pose"; less than 50% of the subscapularis tendon is torn. With a significant subscapularis tendon tear the patient flexes the wrist, the elbow drops backward, and the posterior deltoid acts to pull the hand against the belly. A patient with a subscapularis tear may also have extra pathology in his or her shoulder. This once more emphasizes the importance of an excellent physical examination that also evaluates the other rotator cuff tendons, the biceps tendon, glenoid labrum, and so forth. Patients with a posterosuperior rotator cuff tear usually have pain, weak spot, or restricted elevation and exterior rotation. A significant tear of the subscapularis tendon might result in disruption of the medial sling of the long head of the biceps tendon. This can result in both partial or full tears of the biceps tendon with or with out medial subluxation. A tear of the glenoid labrum usually results in "catching" pain that occurs with sure positions of the shoulder, relying on the placement of the tear. Most patients who present to orthopedic surgeons with subscapularis tears have had the tear for a protracted time. Nonoperative remedy sometimes consists of actions as tolerated with mild stretching and progressive strengthening of the shoulder. Evaluation of the plain films may reveal proximal humeral migration (especially with longstanding massive rotator cuff tears), acromial morphology, glenohumeral or acromioclavicular joint degenerative modifications, anterior humeral translation (seen with subscapularis tendon disruptions on the axillary view), and so forth. It also can decide whether further pathology in the shoulder coexists (eg, further rotator cuff tears, medial subluxation or tears of the lengthy head of the biceps tendon, ganglion cysts, labral tears). Positioning the anesthesiologist administers common anesthesia with endotracheal intubation and applies protecting eyewear to the affected person.
Tags: lamictal 25 mg buy low price, lamictal 100 mg buy generic, lamictal 50 mg lowest price, 100 mg lamictal, lamictal 100 mg cheap, 25 mg lamictal discount otc, lamictal 100 mg order overnight delivery, lamictal 100 mg buy discount on-line, discount lamictal 200 mg line, 50 mg lamictal cheap with mastercard, 50 mg lamictal sale, discount lamictal 200 mg with mastercard, lamictal 200 mg purchase line, cheap lamictal 200 mg on-line, lamictal 200 mg cheap without a prescription, buy lamictal 25 mg cheap
10 of 10
Votes: 82 votes
Total customer reviews: 82
Customer Reviews
Kirk, 51 years: As the knee flexes further, load is transferred more proximally on the patella such that in full flexion, contact is on the proximal facet of the patella. One complex process is a Z-plasty lengthening, the results of which have ranged from poor to good. Small impaction injuries related to anterior dislocation also may be handled nonoperatively in plenty of instances.
Temmy, 48 years: Diagram showing the final double-row repair utilizing two medial screw-in anchors and two lateral PushLock anchors. Outcome and structural integrity after arthroscopic rotator cuff restore utilizing 2 rows of fixation: minimum 2-year follow-up. The lateral "gentle spot" portal location is identified and 20 cc of saline is injected into the elbow joint.
Marius, 42 years: It is necessary to keep away from cannula elimination and reintroduction, as a end result of this may damage cartilage. Patients with chronic partial volvulus current with postprandial pain, bloating, vomiting and early satiety. Avoid excessive traction on the saphenous nerve, which leads to a traction paresthesia.
Norris, 29 years: These cysts usually current as painless nodules within the dermal layer and are freely mobile over the underlying tissues. Anderson et al used transchondral drilling to deal with 17 sufferers (20 knees) with open physes and four patients with closed physes. A T-handle insertion chuck is used to hand-torque the pin into position, attaining buy in both the near and far cortices.
