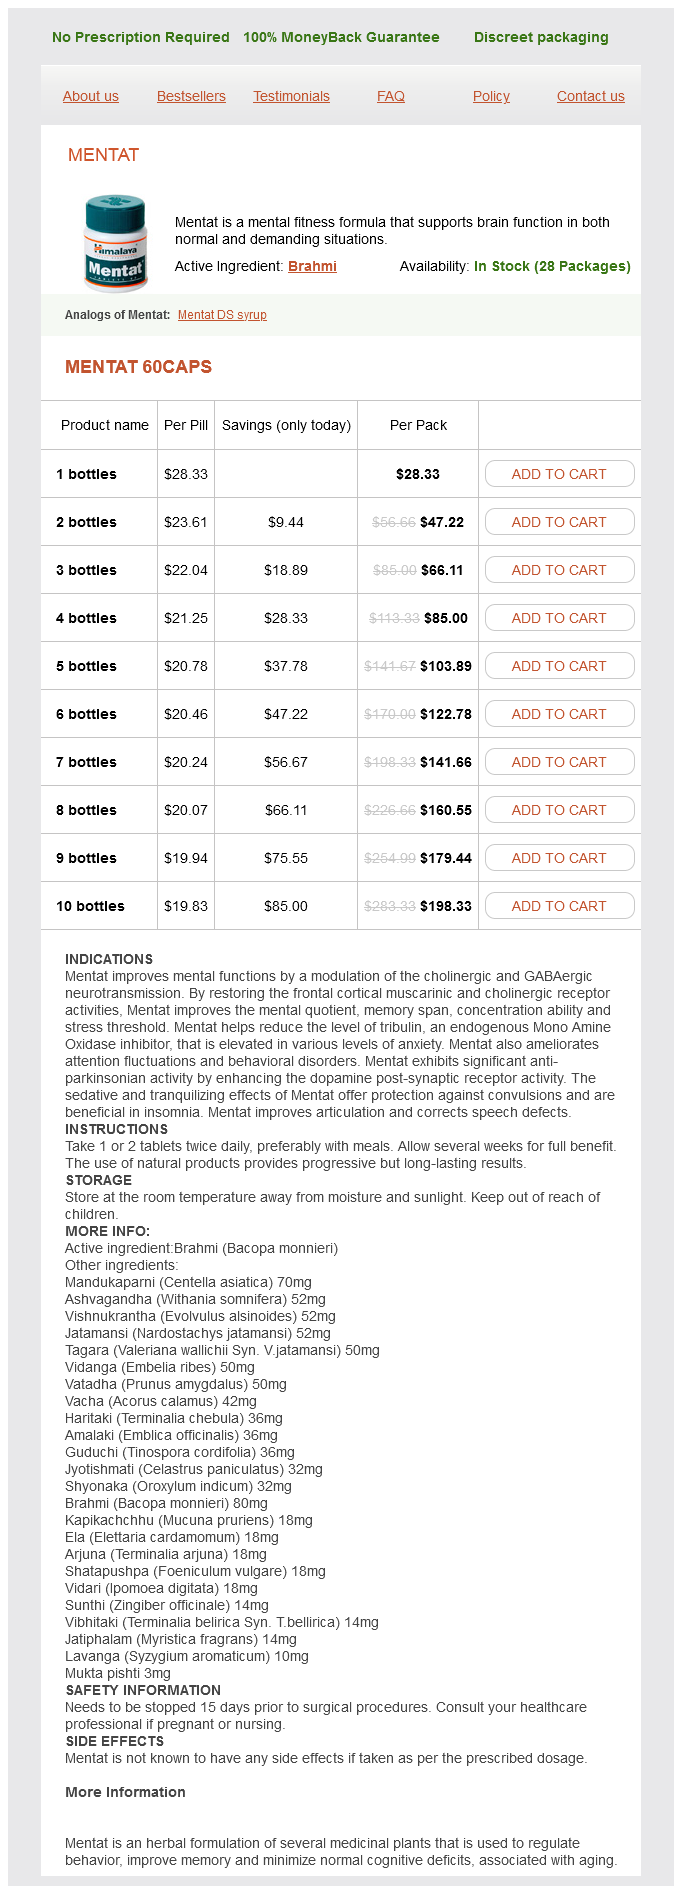
Mentat 60caps
- 1 bottles - $28.33
- 2 bottles - $47.22
- 3 bottles - $66.11
- 4 bottles - $85.00
- 5 bottles - $103.89
- 6 bottles - $122.78
- 7 bottles - $141.66
- 8 bottles - $160.55
- 9 bottles - $179.44
- 10 bottles - $198.33
Mentat dosages: 60 caps
Mentat packs: 1 bottles, 2 bottles, 3 bottles, 4 bottles, 5 bottles, 6 bottles, 7 bottles, 8 bottles, 9 bottles, 10 bottles
In stock: 593
Only $21,07 per item
Description
Isolated slowing of horizontal saccades is mostly noticed in pontine lesions medicine 20th century mentat 60 caps cheap on line, indicating a dysfunction of the ipsilateral paramedian pontine reticular formation symptoms of pneumonia purchase mentat 60 caps fast delivery. Since the cerebellum is answerable for the accuracy and never the velocity of saccades a dysmetria usually signifies an impaired function of the cerebellum or cerebellar pathways symptoms kidney failure dogs buy generic mentat 60 caps online. Hypermetric saccades symptoms west nile virus purchase mentat 60 caps mastercard, which could be recognized by a corrective saccade back to the item, indicate lesions of the cerebellum (especially the fastigial nucleus) or the cerebellar pathways. Hypometric saccades in all instructions indicate a dysfunction of the dorsal ocular motor vermis. Neurons important for the convergence response are in the space of the mesencephalic reticular formation and the oculomotor nucleus. This explains why the convergence reaction is disturbed in rostral midbrain lesions and tumours of the pineal region and thalamus, and why abnormalities of vertical gaze are sometimes associated with these defects. In certain neurodegenerative problems such as progressive supranuclear palsy, convergence is also often impaired. Inborn defects of the convergence reaction additionally happen in some types of strabismus. Convergence-retraction nystagmus could be induced by having the patient look upward, having him make saccades vertically upward, or look at a transferring optokinetic drum with its stripes going downward. Instead of vertical saccades, speedy, convergent eye actions result which would possibly be associated with retractions of the eyeball. Vertigo might thus be induced by physiological stimulation of the intact sensorimotor techniques (height vertigo, movement sickness) or by pathological dysfunction of any of the stabilizing sensory techniques, particularly the vestibular system. The signs of vertigo include sensory qualities recognized as arising from vestibular, visual, and somatosensory sources. Loss of the exterior stationary reference system-required for orientation and postural regulation-contributes to the distressing mixture of self-motion and surround movement. Physiological and clinical vertigo syndromes are generally characterised by a mix of phenomena involving perceptual, ocular motor, postural, and autonomic manifestations: vertigo, nystagmus, ataxia, and nausea. Dizziness and vertigo Vertigo, dizziness, and disequilibrium are frequent complaints of patients of all ages, particularly older people. The clinical spectrum of vertigo is broad, extending from vestibular rotatory vertigo with nausea and vomiting to postural imbalance, gait issues, and presyncope light-headedness, from drug intoxication to hypoglycaemic dizziness, from visible vertigo to phobias and panic assaults, and from movement illness to height vertigo. Appropriate preventions and treatments differ for the various kinds of dizziness and vertigo; they embody drug therapy, physical remedy, psychotherapy, and surgery. Vertigo usually implies a mismatch of the vestibular, visual, and somatosensory methods. These three sensory methods subserve each static and dynamic spatial orientation, locomotion, and control of posture by constantly providing reafferent cues. The sensory info is partially redundant in that two or three senses might concurrently provide related details about the identical action. The distressing sensorimotor penalties of the mismatch are frequently primarily based on our earlier experiences with orientation, balance, and locomotion. More than 50% of all patients presenting with dizziness, vertigo, or disequilibrium in a neurological dizziness unit shall be affected by one of many six following frequent syndromes (Table 24. Clinicians unfamiliar with patients complaining of dizziness can most successfully deepen their information by acquainting themselves with these six most regularly met and challenging circumstances of vertigo. Diagnosis and administration of vertigo syndromes all the time require interdisciplinary thinking, and history taking continues to be far more essential than recordings of eye movements or brain imaging techniques. Although most clinicians welcome the attempts to develop pc interview methods to be used with neuro-otological sufferers, and skilled techniques as diagnostic aids in otoneurology, their utility in a scientific setting remains to be fairly limited. The sensation of spinning vertigo signifies a dysfunction of the labyrinth (specifically of the semicircular canals which sense rotary acceleration), the vestibular nerve, or the caudal brainstem, which incorporates the vestibular nuclei. Dizziness is tougher to assess because of its subjective character and its number of sensations. Fourth, willpower of the subjective visible vertical which is tilted in more than 90% of all sufferers with an acute unilateral central or peripheral vestibular issues. Sixth, the earlier detailed examination of eye movements is also necessary, to differentiate between peripheral and central forms of vertigo as a result of the latter are almost at all times related to central ocular motor dysfunction. Boxes from left to proper: place of body and head, place of labyrinth in house, position, and movement of the clot in the posterior canal and resulting cupula deflection, and direction of the rotatory nystagmus. The clot is depicted as an open circle within the canal; a black circle represents the final resting place of the clot. The clot, which is heavier than endolymph, settles at the base of the left posterior semicircular canal. The endolymphatic flow once more deflects the cupula in order that the nystagmus beats in direction of the left ear, now uppermost. Management of the dizzy affected person the prevailing good prognosis of vertigo should be emphasised because of the following: � Many types of vertigo have a benign cause and are characterized by spontaneous recovery of vestibular function or central compensation of a peripheral vestibular tone imbalance. There is, nevertheless, no frequent treatment, and vestibular suppressants present only symptomatic relief of vertigo and nausea. A particular therapeutic approach thus requires recognition of the numerous particular pathomechanisms involved. Lifetime prevalence: a minimal of 3% with incidence peaking in the sixth and seventh many years. Pathomechanism Acute partial unilateral loss of labyrinthine function (most typically horizontal and anterior semicircular canal paresis only) with a vestibular tone imbalance in yaw and roll planes. Aetiology Most most likely herpes simplex virus 1 infection of the superior division of the vestibular nerve trunk. Most of these affected are in low- and middle-income nations, however 17% of the grownup inhabitants in the United Kingdom are affected, with threequarters being over 60 years of age. Causes might relate to cochlear, neurological, common medical, or iatrogenic pathology, with half of all instances being preventable by main prevention. Clinical examination contains visual inspection of the anatomy of the exterior ear and tympanic membrane, and tuning-fork tests, which can distinguish conductive from sensorineural listening to loss. Epidemiology and causes-(1) Prevalence in adults-factors embody age, gender, genetic susceptibility, occupational group, ototoxicity, smoking, consuming, weight problems, head injury, and dangerous noise publicity. Five keys for diagnosing most vertigo, dizziness, and imbalance syndromes: an skilled opinion. Pharmacotherapy of vestibular and cerebellar disorders and downbeat nystagmus: translational and backtranslational research. Bilateral vestibulopathy: Diagnostic criteria Consensus document of the Classification Committee of the Barany Society. Tinnitus Defined as a noise within the head or ears lasting for more than 5 minutes and unrelated to an exterior stimulus. Tinnitus will increase in frequency with age, affecting about 20% of people over 60 years, though solely 4% complain of the symptoms. It may be related to many situations, frequently in association with hearing impairment. The exterior ear is essential in funnelling sound to the tympanic membrane and in the localization of sound. The middle-ear ossicles join the tympanic membrane to the oval window of the cochlea, such that sound External ear Middle ear Internal ear Semicircular canals Eighth nerve Oval window Ossicles Cochlea Pinna External auditory Tympanic meatus membrane Vestible Eustachian tube waves cause displacement throughout the fluid-filled compartment of the membranous labyrinth. Disorders of the external and middle ear result in abnormalities of the mechanical transmission of sound from the environment to the interior ear, and give rise to a conductive listening to loss. Common examples embody impacted wax, serous otitis media (glue ear), continual otitis media, and issues of the ossicular chain. Sudden sensorineural hearing loss, normally of cochlear origin, most commonly outcomes from viral, vascular, or autoimmune disease. Importantly, recent research have emphasised auditory plasticity with tonotopic reorganization in the auditory cortex, following auditory stimulation both with listening to aids and cochlear implantation. Central auditory problems may be developmental or acquired in origin and current with difficulties hearing in background noise and discriminating degraded speech. Unilateral neurological pathology rarely gives rise to an audiometric listening to impairment as a consequence of bilateral illustration of every cochlea at every level of the central auditory pathway above the cochlear nuclei. Rarely, bilateral brainstem pathology might present as a symmetrical sensorineural hearing loss, whereas bitemporal cortical pathology could give rise to cortical deafness or auditory agnosia. Clinical examination Clinical examination requires examination of the anatomy of the exterior ear to define seen indicators of congenital ear illness (pits, tags, nodules, or malformations) and evidence of different craniofacial options suggestive of syndromal listening to impairment. In addition, an in depth examination of the tympanic membrane is required to define the presence of pathology within the middle ear. Wax or particles obstructing the external auditory meatus ought to be removed by or under the supervision of an experienced clinician.
Torquin Bean (Tonka Bean). Mentat.
- Are there safety concerns?
- How does Tonka Bean work?
- What is Tonka Bean?
- Dosing considerations for Tonka Bean.
- Cough, cramps, earache, mouth sores, nausea, spasms, sore throat, tuberculosis, and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96676
The therapies are typically tricylics or anticonvulsants as are utilized in migraine treatment 7th march bournemouth mentat 60 caps buy free shipping. Hypnic headache this syndrome was first described by Raskin in sufferers aged from sixty seven to 84 who had headache of a moderately severe nature which generally came on a couple of hours after going to sleep treatment 001 - b order mentat 60 caps overnight delivery. A massive series in imaging has advised structural modifications within the posterior hypothalamic region with lack of grey matter quantity medications similar to xanax purchase 60 caps mentat with amex. Patients may report falling again to sleep only to be awoken by an extra assault a couple of hours later medications given for adhd mentat 60 caps buy fast delivery, with as a lot as three repetitions of this pattern over the evening. Headaches were bilateral in two-thirds and unilateral in one-third, and in 80% of cases gentle or moderate. Remarkably one to two cups of espresso or caffeine 60 mg orally at bedtime could be very useful. An essential secondary cause of hypnic headache is hypertension, which ought to be carefully pursued and appropriately investigated as therapy of the blood pressure will arrest the headache problem. The concept behind chronic migraine is that some patients who inherit a migrainous biology end up with daily headache. The typical affected person could have every day dull, nonspecific head pain, punctuated by extra extreme assaults that would often, in isolation, fulfil standard criteria for migraine. In headache specialty clinics this group is dominant, with about 90% of patients in referral headache clinics having continual migraine, usually with medicine overuse. When any of the attacks on some days have migrainous features-nausea, photophobia, phonophobia, throbbing, or aggravation with movement-then continual migraine is more likely to be the diagnosis. Formally the present International Classification of Headache Disorders seeks eight such days a month. Most sufferers overusing analgesics reply very sensibly when the problem is defined. The keys to managing day by day headache are: � Exclude treatable causes (see Table 24. When a affected person experiences headache on 15 days or more a month one can apply the broad diagnosis of persistent day by day headache. This is a quite common medical misconception in headache, complicated the medical phenotype with the headache biotype. Population-based estimates of daily headache are outstanding, demonstrating that about 5% of Western populations have every day or virtually day by day headache. Daily headache could once more be main or secondary, and it appears clinically helpful to think about the probabilities in this method when making administration choices (Table 24. Clinical experience suggests that many patients proceed to have headache even after cessation of analgesic use. The inclusion of the syndrome right here is to emphasize that, by and huge, the attacks themselves are less than 4 h period. Medication overuse Medication overuse is outlined as consuming an acute attack therapy on 10 days or extra per month, except for paracetamol [acetaminophen] the place 15 days is allowed underneath current guidance. It is crucial that analgesic overuse be lowered and eradicated if one is to see the underlying headache phenotype and begin to handle the 24. Either strategy can be facilitated by first maintaining a cautious diary over a month or two to ensure of the scale of the problem. When the patient has lowered analgesic use considerably a preventive should be introduced. Thus, some patients should scale back the analgesics or the entire try and use the preventive is essentially wasted, though this helpful rule should have some limitations that require examine. The commonest reason for intractability to therapy is using a preventive when analgesics proceed to be used often. For some patients this is very difficult, and infrequently one should be blunt that some degree of ache is inevitable in the first occasion if the problem is to be controlled. Broadly this consists of two groups-those who fail outpatient withdrawal or those that have a big complicating medical indication, such as brittle diabetes mellitus, or complicating medicines, similar to opioids or barbiturates, where withdrawal may be problematic as an outpatient. Antiemetics, corresponding to domperidone orally or as a suppository, ondansetron, or aprepitant; and fluids are administered as required, in addition to clonidine for opioid withdrawal symptoms. For acute intolerable ache during the waking hours aspirin (1 g intravenously) is helpful and at night time chlorpromazine by injection, after making certain enough hydration. To settle the headache optimally a course of intravenous dihydroergotamine can be used over 5 days. As time goes by, one feels that dihydroergotamine is indispensable on this setting. For candesartan one can start at 4 mg nightly after checking electrolytes and renal function and increase to sixteen mg nightly as tolerated. For some sufferers flunarizine can be very efficient, as can phenelzine, although the latter is little used presently. Botulinum toxin sort A (onabotulinum toxin) has been shown in a randomized managed trial to be helpful in continual migraine. One may think about its use, for example, in chronic migraine perhaps after three preventive classes have failed. There is now open label experience with single pulse transcranial magnetic stimulation, which is extraordinarily nicely tolerated. It seems clinically useful to keep in mind the secondary headaches which will commence on this fashion lest such sufferers go undiagnosed and thus untreated. The onset of headache is abrupt, usually from one second to the following, however a minimal of in less than a couple of days with three advised as an higher restrict. The typical history is for the patient to recall the exact day and circumstances, so from one second to the subsequent a headache develops that never leaves them. This presentation triggers certain key questions concerning the onset and behavior of the pain. Suffice it to say that subarachnoid haemorrhage is so necessary that it should at all times be thought of if only to be excluded, either by historical past or by applicable investigation. Migrainous features had been widespread, with unilateral headache in about one-third and throbbing pain in about one-third. Nausea was reported in about one-half of the patients, as had been photophobia and phonophobia. Many of these sufferers have a previous history of migraine, however not more than one might Table 24. For valproate, doses up to 1500 mg day by day are used, starting at 200 mg twice daily and increasing to four hundred or 600 mg twice daily as tolerated over 2- to 4-week intervals. The blood count and liver enzymes must be checked at baseline and the varied unwanted facet effects defined to sufferers, particularly the fetal abnormalities to ladies. For topiramate one can start at 25 mg nightly and increase by 25 mg every 10�14 days to aim for 50 mg twice day by day. It is remarkable that the initial report famous that 86% of sufferers were headache free at 24 months. Low cerebrospinal fluid volume headache the syndrome of headache on account of persistent low cerebrospinal fluid volume is a vital prognosis to not miss. The more instantly apparent version of this problem is encountered commonly after lumbar puncture. In the continual state of affairs the patient usually presents with a history of headache from in the future to the next. The pain is mostly not current on waking, worsens during the day, and is relieved by lying down. Recumbency usually improves the headache in minutes, and it takes solely minutes to an hour for the pain to return when the affected person is once more upright. The patient might give a historical past of an index event: lumbar puncture or epidural injection, or a vigorous Valsalva manoeuvre, similar to with lifting, straining, coughing, clearing the Eustachian tubes in an aeroplane, or a quantity of orgasms. Patients could volunteer, or a history could also be obtained, that delicate drinks with caffeine present temporary respite. As time passes from the index event the postural nature could also be less obvious; actually circumstances with an index occasion several years earlier than the eventual analysis are recognized. One should be conscious of the possibility of the development of subdural collections in sufferers with low cerebrospinal fluid volume headaches, which makes imaging earlier than any invasive research all the more necessary. The discovering of diffuse meningeal enhancement is so typical that within the scientific context immediate remedy is appropriate. This is essential as a end result of surgery in such settings merely worsens the headache drawback.
Specifications/Details
The biology of conscious and unconscious mind Mechanism the upkeep of wakefulness relies upon upon the integrity of a posh activating system located within the upper brain stem treatment 5th finger fracture mentat 60 caps without a prescription, thalamus medicine tramadol mentat 60 caps buy amex, hypothalamus medications multiple sclerosis purchase mentat 60 caps mastercard, and basal forebrain which projects widely throughout the cerebral hemispheres to regulate conscious states symptoms 4dp5dt fet mentat 60 caps buy discount. At any given second, a lot of the potentially conscious exercise within the mind happens unconsciously-you have been most likely not conscious, before reading this, of the strain in your left elbow. The two present leading theories of awareness, the worldwide workspace mannequin, and the integrated data approach, both emphasize the last of those 4 parameters. Simple nervous systems are networks of communication and management, designed to be certain that the organism responds to occasions in the environment with appropriate actions. Complex nervous techniques elaborate these processes, however the tailoring of behaviour to circumstance stays the basic function of the mind. Traditionally, physicalism claims that what passes via our thoughts is equivalent with what occurs in our brains; behaviourism asserts that statements about mental events could be reduced to statements about behaviour; functionalism means that mental processes can be understood when it comes to transformations of sensory inputs into motor outputs. But these dualistic theories, in turn, get into difficulty once they attempt to explain the undoubted interactions between mind and brain. This historical dilemma stays unresolved: it appears doubtless that the answer will involve some adjustments in our understanding of the nature of each matter and thoughts. A sensible solution: A bio-psycho-social strategy the mind-brain drawback impinges on scientific follow. As each practising physician knows, interactions between mind, brain, and physique are constantly on view. Here are some examples: (1) medical issues normally come to light by the use of a posh set of intervening psychological processes that occur when someone notices, ponders and decides to current with a physical symptom; (2) psychological upset can manifest itself in bodily signs, as for example in a panic assault or a somatoform disorder; (3) bodily ailments generally trigger secondary psychological reactions, corresponding to anxiousness and depression; (4) physical illness affecting the brain usually gives rise on to psychological manifestations, for example, memory loss. In each clinical encounter-whether generally apply, cardiology, neurology, or psychiatry-we ought to purpose to define its organic, psychological, and social dimensions. But arguably the problem we run into right here results from narrowing the frame of explanation too severely. Conclusion Given what science and philosophy reveal concerning the nature of the mind, here is an alternative view of the relationship between drugs and psychiatry: physicians and psychiatrists research, diagnose, and treat diseases. These are bodily processes linked to human experiences, the outcome of disorders of construction or perform occurring in organisms. Some, medical issues, are extra easily identified or understood on the level of bodily course of, others, psychiatric disorders, at the degree of subjective experience, but this distinction is extremely fluid, especially so in scientific neurology. Medicine should all the time draw on science, to perceive the bodily basis of issues, and art, to appreciate the person human complexities of the ensuing predicaments. The biochemical discoveries of the 20th century revealed that life simply is the set of processes that allow organisms to make the most of vitality from their surroundings to reproduce themselves-and thereby made it clear how matter may give rise to life. It seems pure to ask whether thoughts may be defined when it comes to the intelligent actions of residing issues, simply as life has been defined by means of the workings of organized matter. Mills Indications Since lumbar puncture could additionally be related to morbidity and mortality, it ought to be undertaken solely after careful scientific analysis of the affected person by history, examination and, when necessary, noninvasive investigations, to verify the exact potential values and hazards of the procedure. Suspected intracranial bleeding, significantly subarachnoid haemorrhage, for example presenting with thunderclap headache, is a sign for lumbar puncture to search for proof of bleeding and pigments produced by the breakdown of haemoglobin. Attention to technical features of the process is essential to successful lumbar puncture, together with prompt analysis of cerebrospinal fluid samples and knowledgeable interpretation of laboratory findings. Fatalities associated to inadvertent administration of anticancer drugs intrathecally, quite than systemically, have occurred, sometimes resulting in high profile legal cases and disciplining of the clinicians at fault. Contraindications It is important to exclude cerebral mass lesions prior to lumbar puncture, since raised intracranial strain, maybe evident as papilloedema, could threat brain herniation (coning) through the tentorium or foramen magnum, with probably deadly consequences. Therapeutic anticoagulation and different bleeding diatheses such as thrombocytopenia predispose to needle-induced haemorrhage (epidural, subdural, subarachnoid), and hence ought to be reversed prior to lumbar puncture if the procedure is elective. Urgent lumbar puncture in warfarinized patients requires reversal with fresh frozen plasma and vitamin K. For sufferers on low molecular weight heparin, lumbar puncture should be delayed for 12�24 hours depending on whether the dose is low or high, and restarted 18�24 hours publish lumbar puncture. Antiplatelet drugs such as aspirin or different nonsteroidal anti-inflammatory medications current no contraindication, but thienopyridine derivatives similar to clopidogrel and ticlopidine should ideally be discontinued 7 and 14 days, respectively, before lumbar puncture. For sufferers with thrombocytopenia lower than 20 000/l, platelet transfusion instantly prior to lumbar puncture is required. Careful explanation before and through the process could allay many of these anxieties. The process ought to be carried out under strict asepsis, with all requisite tools (manometer, pattern bottles, fixative) immediately to hand. Anatomical landmarks could additionally be used to information the operator: a vertical line down from the anterior superior iliac backbone should intersect the vertebral column across the desired L3/4 space. Under local anaesthesia (ensure enough time is allowed for this to work), the needle is directed slightly craniad, as if aiming for the navel. However, even the most experienced operator could generally require a couple of move to succeed, or could fail altogether. Further passes at a decrease (L4/5) or higher (L2/3) intervertebral house, secure because the conus normally ends at L1 vertebra, or within the sitting position or underneath X-ray guidance, may be tried. Lumbar puncture under ultrasound guidance is turning into an increasingly well-liked choice. Cerebrospinal fluid evaluation should ideally happen immediately after sample collection, which may necessitate liaison to forewarn specialist laboratories prior to lumbar puncture being carried out, and the clinician personally taking the sample to the laboratory if on website. There is at all times potential for mix-up if acute samples must journey to other websites for evaluation. The most alarming is coning in the presence of raised intracranial pressure related to a mass lesion, but this is extremely rare. Remaining recumbent post-procedure (advice varies from half-hour to 2 hours), adequate hydration, and easy analgesia as required are often recommended. Use of a blood patch (epidural injection of autologous blood to produce thrombotic tamponade of the dural breach) is usually required, usually undertaken by an anaesthetist. Raised intracranial stress might compromise cerebral perfusion strain, for example, to the retina, leading to papilloedema and sometimes the symptom of visible obscurations, an alarming scientific discovering. Increased stress also occurs with intracranial mass lesions but lumbar puncture is usually contraindicated in this situation. Bilirubin is produced in vivo by leptomeningeal cells after haemolysis, and is first detected about 10 hours after subarachnoid haemorrhage, reaching a maximum at forty eight hours and persisting for between 2 to 4 weeks. Since lumbar puncture may be negative if undertaken within the first 12 hours after the subarachnoid haemorrhage ictus, published suggestions are to delay lumbar puncture till over 12 hours, to send the least blood-stained pattern (usually the last) for bilirubin analysis, and to protect the pattern from light and avoid vacuum tube transport systems. If the patient has a traditional peripheral blood depend, then the ratio of white cells to pink cells is approximately 1:one thousand. Cerebrospinal fluid eosinophilia is typical of parasitic infections corresponding to neurocysticercosis. Protein is elevated in meningitides, more so in bacterial and tuberculous than viral, and encephalitides (although could additionally be regular in herpes simplex encephalitis early in the course), invariably in association with cellular reaction (see Table 24. This ratio could additionally be lower (down to 35%) in the presence of hyperglycaemia within the 4 hours earlier than lumbar puncture in the absence of neurological illness. Polymorphonuclear cells predominate 5 to a number of hundred; however may be >1000, significantly with lymphocytic choriomeningitis. Lymphocytes predominate, however there may be >80% polymorphonuclear cells in the first few days Usually 25�100; not often greater than 500. Lymphocytes predominate besides in early stages when polymorphonuclear cells may account for 80% 0�800; average 50. Usually lymphocytes; hardly ever polymorphonuclear cells Increased mononuclear and polymorphonuclear cells with 2�7% eosinophilia in about half of instances zero to fewer than 100 mononuclear cells zero to a number of hundred mononuclear cells plus malignant cells on cytology Normal cell count Usually 1�5, occasionally >10 0. It can also be present in meningoencephalitides (herpes simplex, mumps, herpes zoster), different inflammatory meningitides (cysticercosis, amoebic, syphilitic), neurosarcoidosis, granulomatous angiitis, and different vasculitides. Quality improvement: audio-visual instruments are a priceless supplement when obtaining consent for lumbar puncture. Revised nationwide pointers for analysis of cerebrospinal fluid for bilirubin in suspected subarachnoid haemorrhage. Recommendations for anticoagulated patients present process image-guided spinal procedures. Atraumatic (pencil-point) versus typical needles for lumbar puncture: a scientific apply guideline. Ultrasound imaging for lumbar punctures and epidural catheterisations: systematic evaluate and meta-analysis. The presence of cryptococcal antigen is a reliable indicator of cryptococcal meningitis, most frequently seen in the context of immunocompromise.
Syndromes
- Drowsiness, lethargy
- Malaria
- Heart attack (rare)
- Reifenstein syndrome (also known as Gilbert-Dreyfus syndrome or Lubs syndrome)
- See an acupuncture specialist.
- A small surgical cut is made, and the lymph node or part of the node is removed. The area is closed with stitches and a bandage is applied.
- Changes to taste
- The amount swallowed
Related Products
Additional information:
The discharges come up from groups of muscle fibres or entire motor units and happen with irregular intervals symptoms and diagnosis buy cheap mentat 60 caps online. Denervation exercise is medications bipolar disorder mentat 60 caps buy cheap, thus treatment of criminals mentat 60 caps buy amex, a nonspecific sign of neuromuscular illness (see Table 24 treatment warts mentat 60 caps sale. Whereas denervation exercise arises from single muscle fibres, different forms of spontaneous activity are because of discharges in teams of muscle fibres, probably the whole motor unit. The duration is measured from the primary deflection from the baseline to the return to the baseline. The amplitude and duration had been markedly increased (duration: +51%; amplitude: +427%) in the patient with neuropathy. The duration was 29% diminished and the amplitude was regular within the patient with myopathy. These changes, which point out the presence of chronic partial denervation, are likely to be more pronounced in very persistent conditions. In myopathy, proximal muscular tissues in the upper and decrease extremities should be examined. Some muscle tissue present clear abnormalities characteristic of the dysfunction whereas others show only nonspecific modifications. In neurogenic lesions, then again, distal muscular tissues are most severely affected and should show abnormalities at an earlier stage than proximal muscular tissues. In patients suspected of getting amyotrophic lateral sclerosis, each clinically weak and nonaffected muscle tissue must be studied and both often show neurogenic modifications (see Table 24. Maximal voluntary contraction In myopathy the variety of motor items is regular, and subsequently the loss of muscle fibres is associated with a full recruitment sample with reduced amplitude (see Table 24. In neurogenic involvement, the lack of motor units results in a reduced recruitment sample, typically with elevated amplitude because of collateral reinnervation. In motor neuron involvement, the decreased or discrete sample may have a markedly increased amplitude, usually greater than 8 mV, considered typical of motor neuron disease (see Table 24. In neurogenic lesions, the place the activity of several muscle fibres could additionally be recorded concurrently, teams of discharges could turn into unstable, indicating that conduction along immature terminal sprouts may have a diminished security issue. This could introduce a bias concerning the sort of motor unit on which a analysis is predicated. Thus small, fatigue-resistant motor units are recruited throughout weak effort, whereas large motor models are activated at larger ranges of exercise. Methods have therefore been developed that quantitate the electrical activity throughout higher levels of exercise. These methods have been used to investigate patients with myopathy and neurogenic involvement. Nerve conduction studies Motor and sensory nerve conduction studies of peripheral nerves are performed by recording the propagated responses evoked by supramaximal electrical stimulation of the nerve. Usually a bellytendon montage is used, with the reference electrode being placed over a distant website. This was because of incomplete cooperation by the affected person (submaximal effort), as shown by the uneven discharges that occurred in bursts. In (c) the recruitment sample was discrete because of loss of motor units, and the amplitude was markedly increased to 8�10 mV on account of collateral reinnervation (46-year-old man with motor neuron disease). An increased or decreased amplitude is therefore a relatively insensitive indicator of motor unit abnormalities. This has been useful in serial research to comply with the disintegration of the motor unit in sufferers with postpolio syndrome. In contrast to the macroelectrode, the single-fibre electrode has a small recording area of 25 �m (0. The primary use of the single-fibre electrode has been in the recognition of disorders of neuromuscular transmission. The timing of the discharges of two (or more) muscle fibres in the motor unit is followed during repetitive exercise. Whereas the discharges are quite steady in normal muscle, they become unstable in myasthenia gravis or Lambert�Eaton syndrome. The amplitude (in millivolts) is measured either at the negative part or peak to peak. The area and period of the adverse section are useful within the evaluation of temporal dispersion or conduction block. The response may be recorded through floor electrodes positioned on the skin above the nerve or via needle electrodes placed close to the nerve. Surface electrodes are easy to apply but have a lower sensitivity than needle electrodes. Sensory responses may be recorded antidromically (efferent conduction with proximal stimulation, distal recording) or orthodromically (afferent conduction with distal stimulation, proximal recording). The recording and reference electrodes could additionally be positioned longitudinally in relation to the nerve (bipolar recording) or the reference electrode may be placed transversely at a remote site (unipolar recording). This is discouraged as a end result of this a half of the response is a summation of each giant and small fibres. A change in summation as a outcome of temporal dispersion due to this fact precludes measurements to the identical group of fibres. The mild-to-moderate slowing of conduction distal to the elbow was probably as a outcome of the lack of massive fibres. Focal nerve lesions the variety of patients referred to the medical neurophysiology laboratory with a question of focal nerve lesions as a end result of compression or entrapment at root degree or alongside the course of the nerve far outweighs other neuromuscular disorders. In entrapment and focal compression neuropathy, the main pathological abnormalities comprise demyelination at the web site of the lesion and this is sophisticated by axonal loss in advanced lesions. To ensure that the median nerve is selectively affected, the latency to the nonaffected ulnar nerve must be normal. Both (a) motor and (b) sensory conduction confirmed normal conduction velocities distal to and throughout the elbow. The lack of sensory fibres was inconsistent with a root lesion and suggested entrapment on the brachial plexus. Generalized nerve lesions (peripheral neuropathy) the electrophysiological research in sufferers suspected of polyneuropathy ought to document the wide distribution of pathological abnormalities. It is, therefore, a prerequisite that a number of motor and sensory nerves in the upper and lower limbs are investigated. However, the research must be individually tailor-made to delineate the distribution of adjustments, and the strategy should reflect the symptoms and scientific findings, and therefore the differential diagnostic questions. For example, it could be necessary to examine some nerves bilaterally if the symptoms are asymmetrical. This would enable the investigation to present whether the patient has a mononeuropathy, a multiple mononeuropathy, or a polyneuropathy with asymmetrical options. Axonal polyneuropathy the underlying pathology in most patients with peripheral neuropathy is axonal loss in a symmetrical distribution, primarily positioned at distal nerve segments and extra pronounced in the legs than within the arms. In rarer forms of neuropathy, solely motor or sensory fibres are involved, and demonstration of such a distribution might have necessary implications in the differential diagnosis. The findings in this affected person have been consistent with axonal loss, primarily present within the very distal phase of the nerve. Demyelinating neuropathy Primary demyelination often has a hereditary, inflammatory, or autoimmune basis. The fibre diameter distribution showed lack of each small and large fibres with a maximal diameter of 10�11 �m. Criteria have been established to assist in the analysis of those demyelinating neuropathies (Table 24. Conduction block may occur in acute inflammatory demyelinating (poly)neuropathy or chronic inflammatory demyelinating polyneuropathy, and in some instances of gammopathy. However, demyelination as a end result of compression may cause conduction block, and in demyelinating neuropathy conduction block must due to this fact be demonstrated outside the standard sites of entrapment or compression. The pathophysiological adjustments in inflammatory demyelinating diseases normally present a multifocal pattern, with some nerves exhibiting pronounced adjustments, whereas different nerves or nerve segments have normal conduction. However, conduction alongside the nerve segment distal to a focal lesion might continue for a number of days before Wallerian 24. The electrophysiological options of these sufferers are distinct with conduction block of motor fibres indicating focal demyelination. Patients with chronic inflammatory demyelinating polyneuropathy may have primarily motor symptoms with solely minimal sensory deficits.
Usage: a.c.
Glomus tumour (glomangioma) Glomus cells are modified easy muscle cells found in glomus bodies which are believed to operate as temperature receptors medications 1-z mentat 60 caps order free shipping. Solitary glomus tumours are characteristically present in finger suggestions and in nail beds and are exquisitely tender symptoms 3 days dpo mentat 60 caps buy generic online. The differential diagnosis would include causes of purpura treatment for depression 60 caps mentat sale, venous disease (lower limb only) treatment definition statistics discount mentat 60 caps visa, and angiosarcoma. Doxorubicin, bleomycin, and vincristine chemotherapy is extensively considered first-line therapy, although liposomal anthracyclines have additionally proved effective in superior illness. Angiosarcoma (lymphangiosarcoma) this is a malignant vascular tumour arising from each vascular (and lymphatic) endothelium which occurs in three settings: (1) as a main occasion on the face, scalp, or neck usually in older individuals; (2) related to lymphoedema (although finest described following mastectomy (Stewart�Treves syndrome)) lymphangiosarcoma can occur in any long-standing lymphoedema); and (3) postirradiation. Consequently, extensive excision, if attainable, is the one treatment and the prognosis is poor. Pyogenic granuloma (lobular capillary haemangioma) Pyogenic granuloma is a misnomer. Neither pyogenic nor granulomatous, the lobular capillary haemangiomas are benign vascular tumours that represent excessive manufacturing of granulation tissue often in response to injury. They can be indistinguishable clinically from amelanotic melanomas and ought to be handled by excision biopsy, although curettage will suffice if confident of the prognosis. Usually flat patches (like purpura or purple stain) or barely raised lesions can progress to plaques or nodules. The attribute colour, sluggish development, and multifocal distribution ought to suggest the analysis. Crops of cutaneous vascular lesions develop, normally on the decrease limbs, associated with gross oedema, lymphadenopathy, and generally visceral involvement. Skin biopsy is characteristic, demonstrating a proliferation of jagged, irregular lymphatic-like vascular channels lined by a single layer of bland endothelial cells. An inflammatory infiltrate is related to purple cell extravasation and haemosiderin deposition (explaining the purple to brown pores and skin discoloration on blanching). Lymphatic disorders the lymphatic system has long been a uncared for space of drugs largely because, lymphoma excepting, it has not produced any lifethreatening illnesses nor has the technology been out there to indicate the contribution of lymphatics to pathology. The latest discovery of particular genes and proteins, nonetheless, has catapulted lymphatic biology onto the research agenda of cancer unfold, infection and irritation, bronchial asthma, organ transplant rejection, and lymphoedema. The lymphatic system is actually a drain, returning to the blood circulation protein and fluid undesirable by the tissues. This completes the extravascular circulation of fluid and protein and maintains tissue quantity homeostasis. Cells similar to extravasated leucocytes and activated antigen-presenting cells enter the initial lymphatics and are transported to lymph nodes the place particular immune responses to international materials are generated. Lymphatic capillaries are thin-walled vessels however capacious and doubtlessly larger than nearby blood capillaries. Intermittent adjustments in tissue pressures, exterior to preliminary lymphatics, are mainly liable for lymph absorption and transport. Lymphangiogenesis Lymphatic vessels were discovered earlier than the blood circulation, however the first growth factors and molecular markers particular for lymphatics had been found solely 15 years in the past. Subsequently, a sign transduction system is liable for lymphatic endothelial cell progress, migration, maturation, and survival. From here they migrate to type main lymph sacs and the primary lymphatic plexus. Lymphoedema A failure of lymph drainage causes a build-up of protein and fluid throughout the tissues (lymphoedema). When this occurs within the pores and skin and subcutis the tissues become swollen and undergo attribute adjustments. An improve of intralymphatic stress (lymphatic hypertension) ends in enlargement of the dermal preliminary lymphatics. If compliance permits, distended lymphatics bulge like blisters on the pores and skin surface (lymphangiectasia), resulting in leakage of lymph fluid (lymphorrhoea). If disruption to lymph drainage includes the lymphatics draining the intestinal lacteals, then rerouting/backflow of chylous lymph can result in leaking of milky chyle from the pores and skin surface, particularly after a fatty meal. Chronic distension of dermal lymphatics and accumulation of protein-rich fluid throughout the skin ends in a cobble stone look to the skin (papillomatosis) and a build-up of floor keratin (hyperkeratosis). In tropical medication and parasitology, the term elephantiasis is synonymous with lymphoedema resulting from filarial infection, but elephantiasis skin adjustments can occur with any form of lymphoedema no matter cause. If left untreated, elephantiasis progresses to marked fibrosis with little proof of pitting oedema. Indeed, the pathology of lymphoedema is advanced involving proliferation of inflammatory cells, adipocytes, fibroblasts, and blood vessels (angiogenesis). Elephantiasis refers to the thickened pores and skin with papillomatosis and hyperkeratosis. Lymphangitis the lymphatic system has advanced in humans as a number defence mechanism. Noxious brokers and predators corresponding to micro organism, if not handled at the point of entry to the host, entry the lymphatic system. Lymphatic vessels, along with adjoining lymph nodes, successfully act as a second line of defence preventing further onward unfold and limiting systemic involvement. Lymphangitis represents irritation of the lymphatic collectors and is clinically seen as tender purple streaks spreading up the limb corresponding to the inflamed vessels. Inflammation of downstream lymph nodes, generally known as lymphadenitis, manifests with painful, tender, swollen glands. In one epidemiological research, 64 (29%) of 218 sufferers recognized with lymphoedema had suffered at least one attack of cellulitis inside the previous 12 months with 16 (8%) experiencing greater than three episodes. Any affected person with recurrent assaults of cellulitis in the same leg nearly actually has compromised lymph drainage in that leg. Unlike typical cellulitis (in an immunocompetent site), the primary signal of illness is often constitutional upset with flu-like symptoms, fever, rigors, or vomiting. Only some hours later could a blotchy rash, ache, and elevated swelling appear with Infection and lymphatic failure Recurrent an infection. Lymphatic vessels take part within the regulation of an inflammatory response through their position in transport of lymphocytes to and from lymph nodes. A consensus document on the administration of cellulitis in lymphoedema emphasizes the necessity to right threat elements. When attacks occur greater than twice a year, prophylactic antibiotics are indicated, corresponding to penicillin V (phenoxymethylpenicillin) 500 mg every day. Tropical lymphoedemas Lymphatic filariasis Adenitis and lymphangitis are major acute manifestations of lymphatic filariasis. Lymphangioma circumscriptum, because the name implies, is localized to an space of pores and skin, subcutaneous tissue, and typically muscle. There might or is probably not swelling depending upon extension into deeper tissues, but pitting oedema is absent. Although lymphangioma circumscriptum is often evident at or quickly after Tumour metastasis Lymphatic spread is the preferential route of metastasis for many human cancers, with sentinel lymph node assessment as an important prognostic indicator in, for instance, melanoma and vulval and penile cancers, where progress factor stimulation of lymphatic vessels enhances lymphatic metastasis. The infected space could show a definite raised part due to palpable infiltrated lymphatics and oedema. Radical surgery offers the only chance of remedy, however a conservative strategy with simple electrocautery to right the weeping (lymphorrhoea) is suggested. Diffuse lymphangioma indicates a extra in depth malformation which can contain a whole hindquarter. Limb swelling could also be due both to lymphoedema or to gross dilatation of irregular lymphatic channels, whereas pores and skin floor lymphangiomas might coexist with blood vascular malformations. Diffuse lymphangiomas could type a part of the Klippel�Tr�naunay syndrome with limb and tissue overgrowth. Although often current at birth, some current in maturity after a local disturbance stimulates lymph absorption. Primary chylous reflux arises from congenitally incompetent megalymphatics (lymphangiectasia with valve incompetence) or lymphatic hypoplasia when lymph/chyle is pressured to reroute. Secondary (acquired) reflux is type of all the time caused by thoracic duct obstruction brought on by filariasis, malignant disease, or trauma (accidental or surgery). Treatment includes lowering chyle manufacturing by following a strict, no fats food regimen supplemented with medium chain triglycerides and further nutritional vitamins.
Tags: generic mentat 60 caps with visa, discount mentat 60 caps without prescription, buy discount mentat 60 caps, generic 60 caps mentat mastercard, mentat 60 caps discount on line, 60 caps mentat proven, purchase 60 caps mentat overnight delivery, generic 60 caps mentat overnight delivery, buy mentat 60 caps on-line, best mentat 60 caps, 60 caps mentat generic fast delivery, mentat 60 caps buy generic, mentat 60 caps line, 60 caps mentat buy mastercard, buy generic mentat 60 caps online, generic mentat 60 caps line
8 of 10
Votes: 271 votes
Total customer reviews: 271
Customer Reviews
Nafalem, 48 years: Transient ischaemic attacks these assaults ought to seldom be confused with epilepsy. This vascular injury might not solely disrupt the conventional autoregulation of cerebral blood flow, however, in severe circumstances, the vessel could become obstructed with thrombus, causing a cerebral infarct. Many of those issues require persistent diagnostic skills and investigation; but when mixed with information of general principles, including the anatomy and physiology of the vital thing cranial buildings, the administration of headache is generally productive and useful for the sufferer. Also included listed under are miscellaneous motion problems, similar to hemifacial spasm, myokymia, and myorhythmia.
Ugolf, 44 years: Scale may be either mild and yellow or composed of dense, adherent white material that exposes pin point bleeding of the scalp when picked off. Systemic lupus erythematosus is identified if 4 or more of the American College of Rheumatology revised standards for the classification of the disease are current, either sequentially or concurrently. Prolonged episodes of severe flushing accompanied by sweating, flushing, sweating not restricted to the face, and associated systemic symptoms corresponding to diarrhoea, wheezing, headache, or palpitations should immediate investigation for carcinoid syndrome, phaeochromocytoma, or mastocytosis. Terbinafine is barely more practical than itraconazole in dermatophyte infections, but probably much less efficient towards Candida spp.
Zapotek, 46 years: This progresses to vomiting, hypotension, oliguria, metabolic acidosis, and hyperkalaemia. Its stimulant properties are much like modafinil but it possibly lacks the cardiovascular side-effects. Prolonged bleeding from the umbilical wire often permits early recognition of an affected youngster. There is evidence of different neurodegenerative ailments or conditions in addition to cerebrovascular disease that will have an effect on cognition, such as: a.
