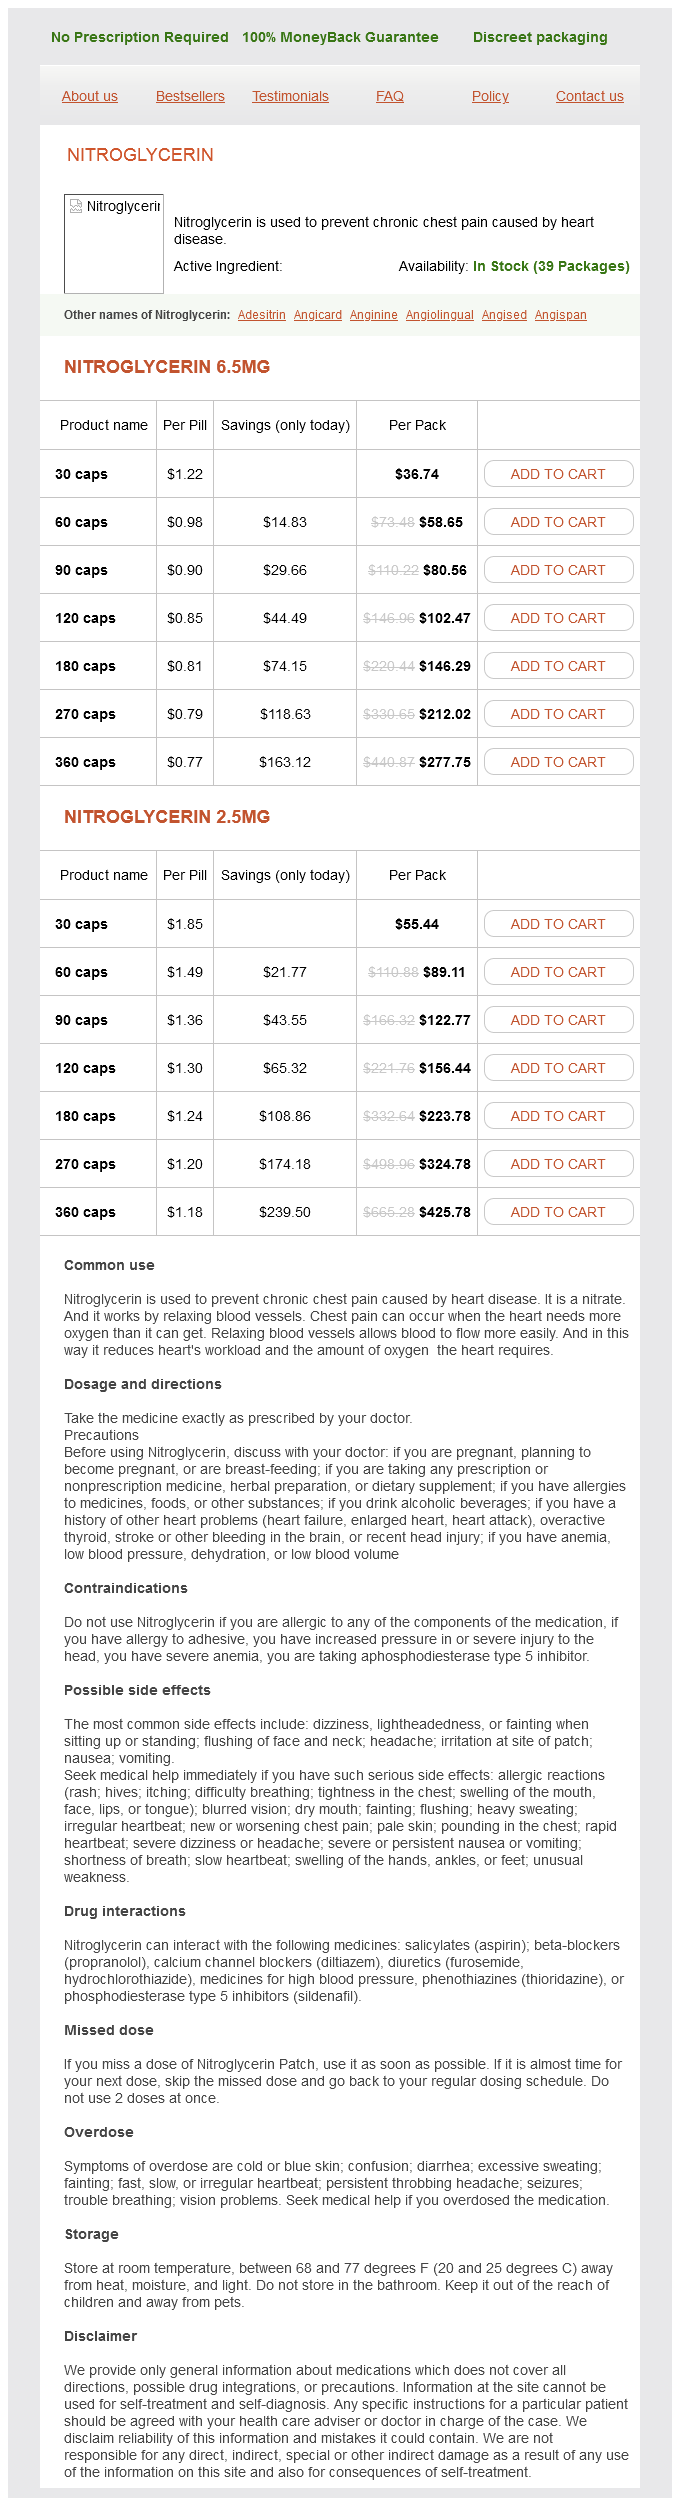
Nitroglycerin 6.5mg
- 30 caps - $36.74
- 60 caps - $58.65
- 90 caps - $80.56
- 120 caps - $102.47
- 180 caps - $146.29
- 270 caps - $212.02
- 360 caps - $277.75
Nitroglycerin 2.5mg
- 30 caps - $55.44
- 60 caps - $89.11
- 90 caps - $122.77
- 120 caps - $156.44
- 180 caps - $223.78
- 270 caps - $324.78
- 360 caps - $425.78
Nitroglycerin dosages: 6.5 mg, 2.5 mg
Nitroglycerin packs: 30 caps, 60 caps, 90 caps, 120 caps, 180 caps, 270 caps, 360 caps
In stock: 528
Only $0,77 per item
Description
Adjuvant Systemic Chemotherapy Standard adjuvant chemotherapy regimens embrace a fluoropyrimidine (fluorouracil [with leucovorin] or capecitabine) as a single agent and in combination with oxaliplatin symptoms viral infection cheap 6.5 mg nitroglycerin overnight delivery. Combinations of fluorouracil plus leucovorin have been studied extensively in the adjuvant setting medications held for dialysis 2.5 mg nitroglycerin generic, based on the statement that fluorouracil plus leucovorin considerably improves response charges as compared with fluorouracil alone for metastatic disease medications used to treat bipolar buy 2.5 mg nitroglycerin with amex. When leucovorin is unavailable medicine 512 6.5 mg nitroglycerin generic, levoleucovorin, the active isomer of racemic leucovorin, can be substituted instead. This technique of administration is now the most typical methodology of administration in the United States and has changed the Roswell Park and Mayo Clinic regimens. Clinically significant variations in toxicity happen based mostly on the dose, route, and schedule of fluorouracil administration. In this strategy, the patient is instructed to chew and maintain ice chips in the mouth during the period between 5 minutes previous to and 30 minutes following the bolus injection of fluorouracil. The protective results of this process are in all probability associated to the native vasoconstriction attributable to the ice chips, which temporarily reduces blood move to the oral mucosa, thereby reducing drug publicity to the oral mucosa. A rare pharmacogenetic disorder characterised by full or near-complete deficiency of this enzyme has been identified in patients with cancer. Patients with this enzyme deficiency develop extreme toxicity, together with death, after fluorouracil administration. A weekly or bimonthly schedule of leucovorin plus fluorouracil (either bolus or steady infusion) may be more convenient for the patient by means of fewer scheduled clinic appointments, less interference with work schedules, and ease of dose changes based mostly on toxicity. The neuropathies usually occur peripherally, however may happen within the jaw and tongue. A rare acute syndrome of pharyngolaryngeal dysesthesia (1%-2% of patients) is characterized by subjective sensations of difficulty in swallowing and shortness of breath. Overall, acute neuropathies occur in about 90% of sufferers, and are precipitated or exacerbated by exposure to chilly temperatures or chilly objects. Thus, sufferers should be instructed to avoid cold drinks and use of ice, and to cowl skin earlier than exposure to cold or chilly objects. Several prophylactic and therapy strategies have been studied with varying levels of success. Persistent neuropathy is usually a cumulative adverse impact, occurring after 8 to 10 cycles. The neuropathy is characterised by paresthesia, dysesthesia, and hypoesthesia, however may also embody deficits in proprioception that may intervene with daily actions (eg, writing, buttoning, swallowing, and problem walking because of impaired proprioception). Persistent neuropathy occurs in about one-half of patients receiving oxaliplatin however usually resolves with dosage reductions or cessation of oxaliplatin remedy. Anticonvulsant and antidepressant brokers are probably helpful to deal with signs. Capecitabine Regimens Capecitabine has been evaluated in adjuvant studies as a substitute for fluorouracil in an attempt to enhance the security and ease of administration of the chemotherapy regimen. Capecitabine is converted to fluorouracil via a three-step activation course of, the ultimate step being activation by thymidine phosphorylase, which is current in best concentrations on the tumor web site. These activation steps result in about a threefold enhance in tumor fluorouracil levels. The toxicities differed for the 2 regimens, with increased risks of neuropathies and hand�foot syndrome with CapOx and increased danger of neutropenia/neutropenic fever with fluorouracil. In specific, the incidence of diarrhea, stomatitis, and neutropenia was decreased with capecitabine, but the incidence of hand�foot syndrome was elevated with capecitabine. Patients with renal dysfunction can accumulate drug and infrequently require dose modification. This routine is beneficial when patients are thought-about unable to tolerate combination remedy. For example, sufferers who develop extreme hand�foot syndrome could tolerate bolus fluorouracil/leucovorin because this toxicity is minimal with this administration methodology. Current tips discourage the use of age as a sole determining consider choosing an adjuvant chemotherapy routine. However, subset evaluation of large scientific trials has shown that patients older than the age of 70 years may not profit from adjuvant oxaliplatin and may need to be treated in a unique way. Adjuvant and Neoadjuvant Therapy for Rectal Cancer Rectal most cancers includes those tumors discovered under the peritoneal reflection in essentially the most distal 15 cm of the large bowel, and as such is distinct from colon cancer in that it has a propensity for both local and distant recurrence. The greater incidence of local failure and overall poorer prognosis associated with rectal cancer is a result of anatomic limitations in excising enough radial margins across the rectal tumor. Patients are generally classified as having resectable, probably resectable, or unresectable metastatic illness. Chemotherapy is for disseminated disease and the primary treatment modality for unresectable metastatic colorectal most cancers. Patients with resectable or potentially resectable metastases are candidates for multimodality remedy. Resectable or Potentially Resectable Metastatic Colorectal Cancer Surgery Up to 25% of sufferers will current with hepatic metastases on the time of analysis, and 60% of patients with colorectal most cancers will develop hepatic metastases someday during the course of their illness. Adjuvant systemic chemotherapy is really helpful to cut back the danger of recurrence following resection. Neoadjuvant chemotherapy, additionally referred to as conversional chemotherapy, is the primary methodology to enhance full resection charges in both sufferers with resectable or potentially resectable liver or lung lesions. In some cases, people with metastatic disease initially deemed unresectable may obtain significant tumor regression following neoadjuvant chemotherapy to then be thought of for surgery. Administration of each pre- and postoperative chemotherapy is common practice, however hepatotoxicity related to preoperative chemotherapy should be considered. Steatohepatitis occurs in 4% to 28% of patients who obtain irinotecan-containing regimens and vascular sinusoidal obstructive liver damage develops in 10% to 61% of sufferers receiving oxaliplatin. Preoperative chemotherapy is restricted to a 2- to 3-month time period, and patients undergo close monitoring. Postoperative chemotherapy must be administered to sufferers to full a total of 6 months of chemotherapy (pre- and postoperative). However, because the first aim is surgical resection every time attainable, sufferers must be evaluated for attainable resection after each 2 months of therapy. If resection occurs, adjuvant chemotherapy ought to be administered to complete a complete of 6 months of chemotherapy. Hepatic-Directed Therapies Individuals with liver-only or liver-predominant metastatic illness may be thought of for hepatic-directed therapy in addition to or as an alternative selection to surgical resection. Floxuridine with dexamethasone and fluorouracil with or with out leucovorin are mostly used brokers. This procedure includes the instillation of a mix that includes chemotherapeutic agents, radioactive contrast dye, and/or an embolic agent instantly into the hepatic artery. Agents most commonly used embody doxorubicin, mitomycin, and cisplatin, which are normally dissolved in about 10 to 15 mL of a radiographic contrast dye. Addition of an embolic agent to the mixture leads to either a brief or everlasting occlusion of the hepatic artery. Alternatively, drug-eluding beads of doxorubicin or irinotecan blended with an embolic agent have been used. Local tumor response charges with these strategies are excessive and most patients will expertise partial or complete relief of symptoms. Toxicities embrace postembolization syndrome characterised by nausea, fatigue, and transient elevations in hepatic enzymes and bilirubin, gastrointestinal ulcerations, and biliary toxicity. Although numerous hepatic-directed therapies provide potential disease palliation in choose patients with unresectable, yet restricted hepatic metastases, no conclusive survival advantage has been demonstrated. Other much less frequent methods include tumor ablation procedures using radiofrequency ablation or microwave power to generate heat that destroys localized tumor cells. Cryoablation can also be used, which includes placement of a cryoprobe into the tumor, either percutaneously or intraoperatively, and then reducing the probe temperature to �20�C to �40�C and rewarming it in cycles, leading to formation of an ice ball that causes tumor destruction. Systemic chemotherapy palliates signs and improves survival in sufferers with unresectable illness. Table 130-8 lists common preliminary chemotherapeutic regimens for metastatic disease. The benefit of palliative chemotherapy for metastatic colorectal most cancers as in comparability with remark or supportive care alone with regard to these treatment objectives has been established. Results from a quantity of randomized trials and meta-analyses demonstrate that chemotherapy prolongs life and improves quality of lifetime of sufferers with metastatic colorectal most cancers. Patients considered acceptable for initial intensive chemotherapy sometimes receive an oxaliplatin or irinotecan-containing regimen with infusional fluorouracil plus leucovorin and bevacizumab. Incidence of any grade and reasonable to severe toxicities was comparable among therapies. Median time to worsening performance status was longer with trifluridine/tipiracil than with placebo (5.
Latakasturi (Ambrette). Nitroglycerin.
- Dosing considerations for Ambrette.
- Spasms, snakebites, stomach cramps, low appetite, headaches, stomach cancer, hysteria, gonorrhea, lung problems, and other conditions.
- What is Ambrette?
- Are there safety concerns?
- How does Ambrette work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96064
Adequate surgical debridement to take away all the dead bone and necrotic material symptoms tuberculosis buy 2.5 mg nitroglycerin mastercard, combined with prolonged administration of antibiotics treatment 4 hiv 2.5 mg nitroglycerin discount overnight delivery, offers the best chance to acquire a remedy medicine 5513 nitroglycerin 6.5 mg buy overnight delivery. Infectious Arthritis While many patients who develop infectious arthritis recuperate with no long-term sequelae medications 44334 white oblong generic nitroglycerin 2.5 mg fast delivery, 50% are left with decreased joint operate or mobility. Gonococcal arthritis usually resolves quickly with antibiotics and has fewer sequelae. Individuals at best risk for long-term sequelae are those that have symptoms current for greater than 7 days earlier than beginning therapy and those with infections occurring inside the hip joint and infections brought on by Gram-negative organisms. Common long-term residual results following infectious arthritis are limited joint movement and protracted ache. During the initial section of the infection, weight bearing, such as strolling on the joint must be prevented. Passive range-of-motion exercises should be initiated when the pain begins to subside to keep joint mobility. Approximately one-third of patients with bacterial arthritis have a poor joint consequence, similar to extreme functional deterioration. Poor joint outcomes are associated with older patients, these with preexisting joint disease, and sufferers with an contaminated joint containing artificial material. General Approach to Treatment Osteomyelitis Following completion of the steps wanted to determine the infecting organism, the most important remedy modality of acute osteomyelitis is the administration of applicable antibiotics in enough doses for a enough length of time. It is essential to stress that early antibiotic remedy can mitigate the necessity for surgery, subsequent sepsis, persistent infection, disruption of longitudinal bone progress and angular deformity of the bone. Chronic suppressive antimicrobial remedy and adjunctive treatment with hyperbaric oxygen or antibiotic-impregnated implants during surgical procedure additionally has been used. It is important to emphasize the priority of starting antibiotics immediately after the cultures have been obtained. Infectious Arthritis Patients with infectious arthritis are sometimes admitted to the hospital to acquire synovial fluid and blood cultures and provoke antimicrobial therapy. Attempt to decrease bacterial burden in the joint area is obtained by performing both open or arthroscopic debridement. As with osteomyelitis, it is necessary to stress early initiation of antibiotic remedy to avoid problems similar to avascular necrosis, limb-length discrepancy, and pathologic fractures. Although it could be determined to retain the implant in sure instances for which sufferers will obtain irrigation and debridement in addition to antibiotic remedy, or antibiotic therapy alone in sufferers unable to tolerate surgical procedures. Empiric remedy have to be chosen on the premise of the most probably infecting organism while the results of tradition and susceptibility information are pending. Once tradition and susceptibility results are obtained the antimicrobial remedy should be tailored. Quality of evidence: 1 = Evidence from multiple correctly randomized, managed research or a number of time series; or dramatic results from uncontrolled experiments. With staphylococcus being the most typical micro organism in osteomyelitis, resistance patterns should be thought of when deciding on an empiric agent. For enterococcus, add 4-6 weeks of aminoglycoside remedy in Children: 30 mg/kg/day sufferers with infective endocarditis3 in three equal doses (max Antimicrobial Dosea dose 1. For enterococcus, add 4-6 weeks of aminoglycoside remedy in sufferers with infective endocarditis. Oral Antibiotic Therapy Criteria for using oral outpatient antibiotic remedy for osteomyelitis contains all of the following: Confirmed osteomyelitis Initial scientific response to parenteral antibiotics Suitable oral agent out there Adherence ensured Suitable candidates are children with good medical response to intravenous remedy and adults without diabetes mellitus or peripheral vascular illness. The patients enrolled in oral antibiotic trials generally had illness of latest onset, identification of a particular infecting organism, enforced adherence, and surgical procedure as indicated. In patients who meet these criteria, oral antibiotics appear to provide a fantastic advantage within the therapy of osteomyelitis. Patients not assembly these standards may have the next threat of creating persistent osteomyelitis if oral therapy is inappropriate or not strictly adhered to . When oral antibiotics are used, the whole length of oral and injectable therapy is often no much less than 4 weeks. Limited retrospective knowledge in adults indicated that parenteral remedy for less than four weeks adopted by oral therapy could additionally be efficient. One analysis in youngsters with hematogeous osteomyelitis recommended 20 days of antibiotic remedy after initial parenteral remedy so lengthy as the C-reactive protein level normalized inside 7 to 10 days. Treatment failures could additionally be because of the presence of infected necrotic bone or contaminated hardware (wires, plates, screws, and rods) that might not be removed. In some cases of persistent osteomyelitis, lifelong suppressive remedy could be the most appropriate possibility. With Gram-negative micro organism a longer period (greater than or equal to 8 weeks) is related to much less rates of recurrence in comparability with shorter durations (4-6 weeks). Vertebral osteomyelitis-The precise length of antimicrobial therapy for a affected person with vertebral osteomyelitis is unknown. Many elements play a task in figuring out the severity of the an infection and threat of recurrence. Longer courses might be wanted in patients with Gram unfavorable infections or infections sophisticated by abscesses. Special Populations Osteomyelitis in the intravenous drug person has unique options. They even have an unusual spectrum of organisms with Gram-negative organisms being answerable for 88% of infections. Klebsiella, Enterobacter, and Serratia species additionally can be found however much less commonly. Patients with sickle cell anemia and related hemoglobinopathies additionally represent a singular inhabitants in that two-thirds of bone infections in these patients are caused by Salmonella species, while the rest are normally caused by staphylococci and different Gram adverse organisms. Osteomyelitis in patients with sickle cell disease could occur in any bone, but it mostly entails the medullary cavity of long or tubular bones. Because of the issue in separating bone pain during a sickle cell disaster from that of an infection, osteomyelitis could be comparatively advanced in these patients by the time the analysis is made. Infectious Arthritis Antibiotic Selection the three most important therapeutic maneuvers in the administration of infectious arthritis are appropriate antibiotics, joint drainage, and joint relaxation. Smears of the synovial fluid could be useful to choose acceptable antibiotic therapy initially. [newline]A delay in initiating antibiotics significantly increases the chance for long-term complications. In prosthetic joint infections, antimicrobial cement spacers are sometimes used to aide in delivery of the antimicrobial to the site of an infection. The commonest antimicrobials used include vancomycin and aminoglycosides, tobramycin and gentamicin. Antimicrobial cement spacers-The use of antimicrobial cement spacers is routine for patients with prosthetic joint infections. The antimicrobial agents used locally could place the patient at risk for systemic opposed reactions with little benefit added to systemic remedy. Similar to osteomyelitis, once the an infection is confirmed if initial response to parenteral therapy is achieved, the tradition susceptibilities have resulted, and adherence is ensured, then chosen oral antibiotics can be used for the remedy of infectious arthritis. Shorter durations of antimicrobial therapy are needed to deal with infectious arthritis compared to osteomyelitis. A randomized trial compared 10 days versus 30 days of antimicrobial remedy and located no difference between the teams. Administration of antibiotics in the house surroundings and the use of antibiotics with extended elimination half-lives are generally used. Although acute osteomyelitis is probably considered one of the extra common infectious diseases that can be treated with home intravenous antibiotics, not all sufferers are acceptable candidates for residence administration. Patients must be screened to embody solely those that are receiving a steady therapy program, those that are interested and are motivated in taking part, and those who have good venous entry, as well as those that have assist from family members or neighbors and have house amenities for storage and refrigeration. Patients with sufficient vascular entry might be able to use a peripheral intravenous catheter; nevertheless, a central intravenous catheter could also be required if venous access difficulties happen. Complications of other preexisting diseases, corresponding to diabetic retinopathy, intention tremor, disabling irritation or degenerative joint illness, coagulopathies, or varied neurologic disorders can forestall people from receiving house antibiotics. A history of alcoholism or of intravenous drug abuse also is necessary exclusion standards. In addition to assembly these preliminary screening standards, patients should successfully full an intensive coaching program earlier than hospital discharge. Aseptic technique, proper catheter care, and correct administration strategies should be documented. Once a affected person is receiving therapy within the home surroundings, continued monitoring of their antimicrobial remedy and drug levels when indicated is necessary. Catheter-related complications are widespread in sufferers receiving extended programs of parenteral antibiotics.
Specifications/Details
Viral Pneumonia Viruses are an unusual cause of pneumonia in adults treatment 1st line discount 6.5 mg nitroglycerin, except in the immunosuppressed symptoms checker quality nitroglycerin 6.5 mg. Other common viruses in youngsters embody parainfluenza medicine xanax buy discount nitroglycerin 2.5 mg, adenovirus medications osteoporosis 6.5 mg nitroglycerin cheap with visa, human metapneumovirus, bocavirus, and rhinovirus. Radiographic findings are nonspecific, embrace bronchial wall thickening and perihilar, and diffuse interstitial infiltrates. Pleural effusions may be seen, particularly in adenovirus and parainfluenza pneumonia. Serologic checks for virus-specific antibodies are used typically in epidemiologic and surveillance studies of viral infections since the diagnostic fourfold rise in titer between acute and convalescent part sera may require 2 to 3 weeks to develop. Pneumonia, respiratory misery syndrome, lymphopenia, and clotting abnormalities tend to occur quickly in sufferers contaminated with H5N1. The H1N1 virus affected usually healthy younger adults as opposed to different flu viruses, which are likely to be extra severe in the younger and the aged, and resulted in severe infections requiring hospitalization and dying. It is most distinguished in urban neighborhoods troubled with crowded circumstances and poor entry to healthcare; thus, groups vulnerable to tuberculosis embody the homeless and sufferers in chronic care amenities and homes for the elderly. Unlike previous eras during which tuberculosis was seen most frequently in elderly males, an infection presently is recognized in growing numbers of younger minority adults. Therapy ought to reduce associated morbidity, including one or each of the next: reversible or irreversible illness and drug-induced organ toxicity (eg, renal, lung, or hepatic dysfunction). Most instances of viral pneumonia are self-limiting, although remedy of influenza pneumonia with particular antiviral brokers (oseltamivir and zanamivir) could hasten recovery. All efforts ought to give consideration to the design of essentially the most cost-effective approach to remedy. Whenever potential, the oral (vs parenteral) route for drug administration should be chosen, encouraging outpatient management somewhat than hospitalization. Optimal treatment of infection/lower respiratory tract infection requires a rapid and accurate diagnosis, rapid initiation of efficient antimicrobial remedy, and correct antimicrobial stewardship. Comprehensive rules of optimal antimicrobial therapy and infectious ailments stewardship are mentioned in detail in Chapter 105. General Approach to Treatment the primary precedence in assessing the affected person with pneumonia is to evaluate the adequacy of respiratory function and to determine the presence of indicators of systemic illness, particularly dehydration or sepsis with resulting circulatory collapse. Oxygen or, in severe cases, mechanical air flow and fluid resuscitation should be supplied as needed. Further supportive care of the patient with pneumonia contains humidified oxygen for hypoxemia, administration of bronchodilators (albuterol) when bronchospasm is current, and chest physiotherapy with postural drainage if proof of retained secretions. Appropriate sputum samples could also be obtained to determine the microbiologic etiology. Rehydration should be provided to exchange losses that will have occurred on account of fever, poor consumption, and/or related vomiting. Respiratory tract an infection analysis and therapy guideline reports have been printed by authoritative professional organizations that focus on proper treatment regimens and should be consulted for evidence-based remedy suggestions throughout the spectrum of community- and/or hospital-associated pneumonias. Biofilms show particular properties and serve as a reservoir for pathogen dissemination and resultant systemic an infection. The colonies of pathogens they harbor could be proof against antimicrobial drug (eg, aminoglycosides) and immune cell penetration -biofilms could contain single or combined microbial communities. Biofilm-based microorganisms can produce a quantity of small, diffusible "communication" molecules-some are signaling molecules regulating cell density throughout the biofilm and different intracellular features. An in depth assessment of biofilms is past the scope of this chapter, but an excellent understanding of their many characteristics and approaches to fight them are pivotal to the design of efficient therapy of (lower respiratory tract) infections. Drugs which were studied embody corticosteroids, prostaglandin inhibitors, statins, immunoglobulin remedy, mediator-specific immunomodulators, angiotensinogen-converting enzyme inhibitors, and oral hypoglycemic brokers. Proposed mechanisms for some of the drugs have centered on protecting effects (eg, vasodilation and cough reflex) and antiinflammatory effects. The capacity of a drug to penetrate respiratory secretions depends on multiple physicochemical elements, together with molecular dimension, lipid solubility, and degree of ionization at serum and biologic fluid pH and the extent of protein binding. Studies carried out in animals and cystic fibrosis sufferers suggest that bigger molecular measurement favors the accumulation of drugs in bronchial secretions. This finding contrasts with information on drug penetration of other physiologic compartments, such because the cerebrospinal fluid, and may be a results of the trapping of lower-molecular-weight compounds in mucin pores. The unionized form of drug and lipid solubility additionally appears to favor drug penetration. Of notice, the pH of the infected bronchi typically is more acidic than that of regular tissue and blood. These components combined underscore the importance of considering the inhaled route of antimicrobial drugs for the treatment of sufferers with reasonable to severe pneumonia, particularly in high-risk affected person teams. Prior to the provision of newer -lactam and fluoroquinolone antibiotics possessing constantly potent exercise in opposition to multiple gram-negative pathogens, some investigators promoted the administration of antibiotics by direct endotracheal instillation. In addition, larger native concentrations of antibiotics, notably of the polymyxins (eg, colistin) and aminoglycosides are believed to overcome partially the substantial lower in antibiotic bioactivity noticed when these agents work together with the purulent material current in infectious foci. Limited information are available for assessing the influence of drug protein binding on the speed and quantity of respiratory secretion penetration. The aminoglycosides are giant polar molecules that diffuse poorly into tissue and respiratory secretions; however, with growing concentrations obtained with once-daily dosing, increased target-tissue concentrations could be expected with increasing individual doses. However, with the growing incidence of antibiotic-resistant micro organism many clinicians are focusing on greater ratios of higher than a hundred to 200 to suppress presumably resistant mutants of gram-negative pathogens. Conversely, concentration-dependent killing characteristics best correlate with profitable remedy with the -lactam/-carbapenem and macrolide courses of antimicrobials (see Chapter e104 and Chapter 105 for more in-depth discussion of antibiotic concepts). Investigators have assessed antibiotic concentrations in sputum, frequently describing sputum drug concentrations as a ratio of serum to sputum drug focus; nonetheless, caution must be exercised within the interpretation of those information. Data describing sputum drug concentrations is commonly tough to interpret because of differences in analytic methods, technique of sputum sampling, and random nature of sampling instances relative to drug dose. To more precisely describe the distribution characteristics of antimicrobial agents in sputum, analysis research should be designed to allow sequential repeated sputum sampling over a specified dosage interval under both first-dose and steady-state conditions. Recognizing the numerous deficiencies of utilizing sputum drug focus correlates for prognosticating antibacterial remedy, most investigators now favor the determination of drug concentrations in pulmonary epithelial lining fluid and alveolar macrophages. Multiple factors that help to outline the potential pathogens involved embody patient age, previous and present medication history, underlying disease(s), major organ function, and current medical standing. These elements must be evaluated to select an appropriate and effective empirical antibiotic routine in addition to the most acceptable route for drug administration (oral vs parenteral). Superiority of 1 antibiotic over another when both demonstrate related dose-normalized in vitro activity and tissue distribution traits is troublesome to outline. A full listing of antimicrobial brokers for particular pathogens is beyond the scope of this chapter and is offered in Chapter one hundred and five. Table 107-10 lists dosages for chosen antibiotics used for the remedy of bacterial pneumonia. The massive variety of costly medication mandates critical analysis for formulary choice and scientific use. Similarities of in vitro exercise, resistance to bacterial-inactivating enzymes, and general effectiveness often make rational therapeutic selections tough and even seem random. An understanding and software of inherent drug characteristics appears to be of the utmost significance for the choice of an optimal therapeutic regimen. The bacterial causes are comparatively fixed, even across geographic areas and patient populations. Unfortunately, pathogen resistance to normal antimicrobials is increasing (eg, penicillin-resistant pneumococci), which necessitates careful attention by the clinician to native and regional bacterial susceptibility patterns. Indiscriminate use of just lately introduced brokers will increase healthcare prices and, in some cases (eg, widespread use of fluoroquinolones), induces resistance amongst a big proportion of community-acquired organisms. Interestingly, the European National Institute for Health and Care Excellence pneumonia guidelines advocate point of care C reactive protein tests to assist in figuring out if antibiotics ought to be prescribed to patients with decrease respiratory tract infections when pneumonia has not been identified clinically. Evidence-based empirical therapy differs amongst outpatients, hospitalized sufferers, and hospitalized sufferers admitted to an intensive care unit (see Tables 107-8 and 107-9). Hospital-Acquired Pneumonia Antibiotic choice inside the hospital environment calls for larger care due to constant changes in antibiotic resistance patterns in vitro and in vivo. Strict and cautious control and, possibly, rotation of empirical antibiotics within the hospital setting could assist to restrict the emergence of resistant organisms. Symptoms, such as cough and malaise, could also be present for months following antibiotic therapy. For viral causes of pneumonia, antivirals such as oseltamivir and occasionally amantadine can be utilized, depending on viral susceptibility.
Syndromes
- Fever
- Thiothixene (Navane)
- Cancer
- Bleeding into joints
- Fever
- Injury to the nerves at the needle puncture site
- Do NOT burn poison ivy, oak, or sumac to get rid of it. The resins can be spread via smoke and can cause severe reactions in people who are far downwind.
- The cause of abnormal blood test results, such as liver or kidney problems
- Persistent headache
- Urgent urination
Related Products
Additional information:
Malignant tumors are characterised by an infiltrative destructive progress pattern with malignant cells growing in a disorganized method and dissection into stromal planes medicine synonym 6.5 mg nitroglycerin order with mastercard. Invasive epithelial adenocarcinomas are characterised by histologic subtype and grade medications and mothers milk 2.5 mg nitroglycerin buy, which measures the diploma of cellular differentiation symptoms gastritis nitroglycerin 2.5 mg purchase with mastercard. Undifferentiated tumors are related to a poorer prognosis than these lesions that are thought of to be nicely or moderately differentiated treatment centers for drug addiction 2.5 mg nitroglycerin buy visa. A common grading system for ovarian cancer was developed that mixes mitotic rating, nuclear atypia score, and architectural rating based mostly on the histologic pattern. The peak age of analysis ranges from 45 to sixty five years with 63 years as the median age of prognosis. Endometrioid carcinomas are seen in girls 40 to 50 years of age and comprise about 8% of ovarian carcinomas, of which about 6% are surface epithelial neoplasms. Mucinous carcinomas happen in women between forty and 70 years of age and account for about 36% of all ovarian cancers. The overall prognosis for mucinous carcinoma is healthier than for serous carcinoma as a result of most sufferers present with stage I illness. Clear cell carcinoma comprises about 3% of ovarian carcinomas in ladies, with a mean age of fifty seven years. In contrast to epithelial tumors, about 60% to 70% of germ cell tumors are stage I at diagnosis, which is said to earlier detection and response to symptoms in this younger affected person population. Finally, ovarian sex cord-stromal tumors account for 7% of all ovarian cancers and have a tendency to be recognized at an early stage. The current beneficial standard of care is surgery adopted by therapy with a platinum-based chemotherapy regimen. Ovarian cancer is normally confined to the stomach cavity, however unfold can happen to the lung, liver, and, much less generally, the bone or mind. Disease is unfold by direct extension, peritoneal seeding, lymphatic dissemination, or bloodborne metastasis. Pelvic examinations are noninvasive and well accepted and might detect large tumors with a sensitivity of 67% for detecting all tumors. It can be utilized to evaluate the scale and shape and to detect the presence of cystic or stable masses or stomach fluid. Prevention It is troublesome to make suggestions for prevention for the general population as a end result of ovarian most cancers is a sporadic illness with no established risk components. Noninvasive measures, corresponding to chemoprevention, have demonstrated some profit in decreasing the chance of growing ovarian cancer. Ovulation itself is taken into account a potential insult to the ovarian epithelium, increasing its susceptibility to injury and, finally, to most cancers. Interventions or reproductive situations associated with lowering the variety of ovulations, together with multiparity, might have a protecting effect for the prevention of ovarian cancer. However, the more invasive prevention interventions, similar to prophylactic surgical procedure and genetic screening, ought to be reserved for those ladies identified to be at high risk based on their heredity for creating ovarian cancer. Chemoprevention Although a quantity of agents have been investigated as chemoprevention of ovarian cancer, together with oral contraceptives, aspirin, nonsteroidal anti-inflammatory brokers, and retinoids, none of these agents is currently accepted as commonplace therapy for the prevention of ovarian most cancers. Oral contraceptives inhibit ovulation, which reduces the chance for potential for harm to the ovarian epithelium. When taken for longer than 10 years, oral contraceptives lower the relative risk to lower than 0. The proposed mechanism of these agents is the anti-inflammatory impact on normal ovulation and inhibition of ovulation. The objective is to remove healthy, at-risk organs earlier than any carcinogenic activity is initiated, finally lowering the risk of creating most cancers. These surgeries embody prophylactic oophorectomy or bilateral salpingo-oophorectomy and tubal ligation. These procedures will trigger surgical menopause, which could be associated with severe sizzling flashes, vaginal dryness, sexual dysfunction, and increased threat for growth of osteoporosis and coronary heart disease in these girls. Primary peritoneal cancers can typically result from "seeding" during the prophylactic surgery. It is recommended for peritoneal washings to be completed through the prophylactic surgical procedure to check for presence of peritoneal surfaces. If positive, then prophylactic surgical procedure would change to staging and therapy surgery to decide extent of illness and remove some other attainable lesions. Tubal ligation is another procedure that can probably cut back the risk for developing ovarian most cancers. Genetic Screening Genetic screening ought to be thought of for those ladies with a significant household historical past of ovarian most cancers. Patients with ovarian cancer typically current with nonspecific, vague signs similar to abdominal bloating, strain or ache, indigestion, or change in bowel movements. Patients will often not search medical consideration until these symptoms become unrelenting and bothersome, which allows the illness to progress undetected. Patients with superior disease might report symptoms such as pain, abdominal distension, and ascites. Furthermore, healthcare professionals should keep ovarian cancer within the differential for ladies presenting with these persistent signs. Symptoms the affected person may complain of abdominal discomfort, nausea, dyspepsia, flatulence, bloating, fullness, early satiety, urinary frequency, change in bowel function (diarrhea or constipation), weight change, and digestive disturbances. Patient could have signs of ascites (abdominal distension, shifting, and dullness to percussion-may present like "pregnant stomach"). Abnormalities in renal operate checks may counsel compression of the renal system by the tumor. Unfortunately, by the point a pelvic mass could be palpitated on physical exam, the disease is already advanced beyond the pelvic cavity. A detailed household history should be taken, especially noting the quantity and sample of first-degree relatives with malignancies. When a affected person presents with an belly mass, it is necessary to rule out other cancers within the abdominal cavity. Other diagnostic exams should embrace a transvaginal or stomach ultrasonography, chest radiography, computed tomography, magnetic resonance imaging, or positron emission tomography scan. While ideally Most "therapy for remedy" is desired, you will need to set realistic expectations for the patient. Although general survival has not considerably changed for ovarian most cancers sufferers, the progression-free survival has improved, which translates to much less time on chemotherapy and overall enchancment in quality of life for these patients. In the setting of recurrent platinum-resistant ovarian cancer, the treatment goal is also to alleviate symptoms and delay survival as long as high quality of life is acceptable. General Approach A multimodality approach that includes comprehensive surgical procedure and chemotherapy is used for the preliminary treatment of ovarian most cancers with curative intent. Although most sufferers will initially obtain a complete response, more than 50% will recur throughout the first 2 years. Chemotherapy regimens for ovarian most cancers have developed over the previous a quantity of decades. Treatment regimens started with single-agent melphalan adopted by single-agent cyclophosphamide. Shortly after cisplatin was introduced into scientific practice, it was added to cyclophosphamide, and this mixture was the "commonplace of care" for more than a decade until the introduction of paclitaxel within the 1980s. Paclitaxel soon replaced cyclophosphamide, and paclitaxel plus cisplatin turned the usual of care. Carboplatin was then substituted for cisplatin due to its improved toxicity profile, and paclitaxel plus carboplatin was adopted. The histologic subtype of the tumor is a prognostic factor; clear cell histology is extra likely to be poorly differentiated, faster growing, and have intrinsic drug resistance. For unknown causes, white women are likely to have a worse prognosis and response to therapy as in contrast with girls of different ethnic backgrounds. A complete exploratory laparotomy is important for the correct confirmation of prognosis and Unlike different cancers that are sometimes identified by biopsy or staging of ovarian most cancers. The talent of the surgeon has a major effect on prognosis, with definitive benefit of a educated gynecologic oncologist performing surgery as in contrast with a gynecologist or basic surgeon. It is beneficial that the initial surgical staging and tumor-debulking surgery be accomplished by a skilled gynecologic oncology surgeon when ovarian cancer is suspected to stop understaging and to optimize general end result. Secondary cytoreduction or interval debulking is when surgery is performed after completion of some or all chemotherapy to take away residual disease.
Usage: p.c.
An instance of this case is an abscess associated with diverticular illness of the colon treatment 4 autism 2.5 mg nitroglycerin. Management could include drainage of the abscess and resection of the concerned part of the colon symptoms 1dpo 2.5 mg nitroglycerin discount otc. All overseas materials treatment internal hemorrhoids buy 2.5 mg nitroglycerin, necrotic tissue symptoms viral infection order nitroglycerin 2.5 mg online, feces, blood, or pus ought to be removed from the operative subject, and the peritoneum should be copiously irrigated with 0. The management of an intra-abdominal abscess with percutaneous catheter drainage may be enough to resolve the infection. These minimal-access methods could provide advantages in comparison with traditional surgical procedure but will in all probability be used less usually than radiologically assisted percutaneous drainage strategies. The most dear microbiologic data may be obtained at the time of percutaneous or operative abscess drainage. The specimen must be taken promptly to the microbiology laboratory, the place a Gram stain should be performed immediately and cultures prepared for identification of aerobic and anaerobic bacteria. Fluid Therapy Patients should be evaluated for indicators of hypovolemia, hypoperfusion, and shock. Aggressive fluid repletion and management are required for successful therapy of intra-abdominal infections. Loss of fluid via vomiting, diarrhea, or nasogastric suction contributes to dehydration. Urine output must be monitored constantly in severely sick patients by use of a urinary bladder catheter, quantitated hourly, and should equal or exceed zero. In patients with peritonitis, hypovolemia is commonly accompanied by metabolic acidosis. Once targeted therapeutic targets are reached, maintenance fluids ought to be instituted with zero. The administration price must be primarily based on estimated every day fluid loss by way of urine and nasogastric suction, including zero. If appropriate fluid administration fails to restore target goals of perfusion, vasopressor therapy must be initiated. The criteria for blood transfusion are controversial, but a hematocrit of 25% is mostly accepted. In the person affected person, the decision is commonly determined by the overall medical standing and the ability of the affected person to compensate for the discount in oxygen-carrying capacity related to an acute anemia. Additional blood part therapy with fresh-frozen plasma or platelets is also based mostly on the needs of the individual affected person. Aggressive fluid therapy should typically be continued in the postoperative period as a end result of fluid will proceed to sequester within the peritoneal cavity, bowel wall, and lumen. Pharmacologic Treatment Antimicrobial Therapy the targets of antimicrobial remedy are (a) to control any bacteremia and stop the institution of metastatic foci of infection, (b) to scale back suppurative issues (eg, abscess formation) after bacterial contamination, and (c) to prevent native spread of present infection. After suppuration has occurred, a remedy by antibiotic remedy alone is very troublesome to achieve; antimicrobials could serve to enhance the results obtained with surgical procedure. An empirical antimicrobial routine ought to be began as soon as the presence of intra-abdominal an infection is suspected. Therapy have to be initiated based on the doubtless pathogens, potential resistance, and severity of patient sickness. Increased resistance among Gram-negative pathogens to fluoroquinolones and ampicillin�sulbactam emphasize the importance of using local susceptibility knowledge to information empiric therapy and tailoring the antibiotic routine based mostly on susceptibility outcomes. Predominant pathogens, as discussed in the preceding part, vary relying on the site of intraabdominal an infection and the underlying disease course of. Table 114-5 lists the likely pathogens against which antimicrobial agents must be directed. Empiric remedy should be guided by the local epidemiology of resistant pathogens, patient-specific danger factors for resistant pathogens, and patient severity of illness. Single-agent regimens (such as cephalosporins with anaerobic exercise, extended-spectrum penicillins with -lactamase inhibitors, and carbapenems) are as efficient but have the benefit of being less nephrotoxic in comparability with combos of aminoglycosides with antianaerobic brokers. This can additionally be true for antimicrobial treatment of acute bacterial contamination from penetrating abdominal trauma. If the causative pathogens are susceptible and the affected person has clinically responded, antimicrobial therapy may be completed orally with amoxicillin�clavulanate, metronidazole with either ciprofloxacin or levofloxacin, or moxifloxacin. Four days of antimicrobial therapy is sufficient for many intra-abdominal infections with adequate supply management. The regimen employed and duration of remedy is determined by the precise scientific circumstances (ie, the character of the underlying illness process, severity of illness, and risk of resistant pathogens). Recommendations For most intra-abdominal infections, the antimicrobial regimen must be efficient towards each cardio and anaerobic micro organism. Table 114-6 presents the really helpful agents for therapy of community-acquired complicated intra-abdominal infections from the Infectious Diseases Society of America and the Surgical Infection Society. Table 114-7 lists extra evidence-based recommendations for the therapy of sophisticated intra-abdominal infections. Most community-acquired infections are of mild-to-moderate severity whereas healthcare-associated infections are probably to be more extreme, harder to deal with, and extra generally because of resistant pathogens. Table 114-8 presents tips for remedy and various regimens for particular conditions. Empiric quinolone use should be averted except local antibiograms present >80% to 90% susceptibility of E. These brokers embrace B-3 meropenem, imipenem�cilastatin, doripenem, piperacillin�tazobactam, or ceftazidime or cefepime in combination with metronidazole. Aztreonam or an aminoglycoside may be used in place of ceftazidime or cefepime as long as combined with a Gram-positive agent three. Quinolones may be used rather than Gram-negative brokers if native Alternatives Peritoneal dialysis Initial empiric regimens should be lively against both Gram-positive (including S. Vancomycin should be used if concern for methicillin-resistant Staphylococcus spp. Linezolid or daptomycin ought to ideally be used to deal with vancomycinresistant Enterococcus spp. Pseudomonas aeruginosa: two agents with differing mechanisms of action, such as an oral quinolone plus ceftazidime, cefepime, tobramycin, or piperacillin Secondary Bacterial Peritonitis Perforated peptic First-generation cephalosporins ulcer 1. Ciprofloxacinb or levofloxacinb every with metronidazole or moxifloxacinb Third- or fourth-generation cephalosporin alone with metronidazole, piperacillin� 2. Antianaerobic cephalosporinsa Abscess Third- or fourth-generation cephalosporin with metronidazole, or piperacillin� 2. Ciprofloxacinb or levofloxacinb each tazobactam with metronidazole or moxifloxacin alone As above Use metronidazole if amoebic liver abscess is suspected 1. The regimen must be based on in vitro sensitivity exams Other General Liver Primary Agents Spleen Ceftriaxone or cefotaxime Same administration as for communityacquired complicated intra-abdominal infections as listed in Table 114-639 Ceftriaxone or cefotaxime Ceftriaxone or cefotaxime every with or with out metronidazole Other Intra-abdominal Infections Appendicitis Communityacquired acute cholecystitis Cholangitis Alternatives Moxifloxacinb or levofloxacinb Severe an infection, piperacillin/tazobactam, antipseuodomonal carbapenem, aztreonam with metronidazole Vancomycin with aztreonam with or without metronidazole 1. Ciprofloxacinb or levofloxacinb each with metronidazole or moxifloxacin alone Acute Antianaerobic cephalosporinsa or contamination metronidazole with both ceftriaxone or from stomach cefotaxime trauma or ceftizoxime; these agents should be avoided empirically except native antibiograms show >80% to 90% susceptibility of E. Most patients with extreme intra-abdominal an infection, sepsis of intra-abdominal supply, or healthcareassociated an infection should be positioned on piperacillin�tazobactam, cefepime with metronidazole, or a carbapenem with Pseudomonas activity corresponding to imipenem, doripenem, or meropenem. In patients with IgE-mediated allergic reactions to -lactams (hives/urticaria, bronchospasm, angioedema, or anaphylaxis), combination remedy with aztreonam, vancomycin and metronidazole could also be used. Aminoglycosides are reserved primarily for infections due to presumed or proven multidrug-resistant pathogen(s) or maybe in sufferers with IgE-mediated allergic reactions to various brokers. Traditionally, gentamicin and tobramycin were administered a number of instances daily with particular peak (6-10 mcg/mL) [mg/L; 13-21 mol/L]) and trough (less than 1-2 mcg/mL) [mg/L; lower than 2-4 mol/L]) concentration targets. Because aminoglycosides have concentration-dependent bUse aCefoxitin killing and have a relatively lengthy postantibiotic effect for cardio Gram-negative bacilli, extendedinterval dosing of aminoglycosides is feasible. For most sufferers and indications, extended-interval aminoglycoside dosing (ie, 5-7 mg/kg as soon as day by day for tobramycin or gentamicin, 15-20 mg/kg as quickly as daily for amikacin) has replaced traditional dosing given equal efficacy and decreased nephrotoxicity. With the elevated use of carbapenems, pathogens proceed to evolve with the event of -lactamases that hydrolyze carbapenems. Especially in patients with healthcare-associated intraabdominal infections, these multidrug-resistant pathogens have pressured clinicians to use more toxic and doubtlessly much less efficient agents such because the polymyxins, tigecycline, and aminoglycosides. For example, the product labeling for tigecycline now carries a Black Box Warning because it has been associated with an elevated danger of mortality relative to comparator agents based on pooled information collected from randomized managed trials together with patients with intra-abdominal infections, pores and skin and skin construction infections, and ventilator-associated pneumonia. Ceftolozane/tazobactam will not be as efficient as meropenem and metronidazole inthe remedy of sophisticated intra-abdominal infections.
Tags: nitroglycerin 2.5 mg cheap visa, nitroglycerin 6.5 mg order without prescription, cheap nitroglycerin 2.5 mg with mastercard, buy discount nitroglycerin 2.5 mg, 2.5 mg nitroglycerin buy overnight delivery, 2.5 mg nitroglycerin generic overnight delivery, order nitroglycerin 6.5 mg overnight delivery, nitroglycerin 6.5 mg otc, cheap nitroglycerin 2.5 mg without prescription, 6.5 mg nitroglycerin generic with visa, purchase 6.5 mg nitroglycerin mastercard, discount nitroglycerin 2.5 mg, cheap nitroglycerin 6.5 mg on-line, 6.5 mg nitroglycerin quality, cheap 2.5 mg nitroglycerin fast delivery, generic 6.5 mg nitroglycerin fast delivery
9 of 10
Votes: 192 votes
Total customer reviews: 192
Customer Reviews
Grim, 31 years: Rasburicase, a recombinant urate-oxidase enzyme produced by genetic modification of Saccharomyces cerevisiae, catalyzes the enzymatic oxidation of uric acid into the inactive soluble metabolite, allantoin. Mucinous adenocarcinomas possess the identical fundamental structure as adenocarcinomas however differ in that they secrete an plentiful amount of extracellular mucus. Steroids and antihistamines have been administered previous to initiation of syphilitic remedy but are of limited value.
Narkam, 51 years: Risk components and likelihood of development from an infection to disease may also be discussed. Current Diagnosis & Treatment of Sexually Transmitted Diseases [electronic version]; AccessMedicine, 2007. Similarly, dad and mom and siblings of relations recognized with adenomatous polyps are at increased threat for creating colorectal most cancers.
Taklar, 53 years: Headache, fever, nausea, vomiting, mental standing changes, and neck stiffness generally are observed. Other issues embody renal dysfunction and the use of a platinum agent, and historical past of hemoptysis and the use of bevacizumab. The ultimate goal of remedy for noninvasive carcinomas is to prevent the development of invasive disease.
Jensgar, 49 years: The most common antagonistic effects of pembrolizumab and nivolumab are fatigue, cough, nausea, pruritis, rash, decreased appetite, constipation, arthralgias and diarrhea. Whereas from 1989 to 2003 over 30% of autopsies of patients with hematologic malignancies found deep fungal infection (75% of which were undiagnosed previous to death), this quantity decreased to 19% from 2004 to 2008 (49% of which were undiagnosed previous to death). Other professional organizations, for example, the American Academy of Pediatrics, the American Academy of Family Physicians, or the American College of Obstetrics and Gynecology, publish tips.
Silas, 55 years: Following isolation, it is suggested that typing of the virus be carried out because of prognostic implications. Contact dermatitis, eczema, psoriasis and callus formation ought to be in the differential prognosis. For effective prognosis and management, it is very important distinguish noninflammatory diarrhea that produces watery diarrhea from inflammatory diarrhea or dysentery.
Temmy, 41 years: Vancomycin ought to be used if concern for methicillin-resistant Staphylococcus spp. The medical impression of the detection of potential etiologic pathogens of community-acquired pneumonia. Sequential reintroduction of the medicine with frequent testing of liver enzymes is usually profitable in figuring out the offending agent; other brokers may be continued.
