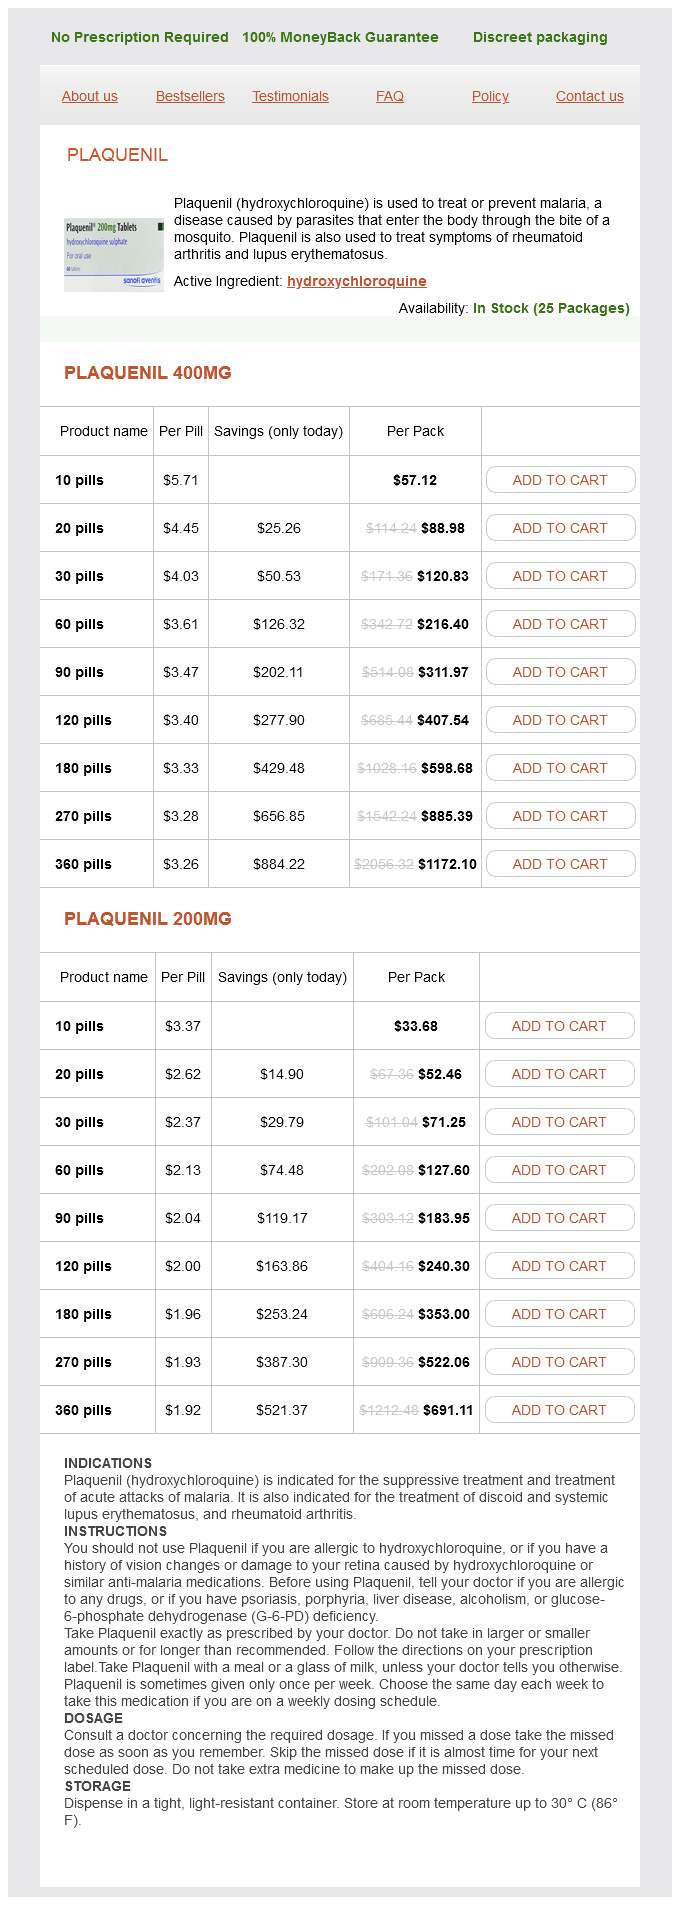
Plaquenil 400mg
- 10 pills - $57.12
- 20 pills - $88.98
- 30 pills - $120.83
- 60 pills - $216.40
- 90 pills - $311.97
- 120 pills - $407.54
- 180 pills - $598.68
- 270 pills - $885.39
- 360 pills - $1172.10
Plaquenil 200mg
- 10 pills - $33.68
- 20 pills - $52.46
- 30 pills - $71.25
- 60 pills - $127.60
- 90 pills - $183.95
- 120 pills - $240.30
- 180 pills - $353.00
- 270 pills - $522.06
- 360 pills - $691.11
Plaquenil dosages: 400 mg, 200 mg
Plaquenil packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 853
Only $0,86 per item
Description
Pericardiocentesis may also be used to aspirate fluid in such subacute conditions as viral or bacterial infection and pericarditis arthritis medication and high blood pressure plaquenil 200 mg generic line. Complications Pericardiocentesis carries some threat of doubtless fatal complications arthritis achy foot & muscle cream discount 200 mg plaquenil visa, similar to inadvertent puncture of internal organs (particularly the guts treatment for arthritis in dogs nz plaquenil 200 mg order with visa, lungs gouty arthritis diet foods plaquenil 400 mg buy on-line, stomach, and liver) or laceration of the myocardium or a coronary artery. Emergency equipment ought to be available in the course of the procedure in case of such issues. In this process, a window is created that permits fluid to drain in to the pleural house. In constrictive pericarditis, total pericardiectomy may be necessary to allow the heart to fill and contract adequately. What to do � Collaborate with a talented staff, which may embrace a cardiologist, an infectious disease specialist, a cardiothoracic surgeon, a respiratory therapist, and a bodily therapist. Administer supplemental oxygen as needed, based on oxygen saturation or blended venous oxygen saturation levels. Watch the clock � Administer antibiotics on time to maintain consistent drug ranges within the blood. The nature and severity of associated symptoms determine remedy in valvular coronary heart illness. What causes it Mitral insufficiency can result from rheumatic fever, hypertrophic cardiomyopathy, mitral valve prolapse, myocardial infarction, extreme left-sided heart failure, endocarditis, untreated hypertension, or ruptured chordae tendineae. How it occurs In mitral insufficiency, blood from the left ventricle flows again in to the left atrium throughout systole, causing the atrium to enlarge to accommodate the backflow. As a outcome, the left ventricle also dilates to accommodate the elevated volume of blood from the atrium and to compensate for diminished cardiac output. System failure Ventricular hypertrophy and increased end-diastolic strain lead to increased pulmonary artery stress, finally resulting in left-sided and right-sided coronary heart failure. What to search for Signs and signs of mitral insufficiency include: � orthopnea, dyspnea, or cough (particularly when mendacity down) � fatigue (c) 2015 Wolters Kluwer. Atrial fibrillation or atrial flutter requires beta-adrenergic blockers or digoxin to sluggish the ventricular fee. Other acceptable measures embrace anticoagulant therapy to prevent thrombus formation round diseased or replaced valves and prophylactic antibiotics earlier than and after surgery or dental care to forestall endocarditis. In addition, clarify the potential need for prophylactic antibiotics during dental surgical procedure or other invasive procedures. When instructing a patient, stress the significance of complying with antibiotic therapy. Trouble forward Complications of mitral stenosis include pulmonary hypertension, left atrial enlargement, arrhythmias (particularly of atrial origin), endocarditis, right- and left-sided coronary heart failure, pulmonary edema, and hemoptysis. What causes it Most commonly resulting from rheumatic fever, mitral stenosis typically occurs in females. It can also be related to other congenital anomalies and radiation remedies to the chest. Rarely, blood clots and tumors can block the valve, stopping it from opening correctly. How it happens In mitral stenosis, the valve narrows because of valvular abnormalities, fibrosis, calcification, or other factors. Not going with the circulate Greater resistance to blood flow causes pulmonary hypertension, right ventricular hypertrophy, and right-sided coronary heart failure. What to search for Signs and symptoms of mitral stenosis embody: � dyspnea on exertion, paroxysmal nocturnal dyspnea, and orthopnea � fatigue and weak spot � right-sided coronary heart failure and cardiac arrhythmias � crackles on auscultation � coronary heart murmur. In mitral stenosis, chest X-rays reveal left atrial and ventricular enlargement, enlarged pulmonary arteries, and mitral valve calcification. Small doses of betaadrenergic blockers can also be used to sluggish the ventricular price when cardiac glycosides fail to management atrial fibrillation or flutter. Synchronized cardioversion may be used to correct atrial fibrillation in an unstable affected person. If hemoptysis develops, the patient requires bed relaxation, sodium restriction, and diuretics to lower pulmonary venous strain. In asymptomatic mitral stenosis in young patients, penicillin is a crucial prophylactic to prevent endocarditis. Consider the complications Complications of aortic insufficiency embody left ventricular hypertrophy, heart failure, pulmonary edema, arrhythmias, and endocarditis. What causes it Aortic insufficiency may result from rheumatic fever, syphilis, hypertension, or endocarditis, or it might be idiopathic. The extra volume causes fluid overload within the left atrium and, finally, the pulmonary system. In aortic insufficiency, blood flows back in to the left ventricle during diastole, inflicting fluid overload and, finally, left-sided heart failure and pulmonary edema. What to look for Signs and signs of aortic insufficiency embrace dyspnea (especially with exertion), chest ache, syncope, arrhythmias, cough, left-sided coronary heart failure, pulsus bisferiens (rapidly rising and collapsing pulses), and blowing diastolic murmur or third heart sound. What exams let you know � Cardiac catheterization reveals a reduction in arterial diastolic strain, aortic insufficiency, other valvular abnormalities, and increased left ventricular end-diastolic stress. This is probably not potential, nevertheless, as a end result of signs and signs seldom occur until after myocardial dysfunction develops. Aortic stenosis Aortic stenosis is hardening or narrowing of the aortic valve or of the aorta itself. Complications of aortic stenosis embody endocarditis, left ventricular hypertrophy, coronary heart failure, myocardial infarction, pulmonary edema, and arrhythmias. What causes it Aortic stenosis outcomes from a congenital aortic bicuspid valve (associated with coarctation of the aorta), congenital stenosis of valve cusps, rheumatic fever, or, in elderly sufferers, atherosclerosis or calcification. How it occurs In aortic stenosis, elevated left ventricular strain tries to overcome the resistance of the narrowed valvular opening. Diminished cardiac output causes poor coronary artery perfusion, ischemia of the left ventricle, and leftsided heart failure. What tests inform you � Cardiac catheterization reveals elevated ventricular enddiastolic strain. Prophylactic antibiotics may be essential before invasive procedures to stop endocarditis. Adults with calcified valves need valve alternative once they turn out to be symptomatic or are at risk for developing left-sided heart failure. Patients with mechanical valve replacements require lifelong anticoagulant remedy. This procedure might enhance left ventricular function in order that the affected person can tolerate valve alternative surgical procedure. Consult with a dietitian to make certain that the patient receives meals he likes whereas adhering to the food plan restrictions. Pulmonic stenosis Pulmonic stenosis is a hardening or narrowing of the opening between the pulmonary artery and the right ventricle. Complications of pulmonic stenosis include arrhythmias, right-sided heart failure, and right ventricular hypertrophy. What causes it Pulmonic stenosis is rare but can result from congenital stenosis of the valve cusp or from rheumatic coronary heart illness. How it occurs In pulmonic stenosis, obstructed right ventricular outflow causes right ventricular hypertrophy in an try to overcome (c) 2015 Wolters Kluwer. What to look for Although a affected person with pulmonic stenosis may be asymptomatic, attainable indicators and signs embody dyspnea on exertion, rightsided heart failure, arrhythmias or palpitations, peripheral edema, and a systolic murmur. What exams inform you � Cardiac catheterization reveals elevated proper ventricular stress, decreased pulmonary artery stress, and irregular valve orifice. Additionally, cardiac catheter balloon valvuloplasty is often effective even with average to severe obstruction. What to do � Alternate periods of activity and relaxation to prevent extreme fatigue and dyspnea. Bacterial invasion produces vegetative growths on the guts valves, the endocardial lining of a coronary heart chamber, or the endothelium of a blood vessel. Myocarditis is a focal or diffuse irritation of the cardiac muscle (myocardium). Pleuritic pain will increase with deep inspiration and reduces when the patient sits up and leans forward.
Ranunculus friesianus (Buttercup). Plaquenil.
- How does Buttercup work?
- Are there safety concerns?
- What is Buttercup?
- Arthritis, blisters, bronchitis, chronic skin problems, nerve pain, and other conditions.
- Dosing considerations for Buttercup.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96646
Obturator internus attaches to the internal floor of the physique and ramus anteromedially rheumatoid arthritis gold 400 mg plaquenil purchase fast delivery, whereas obturator externus and adductor magnus attach to the ramus externally psoriatic arthritis in neck symptoms purchase 200 mg plaquenil visa. The mature acetabulum consists of about one-fifth pubis and two-fifths each of ilium and ischium arthritis of fingers and hand cheap plaquenil 200 mg on line. Its articular floor is in the form of a horseshoe open anteriorly rheumatoid arthritis leg pain plaquenil 200 mg purchase fast delivery, the hole being bridged by the transverse ligament. The ligament of the head of the femur attaches to the skinny, medially placed floor. Arthrology the joints which involve the pelvic girdle are the sacroiliacs, the pubic symphysis, and the hip joints. The giant and really steady sacroiliac joints connect the girdle proper to the axial skeleton. The tendency for downward and backward displacement of the sacrum between the innominate (hip) bones is opposed by the anterior and posterior sacroiliac ligaments, the latter being broadly attached to the dorsal surface of the sacrum, and by the iliolumbar ligaments attaching Pubis this is formed like a rotated L. Its longer, horizontal, superior ramus connects the acetabular and symphyseal articular surfaces of the pubis. The inferior ramus extends downwards from the tubercle to its point of fusion with the ischium. The true pelvis lies below this brim, with its outlet bounded by the ischial bones, the pubic arch and the coccyx. Obturator internus extends again to the larger sciatic notch and virtually meets the stomach of piriformis, which fills in the concavity of the sacrum and leaves the pelvis by way of that notch. The muscles which type the pelvic floor or diaphragm, levator ani and coccygeus, are attached along the inside wall of the true pelvis. Levator ani attaches laterally from the again of the pubis, across the obturator fascia lining obturator internus, to the ischial backbone. Thus the higher sciatic notch (foramen) connects pelvis and buttock (gluteal region), while the lesser connects buttock and perineum. The continuous layer of fascia covering the superior floor of levator ani, coccygeus and the pelvic wall (superior) elements of obturator internus and piriformis is the parietal pelvic fascia. Note that the rising sacral anterior major rami lie deep to this fascia, while the interior iliac vessels lie superficial to it. The parietal fascia merges medially with the visceral pelvic fascia surrounding the pelvic organs and their nerves and vessels. Above the pelvic brim the extraperitoneal parietal layer of fascia covers iliacus and psoas. The iliacus fascia joins the tranversalis fascia of the lower belly wall to kind the femoral sheath. The anterior part of the pelvic outlet types the urogenital Sacrum Posterior sacro-iliac ligament Sacrospinous ligament Coccyx Sacrotuberous ligament Ischiofemoral ligament. The tendency for downward rotation of the sacrum within the sagittal aircraft is additionally opposed by the sacrotuberous and sacrospinous ligaments attaching the sacrum to the ischium. The symphysis pubis, like all symphyses, lies within the median plane and includes a disc of fibrocartilage firmly fastened between two articular surfaces of hyaline cartilage. The joint is strengthened anteriorly by decussating bands of collagen, and inferiorly by the arcuate pubic ligament. There is a bit more motion throughout being pregnant and childbirth because the ligaments relax barely. Major anatomical relations � sacroiliac joints: the inner iliac vessels move anteriorly; and � pubic symphysis: the urethra and the deep dorsal vein of the penis or clitoris pass inferiorly. All are common websites of pathology, traversed by major nerves and vessels in continuity. Anteriorly lie the pelvicrural and obturator areas, and posteriorly the sciatic foramina connecting the gluteal region with pelvis and perineum. The femoral vessels of their sheath, the femoral nerve, the femoral canal, muscle tissue (psoas, iliacus and pectineus), and cutaneous nerves (genitofemoral and lateral femoral) all traverse this area. Anteromedially the obturator nerve and vessels emerge from the obturator canal in to the thigh deep to obturator externus, and instantly divide in to their anterior and posterior branches. The larger sciatic foramen, connecting pelvis and buttock, is traversed by piriformis, and the lesser sciatic foramen, between perineum and buttock, by obturator internus. Obturator internus lies both within the lateral wall of the pelvis, above the levator ani, and in that of the perineum beneath it. Structures leaving the pelvis with piriformis include the superior gluteal nerve and vessels above the muscle, and the sciatic nerve, inferior gluteal nerve and vessels, and the pudendal nerve and vessels beneath it. Nerves Several major nerves associated to the pelvic girdle could also be involved in injuries and disease of the bones of the pelvis and its contained viscera. The nerves of the decrease limb derive from the anterior (ventral) major rami making up the lumbosacral plexus, and thus must cross all or a half of the pelvis early of their course. As within the brachial plexus, some of the rami are destined to provide muscular tissues and dermatomes of the flexor and adductor parts of the limb, and some to provide those of the extensor part. As a results of rotation during improvement, the extensor component of the decrease limb distal to the hip lies anteriorly, with the flexor element posterior. The lumbosacral plexus and its branches lie extraperitoneally and deep to the parietal pelvic fascia, and are thus closely related to the musculoskeletal structures of the body wall and pelvic girdle. All three major limb nerves lie on or near bone within the proximal a half of their course, making each weak in pelvic and in lower spinal trauma. Common peroneal nerve Tibial nerve Posterior cutaneous nerve of thigh Pudendal nerve Pelvic splanchnic nerve Perforating cutaneous nerve from that of T12, and the sacral plexus from the upper 4 sacral and the decrease two lumbar rami. The key to the lumbar plexus is the psoas muscle: the rami lie inside it, and the main limb nerves from the plexus emerge and run either facet of it. The femoral nerve is lateral, while the obturator nerve and the lumbosacral trunk (on its method to the sciatic nerve) are medial to the muscle. The lumbosacral trunk is weak where it lies on bone and on the sacroiliac joint as it crosses the pelvic brim. The femoral nerve is near bone the place it crosses the pubis between psoas and iliacus, and is thus susceptible in anterior pelvic harm. The obturator nerve crosses the pelvic brim posteriorly behind the frequent iliac vessels, then runs in shut relation to the lateral pelvic wall to reach its canal within the superolateral angle of the obturator foramen. The key to the sacral plexus is the piriformis muscle, on which the plexus lies and above and beneath which its main branches depart the pelvis. The nerve to the flexor component of the decrease limb is the tibial part of the sciatic. The different main branches of the sacral plexus to the limb (common peroneal, gluteal nerves) supply the extensor element. The sacral plexus also provides the perineum, through the pudendal nerve: this fact is of great significance within the scientific assessment of spinal injuries. Posterior divisions are shaded darker to distinguish them from the anterior divisions. The autonomic input to the lumbosacral plexus is perhaps much more essential than that to the brachial plexus, as, in the former, both major parts of the autonomic system are concerned. All lumbar and sacral ventral rami receive gray rami communicantes from the corresponding sympathetic ganglia. The higher two lumbar ventral rami, with all of the thoracic, send white rami communicantes to the sympathetic chain. The second to fourth sacral ventral rami convey the sacral parasympathetic outflow to the pelvic splanchnic nerves, supplying the pelvic viscera. The joints of the upper limb are versatile, and their muscle tissue are exactly attached. These muscle tissue virtually all the time work from their proximal attachments (origins) to their distal (insertions), because the distal end of the limb is free and cellular. They usually have essential r�les both as stabilisers and motors of the joints which they cross. The head is borne on a comparatively lengthy neck, which forms an angle both with the shaft and with the transcondylar axis (coronal plane) of the bone. The neck is angled medially on the shaft, the open neck-shaft angle being about 130�. It is also normally angled ahead (anteverted) from the coronal aircraft by about 15� within the grownup.
Specifications/Details
Benign tumours rarely cause medical signs lupus arthritis in fingers plaquenil 200 mg buy discount line, though when massive they might trigger ache arthritis lumps plaquenil 400 mg purchase visa. The fungus contaminates food saved in hot arthritis in neck and fainting 400 mg plaquenil generic, humid conditions and may be answerable for the geographical distribution; and anabolic steroids deep heat arthritis relief plaquenil 200 mg buy without prescription, androgenic steroids, and oral contraceptive agents have been implicated. Malignant tumours these usually present with anorexia, weight reduction, cachexia and jaundice. Metastatic tumours Common major origins embody the gastrointestinal tract, lung and breast. Hepatocellular carcinoma Aetiological factors embody: Spread of the tumour is by intrahepatic veins. Lymphatic spread occurs to lymph nodes on the porta hepatis, but distant metastases are uncommon. Hepatocellular carcinoma produces alpha-fetoprotein which is secreted in to the blood stream, where it forms a useful diagnostic marker. Aetiological elements embody the liver fluke, Clonorchis sinensis, and first sclerosing cholangitis (often in association with ulcerative colitis). The prognosis is poor, most sufferers being dead within a number of months of presentation. They may be associated with congenital polycystic disease of the kidney, or von Hippel Lindau disease. Cyst fluid is highly allergenic, and spillage at surgical procedure may precipitate a Type I anaphylactic hypersensitivity response. Choledochal cysts these are uncommon congenital cysts of the bile duct which can be intra- or extrahepatic. In portal hypertension, portal stress exceeds 10 mmHg, averaging round 20�25 mmHg, and will rise as high as 50�60 mmHg. Anatomy of portal hypertension A portal vessel is one which has capillaries at every finish. The portal venous system drains blood to the liver from the belly a part of the alimentary canal (excluding the decrease part of the anus), the spleen, the pancreas and the gall bladder. The portal vein is formed by the junction of the splenic vein and superior mesenteric vein behind the neck of the pancreas. The inferior mesenteric vein ascends above the point of origin of its artery to enter the splenic vein behind the physique of the pancreas. The portal vein ascends behind the primary part of the duodenum entering the free edge of the lesser omentum within the anterior wall of the foramen of Winslow. At this level the portal vein is straight away posterior to the bile duct and the hepatic artery. The portal vein then ascends to the porta hepatis, the place it divides in to the right and left branches and breaks up in to the capillaries running between the lobules of the liver. In order for the blood to escape, the blood passes via any anastomosis between the portal and systemic system, and the anastomotic veins turn out to be dilated and will bleed. Surgery on sufferers with portal hypertension may be very sophisticated and really bloody. This is as a result of of dilated veins within the abdominal wall, within the mesentery and within the retroperitoneal space. Pressure in these veins could additionally be extremely high, leading to considerable portal venous bleeding. Gall stones (cholelithiasis) In 80% of sufferers gall stones are composed predominantly of ldl cholesterol with smaller quantities of calcium salts and bile pigments. They are referred to as combined stones, are normally a quantity of with a faceted floor, and have a attribute laminated surface on cross-section. When bile accommodates extra cholesterol than may be solublised within the bileacid-lecithin micelles, crystals of ldl cholesterol form in the bile. The higher the focus of bile acids and lecithin in bile, the greater is the amount of cholesterol that may be contained within the blended micelles. Lecithin is essential because lecithin-cholesterol blended micelles can solubilise extra cholesterol than can micelles of bile acids alone. Oestrogen will increase the hepatic synthesis of ldl cholesterol, and this will explain why females of childbearing age have a better incidence of cholesterol stones. A excessive animal fat, low fibre food regimen is also related to ldl cholesterol stones due to excretion in bile of the surplus ldl cholesterol absorbed from the gut. Clofibrate, a cholesterol-lowering agent, has been implicated in cholesterol stone formation, as a result of it will increase excretion of ldl cholesterol in the bile. Decreased gall bladder motility in all probability plays a task within the aetiology of gall stones. Cholesterol and different substances which form the nuclei for gall stone formation should stay in the gall bladder lengthy enough for crystal progress to occur. Stasis occurs during pregnancy due to the smoothmuscle-relaxing impact of progesterone. Pure pigment stones occur in sickle cell disease, thalassaemia and hereditary spherocytosis. These organisms produce beta-glucuronidase which splits bilirubin diglucuronide and releases free bilirubin. The latter combines with calcium to type the relatively insoluble calcium bilirubinate. The bile is absorbed from the gall bladder, and mucus is secreted in to it from the mucus-secreting cells of the epithelium. The lack of irritation in the wall permits the gall bladder to distend to several occasions its regular dimension. Cholecystitis Cholecystitis is irritation of the gall bladder and is often related to stones. Acalculous cholecystitis could occur after prolonged hunger or complete parenteral vitamin. The gall bladder turns into oedematous, with mucosal ulceration, and a fibrinopurulent exudate. Even within the presence of thrombosis of the cystic artery, gangrene is rare, because the gall bladder positive aspects a blood supply directly from the liver through the gall bladder bed. However, gangrene does sometimes happen with perforation of the gall bladder, resulting in generalised bile peritonitis or a localised abscess relying on whether the gall bladder has been walled off by adhesions or not. An empyema of the gall bladder can also result, suppuration occurring inside the gall bladder and the gall bladder becoming distended with pus. Empyema this happens when a stone impacts in the neck of the gall bladder in the presence of infection within the bile. Suppuration takes locations throughout the gall bladder and the gall bladder distends with pus. This is usually a symptomless situation however may accompany or predispose to cholesterol stones. Both are normally clinically silent however may present up on an ultrasound scan of the gall bladder and raise suspicion of a extra sinister lesion. Chronic cholecystitis Chronic cholecystitis is invariably associated with gall stones. It might develop after repeated episodes of acute cholecystitis but extra often develops insidiously with none previous clinically evident acute attacks. The gall bladder wall is infiltrated with continual inflammatory cells � lymphocytes, plasma cells and macrophages. Glandular outpouchings are fashioned by the lining of the mucosa and are often known as Aschoff-Rokitansky sinuses. If obstructive jaundice happens, it is due to a stone impacted within the widespread bile duct. Malignant tumours Carcinoma of the gall bladder is the commonest malignant tumour. It happens in aged individuals and is invariably related to gall stones and continual cholecystitis. The tumour is most often an adenocarcinoma, though in 10% of cases squamous cell carcinomas may occur. The tumour is usually advanced at presentation, having invaded directly in to the liver or adjacent organs. Infiltration in to the bile duct or metastases to the nodes of the porta hepatis will trigger obstructive Mucocele this happens when a stone impacts in the neck of the gall bladder within the absence of an infection within the bile.
Syndromes
- Diminished arm reflexes
- Dry eyes
- The entire goiter will then be removed.
- Respiratory distress
- Nausea, vomiting
- Vision color changes (brown tinge)
- Do NOT apply ice, butter, ointments, medications, fluffy cotton dressings, or adhesive bandages to a burn
Related Products
Additional information:
They possess a segmented nucleus and ample cytoplasmic granules containing enzymes how is arthritis in dogs diagnosed best plaquenil 200 mg. They spend 14 days in the bone marrow arthritis in fingers and wrists discount plaquenil 200 mg fast delivery, whereas their half-life in the blood is just 6�12 h rheumatoid arthritis x ray images plaquenil 400 mg buy with visa. This sort of illness is seen in patients receiving chemotherapy for malignant illness or immunosuppressive remedy for organ transplantation arthritis in neck shoulder pain plaquenil 400 mg discount online. They adhere to exposed subendothelial tissues, mixture, and kind a haemostatic plug. Platelet-derived growth factor is mitogenic for easy muscle and fibroblasts; it might even be involved within the development of atherosclerosis. Eosinophils the eosinophil is necessary within the mediation of the allergic response and the defence towards parasitic infections. They are thought to be necessary in immediate hypersensitivity reactions, after they launch histamine. Changes in white cells in illness Leucocytosis Leucocytosis is a rise within the number of circulating white cells. It may contain any of the white cells, however a polymorphonuclear leucocytosis is the commonest, i. It consists of 4 components: vasoconstriction, platelet activation, the coagulation mechanism and the fibrinolytic system. Vasoconstriction this is as a end result of of smooth muscle contraction mediated by native reflexes, thromboxane A2 and serotonin launched by activated platelets. The coagulation mechanism is advanced and entails two interacting systems: the intrinsic and extrinsic pathways. Activation of factor X is the end result of preceding enzyme reactions in the two pathways. The intrinsic pathway involves regular blood elements; the extrinsic pathway requires tissue thromboplastin released by damaged cells. Plasmin is derived from the inactive precursor plasminogen by the motion of plasminogen activators. Control of the activation of plasminogen is supplied by plasminogenactivator inhibitor I, which is released by endothelial cells and rapidly inactivates tissue plasminogen activator. Platelet activation Vascular injury promotes haemostasis if the endothelial lining of blood vessels is disrupted. Platelets adhere to , and combination at, the sites of disruption, ultimately forming a platelet plug. Adherence Following harm to the vessel wall, lack of endothelium exposes subendothelial collagen, permitting adhesion of platelets to the broken area and activation of the intrinsic pathway of coagulation. Damaged endothelial cells release von Willebrand issue, which is necessary for platelet adhesion, and likewise launch tissue thromboplastin which activates the intrinsic pathway of coagulation. Aggregation Thromboxane A2 is produced from arachidonic acid released from platelet phospholipids. Platelet plug the aggregated platelets act as catalysts of coagulation with local generation of thrombin and conversion of fibrinogen to fibrin. Bleeding time this is examined by measuring the time for a small puncture wound within the skin, made by a standard approach, to stop bleeding. A time inside this normal range implies an enough platelet depend, normal platelet operate, and a standard vascular response to harm. A extended bleeding time implies thrombocytopaenia, a platelet defect, or failure of vascular contraction. A clotting time inside this range requires integrity of the intrinsic system, an sufficient ultimate common pathway, and regular platelet function. The take a look at outcomes and the conclusions which could be drawn from them are shown in Table 10. Acquired problems of coagulation Vitamin K deficiency Vitamin K is present in green greens and is synthesised by intestinal bacteria. Vitamin K deficiency may happen in the surgical affected person as the result of obstructive jaundice, antibiotic therapy which alters the normal intestinal flora, or extended parenteral vitamin with out vitamin K supplements. Liver disease that is commonly related to coagulation defects as a outcome of failure of clotting factor synthesis and the manufacturing of abnormal fibrinogen. Activation of the coagulation system leads to the formation of microthrombi in many organs, with the consumption of clotting elements and platelets, in turn resulting in haemorrhage. The presence of thrombocytopaenia, decreased fibrinogen, and elevated fibrinogen degradation merchandise confirms the diagnosis. Low molecular weight heparin is used subcutaneously and has an extended biological half life. Bleeding as a result of overdose is managed by stopping the heparin and administering protamine sulphate intravenously. Side results of heparin include thrombocytopaenia, hypersensitivity reactions, alopecia, and osteoporosis when used long term. Bleeding is managed by stopping warfarin and administering either fresh frozen plasma or vitamin K, depending upon the degree of urgency. These include antibiotics, laxatives (interfere with vitamin K absorption), phenylbutazone (interferes with binding of warfarin to albumin) and cimetidine (inhibits hepatic microsomal degradation). A and B are responsible for changing a fundamental substance H, present in every red cell, in to A or B substances, thus converting the cells to group A or group B. Individuals inherit antibodies (agglutinins), which react against red cells of teams aside from their very own, i. Individuals with blood group A, have A antigens on the pink cells and B antibodies within the plasma. It is a vitamin K antagonist and in effect induces a state analogous to vitamin K deficiency. An Rh ve individual could make anti-D solely after sensitisation from an Rh ve exposure. An Rh ve particular person has a 50% likelihood of developing anti-D after the transfusion of a single unit of Rh ve blood. Major importance of a data of the Rh system is to avoid the hazard of RhD incompatibility between mom and fetus. When red cells carrying one or each antigens (A, B) are exposed to corresponding antibodies, they agglutinate or clump together. In the process of grouping, blood is mixed with reagents, including different antibodies, i. Grouping is checked by determining whether or not anti-A or anti-B is present within the recipient serum by adding identified group A and B cells. Sensitisation can be prevented by administering a single dose of anti-Rh antibodies within the type of Rh immunoglobulin through the postpartum interval after the start of an Rh ve baby. Cross-matching Antibodies to A and B antigens are naturallyoccurring, whereas these to different purple cell antigens. In finishing up cross-matching, group-compatible red cells from a donor pack of blood is mixed with recipient serum and examined for agglutination, i. Cross-matching may also rule out any errors which will have occurred within the determination of the donor and recipient blood group. Whole blood Nowadays complete blood is less readily available because of the demand for blood products. Ideally, whole blood ought to be the product of alternative for large transfusion but in apply concentrated pink cells with colloid or crystalloid is given often following huge haemorrhage. Administration of platelet concentrate ought to occur 4 hours earlier than any invasive process. The traditional grownup dose is six items which should raise the platelet depend by forty,000 109/L. Granulocytes Granulocytes have a very short shelf-life (24 h at room temperature). Fresh frozen plasma Red cell concentrates Red cell concentrates, or packed cells, include whole blood from which the majority of plasma has been eliminated. Platelet concentrates Platelet concentrates include platelets suspended in plasma. Their shelf-life is just three days at room Cryoprecipitate Cryoprecipitate is a concentrate prepared by freezethawing of plasma from a single donor.
Usage: b.i.d.
The first essential function of the shaft of the humerus is the spiral groove arthritis uptodate purchase 200 mg plaquenil otc, by which the radial nerve and the profunda brachii vessels run between the lateral and medial heads of triceps and in direct contact with bone does arthritis pain get better generic plaquenil 200 mg otc. The other primary characteristic is the tubercle for the attachment of the deltoid muscle arthritis lighter plaquenil 400 mg, nearly half means down the lateral border of the bone mild arthritis in knee exercises 400 mg plaquenil purchase free shipping. The triangular shape of deltoid offers it its name: its broad base lies proximally on the pectoral girdle, in order that it has fibres running anteriorly, superiorly and posteriorly to the shoulder joint. It can thus flex and lengthen the joint, along with its primary perform as an abductor. The motor provide of deltoid is the axillary nerve (C5,6), vulnerable just under the joint capsule at the surgical neck. The distal expanded finish of the humerus is shaped by the two condyles, medial and lateral. The complex articular floor contains components of each condyles: the lateral condyle includes the rounded capitulum, which articulates with the radius, and the lateral a half of the pulley-like trochlea which articulates with the ulna. The peripheral projections on every condyle are the epicondyles, medial and lateral. The ulnar nerve is instantly related to bone behind the medial epicondyle, and anconeus muscle attaches behind the lateral. The cross-sectional profile of the shaft adjustments from tubular to flattened from front to back on the distal metaphysis. All three major nerves of the arm and forearm lie on or close to bone right here, the ulnar posteromedially, the radial anterolaterally and the median anteriorly with the brachial artery. The primary group of forearm flexors attaches to the medial epicondyle (common flexor origin), and the extensors to the lateral (common extensor origin). The humerus is related to the deep fascia of the arm by the medial and lateral intermuscular septa. The medial septum extends distally from the teres main attachment to the medial epicondyle, and the lateral equally from the deltoid attachment to the lateral epicondyle. These septa divide the higher arm in to flexor and extensor osteofascial compartments. The line of capsular attachment for the elbow includes the trochlea and capitulum however excludes both epicondyles. There are two definitive progress plates for the distal humerus: that for the medial epicondyle is completely extracapsular, while that for the trochlea and lateral condyle crosses the capsular attachment and is extracapsular solely posterolaterally. Immediately distal to the circumferential radioulnar articular surface of the pinnacle is the narrower neck of the bone. The annular ligament runs around this circumferential articular surface of the pinnacle, not around the neck. The main muscles attaching to the proximal radius are the biceps medially, to the bicipital tuberosity, and the supinator laterally, wrapping across the neck and proximal shaft. Muscles attaching to the shaft anteriorly include flexor digitorum superficialis proximally, flexor pollicis longus over many of the center third, and pronator teres within the distal third. Posteriorly, the lateral attachments of abductor pollicis longus and extensor pollicis brevis occupy the center third, whereas pronator teres attaches posterolaterally at midshaft stage. The distal expanded end is clean and concave anteriorly however grooved and convex posteriorly (dorsally). It is extended laterally in to the radial styloid process, and its concave distal surface articulates with the scaphoid and lunate bones of the proximal carpus. The dorsal grooves bear the extensor tendons in their sheaths, most importantly that of extensor pollicis longus mendacity simply medial to the dorsal tubercle (of Lister). Attrition rupture of this tendon can happen right here when the wrist is immobilised in a forged. The lateral surface of the distal end is grooved by the tendons of abductor pollicis longus and extensor pollicis brevis in their sheaths, whereas the medial surface is concave and bears an articular surface for the inferior radioulnar joint. The distal development plate of the radius lies entirely exterior the capsule of the wrist joint. The interosseous membrane between radius and ulna divides the forearm in to its flexor and extensor osteofascial compartments. The posterior interosseous nerve (the deep department of the radial) is vulnerable the place it winds across the neck of the radius throughout the supinator muscle. The cutaneous terminal portion of the radial nerve runs fairly close to the lateral aspect of the distal radius, in the favoured website for insertion of intravenous cannulae and crossing the widespread distal radial fracture strains. Anconeus attaches to the posterior floor of the olecranon and of the proximal metaphysis. The lateral facet of the metaphysis bears the concave articular floor of the superior radioulnar joint (radial notch), which is in continuity with that of the trochlear notch. The proximal development plate of the ulna lies outside the capsular attachment of the elbow joint. The ulnar shaft is cylindrical and narrower distally, and is barely convex medially. Flexor digitorum profundus attaches broadly to its middle two fourths, and pronator quadratus to the distal fourth. Flexor digitorum profundus also shares an aponeurotic attachment to the posterior border of the ulna with flexor and extensor carpi ulnaris. Distal and medial to this aponeurosis, abductor pollicis longus, extensor pollicis longus and extensor indicis attach to the medial a part of the posterior surface of the shaft. The distal expanded end of the ulna is extended medially as the ulnar styloid course of, and bears a groove dorsally for extensor carpi ulnaris tendon. There is an articular floor laterally for the inferior radioulnar joint, and distally for the triangular cartilage whose distal surface is part of the wrist joint. The distal growth plate of the ulna lies outside the line of attachment of the wrist joint capsule. The ulnar nerve lies near the medial facet of the olecranon because it enters the forearm inside flexor carpi ulnaris. Its dorsal branch runs carefully across the distal shaft about four cm proximal to the styloid course of. The proximal row, from radial (lateral) to ulnar (medial) facet, includes scaphoid, lunate and triquetral, with the pisiform, a sesamoid bone within the tendon of flexor carpi ulnaris, situated anteromedially. Some features of the scaphoid, essentially the most commonly fractured carpal bone, must be recognised, particularly the waist of the bone and the method in which in which the blood provide enters primarily from the distal finish, making avascular necrosis of the proximal end doubtless after a displaced waist fracture. The distal row, once more from radial to ulnar, is made up of the trapezium, trapezoid, Ulna. The proximal end terminates in the olecranon, the bony process for attachment of the triceps tendon. The peak of this arch is elevated by ventral (palmar) bony processes, the hook of the hamate, the ridge of the trapezium and the tubercle of the scaphoid, and by the pisiform medially. Arthrology Glenohumeral joint this is a ball-and-socket joint, the relative form and dimension of whose articular surfaces make it totally reliant on gentle tissue constructions for static and dynamic stability. The capsule is connected across the margin of the glenoid cavity of the scapula, extending on to the base of the coracoid superiorly to embody the biceps attachment. The glenoid labrum, deepening the concavity of the glenoid fossa, is completely intracapsular. On the humerus, the capsule is hooked up across the anatomical neck except the place it passes on to the medial metaphysis inferiorly. The latter attachment brings the inferior capsule in to close relation with the axillary nerve, rendering the nerve weak in anteroinferior dislocations. It also means that a metaphyseal osteomyelitic lesion of the proximal humerus may be intracapsular, resulting in the risk of septic arthritis as a sequel. The capsule is reinforced by the tendons of the rotator cuff muscles, which mix with it everywhere except inferiorly, and moreover by the coracohumeral ligament superiorly. The synovial sheath extends distally beneath the transverse ligament of the humerus in to the bicipital groove. The two major bursae related to the joint are the subacromial/subdeltoid bursa superiorly and the subscapular bursa anteriorly. The joint may be aspirated or injected anteriorly or posteriorly, the posterior subacromial strategy being considerably simpler and likewise being that usually used for arthroscopy. The common strategy for open shoulder surgical procedure is anterior, passing between deltoid and pectoralis major. The muscles attaching to the coracoid are displaced medially, protecting axillary neurovascular structures, and the capsule is entered after dividing subscapularis. Movements and muscular tissues � flexion: anterior a part of deltoid, pectoralis major, biceps brachii, coracobrachialis; � extension: posterior deltoid, teres major, latissimus dorsi; � abduction: mid-part of deltoid, supraspinatus; � adduction: pectoralis major, latissimus dorsi, teres major, coracobrachialis, [gravity]; � medial rotation: subscapularis, anterior deltoid, latissimus dorsi, teres main; � lateral rotation: posterior deltoid, infraspinatus, teres minor; and � circumduction: all the above.
Tags: plaquenil 200 mg buy otc, cheap plaquenil 200 mg, plaquenil 400 mg discount with visa, plaquenil 200 mg buy online, order 200 mg plaquenil amex, plaquenil 200 mg low cost, generic 200 mg plaquenil, discount plaquenil 400 mg mastercard, plaquenil 400 mg buy visa, plaquenil 200 mg buy cheap line, plaquenil 200 mg quality, buy plaquenil 200 mg fast delivery, plaquenil 200 mg buy lowest price, proven 200 mg plaquenil, buy cheap plaquenil 400 mg on line, plaquenil 400 mg generic visa
9 of 10
Votes: 60 votes
Total customer reviews: 60
Customer Reviews
Bozep, 25 years: There are a number of elevations seen right here which kind the lingual tonsil, a lymphoid aggregation embedded in the musculature.
Sobota, 58 years: Inform the patient and his household about how the condition might be handled, being certain to clarify new procedures earlier than beginning them.
Derek, 46 years: It prolongs in to the axilla because the axillary sheath enclosing the brachial plexus and the subclavian artery.
Rune, 41 years: The nasopharyngeal tonsils are prominent in youngsters but like all lymphoid tissues endure atrophy after puberty.
