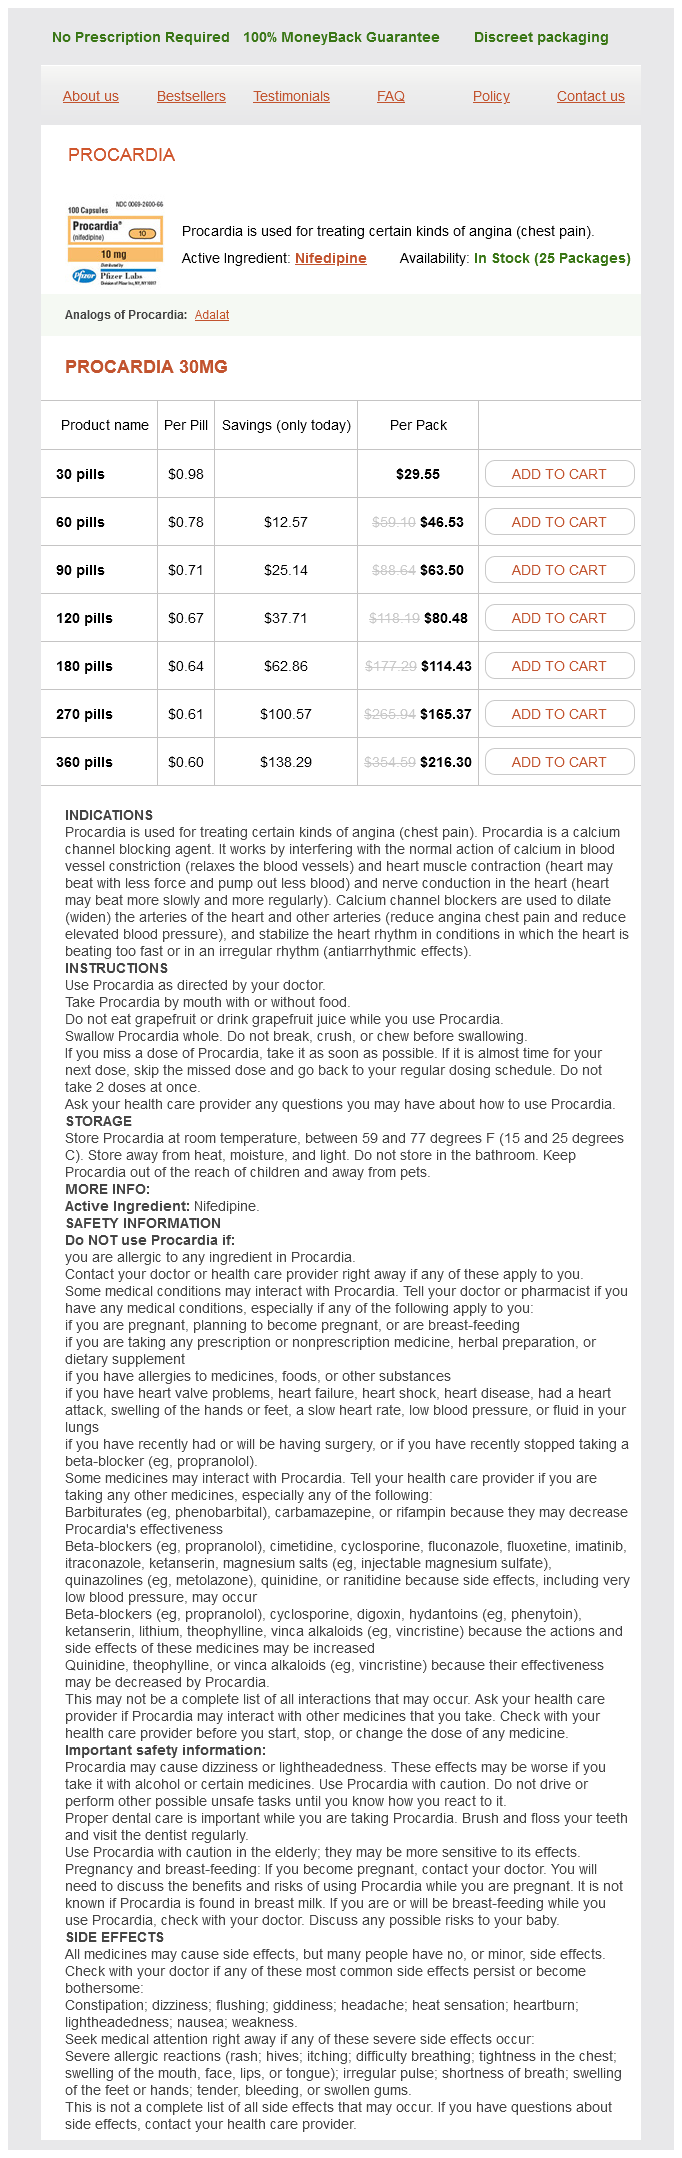
Procardia 30mg
- 30 pills - $29.55
- 60 pills - $46.53
- 90 pills - $63.50
- 120 pills - $80.48
- 180 pills - $114.43
- 270 pills - $165.37
- 360 pills - $216.30
Procardia dosages: 30 mg
Procardia packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 742
Only $0,64 per item
Description
Analysis of arterial blood vessels surrounding the myoma: relevance to myomectomy cardiovascular system worksheet pdf procardia 30 mg purchase online. Analysis of the impression of physique mass index on the surgical outcomes after robot-assisted laparoscopic myomectomy cardiovascular rrr discount procardia 30 mg with mastercard. Obstetric outcomes after uterine myomectomy: laparoscopic versus laparotomic strategy cardiovascular disease epidemiology australia discount procardia 30 mg with amex. The advert hoc committee on hysteroscopic coaching pointers of the American Association of Gynecologic Laparoscopists coronary heart disease causes generic procardia 30 mg on-line. Pregnancy following robot-assisted laparoscopic myomectomy in girls with deep intramural myomas. The past, current and future of minimally invasive endoscopy in gynecology: a review and speculative outlook. Cross-linked sodium hyaluronate, an anti-adhesion barrier gel in gynaecological endoscopic surgical procedure. Complications of uterine fibroids and their management, surgical management of fibroids, laparoscopy and hysteroscopy versus hysterectomy, haemorrhage, adhesions, and problems. Robotic-assisted laparoscopic vs stomach and laparoscopic myomectomy: systematic evaluation and meta-analysis. Adhesion formation and reproductive outcome after myomectomy and second-look laparoscopy. Uterine artery embolization versus surgical procedure in the remedy of symptomatic fibroids: a systematic evaluation and metaanalysis. Hysteroscopic myomectomy for menorrhagia using Versascope bipolar system: efficacy and prognostic elements at a minimal of one year follow up. Transcervical hysteroscopic resection of submucous fibroids for abnormal uterine bleeding: outcomes regarding the degree of intramural extension. A myomectomy may be carried out by a laparotomy or endoscopy (laparoscopy or hysteroscopy). The selection of surgical strategy is dependent upon the quantity, size, location, and type of fibroids and particularly on the experience of the surgeon and his or her group. Myomatous uteri have an elevated variety of arterioles and venules, and myomectomy may involve important blood loss [1]. However, research show that with comparable uterine measurement, the blood loss is similar whether or not hysterectomy or myomectomy is performed [2]. The average volumes of blood loss are 200�800 mL during stomach myomectomy (performed via laparotomy, also referred to as open myomectomy) [2] and 80�250 mL for laparoscopic myomectomy [3]. Surgical hemorrhage may lead to anemia, hypovolemia, and coagulation abnormalities. Controlling blood loss during myomectomy continues to be a problem faced by endoscopic surgeons. Multiple options have been described and promoted over time to achieve this aim. Despite the applying of even one of the best method, extreme bleeding may be encountered and additional options are wanted in controlling blood loss throughout surgery. This article intends to focus on the assorted choices with respect to their mechanism of motion, effectiveness, and evidence supporting their use. Although the individual surgeon always has his or her favorite technique, it shall be prudent right here to throw some mild on the comparative efficacies of particular person strategies. Categorization or classification of submucous leiomyomas could be helpful when contemplating therapeutic choices, including the surgical method. The effectiveness of this has been questioned secondary to the potential loss of the surgical airplane and consequently elevated difficulty in completing the surgery. Newer agents beneath present investigation embrace selective progesterone receptor modulators. Chemical choices include intravenous administration of medicines (oxytocin, tranexamic acid, injection of regular saline, or a vasoconstrictive agent similar to vasopressin) into the subcapsular layer of the myoma. Mechanical options embody application of a tourniquet at the degree of the uterine artery insertion into the uterus, ligating/clipping/coagulating the uterine arteries, or momentary clamping of the uterine arteries (Table 6. To scale back these dangers, medical pretreatment can be utilized to scale back fibroid size and thereby probably lower intraoperative blood loss, the need for blood transfusion, and emergency hysterectomy. No differences had been seen in charges of blood transfusion for either kind of surgical procedure. There have been no surgical parameters reported in these research, and surgical expertise is variable. Immediate suturing with obliteration of dead space 50 6 Reducing intRaopeRative Blood loss in MyoMectoMy loss and improve surgical outcomes in leiomyoma surgical procedure. Misoprostol Misoprostol is a prostaglandin E1 analogue that reduces uterine blood flow, increases myometrial contractions, and has the potential to reduce blood loss during uterine surgery [9]. The proof for misoprostol as an adjunct for myomectomy is limited and conflicting. However, even a single dose of misoprostol is efficacious in patients present process abdominal myomectomy. Placebo-controlled randomized research have shown that a single dose of misoprostol 400 g given vaginally 1 h prior or rectally 30 min prior to stomach myomectomy resulted in a statistically significant discount in operative time [10], blood loss, postoperative hemoglobin drop, and need for postoperative blood transfusion. In one randomized trial, no benefit was noticed in using misoprostol alone for abdominal myomectomy, but misoprostol four hundred g by rectum combined with intravenous oxytocin (10 U/h) in girls present process laparoscopically assisted vaginal hysterectomy found vital enhancements in operative outcomes compared with placebo [11]. The role of misoprostol for cervical priming earlier than operative hysteroscopy has also been reported, though not all patients in that study had fibroids as the indication for surgery [12]. The authors discovered that within the misoprostol group there was less want for surgical dilation, shorter time for cervical dilation to Hegar 9, shorter operative time, and fewer occurrences of cervical lacerations than the placebo group. Oxytocin Although latest proof suggests the presence of oxytocin receptors in uterine myomas, the proof for its use to reduce blood loss is somewhat conflicting. Vasopressin Vasopressin is a naturally occurring hormone that can trigger vascular spasm and uterine muscle contraction and hence has the potential to prevent bleeding throughout uterine surgery [14]. As there have been several reviews of cardiovascular collapse following intramyometrial injection of vasopressin, caution must be taken to guarantee correct dilution and clear communication with the anesthesiologist [15]. A retrospective comparability of prospectively collected information of a hundred and fifty patients who underwent laparoscopic myomectomy was carried out [16]. This examine reveals that vasopressin is effective in decreasing blood loss throughout laparoscopic myomectomy [16]. Patients present process typical laparoscopic or robot-assisted laparoscopic myomectomy have been randomly assigned to obtain 200 mL of diluted vasopressin resolution (20 U in four hundred mL regular saline) or 30 mL of concentrated vasopressin solution (20 U in 60 mL normal saline). In one trial, dilute vasopressin (20 U in 20 mL saline injected previous to uterine incision) had effects comparable to these of mechanical vascular occlusion (Penrose drain tourniquet and vascular clamps at the infundibulopelvic ligament) with respect to blood loss, postoperative morbidity, and transfusion necessities [18]. In contrast, another study reported much less blood loss in the vasopressin group (20 U in 20 mL) than in the tourniquet group (512. However, no statistically significant differences had been seen within the hemoglobin drop, number of transfusions, intraoperative blood stress, or highest postoperative pulse and temperature [19]. A 2011 study in contrast intraoperative bleeding during laparoscopic myomectomy utilizing dilute vasopressin (6 U in 20 mL) with Roeder knot loop ligation on the base of the fibroid with use of vasopressin alone and with placebo [19]. Antifibrinolytics Tranexamic acid is a synthetic derivative of lysine with antifibrinolytic activity and has been used to reduce blood loss and the necessity for blood transfusion in surgical procedures. However, only one trial has studied its impact throughout stomach myomectomy using intravenous tranexamic acid (10 mg/kg patient physique weight to a maximum of 1 g) given 15 min earlier than skin incision versus placebo [21]. Gelatin�Thrombin Matrix Gelatin�thrombin matrix is a hemostatic sealant with bovine-derived gelatin and thrombin parts. In contrast to fibrin glue, gelatin� thrombin matrix is hydrophilic and adheres well to moist tissue. When applied to tissue, the large focus of thrombin and gelatin can lead to rapid hemostasis, which can be helpful in gynecologic surgical procedure. Postoperative blood losses had been about 25 mL for the FloSeal group and 250 mL in the other group. This research suggests the flexibility of gelatin�thrombin matrix to cut back blood loss when applied instantly and directly to the bleeding uterine website before closure of the hysterotomy incision [22]. The blood loss was considerably lower in the group with each bilateral uterine artery and utero-ovarian vessel occlusion (P < zero. Selective progesterone receptor modulators and gonadotropin-releasing hormone analogues are effective at correcting anemia and must be considered preoperatively in sufferers with anemia. Use of vasopressin, bupivacaine and epinephrine, misoprostol, pericervical tourniquet, or gelatin�thrombin matrix reduces blood loss at myomectomy and must be thought of.
Poivre (Black Pepper And White Pepper). Procardia.
- Are there any interactions with medications?
- Dosing considerations for Black Pepper And White Pepper.
- Are there safety concerns?
- How does Black Pepper And White Pepper work?
- Use of white pepper for malaria and cholera.
- Use of black pepper for airway inflammation, or "bronchitis."
- Use of black or white pepper for stomach upset, cancer, pain, scabies, and other conditions.
- What is Black Pepper And White Pepper?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96778
In poorly differentiated or undifferentiated tumors coronary heart joke 30 mg procardia best, immunohistochemical research should be used for additional classification heart disease leading cause of death buy 30 mg procardia fast delivery. A and B cardiovascular technologist programs discount procardia 30 mg with mastercard, Tumor cells have a high nuclear to cytoplasmic ratio cardiovascular system physiology pdf procardia 30 mg, present prominent mitotic activity with focal necrosis (B) and no apparent keratinization. C, Immunostaining for p16 shows sturdy, diffuse nuclear and cytoplasmic positivity. Cytokeratin-negative tissues should then be investigated with antibodies to leukocyte-common antigen to show or rule out malignant lymphoma. The physician ought to keep in mind, nonetheless, that salivary gland tumor tissue sometimes tests constructive for prostate-specific antigen. In these circumstances, cutaneous Merkel cell carcinoma or small cell neuroendocrine carcinoma from either lung or salivary gland is the more than likely diagnosis. Various tissues have been categorized in accordance with their pattern of keratin staining. When epithelial tissue undergoes malignant transformation, its keratin profile normally stays fixed. Both methods provide a really high degree of sensitivity and specificity when used to identify the virus in nasopharyngeal carcinoma and their metastases and thus may be highly helpful ancillary diagnostic aids. Indeed, estrogen receptors may be discovered not only in adenocarcinomas from many different websites, including tumors of salivary gland and thyroid gland origin, but in addition in brain tumors, malignant melanomas, and sarcomas. Thyroid transcription issue 1 is expressed in approximately 80% of adenocarcinomas. Dacic and colleagues315 confirmed that small cell neuroendocrine carcinomas display distinctive profiles of tumor suppressor gene loss in relationship to the first web site of origin and that a profile of allelic imbalance enables main site willpower for these tumors, despite their comparable histologic appearance. The differential diagnosis should concentrate on more than subclassification of malignant tumors, as outlined within the earlier section. Furthermore, the pathologist must be aware that benign lesions may be confused with metastatic disease. In all these entities, the bland appearance of the epithelium that strains the cysts helps to rule out metastatic squamous cell carcinoma. The cysts seen in sufferers with acquired immunodeficiency syndrome are incessantly multiple and bilateral, and the associated lymphoid tissue could exhibit features in maintaining with persistent generalized lymphadenopathy. These inclusions are histologically benign; they lack dysplasia and atypia, as properly as desmoplasia in the adjacent stroma, as is regularly seen in metastatic adenocarcinoma. The authors describe 5 autopsy cases by which cervical nodes contained thyroid tissue; the whole thyroid gland was serially sectioned in every case, but a main tumor was identified in only one case, and it was situated within the contralateral lobe. There is a unilocular cyst lined by bland squamous epithelium with outstanding lymphoid stroma. Hence, diagnostic and therapeutic procedures should be suited to the lesser threat of a in all probability small thyroid most cancers in the context of the lifethreatening head and neck cancer for which the affected person was initially evaluated. This function alone may cause difficulties in both scientific administration and pathologic analysis. For optimum treatment outcomes with a minimum of issues, careful patient choice is crucial. This is reflected by a lower in the 5-year survival price from approximately 60% to 20% with development from stage N1 to N3. The majority of primary tumors are detected within three years after ending therapy of metastatic disease. Neck Dissection In 1991 an important new classification system for neck dissections was put forth by the American Academy of Otolaryngology�Head and Neck Surgery and the American Society of Head and Neck Surgery. They are submental and submandibular; higher, center, and lower jugular, anterior teams; posterior trianglev and superior mediastinal. The submandibular gland is often included within the specimen when the lymph nodes within this triangle are eliminated. The lymph nodes in this group are positioned around the upper third of the inner jugular vein and adjacent spinal accessory nerve extending inferiorly from the level of the lower physique of the hyoid bone to the cranium base. Lymph nodes positioned across the middle third of the internal jugular vein, extending superiorly from a horizontal plane outlined by the inferior body of the hyoid bone and inferiorly to the level of the decrease margin of the cricoid cartilage. The posterior boundary is the posterior border of the sternocleidomastoid muscle or sensory branching of the cervical plexus, and the anterior boundary is the lateral border of the sternohyoid muscle. This group includes lymph nodes situated across the decrease third of the internal jugular vein, extending superiorly from the horizontal airplane defined by the inferior border of the cricoid cartilage to the clavicle inferiorly. The posterior boundary is the posterior border of the sternocleidomastoid muscle, and the anterior boundary is the lateral border of the sternohyoid muscle. This group comprises predominantly the lymph nodes situated alongside the lower half of the spinal accent nerve and along the transverse cervical artery. The posterior boundary is the anterior border of the trapezius muscle, and the anterior boundary is the posterior border of the sternocleidomastoid muscle. This group includes lymph nodes surrounding the midline visceral buildings of the neck, extending from the level of the hyoid bone superiorly to the suprasternal notch inferiorly. Located within this compartment are the perithyroidal lymph nodes, paratracheal lymph nodes, lymph nodes along the recurrent laryngeal nerves, and precricoid lymph nodes. Lymph nodes on this group embody pretracheal, paratracheal, and esophageal groove, extending from the level of the suprasternal notch cephalad and up to the innominate artery caudad. These nodes are at best risk of involvement by thyroid and esophageal cancers. Neck dissections are divided into four classes: radical, modified radical, selective, and prolonged (Table eleven. This includes elimination of the sternocleidomastoid muscle, the interior jugular vein, and the spinal accessory nerve. The modified radical neck dissection refers to excision of all lymph nodes routinely removed by radical neck dissection, with preservation of a number of of the nonlymphatic buildings. The Committee recommends that the structure(s) preserved be particularly named, for instance, modified radical neck dissection with preservation of the spinal accent nerve. Which lymph node groups are removed is based on the sample of metastases, which is predictable relative to the first web site of illness. The revised classification now not uses these names, except in the description of specific lymph node levels. An adequate neck dissection typically will embody 15 or extra lymph nodes in a beforehand untreated patient. Ideally, every stage and sublevel of lymph nodes must be labeled and submitted to the pathology laboratory in separate containers, one container for every stage or sublevel of lymph nodes removed. After the tissue specimen has been oriented and the platysma muscle has been removed, the first step in a gross examination is to measure the dimensions of the sternocleidomastoid muscle and the internal jugular vein and describe their involvement by the tumor. Next, the pathologist should dissect and divide the submandibular gland, sternocleidomastoid muscle, and inside jugular vein and separate the node-containing fats into the five levels: sublingual and submandibular, superior jugular, middle jugular, lower jugular, and posterior. The presence of tumor in soft tissues, submandibular gland, and muscle must be described. The variety of lymph nodes (by level) ought to be noted, and if tumor tissue is present, the scale of the metastases and presence of extranodal extension are likewise indicated. Tissue sections of all lymph nodes (separated by level), the submandibular gland, the sternocleidomastoid muscle, and the interior jugular vein are then submitted for microscopic examination. If the neck dissection is of the extended type, sections of all further lymph node groups and nonlymphatic buildings that had been additionally eliminated ought to be submitted for microscopic examination. If macroscopically enlarged lymph nodes are present, these are famous and embedded of their entirety. Care should be taken to solely depend once those lymph nodes that appeared in multiple sections. This technique permits correct and complete pathologic staging of cervical metastases as a result of the complete neck dissection specimen is examined, as a substitute of choosing obvious lymph nodes. In a multivariate analysis carried out by Carter and colleagues,347 using Cox regression strategies, the important components in predicting survival time were the variety of concerned nodes and the number of involved anatomic teams (P = zero. Involvement of the decrease jugular and 11 Cysts of the Neck, Unknown Primary Tumor, and Neck Dissection 917 posterior triangle nodes and noncontiguous or a number of disease websites have been related to poorer prognoses. Sensitive methods, similar to immunohistochemical and molecular analyses, provide better detection of inapparent metastasis than conventional pathologic strategies, however it is rather necessary to know whether this additional information really has an influence on prognosis. A lymph node free of metastasis by typical histologic examination (pN0, H&E) could present individual malignant cells or a gaggle of them on immunohistochemical evaluation (pN1mi, immunohistochemistry), and a lymph node negative for malignant cells (pN0) by each methods may contain isolated or small clusters of malignant cells by molecular evaluation (pN1mi, molecular analysis). These procedures are more and more being utilized in teaching hospitals and in analysis centers all over the world as potential means of augmenting present pathologic practices. Clinical research in head and neck squamous cell carcinomas recommend that the presence of occult metastasis could identify patients at elevated danger of recurrence and should point out poor prognosis. The approach is predicated on the premise that metastases to the regional lymphatics follow an orderly progression.
Specifications/Details
Laryngeal tuberculosis should be distinguished from overseas body�type granulomatous inflammation in the larynx arteries kidneys procardia 30 mg order visa, which can be seen after Teflon injection or with laryngeal amyloidosis cardiovascular unit nurse proven 30 mg procardia. Empirical remedy (isoniazid coronary heart disease quotes purchase procardia 30 mg fast delivery, rifampin cardiovascular research supplements 30 mg procardia order overnight delivery, pyrazinamide, and streptomycin or ethambutol) is recommended for eight weeks adopted by isoniazid and rifampin for 16 weeks for vulnerable strains. It is endemic to rural areas of Latin America, South and Southeast Asia, Saharan Africa, the Mediterranean basin, and Northern Europe. Leprosy has a predisposition to have an result on cooler peripheral areas, such because the digits, ears, and nostril. It presents as cutaneous hypo- or hyperpigmented, hypoesthetic isolated macular lesions. Early lesions may also be tender, erythematous, and indurated (erythema nodosum leprosum) and may ulcerate. Neural involvement is frequent to all types of leprosy and results in extreme ache and muscle atrophy. Sensory loss finally results in repeat mechanical trauma and secondary infections. Lepromatous leprosy presents with widespread symmetric facial distribution of lesions leading to coarsening of options (leonine facies). Intranasal and paranasal sinus involvement is widespread and happens after cutaneous nasal involvement. Paranasal sinus involvement causes mucopurulent rhinitis, producing copious mucus rife with mycobacteria. Early mucosal lesions are plaque-like; late sinonasal lesions are nodular and/or ulcerative and should finally result in nasal collapse. In a study of 973 untreated leprous sufferers, laryngeal involvement was associated to mycobacterial load: it was seen in 65% of sufferers with lepromatous leprosy and was normally seen with the most advanced cases. Vocal cord paralysis, secondary to recurrent laryngeal nerve involvement, was present in 9% of patients. Upper airway obstruction and dysphonia have been reported as a consequence of laryngeal leprosy. Nerves are surrounded by cuffs of lymphocytes or granulomas or may comprise free acid-fast bacilli. Lepromatous leprosy is characterised by a poor immunologic response and reveals diffuse infiltration by histiocytes that are incapable of present process epithelioid transformation and unable to type granulomas. These foamy histiocytes (lepra cells, Virchow cells) could additionally be "stuffed" with ample mycobacilli (globi), which remain uncleared by the host. The histoid type of leprosy seen in late leprosy is characterized by spindle-shaped histiocytes forming dermatofibroma-like tumors, similar to spindled pseudotumors that may develop in atypical mycobacterial infections. In a biopsy study of 30 circumstances of laryngeal leprosy, solely seven revealed bacilli, most frequently in cases with foamy histiocytes. Primary syphilis results in a localized chancre at the mucosal inoculation website, 1 week to 3 months after initial publicity. In addition to genitourinary websites, chancres can develop in the oral cavity after oral-genital contact and may by the way infect the unwary ungloved examiner. On mucosal surfaces, major chancres may seem as silvery gray erosions, granulation tissue, or nonspecific ulcers, or even mimic carcinoma. Secondary syphilis occurs weeks to months after the primary chancre and is the outcomes of hematogenous spirochete dissemination. Epithelial surfaces are regularly concerned with a wide manifestation of cutaneous and mucosal lesions. The mucosal lesions embrace mucous patches, that are raised and flattened, macerated lesions with a skinny grayish membranous overlaying, and painless ulcers resembling aphthous ulcers, macular/papular lesions, and condyloma latum. Patients often develop fever, pharyngitis, and a generalized, symmetric macular/papular pores and skin rash; the latter might affect the hair follicles of the scalp, eyebrows, and beard, causing a patchy "moth-eaten" alopecia (alopecia syphilitica). The diffuse maculopapular rash can extend intraorally and could also be related to laryngeal hyperemia. The macular/papular 5 Nonsquamous Pathologic Diseases of the Hypopharynx, Larynx, and Trachea 327 lesions coalesce in heat moist areas, such because the anogenital and intertriginous areas, to type the hyperplastic lesion condyloma latum (flat condyloma), which can be infectious. Generalized lymphadenopathy happens during the secondary stage, with a predisposition for periarticular lymph nodes, as in epitrochlear and inguinal areas. Secondary syphilis will lapse into a latent state, but sufferers may frequently expertise recurrent mucocutaneous symptoms of secondary syphilis. When untreated, roughly one-fourth of sufferers will develop a relapse of secondary signs; 90% of relapses happen within the first year of infection. Tertiary syphilis is the long-term persistent systemic results of untreated infection, which can be manifested years to decades after primary an infection. Tertiary syphilis has a predisposition to have an result on the central and peripheral nervous methods and the cardiovascular system. Gummas, the harmful lesions of late tertiary syphilis, have a proclivity for membranous bones, generally affecting the palate. Laryngeal framework, nasal and temporal bones, and ossicles may develop gummas. Gummas are painless raised ulcerative plenty that may rapidly progress to necrotic destructive lots. Mucosal patches on the tongue, palate, and lips could turn into fissured and hemorrhagic, leading to radial scars. Primary chancre reveals central necrotic particles and dense continual irritation on the periphery. Lymphoplasmacytic vasculitis in a "coat sleeve"�like association, giant cells, and endothelial swelling are seen. Interpretation of the silver stains is made tough by the presence of melanocytes and reticulin fibers, in addition to spirochetes apart from T. Granulomas with multinucleated big cells and epithelioid histiocytes could additionally be a late finding. Condyloma latum is composed of epithelial hyperplasia (rather than the attenuated epithelium of chancres) with elongated rete pegs and dense lymphoplasmacytic infiltrates with perivascular cuffing of plasma cells. Lymph nodes comprise noncaseating granulomas, perivascular cuffing of plasmacytes, and capsular fibrosis. The gummas of late secondary and tertiary syphilis reveal necrotizing granulomas with multinucleated Langerhanstype big cells and obliterative endarteritis. Recurrent laryngeal nerve paralysis may be seen in neurosyphilis as a manifestation of central nervous system disease, along with different cranial nerve deficits or as an isolated nerve palsy. The classic dark-field examination is made by examining transudate from a chancre suspended in saline for the motile spirochetes. A extra particular form of this examination is the dark-field direct immunofluorescent antibody test for T. Immunohistochemical staining, with commercially obtainable polyclonal antibody, could also be helpful in cases that clinically and histologically counsel major or secondary syphilis, but are adverse by silver staining. Lymphoplasmacytic infiltrates can also be seen in nonspecific laryngitis and in the early levels of scleroma (see later). Blastomyces an infection is classically identified for inducing a hyperplastic hyperkeratotic mucosal response, similar to condyloma latum. Clinical historical past and special stains and/or cultures should distinguish blastomycosis from condyloma latum. The hyperplasia of condyloma latum may also be confused with laryngeal malignancy. A, Mixed cell inflammation of the floor epithelium, and dense inflammation of the subepithelial stroma with plasma cells. B, Immunohistochemistry reveals numerous spirochetes in the surface epithelium and few in the stroma. These latter infections may be separated on the idea of tradition and particular stains. Patients allergic to penicillin may be treated with erythromycin, tetracycline, or ceftriaxone. Ferdinand von Hebra and Moritz Kohn (formerly named Kaposi) coined the term rhinoscleroma to describe these patients presenting with onerous (sclero) noses (rhino),35 which they originally concluded have to be secondary to indolent malignancy. Interestingly, aniline dye workers in San Salvador had been noted within the late 19th century to have an elevated prevalence of rhinoscleroma. Alvarez found a bacillus in the legume, which he known as Bacillus indigogenous, and concluded that it was similar to Frisch bacillus. Human-to-human transmission has been assumed to be the only mode of contact, and infection will end result solely after prolonged publicity. Increased incidence amongst relations and contacts has been famous, but this stays controversial.
Syndromes
- Electroencephalogram (EEG)
- Reactions to medicines
- You have a sore that does not heal
- Low density lipoprotein (LDL or "bad" cholesterol)
- Tremors (shaking)
- Sudden severe pain in one testicle. The pain may occur without a clear reason.
Related Products
Additional information:
Clinically heart disease cardiomyopathy procardia 30 mg trusted, enlargement of the thyroid gland by any trigger is referred to as goiter zebra cardiovascular system 30 mg procardia order with visa. Hyperplasia of the thyroid gland may be related to hyperfunction (Graves disease) cardiovascular disease mortality procardia 30 mg buy generic on line, hypofunction (endemic goiter arteries and veins of the neck cheap 30 mg procardia overnight delivery, dyshormonogenetic goiter), or regular perform (multinodular goiter). Graves Disease (Diffuse Hyperplasia) Graves disease (diffuse poisonous goiter) is essentially the most frequent cause of thyrotoxicosis. The time period thyrotoxicosis refers to a spectrum of changes that result from publicity of the physique to excess quantities of thyroid hormone. The causes of hyperthyroidism in the order of frequency embrace Graves disease, poisonous multinodular goiter, and toxic adenoma. Most patients with Graves illness present in the third or fourth decade, with a four- to five-fold predominance in girls. A genetically decided organ-specific defect in suppressor T lymphocytes could also be answerable for initiating immunoglobulin production by B lymphocytes. On cross section, the gland lacks the glistening appearance of regular thyroid but somewhat seems beefy and pink. Colloid is scanty and typically reveals a really pale eosinophilic appearance with peripheral scalloping. Increased abundance of colloid is usually current on the time of thyroidectomy following medical treatment to slow the release of thyroid hormones from the follicles. The stroma might seem barely fibrotic, and occasional lymphoid follicles with energetic germinal centers may be evident. Both lobes of the thyroid are diffusely en- follicular cells, which become cuboidal quite than columnar, and in the accumulation of colloid. The late adjustments include fibrosis with follicular atrophy and scattered follicular cells with enlarged hyperchromatic nuclei. The major agents employed in the chemotherapeutic management of affected patients include medicine of the thioamide class, which inhibit the oxidation and natural binding of iodide. Subtotal thyroidectomy, conversely, is related to recurrent illness in only 10% of circumstances, however the danger of problems, together with everlasting hypothyroidism, vocal twine paralysis, and hypoparathyroidism, is comparatively high. Radioiodine administration produces the ablative results of surgical procedure with out the immediate operative and postoperative problems of subtotal thyroidectomy. The major disadvantage of radioactive iodine administration, however, is the late improvement of hypothyroidism. Selection of specific forms of remedy ought to be tailor-made to the needs of particular person patients. The time period endemic goiter is used when this situation occurs in more than 10% of the population in a defined geographic space. The most essential endemic goiter regions include the northern and southern slopes of the Himalayas, the Andean region of South America, the European Alps, mountainous regions of China, central regions of Africa, and, to a lesser extent, the coastal areas of Europe. Low levels of dietary iodine are the most important explanation for endemic goiter; nevertheless, ingestion of pure goitrogens (vegetables of the Brassica household, together with cabbage and turnips, which comprise high concentrations of thioglucosides) may be responsible for the event of goiter. Cyanoglucosides represent another important group of goitrogens and are present in excessive concentrations in cassava, maize, bamboo shoots, and candy potatoes. In basic, the severity of goiter formation is said to the extent of iodine deficiency. Initially, goiter formation is diffuse, but with repeated episodes of hyperplasia and involution, multiple nodules supervene to produce a diffuse and nodular goiter, just like that noticed in patients with nontoxic nodular goiter. Endemic goiter may be prevented by the addition of iodine to the food plan and by the elimination of goitrogens in the food plan. The varied defects embrace these involved in iodide transport, organification, iodotyrosine coupling, iodotyrosine dehalogenase activity, and iodoprotein secretion. On cross part, individual nodules range from these which are beefy red to these which are firm and white to gray-tan. Other nodules could exhibit more stable development patterns with pronounced nuclear hyperchromasia and mitotic exercise. Because of the atypical cytologic features, the solid look of lots of the nodules, and the presence of partial fibrous encapsulation, the potential of malignancy is commonly entertained, particularly when the medical historical past is unavailable. Rare examples of follicular and papillary thyroid carcinoma developing in sufferers with dyshormonogenetic goiter have been reported. Surgery is indicated in these sufferers with very massive goiters causing bodily disfigurement or compressive signs. In sufferers with severe types of the illness, each progress retardation and mental retardation happen except thyroid hormone is changed very early in the course of the disease. The term nontoxic goiter, also identified as multinodular, easy, or colloid goiter, refers to nodular enlargement of the thyroid gland within the absence of hyperthyroidism or hypothyroidism, inflammatory processes, or neoplasms. With large goiters, displacement or compression of the esophagus and trachea could give rise to dysphagia or dyspnea. The development of goiter more than likely results from a selection of mechanisms that lead to impairment of T3 and T4 production. The preliminary phase of the event of this sort of goiter is characterised by diffuse glandular enlargement. There is nodular hyperplasia of follicular cells with the formation of papillary infoldings of the epithelium and scant quantities of colloid. Rupture of follicles might result in inflammation with histiocytes, lymphocytes, and multinucleate big cells. The illness process is, due to this fact, characterized by alternating phases of hyperplasia and involution. Usually, the gland is markedly distorted by multiple nodules that measure from lower than 1 cm to many centimeters in diameter. Individual nodules may be partially demarcated from the adjoining thyroid parenchyma by an incomplete fibrous capsule. In contrast to adenomas, which generally have a uniform follicular architecture, hyperplastic nodules are characterised by variation in follicular dimension. Degenerative changes together with hemorrhage, calcification, and ossification are frequent. In some instances, a single nodule could also be present, with the remainder of the gland showing either normal or mild hyperplastic change. The nodules may be partially encapsulated and have a comparatively uniform microfollicular progress sample. In such instances, the distinction between a hyperplastic nodule and a follicular adenoma is especially troublesome. The time period adenomatoid nodule or adenomatous change is usually used for these nodules, acknowledging a similarity of their appearance to follicular adenomas. This thyroid lobe is totally changed by multiple nodules, a few of that are partially encapsulated. Patients with large multinodular goiters with evidence of compressive symptoms are generally handled by thyroidectomy. The dying price for thyroid most cancers of all kinds is roughly 5 cases per million, with a rise of 0. Genetic and environmental elements have been implicated within the development of thyroid cancer. Tumors of C-cell origin account for approximately 2% to 3% of all thyroid neoplasms, whereas malignant lymphomas account for a smaller proportion of the instances. The introduction of this system has resulted in a decreased fee of thyroid surgery and an increased price of identifying cancer when surgical procedure is performed. In basic, the true false-negative fee varies between 1% and 2%,one hundred thirty whereas the false-positive fee is approximately 1%. Therefore frozen section is often only reported as follicular neoplasm and ultimate classification is deferred to permanent evaluation. They are normally the result of degeneration, hemorrhage, or necrosis of an adenomatous nodule. True main cysts of the thyroid are exceedingly rare, though cystic degeneration of solid cell nests has been reported. Aspirates of many thyroid cysts are sometimes technically inadequate because of poor cellularity. It is subsequently essential to assess the adequacy of the specimen to avoid a false-negative diagnosis. Any cyst that recurs or any palpable nodule recognized after evacuation of a cyst should be reaspirated to rule out malignancy.
Usage: t.i.d.
Rarely quivering arteries 30 mg procardia quality, glandular odontogenic cysts even may exhibit small islands resembling mucoepidermoid carcinoma inside their partitions cardiac disease 30 mg procardia discount free shipping. Although predominantly cystic (>85% of cases) cardiovascular system energy cheap procardia 30 mg line, a major percentage of these lesions demonstrates a strong cardiovascular disease journals buy procardia 30 mg with mastercard, neoplastic growth sample and have been referred to as dentinogenic ghost cell tumor. Moreover, malignant transformation of both the cystic and solid variants has been described (ghost cell odontogenic carcinoma, among different terms). Several excellent papers have reviewed the debate pertaining to classification of ghost cell lesions. The calcifying odontogenic cyst may be encountered at any age, with a peak within the second and third a long time (mean age, 33 years) and no vital gender predilection. There is an equal distribution between the maxilla and mandible, with the majority of lesions involving the incisor/ canine area. Lesions seldom exceed 4 cm in greatest diameter; nevertheless, massive lesions measuring over 10 cm have been described. B, Well-demarcated, corticated radiolucency with central radiopaque areas of the anterior maxilla. Medium-power photomicrograph exhibiting odontogenic epithelium surrounding a cystic lumen. Note the palisaded cuboidal basal cells related to stellate-reticulum-like tissue and non-nucleated, eosinophilic cells (ghost cells). High-power photomicrograph exhibiting aggregates of ghost cells present process focal calcification (inset). Radiographic examination usually reveals an ill-defined radiolucent or mixed radiolucent-radiopaque lesion with resorption or displacement of the adjacent tooth roots. Overall, a predominantly cystic architecture is seen in 85% of cases, whereas a stable, neoplastic progress sample is evident in 15% of instances. The epithelial lining reveals a peripheral basal cell layer of cuboidal or columnar cells that help loosely arranged, stellate reticulum-like cells paying homage to an ameloblastoma. The mechanism of this cellular alteration is unclear and has been attributed to aberrant keratinization or coagulation necrosis. High-power photomicrograph showing ghost cell change with areas of dystrophic calcification. On occasion, a calcified matrix that doubtless represents dysplastic dentin is recognized. The cyst lumen may be crammed with ghost cells and dystrophic calcifications or, in rare situations, projections of epithelium that mimic an ameloblastoma. Satellite cysts that elicit a foreign physique response may be observed within the cyst wall. The calcifying odontogenic cyst can be related to other odontogenic tumors, corresponding to odontoma (most commonly),159,160 adenomatoid odontogenic tumor, ameloblastic fibroma, and ameloblastoma. The epithelium displays ameloblastic options, together with columnar peripheral cells that show nuclear palisading and surround stellate reticulum-like tissue. Typically, ghost cells are readily identifiable, and ranging quantities of juxtaepithelial dentinoid are current. Ghost cell odontogenic carcinoma displays features just like these of the dentinogenic ghost cell tumor however with cytologic features of malignancy, including mobile atypia and pleomorphism, conspicuous mitotic exercise, necrosis, and infiltration of the adjoining tissues. Transition from a calcifying odontogenic cyst or dentinogenic ghost cell tumor may be seen. Although immunohistochemical studies are limited, at least one group has demonstrated constant positivity within the epithelial cells of calcifying odontogenic cysts for cytokeratins 7, eight, 14, and 19. The epithelium in ameloblastoma closely resembles that of calcifying odontogenic cyst. Similarly, these features help in distinguishing ghost cell odontogenic carcinoma from ameloblastic carcinoma. Interestingly, marked similarities exist between calcifying odontogenic cyst and pituitary craniopharyngioma. Enucleation and curettage are the treatments of choice for the calcifying odontogenic cyst, and the prognosis is good. The behavior of dentinogenic ghost cell tumors and ghost cell odontogenic carcinomas is tough to predict due to their rarity. En bloc resection usually is advocated, as is longterm clinicoradiographic surveillance. For ghost cell odontogenic carcinomas, the 5-year survival price is 73%, with deaths attributed to uncontrolled native disease or metastases. When the pulp of a tooth undergoes necrosis due to caries or trauma, a granulation tissue response (known as a periapical granuloma) may develop around the root apex as a defensive reaction to bacteria and poisonous merchandise from the basis canal. If this inflammation persists, it might stimulate proliferation of epithelium around the root to form a cyst. In most instances, the source of this epithelium is believed to be the rests of Malassez, which are remnants of odontogenic epithelium discovered throughout the periodontal ligament alongside the tooth root. In different situations, the cystic epithelium could originate from the gingival crevicular epithelium, sinus mucosa, or lining of a fistulous tract. Periapical cysts occur in sufferers over a large age vary, with a peak within the third and fourth many years of life. However, many periapical cysts are asymptomatic and discovered incidentally throughout routine radiographic examination. Wellcircumscribed radiolucency positioned at the apex of the maxillary left lateral incisor. Well-circumscribed radiolucency situated lateral to the basis of the proper maxillary lateral incisor, which has already undergone root canal therapy. Low-power view displaying a cyst lined with an irregular and proliferative layer of stratified squamous epithelium. High-power view showing arcading of the rete ridges and scattered inflammatory cells throughout the epithelium and cyst wall (inset). The radiolucency might seem either well defined or poorly circumscribed, and adjoining root resorption is feasible. Most periapical cysts are 2 cm or less in most diameter, although occasional lesions could demonstrate dramatic enlargement with destruction of a significant portion of the jaw. Although such cysts may seem radiographically similar to the developmental lateral periodontal cyst, they need to be distinguished as being inflammatory in etiology. Such a lesion normally presents as a well-circumscribed radiolucency in the extraction web site. Older residual periapical cysts generally develop dystrophic calcification, resulting in a central area of radiopacity. At occasions, the wall may exhibit bright yellow zones that microscopically correspond to collections of lipidladen foamy macrophages. Microscopically, most lesions are lined by nonkeratinizing stratified squamous epithelium, although ciliated pseudostratified columnar or simple cuboidal epithelium additionally may be famous in some instances. Because of in depth ulceration, some periapical cysts may present solely focal remnants of an epithelial lining. Mucous cells have been recognized in roughly 7% to 40% of periapical cysts; these cells often are discovered along the floor layer, both individually or in a steady row. In addition, many periapical cysts include cholesterol clefts which may be associated with a giant cell response. Therefore clinical correlation and cautious microscopic examination of the whole cystic lining are necessary to guarantee the proper diagnosis. The therapy of periapical cysts often includes both root canal therapy or extraction of the related tooth. If the tooth is extracted, the cyst should be curetted and submitted for histopathologic examination to confirm the analysis. Such malignancies may characterize lower than 2% of all carcinomas seen in some oral and maxillofacial pathology companies. B, Islands of invasive squamous cell carcinoma could be seen infiltrating into the cyst wall. Compared to plain radiography, computed tomography may be superior for demonstrating border irregularity and tumor extent.
Tags: cheap procardia 30 mg free shipping, generic procardia 30 mg without a prescription, buy cheap procardia 30 mg line, 30 mg procardia best, order procardia 30 mg without a prescription, buy 30 mg procardia visa, 30 mg procardia with mastercard, buy cheap procardia 30 mg on-line, procardia 30 mg generic mastercard, procardia 30 mg generic on line, procardia 30 mg order online, buy discount procardia 30 mg on-line, purchase procardia 30 mg free shipping, order procardia 30 mg line, buy discount procardia 30 mg line, 30 mg procardia fast delivery
9 of 10
Votes: 111 votes
Total customer reviews: 111
Customer Reviews
Diego, 50 years: Lack of monotypic plasma cells and absence of atypia argue in opposition to a malignant process. The term H�rthle cell, although ingrained in pathology terminology, is technically a misnomer as a result of the cells that H�rthle described in the dog thyroid have been most likely C cells.
Daryl, 49 years: Gelatin�Thrombin Matrix Gelatin�thrombin matrix is a hemostatic sealant with bovine-derived gelatin and thrombin components. They are the end result of the harm to desmosomes and 5 Nonsquamous Pathologic Diseases of the Hypopharynx, Larynx, and Trachea 357 hemidesmosomes, brought on by acquired or inherited defects in proteins, that are constituents of desmosomes or hemidesmosomes or bind to these constructions.
Gelford, 59 years: Even its surgery is associated with the chance of problems, notably ureteric and uterine vessel accidents and hid hematoma formation [9]. The analysis of minor salivary gland tumors on limited biopsy materials is particularly difficult as a end result of benign minor salivary tumors are rarely encapsulated but are incessantly nicely circumscribed.
Hatlod, 62 years: In addition, one affected person with lymph node metastasis additionally developed distant metastasis to the lung and vertebrae, and died of the disease 20 years after preliminary analysis. There are multiple nests of basaloid tumor cells with focal ductal differentiation in a lymphoid background.
Quadir, 29 years: In addition, enchondromas may contain some cells with enlarged, open-faced nuclei, as in chondrosarcoma. The clear cell variant should be distinguished from different clear cell salivary gland tumors, together with metastatic renal cell carcinoma559 (Table 6.
Pranck, 47 years: Salivary duct carcinoma: an replace on morphologic mimics and diagnostic use of Androgen Receptor 1383. D Sandmeier, H Bouzourene, 2002 Necrotizing sialometaplasia: A diagnostic pitfall.
