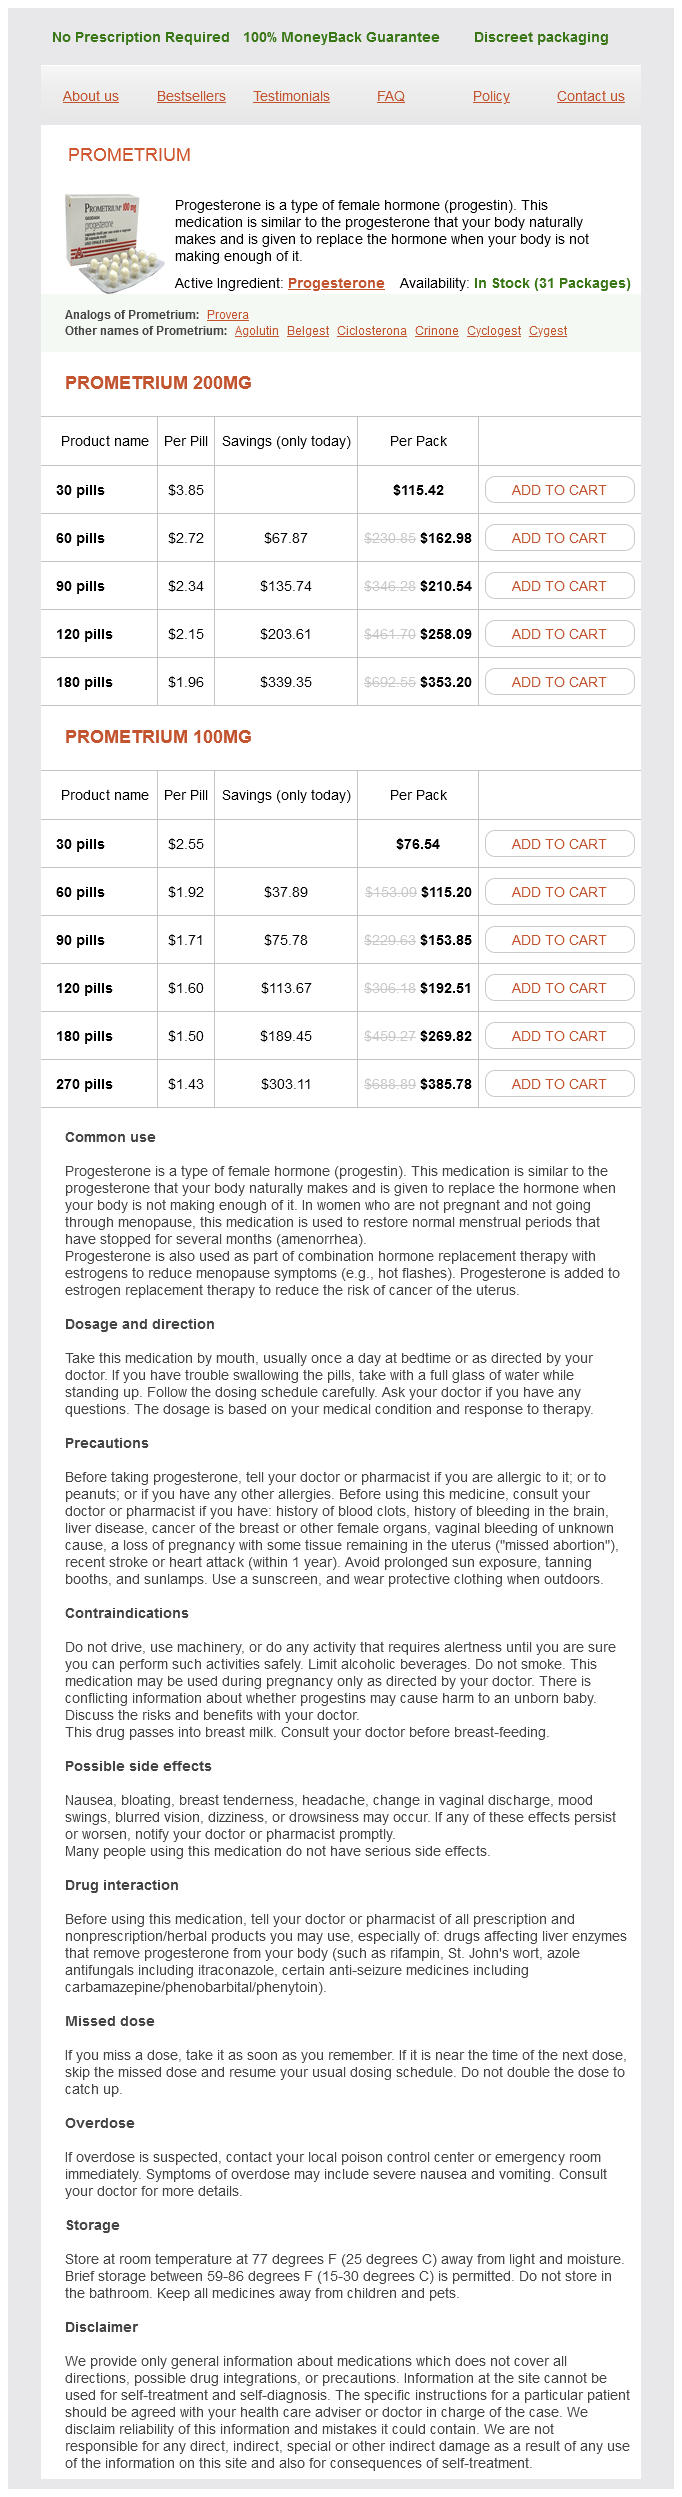
Prometrium 200mg
- 30 pills - $115.42
- 60 pills - $162.98
- 90 pills - $210.54
- 120 pills - $258.09
- 180 pills - $353.20
Prometrium 100mg
- 30 pills - $76.54
- 60 pills - $115.20
- 90 pills - $153.85
- 120 pills - $192.51
- 180 pills - $269.82
- 270 pills - $385.78
Prometrium dosages: 200 mg, 100 mg
Prometrium packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills
In stock: 839
Only $1,52 per item
Description
Scalp the scalp is properly vascularized medications canada trusted prometrium 200 mg, and when lacerated treatment xanax overdose buy 200 mg prometrium otc, bleeds copiously and sufficiently to lead to symptoms 12 dpo 200 mg prometrium safe shock symptoms zyrtec overdose prometrium 200 mg discount online. Blows to the pinnacle usually lead to jagged stellate lacerations of the scalp, whereas bullet wounds tend to be discrete rounded defects. Fortunately, the scalp is very resilient, and solely essentially the most severe avulsing injuries lead to everlasting harm (these avulsion injuries often end result from entanglement of hair in machinery or in vehicular accidents in which the head is dragged on the pavement). FungusCerebri If a traumatic or surgical defect is present within the cranium, mind under increased stress can extrude from the opening. Cerebral Edema Another pathophysiologic course of that may contribute to elevated intracranial pressure is the development of cerebral edema. Cerebral edema can complicate any course of that offers rise to elevated stress, making a self-perpetuating cycle during which growing edema begets growing stress which in turn begets extra edema. The blood-brain barrier compartmentalizes the brain from the Skull the cranium is the most important protector of the mind. Its perform is to soften blows and, when the forces are sufficiently intense, to fracture, dissipating the energy of the influence. The most typical boney defect is a linear cranium fracture, so named as a result of they seem on skull radiographs as radiolucent lines that can run considerable distances from their origins. In addition, seepage of blood into the delicate tissues of the top can result in black eyes and blood in the center ear. Dura Lacerations of vessels of the dura lead to life-threatening accumulations of blood within the cranial vault including epidural and subdural hematomas. Patients with burst lobes may have delayed neurological deterioration between 24 and seventy two hours after damage due to cerebral edema and contusion enlargement. The neurological deterioration is usually fast, and these patients fare no better than these in whom the hematoma was an extension of extreme major mind harm. They normally happen in the context of a skull fracture involving the groove of the middle meningeal artery in which that artery is lacerated by the jagged edges of bone. This arterial bleeding can result in rapid accumulation of blood in the epidural area with concomitant increased intracranial strain. The affected person may be deceptively lucid in the early phases of hematoma accumulation, however within minutes to hours, progressive mental standing deterioration happens if the hematoma is giant, leading to mass effect and uncal herniation. In these cases, only well timed surgical evacuation of the hematoma will save the affected person. With rising age, the dura mater becomes extra adherent to the overlying bone, decreasing the prospect that a hematoma can develop in the house between the cranium and dura; nonetheless, concomitantly the meningeal vessels become embedded in bone and are at greater danger for being lacerated. Also observe the current focal cortical infarction in anterior cerebral artery vascular territory because of severe cingulate herniation. These veins traverse a longer, more tightly tethered course because the mind undergoes atrophy with getting older or substance abuse; due to this fact, the high-risk populations are composed of elderly or alcoholic persons. The clinical course may be indolent, but continual subdural hematomas may be deceptively harmful. Because these membranes possess numerous delicate blood vessels, recurrent hemorrhage happens usually leading to gradual enlargement of the lesion. Surgical drainage of the hematoma and removing of the membranes is necessary for definitive treatment. The formation of the outer layer membranes proceeds at a predictable pace and is beneficial for the forensic courting of the hematoma. Later, between 2 and three weeks, a skinny inside membrane (the visceral layer) forms between the hematoma and the thin residual inner border cell, resulting in full encapsulation of the hematoma. In many situations, nevertheless, these delicate vessels are subjected to shear forces related to on an everyday basis head actions, resulting in microhemorrhages that in turn lead to gradual enlargement of the hematoma. Concussion Concussion is a transient alteration of consciousness following a non-penetrating blow to the head. The structural and physiological foundation of this phenomenon is unclear, though it could contain transient torsion with malfunction of the reticular activating system. The autopsy in the uncommon dying which occurs on this setting might disclose no structural abnormalities or minimal swelling. The small, dark areas replicate latest hemorrhages resulting in gradual enlargement of the lesion. The darkish brown and tan regions comprise subacute to persistent blood breakdown merchandise. A, Microscopic part of a chronic subdural hematoma showing microhemorrhages and granulation tissue. B, Computed tomographic picture of an acute on continual subdural hematoma showing admixture of recent and old blood. The subdural hematoma is exerting substantial mass effect with sulcal effacement and midline shift. These accidents end result from the mind being jostled towards intracranial boney and dural surfaces. The severity and distribution of cerebral contusions is decided partly by the mobility of the head at impact. If the pinnacle is struck whereas immobilized, the major target of the damage shall be on the impression site-a so-called coup injury. Contra-coup accidents are thought to outcome from acceleration or deceleration (in the case of falls) imparted to the mind by the impression. Histologically, acute contusions encompass hemorrhagic necrosis; later, the dead tissue is removed by macrophages leaving an irregular tan defect with a glial ground on the cortical surface. Multiple current contusions of varying size and depth involving inferior frontal lobes. Intermediate contusions of central white matter and small gliding contusions are present within the left parasagittal subcortical white matter. Hemosiderin-stained areas of gliotic and meningeal fibrotic scarring representing continual contusions of inferior frontal and temporal lobes. There is lack of olfactory nerves (anosmia is the most common cranial neuropathy following closed traumatic brain injury). If the cranium fractures, then fracture contusions occur beneath the positioning of a fracture, often at the website of influence, and mind lacerations are potential. Contra-coup contusions occur one hundred eighty levels away from the influence site on the alternative side of the mind. Intermediate contusions, also called gliding contusions, are intracerebral contusions that happen deep throughout the neuroglial parenchyma between the impact site and the opposite facet of the mind. Intermediate contusions are often associated with diffuse axonal damage, reflecting the shared underlying biomechanics. Herniation contusions contain the medial temporal lobes and the cerebellar tonsils and are produced by motion of the brain impacting on the inflexible tentorium cerebelli or the bony margins of the foramen magnum. The total contusion sample is decided by the course and magnitude of the impacting pressure and whether the head is stationary or in motion at the time of the influence. If the pinnacle is stationary at the time of impression and experiences linear or angular acceleration, the contusion pattern is extra complex than if the pinnacle is stationary and constrained from motion. The surface contusions will be most severe in the frontal and temporal lobes irrespective of the cranial influence website, provided the forces performing on the top are adequate to impart movement of the mind over the irregular bony surfaces of the anterior and middle cranial fossae. Sudden deterioration is a feature particularly of patients with severe bifrontal contusions, temporal pole pulping, and "burst" lobes. Cerebral contusions are focal accidents that result when mechanical forces damage the small blood vessels and neuroglial tissue. Bleeding from broken blood vessels is essentially the most conspicuous function on macroscopic and microscopic examination with the lesions starting from microhemorrhages to confluent hemorrhage disrupting the tissue. In a easy contusion, the overlying pial membrane remains intact, whereas disruption of the pial membrane with tearing of the underlying tissue constitutes a laceration. Contusions and lacerations, subsequently, exist on a continuum of tissue harm severity. Surface contusions of the brain present a variety of morphologic appearances from microhemorrhages visible only with the microscope to confluent hemorrhagic necrotic lesions extending through the cortex into the subcortical white matter. In 1980 and 1985, Adams and colleagues30,31 proposed a contusion index that was designed to capture, quantify, and simplify the contusion burden in a mind primarily based on regional surface distribution and parenchymal depth of contusions of the mind. Five hours later, extreme clinical deterioration has occurred and enormous bilateral frontal contusions with intraventricular extension of hemorrhage are seen on axial (B) and coronal (C) imaging. In the Omalu system, gyral unfold is assigned a grading scheme of 0 to three, and the parenchymal depth of contusions is assigned a grading scheme of zero to 4.
Chimaphila Umbellata (Pipsissewa). Prometrium.
- What is Pipsissewa?
- How does Pipsissewa work?
- Dosing considerations for Pipsissewa.
- Urinary tract infections (UTIs), kidney stones, spasms, fluid retention, seizures, anxiety, cancer, ulcerous sores, and blisters.
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96144
Efficacy of methylphenidate in the rehabilitation of consideration following traumatic brain harm: a randomised symptoms bone cancer purchase prometrium 200 mg without prescription, crossover symptoms upper respiratory infection 100 mg prometrium, double blind treatment regimen buy prometrium 100 mg online, placebo managed inpatient trial medicine reminder app order 200 mg prometrium. Impact of pharmacological therapies on cognitive and behavioral outcome in the postacute levels of grownup traumatic brain injury: a meta-analysis. Pharmacological enhancement of cognitive and behavioral deficits after traumatic mind harm. Atomoxetine for consideration deficits following traumatic mind injury: results from a randomized controlled trial. Cholinergic augmentation with donepezil enhances recovery in short-term memory and sustained attention after traumatic mind damage. An open-label, comparative research of rivastigmine, donepezil and galantamine in a real-world setting. Sertraline to enhance arousal and application in severe traumatic brain harm secondary to motorcar crashes. Sertraline within the treatment of main melancholy following delicate traumatic brain damage. Impact of early administration of sertraline on depressive symptoms within the first year after traumatic brain injury. Dopaminergic-adrenergic interactions in the wake promoting mechanism of modafinil. Efficacy of modafinil on fatigue and excessive daytime sleepiness associated with neurological issues: a systematic evaluate and meta-analysis. A randomized trial of modafinil for the remedy of fatigue and excessive daytime sleepiness in people with persistent traumatic mind injury. The impact of acute care drugs on rehabilitation end result after traumatic mind harm. The Overt Aggression Scale for the objective rating of verbal and physical aggression. Pharmacological management of neurobehavioural sequelae of traumatic mind harm: a survey of present physiatric practice. Pharmacological administration for agitation and aggression in individuals with acquired brain harm. Effectiveness of amantadine hydrochloride in the discount of continual traumatic brain damage irritability and aggression. Insomnia in sufferers with traumatic brain injury: frequency, characteristics, and risk factors. Association of sleep and co-occurring psychological circumstances at 1 12 months after traumatic brain harm. Subjective and objective measures of insomnia in the context of traumatic mind injury: a preliminary research. Efficacy of cognitive-behavioral therapy for insomnia associated with traumatic brain injury: a single-case experimental design. The effect of sleep medications on cognitive recovery from traumatic mind harm. A randomized controlled trial of sertraline for the treatment of despair in persons with traumatic brain damage. Depression following grownup, non-penetrating traumatic mind damage: a metaanalysis analyzing methodological variables and sample traits. Racial/ethnic disparities in psychological well being over the primary two years after traumatic brain damage: a mannequin methods examine. Comparing results of methylphenidate, sertraline and placebo on neuropsychiatric sequelae in patients with traumatic mind injury. Latest approaches for the treatment of spasticity and autonomic dysreflexia in chronic spinal twine injury. Clinical scales for the evaluation of spasticity, related phenomena, and performance: a systematic review of the literature. Meta-analysis of the efficacy and security of Sativex (nabiximols), on spasticity in folks with multiple sclerosis. Systematic evaluate: efficacy and security of medical marijuana in selected neurologic problems: report of the Guideline Development Subcommittee of the American Academy of Neurology. A novel pressure of Clostridium botulinum that produces type B and kind H botulinum toxins. Medical issues, bodily function and communication expertise in sufferers with traumatic brain harm: a single centre 5-year experience. Incidence, threat components, and outcomes of fecal incontinence after acute brain harm: findings from the Traumatic Brain Injury Model Systems national database. Urinary disturbances following traumatic mind injury: clinical and urodynamic evaluation. Clinical outcomes of sacral neuromodulation in patients with neurologic circumstances. Causes and complications related to swallowing issues in traumatic brain damage. Evolution of tracheal aspiration in severe traumatic mind injury-related oropharyngeal dysphagia: 1-year longitudinal follow-up examine. Mortality over four decades after traumatic brain harm rehabilitation: a retrospective cohort study. Formal swallowing analysis and remedy after traumatic mind damage improves dysphagia outcomes. Functional oral consumption and time to reach unrestricted weight-reduction plan for sufferers with traumatic brain injury. Hypermetabolism following moderate to severe traumatic acute brain damage: a systematic evaluation. Metabolism and diet in patients with average and severe traumatic mind harm: a systematic evaluation. Tolerance and efficacy of enteral diet in traumatic brain-injured patients induced into barbiturate coma. Nutritional support for sufferers sustaining traumatic brain injury: a scientific review and metaanalysis of prospective research. The Brain Trauma Foundation; the American Association of Neurological Surgeons; the Joint Section on Neurotrauma and Critical Care. Venous thromboembolism prophylaxis and treatment in sufferers with acute stroke and traumatic brain injury. Evidence-based venous thromboembolism prophylaxis is associated with a six-fold decrease in numbers of symptomatic venous thromboembolisms in rehabilitation inpatients. Head damage and pulmonary embolism: a retrospective report based on the Pennsylvania Trauma Outcomes study. Incidence and threat elements for deep venous thrombosis after average and severe mind harm. The utility of routine screening for deep vein thrombosis upon admission to an inpatient mind harm rehabilitation unit. Safety and efficacy of early thromboembolism chemoprophylaxis after intracranial hemorrhage from traumatic mind harm. Safety and efficacy of heparin or enoxaparin prophylaxis in blunt trauma patients with a head abbreviated damage severity rating >2. Deep venous thrombosis administration following traumatic mind harm: a follow survey of the traumatic brain injury model techniques. Survival effects of inferior vena cava filter in sufferers with acute symptomatic venous thromboembolism and a significant bleeding threat. Comparison of the efficacy and security of new oral anticoagulants with warfarin in patients with atrial fibrillation: a meta-analysis of randomised trials. Headache after traumatic brain damage: a national survey of clinical practices and therapy approaches. Deficient pain modulatory methods in patients with gentle traumatic mind and chronic posttraumatic headache: implications for its mechanism. Evidence-based guideline replace: pharmacologic treatment for episodic migraine prevention in adults: report of the Quality Standards Subcommittee of the American Academy of Neurology and the American Headache Society.
Specifications/Details
Despite this improve in rates of early mortality treatment warts cheap prometrium 100 mg line, there was a significant discount in the overall end result of dying or dependency (poor useful outcome) treatment 5th finger fracture prometrium 100 mg order online, with an odds ratio of zero medicine 3605 v discount prometrium 100 mg visa. Thus for sufferers who avoided early demise medications by class purchase 200 mg prometrium overnight delivery, there was a considerable discount within the danger of turning into dependent. Of the entire dose, 10% must be administered as a bolus over 1 minute, and the remainder of the dose infused over a 60-minute interval. In addition, antagonistic occasions that must be beneath surveillance include systemic bleeding, myocardial rupture (with concomitant or earlier myocardial infarction), anaphylaxis, and angioedema (5. If the presence of intracranial or systemic hemorrhage is suspected, diagnostic tests (including full blood cell depend with platelet counts) and coagulation research must be carried out. Empirically, care ought to be offered in accordance with pointers for the administration of acute hemorrhagic stroke. Thus though these agents have proven some promise, their security and efficacy have to be additional assessed in large randomized managed trials earlier than they are often beneficial for routine care. Intra-arterial thrombolysis was developed as an various to extend this time window by delivering thrombolytic agents directly to the location of occlusion. This motion theoretically bypasses the antagonistic results of systemic hemorrhage at longer time factors, with comparable rates of recanalization. In the four research evaluated in this meta-analysis, the median time to randomization ranged from four. Mechanical Clot Removal Mechanical clot elimination entails using an endovascular clot-breaking or clot-retrieving device that bodily removes the thromboembolus occluding a cerebral artery. When sufferers are carefully chosen on the premise of imaging parameters as an alternative of inflexible time standards, thrombectomy could be secure and effective. These trials were successful largely due to the adaptation of newer techniques for thrombectomy and the development of newer devices that make the process faster and safer. For additional dialogue of mechanical thrombectomy and these latest trials, see Chapter 372. In theory, reasonable hypertension, typically termed permissive hypertension, may improve neurological status and outcomes by allowing elevated perfusion to areas of ischemic brain. In the presence of intracranial hemorrhage, nevertheless, increased blood pressure greater than doubles the chance of subsequent demise or poor practical outcome. Randomized managed trials have been carried out with only some of these sorts of medicine. Antiplatelet Therapy Both aspirin and clopidogrel have been studied within the therapy of acute ischemic stroke and its prevention. Aspirin remedy within 48 hours of ischemic stroke has been proven to have a small however significant benefit with regard to dying and dependency in patients, thought to outcome from the prevention of recurrent occasions. The administration of 325 mg of aspirin within 24 to forty eight hours of stroke onset has been beneficial for many patients by the American Heart Association. However, the relative danger of average to severe bleeding in sufferers who obtained dual antiplatelet therapy was 1. Hypertension in the acute aftermath of stroke might result from many components, including preexisting hypertension, stress, sympathetic activation, and the Cushing reflex. Blood pressure must be measured more incessantly for systolic blood pressures higher than one hundred eighty mm Hg or diastolic blood pressures larger than one hundred and five mm Hg. Blood pressure is often high in sufferers during acute ischemic stroke, and people with a historical past of hypertension are prone to have even greater blood pressures. Temperature Fever has been recognized as an independent predictor of poor outcome in each ischemic and hemorrhagic stroke. A randomized controlled trial with 1400 sufferers demonstrated no difference in useful outcomes with the early administration of acetaminophen after stroke to forestall fever. Large areas of cerebral infarction finally cause massive areas of cytotoxic cerebral edema as cells die. Edema increases intracranial pressure and can lead to herniation and demise, also termed malignant cerebral infarction. Definitive treatment with surgical decompression in these circumstances is clearly supported by proof because it reduces the danger of death. In the case of posterior fossa infarction involving the cerebellum, anecdotal evidence and concept counsel that early resection of the affected cerebellum could enhance consequence, inasmuch as cerebellar edema can lead to brainstem compression. Despite the shortage of research of this intervention, early surgical procedure for decompression ought to be thought-about in instances of posterior fossa stroke. The efficacy and indications for surgical therapy after intracranial hemorrhage have been controversial matters. Ultimately, no long-term end result profit was noticed for early surgery versus medical therapy. Subgroup analyses did demonstrate (1) a good factor about early surgical procedure in patients with intracerebral hemorrhage that occurred superficially within 1 cm of the cortical surface and (2) possible hurt brought on by early surgical procedure in patients with intracerebral hemorrhage in deep structures (such as basal ganglia or internal capsule). There was no distinction between sufferers who underwent early surgical procedure group and individuals who obtained solely medical therapy (59% versus 62%; P =. Despite this, early surgery significantly elevated the likelihood of favorable end result in sufferers with poor prognoses and may be most appropriate for such patients. These research have to be accomplished earlier than extra definitive recommendations may be given. The two main approaches are sometimes considered within the treatment of intracranial hemorrhage have been (1) to cease the supply of bleeding and (2) to remove hematoma to mitigate mass impact and poisonous effects of free radicals from blood breakdown. Apart from these approaches, the important care administration of the issues of intracerebral hemorrhage are the firstline interventions. The intracranial hemorrhage score-calculated from the scale of hemorrhage, age, Glasgow Coma Scale score, location of the hematoma (supratentorial versus infratentorial), and presence of intraventricular hemorrhage-reflects the current knowledge of the danger elements affecting outcomes after intracerebral hemorrhage. Intravenous thrombolysis with recombinant tissue plasminogen activator for acute hemispheric stroke. Heart disease and stroke statistics-2015 update: a report from the American Heart Association. Incidence and 10-year survival of intracerebral hemorrhage in a population-based registry. Temporal tendencies in affected person characteristics and treatment with intravenous thrombolysis among acute ischemic stroke sufferers at Get With the Guidelines-Stroke hospitals. National Institutes of Health Stroke Scale certification is dependable throughout a number of venues. Stroke magnetic resonance imaging is accurate in hyperacute intracerebral hemorrhage: a multicenter research on the validity of stroke imaging. Effects on routine coagulation screens and assessment of anticoagulant depth in sufferers taking oral dabigatran or rivaroxaban: guidance from the British Committee for Standards in Haematology. Thrombolysis (different doses, routes of administration and agents) for acute ischaemic stroke. Ancrod in acute ischemic stroke: outcomes of 500 subjects starting remedy inside 6 hours of stroke onset within the Ancrod Stroke Program. Results of a multicentre, randomised managed trial of intra-arterial urokinase in the treat- 25. Incidence and prognostic significance of fever following intracerebral hemorrhage. Early studies in a macaque mannequin of cerebral ischemia demonstrated that scientific symptoms developed imme diately after vessel occlusion, whereas ischemic mind tissue progressed to infarction only after several hours. Importantly, no knowledge were offered regard ing the size of infarct before intervention, neither is it clear that a proximal occlusion was recognized on presentation. Of observe, this was the first trial performed in the period of stentrievers, with this class of units utilized in eighty one. At ninety days, 53% of the remedy arm had functional independence in contrast with 29. Remarkably, this trial was the primary to reveal improvement in mortality with reperfusion remedy (10. The trial was halted early after enrolling a hundred and forty patients because of important profit within the treat ment arm. The medical benefit persisted at ninety days, as 51% of the therapy arm had functional independence in contrast with 29% of the management arm.
Syndromes
- Radiation therapy
- Kidney failure
- Loss of height
- Diphenhydramine
- Pneumonia
- Allergies and lice that affect the eyelashes (less common)
- Eyes with small (pinpoint) pupils
- Do NOT use decongestants which can dry out the vocal cords.
- Port-wine stains are growths that contain blood vessels (vascular growths). They are red to purplish in color. They are frequently seen on the face, but may occur on any area of the body.
- Other medical instruments will be inserted through the other cuts.
Related Products
Additional information:
It appeared that the atlantoaxial joint in such instances was in an abnormal position medications covered by blue cross blue shield buy prometrium 100 mg on line, and progressive worsening of the dislocation was probably secondary to growing slippage of the sides Clinical Features A majority of basilar invagination patients with sort A atlantoaxial facetal dislocation had a history of minor to major head harm previous the onset of the symptoms symptoms quad strain buy generic prometrium 200 mg online. Symptoms in patients with varieties B and C atlantoaxial facetal dislocation were longstanding and slowly progressive symptoms 7 days after ovulation 100 mg prometrium discount visa. C treatment variance buy prometrium 200 mg low price, Magnetic resonance imaging showing twine compression associated to the odontoid course of. C, T2-weighted magnetic resonance picture showing Chiari malformation and syringomyelia. A, Magnetic resonance image showing basilar invagination, Chiari malformation, and syringomyelia. Precipitating Factors Trauma of varying severity was a noteworthy precipitating think about instances of basilar invagination with sort A circumstances. Short neck and torticollis were extra incessantly encountered in sufferers with varieties B and C dislocation. OmegaAngle Although not frequently used, the omega angle or the angulation of the odontoid process from the vertical as described by Klaus served as a useful guide. The line of the onerous palate was unaffected by the relative motion of the pinnacle and the cervical backbone in the course of the movement of the neck in these "fastened" craniovertebral anomalies. The omega angle was severely reduced in sufferers with kind A atlantoaxial dislocation, whereas it was a lot larger in sufferers with sorts B and C atlantoaxial dislocation. The discount in the omega angle demonstrated that in patients with kind A dislocation the odontoid process had tilted towards the horizontal and was posteriorly angulated. Conversely, odontoid course of was close to vertical and superiorly migrated in sufferers with types B and C atlantoaxial dislocation. We noticed that this scientific grading system is easy and reproducible, and it provided a clear impression of the clinical standing of the patient. OccipitalizationoftheAtlas Occipitalization of the atlas related to basilar invagination was noted first by Rakitansky (cited by Grawitz)36 and has since been referenced regularly. Many authors have regarded assimilation as a attribute function of basilar invagination. The parameter of direct bodily measurement of the neck size from inion to the tip of the C7 spinous course of can additionally be useful. In sufferers with types B and C atlantoaxial dislocation, the relationship of the tip of the odontoid process and the lower end of the clivus and the atlantodental and clival�dental interval remained comparatively normal. Occipitocervical fixation using bone graft and hardware has been associated with satisfactory medical end result. However, the long-term medical outcome following the dual operation of transoral decompression adopted by posterior stabilization was seen to be inferior to the clinical outcome Platybasia A line is drawn alongside the anterior skull base. The technique of craniovertebral realignment by broad elimination of atlantoaxial joint capsule and articular cartilage by drilling and subsequent distraction of the joint by manual manipulation provided a novel opportunity to achieve fixation and to get hold of reduction of the basilar invagination and of atlantoaxial dislocation. The major aim of surgical procedure is atlantoaxial fixation and craniovertebral stabilization. The process of stabilization with our method by itself will lead to craniovertebral realignment, extra significantly in sufferers with sort A atlantoaxial dislocation. In sorts B and C atlantoaxial dislocation, the purpose of surgical procedure is just fixation with no attempts at reducing the basilar invagination. The steps of introduction of bone graft within the joint are necessary in all circumstances. The introduction of spacers inside the joint cavity is necessary when it seems that the spacers will present additional stability to the region. Essentially, spacers are placed to present enhanced stability to the area somewhat than being geared toward lowering the basilar invagination. The exposure of the atlantoaxial joint in cases with basilar invagination is significantly harder and technically challenging compared with a normally aligned atlantoaxial joint encountered in the course of the remedy of posttraumatic instability. The joint is rostral in location, and the microscope needs to be appropriately angled. The difficulty in publicity is significantly more in patients with types B and C dislocation. In all instances of basilar invagination, the atlantoaxial facet joints are broadly uncovered on both sides after sectioning of the massive C2 ganglion. The joint capsule is excised, and the articular cartilage is widely removed utilizing a microdrill. The flat edge of the osteotome is launched into the joint and is then turned vertically to impact distraction. The standing of the dislocation and of basilar invagination is evaluated by intraoperative radiographic management. Corticocancellous bone graft harvested from the iliac crest is stuffed into the joint in small items. Specially designed titanium spacers are used in selected instances as strut graft and impacted into the joints to provide additional distraction and stability. Subsequent fixation of the joint with the help of interarticular screws and a steel plate offered a biomechanically agency fixation and sustained distraction. The fixation was sturdy enough to sustain the vertical, transverse, and rotatory strains of the most cell area of the backbone. The inclusion of such further motion segments can scale back the power of the instrumentation and the last word bone fusion. Postoperatively, the traction is discontinued and the patient is placed in a four-post hard cervical collar for 3 months. All bodily actions involving the neck are restrained during the postoperative interval. Our recent studies suggest that even neural abnormalities, such as Chiari malformation and syringomyelia, are also reversible after surgical procedures that contain stabilization of the atlantoaxial joint. The widespread educating on the subject is that the quick neck and torticollis are a results of embryologic dysgenesis and effectively result in indentation of the odontoid process into the cervicomedullary twine. Pain, restriction of neck movements, and hyperlordosis of the neck point out the presence of instability of the craniovertebral junction. All these natural responses probably allow the wire a relatively stretch-free traversal over the indenting odontoid process. Reduction of the disk areas, osteophyte formation, incomplete and full cervical fusions, and alterations in the craniospinal and cervical angulations appear to be immediately related to the reduction in neck length. The reduction in the disk-space height and fusions are seen extra prominently within the upper cervical vertebrae. It appears that cervical fusions and assimilation of the atlas could additionally be related to longstanding and progressive reduction within the disk-space peak. Atlantoaxial fixation utilizing plate and screw technique: A report of one hundred sixty treated sufferers. Reversal of longstanding musculoskeletal modifications in basilar invagination after surgical decompression and stabilization. These anomalies embrace brief neck, torticollis, platybasia, cervical vertebral physique fusion (Klippel�Feil abnormality) together with assimilation of atlas, spondylotic spinal adjustments, and restriction of neck actions. Treatment of basilar invagination by atlantoaxial joint distraction and direct lateral mass fixation. Lateral atlantoaxial facetal dislocation in craniovertebral area tuberculosis: report of a case and evaluation of an alternative treatment. Atlantoaxial fixation using plate and screw method: a report of 160 handled patients. Biomechanical comparision of two stabilization methods of the atlantoaxial joints: transarticular screw fixation versus screw androd fixation. Die Leitungsbahnen des Schmerzgefuhls und die Chirurgische Behandlung der Schmerzzustande. Posterior C2 fixation utilizing bilateral, crossing C2 laminar screws: case collection and technical notice. Primary posteriorfusions C1-2 in odontoidfractures: indications, technique and results of transarticular screw fixation. Atlantoaxial joint jamming as a remedy for atlantoaxial dislocation: a preliminary report. Primary craniovertebral anomalies and hindbrain herniation syndrome (Chiari I): database analysis. Beitragezurphysischen Anthropologie der Deutschen, mit besonderer Berucksichtigung der Friesen. A bizarre developmental anomaly of the occipital bone and higher cervical spine with striking and misleading neurologic manifestations.
Usage: t.i.d.
Adjacent segment disease after posterior lumbar interbody fusion: primarily based on circumstances with a minimum of 10 years of follow-up new medicine 100 mg prometrium generic free shipping. L5-S1 segment survivorship and clinical outcome evaluation after L4-L5 isolated fusion medications removed by dialysis generic prometrium 200 mg. Four-year follow-up results of lumbar backbone arthrodesis utilizing the Bagby and Kuslich lumbar fusion cage medicine quinidine discount 100 mg prometrium overnight delivery. Risk components for adjacent-segment failure following lumbar fixation with rigid instrumentation for degenerative instability treatment zinc toxicity cheap 200 mg prometrium visa. Lumbar motion section pathology adjacent to thoracolumbar, lumbar, and lumbosacral fusions. Kinematic evaluation of the adjoining segments after lumbar instrumented surgery: a comparison between inflexible fusion and dynamic non-fusion stabilization. Adjacent segment degeneration after lumbar interbody fusion with percutaneous pedicle screw fixation for grownup low-grade isthmic spondylolisthesis: minimal three years of follow-up. Two-level anterior lumbar interbody fusion with percutaneous pedicle screw fixation: a minimal 3-year follow-up research. Post-laminectomy kyphosis in sufferers with cervical ossification of the posterior longitudinal ligament: does it trigger neurological deterioration Spinal deformity and instability after multilevel cervical laminectomy for spondylotic myelopathy. Laminoplasty versus laminectomy and fusion for multilevel cervical myelopathy: an independent matched cohort evaluation. Analysis and prevention of spinal column deformity following cervical laminectomy. Pathogenesis and prophylaxis of postlaminectomy deformity of the backbone after multiple stage laminectomy: difference between kids and adults. A comparison of anterior cervical fusion, cervical laminectomy, and cervical laminoplasty for the surgical administration of a quantity of stage spondylotic radiculopathy. Factors associated with cervical instability requiring fusion after cervical laminectomy for intradural tumor resection. Spinal column deformity and instability after lumbar or thoracolumbar laminectomy for intraspinal tumors in children and young adults. Analysis of cervical instability ensuing from laminectomies for removal of spinal twine tumor. Incidence of spinal column deformity after multilevel laminectomy in children and adults. Long-term consequence of laminectomy for cervical ossification of the posterior longitudinal ligament. Cervical alignment and range of motion after laminoplasty: radiographical data from greater than 500 instances with cervical spondylotic myelopathy and a review of the literature. Techniques for the ventral correction of postsurgical cervical kyphotic deformity. Deformity planning for sagittal plane corrective osteotomies of the spine in ankylosing spondylitis. Anterior cervical corpectomy in sufferers previously managed with a laminectomy: short-term problems. Results of surgical therapy for degenerative cervical myelopathy: anterior cervical corpectomy and stabilization. Biomechanical comparability of cervical backbone reconstructive techniques after a multilevel corpectomy of the cervical backbone. Anterior cervical fixation: analysis of load-sharing and stability with use of static and dynamic plates. An outcomes analysis of the remedy of cervical pseudarthrosis with posterior fusion. The efficacy of anterior cervical plating in the administration of symptomatic pseudoarthrosis of the cervical backbone. Treatment of anterior cervical pseudoarthrosis: posterior fusion versus anterior revision. A meta-analysis of the scientific and fusion results following therapy of symptomatic cervical pseudarthrosis. Risk components for dysphagia after anterior cervical backbone surgical procedure: a two-year potential cohort examine. Preoperative laryngeal nerve screening for revision anterior cervical spine procedures. Translaminar versus pedicle screw fixation of C2: comparability of surgical morbidity and accuracy of 313 consecutive screws. Seven years of experience with C2 translaminar screw fixation: medical collection and review of the literature. Biomechanical comparison of transpedicular versus intralaminar C2 fixation in C2-C6 subaxial constructs. Prospective research of surgical remedy of degenerative spondylolisthesis: comparability between decompression alone and decompression with Graf system stabilization. Minimum 10-year end result of decompressive laminectomy for degenerative lumbar spinal stenosis. Clinical outcomes and radiological instability following decompressive lumbar laminectomy for degenerative spinal stenosis: a comparison of sufferers undergoing concomitant arthrodesis versus decompression alone. A radiographic evaluation of the flexibility of the extreme lateral interbody fusion procedure to indirectly decompress the neural parts. Indirect foraminal decompression is impartial of metabolically energetic side arthropathy in excessive lateral interbody fusion. Unilateral versus bilateral percutaneous pedicle screw fixation in minimally invasive transforaminal lumbar interbody fusion. Dorsal lumbar interbody fusion for continual axial, mechanical low again pain: a modification of two established strategies. Clinical outcomes after lumbar discectomy for sciatica: the effects of fragment kind and anular competence. Long-term outcomes of standard discectomy for lumbar disc herniation: a follow-up study of more than 10 years. Results and danger components for recurrence following single-level tubular lumbar microdiscectomy. A 10-year follow-up examine on long-term scientific outcomes of lumbar microendoscopic discectomy. Long-term outcomes of disc excision for recurrent lumbar disc herniation with or with out posterolateral fusion. Posterior lumbar interbody fusion for revision disc surgical procedure: evaluation of 50 circumstances in which carbon fiber cages were implanted. Clinical outcomes of a single central interbody fusion cage and transpedicle screws fixation for recurrent herniated lumbar disc and low-grade spondylolisthesis. Association between peridural scar and recurrent radicular pain after lumbar discectomy: magnetic resonance evaluation. Treatment of the failed again surgery syndrome as a outcome of lumbo-sacral epidural fibrosis. Minimally invasive lateral interbody fusion for the therapy of rostral adjacent-segment lumbar degenerative stenosis without supplemental pedicle screw fixation. Minimally invasive lateral transpsoas interbody fusion utilizing a stand-alone construct for the remedy of adjoining section disease of the lumbar backbone: evaluate of the literature and report of three instances. Two column lesions within the thoracolumbar junction: anterior, posterior or combined approach Proximal junctional kyphosis in adult spinal deformity after segmental posterior spinal instrumentation and fusion: minimal five-year follow-up. Proximal junctional kyphosis as a distinct type of adjacent section pathology after spinal deformity surgery: a scientific evaluate. Proximal junctional kyphosis in adolescent idiopathic scoliosis after three different varieties of posterior segmental spinal instrumentation and fusions: incidence and risk factor analysis of 410 circumstances. Risk components and outcomes for catastrophic failures at the prime of lengthy pedicle screw constructs: a matched cohort analysis performed at a single center. Proximal junctional kyphosis and failure after spinal deformity surgical procedure: a systematic evaluation of the literature as a background to classification development. Reproducibility measuring the angle of proximal junctional kyphosis using the primary or the second vertebra above the upper instrumented vertebrae in sufferers surgically treated for scoliosis. Proximal junctional acute collapse cranial to multilevel lumbar fusion: a value evaluation of prophylactic vertebral augmentation. Incidence and danger elements for proximal and distal junctional kyphosis following surgical remedy for Scheuermann kyphosis: minimum five-year follow-up.
Tags: purchase 100 mg prometrium with visa, cheap prometrium 200 mg overnight delivery, cheap prometrium 200 mg amex, 100 mg prometrium cheap otc, prometrium 200 mg generic overnight delivery, discount prometrium 100 mg without a prescription, buy 200 mg prometrium with visa, prometrium 200 mg quality, prometrium 200 mg buy online, discount 200 mg prometrium with mastercard, generic prometrium 100 mg free shipping, 100 mg prometrium free shipping, purchase prometrium 200 mg on-line, generic 200 mg prometrium mastercard, purchase prometrium 200 mg overnight delivery, 200 mg prometrium generic overnight delivery
9 of 10
Votes: 106 votes
Total customer reviews: 106
Customer Reviews
Orknarok, 55 years: C, Illustration of dural closure that incorporates a beneficiant dural patch to allow outward herniation of the mind. Treatment of chronic thoracic spinal wire injury patients with autologous Schwann cell transplantation: an interim report on safety concerns and potential outcomes.
Rufus, 47 years: The two main approaches are sometimes considered within the therapy of intracranial hemorrhage have been (1) to cease the source of bleeding and (2) to take away hematoma to mitigate mass effect and poisonous effects of free radicals from blood breakdown. The program could be started when the athlete is asymptomatic at relaxation; within the event that postconcussion signs occur at any step, another 24-hour period of relaxation is completed, and the athlete drops again to the previous step in this system.
Yorik, 23 years: However, evidence exists for an affiliation between the presence of the apoE four allele with poorer functional restoration. Admission to hospital following head injury in England: incidence and socio-economic associations.
Zarkos, 29 years: Dynamic stabilization for degenerative spondylolisthesis and lumbar spinal instability. These talents proved essential as a outcome of the many surgical strategies and bracing units created in subsequent years could probably be objectively compared.
Lukar, 30 years: Transporters for l-glutamate: an update on their molecular pharmacology and pathological involvement. In the setting of aspiration, the physiologic response is reflex coughing, however aspiration is silent in up to 60% of neurological patients.
Lares, 65 years: The idea that every habits or cognitive operate is carried out by one brain area or construction is now considered outdated. Xenon does have the potential to trigger complications, nausea, convulsions, respiratory depression, and narcosis, however normally not until the concentration in inhaled air approaches 80%, which is way larger than the method requires.
