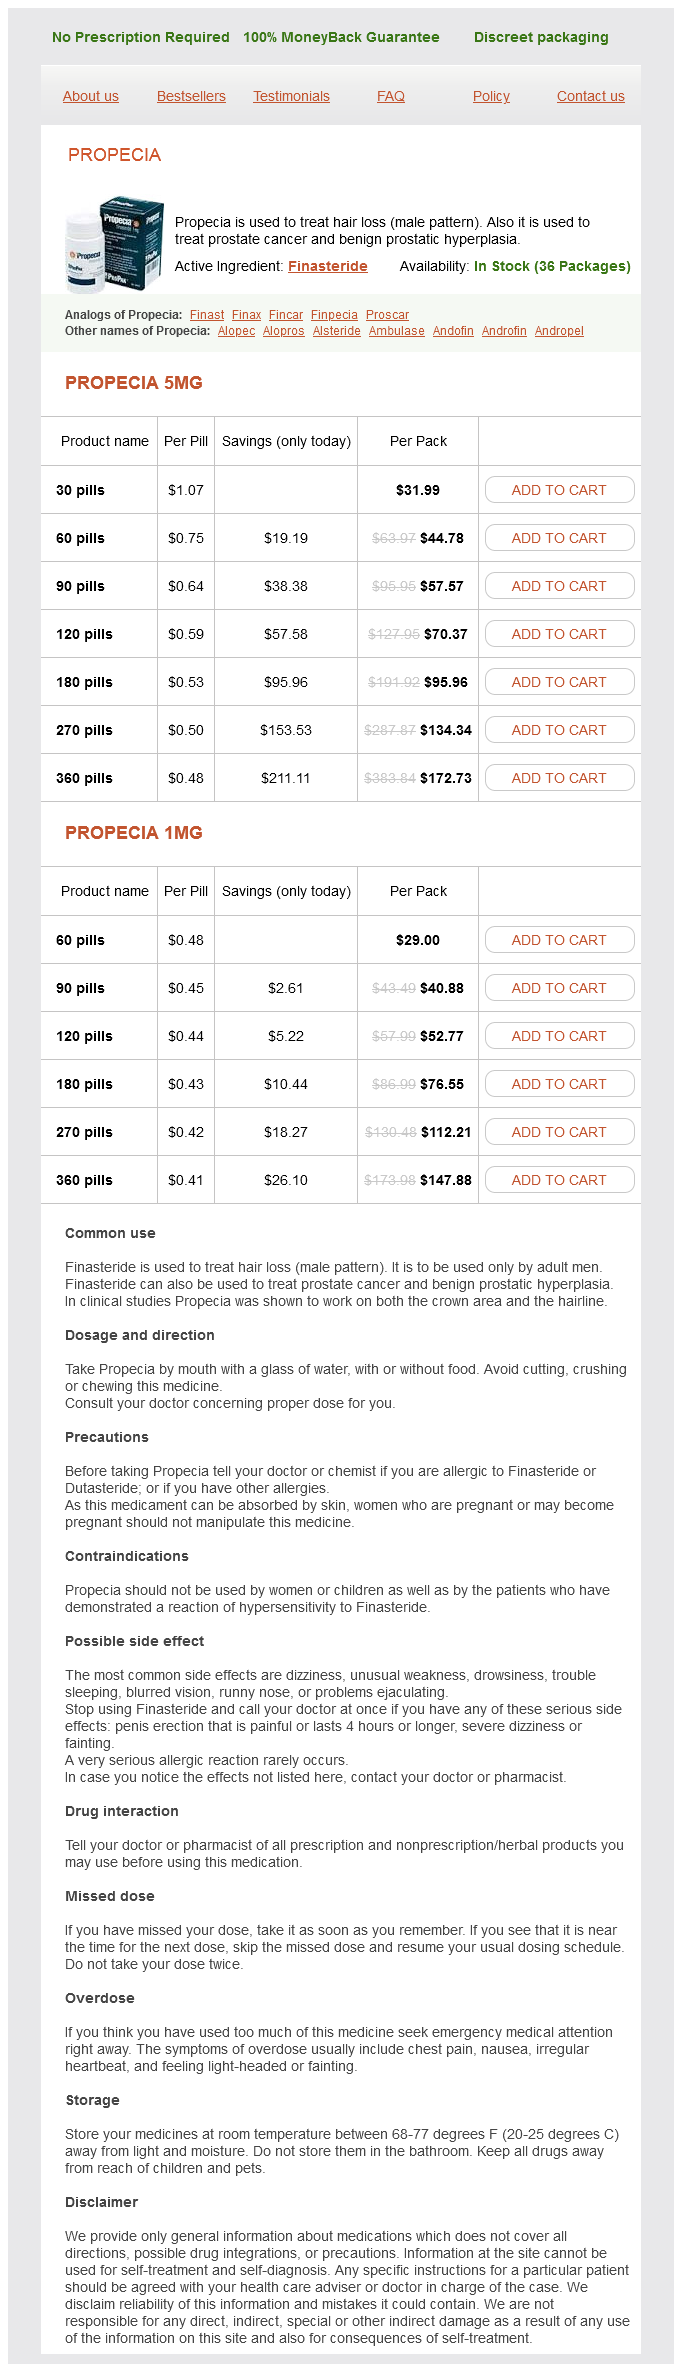
Propecia 5mg
- 30 pills - $31.99
- 60 pills - $44.78
- 90 pills - $57.57
- 120 pills - $70.37
- 180 pills - $95.96
- 270 pills - $134.34
- 360 pills - $172.73
Propecia 1mg
- 60 pills - $29.00
- 90 pills - $40.88
- 120 pills - $52.77
- 180 pills - $76.55
- 270 pills - $112.21
- 360 pills - $147.88
Propecia dosages: 5 mg, 1 mg
Propecia packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 805
Only $0,44 per item
Description
Note the convolutions of the small intestine in situ hair loss in men exercise buy propecia 1 mg mastercard, encircled on three sides by the large intestine and revealed by elevating the greater omentum hair loss epilepsy medication 1 mg propecia discount mastercard. The convolutions of the small intestine have been retracted superiorly to show the mesentery hair loss gastric bypass propecia 1 mg generic. This orientation drawing of the alimentary system indicates the general place and relationships of the intestines hair loss 6 months post partum propecia 1 mg purchase visa. It begins on the pylorus on the right aspect and ends on the duodenojejunal flexure (junction) on the left side. This junction occurs roughly on the stage of the L2 vertebra, 2�3 cm to the left of the midline. The junction often takes the form of an acute angle, the duodenojejunal flexure. Most of the duodenum is mounted by peritoneum to structures on the posterior abdominal wall and is taken into account partially retroperitoneal. The duodenum, pancreas, and spleen and their blood provide are revealed by elimination of the stomach, transverse colon, and peritoneum. The belly aorta and inferior vena cava occupy the vertical concavity posterior to the pinnacle of the pancreas and third a part of the duodenum. The uncinate process is the extension of the top of the pancreas that passes posterior to the superior mesenteric vessels. The bile duct is descending in a fissure (opened up) in the posterior part of the head of the pancreas. Superior (first) part: quick (approximately 5 cm) and lies anterolateral to the body of the L1 vertebra. Descending (second) half: longer (7�10 cm) and descends along the proper 1094 sides of the L1�L3 vertebrae. Ascending (fourth) part: brief (5 cm) and begins on the left of the L3 vertebra and rises superiorly so far as the superior border of the L2 vertebra. The first 2 cm of the superior part of the duodenum, instantly distal to the pylorus, has a mesentery and is cell. This free part, known as the ampulla (duodenal cap), has an look distinct from the remainder of the duodenum when observed radiographically utilizing distinction medium. The superior a half of the duodenum ascends from the pylorus and is overlapped by the liver and gallbladder. The proximal half has the hepatoduodenal ligament (part of the lesser omentum) connected superiorly and the greater omentum hooked up inferiorly. The descending part of the duodenum runs inferiorly, curving around the head of the pancreas. These ducts often unite to form the hepatopancreatic ampulla, which opens on an eminence, referred to as the major duodenal papilla, situated posteromedially in the descending duodenum. The anterior floor of its proximal and distal thirds is covered with peritoneum; however, the peritoneum displays from its middle third to form the double-layered mesentery of the transverse colon, the transverse mesocolon. It is crossed by the superior mesenteric artery and vein and the foundation of the mesentery of the jejunum and ileum. The ascending a half of the duodenum runs superiorly and along the left facet of the aorta to reach the inferior border of the body of the pancreas. Here it 1095 curves anteriorly to be a part of the jejunum on the duodenojejunal flexure, supported by the attachment of a suspensory muscle of the duodenum (ligament of Treitz). This muscle is composed of a slip of skeletal muscle from the diaphragm and a fibromuscular band of smooth muscle from the third and fourth parts of the duodenum. Contraction of this muscle widens the angle of the duodenojejunal flexure, facilitating motion of the intestinal contents. The suspensory muscle passes posterior to the pancreas and splenic vein and anterior to the left renal vein. The arteries of the duodenum come up from the celiac trunk and the superior mesenteric artery. The celiac trunk, through the gastroduodenal artery and its branch, the superior pancreaticoduodenal artery, provides the duodenum proximal to the entry of the bile duct into the descending part of the duodenum. The superior mesenteric artery, through its branch, the inferior pancreaticoduodenal artery, provides the duodenum distal to the entry of the bile duct. The pancreaticoduodenal arteries lie in the curve between the duodenum and the top of the pancreas and provide each constructions. The foundation of this transition in blood supply is embryological; that is the junction of the foregut and midgut. The veins of the duodenum observe the arteries and drain into the hepatic portal vein, some instantly and others indirectly, by way of the superior mesenteric and splenic veins. The anterior lymphatic vessels drain into the pancreaticoduodenal lymph nodes, positioned alongside the superior and inferior pancreaticoduodenal arteries, and into the pyloric lymph nodes, which lie along the gastroduodenal artery. The posterior lymphatic vessels pass posterior to the top of the pancreas and drain into the superior mesenteric lymph nodes. Efferent lymphatic vessels from the duodenal lymph nodes drain into the celiac lymph nodes. The close positional relationship of these organs leads to sharing of blood vessels, lymphatic vessels, and nerve pathways, in entire or in part. The nerves of the duodenum derive from the vagus and larger and lesser (abdominopelvic) splanchnic nerves by the use of the celiac and superior mesenteric plexuses. The nerves are subsequent conveyed to the duodenum by way of periarterial plexuses extending to the pancreaticoduodenal arteries (see also "Summary of the Innervation of Abdominal Viscera," p. The third part of the small gut, the ileum, ends on the ileocecal junction, the union of the terminal ileum and the cecum. Together, the jejunum and ileum are 6�7 m lengthy, the jejunum constituting roughly two fifths and the ileum roughly three fifths of the intraperitoneal section of the small gut. The terminal ileum normally lies within the pelvis from which it ascends, ending within the medial facet of the cecum. Structure of the mesentery and small intestine: distinctive options of the jejunum and ileum. The mesentery is a double-layered fold of visceral peritoneum that suspends the gut and conducts neurovasculature from the posterior physique wall. The mesentery is a fan-shaped fold of peritoneum that attaches the jejunum and ileum to the posterior stomach wall. The origin or root of the mesentery (approximately 15 cm long) is directed obliquely, inferiorly, and to the best. It extends from the duodenojejunal junction on the left aspect of vertebra L2 to the ileocolic junction and the proper sacro-iliac joint. The common size of the mesentery from its root to the intestinal border is 20 cm. Between the 2 layers of the mesentery are the superior mesenteric vessels, lymph nodes, a variable quantity of fat, and autonomic nerves. The transverse and sigmoid mesocolons and the mesentery of the jejunum and ileum 1101 have been minimize at their roots. The ileocolic and proper colic arteries on the right aspect and the left colic and sigmoid arteries on the left facet originally coursed within mesenteries (ascending and descending mesocolons) that later fused to the posterior wall; they are often re-established surgically. The arteries unite to kind loops or arches, referred to as arterial arcades, which give rise to straight arteries, called vasa recta. Specialized lymphatic vessels within the intestinal villi (tiny projections of the mucous membrane) that absorb fats are known as lacteals. They empty their milklike fluid into the lymphatic plexuses in the walls of the jejunum and ileum. The lacteals drain in flip into lymphatic vessels between the layers of the mesentery. Within the mesentery, the lymph passes sequentially through three groups of lymph nodes. The superior nodes type a system in which the central nodes, on the root of the superior mesenteric artery, obtain lymph from the mesenteric, ileocolic, proper colic, and center colic nodes, which in turn receive lymph from juxta-intestinal lymph nodes. Efferent lymphatic vessels from the mesenteric lymph nodes drain to the 1103 superior mesenteric lymph nodes. Lymphatic vessels from the terminal ileum follow the ileal department of the ileocolic artery to the ileocolic lymph nodes. The sympathetic fibers in the nerves to the jejunum and ileum originate within the T8�T10 segments of the spinal twine and attain the superior mesenteric nerve plexus by way of the sympathetic trunks and thoracic abdominopelvic (greater, lesser, and least) splanchnic nerves.
Citrus Peel extract (Grapefruit). Propecia.
- Are there any interactions with medications?
- Asthma, lowering cholesterol, hardening of the arteries (atherosclerosis), preventing cancer, weight loss, psoriasis, muscle fatigue, promoting hair growth, toning the skin, reducing acne and oily skin, treating headaches, stress, depression, infections, digestive complaints in people with eczema, yeast infections (as a vaginal douche), and other conditions.
- How does Grapefruit work?
- Dosing considerations for Grapefruit.
- What is Grapefruit?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96909
The resilience of the cranial bones of infants allows them to resist forces that might produce fractures in adults hair loss 6mp cheap propecia 1 mg free shipping. The fibrous sutures of the calvaria additionally permit the cranium to enlarge throughout infancy and childhood hair loss in men lh 5 mg propecia buy visa. The enhance within the measurement of the calvaria is biggest during the first 2 years hair loss in menopause symptoms propecia 1 mg on line, the period of most fast brain improvement hair loss joan rivers cheap propecia 1 mg on-line. After this, the calvaria usually will increase slightly in measurement for 3�4 years because of bone thickening. Age Changes in Face the mandible is probably the most dynamic of our bones; its measurement and form and the number of tooth it usually bears undergo appreciable change with age. In the neonate, the mandible consists of two halves united within the median airplane by a cartilaginous joint, the mandibular symphysis. This union begins in the course of the 1st year, and the halves are fused by the tip of the 2nd year. The body of the mandible in neonates is a mere shell missing an alveolar part with every half enclosing 5 deciduous tooth. The body of the mandible elongates, 1914 particularly posterior to the psychological foramen. Rapid development of the face during infancy and early childhood coincides with the eruption of deciduous tooth. Vertical development of the upper face results mainly from dento-alveolar development of alveolar bone. Concurrent enlargement of the frontal and facial regions is related to the increase within the dimension of the paranasal sinuses, the air-filled extensions of the nasal cavities in sure cranial bones. Growth of the paranasal sinuses is necessary in altering the shape of the face and in adding resonance to the voice. Obliteration of Cranial Sutures the obliteration of sutures between the bones of the calvaria often begins between the ages of 30 and forty years on the internal floor. Obliteration of sutures usually begins at the bregma and continues sequentially in the sagittal, coronal, and lambdoid sutures. Age Changes in Cranium As folks age, the cranial bones usually turn out to be progressively thinner and lighter, and the diplo� gradually becomes crammed with a grey gelatinous material. In these people, the bone marrow has lost its blood cells and fat, giving it a gelatinous look. Craniosynostosis Malformations 1917 and Cranial Premature closure of the cranial sutures (primary craniosynostosis) ends in a number of cranial malformations. The incidence of major craniosynostosis is roughly 1 per 2,000 births (Kliegman et al. The explanation for craniosynostosis is unknown, however genetic elements appear to be important. The prevailing hypothesis is that abnormal improvement of the cranial base creates exaggerated forces on the dura mater (outer masking membrane of the brain) that disrupt normal cranial sutural improvement. These malformations are more widespread in males than in females and are sometimes related to different skeletal anomalies. The kind of malformed cranium that varieties depends on which sutures shut prematurely. Premature closure of the sagittal suture, by which the anterior fontanelle is small or absent, ends in a protracted, narrow, wedge-shaped cranium, a condition called scaphocephaly. When premature closure of the coronal or the lambdoid suture happens on one aspect only, the skull is twisted and asymmetrical, a condition often identified as plagiocephaly. Premature closure of the coronal suture results in a high, tower-like skull, called 1919 oxycephaly or turricephaly. Relatively thin (but mostly curved) flat bones provide the necessary power to preserve cavities and defend contents. Internal features of the cranial base mirror the major formations of the mind that rest on it. Thus, delivery defects, scarring, or different alterations ensuing from pathology or trauma have marked consequences past their physical results. The individuality of the face outcomes primarily from anatomical variations within the shape and relative prominence of the features of the underlying cranium; in the deposition of fatty tissue; in the shade and results of getting older on the overlying pores and skin; and within the abundance, nature, and placement of hair on the face and scalp. The comparatively massive dimension of the buccal fat-pads in infants prevents collapse of the cheeks throughout sucking and produces their chubby-cheeked appearance. The ethmoid bone, orbital cavities, and superior parts of the nasal cavities have practically accomplished their growth by the seventh year. Expansion of the orbits and growth of the nasal septum carry the maxillae infero-anteriorly. Considerable facial progress happens during childhood as the paranasal sinuses develop and everlasting teeth erupt. Our interactions with others happen largely through the face (including the ears) and thus the time period interface for a web site of interactions. Whereas the form and options of the face present our id, much of our effect on others and their perceptions about us end result from the way we use facial muscular tissues to make the slight alterations in the options that represent facial expression. Scalp the scalp consists of skin (normally hair bearing) and subcutaneous tissue that cowl the neurocranium from the superior nuchal traces on the occipital bone to the supra-orbital margins of the frontal bone. The scalp is composed of five layers, the first three of which are related intimately and transfer as a unit. The pores and skin is certain tightly to the epicranial aponeurosis, which moves freely over the pericranium and skull because of the intervening loose connective tissue. Aponeurosis refers to the epicranial aponeurosis, the flat intermediate tendon of the occipitofrontalis muscle. Innervation of the two bellies by the posterior auricular and temporal branches of the facial nerve is demonstrated. Skin: thin, besides within the occipital region, incorporates many sweat and sebaceous glands and hair follicles. Aponeurosis (epicranial aponeurosis): the broad, sturdy, tendinous sheet that covers the calvaria and serves as the attachment for muscle bellies converging from the brow and occiput (occipitofrontalis muscle). The frontal belly of the occipitofrontalis pulls the scalp anteriorly, wrinkles the brow, and elevates the eyebrows. The occipital belly of the occipitofrontalis pulls the scalp posteriorly, smoothing the skin of the forehead. The superior auricular muscle (a specialised posterior part of the temporoparietalis) elevates the auricle of the external ear. All elements of the epicranius (muscle and aponeurosis) are innervated by the facial nerve. Loose areolar tissue: a sponge-like layer including potential spaces that may distend with fluid as a outcome of harm or an infection. This layer permits free movement of the scalp proper (the first three layers-skin, connective tissue, and epicranial aponeurosis) over the underlying calvaria. Pericranium: a dense layer of connective tissue that forms the external periosteum of the neurocranium. It is firmly connected but can be stripped from the crania of dwelling individuals, besides where the pericranium is steady with the fibrous tissue within the cranial sutures. Muscles of Face and Scalp the facial muscle tissue (muscles of facial expression) are in the subcutaneous tissue of the anterior and posterior scalp, face, and neck. Most muscles connect to bone or fascia and produce their results by pulling the pores and skin. All muscle tissue of facial expression develop from mesoderm in the second pharyngeal arches. The muscular sheet differentiates into muscle tissue that surround the facial orifices (mouth, eyes, and nose), serving as sphincter and dilator mechanisms that additionally produce many facial expressions. Because of their widespread embryological origin, the platysma and facial muscles are sometimes fused, and their fibers are frequently intermingled. These muscles are superficial sphincters and dilators of the orifices of the pinnacle. Because the aponeurosis is a layer of the scalp, independent contraction of the occipital stomach retracts the scalp and contraction 1927 of the frontal stomach protracts it. Acting concurrently, the occipital stomach, with bony attachments, works as a synergist with the frontal belly, which has no bony attachments, to elevate the eyebrows and produce transverse wrinkles across the brow.
Specifications/Details
However hair loss with menopause buy 5 mg propecia visa, the transverse colon may obtain arterial blood from the right and left colic arteries via anastomoses hair loss cure close buy propecia 1 mg with mastercard, part of the collection of anastomotic arcades that collectively form the marginal artery (of Drummond hair loss cure 7 jours propecia 1 mg buy cheap on-line, juxtacolic artery) hair loss restoration 5 mg propecia discount mastercard. The lymphatic drainage of the transverse colon is to the center colic lymph nodes, which in turn drain to the superior mesenteric lymph nodes. These nerves transmit sympathetic, parasympathetic (vagal), and visceral afferent nerve fibers (see also "Summary of Innervation of Abdominal Viscera," p. As it descends, the colon passes anterior to the lateral border of the left kidney. As with the ascending colon, the descending colon has a paracolic gutter (the left one) on its lateral aspect. The sigmoid colon, characterized by its S-shaped loop of variable length, hyperlinks the descending colon and the rectum. The sigmoid colon extends from the iliac fossa to the third sacral (S3) vertebra, where it joins the rectum. The termination of the teniae coli, approximately 15 cm from the anus, signifies the rectosigmoid junction. The sigmoid colon often has an extended mesentery-the sigmoid mesocolon- and due to this fact has considerable freedom of movement, particularly its middle half (see the Clinical Box "Volvulus of Sigmoid Colon," p. The root of the sigmoid mesocolon has an inverted V-shaped attachment, extending first medially and superiorly alongside the exterior iliac vessels and then medially and inferiorly from the bifurcation of the frequent iliac vessels to the anterior side of the sacrum. The left ureter and the division of the left common iliac artery lie retroperitoneally, posterior to the apex of the foundation of the sigmoid mesocolon. The teniae coli additionally disappear because the longitudinal muscle in the wall of the colon broadens to kind a whole layer in the rectum. The arterial supply of the descending and sigmoid colon is from the left colic and sigmoid arteries, branches of the inferior mesenteric artery. The sigmoid arteries descend obliquely to the left, where they divide into ascending and descending branches. The superior branch of the most superior sigmoid artery anastomoses with the descending department of the left colic artery, thereby forming a part of the marginal artery. Venous drainage from the descending colon and sigmoid colon is offered by the inferior mesenteric vein, flowing usually into the splenic vein after which the hepatic portal vein on its method to the liver. Lymphatic drainage from the descending colon and sigmoid colon is carried out via vessels passing to the epicolic and paracolic nodes after which via the intermediate colic lymph nodes along the left colic artery. However, lymph from the left colic flexure can also drain to the superior mesenteric lymph nodes. Orad (toward the mouth, or proximal) to the left colic flexure, sympathetic and parasympathetic fibers journey collectively from the abdominal aortic plexus through peri-arterial plexuses to attain the stomach part of the alimentary tract. The sympathetic nerve provide of the descending and sigmoid colon is from the lumbar part of the sympathetic trunk by way of lumbar (abdominopelvic) splanchnic nerves, the superior mesenteric plexus, and the peri-arterial plexuses following the inferior mesenteric artery and its branches. The parasympathetic nerve supply is from the pelvic splanchnic nerves through the inferior hypogastric (pelvic) plexus and nerves, which ascend retroperitoneally from the plexus, largely impartial of the arterial provide to this part of the gastrointestinal tract. Orad to the center of the sigmoid colon, visceral afferents conveying pain sensation move retrogradely with sympathetic fibers to thoracolumbar spinal sensory ganglia, whereas these carrying reflex info travel with the parasympathetic fibers to vagal sensory ganglia. Aborad to the middle of the sigmoid colon, all visceral afferents follow the parasympathetic fibers retrogradely to the sensory ganglia of spinal nerves S2�S4 (see also "Summary of Innervation of Abdominal Viscera," p. These components of the massive intestine are described with the pelvis in Chapter 6, Pelvis and Perineum. In portal hypertension (an abnormally increased blood pressure within the portal venous system), blood is unable to pass by way of the liver by way of the hepatic portal vein, inflicting a reversal of move in the esophageal tributary. The giant quantity of blood causes the submucosal veins to enlarge markedly, forming esophageal varices. As indicated by its common name, heartburn, pyrosis is commonly perceived as a "chest" (vs. Bariatric Surgery Bariatric surgical procedure is carried out on morbidly overweight people to achieve weight reduction. It contains a variety of approaches aimed toward reducing abdomen volume (restrictive procedures), lowering nutrient absorptive space (malabsorptive procedures), or a combination of the 2 (mixed procedures), many of which may be performed laparoscopically. Restrictive procedures include the appliance of mounted or adjustable bands externally to the stomach (banding), resectioning of the stomach making a small pouch or tubular "sleeve," or 1120 folding of the abdomen onto itself (fundoplication). Malabsorptive procedures contain rerouting of the connection of the stomach with the small intestine and/or of variable parts of the small intestine. Mixed procedures embody gastric bypass surgery, once the commonest bariatric process but declining markedly in frequency. In addition to reaching important weight loss, the procedures have reduced particularly diabetes but also other comorbidities together with malabsorption syndrome and sleep apnea. Strict postsurgical adherence to healthy consuming habits is a vital factor in the success of bariatric surgery. Displacement of Stomach Pancreatic pseudocysts and abscesses within the omental bursa could push the stomach anteriorly. Following pancreatitis (inflammation of the pancreas), the posterior wall of the stomach may adhere to the a half of the posterior wall of the omental bursa that covers the pancreas. This adhesion happens due to the close relationship of the posterior wall of the stomach to the pancreas. Hiatal Hernia A hiatal (hiatus) hernia is a protrusion of part of the stomach into the mediastinum via the esophageal hiatus of the diaphragm. The hernias happen most often in people after center age, possibly because of weakening of the muscular part of the diaphragm and widening of the esophageal hiatus. Although clinically there are a number of kinds of hiatal hernia, the 2 main varieties are paraesophageal hiatal hernia and sliding hiatal hernia (Skandalakis et al. However, a pouch of peritoneum, typically containing part of the fundus of the abdomen, extends through the esophageal hiatus anterior to the esophagus. In these cases, often no regurgitation of 1121 gastric contents occurs as a outcome of the cardial orifice is in its regular position. In the widespread sliding hiatal hernia, the abdominal part of the esophagus, the cardia, and elements of the fundus of the abdomen slide superiorly by way of the esophageal hiatus into the thorax, especially when the particular person lies down or bends over. Some regurgitation of abdomen contents into the esophagus is possible because the clamping action of the best crus of the diaphragm on the inferior finish of the esophagus (the lower "esophageal sphincter") is weak. Pylorospasm Spasmodic contraction of the pylorus sometimes happens in infants, normally between 2 and 12 weeks of age. Pylorospasm is characterised by failure of the graceful muscle fibers encircling the pyloric canal to relax normally. Congenital Hypertrophic Pyloric Stenosis Congenital hypertrophic pyloric stenosis is a marked thickening of the graceful muscle (hypertrophy) in the pylorus that affects roughly 1 of each one hundred fifty male infants and 1 of each 750 feminine infants (Moore, Persaud, and Torchia, 2016). Normally, gastric peristalsis pushes chyme via the pyloric canal and orifice into the small gut at irregular intervals. Proximally, the abdomen may turn into secondarily dilated due to the pyloric stenosis (narrowing). Pyloric stenosis could be handled by a simple operation, pyloromyotomy, by which the surgeon cuts through the hypertrophied round muscle layer of the pylorus, allowing free passage. Carcinoma of Stomach When the body or pyloric part of the stomach contains a malignant tumor, the mass could also be palpable. Using a gastroscope, physicians can inspect the mucosa of the air-inflated abdomen, enabling them to observe gastric lesions and take biopsies. The in depth lymphatic drainage of the stomach and the impossibility of eradicating all of the lymph nodes create a surgical downside. The nodes along the splenic vessels can be excised by eradicating the spleen, gastrosplenic and splenorenal ligaments, and the body and tail of the pancreas. Involved nodes along the gastro-omental vessels could be eliminated by resecting the greater omentum; however, removal of the aortic and celiac nodes and those around the head of the pancreas is troublesome. Gastrectomy and Lymph Node Resection Total gastrectomy (removal of the complete stomach) is unusual. Partial gastrectomy (removal of a half of the stomach) could also be carried out to take away a area of the stomach concerned by a carcinoma, for instance. Because the anastomoses of the arteries supplying the stomach provide good collateral circulation, one or more arteries could also be ligated throughout this procedure without significantly affecting the blood supply to the a part of the stomach remaining in place. When eradicating the pyloric antrum, for example, the higher omentum is incised parallel and inferior to the right gastro-omental artery, requiring ligation of all the omental branches of this artery. Partial gastrectomy to remove a carcinoma usually additionally requires elimination of all involved regional lymph nodes. Because cancer incessantly occurs in the pyloric region, removal of the pyloric lymph nodes in addition to the best gastro-omental 1125 lymph nodes additionally receiving lymph drainage from this region is very important.
Syndromes
- Pain
- Acute respiratory distress syndrome (ARDS)
- Constipation
- Intermittent claudication
- Other congenital problems
- Mouth
- Eyelid myotonia (a condition in which after opening and closing the eyes, the patient cannot open them for a short time)
- Nausea and vomiting
- Changes in consciousness
- Swollen lining of the eyes (chemosis)
Related Products
Additional information:
Several components of the gastrointestinal tract and associated organs turn into secondarily retroperitoneal hair loss cure kennel 1 mg propecia for sale. Some of the information regarding hair loss and stress 5 mg propecia cheap fast delivery this include the next: the peritoneal cavity houses a great length of intestine hair loss cure natural cheap propecia 5 mg online, most of which is roofed with peritoneum hair loss menopause 1 mg propecia generic with visa. Extensive continuities are required between the parietal and visceral peritoneum to convey the required neurovascular constructions from the physique wall to the viscera. Various phrases are used to describe the parts of the peritoneum that connect organs with other organs, or to the abdominal wall, and the compartments and recesses which would possibly be fashioned as a consequence. A mesentery is a double layer of peritoneum that occurs because of the invagination of the peritoneum by an organ and constitutes a continuity of the visceral and parietal peritoneum. It provides a method for neurovascular communications between the organ and the body wall. In this opened peritoneal cavity, components of the larger omentum, transverse colon, and the small intestine and its mesentery have been minimize away to reveal deep constructions and the layers of the mesenteric constructions. The mesentery of the jejunum and ileum (small intestine) and sigmoid mesocolon have been minimize near their parietal attachments. This median section of the abdominopelvic cavity of a male exhibits the relationships of the peritoneal attachments. The higher omentum is proven in its "normal" place, overlaying most of the belly viscera. The larger omentum has been faraway from the greater curvature of the stomach and transverse colon to reveal the intestines. The greater omentum has been mirrored superiorly, and the small intestine has been retracted to the right side to reveal the mesentery of the small gut and the transverse mesocolon. The small intestine mesentery is usually referred to simply as "the mesentery"; nonetheless, mesenteries associated to different specific components of the alimentary tract are named accordingly-for example, the transverse and sigmoid mesocolons. Mesenteries have a core of connective tissue containing blood and lymphatic vessels, nerves, lymph nodes, and fats. An omentum is a double-layered extension or fold of peritoneum that passes from the abdomen and proximal part of the duodenum to adjacent organs in the belly cavity. The higher omentum is a distinguished, four-layered peritoneal fold that hangs down like an apron from the greater curvature of the stomach and the proximal part of the duodenum. After descending, it folds again and attaches to the anterior floor of the transverse colon and its mesentery. The lesser omentum is a a lot smaller, double-layered peritoneal fold that connects the lesser curvature of the stomach and the proximal a half of the duodenum to the liver. It additionally connects the stomach to a triad of buildings that run between the duodenum and liver in the free edge of the lesser omentum. A peritoneal ligament consists of a double layer of peritoneum that connects an organ with one other organ or to the abdominal wall. The central a part of the greater omentum has been reduce out to show its relation to the transverse colon and mesocolon. The time period higher omentum is usually used as a synonym for the gastrocolic ligament, but it truly additionally contains the gastrosplenic and gastrophrenic ligaments, all of which have a continuous attachment to the larger curvature of the stomach. The hepatoduodenal ligament (free fringe of lesser omentum) conveys the portal triad: hepatic artery, bile duct, and portal vein. The hepatogastric and hepatoduodenal ligaments are steady elements of the 1053 lesser omentum and are separated just for descriptive comfort. The stomach is connected to the: inferior floor of the diaphragm by the gastrophrenic ligament. All these buildings have a continuous attachment along the higher curvature of the stomach and are all part of the higher omentum, separated only for descriptive functions. Such areas are referred to as naked areas, formed in relation to the attachments of the peritoneal formations to the organs, including mesenteries, omenta, and ligaments that convey the neurovascular constructions. Some peritoneal folds contain blood vessels and bleed if cut, such as the lateral umbilical folds, which include the inferior epigastric arteries. Subdivisions of Peritoneal Cavity After the rotation and improvement of the higher curvature of the abdomen throughout growth (see the Clinical Box "Brief Review of Embryological Rotation of Midgut," p. A surgical incision via the anterolateral abdominal 1054 wall enters the higher sac. This median part of the abdominopelvic cavity reveals the subdivisions of the peritoneal cavity. The supracolic and infracolic compartments of the higher sac are proven after removing of the higher omentum. The infracolic spaces and paracolic gutters decide the flow of ascitic fluid (arrows) when inclined or upright. The transverse mesocolon (mesentery of the transverse colon) divides the abdominal cavity into a supracolic compartment, containing the abdomen, liver, and spleen, and an infracolic compartment, containing the small intestine and ascending and descending colon. The infracolic compartment lies posterior to the greater omentum and is divided into right and left infracolic areas by the mesentery of the small gut. Free communication happens between the supracolic and the infracolic compartments by way of the paracolic gutters, the grooves between the lateral side of the ascending or descending colon and the posterolateral stomach wall. This section shows that the omental bursa is an isolated a half of the peritoneal cavity, lying dorsal to the abdomen and extending superiorly to the liver and diaphragm (superior recess) and inferiorly between the layers of the greater omentum (inferior recess). The pink arrows move from the higher sac through the omental foramen into the omental bursa. The omental bursa permits free movement of the abdomen on the structures posterior and inferior to it as a outcome of the anterior and posterior walls of the omental 1056 bursa slide smoothly over each other. Most of the inferior recess of the bursa becomes sealed off from the main part posterior to the abdomen after adhesion of the anterior and posterior layers of the greater omentum. The omental bursa communicates with the higher sac by way of the omental foramen (epiploic foramen), a gap located posterior to the free fringe of the lesser omentum (hepatoduodenal ligament). The omental foramen can be located by working a finger alongside the gallbladder to the free edge of the lesser omentum. The index finger is passing from the higher sac via the omental foramen into the omental bursa (lesser sac). The hepatoduodenal ligament is being pinched between thumb and index finger, which would compress the structures of the portal triad (portal vein, hepatic artery, and bile duct). Anteriorly: the hepatoduodenal ligament (free edge of lesser omentum), containing the hepatic portal vein, hepatic artery, and bile duct. A major mechanism in preventing such infection is a mucous plug that successfully blocks the exterior os (opening) of the uterus to most pathogens, however not to sperm cells. The patency of the uterine tubes can be examined clinically by the use of a method by which air or radiopaque dye is injected into the uterine cavity, from which it usually flows by way of the uterine tubes into the peritoneal cavity (hysterosalpingography; see Chapter 6, Pelvis and Perineum, for more details). The Peritoneum and Surgical Procedures Because the peritoneum is well innervated, sufferers undergoing abdominal surgery experience extra ache with large, invasive, open incisions of the peritoneum (laparotomy) than they do with small laparoscopic incisions or vaginal operations. It is the covering of visceral peritoneum (often referred to clinically because the serosa) that makes watertight end-to-end anastomoses of intraperitoneal organs, such because the small gut, comparatively straightforward to obtain. It is tougher to obtain watertight anastomoses of 1058 extraperitoneal structures which have an outer adventitial layer, such as the thoracic esophagus. Because of the excessive incidence of complications corresponding to peritonitis and adhesions (see the Clinical Box "Peritoneal Adhesions and Adhesiotomy," p. When opening the peritoneal cavity is important, nice effort is made to keep away from contamination of the cavity. Peritonitis and Ascites When bacterial contamination happens throughout laparotomy, or when the gut is traumatically penetrated or ruptured as the outcome of infection and inflammation. Exudation of serum, fibrin, cells, and pus into the peritoneal cavity occurs, accompanied by ache within the overlying skin and a rise in the tone of the anterolateral belly muscle tissue. Given the extent of the peritoneal surfaces and the fast absorption of material, together with bacterial toxins, from the peritoneal cavity, when a peritonitis becomes generalized (widespread within the peritoneal cavity), the situation is dangerous and maybe deadly. In addition to the extreme stomach pain, tenderness, nausea and/or vomiting, fever, and constipation are present. General peritonitis additionally occurs when an ulcer perforates the wall of the stomach or duodenum, spilling its acidic contents into the peritoneal cavity. Ascites can also occur on account of mechanical damage (which may also produce inside bleeding) or other pathological situations, corresponding to portal hypertension (venous congestion), widespread metastasis of most cancers cells to the abdominal viscera, and hunger (when plasma proteins fail to be produced, altering concentration gradients and producing a paradoxically protuberant abdomen). In all these circumstances, the peritoneal cavity could also be distended with several liters of abnormal fluid, interfering with actions of the viscera. Rhythmic actions of the anterolateral stomach wall usually 1059 accompany respirations. If the abdomen is drawn in as the chest expands (paradoxical abdominothoracic rhythm) and muscle rigidity is present, both peritonitis or pneumonitis (inflammation of the lungs) could additionally be present.
Usage: q._h.
In an intermediate sense hair loss in men quote propecia 1 mg mastercard, it has included only the perineal area hair loss under arms propecia 5 mg free shipping, a superficial (surface) area bounded by the thighs laterally hair loss 6 months post partum propecia 1 mg discount on-line, the mons pubis anteriorly hair loss alopecia order 5 mg propecia otc, and the coccyx posteriorly. In its widest sense, as utilized in Terminologia Anatomica (the worldwide anatomical terminology), and in this e-book, it refers to the area of the body that features all structures of the anal and urogenital triangles, superficial and deep, extending as far superiorly as the inferior fascia of the pelvic diaphragm. The primary functions of the pelvic girdle are to bear the load of the higher body when sitting and standing. Other features of the pelvic girdle are to contain and shield the pelvic viscera (inferior elements of the urinary tracts and the inner reproductive organs) and the inferior stomach viscera. Bones and Features of Pelvic Girdle In mature individuals, the pelvic girdle is shaped by three bones. Features of the pelvic girdle demonstrated anatomically (A) and radiographically (B). The pelvic girdle is shaped by the two hip bones (of the inferior axial 1297 skeleton) anteriorly and laterally and the sacrum (of the axial skeleton) posteriorly. The preadolescent hip bone is composed of three bones-ilium, ischium, and pubis-that meet in the cup-shaped acetabulum. Prior to their fusion, the bones are united by a triradiate cartilage along a Y-shaped line (blue). The internal (medial or pelvic) features of the hip bones certain the pelvis, forming its lateral walls; these elements of the bones are emphasized right here. Their external elements, primarily involved in offering attachment for the decrease limb muscular tissues, are discussed in Chapter 7, Lower Limb. As a half of the vertebral column, the sacrum and coccyx are mentioned intimately in Chapter 2, Back. In infants and youngsters, each hip bone consists of three separate bones united by a triradiate cartilage at the acetabulum, the cup-like melancholy within the lateral floor of the hip bone that articulates with the top of the femur. The right and left hip bones are joined anteriorly at the pubic symphysis, a secondary cartilaginous joint. The hip bones articulate posteriorly with the sacrum at the sacro-iliac joints to type the pelvic girdle. The ala (wing) of the ilium represents the unfold of the fan, and the body of the ilium, the handle of the fan. The iliac crest, the rim of the fan, has a curve that follows the contour of the ala between the anterior and posterior superior iliac spines. Posteriorly, the 1298 sacropelvic floor of the ilium options an auricular surface and an iliac tuberosity, for synovial and syndesmotic articulation with the sacrum, respectively. The body of the ischium helps kind the acetabulum and the ramus of the ischium varieties a part of the obturator foramen. The small pointed posteromedial projection close to the junction of the ramus and body is the ischial backbone. The bigger concavity, the greater sciatic notch, is superior to the ischial spine and is fashioned in part by the ilium. The pubis is an angulated bone with a superior ramus, which helps type the acetabulum, and an inferior ramus, which contributes to the bony borders of the obturator foramen. A thickening on the anterior part of the body of the pubis is the pubic crest, which ends laterally as a outstanding swelling, the pubic tubercle. The lateral part of the superior pubic ramus has an indirect ridge, the pecten pubis (pectineal line of the pubis). The pelvis is divided into greater (false) and lesser (true) pelves by the indirect airplane of the pelvic inlet (superior pelvic aperture). The bony edge (rim) surrounding and defining the pelvic inlet is the pelvic brim, shaped by the promontory and ala of the sacrum (superior surface of its lateral part, adjoining to the body of the sacrum). The pubic arch is formed by the proper and left ischiopubic rami (conjoined inferior rami of the pubis and ischium;. These rami meet on the pubic symphysis, their inferior borders defining the subpubic angle. The width of the subpubic angle is set by the gap between the proper and the left ischial tuberosities. This may be measured with the gloved fingers within the vagina during a pelvic examination. Pubic arches or subpubic angles typical for each gender (male = red; female = green) may be approximated by spreading the index and middle finger (demonstrating narrow subpubic angle of male pelvis) or thumb and index finger (demonstrating wider subpubic angle of feminine pelvis). The lesser pelvis (true pelvis) is the part of the pelvis between the pelvic inlet and pelvic outlet. The concave superior surface of the musculofascial pelvic diaphragm types the ground of the true pelvic cavity, which is thus deepest centrally. The convex inferior floor of the pelvic diaphragm types the roof of the perineum, which is due to this fact shallow centrally and deep peripherally. The phrases pelvis, lesser pelvis, and pelvic cavity are commonly used incorrectly, as in the occasion that they were synonymous terms. Consequently, the curved axis of the pelvis intersects the axis of the abdominal cavity at an oblique angle. Pelvic Girdle Sexual Differences Distinction between male and female skeletons is most evident within the pelvic girdle. These sexual differences are related primarily to the heavier build and bigger muscle tissue of most men and to the variation of the pelvis (particularly the lesser pelvis) in girls for parturition (childbearing). Greater dimensions of the girdle in male but greater quantity of the pelvic cavity appear throughout infancy, with the best distinctions developing following puberty. The sacro-iliac joints hyperlink the axial skeleton (skeleton of the trunk, composed of the vertebral column at this level) and the inferior appendicular skeleton (skeleton of the decrease limb). The lumbosacral and sacrococcygeal joints, although joints of the axial skeleton, are immediately associated to the pelvic girdle. The lumbosacral and sacrococcygeal joints are joints of the axial skeleton immediately associated to the pelvic girdle. The auricular surfaces and tuberosities of the ilium and sacrum are demonstrated in an "opened e-book" view. Sacro-iliac Joints the sacro-iliac joints are sturdy, weight-bearing compound joints, consisting of an anterior synovial joint (between the ear-shaped auricular surfaces of the sacrum and ilium, lined with articular cartilage) and a posterior syndesmosis (a fibrous joint between the tuberosities of those bones). The auricular surfaces of the synovial joint have irregular but congruent elevations and depressions that interlock. The sacro-iliac joints differ from most synovial joints in that limited mobility is allowed, a consequence of their role in transmitting the burden of many of the physique to the hip bones. The posterior half of a coronally sectioned pelvic girdle and its sacro-iliac joints are proven. The sturdy interosseous sacro-iliac ligaments lie deep (anteroinferior) to the posterior sacro-iliac ligaments and encompass shorter fibers connecting the tuberosity of the sacrum to the tuberosity of the ilium, suspending the sacrum from the ilia (left and proper ilium) like the central portion of a suspension bridge suspended from the pylons at each finish. The weight of the body is transmitted to the sacrum anterior to the axis of rotation at the 1305 sacro-iliac joint. The tendency for increased weight or force to rotate the upper sacrum anteriorly and inferiorly is resisted by the robust sacrotuberous and sacrospinous ligaments anchoring the inferior sacrum and coccyx to the ischium. Weight is transferred from the axial skeleton to the ilia (plural of ilium) via sacro-iliac ligaments. As long as tight apposition is maintained between the articular surfaces, the sacro-iliac joints stay secure. Unlike a keystone at the prime of an arch, the sacrum is definitely suspended between the iliac bones and is firmly hooked up to them by posterior and interosseous sacro-iliac ligaments. The skinny anterior sacro-iliac ligaments are merely the anterior part of the fibrous capsule of the synovial a part of the joint. The abundant interosseous sacro-iliac ligaments (lying deep between the tuberosities of the sacrum and ilium and occupying an space of roughly 10 cm2) are the first constructions involved in transferring the load of the higher physique from the axial skeleton to the two ilia of the appendicular skeleton. The ligaments of hip joint (shown however not labeled) are identified in Chapter 5 (Lower Limb). The posterior sacro-iliac ligaments are the posterior external continuation of the identical mass of fibrous tissue. Because the fibers of the interosseous and posterior sacro-iliac ligaments run obliquely upward and 1306 outward from the sacrum, the axial weight pushing down on the sacrum actually pulls the ilia inward (medially) so that they compress the sacrum between them, locking the irregular however congruent surfaces of the sacro-iliac joints together. Inferiorly, the posterior sacro-iliac ligaments are joined by fibers extending from the posterior margin of the ilium (between the posterior superior and posterior inferior iliac spines) and the base of the coccyx to kind the huge sacrotuberous ligament. This ligament passes from the posterior ilium and lateral sacrum and coccyx to the ischial tuberosity, reworking the sciatic notch of the hip bone into a large sciatic foramen. The sacrospinous ligament, passing from the lateral sacrum and coccyx to the ischial spine, further subdivides this foramen into higher and lesser sciatic foramina.
Tags: propecia 1 mg cheap on-line, 1 mg propecia visa, 5 mg propecia otc, 1 mg propecia discount visa, 1 mg propecia order free shipping, cheap propecia 1 mg online, 1 mg propecia cheap amex, purchase propecia 5 mg amex, propecia 5 mg order, propecia 5 mg generic visa, discount propecia 5 mg online, purchase 5 mg propecia fast delivery, cheap propecia 5 mg, 5 mg propecia cheap with visa, 5 mg propecia order with amex, 1 mg propecia discount overnight delivery
9 of 10
Votes: 191 votes
Total customer reviews: 191
Customer Reviews
Goose, 51 years: The deep groove surrounding the convexity of the diaphragm is the costodiaphragmatic recess, lined with parietal pleura. There is a website of narrowing (stenosis) of the best common iliac artery (circled area). Some clinicians use the transpyloric and interspinous planes to set up the nine regions.
Makas, 48 years: The ureter lies posterolateral to the ductus deferens 1366 and enters the posterosuperior angle of the bladder, simply superior to the seminal gland. Dura mater 2376 has been removed opening the trigeminal cave, cavernous sinus and hypophysial fossa, demonstrating contained cranial nerves, inner carotid artery, and hypophysis. After descending, it folds again and attaches to the anterior floor of the transverse colon and its mesentery.
Cronos, 42 years: They cross through the paravertebral ganglia of the trunks without synapsing to enter the abdominopelvic splanchnic nerves, which convey them to the prevertebral ganglia of the abdominal cavity. Facial Aspect of Cranium Features of the anterior or facial (frontal) aspect of the skull are the frontal and zygomatic bones, orbits, nasal area, maxillae, and mandible. A 71-year-old male with four a long time of symptoms referable to each central and peripheral nervous system.
Lisk, 29 years: Of these supports, the muscle tissue are most necessary; therefore, many sport injuries are preventable through acceptable conditioning and training. The infrahyoid muscles are retracted laterally, and the isthmus of the thyroid gland is either divided or retracted superiorly. The commonest are fragments of thrombus formed because of atrial fibrillation or myocardial infarction (Table 2.
