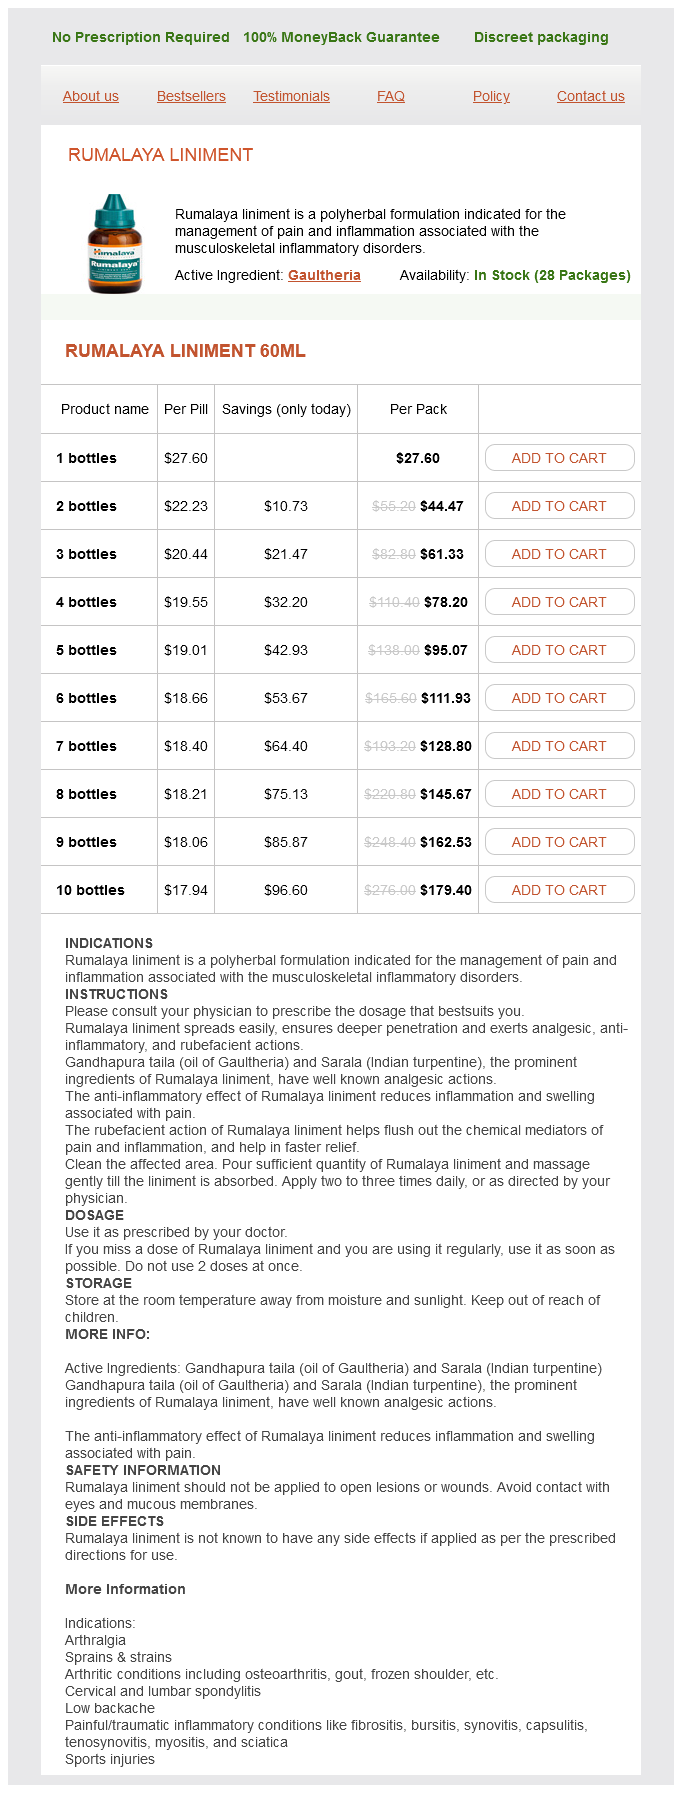
Rumalaya liniment 60ml
- 1 bottles - $27.60
- 2 bottles - $44.47
- 3 bottles - $61.33
- 4 bottles - $78.20
- 5 bottles - $95.07
- 6 bottles - $111.93
- 7 bottles - $128.80
- 8 bottles - $145.67
- 9 bottles - $162.53
- 10 bottles - $179.40
Rumalaya liniment dosages: 60 ml
Rumalaya liniment packs: 1 bottles, 2 bottles, 3 bottles, 4 bottles, 5 bottles, 6 bottles, 7 bottles, 8 bottles, 9 bottles, 10 bottles
In stock: 544
Only $19,06 per item
Description
Vitamin D is low quetiapine spasms 60 ml rumalaya liniment with mastercard, virtually all the time secondary to renal illness rather than dietary deficiency spasms during mri 60 ml rumalaya liniment cheap free shipping. Massive thickening of the calvaria and skull base narrows neural and vascular channels spasms in spanish generic rumalaya liniment 60 ml without prescription. Progressive cranial nerve involvement-most commonly compressive optic neuropathy-and carotid stenosis with ischemic signs are typical spasms quadriplegia 60 ml rumalaya liniment generic fast delivery. Fibrous alternative, hemorrhage, and necrosis lead to formation of brownish-appearing cysts. Note markedly thickened skull with multiple "brown tumors", thickened calcified pannus across the odontoid. The thickened bone causes significantly decreased volume of the orbits with compression of the optic nerve sheaths at the orbital apex. All three issues share widespread options on brain imaging though their clinical presentation and laboratory findings vary. Subcutaneous delicate tissue calcifications are common in the extremities however rare within the head and neck. Spinal ligament calcification/ossification, osteophyte formation, and enthesopathy (especially across the pelvis) are typical. Complications of chronic hypocalcemia in adults embody renal dysfunction, nephrocalcinosis, kidney stones, basal ganglia calcifications, and posterior subcapsular cataracts, in addition to low bone turnover and increased bone density. In some circumstances, diffuse neurofibrillary tangles with Fahr-type calcification have been recognized in sufferers with early-onset Alzheimer dementia. Clinical Issues Fahr illness is typically asymptomatic within the first and second many years. Deposition of calcium, together with different minerals, sometimes begins in the third decade, however signs develop one or 20 years later, often between ages 30 and 60 years. Clinical findings observe a bimodal distribution; schizophrenic-like psychosis usually presents in early adulthood with extrapyramidal signs, and subcortical dementia predominates in sufferers over the age of 50. Signal depth varies based on disease stage and the quantity of calcification and heavy steel deposition. Transcranial sonography performed through the temporal bone acoustic windows demonstrates increased echogenicity in the basal ganglia, thalami, and substantia nigra. This could mirror hyperactivation with disruption of the cortical-subcortical neural circuits responsible for the psychotic episodes typically related to Fahr illness. Specific sublocation of the calcification can be very useful in determining its underlying etiology. Mineralizing microangiopathy is a late complication of radiation-induced brain injury. Seizures and Related Disorders Seizures can be precipitated by many infective, metabolic, poisonous, developmental, neoplastic, or degenerative circumstances and might have an result on quite a few completely different areas of the mind. Because the temporal lobe is the most generally affected website, we start this part with a brief evaluate of its normal gross and imaging anatomy. Special attention is given to the hippocampus as the location concerned in mesial temporal sclerosis, an necessary imaging diagnosis. Two traditional disorders symbolize the effects of persistent repeated seizures (mesial temporal sclerosis) and prolonged acute seizure exercise (status epilepticus) on the brain. The parahippocampal gyrus lies on the medial surface of the temporal lobe and merges into the uncus (32-38). The human hippocampus is a phylogenetically older part of the mind that performs a key function in reminiscence. It could be affected by many common neurologic problems, including acute ischemic stroke, transient world amnesia, epilepsy, and encephalitis. The hippocampus is a half of the limbic system, three nested Cshaped arches that encompass the diencephalon and basal ganglia (32-37). The hippocampus proper is a part of the center arch, which extends from the temporal to the frontal lobes. Normal Anatomy of the Temporal Lobe Here, we briefly review common anatomy of the temporal lobe earlier than focusing in higher detail on the hippocampus. Its lateral floor presents three gyri: the superior temporal gyrus (contains the first auditory cortex), the center temporal gyrus (connects with auditory, (32-37) Sagittal graphic exhibits 3 nested C-shaped arches of the limbic system. Digitated anterior head, body, tail of the hippocampus lie along the floor of the temporal horn of the lateral ventricle. The two Ushaped interlocking layers of gray matter shaped by the dentate gyrus inside and Ammon horn outside comprise the hippocampus and are nicely seen. Acquired Metabolic and Systemic Disorders 1049 (32-41) Coronal graphic depicts typical mesial temporal sclerosis. The proper hippocampus is atrophied and sclerotic with loss of normal internal architecture. The hippocampus lies on the medial facet of the temporal horn and bulges into its ground. The hippocampus has three anatomic segments: the pinnacle (pes hippocampus, the digitated anterior part), the body (cylindrical), and a posterior tail that narrows and curves around the corpus callosum splenium (32-37). On coronal sections through the physique, the hippocampus is composed of two interlocking U-shaped layers of gray matter: the Ammon horn and the dentate gyrus. The Ammon horn-the hippocampus proper-forms the more superolateral, upside-down "U," while the dentate gyrus forms the inferomedial "U" (32-39). The Ammon horn is subdivided into 4 zones primarily based on width, cell size, and cell density. The parahippocampal gyrus is separated from the dentate gyrus by the hippocampal sulcus. The collateral sulcus is a crucial landmark that lies just inferolateral to the parahippocampal gyrus. Etiology A variety of events such as trauma or infection might precipitate intractable complex partial seizures (32-42). The hippocampal physique (8590%) is the most generally affected site, followed by the tail (60%) and head (50%). Preceding "auras" with concern, nervousness, and associated autonomic symptoms are common. Of these, 35-50% are pharmacoresistant and are refractory to anticonvulsant therapy. Note lowered metabolism in the best temporal lobe, probably reflecting chronic subclinical mirroring seizures. Etiology Prolonged ictal exercise induces hypermetabolism with elevated glucose utilization. With extended severe seizure activity, the blood-brain barrier might turn out to be permeable, allowing leakage of fluid and macromolecules into the extracellular spaces. Most acute periictal abnormalities are reversible and normalize inside a couple of days. Crossed cerebellar diaschisis, ipsilateral thalamic involvement, and basal ganglia lesions are seen in some instances. Diffusion restriction with uni- or bilateral hippocampal, thalamic, and cortical lesions is common (32-45) (32-46). Herpes encephalitis is usually preceded by a viral prodrome, affects the limbic system, is frequently bilateral but asymmetric, and sometimes demonstrates petechial hemorrhage. Transient international amnesia causes tiny dot-like foci of restricted diffusion within the lateral hippocampus. Note engorgement of proper cortical vessels and draining veins compared with the conventional left aspect. Eclampsia and hemolytic-uremic syndrome have been reported as rare attainable causes. Miscellaneous reported associations embody migraine headache, trauma, high-altitude cerebral edema, systemic lupus erythematosus, internal cerebral vein occlusion, Charcot-Marie-Tooth illness, and neoplasms. The corpus callosum-especially the splenium-has a high density of excitatory amino acid, toxin, and drug receptors and is hence extra vulnerable to the event of cytotoxic edema. The use and subsequent withdrawal of antiepileptic medicine is probably the most generally related condition.
Blueberries (Blueberry). Rumalaya liniment.
- What is Blueberry?
- How does Blueberry work?
- Are there any interactions with medications?
- Are there safety concerns?
- Preventing cataracts and glaucoma, ulcers, urinary tract infections (UTIs), multiple sclerosis (MS), chronic fatigue syndrome (CFS), fever, sore throat, varicose veins, hemorrhoids, bad circulation, diarrhea, constipation, labor pains, and other conditions.
- Dosing considerations for Blueberry.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96974
The brain is extremely small spasms vulva buy cheap rumalaya liniment 60 ml online, and the sulcation pattern appears significantly simplified or nearly utterly smooth (37-22) muscle relaxant for elderly safe 60 ml rumalaya liniment. In microcephaly with extensive polymicrogyria muscle relaxant cyclobenzaprine dosage rumalaya liniment 60 ml buy with visa, the brain is small spasms while pregnant rumalaya liniment 60 ml purchase online, and polymicrogyria is the predominant gyral sample (37-21). Familial main microcephaly is an autosomal-recessive disorder with a single scientific phenotype and genetic heterogeneity. Several chromosomal syndromes are characterised by mental retardation and microcephaly. These embrace trisomy 21 (Down), trisomy 18 (Edward), cridu-chat ("cat cry," 5p syndrome), Cornelia de Lange, and Rubinstein-Taybi syndromes. Most instances of primary (genetic) microcephaly are detected in utero or shortly after delivery. Mental retardation, developmental delay, and seizures are the most typical medical symptoms. In older children, the cranium is thickened, and the sinuses seem overpneumatized. The brain can seem small but relatively regular, small with simplified gyral pattern, or microlissencephalic. In microcephaly with simplified gyral pattern, the gyri are fewer in number and seem simplified. Differential Diagnosis the most important diagnostic dilemma is differentiating major from secondary microcephaly. Commissural and Cortical Maldevelopment 1205 (37-24) Resected surgical specimen from a affected person with intractable epilepsy reveals a traditional "funnel-shaped" area of thickened cortex, blurred gray-white interface. Note funnel-shaped malformation with indistinct gray-white matter interface and curvilinear hyperintense foci extending toward the lateral ventricle. A funnel-shaped configuration of mildly thickened, barely firm cortex with poor demarcation from the underlying white matter is characteristic (37-24). Cortical thickness is elevated, and the gray-white matter interface is blurred in each subtypes. Most foci are smaller than 2 cm in diameter and could be troublesome to detect, particularly on commonplace imaging studies. Associations with Proteus, Klippel-Weber-Trenaunay, and epidermal nevus Congenital Malformations of the Skull and Brain 1208 syndromes, neurofibromatosis kind 1, and hypomelanosis of Ito have been reported. Abnormal gyral sample, cortical dysgenesis, enlarged lateral ventricle, and white matter hypertrophy are common. Areas of dysplastic hamartomatous overgrowth are present, and the gray-white matter junction is often vague (37-28). Gray matter heterotopias and clusters of Clinical Issues Epidemiology and Demographics. Extracranial hemihypertrophy of half or all the ipsilateral body could also be present. Prognosis is poor because seizures are often intractable and developmental delay is extreme. Commissural and Cortical Maldevelopment the contralateral "regular" hemisphere are widespread and so ought to be fastidiously searched for as a half of surgical planning. In uncommon circumstances, the dysplastic changes contain only a half of one hemisphere ("focal," "localized," or "lobar" hemimegalencephaly). Congenital Malformations of the Skull and Brain 1210 (37-31) Axial graphic shows in depth bilateral subependymal heterotopia lining the lateral ventricles. T2 scans present areas of pachy- and polymicrogyria with vague borders between gray and white matter (37-30). Other than dysplastic cerebellar gangliocytoma (Lhermitte-Duclos disease), tumors consisting solely of neoplastic neurons (often with dysplastic features) are exceptionally uncommon. The newly described multinodular and vacuolating neuronal tumor of the cerebrum has a distinct Abnormalities of Neuronal Migration Abnormalities of neuronal migration are divided into 4 main subgroups as discussed above. The part concludes with a short discussion of subcortical heterotopias, sublobar dysplasias, and cobblestone advanced. Heterotopias Arrest of regular neuronal migration along the radial glial cells can lead to grossly visible masses of "heterotopic" gray matter. These collections come in many shapes and sizes and may be discovered virtually wherever between the ventricles and the pia. They may be solitary or multifocal and exist both as an isolated phenomenon or in affiliation with other malformations. The most typical is ventriculomegaly adopted by agenesis of the corpus callosum and cortical dysplasia. Collections of round or ovoid nodules indent the lateral partitions of the ventricles, giving them a particular "lumpy-bumpy" look. The overlying cortex usually appears thinned, however sulcation and gyration are typically regular. The involved portion of the affected hemisphere is abnormally small, and the overlying cortex appears skinny and generally dysplastic (37-35). The overlying cortex is thin, and the underlying ventricle typically appears distorted (37-36). Although these have been described with megalencephaly and polymicrogyria, most are in all probability a half of the "double cortex" type of lissencephaly (see below). The main differential analysis of subcortical heterotopia is neoplasm, most particularly gangliocytoma. The giant, focal, mass-like collection of grey matter, thin overlying cortex are typical. Malformations because of widespread abnormal transmantle migration embody agyria, pachygyria, and band heterotopia. Agyria is defined as a thick cortex with absence of floor gyri ("full" lissencephaly). The white matter is severely decreased in quantity and infrequently incorporates foci of heterotopic neurons. In essentially the most extreme varieties, the cerebral hemispheres are clean with poor operculization and underdeveloped sylvian fissures. Coronal sections show a markedly thickened cerebral cortex with broad gyri and lowered quantity of the underlying white matter (37-38). From the outermost to the innermost, these layers are (1) a thin subpial molecular layer, (2) a thin outer cortex composed of disorganized giant Clinical Issues Epidemiology and Demographics. Patients with band heterotopia usually present with developmental delay and a milder seizure disorder. The right hemisphere demonstrates milder lissencephaly with band heterotopia ("double cortex" syndrome) and skinny outer cortex. A thick band of relatively well-delineated dense cortex surrounds a thinner, easy band of white matter (37-39A). A deeper, thick layer of arrested migrating neurons is frequent and will mimic band heterotopia (37-39B) (37-39C). The corpus callosum has a skinny flat body with a extra vertically oriented splenium. Differential Diagnosis Extremely premature mind is easy at 24-26 gestational weeks and normally has a "lissencephalic" appearance (see Chapter 35). In microcephaly with simplified gyral sample, the top circumference is no much less than three normal deviations below regular. Too few gyri, abnormally shallow sulci, and a standard or skinny (not thick) cortex are present. Cobblestone Lissencephaly Cobblestone lissencephaly is also recognized as type 2 lissencephaly and is genetically, embryologically, pathologically, and radiologically distinct from sort 1 ("classic") lissencephaly. The cerebellum is usually small, and its folia are frequently fused and disorganized. Etiology Cobblestone cortex outcomes from abnormalities brought on by defects in the limiting pial basement membrane. Overmigration of neuroblasts via these breaches leads to an extracortical layer of aberrant gray matter nodules-the "cobblestones"-on the brain surfaces.
Specifications/Details
It is the second most typical pediatric main cranium lesion (after dermoid cysts) spasms meaning in urdu purchase rumalaya liniment 60 ml with visa. Radiation remedy is generally averted muscle relaxant hair loss rumalaya liniment 60 ml buy lowest price, as it may induce malignant transformation muscle relaxant allergy order rumalaya liniment 60 ml online. Intravenous bisphosphonate therapy has been used to ameliorate the illness course with some reported success spasms vs seizures rumalaya liniment 60 ml buy discount. In basic, very early lesions are radiolucent after which endure progressive calcification, resulting in a "ground-glass" appearance. A sample with mixed areas of radiopacity and radiolucency is present in almost half of all circumstances (26-4A) (26-5). Moderate hypointensity is attribute of ossified and/or fibrous parts of the lesion (26-4B). Signal intensity following contrast administration varies depending on the lesion stage and ranges from no enhancement to diffuse, avid enhancement in lively lesions (26-4C). Intraosseous meningiomas are extra widespread in the calvaria than within the cranium base and facial bones. A strongly enhancing en plaque gentle tissue mass is often associated with the bony lesion. These embody osteitis deformans, florid osseous dysplasia, focal cementoosseous dysplasia, and periapical cemental dysplasia. Paget illness typically occurs in elderly sufferers and normally entails the calvaria and temporal bone. PaD is characterized by fast bone turnover within a number of discrete skeletal lesions. Etiology Genetic alterations happen in both basic Paget disease of the aged and the uncommon familial Paget-like bone dysplasias that arise throughout childhood. The skull (both calvaria and skull base) is affected in 25-65% of patients (26-6). In the early lytic stage, energetic PaD is characterized by mobile fibroosseous lesions with minimally calcified osteoid trabeculae. Osteoclasts are numerous and larger than normal; additionally they have elevated numbers of nuclei. In the inactive stage, bone turnover and extreme vascularity lower and the trabeculae coarsen. It is particularly prevalent within the United States, the British Isles, Canada, Australia, and some elements of Western Europe. Most patients are 5585 years of age with lower than 5% of instances occurring in patients under the age of 40. Juvenile PaD, also called idiopathic hyperphosphatasia, is an autosomalrecessive bone dysplasia. It begins in infancy or early childhood and is characterised by lengthy bone widening, acetabular protrusion, pathologic fractures, and skull thickening. Presentation varies with location, and all bones of the craniofacial complex may be affected. Patients could present with both conductive (ossicular involvement) or sensorineural hearing loss (cochlear involvement or bony compression). Markedly elevated serum alkaline phosphatase is a constant characteristic, whereas calcium and phosphate ranges stay inside normal vary. In the extracranial skeleton, osseous growth with progressive skeletal deformity is typical. In comparability, craniofacial PaD usually has a extra benign course and should stay asymptomatic for a number of years. Two neoplastic processes are related to PaD: big cell tumor (benign) and sarcoma (malignant). Giant cell tumor is an expansile intraosseous mass that usually happens within the epiphyses and metaphyses of lengthy bones in patients with longstanding polyostotic PaD. Most osteosarcomas are excessive grade and have already metastasized at the time of prognosis. Bisphosphonates cut back bone turnover and have been effective in many circumstances of PaD. In the early lively stage, radiolucent lesions develop within the calvaria, a condition termed osteoporosis circumscripta. Enlarged bone with blended lytic and sclerotic foci and confluent nodular calcifications follows (the "cotton wool" appearance) in the combined energetic stage. Mixed areas of bony lysis and sclerosis then develop, producing the "cotton wool" appearance (26-8). In extreme instances, the softened expanded cranium base can produce basilar invagination. Patchy enhancement on T1 C+ can happen in the advancing hypervascular zone of lively PaD (26-9C). Sclerotic metastases might resemble PaD, however no trabecular coarsening or bony enlargement is current. The early lytic section of PaD may resemble lytic metastases or a quantity of myeloma; neither enlarges the affected bone. Lesions can happen in the jaws (maxilla, mandible), petrous temporal bone, basisphenoid, and paranasal sinuses. Hemorrhages of varying ages with fluid-fluid levels are a outstanding imaging feature, as are smaller cysts ("diverticula") that project from larger lesions. The surrounding rim and fibrous septa improve following contrast administration (26-11). The dependent blood-fluid levels in the cysts are higher appreciated on the axial scan. Pathology Chordomas are midline tumors that will arise wherever along the primitive notochord. The sacrum is the most typical web site (50% of all chordomas) followed by the sphenooccipital (clival) region (35%) and spine (15%). Occasionally, a chordoma is predominantly extraosseous and arises off-midline, usually in the nasopharynx or cavernous sinus. Etiology Skull base (clival) chordomas most likely arise from the cranial finish of primitive notochordal remnants. Subpopulations of (26-12) Sagittal graphic shows an expansile, destructive, lobulated clival mass with a "thumb" of tumor indenting the pons. Neoplasms, Cysts, and Tumor-Like Lesions 828 Three main histologic forms of chordoma are acknowledged: conventional ("traditional"), chondroid, and dedifferentiated. Conventional chordoma is the most common kind and consists of physaliphorous cells that contain mucin and glycogen vacuoles, giving a characteristic "bubbly" look to its cytoplasm (26-13). Chondroid chordomas have stromal components that resemble hyaline cartilage with neoplastic cells nestled inside lacunae. Dedifferentiated chordoma represents lower than 5% of chordomas and sometimes occurs in the sacrococcygeal region, not the clivus. Clinical Issues Chordomas account for 2-5% of all main bone tumors however trigger nearly 40% of sacral tumors. Although chordomas might occur at any age, peak prevalence is between the fourth and sixth decades. Large chordomas could cause a quantity of cranial neuropathies, together with visual loss and facial pain. Although they develop slowly, chordomas are finally lethal until treated with aggressive resection and proton beam irradiation. Chondroid chordomas exhibit the most favorable outcomes, whereas dedifferentiated tumors are associated with the most rapid development and poor general survival. Intratumoral calcifications usually symbolize sequestrations from destroyed bone. On sagittal photographs, a "thumb" of tumor tissue is often seen extending posteriorly through the cortex of the clivus and indenting the pons. Intratumoral calcifications and hemorrhage may cause foci of decreased sign inside the general hyperintense mass. Moderate to marked however heterogeneous enhancement is typical after contrast administration. Increased tumor-to-pons postcontrast sign depth is related to extra abundant blood supply and increased threat of tumor progression. Ecchordosis physaliphora is a uncommon nonneoplastic notochordal remnant which will arise wherever from the cranium base to the sacrum.
Syndromes
- Fever
- Detect abnormal circulation (shunts) in the blood vessels of the lungs (pulmonary vessels)
- Thoroughly wash and rinse the area between the lips of the vagina or the head of the penis.
- You have many sex partners.
- Chemotherapy to kill cancer cells
- Cardiac arrest due to the electrical effect on the heart
- Dementia
Related Products
Additional information:
Historically spasms nose rumalaya liniment 60 ml purchase, surgical procedure has been performed through an anterior approach for d�bridement and grafting as a result of tuberculous spondylitis is typically ventral in location muscle relaxant homeopathic discount 60 ml rumalaya liniment amex. Posterior instrumented fusion is often performed after the anterior process either concurrently or as a staged process muscle relaxant 2632 rumalaya liniment 60 ml generic without prescription. Several studies have reported on posterior-only approaches for anterior d�bridement and circumferential reconstruction using costotransversectomy or an extracavitary method spasms diaphragm hiccups rumalaya liniment 60 ml lowest price. Since 2002, posterior-only vertebral column resection has become common within the treatment of angular kyphotic deformity ensuing from tuberculosis. It may end up in neurologic deficits, sagittal imbalance, or cardiopulmonary restriction. In 2012, there was a large outbreak of fungal infections together with spinal epidural abscesses brought on by contaminated injections of 46 Methicillin-resistant S aureus was seen in 15% to 40% methylprednisolone. Other etiologies embrace methicillin-sensitive S aureus, E coli, and Pseudomonas aeruginosa. In most cases, the abscess is positioned dorsal to the spinal wire;25,45 nevertheless, the abscess was circumferential in approximately 23% of instances. In addition, the spinal epidural abscess commonly entails multiple location. Ventrally situated epidural abscesses are more doubtless associated with spondylodiscitis. The precise mechanism of how an epidural abscess causes neurologic deficits continues to be controversial. Most plausibly, a combination of direct mechanical compression and vascular compromise and ischemia, with or without irritation of the blood vessels, probably ends in spinal twine injury. Clinical Features Clinically, patients with spinal epidural abscess can present with a variety of symptoms that vary from easy back or neck ache to complete paralysis. Only a small percentage of patients current with the traditional medical triad of back ache, fever, and neurologic deficits. Almost all patients have sitespecific pain and 50% of patients present with fever or weak point. Diagnosis A through historical past and physical examination are important in the evaluation of a patient suspected of getting an epidural abscess. Most patients present with site-specific again or neck pain; nevertheless, solely 50% of sufferers might be febrile and fewer than 50% of patients have neurologic deficits. Noncontiguous spinal epidural abscess lesions are frequent and have been reported to happen in as a lot as 10% of patients with spinal epidural abscesses. Treatment In most retrospective studies, the mainstay of therapy is surgical decompression and d�bridement mixed with antibiotics. Initial broad-spectrum antibiotic protection is really helpful until the culture results have been obtained. After the results have been finalized, the antibiotic routine could be modified toward the particular organism. Case collection have also described nonsurgical treatment of spinal epidural abscesses. No randomized clinical studies have been printed on the timing of surgery; nonetheless, the consensus appears to be that if the choice is made for surgical intervention, it should be performed as expeditiously as potential. The present mortality fee is roughly 10% in contrast with more than 30% in the course of the Fifties. The mortality fee stays elevated through the first yr following spinal epidural abscess however decreases to virtually that of the reference population over time. The incidence of postoperative infection varies significantly, with increased charges related to the use of instrumentation, a number of ranges, extended surgical time, open procedures, and medical comorbidities corresponding to diabetes mellitus. D�bridement ought to proceed systematically from superficial layers to deep layers with cultures obtained at each layer. Well-fixed instrumentation often can be retained; nonetheless, loose hardware could require removing. Infected interbody polyether ether ketone cages are a particular problem and regularly require removal to eradicate an infection. Recently, a number of stories recommend that placement of vancomycin powder instantly into the surgical wound significantly reduces the speed of postoperative an infection. Treatment usually features a mixture of surgical intervention and antibiotics; nonetheless, chosen cases could be treated with antibiotics alone with shut monitoring. Irrespective of the underlying condition, the goals of surgical intervention are the same: d�bridement and excision of all contaminated and necrotic tissue, decompression of neural parts when needed, and restoration of alignment and stability to the spinal column. Less-invasive surgical strategies have gotten extra common in the surgical therapy of those patients and are associated with doubtlessly less morbidity, faster restoration, and improved outcomes. Key Study Points In most spine infections, surgical intervention is indicated for failure of antibiotic administration, substantial instability or deformity, and substantial neural compression with or with out neurologic deficits. Neurologic deficits may finish up from a combination of ischemia and direct compression. Postoperative infections usually require aggressive surgical intervention together with antibiotics. The incidence of osteomyelitis is increasing, but whether the rise is real or brought on by improved diagnostic methods remains unknown. Shiban E, Janssen I, Wostrack M, et al: A retrospective research of 113 consecutive instances of surgically treated spondylodiscitis patients: A single-center expertise. This retrospective study from one establishment showed that a staged surgical method and a brief 1- to 2-week interval of intravenous antibiotics followed by 3 months of oral antibiotics is efficient. The authors of this retrospective study from one institution concluded that immediate surgical decompression combined with appropriate antibiotic treatment is supported for patients with focal neurologic deficits. Mylona E, Samarkos M, Kakalou E, Fanourgiakis P, Skoutelis A: Pyogenic vertebral osteomyelitis: A systematic review of medical traits. Loibl M, Stoyanov L, Doenitz C, et al: Outcome-related co-factors in a hundred and five cases of vertebral osteomyelitis in a tertiary care hospital. This retrospective examine presents demographic data and medical options of vertebral osteomyelitis. Gasbarrini A, Boriani L, Salvadori C, et al: Biopsy for suspected spondylodiscitis. This systematic evaluate and meta-analysis concluded that image-guided spinal biopsy is highly specific and performs nicely within the prediction of spontaneous vertebral osteomyelitis however has reasonable accuracy for ruling out this diagnosis. Shousha M, Boehm H: Surgical treatment of cervical spondylodiscitis: A evaluate of 30 consecutive patients. The authors of this research reviewed 30 consecutive patients with cervical osteomyelitis and concluded that radical surgical d�bridement and acceptable antibiotic therapy present a reliable strategy to achieve complete therapeutic of inflammation. This cohort examine showed that antibiotic remedy of methicillin-resistant S aureus hematogenous vertebral osteomyelitis of a minimum of 8 weeks is associated with less relapse. Verd�-L�pez F, Vanaclocha-Vanaclocha V, Gozalbes-Esterelles L, S�nchez-Pardo M: Minimally invasive spine surgical procedure in spinal infections. The use of minimally invasive surgical methods to manage spine infections is discussed. The authors conclude that these methods are safe and efficient and may have helpful results on morbidity and permit quicker affected person restoration. Ten adults with infectious spondylodiscitis of the lumbar backbone were handled with posterior d�bridement and instrumented fusion. Gorensek M, Kosak R, Travnik L, Vengust R: Posterior instrumentation, anterior column reconstruction with single posterior strategy for therapy of pyogenic osteomyelitis of thoracic and lumbar backbone. This study discusses the posterior-only strategy with anterior d�bridement and posterior fixation for lumbar vertebral osteomyelitis without sacrificing the segmental nerve root. This case sequence reported on patients with vertebral osteomyelitis who underwent treatment with posterior fixation and antibiotic remedy. The authors report that changed costotransversectomy achieved good medical outcomes in a collection of sufferers with thoracic spondylodiscitis. This research reported on percutaneous endoscopic lavage and drainage carried out to get hold of specimens to guide antibiotic remedy and relieve signs. This article discusses percutaneous endoscopic lavage and d�bridement in sufferers with infectious spondylodiscitis.
Usage: q._h.
Serial follow-up of indeterminate cystic lesions of the pineal region shows muscle relaxant magnesium buy cheap rumalaya liniment 60 ml on-line, in most lesions spasms going to sleep rumalaya liniment 60 ml generic with mastercard, no important change in size or character over time intervals from months to years spasms in colon 60 ml rumalaya liniment mastercard. Approximately 1-2% are very hyperintense spasms upper right abdomen discount 60 ml rumalaya liniment mastercard, which may indicate intracystic hemorrhage. Thin-section high-resolution sagittal and axial T2 scans are especially useful for detecting and characterizing lesions in the anatomically complex pineal region. Neoplasms, Cysts, and Tumor-Like Lesions 886 Differential Diagnosis the most typical differential prognosis is normal pineal gland. Normal pineal glands often contain one or more small cysts and may have nodular, crescentic, or ring-like enhancement. Pineocytomas can stay secure for many years with out vital change on serial imaging. Once a cyst has been identified as lying within the brain itself, the differential prognosis is limited. The most common parenchymal cysts-prominent perivascular areas and hippocampal sulcus remnants-are anatomic variants. Cyst formation may relate to blood-brain-barrier deficiency with peritumoral extravasation of water, electrolytes, and plasma proteins from altered microvessels. They are often uneven, may cause mass impact, and have incessantly been mistaken for multicystic mind tumors. The cyst wall generally consists of gliotic mind with reactive astrocytes and lymphocytes. Most are solitary, but occasionally multiple loculated fluid collections are trapped on the tumor-brain interface. The common look is one or more "swimming pools" of trapped fluid surrounding an extraaxial tumor mass (28-30). Enhancement is minimal or absent and customarily associated to reactive inflammatory modifications in the cyst wall, not tumor. They are additionally frequent within the subcortical and deep white matter in addition to the midbrain and dentate nuclei of the cerebellum. For instance, in the event that they happen within the subcortical white matter, the overlying gyri are enlarged with concomitant compression of adjacent sulci (28-38). Differential Diagnosis the most important differential prognosis is chronic lacunar infarction. Infectious cysts (especially parenchymal neurocysticercosis cysts) are usually small. These remnant cavities-hippocampal remnant cysts-are regular anatomic variants (28-40). Small blood vessels are sometimes additionally included because the hippocampal sulcus types, folds, and fuses. They appear as a "string of beads" with a number of small round or ovoid cysts curving along the hippocampus between the dentate gyrus and subiculum, just medial to the temporal horn of the lateral ventricle. Etiology At 15 fetal weeks, the hippocampus usually unfolds and surrounds an "open" shallow fissure-the hippocampal sulcus-along the medial surface of the temporal lobe. The partitions of the hippocampal sulcus gradually fuse, and the sulcus is ultimately obliterated. When they happen in the temporal lobe, enlarged perivascular spaces are found in the subcortical white matter of the insula and anterior tip of the temporal lobe, not medial to the temporal horn of the lateral ventricle. They are benign fluid-containing cavities buried within the cerebral white matter. Porencephalic cysts talk with the ventricle and are lined by gliotic or spongiotic white matter. Arachnoid cysts are extraaxial, not intraaxial, and are lined with flattened arachnoid cells. Connatal cysts are cystic ependyma-lined areas adjacent to the superolateral margins of the body and frontal horns of the lateral ventricles. They are relatively widespread and usually innocuous lesions caused by coarctation or coaptation of the partitions of the frontal horns. Etiology Porencephalic cysts are encephaloclastic lesions, the end results of a harmful course of. Pathology Porencephalic cysts range in dimension from a couple of centimeters to cysts that involve nearly an entire cerebral hemisphere. Porencephalic cysts are deep, uni- or bilateral, smooth-walled cavities or excavations within the mind parenchyma. They are sometimes "full-thickness" lesions, extending from the ventricle to the glia limitans of the cortex (28-45). Occasionally, a skinny rim of ependyma or subependymal white matter could separate the cyst from the ventricle. Porencephalic cysts are relatively widespread, especially in children, in whom they symbolize 2. Spastic hemiplegia, medically refractory epilepsy, and psychomotor retardation are the commonest signs. Occasionally a porencephalic cyst will continue to sequester fluid and increase, inflicting mass effect. Porencephalic Cyst Terminology "Porencephaly" literally means a gap within the mind. These cysts or cavities also usually talk by way of a "pore" with the subarachnoid area. The ipsilateral ventricle is usually enlarged secondary to volume loss within the adjoining parenchyma. Porencephalic cysts are lined by reactive gliosis (glial "scar"), which occurs when histologically benign astrocytes proliferate in and round damaged mind parenchyma. A porencephalic cyst with surrounding reactive gliosis must be distinguished from spongiosis, a process that represents tissue loss (not astrocytic proliferation) with formation of empty (spongiform) areas ("holes") in the brain. Schizencephaly (literally "break up brain") is a congenital lesion that can be either "open" or "closed lip. Hydranencephaly ("water on the brain") is a congenital lesion during which a lot of the supratentorial developing brain has been destroyed by arterial occlusion. Hydranencephaly is bilateral and symmetric, whereas most porencephalic cysts are unilateral or bilateral but uneven. Occasionally, massive cysts could seem considerably atypical and cause diagnostic concern. Acquired lesions are much more frequent; lipid that accumulates from desquamating, degenerating choroid plexus epithelium coalesces into macrocysts and provokes a xanthomatous response. Clinical Issues � Most common intracranial cyst � Most found incidentally � Most widespread in fetus/infants, older adults Clinical Issues Demographics. Irregular clumps of calcification around the margins are Nonneoplastic Cysts 895 (28-51) Axial graphic reveals a classic colloid cyst at the foramen of Monro inflicting mild/moderate obstructive hydrocephalus. Note that the fornices and choroid plexus are elevated and stretched over the cyst. This may due to this fact represent pseudorestriction rather than true restricted diffusion. An enhancing, enlarged choroid plexus with out frank cyst formation can additionally be seen with Sturge-Weber malformation, collateral venous drainage, and diffuse villous hyperplasia. Sturge-Weber and collateral venous drainage often cause unilateral choroid plexus enlargement. Ependymal cysts usually displace and compress the choroid plexus somewhat than come up from it. Intraventricular parasitic cysts, specifically those of neurocysticercosis, are comparatively uncommon. The roughly 10% that do enlarge tend to be bigger lesions, typically causing hydrocephalus, and located in youthful patients. Incidental lesions rarely cause acute obstructive hydrocephalus or sudden neurological deterioration. Cyst "apoplexy" with intracystic hemorrhage and sudden enlargement happens however is rare.
Tags: buy cheap rumalaya liniment 60 ml online, discount rumalaya liniment 60 ml online, buy 60 ml rumalaya liniment mastercard, rumalaya liniment 60 ml discount overnight delivery, generic rumalaya liniment 60 ml without a prescription, cheap rumalaya liniment 60 ml overnight delivery, 60 ml rumalaya liniment cheap free shipping, discount rumalaya liniment 60 ml otc, purchase rumalaya liniment 60 ml free shipping, rumalaya liniment 60 ml buy discount line, generic rumalaya liniment 60 ml, buy rumalaya liniment 60 ml fast delivery, rumalaya liniment 60 ml buy with amex, 60 ml rumalaya liniment purchase visa, 60 ml rumalaya liniment order with visa, order rumalaya liniment 60 ml on-line
9 of 10
Votes: 182 votes
Total customer reviews: 182
Customer Reviews
Nerusul, 22 years: The research, which included a hundred and fifty five sufferers, reported 75 problems, together with finish plate fracture/subsidence (18. Clinical Considerations the only most important clinical characteristic in establishing an appropriate differential analysis for a sellar region mass is patient age.
Vatras, 39 years: Although the speed of complications was similar in each groups, sufferers who received surgical treatment had a significantly decrease nonunion rate. Current Status On examination, a 2- to 3-cm mass was palpated in the upper quadrant of Mrs.
Xardas, 24 years: Glucocorticoid remedy could also be administered in those with moderate to extreme disease. Concomitant pulmonary pathophysiology necessitates the therapy of the spinal deformity with simultaneous preservation of the chest wall and lung progress.
Shawn, 26 years: Here the pituitary gland occupies less than 50% of the pituitary fossa, and its superior floor seems concave. The effects of leveraging masters-level�educated nurses to offset the effects of upper patient-to-nurse ratios in a hospital setting are examined.
Konrad, 64 years: Therapeutic options rely upon symptoms, location, and disease extent, ranging from easy surgical excision to radiation and chemotherapy. With the exception of the labyrinthine section, a sturdy vascular plexus surrounds many of the intratemporal facial nerve.
