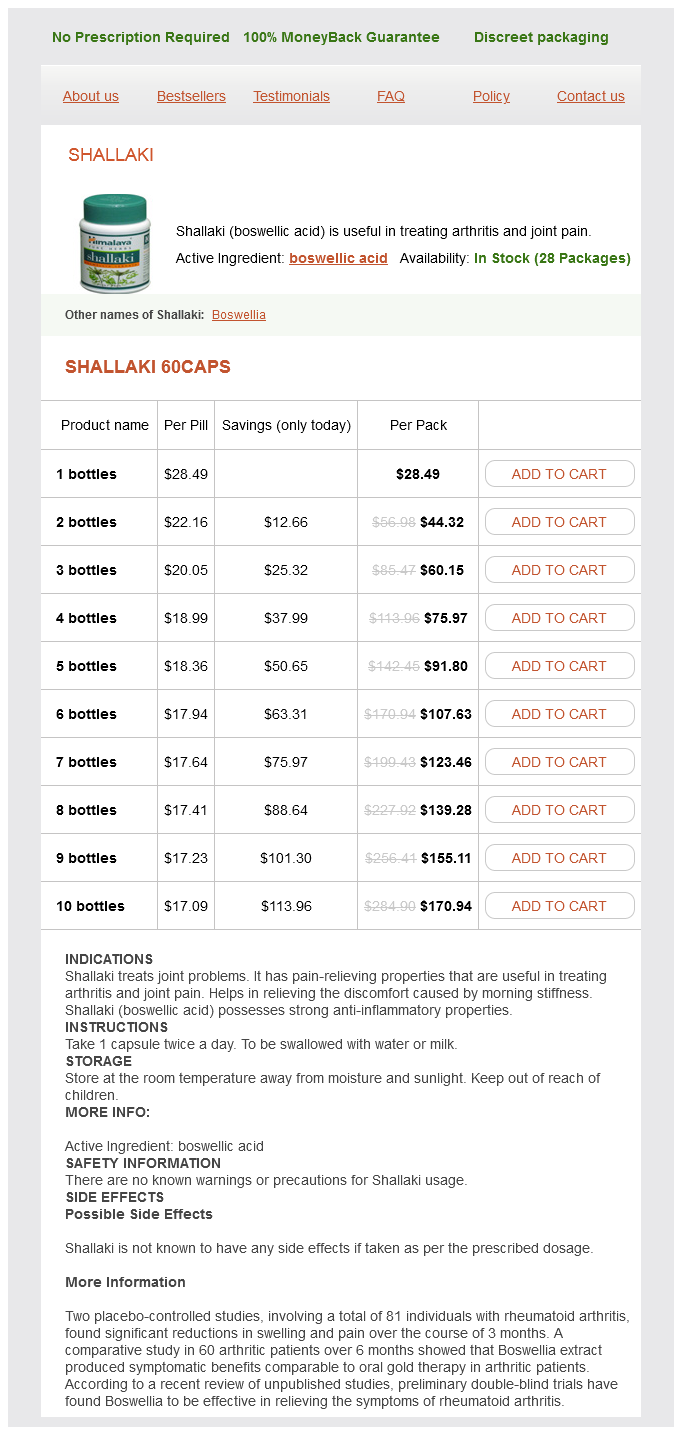
Shallaki 60caps
- 1 bottles - $28.49
- 2 bottles - $44.32
- 3 bottles - $60.15
- 4 bottles - $75.97
- 5 bottles - $91.80
- 6 bottles - $107.63
- 7 bottles - $123.46
- 8 bottles - $139.28
- 9 bottles - $155.11
- 10 bottles - $170.94
Shallaki dosages: 60 caps
Shallaki packs: 1 bottles, 2 bottles, 3 bottles, 4 bottles, 5 bottles, 6 bottles, 7 bottles, 8 bottles, 9 bottles, 10 bottles
In stock: 829
Only $18,16 per item
Description
The medial surface of the calcaneus is concave and has one outstanding feature associated with its upper margin (the sustentaculum tali; spasms esophageal generic shallaki 60 caps without prescription. The underside of the sustentaculum tali has a definite groove working from posterior to anterior and along which the tendon of the exor hallucis longus muscle travels into the only of the foot muscle relaxant drugs generic 60 caps shallaki with amex. The superior surface of the sustentaculum tali has a side (middle talar articular surface) for articulation with the corresponding middle side on the head of the talus spasms in legs 60 caps shallaki order visa. Anterior and posterior talar articular surfaces are on the superior floor of the calcaneus itself spasmus nutans treatment buy shallaki 60 caps mastercard. The posterior talar articular floor is massive and is approximately close to the center of the superior floor of the calcaneus. Between the posterior talar articular floor, which articulates with the body of the talus and the other two articular surfaces, which articulate with the head of the talus, is a deep groove (the calcaneal sulcus;. Clinical app Achilles tendon rupture Rupture of the Achilles tendon is often associated to sudden or direct trauma. In addition, there are specific circumstances which will predispose the tendon to rupture. Among these conditions are tendinopathy (due to overuse, or to age-related degenerative changes) and previous Achilles tendon interventions corresponding to injections of prescription drugs and the use of sure antibiotics (quinolone group). Intermediate tarsal bone the intermediate tarsal bone on the medial facet of the foot is the navicular (boat shaped). This bone articulates behind with the talus and articulates in front and on the lateral facet with the distal group of tarsal bones. One distinctive characteristic of the navicular is a prominent rounded tuberosity for the attachment of the tibialis posterior tendon, which initiatives inferiorly on the medial side of the plantar surface of the bone. Distal group 318 From lateral to medial, the distal group of tarsal bones consists of. Three cuneiforms (Latin for "wedge")-the lateral, intermediate, and medial cuneiform bones, along with articulating with one another, articulate posteriorly with the navicular bone and anteriorly with the bases of the medial three metatarsals. The lateral side of the base of metatarsal V has a distinguished tuberosity, which projects posteriorly and is the attachment website for the tendon of the bularis brevis muscle. Each metatarsal has a head on the distal end, an elongate shaft in the center, and a proximal base. The head of each metatarsal articulates with the proximal phalanx of a toe and the base articulates with one or more of the distal group of tarsal bones. Each toe has three phalanges (proximal, middle, and distal), apart from the nice toe, which has only two (proximal and distal). Each phalanx consists of a base, a shaft, and a distal head: the base of each proximal phalanx articulates with the head of the associated metatarsal. The head of each distal phalanx is nonarticular and attened into a crescent-shaped plantar tuberosity underneath the plantar pad on the end of the digit. In every toe, the whole size of the phalanges mixed is far shorter than the size of the associated metatarsal. Imaging app Visualizing the bones of the foot Medial Metatars als cuneiform Navicular Talus Tibia Fibula. The ankle joint is synovial in type and involves the talus of the foot and the tibia and bula of the leg. The ankle joint mainly permits hingelike dorsi exion and plantar exion of the foot on the leg. The distal finish of the bula is rmly anchored to the larger distal finish of the tibia by robust ligaments. Together, the bula and tibia create a deep bracket-shaped socket for the upper expanded a part of the physique of the talus: the roof of the socket is shaped by the inferior floor of the distal end of the tibia. The longer lateral facet of the socket is shaped by the lateral malleolus of the bula. The articular a half of the talus is shaped like a short half cylinder tipped onto its at side with one end going through lateral and the other end dealing with medial. The curved upper floor of the half cylinder and the 2 ends are covered by hyaline cartilage and t into the bracket-shaped socket fashioned by the distal ends of the tibia and bula. As a outcome, the bone ts tighter into its socket when the foot is dorsi exed and the wider surface of the talus strikes into the ankle joint than when the foot is plantar exed and the narrower a part of the talus is within the joint. The articular cavity is enclosed by a synovial membrane, which attaches around the margins of the articular surfaces, and by a brous membrane, which covers the synovial membrane and can be hooked up to the adjoining bones. The tibiocalcaneal half, which is extra central, attaches to the sustentaculum tali of the calcaneus bone. The posterior tibiotalar part attaches to the medial side and medial tubercle of the talus. The fourth part (the anterior tibiotalar part) is deep to the tibionavicular and tibiocalcaneal components of the medial ligament and attaches to the medial floor of the talus. Its apex is hooked up above to the medial malleolus and its broad base is attached below to a line that extends from the tuberosity of the navicular bone in front to the medial tubercle of the talus behind. The medial ligament is subdivided into 4 parts primarily based on the inferior factors of attachment. Fibrous cubonavicular joint Lateral ligament the lateral ligament of the ankle consists of three separate ligaments, the anterior talo bular ligament, the posterior talo bular ligament, and the calcaneo bular ligament. The posterior talo bular ligament runs horizontally backward and medially from the malleolar fossa on the medial facet of the lateral malleolus to the posterior strategy of the talus. The calcaneo bular ligament is hooked up above to the malleolar fossa on the posteromedial aspect of the lateral malleolus and passes posteroinferiorly to connect below to a tubercle on the lateral surface of the calcaneus. Navicular Calcaneocuboid joint Talocalcaneonavicular joint Trans ve rs e tars al jo int Cuboid Talus Subtalar joint Calcaneus Intertarsal joints the numerous synovial joints between the individual tarsal bones mainly invert, evert, supinate, and pronate the foot. Pronation is rotating the entrance of the foot laterally relative to the back of the foot, and supination is the reverse movement. Coronal view of ankle joint displaying posterior talo bular and calcaneo bular ligaments. The main joints at which movements occur embody the subtalar, talocalcaneonavicular, and calcaneocuboid joints. The talocalcaneonavicular and calcaneocuboid joints collectively type what is commonly referred to as the transverse tarsal joint. Intertarsal joints between the cuneiforms and between the cuneiforms and the navicular permit only restricted motion. Interos s eous talocalcaneal ligament 6 Talus Subtalar joint Calcaneus Clinical app Ankle accidents the anatomy of the ankle joint is advanced. However, from a clinical perspective it might be considered a bro-osseous ring oriented within the coronal airplane. The upper a part of the ring is formed by the distal ends of the bula and tibia, the distal joint between the tibia and bula, the tibio bular ligaments, and the ankle joint itself. The sides of the ring are fashioned by the ligaments that connect the medial malleolus and lateral malleolus to the adjacent tarsal bones. The medial (deltoid) ligament consists of the anterior tibiotalar, posterior tibiotalar, tibiocalcaneal, and tibionavicular components. The lateral ligament consists of the anterior talo bular ligament, calcaneo bular ligament, and the posterior talo bular ligament. In this damage, the anterior talo bular and calcaneo bular elements of the lateral ligament are disrupted. These structures, once disrupted, permit the ankle to invert often producing a fracture of the medial malleolus or a partial tear to the medial (deltoid) ligament. The subtalar joint allows gliding and rotation, that are concerned in inversion and eversion of the foot. Lateral, medial, posterior, and interosseous talocalcaneal ligaments stabilize the joint. The talocalcaneonavicular joint permits gliding and rotation movements, which together with related movements of the subtalar joint are concerned with inversion and eversion of the foot. The elements of the talocalcaneonavicular joint between the talus and calcaneus are: the anterior and center calcaneal aspects on the inferior surface of the talar head, and the corresponding anterior and middle talar sides on the superior floor and sustentaculum tali, respectively, of the calcaneus. The a half of the joint between the talus and the plantar calcaneonavicular ligament (spring ligament) is between the ligament and a facet on the inferior floor of the talar head. The joint between the navicular and talus is the biggest a half of the talocalcaneonavicular joint and is between the ovoid anterior finish of the talar head and the corresponding concave posterior floor of the navicular. The articular cavity is enclosed by synovial membrane, which is roofed by a brous membrane.
Manzanilla (German Chamomile). Shallaki.
- What is German Chamomile?
- Intestinal gas, travel sickness, nasal swelling (inflammation), hayfever, diarrhea, restlessness, sleeplessness, attention deficit-hyperactivity disorder (ADHD), fibromyalgia, stomach and intestinal disorders, menstrual cramps, and other conditions.
- How does German Chamomile work?
- Is German Chamomile effective?
- Preventing skin irritation caused by radiation used to treat cancer.
- Colic in breastfed infants when used in combination with other herbs.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96914
Constitutive activation of the distal renal epithelial Na+ channel muscle relaxant drug list discount 60 caps shallaki mastercard, independent of aldosterone yawning spasms discount 60 caps shallaki amex, happens in Liddle syndrome muscle relaxant kidney stones discount 60 caps shallaki with visa. Increased distal delivery of a nonreabsorbable anion also can potentiate the lumennegative gradient that drives K+ secretion muscle relaxant in india shallaki 60 caps buy without prescription. Fatigue, myalgias, and muscular weakness or cramps of the decrease extremities are frequent. Smooth muscle operate may also be affected and may manifest with complaints of constipation or frank paralytic ileus. Severe hypokalemia might result in complete paralysis, hypoventilation, or rhabdomyolysis. The applicable response to hypokalemia is to excrete <25 mEq/d of K+ in the urine. Urinary K+ excretion can be measured with a 24-hour urine collection or estimated by multiplying the spot urine [K+] by the whole every day urine output. A spot urine [K+] could also be useful (urine [K+] <15 mEq/L suggests appropriate K+ conservation), but the results may be confounded by quite a lot of components. Intracellular shifting and renal excretion of K+ are often closely linked with the acid-base status. Hypomagnesemia must also be sought in all hypokalemic sufferers and corrected to enable efficient K+ repletion. It is usually safer to appropriate the K+ deficit via the oral route when hypokalemia is gentle and the patient can tolerate oral administration. Oral doses of 40 mEq are typically well tolerated and may be given as often as every four hours. However, with growing severity of hypokalemia, this grossly underestimates the K+ necessary to normalize total K+ content material. In such cases, potassium supplementation ought to be increased and continued until serum levels rise. The maximum focus of administered K+ must be not extra than 40 mEq/L through a peripheral vein or 100 mEq/L through a central vein. Pseudohyperkalemia represents an artificially elevated plasma [K+] as a outcome of K+ motion out of cells instantly before or following venipuncture. Contributing elements embody repeated fist clenching, hemolysis, and marked leukocytosis or thrombocytosis. True hyperkalemia occurs on account of (a) transcellular shift, (b) increased exposure to K+, and most commonly, (c) decreased renal K+ excretion. Combinations of these mechanisms often underlie circumstances of hyperkalemia in scientific follow, and decreased renal excretion is nearly all the time some part of the pathophysiology. Familial periodic paralysis, mentioned beforehand, is a uncommon cause of hyperkalemia. In the setting of hyperkalemia, the kidney is able to producing a major urinary excretion of K+. Drugs may also be implicated in the genesis of hyperkalemia via quite a lot of mechanisms. Heparin and ketoconazole can also contribute to hyperkalemia by way of the decreased manufacturing of aldosterone, although these agents alone are typically inadequate to sustain a clinically important hyperkalemia. Severe hyperkalemia causes partial depolarization of the skeletal muscle cell membrane and may manifest as weak spot, doubtlessly progressing to flaccid paralysis and hypoventilation if the respiratory muscular tissues are concerned. High aldosterone levels, usually accompanied by excessive renin levels, counsel aldosterone resistance (pseudohypoaldosteronism) but may additionally be seen in K+-sparing diuretics. Acute remedy may encompass some or all of the following (the hypokalemic effect is additive). Albuterol could be administered in a dose of 10-20 mg as a steady nebulized remedy over 30-60 minutes. This could be achieved with the administration of saline in sufferers who seem quantity depleted. When given by mouth, the standard dose is 25-50 g blended with one hundred mL 20% sorbitol to prevent constipation. Sodium polystyrene sulfonate can additionally be administered as a retention enema consisting of fifty g resin in a hundred and fifty mL tap water. Enemas ought to be averted in postoperative patients due to the increased incidence of colonic necrosis, particularly following renal transplantation. Newer brokers corresponding to sodium zirconium cyclosilicate are being studied and have proven improved safety profiles in preliminary studies. Chronic therapy could contain dietary modifications to avoid excessive K+ foods (see Potassium, Hyperkalemia, Etiology section), correction of metabolic acidosis with oral alkali, the promotion of kaliuresis with diuretics, and/or administration of exogenous mineralocorticoid in states of hypoaldosteronism. Nearly 50% of serum calcium is ionized (free), whereas the rest is complexed to albumin (40%) and anions corresponding to phosphate (10%). It stimulates intestinal absorption of calcium and is certainly one of many elements that provide feedback to the parathyroid gland. Underlying disturbances to calcium metabolism are thus usually masked by compensatory mechanisms until the patient develops a P. Primary hyperparathyroidism causes most circumstances of hypercalcemia in ambulatory sufferers. It is a standard disorder, particularly in aged girls, in whom the annual incidence is roughly 2 in a thousand. Nearly 85% of instances are due to an adenoma of a single gland, 15% to hyperplasia of all four glands, and 1% to parathyroid carcinoma. Malignancy is responsible for most cases of hypercalcemia among hospitalized sufferers. Less widespread causes account for about 10% of circumstances of hypercalcemia: Increased vitamin D activity occurs with exogenous exposure to vitamin D or elevated era of calcitriol in persistent granulomatous ailments. The milk-alkali syndrome describes the acute or continual growth of hypercalcemia, alkalosis, and renal failure that may result from the ingestion of enormous portions of calcium-containing antacids. Hyperthyroidism, adrenal insufficiency, prolonged immobilization, Paget disease, and acromegaly could also be associated with hypercalcemia. Familial hypocalciuric hypercalcemia is a uncommon, autosomal dominant disorder of the calcium-sensing receptor, which is characterized by asymptomatic hypercalcemia from childhood and a family historical past of hypercalcemia. If serum calcium rises above 13 mg/dL, renal failure with nephrocalcinosis and ectopic gentle tissue calcifications are attainable. Osteopenia and frequent fractures may occur from the disproportional resorption of bone in hyperparathyroidism. Rarely, osteitis fibrosa cystica can develop when hyperparathyroidism is profound and extended, leading to "brown tumors" and marrow alternative. Diagnostic Testing the history and physical examination ought to give attention to (a) the duration of symptoms of hypercalcemia, (b) scientific evidence of any of the unusual causes of hypercalcemia, and (c) symptoms and indicators of malignancy (which virtually always precede malignant hypercalcemia). If hypercalcemia has been current for greater than 6 months with out an obvious etiology, primary hyperparathyroidism is nearly definitely the trigger. Serum calcium ought to be interpreted with data of the serum albumin, or an ionized calcium must be measured. Serum phosphorus is commonly decreased in hyperparathyroidism due to stimulation of phosphaturia, whereas Paget disease and vitamin D intoxication both are probably to have increased phosphorus ranges. Urine calcium may be elevated in main hyperparathyroidism due to a filtered load of calcium that exceeds the capability for renal reabsorption. If the household history and clinical picture are suggestive, sufferers with familial hypocalciuric hypercalcemia can be distinguished from patients with primary hyperparathyroidism by documenting a low calcium clearance by 24-hour urine assortment (<200 mg calcium per day) or fractional excretion of calcium (<1%). Maintenance fluids can be continued after reaching euvolemia to sustain a urine output of 100-150 mL/h. Loop diuretics can be used if indicators of quantity overload restrict additional saline administration while hypercalcemia persists. These brokers reduce paracellular reabsorption of calcium within the loop of Henle and thus may slightly improve calcium excretion. A hypocalcemic response is typically seen inside 2 days and should persist for 2 weeks or longer. Other options Calcitonin inhibits bone resorption and increases renal calcium excretion. Glucocorticoids are efficient in hypercalcemia as a end result of hematologic malignancies and granulomatous manufacturing of calcitriol.
Specifications/Details
Diagnostic Testing Diagnosis is normally clinical or by acute and convalescent serologic research spasms hindi meaning 60 caps shallaki generic with amex. Malaria is typically characterized by triphasic muscle relaxant anxiety buy 60 caps shallaki fast delivery, periodic (every forty eight hours for Plasmodium ovale and Plasmodium vivax) paroxysms of rigors followed by excessive fever with headache spasms gelsemium semper purchase shallaki 60 caps line, cough muscle spasms 72885 order shallaki 60 caps without a prescription, and nausea, then culminating in profuse sweating. Plasmodium falciparum malaria, essentially the most extreme type, is a possible medical emergency. Complicated, or severe, falciparum malaria is recognized in the setting of hyperparasitemia (>5%), cerebral malaria, hypoglycemia, lactic acidosis, renal failure, acute respiratory distress syndrome, or coagulopathy. Diagnosis is made by visualization of parasites on Giemsa-stained thick blood smears. Rapid diagnostic exams focusing on antigens widespread to all Plasmodium species as properly these specific to P. Alternatively, can use atovaquone-proguanil (250 mg atovaquone/100 mg proguanil) 4 tablets every day for 3 days. Rule out glucose-6-phosphate dehydrogenase deficiency earlier than initiating primaquine. Diagnosis is made by exclusion of different causes of lymphadenitis and by detection of antibodies to B. Culture-negative endocarditis has been discussed in the Cardiovascular Infections part (Clin Infect Dis 2005;41:1373). Symptom onset is 5-14 days after contact with infected animals or water contaminated with their urine. Anicteric leptospirosis, which accounts for many circumstances, is a biphasic illness that begins with influenza-like symptoms and proceeds to conjunctival suffusion and aseptic meningitis after a quick defervescent period. A minority of cases progress directly to Weil disease (icteric leptospirosis), with multiorgan failure manifested by severe jaundice, uremia, and hemorrhagic pneumonitis. Infection is usually preceded by direct contact with physique fluids of livestock animals, by eating unpasteurized dairy meals, or by inhalation of contaminated aerosolized particles. Fever may be spiking and accompanied by rigors but can additionally be relapsing and protracted. Physical exam may be nonrevealing, although lymphadenopathy, hepatomegaly, or splenomegaly could also be current. Diagnostic Testing Diagnosis is confirmed by isolation of the organism from blood or tissue culture. Gentamicin for 5-7 days or rifampin for six weeks may be alternate options to streptomycin (N Engl J Med 2005;352:2325). Tetanus toxoid ought to be administered if the patient has been beforehand vaccinated however has not obtained a booster in the last 5 years. Dog bites comprise 80% of animal bites, however only 5% of such bites become contaminated. For contaminated canine bite wounds, amoxicillin-clavulanate, or clindamycin plus ciprofloxacin, is effective. Because more than 80% of cat bites turn out to be infected, prophylaxis with amoxicillin-clavulanate should be routinely supplied. Wild animal bites: the need for rabies vaccination ought to be decided (see the following text). For most animal bites, amoxicillin-clavulanate is a good alternative for prophylaxis and empiric remedy. Monkey bites should be treated with acyclovir because of the danger of Herpesvirus simiae (B virus). Rabies Rabies causes an invariably deadly neurologic illness classically manifesting with hydrophobia, aerophobia, pharyngeal spasm, seizures, and coma. The need for rabies vaccination and immunoglobulin prophylaxis (see Appendix A, Immunizations and Postexposure Therapies) must be determined after any animal chew. In the United States, most up-to-date indigenous cases have been related to bats, whereas canine bites account for the overwhelming majority of human cases within the developing world. Regardless of species, if the animal is rabid or suspected to be rabid, the human diploid vaccine and rabies immunoglobulin should be administered immediately. Bites by home animals rarely require prophylaxis until the situation of the animal is unknown. Public well being authorities ought to be consulted to decide whether or not prophylaxis is recommended for different types of animal bites. A single case of survival after symptom onset using an aggressive coma-inducing regimen has been reported (N Engl J Med 2005;352:2508). Human Bites Human bites, significantly clenched-fist injuries, are vulnerable to an infection and different problems. The normal oral flora of humans consists of viridans streptococci, staphylococci, Bacteroides spp. Repeat blood cultures must be obtained after starting antibiotic therapy to demonstrate clearance of bacteremia. Management pointers are available from the Infectious Diseases Society of America (Clin Infect Dis 2009;forty nine:1). Gram-negative bacilli, together with Pseudomonas, ought to be coated broadly till species identification and susceptibilities are known. Vancomycin-resistant enterococci may require therapy with daptomycin or linezolid. Therapy in opposition to gram-negative bacilli ought to be guided by antibiotic susceptibility testing. Duration of antifungal therapy ought to be for 14 days after the final constructive blood tradition (Clin Infect Dis 2009;forty eight:503). A dilated ophthalmologic examination is advised to look for Candida endophthalmitis. Insertion web site or tunnel site infection (pus or important irritation on the site) Immunocompromised patients with fever, neutropenia, and hemodynamic instability. In addition to new or progressive pulmonary infiltrate, patients may present with fever, purulent respiratory secretions, tachypnea, and hypoxia. Optimal specimens are uncontaminated sterile body fluids (pleural or blood), bronchoscopy aspirates (cultured quantitatively), or aspirates from endotracheal tubes. Fiberoptic bronchoscopy may be diagnostic (quantitative cultures) and therapeutic (reexpansion of lung segment). Targeted therapy ought to be primarily based on culture results and in vitro sensitivity testing (Am J Respir Crit Care Med 2005;171:388; Clin Infect Dis 2010;51(S1):S42). Options include broad-spectrum agents similar to -lactam/lactamase inhibitor combinations, carbapenems, tigecycline, and polymyxins. Infectious illness session is recommended for classy multidrug-resistant infections. Included on this class are a quantity of highly deadly and easily produced microorganisms, which have the potential to be used as agents of bioterrorism and produce substantial sickness in massive populations by way of an aerosol route of exposure. Most of the doubtless ailments are rare, so a high index of suspicion is important to identify the first few circumstances. Inhalational anthrax (45% case-fatality rate) may result from inadvertent aerosolization of spores from contaminated animal merchandise. Notify native an infection control and public well being division immediately for confirmed cases. Uncomplicated cutaneous anthrax may be treated with oral ciprofloxacin 500 mg bid or doxycycline one hundred mg bid for a similar duration. Postexposure prophylaxis for people at risk for inhalational anthrax consists of oral ciprofloxacin 500 mg bid for 60 days after publicity. However, remaining viral stocks pose a possible bioterrorism threat to unimmunized populations. Lesions progress by way of stages of macules, deep vesicles, pustules, scabs, and everlasting pitting scars. The rash starts on the face and distal extremities, including palms and soles, with relative sparing of the trunk, and all lesions in a single area are in the identical stage of growth. No specific antiviral remedy is at present available, though several investigational medicine are in growth.
Syndromes
- Meets requirements for sodium-free
- Teach your child how to play safe and what to do if a tooth is broken or knocked out.
- Do you walk or stand for long periods of time?
- Headache
- Some birth defects
- MRI of the head or spine
- Long-term infection with hepatitis B or hepatitis C
- Shampoo your hair every day. Leaving the shampoo on your head for at least 5 minutes before rinsing may help.
- It is very important that you take the medicines prescribed to you.
Related Products
Additional information:
Diagnostic Procedures A skin biopsy must be carried out if particular person lesions persist for >24 hours to rule out urticarial vasculitis infantile spasms 8 month old 60 caps shallaki discount with amex. Biopsy of acute urticarial lesions reveals dilation of small venules and capillaries positioned in the superficial dermis with widening of the dermal papillae spasms after eating generic shallaki 60 caps on-line, flattening of the rete pegs muscle relaxant 16 buy shallaki 60 caps low price, and swelling of collagen fibers spasms 1983 imdb 60 caps shallaki discount with visa. Chronic urticaria is characterised by a dense, nonnecrotizing, perivascular infiltrate consisting of T lymphocytes, mast cells, eosinophils, basophils, and neutrophils. Angioedema exhibits related pathologic alterations in the deep, rather than superficial, dermis, and subcutaneous tissue. This trial ought to be done in the presence of a physician with epinephrine available. Careful consideration must be given to the elimination or substitution of each prescription or over-the-counter treatment or complement. If a affected person reacts to one medication in a class, the reaction probably shall be triggered by all drugs in that class. In patients presenting with hereditary and bought angioedema, a prompt evaluation of airway is important, especially in these presenting with a laryngeal assault. Medications If acute urticaria is associated with extra systemic signs corresponding to hypotension, laryngeal edema, or bronchospasm, treatment with epinephrine (0. First Line Acute urticaria and/or angioedema Second-generation antihistamines similar to cetirizine, fexofenadine, or loratadine must be administered to sufferers till the hives have cleared. A first-generation antihistamine such as hydroxyzine could additionally be added as a night dose if wanted to obtain control in refractory cases. Oral corticosteroids ought to be reserved for patients with moderate to extreme signs. If a patient presents with systemic signs, self-administered epinephrine must be prescribed for use within the case of anaphylaxis. Chronic urticaria A stepwise approach has been advised for the remedy of chronic urticaria (J Allergy Clin Immunol 2014;133(5):1270). Omalizumab: Proven safe and effective in a quantity of randomized clinical trials in patients with persistent urticaria not responsive to standard dose of H1 antihistamines Cyclosporine Other anti-inflammatory brokers, immunosuppressants, or biologics Optimal period of remedy has not been established; tapering medications after 3-6 months of symptom management has been advised. Hereditary and purchased angioedema (disorder of C1 inhibitor) Laryngeal assaults or severe stomach assaults: C1 inhibitor concentrate, icatibant, and ecallantide are first-line brokers. Secondary immunodeficiencies are also problems of elevated susceptibility to an infection but are attributable to an external supply. Predominantly antibody deficiencies: the defect is primarily within the capacity to make antibodies. Diseases of immune dysregulation: Autoimmunity and lymphoproliferation are characteristic manifestations in these disorders. Etiology Predominantly antibody immune deficiencies are thought to be caused by defects in B-cell maturation. Combined immunodeficiencies are brought on by faulty T-cell-mediated immunity and associated antibody deficiency. Secondary immunodeficiencies could be attributable to drugs (chemotherapy, immunomodulatory agents, corticosteroids), infectious brokers. Clinical suspicion should be increased by recurrent sinopulmonary infection, deep-seated infections, opportunistic infections, or disseminated infections in an in any other case healthy patient. Selective IgA deficiency is the most common immune deficiency, with a prevalence of 1 in 300-500 individuals. It includes a heterogeneous group of problems in which most sufferers current in the second to fourth decade of life with recurrent sinus and pulmonary infections and are found to have low and dysfunctional IgG, IgA, and/or IgM antibodies with poor response to immunizations. Patients could have associated gastrointestinal illness or autoimmune abnormalities (most commonly autoimmune hemolytic anemia, idiopathic thrombocytopenic purpura, pernicious anemia, and rheumatoid arthritis). There is an increased incidence of malignancy, particularly lymphoid and gastrointestinal malignancy. Specific antibody deficiency is defined as poor or absent antibody responses to polysaccharide antigens. Therapeutic approaches embody adequate antibiotic treatment for infections, pneumococcal conjugate vaccine, and sometimes immunoglobulin substitute. Patients usually have low levels of all immunoglobulin types and very low levels of B cells. Specific genetic defect is in Bruton tyrosine kinase, which is involved in B-cell maturation. Deficiencies of every of the IgG subclasses (IgG1, IgG2, IgG3, and IgG4) have been described. Isolated subclass deficiency without recurrent infections is of unknown scientific significance. Hyper-IgE syndrome (Job syndrome) is characterised by recurrent pyogenic infections of the pores and skin and decrease respiratory tract. The commonest organism involved is Staphylococcus aureus, but different bacteria and fungi have been reported. Patients present with recurrent infections and have associated pruritic dermatitis, coarse (lion-like) facies, development retardation, scoliosis, retention of main teeth, and hyperkeratotic nails. Laboratory data reveal the presence of normal levels of IgG, IgA, and IgM however markedly elevated ranges of IgE. Recurrent disseminated neisserial infections are related to a deficiency in the terminal complement system (C5-C9). Systemic lupus-like disorders and recurrent infection with encapsulated organisms have been associated with deficiencies in different elements of complement. Diagnosis is made by demonstration of defective respiratory burst with flow cytometry assay using dihydrorhodamine. Characteristic infections embody mycobacterial infections (including typical and atypical Mycobacterium) and Salmonella infections. Initial evaluation ought to concentrate on identifying attainable secondary causes of recurrent an infection similar to allergy, drugs, and anatomic abnormalities. Other specialized exams including genetic testing could additionally be wanted to make a definitive prognosis. Titers of particular antibodies are measured earlier than and at 4-8 weeks after immunization. However, these patients ought to be promptly treated at the first sign of an infection with an antibiotic that covers Streptococcus pneumoniae or Haemophilus influenzae. Numerous preparations of immunoglobulin can be found, all of which undergo viral inactivation steps. Possible unwanted effects embody myalgias, vomiting, chills, and lingering headache (due to immune complexmediated aseptic meningitis). Although vasopressin launch is predominately responsive to osmotic cues, quantity contraction may cause a nonosmotic release of vasopressin, resulting in a discount of renal water excretion. Clinically, this manifests as quantity depletion (hypotension, tachycardia) and volume expansion (peripheral or pulmonary edema). Na+ concentration displays the quantity of Na+ distributed in a set amount of water. This response is mediated by cardiovascular, renal, hepatic, and central nervous system sensors of the efficient circulating volume. The Euvolemic Patient In a euvolemic affected person, the aim of fluid and electrolyte administration is to maintain homeostasis. Patient weight, which can indicate internet fluid steadiness, should be monitored fastidiously. Minimum water requirements for every day fluid steadiness can be approximated from the sum of the required urine output, stool water loss, and insensible losses. The minimal urine output essential to excrete the day by day solute load is the amount of solute consumed each day (roughly 600-800 mOsm/d in a mean individual) divided by the maximum quantity of solute that could be excreted per liter of urine (maximum urine concentrating capacity is 1200 mOsm/L in wholesome kidneys). Insensible water losses from the skin and respiratory tract quantity to roughly 400-500 mL/d. The volume of water produced from endogenous metabolism (<250-350 mL/d) ought to be considered as well. The diploma of insensible loss might differ tremendously relying on respiratory price, metabolic state, and temperature (water losses increase by 100-150 mL/d for each degree of body temperature over 37�C).
Usage: gtt.
Evaluating renal perform also is beneficial given the increased prevalence of renal disease in diabetics muscle relaxants for tmj shallaki 60 caps with visa. Cardiovascular threat stratification could require different evaluations (see the earlier part spasms under breastbone shallaki 60 caps without prescription, Preoperative Cardiac Evaluation) spasms upper left abdomen order shallaki 60 caps with amex. If attainable muscle relaxant machine shallaki 60 caps line, the operation ought to be scheduled for early morning to minimize prolonged fasting. On the evening previous to surgical procedure, the regularly scheduled basal insulin ought to be continued. A lower in the final preoperative basal insulin dose may be thought-about on this circumstance. Caution ought to be exercised with the utilization of subcutaneous insulin within the intraoperative and critical care settings, as alterations in tissue perfusion could lead to variable absorption. Type 2 diabetes Treatment of type 2 diabetics varies according to their preoperative requirements and the complexity of the deliberate procedure (Med Clin North Am 2003;87:175). Type 2 diabetes managed with oral remedy Short-acting sulfonylureas and other oral agents must be withheld on the operative day. Other oral agents may be resumed when sufferers are tolerating their pre-procedure diet. Glucose values must be checked often and elevated levels (>180 mg/dL) can be handled with intermittent doses of short-acting insulin. Patients undergoing main procedures will sometimes require an insulin drip perioperatively. The ordinary insulin therapy can be reintroduced once oral consumption is established postoperatively. Earlier literature recommends aggressive glucose management within the important care setting (Diabetes Care 2008;31S:S12; N Engl J Med 2009;360:1283-1297). In a general medical-surgical population, recurring glucose values >200 mg/dL were related to a poor outcome (J Clin Endocrinol Metab 2002;87:978). Pending additional research, a objective of maintaining glucose levels <180 mg/dL within the postoperative setting seems reasonable. It ought to be famous that this will nonetheless require intensive remedies corresponding to insulin infusion. Patients receiving corticosteroids as anti-inflammatory therapy could hardly ever develop postoperative adrenal insufficiency. Levels >18 g/dL at 30 minutes typically counsel an intact hypothalamic-pituitary axis. For patients with major adrenal insufficiency, a stress stratification scheme has been developed, based mostly on skilled opinion. Although this usually entails eradicating quantity, some patients may be hypovolemic and require hydration. Patients being treated with hemodialysis ought to bear dialysis preoperatively, which is usually performed on the day previous to surgical procedure. Hemodialysis could be performed on the day of surgery as properly, however the chance must be considered that transient electrolyte abnormalities and hemodynamic changes publish dialysis can happen. Electrolyte abnormalities Hyperkalemia within the preoperative setting must be handled, notably because tissue breakdown related to surgical procedure could elevate the potassium stage additional postoperatively. Although chronic metabolic acidosis has not been related to elevated perioperative risk, some native anesthetics have decreased efficacy in acidotic patients. Preoperative metabolic acidosis should be corrected with sodium bicarbonate infusions or dialysis. The value of a preoperative bleeding time in predicting postoperative bleeding has been questioned (Blood 1991;77:2547). In patients with coexisting anemia, pink blood cell transfusions can enhance uremic bleeding. For patients with a history of prior uremic bleeding, preoperative desmopressin or conjugated estrogens (0. The possibility that bleeding is liable for a prerenal state deserves special consideration. It is impossible to decide day by day power requirements exactly with predictive equations due to the complexity of factors that have an effect on metabolic fee. Malnutrition and hypocaloric feeding could decrease resting power expenditure to values 15-20% beneath those anticipated for precise body measurement, whereas metabolic stressors, such as inflammatory illnesses or trauma, usually increase vitality necessities (usually by ~50% of pre-illness values). The Harris-Benedict equation provides an affordable estimate of resting energy expenditure (in kilocalories [kcal] per day) in healthy adults. The equation takes under consideration the impact of body size and lean tissue mass (which is influenced by gender and age) on energy necessities and can be utilized to estimate whole daily power needs in hospitalized sufferers: Men = sixty six + (13. Ideal body weight can be estimated primarily based on top: For males: 106 lb + 6 lb for every inch over 5 ft For girls, 100 lb + 5 lb for every inch over 5 ft Protein Protein intake of 0. Inadequate quantities of any of the essential amino acids lead to inefficient utilization. Illness increases the efflux of amino acids from skeletal muscle; nevertheless, rising protein consumption to >1. Essential fatty acids the liver can synthesize most fatty acids, however humans lack the desaturase enzyme needed to produce the -3 and -6 fatty acid sequence. Therefore, linoleic acid ought to constitute at least 2% and linolenic acid at least 0. Endogenous protein and glycerol from lipid stores can endure gluconeogenesis to supply glucose-requiring organs. Major minerals Major minerals are essential for ionic equilibrium, water balance, and normal cell function. Micronutrients (trace elements and vitamins) Trace components and nutritional vitamins are important constituents of enzyme complexes. Dietary reference intakes for vitamin A, vitamin K, arsenic, boron, chromium, copper, iodine, iron, manganese, molybdenum, nickel, silicon, vanadium, and zinc. Essentiality and toxicity in copper health danger evaluation: overview, update and regulatory considerations. Serum retinol binding protein as an indicator of vitamin A standing in cirrhotic patients with night blindness. Evaluation, remedy, and prevention of vitamin D deficiency: an Endocrine Society clinical apply guideline. Diarrhea in this setting could additionally be improved with oral cholestyramine given with the first meal of the day. An evaluation of fluid losses because of diarrhea, ostomy output, and fistula volume should be made to help decide fluid necessities. Intestinal mineral losses may be calculated by multiplying the volume of fluid loss by the fluid electrolyte focus (Table 2-5). A thorough history and bodily exam mixed with acceptable laboratory studies is the best strategy to consider nutritional status. Unintentional weight lack of >10% physique weight within the last 6 months is related to a poor clinical outcome (Am J Med 1980;69:491). Diagnostic Testing Perform laboratory studies to determine specific nutrient deficiencies solely when clinically indicated as a end result of the plasma concentration of many nutrients could not replicate true physique stores (Table 2-3). Although ranges of those plasma proteins correlate with medical consequence, inflammation and harm can alter their synthesis and degradation, limiting their usefulness for nutritional assessment (Crit Care Med 1982;10:305; Gastroenterology 1990;99:1845). Types of feedings Hospital diets include a regular food plan and those modified in both nutrient content material (amount of fiber, fat, protein, or sodium) or consistency (liquid, pur�ed, soft). There are ways in which meals consumption can typically be increased: Encourage sufferers to eat. They include nitrogen within the type of whole proteins and include blenderized food, milkbased, and lactose-free formulas. Other formulas can be found with modified dietary content together with high-nitrogen, high-calorie, fiber-enriched, and low-potassium/phosphorus/magnesium formulas. Although these formulation might have benefit in these with exocrine pancreatic insufficiency or brief intestine, pancreatic enzyme alternative is a cheaper, equally efficient intervention in most of these patients. Oral rehydration solutions stimulate sodium and water absorption by taking advantage of the sodium-glucose cotransporter current within the brush border of intestinal epithelium. Oral rehydration therapy (using 90-120 mEq/L solutions to keep away from intestinal sodium secretion and negative sodium and water balance) can be especially helpful in patients with brief bowel syndrome (Clin Ther 1990;12(suppl A):129).
Tags: shallaki 60 caps best, 60 caps shallaki order otc, 60 caps shallaki purchase with amex, purchase 60 caps shallaki mastercard, purchase 60 caps shallaki with mastercard, proven 60 caps shallaki, purchase shallaki 60 caps amex, best shallaki 60 caps, trusted shallaki 60 caps, order 60 caps shallaki visa, order shallaki 60 caps on line, shallaki 60 caps buy generic on line, 60 caps shallaki order free shipping, discount 60 caps shallaki amex, shallaki 60 caps generic without prescription, purchase shallaki 60 caps otc
9 of 10
Votes: 149 votes
Total customer reviews: 149
Customer Reviews
Vandorn, 22 years: In children with these mutations, B and T lymphocytes are absent and immunity is severely compromised. Nitric oxide synthase A member of a household of enzymes that synthesize the vasoactive and microbicidal Glossary 509 compound nitric oxide from L-arginine.
Norris, 48 years: In the classic pathway, the convertase is the main (b) component of C4 and C2 (C4b2b). Type 1 diabetes is brought on by a deficiency of insulin ensuing from immune-mediated destruction of the insulin-producing cells of the islets of Langerhans in the pancreas, and steady hormone substitute therapy is needed.
Roland, 64 years: The acute sickle chest syndrome is the commonest cause of demise both in kids and adults. For example, cancer immunotherapy entails promotion of active immune responses to tumor antigens or administration of anti-tumor antibodies or T cells to set up passive immunity.
Mortis, 49 years: The features of the gastrointestinal immune system depend on numerous T cells and antibody-secreting cells which might be in a position to recirculate back into the lamina propria and reply quickly to pathogens. These strings are able to embolizing to microvessels downstream and contributing to organ ischemia.
Runak, 44 years: Side results of D-penicillamine and mercaptopropionylglycine embrace fever, rash, arthritis, myelosuppression, hepatotoxicity, and vitamin B6 deficiency. Angioedema typically lasts 12-48 hours and happens in 40-50% of sufferers with urticaria.
Kent, 40 years: Oral rehydration remedy (using 90-120 mEq/L options to avoid intestinal sodium secretion and negative sodium and water balance) can be particularly helpful in patients with short bowel syndrome (Clin Ther 1990;12(suppl A):129). Some of the necessary discoveries in the area of cancer immunotherapy are summarized.
