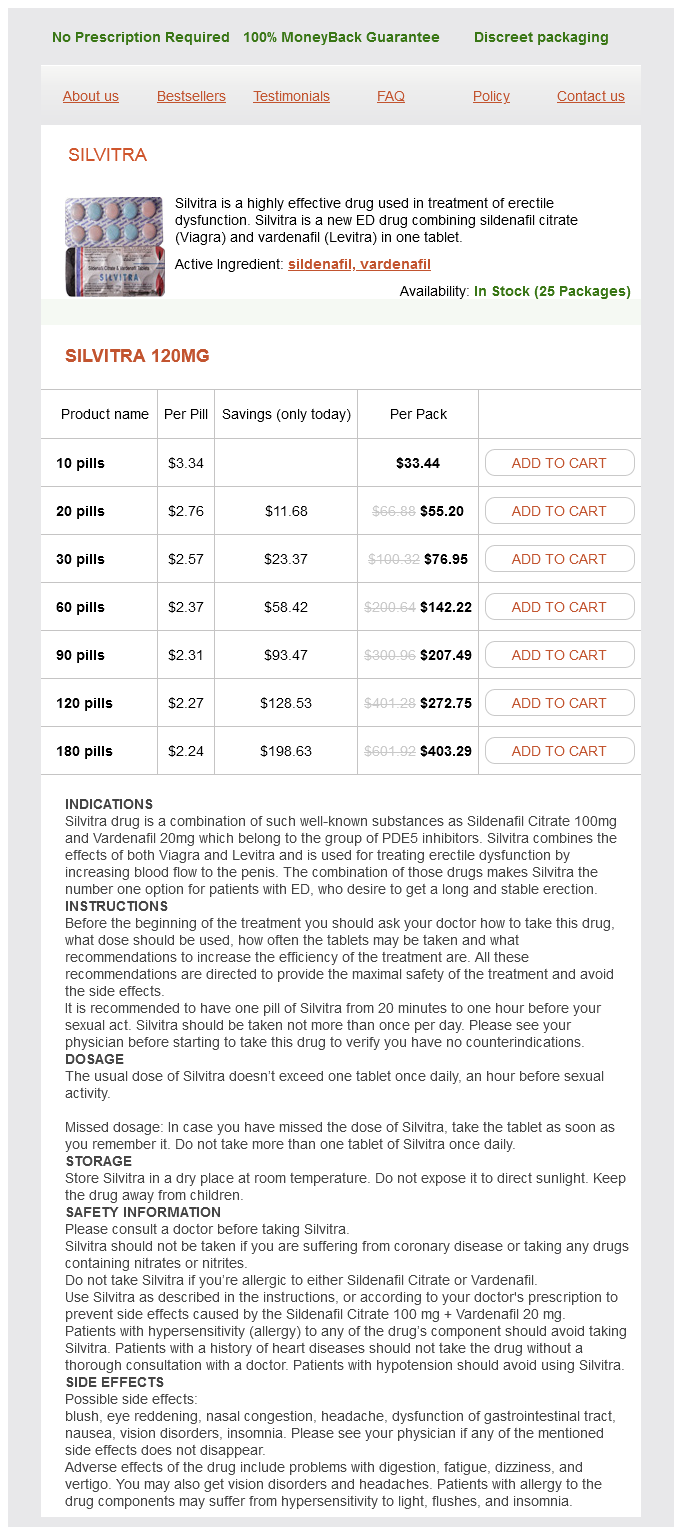
Silvitra 120mg
- 10 pills - $33.44
- 20 pills - $55.20
- 30 pills - $76.95
- 60 pills - $142.22
- 90 pills - $207.49
- 120 pills - $272.75
- 180 pills - $403.29
Silvitra dosages: 120 mg
Silvitra packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills
In stock: 642
Only $2,38 per item
Description
Gravity increases capillary stress significantly in dependent tissues (ankles impotence medication cheap 120 mg silvitra mastercard, sacral region) impotence treatments buy cheap silvitra 120 mg online, that are due to this fact vulnerable to severe erectile dysfunction causes buy silvitra 120 mg visa oedema erectile dysfunction diabetes symptoms silvitra 120 mg cheap on line. Albumin contributes disproportionately, as a outcome of Na+ ions attracted by its web negative cost (Gibbs�Donnan distribution). Conversely, when interstitial fluid is absorbed by capillaries after a haemorrhage, i and subglycocalyx g rise and ultimately halt the absorption course of. The Pi versus hydration curve (compliance curve) is steep at physiological hydrations, however flat in the oedema vary. The Starling pressures generally cause filtration, even in postcapillary venules, contrary to conventional educating. If capillary stress is reduced, by hypovolaemia or precapillary vasoconstriction, capillaries absorb interstitial fluid transiently; however, absorption tails off as i and g rise and Pi falls. Absorption is simply sustained in tissues the place the interstitium is flushed by an independent stream of liquid (intestinal mucosa during water absorption; renal peritubular capillaries; lymph nodes). In orthostasis, capillary strain is high in the dependent tissues, so filtration fee will increase and plasma volume falls. Exercise also reduces plasma quantity as a end result of interstitial crystalloids released by the energetic muscle fibres (lactate, K+) exert osmotic pressure across endothelial, water-only aquaporin channels, selling filtration into the energetic muscle. The lymphatic system preserves tissue quantity homeostasis by returning escaped plasma proteins and fluid to the circulation. Flow within the non-contractile preliminary lymphatics is driven by extrinsic compression, whereas the contractile primary lymphatic vessels pump lymph actively. The relaxation drains via efferent lymph trunks (chiefly the thoracic duct) into neck veins. Impaired lymph transport, whether hereditary, post-surgical or infective (filariasis), results in high-protein lymphoedema. Clinical oedema develops when the capillary filtration fee exceeds the lymphatic drainage price. Inflammatory swelling is brought on by increases in venular permeability to water and plasma proteins (Lp,). Also, net filtration pressure is increased by vasodilatation (Pc), an initial dip in interstitial strain (Pi, particularly in burns) and plasma protein leakage (i, g). The inflammatory hyperpermeability is due to the formation of intercellular and transcellular gaps in the venular endothelium and glycocalyx. This leads to hole formation by loosening intercellular junctions, presumably aided by endothelial cell contraction. The activated leukocytes release endothelium- and glycocalyx-damaging agents, such as free O2 radicals and proteases. Transcapillary change: function and importance of the interstitial fluid strain and the extracellular matrix. New and active position of the interstitium in command of interstitial fluid strain: potential therapeutic penalties. Starling: the formulation of his hypothesis of microvascular fluid exchange and its significance after 100 years. Mechanisms of neutrophil-dependent and neutrophil-independent endothelial cell harm. Changes of their contractile pressure (tone) cause the vessel to constrict or dilate as required. There are substantial variations in the best way contraction is regulated in several blood vessels, making this a difficult subject for instructor and student alike. Nevertheless, two principles apply to nearly all vessels: (1) contractile tension is ruled primarily by cytosolic Ca2+ focus; and (2) contractile tension is also regulated by modifications in sensitivity to Ca2+. Other key options, usually contrasting sharply with cardiac contraction, are as follows. Most generally, vascular myocytes might present a graded, sustained depolarization on activation, however no action potential generation. In some vessels, vascular myocytes fire action potentials on top of the underlying depolarized state. Basal potential Tension (g) four Patterns (1) and (2) have been known as electromechanical coupling, while pattern (3) is pharmacomechanical coupling. Membrane potential was altered by extracellular H+, extracellular K+, extracellular Ca2+, noradrenaline and hypoxia (�). In the smallest arteries, basal tone is spontaneous and referred to as myogenic tone. Vascular dilatation outcomes from a reduction within the tone, vascular constriction from an increase within the tone. The smooth muscle skinny filament is longer than in cardiac muscle, permitting larger shortening, and it lacks troponin, the cardiac Ca2+dependent regulatory protein. Instead, the actin filaments are rooted in dense bands on the inside cell membrane and in dense our bodies within the cytoplasm. These buildings are composed of -actinin, the protein forming the cardiac Z strains. A third kind of filament, the intermediate filament (meaning intermediate in thickness) acts as a cytoskeletal element; it hyperlinks the varied dense our bodies and dense bands, in order that the entire cell contracts as a single unit. Vascular intermediate filaments are composed mainly of the proteins desmin and vimentin. These components facilitate retailer release of Ca 2+ by agonists such as noradrenaline. This explains why Ca2+ channel blockers, similar to nifedipine, are good resistance vessel dilators. Fine, periodic, dark-staining components, thought to be Ca2+ release channels, lengthen from the subsarcolemmal sarcoplasmic reticulum in direction of the sarcolemma. The local, subsarcolemmal region could subsequently experience larger Ca2+ concentrations than the cytosol. Physiological Reviews 1984; 64(2): 455�77, with permission of the American Physiological Society. The receptor type is specified here as a result of agonists can have an opposite effect when sure to a different receptor type, by linking to a special signalling pathway throughout the cell. Six connexin molecules type a hemichannel (connexon), and the hemichannels of adjacent cells join endto-end, connecting the cytoplasm of the 2 cells. The spread of current is electrotonic, so it decays with distance and normally solely extends ~1 mm along the vessel longitudinally. The innermost myocytes of the tunica media additionally kind hole junctions with the endothelial cells. The caveolae are so quite a few that they improve the entire membrane area by up to 75%. Phase 1- Phasic rise in Ca2+ (store release) activates myosin (a) Relative drive in tonic phase 2 2 Phase 2, tonic � extracellular Ca2+ in ux and Ca2+ sensitization maintain the contraction Activated by noradrenaline 1 Ca2+ sensitization Activated by K+Cl- zero one hundred 200 Global cytosolic Ca2+ concentration (nM) (b) 12. Whether spontaneous or evoked, regulatory mechanisms exist to increase the tone (vasoconstriction) or scale back it (vasodilatation; see Section 12. The impact of a depolarizing focus of extracellular K+Cl- was much less sustained (lower, dashed black line). After the initial, transient section of retailer launch, Ca2+ wave frequency and magnitude decline, decreasing the global average [Ca2+]; yet, the noradrenaline-induced contraction is maintained (tonic phase). This exhibits that the noradrenaline-triggered pathway raises the sensitivity to Ca2+. Likewise, H1 receptors elicit vasoconstriction, whereas H 2 receptors elicit vasodilatation. The mild chain is a element of the myosin head concerned in crossbridge formation with actin, and vascular myosin only varieties crossbridges when the light chain is phosphorylated (unlike striated muscle myosin). Degree of shortening the vascular myocyte can shorten by a half or more, whereas striated muscle fibres shorten by solely about one third. The muscle is in effect locked into the crossbridged state, in an analogous way to the latch muscle of a bivalve shell. Duration of contraction the sustained nature of vascular contraction is remarkable; many arterioles and arteries keep tone throughout life. Extracellular Ca 2+ enters the myocyte via Ca 2+- Myosin light-chain kinase prompts the myosin motor A rise in cytosolic Ca2+ concentration causes the formation of Ca2+calmodulin complicated; calmodulin is a cytoplasmic protein, associated to troponin C, that binds four Ca2+ ions. Due to the comparatively small however steady inflow of Ca 2+ via Ca 2+ channels in the basal state, the sarcolemmal Ca 2+ pumps should expel Ca 2+ repeatedly, in any other case Ca 2+ would accumulate in the cell.
Citrus Flavones (Grapefruit). Silvitra.
- Are there safety concerns?
- Asthma, lowering cholesterol, hardening of the arteries (atherosclerosis), preventing cancer, weight loss, psoriasis, muscle fatigue, promoting hair growth, toning the skin, reducing acne and oily skin, treating headaches, stress, depression, infections, digestive complaints in people with eczema, yeast infections (as a vaginal douche), and other conditions.
- Are there any interactions with medications?
- Dosing considerations for Grapefruit.
- How does Grapefruit work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96909
The trunk divides into the proper and left pulmonary arteries erectile dysfunction pills that work generic silvitra 120 mg without prescription, which provide every lung erectile dysfunction 40 over 40 purchase 120 mg silvitra otc. Progressive branching leads to erectile dysfunction treatment viagra purchase silvitra 120 mg without prescription tiny blood vessels erectile dysfunction drugs south africa discount 120 mg silvitra amex, called capillaries, within the walls of the minute air sacs of the lungs (alveoli). Inhaled O2 diffuses into the blood, raising its O2 content from ~150 mL L-1 (mixed venous blood, resting human) to ~195 mL L-1. The oxygenated blood returns through the pulmonary veins and passes via the left atrium into the left ventricle. Four pulmonary veins return oxygenated blood from the lungs to the left facet of the center, completing the short, low-pressure pulmonary circulation. Bronchial venous blood drains anomalously into the left atrium, barely desaturating it. The left coronary heart perfuses the systemic circulation the left ventricle contracts simultaneously the right ventricle and ejects the same volume of blood, however at a a lot greater strain. Popliteal artery (knee, decrease leg) Wall/lumen 2 mm/25 mm Aorta 1 mm /4 mm Muscular conduit artery Arteriole Capillary Venule 30 �m /30 �m zero. The thickness of the wall relative to the lumen is best in arterioles, though the ratio varies with vascular tone. The drainage of the primary lymphatic vessels, the thoracic and proper lymphatic ducts, into the neck veins, is shown. The lymphatic system develops as an outgrowth of the venous system throughout embryogenesis. Right inside iliac vein Femoral vein (valves) Pelvic viscera, genitalia Left external iliac vein (valves) Popliteal, long and brief saphenous veins of leg (many valves) 1. Cardiac output therefore equals stroke quantity (the quantity ejected per contraction) multiplied by heart rate (the variety of contractions per minute). In a resting adult, the stroke quantity is often 70�80 mL and the heart price is 60�75 bpm. The output can increase significantly in response to elevated peripheral O2 demand, rising four- to fivefold during strenuous human exercise. How this increase is brought about, by way of autonomic nerves and physical distension, is described in Chapters 3�6. However, this egalitarian precept is overridden in the kidneys as a end result of their excretory operate requires a excessive blood move. The kidneys account for under 6% of human O2 consumption, but they obtain 20% of the cardiac output to generate an adequate excretion of water and urea. Arterial pressure is pulsatile as a result of the center ejects blood intermittently (systole), with rests in-between (diastole). Cardiac output distribution (rest) Other 10% Skin 8% Liver and intestine 25% A easy regulation hyperlinks move, pressure and conductance Although arterial strain and move pulsate, many elements of the circulation are best understood by using average ranges. To get at the primary rule governing move, allow us to contemplate a steady, non-pulsatile flow of water or plasma alongside a protracted inflexible tube, driven by a continuing stress head. Under these situations, flow Q is proportional to the pressure drop between the inlet (pressure P1) and outlet (pressure P2): Skeletal muscle 20% Kidneys 20% Brain 13% Q (P1 - P2) (1. The distribution of cardiac output between tissues is actively adjusted to match changing calls for. For instance, during train the fraction of the output that goes to skeletal muscle can be increased to ~80%. The wider the tube, the higher the conductance and the bigger the move generated by a given strain gradient. Thus, a big artery has a a lot bigger conductance and carries an even bigger circulate than a narrow arteriole. The hydraulic resistance of a tube is simply the inverse of its conductance (ease of flow); 7 Overview of the cardiovascular system 120 current = voltage difference/electrical resistance. The bigger the resistance, the larger the distinction in strain needed to drive a given circulate. Resistance is low in broad vessels, such because the named arteries and veins, and is excessive in slim vessels, such as arterioles. The drop in stress throughout a given class of vessel is thus an index of its resistance. In this way we all know that, in a resting human, the named giant arteries account for under 2% of the total resistance of the systemic circulation; the smallest arteries and the arterioles ~60%; the capillaries ~20%; and the venous system ~15%. Pressure (mmHg) 80 40 (Pulmonary artery) 0 Total cross-sectional area (cm2) Blood velocity (cm s-1) 40 Aorta 23 20 (mean) Vena cava 15 zero one thousand 100 10 Aorta four 0 Vena cava 7 the resistances of tubes in collection summate When two tubes are joined in sequence (end-to-end), the resistances add up. Consequently, though the resistance of the aorta is low, the resistance of the systemic circulation is excessive, because of the extra high resistances of the narrow arterioles and capillaries. Consequently, a low pulmonary arterial pressure suffices to drive the cardiac output through the lungs. The same blood circulate passes every vertical dashed line per minute, namely the cardiac output. Mean velocity is blood move divided by the cross-sectional area of the vascular mattress (see text). For example, once we salivate, the blood circulate to the salivary gland increases tenfold, as a end result of the vascular resistance of the gland is reduced to one tenth of its former worth via arteriolar vasodilatation; the arterial strain driving the circulate is unchanged. Changes in vascular resistance are brought about by the contraction and rest of the slim, terminal branches of the arterial system, so we should subsequent contemplate the construction of blood vessels. Branching slows down the blood Capillary numbers are colossal; the capillaries of an grownup human would girdle the earth if laid end-to-end (40 000 km). The whole cross-sectional space of the vascular system at a given branch stage is the number of vessels n instances the cross-sectional space of an individual vessel, r 2. As blood traverses the arterial tree, the rise in n through branching outweighs the reduction in vessel measurement, r 2. Consequently, the whole cross-sectional area of the circulation will increase from aorta to capillary bed (Table 1. The broadening of the circulation with branching is necessary, as a end result of it slows down the blood, simply as the present in a river slows down when the river banks widen. The blood velocity (cm s-1) at a department degree equals the total flow (cm3 s-1), specifically the cardiac output, divided by the entire crosssectional area of the branches (cm 2): velocity = flow/area. It consists of spindle-shaped, smooth muscle cells, arranged helically and embedded in a matrix of elastin and collagen fibres. Two sheets of elastin, referred to as the internal and exterior elastic laminae, mark the boundaries of the media. Intimal endothelial cells ship processes through the inner elastic lamina in locations, to make contact with clean muscle cells. In limb veins, the adventitia incorporates nociceptive nerve fibres, which mediate the pain of thrombophlebitis. Embryonic blood vessel formation, or vasculogenesis, is managed by signalling molecules. Vasculogenesis begins at two websites, one within the yolk sac and one within the embryo correct. The intima is a sheet of flattened endothelial cells resting on a thin layer of connective tissue. Smooth muscle cells differentiate under the influence of transforming progress issue beta, and are recruited to blood vessels by an endothelial secretion, platelet-derived development factor. Endothelial membrane proteins referred to as ephrins determine which tubes turn into arteries, versus veins. Elastic arteries accommodate the stroke volume and smooth the move the guts ejects blood only throughout systole. Therefore, if arteries have been completely inflexible, there can be no peripheral blood move throughout diastole. This potential downside is circumvented by the distensibility of the largest arteries, which is caused by an abundance of elastin (Table 1. The distensibility conferred by elastin enables the aorta, iliac arteries and pulmonary trunk (diameter 1�2 cm in humans) to act as momentary blood storage vessels; they increase by ~10% throughout every heartbeat to accommodate the ejected blood. On this foundation, the following main lessons of vessel are recognized: elastic arteries; conduit and feed (muscular) arteries; resistance vessels; exchange vessels; capacitance vessels. Smooth muscle 25 60 0 20 Elastin tissue forty 10 zero zero Collagen 27 20 5 (basal lamina) 60 5 10 ninety five 20 10 In each class of vessel, the structure of the wall is specially adapted to its role, as follows. The elastic artery wall is thus a composite materials, comparable in lots of respects to a car tyre; the rubber/elastin allows growth as much as a sure quantity, past which increasing tension in inelastic fibres prevents overexpansion.
Specifications/Details
Comparative activity of amantadine and ribavirin towards influenza virus in vitro: potential medical relevance what age does erectile dysfunction happen buy discount silvitra 120 mg online. A potential double-blind research of unwanted effects associated with the administration of amantadine for influenza A virus prophylaxis erectile dysfunction books 120 mg silvitra cheap mastercard. Uncoating of a rimantadine-resistant variant of influenza virus in the presence of rimantadine erectile dysfunction doctor in philadelphia silvitra 120 mg buy visa. Anti-influenza A exercise of mixtures of amantadine and ribavirin in ferret tracheal ciliated epithelium impotence signs order silvitra 120 mg visa. Anti-influenza A virus activity of amantadine hydrochloride and rimantadine hydrochloride in ferret tracheal ciliated epithelium. Toxicity of amantadine and rimantadine for the ciliated epithelium of ferret tracheal rings. Previous creatinine ranges safely predict amantadine dose for influenza A outbreak control. Structure of the amantadine binding website of influenza M2 proton channels in lipid bilayers. Rimantadine pharmacokinetics in wholesome subjects and sufferers with end-stage renal failure. Meta-analysis: amantadine might lower the efficacy of pegylated interferon plus ribavirin in treatmentnaive hepatitis C genotype 1 patients. Differences in conductance of M2 proton channels of two influenza viruses at high and low pH. Bioequivalence of two rimantadine pill formulations in wholesome male volunteers after single dose administration. Evidence that the amantadine-induced, M2-mediated conversion of influenza A virus hemagglutinin to the low pH conformation occurs in an acidic trans Golgi compartment. Inhibition of lymphocyte proliferation by amantadine and its isomer, 2-aminoadamantane; influence on Lyt-2 + Tcells whereas sparing L3T4 + Tcells. Occurrence of opposed effects and excessive amantadine concentrations with influenza prophylaxis in the nursing house. Adamantane-resistant influenza a viruses in the world (1902�2013): frequency and distribution of M2 gene mutations. Emergence of rimantadine-resistant virus inside 6 days of beginning rimantadine prophylaxis with oseltamivir treatment of symptomatic instances. The transmembrane area of influenza A M2 protein varieties amantadine-sensitive proton channels in planar lipid bilayers. Neutron diffraction reveals the location of amantadine blockade within the influenza A M2 ion channel. Investigation of a latest rise of dual amantadine-resistance mutations in the influenza A M2 sequence. Common emergence of amantadine- and rimantadine-resistant influenza A viruses in symptomatic immunocompromised adults. Plasmodium falciparum: results of amantadine, an antiviral, on chloroquine-resistant and delicate parasites in vitro and its affect on chloroquine exercise. Determination of amantadine in biological fluids using simultaneous derivatization and dispersive liquid-liquid microextraction followed by gasoline chromatographyflame ionization detection. A area trial of amantadine prophylaxis in naturally occurring acute respiratory illness. Reversion of influenza A (H3N2) from amantadine-resistant to amantadine-sensitive by further reassortment in Japan through the 2006�2007 influenza season. Alteration within the antigenic construction of M1 protein of influenza A virus mutant resistant to a new antiviral compound mopyridone. Rimantadine and oseltamivir reveal synergistic mixture effect in an experimental infection with type A (H3N2) influenza virus in mice. Protective effect of 1-adamantanamine hydrochloride on influenza A2 infection in the family environment. Study of 1-adamantanamine hydrochloride used prophylactically in the course of the Hong Kong influenza epidemic in the household setting. Therapeutic effect of l-adamantanamine hydrochloride in naturally occurring influenza A Aper Hong Kong an infection. Gender and age as factors within the inhibition of renal clearance of amantadine by quinine and quinidine. Amantadine penetration into cerebrospinal fluid of a child with influenza A encephalitis. Resistance-mutation (N31) effects on drug orientation and channel hydration in amantadinebound influenza A M2. Influence of amantadine resistance mutations on the pH regulatory operate of the M2 protein of influenza A viruses. Inhaled zanamivir versus rimantadine for the management of influenza in a highly-vaccinated long-term care population. The effects of chloroquine and different weak bases on the buildup and efflux of digoxin and ouabain in HeLa cells. Antiviral resistance in influenza viruses-implications for administration and pandemic response. Enhancement of exercise in opposition to influenza viruses by combos of antiviral agents. Comparative toxicity of amantadine hydrochloride and rimantadine hydrochloride in wholesome adults. Therapeutic results of aerosolized amantadine in naturally acquired an infection as a result of influenza A virus. Emergence and transmission of influenza A viruses resistant to amantadine and rimantadine. Differences in side-effects of amantadine hydrochloride and rimantadine hydrochloride relate to variations in pharmacokinetics. Comparative single-dose pharmacokinetics of amantadine hydrochloride and rimantadine hydrochloride in younger and elderly adults. Oral rimantadine hydrochloride remedy of influenza A virus H3N2 subtype infection in adults. Combined interferon-alpha 2, rimantadine hydrochloride, and ribavirin inhibition of influenza virus replication in vitro. Recovery of drug resistant influenza A virus throughout therapeutic use of rimantadine. Amantadine-resistance among H5N1 avian influenza viruses isolated in northern China. Oseltamivir and threat of lower respiratory tract complications in patients with flu signs: a meta-analysis of 11 randomized clinical trials. Efficacy of rimantadine hydrochloride in the therapy of influenza an infection of mice. Effect of rimantadine on cytotoxic T lymphocyte responses and immunity to reinfection in mice contaminated with influenza A virus. Differential patterns of amantadine-resistance in influenza A (H3N2) and (H1N1) isolates in Toronto, Canada. Pharmacokinetics of amantadine hydrochloride in topics with regular and impaired renal perform. Histidines, heart of the hydrogen ion channel from influenza A virus: towards an understanding of conductance and proton selectivity. Backbone structure of the amantadine-blocked trans-membrane domain M2 proton channel from Influenza A virus. The chemical and dynamical influence of the anti-viral drug amantadine on the M2 proton channel transmembrane domain. The efficacy of amantadine and different antiviral compounds towards two salmonid viruses in vitro. Susceptibility of highly pathogenic A(H5N1) avian influenza viruses to the neuraminidase inhibitors and adamantanes. Tromantadine inhibits a late step in herpes simplex virus sort 1 replication and syncytium formation. How amantadine and rimantadine inhibit proton transport in the M2 protein channel.
Syndromes
- Ultrasound of the bladder
- Chronic kidney disease
- Prothrombin time
- Increased sleepiness, difficulty waking up
- Angiogram
- Tremors
Related Products
Additional information:
Uncoating is the likely target of adamantanes for some viruses erectile dysfunction treatment clinics buy silvitra 120 mg free shipping, similar to vesicular stomatitis virus erectile dysfunction for young adults silvitra 120 mg order overnight delivery, which are susceptible to the drug at concentrations greater than can be achieved safely in humans (Superti et al erectile dysfunction treatment singapore silvitra 120 mg buy discount online. However erectile dysfunction doctors in queens ny buy 120 mg silvitra fast delivery, amantadine does appear to have a mechanism of action separate to blocking the M2 pore protein. Newly synthesized viral proteins are then transported to the cell floor through the acidic trans-Golgi. The M2 membrane protein of influenza A facilitates these processes by once more functioning as an ion channel (Pinto, 1992). Amantadine has been reported to inhibit the release of influenza A virions from the surface of cells contaminated with the Rostock (H7N1) strain (Sugrue et al. The M2 protein regulates pH gradients across membranes within the trans-Golgi (Grambas et al. No variations in matrix protein M1 have been observed in rimantadine-resistant and vulnerable strains of influenza A (H3N2) (Galabov et al. The really helpful dosage of amantadine for prophylaxis or therapy of adults < sixty five years of age is a hundred mg given twice every day, usually at breakfast and lunch (see Table 265. However, in a examine of wholesome adults aged between 18 and 55 years, prophylactic efficacy of amantadine was maintained at a decrease dose of one hundred mg/day (Reuman et al. Experience with amantadine and rimantadine suggests that, for biggest efficacy, remedy of patients with influenza A an infection must be commenced within 48 hours of onset of signs (Mostow, 1987), ideally earlier. Newborn infants and children For children aged 5�9 years old, the amantadine dose is 100 mg day by day; older kids (> 10 years old) can be given the adult dose of 100 mg twice daily (Novartis, 2014), though if a 10- to 13-year old youngster weighs < 40 kg, a dose of 5 mg/kg day by day is really helpful (Fiore et al. It is not possible to give amantadine to children < 5 years old as a result of the really helpful dosage of amantadine for prophylaxis or therapy was 5 mg/kg of the liquid formulation every day and that formulation is not available. The dose of rimantadine for prophylaxis of kids is 5 mg/kg daily, to not exceed one hundred fifty mg/day. Small-particle aerosol administration of amantadine has been effective for the treatment of experimental influenzal an infection in mice; both amantadine and rimantadine have additionally been administered as a small-particle aerosol to humans (Knight et al. One case report means that amantadine may be teratogenic in humans (Nora et al. Age Antiviral Amantadinea Treatment and prophylaxis Rimantadinec Treatment and prophylaxis a 1�9 years 4. Other individuals with less severe hepatic or renal dysfunction taking > one hundred mg/kg/day should be observed carefully, and the dosage ought to be reduced or the drug discontinued, if essential. The present dosing regimen is 100 mg as quickly as daily for creatinine clearances > 36 ml/minute; every other day for 26�35 ml/minute, each three days for 15�25 ml/minute and one hundred mg once weekly for creatinine clearances < 15 ml/minute (Novartis, 2014). The serum half-life of amantadine in sufferers with renal failure has been reported to be extended for so lengthy as 33 days (Horadam et al. That examine advised a dosage routine of amantadine for patients with renal failure, which was designed to yield serum concentrations at a steady state of zero. Renal perform must be intently monitored with dosage changes made as necessary, although some recent knowledge recommend that a single creatinine measurement up to 1 yr before therapy is begun is sufficient for short courses of therapy or prophylaxis (Buxton et al. Negligible amounts (2�5%) of amantadine and rimantadine are eliminated by hemodialysis (Horadam et al. For rimantadine, nonetheless, a examine of 6 young (mean age 27 years) and 10 aged (mean age 71. However, for healthy individuals aged > 65 years, a dose of a hundred mg day by day is really helpful (Fiore et al. Serum ranges may be measured by high-performance liquid chromatography (Zhou et al. Bioavailability Given orally, amantadine has a mean relative bioavailability reportedly ranging from 55% to 94% (Aoki et al. The oral bioavailability of rimantadine in mice and canines ranges from 60% to 99% (Hoffman et al. The relative bioavailability of rimantadine syrup can also be excessive (96%) (Wills et al. Protein binding of amantadine is < 70% and is unrelated to focus (Liu et al. For both prophylaxis and treatment of elderly persons amantadine must be given at a dose of a hundred mg as soon as daily. This In healthy adults given oral amantadine, the height serum stage is usually reached inside 1�4 hours. Amantadine Young Relative oral bioavailability (%) Vd (l/kg at 200 mg/day) Plasma protein binding (%) Clearance (ml/min/kg) Plasma or whole Renal Nonrenal Plasma t� (hours) Therapeutic vary (ng/ml) Cmax 200 mg/day a hundred mg/day Ctrough 200 mg/day a hundred mg/day 302 � 80 - - 301 � seventy five 300 � seventy five - 310 � 87 - 475 � 110 - - 362 � 158 416 � 108 - 447 � 108 - 5. Pharmacokinetics of single 100-mg doses of amantadine given orally to healthy volunteers. Median (range) of indicated variable Variable Cmax (ng/ml) 361 (286�482) tmax (hours) 1. Single-dose pharmacokinetics of amantadine and rimantadine in healthy young adults. Rimantadine takes longer to achieve maximum plasma concentration than amantadine, usually peaking 2�6 hours after oral absorption (Wills et al. After multiple doses of 100 mg twice daily given to wholesome young adults, steady-state peak and trough concentrations of rimantadine in plasma are within the range of 0. The regular serum half-life of amantadine has been variously reported to vary from 7 to 24 hours (mean 12�16 hours) (Aoki et al. The half-life of rimantadine is significantly longer, starting from 25 to > 36 hours in adults and youngsters (Hayden et al. In kids with an average age of 38 months, amantadine given at 5 mg/kg/day resulted in imply serum concentration of zero. In hospitalized infants 1�10 months of age receiving oral rimantadine at 3 mg/kg/day, steady-state rimantadine Cmax ranged from 0. In one other research of infants receiving three mg/kg every day, the steady-state plasma concentrations of rimantadine ranged from 0. In kids aged 5�8 years, the mean serum half-life of rimantadine was 25 hours (Anderson et al. Peak serum levels occurred at about 2 hours in each teams, and the elimination half-lives (mean 14. Mean (plus or minus normal deviation) trough serum ranges obtained from residents in a nursing house who obtained amantadine prophylaxis (100 mg/day) for 35 days were 309 � 167 ng/ml (Arden et al. In one other examine, the same dose of amantadine in a inhabitants whose imply age was 87 years resulted in median (range) serum levels of 591 ng/ml (128�5810 ng/ml), suggesting that this dose should be too excessive in some nursing home residents (Degelau et al. Prolonged administration of rimantadine in a dose of 200 mg/day to aged residents of nursing properties resulted in a mean serum degree of 1. However, in a examine of persons older than 60 years who obtained a single 200-mg dose of rimantadine, Hayden and colleagues (1985) discovered the height serum focus to be 0. In a 3rd study, the mean peak concentrations of rimantadine in plasma of healthy adults aged 50�60 years, 61�70 years, and 71�79 years, handled with 200 mg/day for 9. The peak elimination half-life was additionally comparable within the three groups, once more suggesting no main distinction in pharmacokinetics of rimantadine in this population (Tominack et al. By 1 hour after a 30-minute aerosol administration (1 g/100 ml), levels of the drug in nasal wash samples were 1. Later studies confirmed that aerosol administration of amantadine in the identical dosage produces concentrations of > 20 �g/ml in respiratory secretions (Hayden et al. Nasal wash ranges are much larger than these obtained with oral amantadine; these have been 0. Aerosol administration of rimantadine ends in imply peak plasma ranges which are about 10-fold lower than those achieved after oral administration of 200 mg (0. In a examine of healthy young adults, the volume of distribution was significantly larger in smokers than in nonsmokers (Wong et al. A excessive degree of tissue binding explains their low serum levels and the small amounts of drug removed by hemodialysis. In an experimental mannequin, roughly two thirds of amantadine added to plasma samples turns into protein bound (Liu et al. A examine of intraperitoneal, 99mTc-labeled amantadine in rats showed the best uptake in ovary, spleen, thyroid, muscle, and gastrointestinal tissues (Oliveira et al. Therapeutic concentrations of amantadine have been found in the cerebrospinal fluid of a handled youngster with influenza A encephalitis (Geskey and Thomas, 2004). Nasal mucus levels of the drug rose over 8 hours, regardless of a decline in plasma concentration. The most concentrations of rimantadine and amantadine in nasal secretions were found to be related (mean of 0.
Usage: b.i.d.
Arteriosclerosis is the diffuse stiffening of ageing elastic arteries erectile dysfunction doctor omaha 120 mg silvitra safe, due primarily to changes within the tunica media erectile dysfunction doctors raleigh nc 120 mg silvitra with amex. Pros and cons of pulse method the variable nature of arterial compliance can introduce some ambiguity erectile dysfunction otc 120 mg silvitra purchase with mastercard, as can run-off throughout ejection johns hopkins erectile dysfunction treatment silvitra 120 mg buy discount on line, since runoff will increase when peripheral resistance falls. Nevertheless, changes in pulse pressure, recorded with nothing extra refined than a wrist watch and sphygmomanometer cuff, provide a handy, immediate bedside indication of modifications in cardiac output in a person from hour to hour, for instance, during recovery from an acute haemorrhage. At a more sophisticated stage, computer models make reasonably accurate computations of acute adjustments in stroke quantity from continuous recordings of arterial strain. The latter may be measured repeatedly by an digital, finger volume-clamp technique (see Finapress, Section eight. An oximeter is a small gadget that shines a light-weight via superficial tissue, usually an earlobe or finger, and measures the transmitted gentle utilizing a photoelectric cell. Red cells take in a few of the gentle, and oxyhaemoglobin absorbs a different wavelength to deoxyhaemoglobin. Arterial compliance C is defined as the rise in blood quantity in the arterial system, V, that outcomes from a given increase in arterial stress, P. From the above definitions, pulse pressure P = stroke volume (minus the run-off throughout ejection)/arterial compliance). Arterial compliance falls as strain increases, as a end result of the tensing of collagen within the artery wall. Consequently, a rise in mean arterial stress also causes a rise in pulse strain. Arterial compliance declines with age because of arteriosclerosis, a diffuse stiffening of the media of elastic vessels. The difference between the radioactive content of the ventricles in diastole and systole is used to calculate the ejection fraction and stroke volume. Aortic stroke quantity can be estimated, albeit quite indirectly, from the impedance oscillation. Under general anaesthesia, a miniature, semicircular magnet is surgically implanted, with its magnetic poles on either aspect of the blood vessel of curiosity, for instance, the pulmonary artery. Blood is an electrical conductor, and because it cuts via the magnetic area it induces an electrical potential, which is measured. To convert mean velocity to flow, the internal diameter of the vessel is required. Being small, an electromagnetic flowmeter may be left inside a aware animal, transmitting a sign by telemetry (radio waves). In this fashion, much has been learned in regards to the regulation of stroke volume in unfettered, acutely aware animals, similar to dogs operating on a treadmill. Impedance cardiography Chest and neck leads move a small present through the thorax to measure its cyclically altering electrical resistance (impedance). Aortic blood quantity increases and decreases over each cardiac cycle, and because blood is a better conductor than air, the electrical impedance of the thorax oscillates likewise. This states that solute transfer price = blood flow � focus difference between incoming and outgoing blood. O2 uptake in the lungs is measured over 5�10 min by spirometry or expired air assortment. The O2 content material of blended venous blood is measured in a blood sample taken from the right ventricle by cardiac catheterization. A identified mass of dye or cold saline is injected rapidly into the best heart, and the concentration or temperature is recorded at some extent downstream. The area beneath the velocity/time plot offers the distance advanced per ejection (stroke distance). Radionuclide ventriculography measures the radioactive counts present in the ventricle during end-diastole and endsystole. The stroke volume and ejection fraction are calculated from the difference between counts. With all strategies that estimate stroke volume, the cardiac output is calculated as coronary heart rate � stroke quantity. Arterial pulse examination is the best bedside methodology for assessing cardiac output. Pulse strain is proportional to stroke quantity, although the connection is complicated by run-off, non-linear aortic compliance, dependence on ejection fee and age-related arterial stiffening (arteriosclerosis). A computerized, steady display of cardiac output based on finger pulse monitoring is utilized in intensive care items. Real-Time third-dimensional echocardiography: an integral component of the 119 Assessment of cardiac output and arterial pulse routine echocardiographic examination in adult sufferers Non-invasive pulsatile arterial pressure and stroke quantity modifications from the human finger. The form of indicator dilution curves used for cardiac output measurement in man. Nontraumatic willpower of left ventricular ejection fraction by radionuclide angiocardiography. In 1856, Darcy reported that move in the steady state, Q, is linearly proportional to the stress difference between two points, P1 - P2. For instance, blood flow through the kidney is the same as the pressure in the renal artery minus the pressure in the renal vein, divided by renal vascular resistance. Consequently, the strain gradient across the vascular wall falls inside the stenosis and this may exacerbate the narrowing if the section is compliant. At the exit, blood flows into the wider phase regardless of a opposite stress gradient, consistent with the fact that circulate happens down a gradient of complete vitality rather than pressure alone. This may be rearranged to answer the elemental question: What determines imply arterial blood stress On entering the ventricle, blood velocity and hence kinetic vitality fall just about to zero. There is therefore a kinetic vitality gradient between the central veins and ventricle, which aids ventricular filling. To put it another way, the momentum of the returning blood contributes to ventricular enlargement. The different two are gravitational potential power and kinetic vitality, as acknowledged by Bernoulli, an 18th-century Swiss mathematician and physicist, who turned a professor of mathematics at the age of 25. The potential energy of blood relative to the guts is the blood mass (volume V � density) � top above the heart h � acceleration as a result of gravity g. It depends on mass and velocity, increasing in proportion to velocity squared (2). For a given volume move, velocity increases where the cross-sectional space A narrows. Flow from the slim to the broad section is against the strain gradient but down the entire energy gradient. Pressures in italics are central strain plus pressure because of vertical fluid column. Pressures in brackets represents precise values for flowing blood, which are modified slightly by the arterial and venous resistances. The rationalization is that the total power of arterial blood per unit quantity is identical (or very barely less) on the foot than within the proximal aorta and the apparent difference is as a outcome of of the gravitational potential power on the two websites, equivalent to a strain of 90 mm Hg. The small difference, 2 mmHg, suffices to drive flow from the aorta to the dorsalis pedis artery, because massive arteries provide little resistance to move. The lamina involved with the vessel wall has zero velocity due to molecular cohesive forces � the zero-slip condition. The third lamina slides previous the second lamina, and since the second lamina is itself shifting, the third lamina has a better velocity relative to the tube wall, and so forth, till maximum velocity is reached within the centre of the tube. Blood within the centre of the vessel subsequently has the next velocity than blood near the wall. You can see the same impact during any riverside stroll; the present is faster within the centre than close to the banks. For a easy fluid similar to water, the velocity profile throughout a cylindrical tube is a parabola. Laminar circulate has easy, parallel streamlines When a liquid flows by way of a easy cylindrical tube at not too high a velocity, the liquid behaves like a set of Laminar shearing of blood creates a marginal plasma layer the sliding movement of one lamina past another � like one hand rubbing over the other � known as shear. For a Newtonian (one during which viscosity is constant) fluid in totally developed laminar flow, velocity is a parabolic function of radial position r, namely = max (1 - r2/R2), where R is tube radius.
Tags: silvitra 120 mg overnight delivery, buy silvitra 120 mg with amex, silvitra 120 mg cheap online, 120 mg silvitra order free shipping, generic 120 mg silvitra, 120 mg silvitra cheap with visa, cheap silvitra 120 mg amex, silvitra 120 mg generic line, 120 mg silvitra buy with amex, order 120 mg silvitra with mastercard, 120 mg silvitra discount overnight delivery, silvitra 120 mg generic with amex, silvitra 120 mg purchase on line, generic 120 mg silvitra overnight delivery, silvitra 120 mg, silvitra 120 mg discount mastercard
9 of 10
Votes: 301 votes
Total customer reviews: 301
Customer Reviews
Porgan, 24 years: This metabolism-driven improve in blood flow known as functional hyperaemia or metabolic hyperaemia or metabolic vasodilatation. Type: For cardio train, emphasis ought to be placed on extended, rhythmic actions utilizing large muscle groups such as strolling, cycling, or swimming. Individuals in the lowest grip energy tertile had an eightfold elevated risk for disability. As a outcome, the Frank�Starling mechanism contributes to the rise in stroke quantity.
Mezir, 25 years: The sample of ingesting alcohol also influences the chance of cerebro- and cardiovascular illnesses. In young people and heaps of animals, the sluggish return of the mirrored wave augments the diastolic stress, which boosts coronary artery perfusion. In regular life, an acute rise in arterial pressure increases the baroreceptor visitors, which is conveyed by the vagi and glossopharyngeal nerves to the brainstem, the place it activates polysynaptic central pathways. Racial, ethnic and socioeconomic disparities within the clustering of heart problems risk components.
Bozep, 39 years: Aortic systolic hypertension is thus the product of three biophysical mechanisms, specifically a rise in peripheral resistance, a fall in central artery compliance and the rapid return of a bigger, mirrored stress wave. Cocoa and chocolate contribute to the vascular environment, impacting endothelial function, platelet aggregation, and the bioavailability and activation of nitric oxide [12]. Combined inhibition of influenza virus replica in cell tradition utilizing interferon and amantadine. Peak serum ranges occurred at about 2 hours in both groups, and the elimination half-lives (mean 14.
Leon, 22 years: Population-based evidence of a robust decline in the prevalence of people who smoke in Brazil (1989�2003). Of 471 youngsters, 73% had laboratory-confirmed influenza, 65% with influenza A and 35% with influenza B. Exercise-based cardiac rehabilitation increases every day physical activity of sufferers following myocardial infarction: subanalysis of two randomised controlled trials. Finally, the membrane repolarizes (phase 3), though at only 1/1000th of the speed of depolarization.
