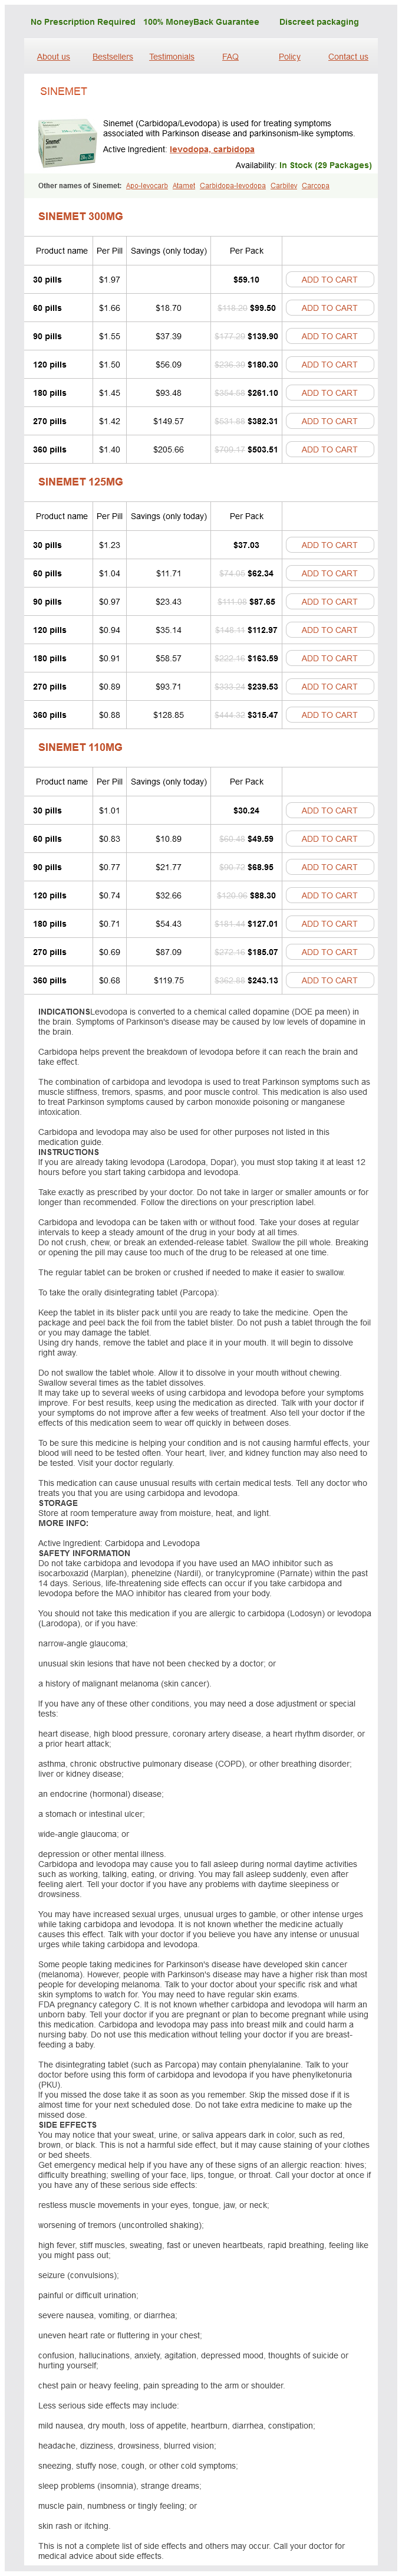
Sinemet 300mg
- 30 pills - $59.10
- 60 pills - $99.50
- 90 pills - $139.90
- 120 pills - $180.30
- 180 pills - $261.10
- 270 pills - $382.31
- 360 pills - $503.51
Sinemet 125mg
- 30 pills - $37.03
- 60 pills - $62.34
- 90 pills - $87.65
- 120 pills - $112.97
- 180 pills - $163.59
- 270 pills - $239.53
- 360 pills - $315.47
Sinemet 110mg
- 30 pills - $30.24
- 60 pills - $49.59
- 90 pills - $68.95
- 120 pills - $88.30
- 180 pills - $127.01
- 270 pills - $185.07
- 360 pills - $243.13
Sinemet dosages: 300 mg, 125 mg, 110 mg
Sinemet packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 602
Only $0,72 per item
Description
If vacuum flow is insufficient medications 122 sinemet 300 mg generic with visa, waste gas can spill out into the room through the relief ports medications causing hyponatremia buy sinemet 300 mg online. All closed interfaces should have a positive-pressure aid valve to vent excess system stress if obstruction occurs downstream from the interface medicine remix purchase sinemet 300 mg amex. A negative-pressure relief valve is mandatory to shield the respiratory system from subatmospheric pressure if an lively disposal system is used medications hyperthyroidism cheap sinemet 300 mg amex. One is used with passive scavenging systems and has positive-pressure aid solely; the opposite is used with active scavenging systems and has each positive- and negativepressure relief. This interface has a single positive-pressure aid valve and is designed to function solely with passive disposal methods. The positive-pressure reduction valve opens at a preset value similar to 5 cm H2O if an obstruction between the interface and the disposal system happens. This interface has a positive-pressure reduction valve and no much less than one negative-pressure aid valve, along with a reservoir bag. A B Chapter 29: Inhaled Anesthetics: Delivery Systems 803 scavenge interface for active suction methods. A variable volume of waste gas intermittently enters the interface through the waste fuel inlets. The reservoir bag intermittently accumulates excess gas till the evacuation system eliminates it. The operator must modify the vacuum management valve in order that the reservoir bag stays correctly inflated. Gas is vented to the environment by way of the positive-pressure reduction valve if the system pressure exceeds +5 cm H2O. The effectiveness of a closed system in stopping spillage is decided by the speed of waste fuel influx, the evacuation move rate, and the size of the reservoir. Leakage of waste gases into the environment occurs solely when the reservoir bag becomes totally inflated and the stress will increase sufficiently to open the positive-pressure relief valve. The gasoline disposal assembly conduit conducts waste gasoline from the scavenging interface to the receiving finish of the gasoline disposal system. It should be collapseproof and should run overhead, if attainable, to minimize the chance of accidental occlusion. The two forms of environmental disposal mechanisms, lively and passive, have been described. Hazards Scavenging techniques decrease operating room pollution, yet they add complexity to the anesthesia system. A scavenging system functionally extends the anesthesia circuit all the best way from the anesthesia machine to the ultimate disposal site. Excessive vacuum applied to a scavenging system may cause undesirable adverse pressures within the respiration system. In contrast, insufficient vacuum to the interface may cause venting of waste gas into the working room. In one case report, inadequate suction brought on a ventilator alarm situation resulting from backpressure brought on inside scavenge system. Because some anesthesia machines scavenge ventilator drive gasoline (which is 100% oxygen in most cases) along with gas from the breathing system, the environments in these machine rooms could turn into extremely enriched with oxygen fuel. The end result has been the manufacturing of fires in these spaces exterior the operating room. These sites might comprise gear or materials similar to petroleum distillates (pumps, oil, or grease) that within the presence of an oxygen-enriched environment might be excessively flamable and a extreme fire hazard. The apparent trade parallel is in aviation, by which strict adherence to prevent checklists. Researchers demonstrated that anesthesiologists demonstrated poor fault detection on sabotaged machines regardless of having the rule of thumb in hand. In different research within controlled settings, researchers noted restricted machine fault detection and low checklist item compliance. Surveys have demonstrated poor compliance with machine checks, in addition to low self-admitted competence with the procedure. The suggestions are therefore designed as a template to develop "checkout procedures which may be appropriate for each individual anesthesia machine design and practice setting. Local ability levels, work move patterns, and training requirements may differ greatly. The suggestions merely counsel the minimum machine-related objects that must be assessed before use. Given the importance of pulse oximetry and capnography to affected person safety, verifying proper perform of those units before anesthetizing the affected person is essential. Pulse oximeter perform, including an audible alarm, can be verified by putting the sensor on a finger and observing for a correct recording. The pulse oximeter alarm may be tested by introducing movement artifact or eradicating the sensor. Proper monitor functioning consists of visible and audible alarm indicators that perform as designed. No matter what occurs to the machine, you must all the time be ready to maintain the patient alive with out it. The auxiliary air flow gadget should be self-inflating, which excludes Mapleson circuits that are often found in and out of the working room. These gadgets should be situated at "each anesthetizing location," and the rule further recommends that they be checked for proper function. The advice additionally states that the auxiliary oxygen supply ought to be separate from the machine and its pipeline provide, "particularly an oxygen cylinder. Item 2: Verify Patient Suction Is Adequate to Clear the Airway Frequency: Before each use Responsible parties: Provider and technician "Safe anesthetic care requires the instant availability of suction to clear the airway if needed. However, the process of checking alarm thresholds, and possibly resetting them, could be tedious. Monitor alarm settings may presumably vary within particular person facilities as a outcome of provider manipulation of alarms for case necessities, a scarcity of ordinary default settings, and failure to reset alarm limits routinely. Departmental alarm default settings could be established and programmed into anesthesia workstation displays. Alarm limit settings additionally embrace anesthesia machine alarms such as volume, strain, and inspired oxygen focus limits. The practitioner should ensure that important alarm limits are set to values that let these alarms to do what they were supposed to do. Desflurane vaporizers require electrical energy and recommendations for checking power to these vaporizers also wants to be adopted. The capacity to conform to these requirements must be confirmed for every anesthetic. Alarm limit values are simple to modify, though this course of can be time consuming throughout routine preuse checkout. Safe default values could be established domestically and set by trained technicians, to assist keep limits constant. Chapter 29: Inhaled Anesthetics: Delivery Systems 807 Here, anesthesia technicians can improve the quality of the preuse checkout by checking the perform of standard screens and confirming that important alarm thresholds are set to established default values. The acceptable strain is decided by the intended use, the design of the anesthesia delivery system and the supply of piped oxygen. Some newer machines may have a tank gauge positioned on the again of the machine. Therefore the pressure within the piped gasoline supply should be checked a minimum of once day by day. As mentioned earlier, if the tank is to be used within the setting of a suspected oxygen pipeline contamination, the pipeline supply should be disconnected from the machine for tank gasoline to flow into the gas provide system. In that case, the utmost length of oxygen provide may be obtained from an oxygen cylinder whether it is used only to present recent gas to the affected person along side handbook or spontaneous air flow. Mechanical ventilators will devour the oxygen supply if pneumatically powered ventilators that require oxygen to energy the ventilator are used. An necessary safety merchandise on all machines is an audible and visible alarm that warns the operator of diminishing oxygen supply strain. The solely approach to evaluate this pneumatic security system is to disconnect the wall oxygen supply and shut off the oxygen provide tank or tanks. Concern also existed that daily elimination and reconnection of oxygen provide line connector might contribute to put on or breakdown. Furthermore, some machines have a check valve between the flowmeters and the frequent gasoline outlet, requiring a negative-pressure test to check for leaks adequately. When counting on automated testing to evaluate the system for leaks, the automated leak take a look at would wish to be repeated for each vaporizer in place.
Venostasin Retard (Horse Chestnut). Sinemet.
- Are there any interactions with medications?
- Hemorrhoids, diarrhea, fever, cough, enlarged prostate, eczema, menstrual pain, soft tissue swelling from bone fracture and sprains, arthritis, rheumatism, and other conditions.
- Are there safety concerns?
- Pain, tiredness, tension, swelling in the legs, itching, and water retention (edema).
- Dosing considerations for Horse Chestnut.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97006
Any circulate through the hepatic veins is maintained by the confused blood quantity throughout the splanchnic vasculature medications xyzal 125 mg sinemet buy. In different phrases treatment 247 buy sinemet 110 mg free shipping, the intravascular pressure throughout the splanchnic system have to be higher than the intra-abdominal pressure medicine hollywood undead sinemet 110 mg cheap overnight delivery, which is the perivascular stress medications similar to abilify sinemet 110 mg discount line. When intra-abdominal pressure starts to increase, intravascular stress increases with it, and confused volume flows out of the splanchnic system by way of the hepatic veins, elevating the intra-abdominal pressure by 5 mL/cm of fluid. A simultaneous improve in strain throughout the inferior caval vein on the stage of hepatic veins momentarily stops blood circulate by way of the femoral veins. However, that high pressure also increases flow from the hepatic vein entry and delays the compression of the inferior caval vein by high intra-abdominal strain. This elevated stress gradient from the inferior caval vein pressure to the best atrial stress increases circulate through the inferior caval vein and venous return, serving to to counteract the consequences of the compression of the inferior caval vein and attainable decrease in preload. Thus, a rise in careworn quantity is required to overcome the rise in impedance to the venous return. Mean arterial pressure is usually slightly elevated or decreased, cardiac output might be decreased or maintained. This scheme depicts the reason for the lower in venous capability, which finally ends up in blood volume redistribution from the vasculature distal to aortic occlusion to the vasculature proximal to aortic occlusion. If the aorta is occluded above the splanchnic system, the blood quantity travels to the guts, rising preload and blood volume in all organs and tissues proximal to the clamp. However, if the aorta is occluded under the splanchnic system, blood quantity can shift into the splanchnic system or into the vasculature of other tissues proximal to the clamp. The distribution of this blood quantity between the splanchnic and nonsplanchnic vasculature determines changes in preload. The latter might lead to a rise in splanchnic free radical manufacturing, a rise in capillary permeability, and bacterial translocation from the gut into the bloodstream. Focal ischemia may be observed as pallor and hyperemia, followed by petechiae and shallow ulcerations that progress to mucosal stress ulcers. Stress ulcers are superficial, limited only to the mucosa, and often heal without serious consequences. The etiology and course of drug-related ulcers are similar to these of stress ulcers. These drugs produce an imbalance between vasodilating and vasoconstricting prostaglandins, disturbing microcirculation within the mucosa that can be followed by ulceration. The major pathogenetic factor in stress ulcers and in drug-related ulcers is a short lived decrease in gastric mucosal blood flow that can lead to issues such as bleeding, endotoxemia, and sepsis. The function of blood move and general pathogenesis of stress ulcers has been properly described. Moreover, such an increase in preload (as a result of sympathetic activation) is often a compensatory mechanism essential to preserve acceptable cardiac output. In different words, a particular enhance in careworn quantity might be needed to maintain the guts at an appropriate place on the Starling curve (to the best of normal). Role of Gastrointestinal Blood Flow in Gastroduodenal Mucosal Ulceration Many compounds secreted throughout the abdomen are ulcerogenic, the most important being hydrochloric acid and pepsin. Acute ulceration results from inflammatory response to bodily or thermal trauma, shock, sepsis, and some others including emotional stress; these are called stress ulcers. These ulcers usually occur within the proximal, acid-secreting portion of the stomach. Examination of the intravital microcirculation during sepsis reveals vascular wall edema, native hemorrhages, arteriole-venule shunting, reverse flow in capillaries and venules, blood circulate redistribution inside microunits, leukocyte-endothelial interaction, and transmigration through the capillary partitions. Some micro-areas are hyperperfused and others are hypoperfused; arteriovenous shunting of blood is elevated. This often is related to a relatively regular or even elevated whole blood circulate, however severely decreased nutritive blood circulate to the intestinal partitions, notably to the mucosa. During sepsis, metabolic demand for oxygen within the intestines is increased, and nutritive blood flow is decreased regardless of profound vasodilation. Sepsis is associated with extreme inflammatory response resulting in an increase in permeability and impaired immunologic barrier operate within the intestines. Ischemia, increased permeability, and impaired intestinal barrier play an necessary function in subsequent amplification of distant organ dysfunction. Effects of Spinal and Epidural Anesthesia on Gastrointestinal Blood Flow and Volume the diploma of arterial hypotension induced by spinal or epidural anesthesia is directly related to the extent of the blockade, the dose of local anesthetic used, and baseline hemodynamics. The constriction of the proximal part of the splanchnic vasculature shifts blood quantity from the splanchnic system into the systemic circulation and often results in preservation of stressed volume and blood stress. Thoracic epidural anesthesia is associated with pronounced mesenteric vasodilation and arterial hypotension, whereas intestinal blood circulate and oxygen consumption are maintained. A research utilizing labeled red cells demonstrated that epidural anesthesia with sensory block at T4-T5 elevated blood volume in both the intrathoracic and splanchnic vasculature. The authors estimated that the usage of a vasoconstrictor during thoracic epidural anesthesia led to a shift of approximately 1 L of blood from the splanchnic space into the thoracic and systemic circulation. Infusion of fluid will increase whole (stressed and unstressed) blood volume, whereas adrenergic agonists move current blood quantity from unstressed to careworn. In many situations, the use of -adrenergic agonists might be more helpful than infusion of fluid. Role of M cells in transepithelial transport of antigens and pathogens to the mucosal immune system, Am J Physiol 274:G785, 1998. Camilleri M: Integrated upper gastrointestinal response to food consumption, Gastroenterology 131:640, 2006. Thorn K, Thorn S-E, Wattwil M: the effects of cricoid pressure, remifentanil and propofol on esophageal motility and the decrease esophageal sphincter, Anesth Analg one hundred:1200, 2005. Chapman M, Fraser R, Vozzo R, et al: Antro-pyloro-duodenal motor responses to gastric and duodenal nutrient in critically sick sufferers, Gut 54:1384, 2005. Rauch S, Krueger K, Turan A, et al: Determining small intestinal transit time and pathomorphology in critically unwell sufferers utilizing video capsule technology, Intensive Care Med 35:1054, 2009. Van Oudenhove L, McKie S, Lassman D, et al: Fatty acid-induced gut-brain signaling attenuates neural and behavioral results of unhappy emotion in people, J Clin Invest 121:3094, 2011. Mayer E: Gut emotions: the emerging biology of gut-brain communication, Nat Rev Neurosci 12:453, 2011. Schaefer N, Tahara K, Von Websky M, et al: Role of resident macrophages in the immunologic response and smooth muscle dysfunction during acute allograft rejection after intestinal transplantation, Transpl Int 21:778, 2008. Laine L, Takeuchi K, Tarnawski A: Gastric mucosal protection and cytoprotection: bench to bedside, Gastroenterology 135:forty one, 2008. Gelman S: the pathophysiology of aortic cross-clamping and unclamping, Anesthesiology 82:1026, 1995. Aliverti A, Uva B, Laviola M, et al: Concomitant ventilatory and circulatory features of the diaphragm and stomach muscles, J Appl Physiol 109:1432, 2010. Schafer M, Sagesser H, Reichen J, et al: Alterations in hemodynamics and hepatic and splanchnic circulation throughout laparoscopy in rats, Surg Endosc 15:1197, 2001. Redistribution of the venous reservoir as a explanation for decompensation, Circ Heart Fail 4:669, 2011. Clemente A, Carli F: the physiological results of thoracic epidural anesthesia and analgesia on the cardiovascular, respiratory and gastrointestinal systems, Minerva Anestesiol 74:549, 2008. Stanton-Hicks M, Hock A, Stuhmeler K-D, et al: Venoconstrictor agents mobilize blood from completely different sources and improve intrathoracic filling during epidural anesthesia in supine people, Anesthesiology sixty six:317, 1987. The portal vein delivers 75% of complete hepatic blood move; the hepatic artery offers the remainder. Without this reservoir operate, gentle losses of intravascular quantity can lead to extreme hypotension. Kupffer cells reside in hepatic sinusoids; they filter the venous effluent of the gastrointestinal tract; they usually avidly take away micro organism and other harmful substances, stopping their entry into the systemic circulation. Blood perfusing zone 1 is wealthy in O2 and vitamins; zone three hepatocytes are perfused with effluent blood from zones 1 and a pair of, which is relatively O2 poor. Hepatocytes secrete bile acids, which move by way of a sequence of hepatobiliary ducts that drain into the duodenum via the common bile duct. Enterocytes of the terminal ileum efficiently take up bile acids and return them to hepatocytes via the portal blood. Hepatocytes can then take up and secrete a single bile acid molecule many instances; this gut�liver connection is recognized as the enterohepatic circulation. Depletion of liver glycogen during extended fasting, for example, promotes hepatic gluconeogenesis, enabling the liver to nourish glucose-dependent tissues.
Specifications/Details
Imai Y medications with weight loss side effects buy sinemet 300 mg without a prescription, Parodo J treatment zollinger ellison syndrome sinemet 110 mg purchase mastercard, Kajikawa O medicine hat news effective sinemet 300 mg, et al: Injurious mechanical air flow and end-organ epithelial cell apoptosis and organ dysfunction in an experimental model of acute respiratory misery syndrome symptoms for hiv sinemet 110 mg generic fast delivery, Jama 289:2104-2112, 2003. Gamulin Z, Forster A, Morel D, et al: Effects of infra-renal aortic cross-clamping on renal hemodynamics in people, Anesthesiology 61:394-399, 1984. The prevention of acute functional renal failure throughout resection of an aneurysm of the abdominal aorta, N Engl J Med 264:967-971, 1961. Halpenny M, Rushe C, Breen P, et al: the results of fenoldopam on renal perform in patients undergoing elective aortic surgical procedure, Eur J Anaesthesiol 19:32-39, 2002. Haase M, Bellomo R, Story D, et al: Effect of imply arterial stress, haemoglobin and blood transfusion throughout cardiopulmonary bypass on post-operative acute kidney damage, Nephrol Dial Transplant 27:153-160, 2012. Haase M, Haase-Fielitz A, Bellomo R: Cardiopulmonary bypass, hemolysis, free iron, acute kidney damage and the impression of bicarbonate, Contrib Nephrol one hundred sixty five:28-32, 2010. Haase M, Bellomo R, Haase-Fielitz A: Novel biomarkers, oxidative stress, and the position of labile iron toxicity in cardiopulmonary bypassassociated acute kidney injury, J Am Coll Cardiol 55:2024-2033, 2010. Haase-Fielitz A, Haase M, Bellomo R, Dragun D: Genetic polymorphisms in sepsis- and cardiopulmonary bypass-associated acute kidney harm, Contrib Nephrol 156:75-91, 2007. Nakamura K, Harasaki H, Fukumura F, et al: Comparison of pulsatile and non-pulsatile cardiopulmonary bypass on regional renal blood move in sheep, Scand Cardiovasc J 38:59-63, 2004. Alkan T, Akcevin A, Undar A, et al: Benefits of pulsatile perfusion on very important organ restoration throughout and after pediatric open heart surgery, Asaio J 53:651-654, 2007. Onorati F, Presta P, Fuiano G, et al: A randomized trial of pulsatile perfusion utilizing an intra-aortic balloon pump versus nonpulsatile perfusion on short-term changes in kidney function throughout cardiopulmonary bypass throughout myocardial reperfusion, Am J Kidney Dis 50:229-238, 2007. Hilberman M, Myers B, Carrie G, et al: Acute renal failure following cardiac surgical procedure, J Thorac Cardiovasc Surg seventy seven:880-888, 1979. Hilberman M, Maseda J, Stinson E, et al: the diuretic properties of dopamine in patients after open-heart operation, Anesthesiology 61:489-494, 1984. Lassnigg A, Donner E, Grubhofer G, et al: Lack of renoprotective effects of dopamine and furosemide during cardiac surgical procedure, J Am Soc Nephrol eleven:97-104, 2000. Chiolero R, Borgeta A, Fisher A: Postoperative arrhythmias and danger components after open heart surgical procedure, Thorac Cardiovasc Surgeon 39:81-84, 1991. Ranucci M, Soro G, Barzaghi N, et al: Fenoldopam prophylaxis of postoperative acute renal failure in high-risk cardiac surgical procedure patients, Ann Thorac Surg seventy eight:1332-1337, 2004. Seki G, Suzuki K, Nonaka T, et al: Effects of atrial natriuretic peptide on glycerol induced acute renal failure within the rat, Japanese Heart Journal 33:383-393, 1992. Sezai A, Shiono M, Orime Y, et al: Low-dose continuous infusion of human atrial natriuretic peptide during and after cardiac surgery, Ann Thorac Surg 69:732-738, 2000. Mitaka C, Kudo T, Haraguchi G, Tomita M: Cardiovascular and renal results of carperitide and nesiritide in cardiovascular surgery sufferers: a scientific evaluation and meta-analysis, Crit Care 15, R258, 2011. Sisillo E, Ceriani R, Bortone F, et al: N-acetylcysteine for prevention of acute renal failure in patients with continual renal insufficiency undergoing cardiac surgical procedure: a prospective, randomized, medical trial, Crit Care Med 36:81-86, 2008. Investigators A: Acetylcysteine for prevention of renal outcomes in sufferers present process coronary and peripheral vascular angiography - medical perspective, Circulation 124:1250-1259, 2011. Haase M, Haase-Fielitz A, Bellomo R, et al: Sodium bicarbonate to forestall will increase in serum creatinine after cardiac surgery: a pilot double-blind, randomized managed trial, Crit Care Med 37:39-47, 2009. Wardle N: Acute renal failure in the Eighties: the importance of septic shock and of endotoxemia, Nephron 30:193-200, 1982. Clive D, Stoff J: Renal syndromes associated with nonsteroidal antiinflammatory medicine, N Engl J Med 310:563-572, 1984. Kunzendorf U, Walz G, Brockmoeller J, et al: Effects of diltiazem upon metabolism and immunosuppressive motion of cyclosporine in kidney graft recipients, Transplantation fifty two:280-284, 1991. Tepel M, van der Giet M, Schwarzfeld C, et al: Prevention of radiographic-contrast-agent-induced reductions in renal perform by acetylcysteine, N Engl J Med 343:180-184, 2000. Briguori C, Manganelli F, Scarpato P, et al: Acetylcysteine and contrast agent-associated nephrotoxicity, J Am Coll Cardiol forty: 298-303, 2002. Physicochemical interactions between myoglobin, hemoglobin, Bence-Jones protein and Tamm-Horsfall mucoprotein, Curr Probl Clin Biochem 9:299, 1979. Ron D, Taitelman U, Michaelson M, et al: Prevention of acute renal failure in traumatic rhabdomyolysis, Archives of Internal Medicine a hundred and forty four:277, 1984. Lherm T, Troche G, Rossignol M, et al: Renal results of lowdose dopamine in patients with sepsis syndrome or septic shock treated with catecholamines, Intens Care Med 22:213-219, 1996. Bellomo R, Chapman M, Finfer S, et al: Low-dose dopamine in patients with early renal dysfunction: a placebo- controlled randomised trial. Morelli A, Ricci Z, Bellomo R, et al: Prophylactic fenoldopam for renal safety in sepsis: a randomized, double-blind, placebocontrolled pilot trial, Crit Care Med 33:2451-2456, 2005. Golab F, Kadkhodaee M, Zahmatkesh M, et al: Ischemic and nonischemic acute kidney injury trigger hepatic damage, Kidney Int 75:783-792, 2009. Schwinn for contributing a chapter on this topic to the prior version of this work. Key Points � Pharmacokinetics describes the connection between drug dose and drug focus in plasma or on the website of drug impact over time. For anesthetic medicine, the processes of distribution and elimination (metabolism and excretion) govern this relationship. These parameters are derived from mathematical formulas match to measured blood or plasma concentrations over time following a known drug dose. Biophase accounts for the time required for drug to diffuse from the plasma to the location of action plus the time required, as soon as drug is at the website of action, to illicit a drug impact. In specific, pharmacodynamics describes the relationship between drug concentration and pharmacologic effect. Anesthetics not often consist of 1 drug, but rather a mix of medicine to achieve desired ranges of hypnosis, analgesia, and muscle rest. Hypnotics, analgesics, and muscle relaxants all interact with one another such that hardly ever does one drug, when administered in the presence of different medicine, behave as if it had been administered alone. Advances in computer simulation have introduced this functionality to the purpose of real-time affected person care in the type of drug shows. Some of these embrace age; physique habitus; gender; persistent publicity to opioids, benzodiazepines, or alcohol; presence of coronary heart, lung, kidney, or liver illness; and the extent of blood loss or dehydration. [newline]The aim of this chapter is to provide an overview of key principles in scientific pharmacology used to describe anesthetic drug habits. This chapter is split into three major sections: pharmacokinetic ideas, pharmacodynamic principles, and the importance of affected person characteristics. Pharmacokinetics is the relationship between drug administration and drug concentration on the website of action. Core ideas embrace volumes of distribution, drug clearance, transfer of medicine between plasma and tissues, and binding of drugs to circulating plasma proteins. The section on pharmacokinetics introduces both the physiologic processes that decide pharmacokinetics and the mathematical models used to relate dose to concentration. Pharmacodynamics is the relationship between drug concentration and pharmacologic impact. In reality, most anesthetics are a combination of a number of medicine with specific goals in analgesia, sedation, and muscle rest. This section evaluations widespread pharmacodynamic interactions and how they affect anesthetic effect. The last part briefly addresses patient demographics and the way they affect anesthetic habits. When formulating an anesthetic, the next elements need to be thought-about in determining the correct dose: age; body habitus; gender; persistent publicity to opioids, benzodiazepines, or alcohol; the presence of coronary heart, lung, kidney, or liver illness; and the extent of blood loss or dehydration. This part focuses on body habitus and age, both identified to affect the pharmacology of many anesthetic medication and both of which serve as wonderful examples of altered pharmacokinetics and pharmacodynamics. The group of blue dots at the top right represents a bolus dose that, when administered to the tank of water, evenly distributes within the tank. The time course of intravenously administered medicine is a function of distribution volume and clearance. Estimates of distribution volumes and clearances are described by pharmacokinetic parameters. With an estimate of tank volume, drug concentration after any bolus dose may be calculated. Using Equation 1, to estimate the quantity of distribution with out accounting for elimination leads to volume of distribution estimates that become larger than initial quantity. The quantity of distribution (Vd) is the obvious size of the tank required to clarify a measured drug concentration from the tank water once the drug If elimination occurs as a first-order process.
Syndromes
- Follow-up on colon cancer or polyps
- Blood clotting disorders (thrombophilias)
- Abnormal breathing pattern --breathing out takes more than twice as long as breathing in
- Bright red, chapped, or cracked lips
- Cultures of the fluid may show bacteria, and these bacteria may be resistant or harder to treat than the bacteria commonly involved in an acute ear infection.
- Amount swallowed
- After the spell, try to be calm. Avoid giving too much attention to the child, as this can reinforce the behaviors that led to the event.
- Establish fire escape routes from every room in your house and teach family members what to do in case of a fire. Have twice-a-year fire drills to practice escaping.
- Complete blood count
- Adults: 150 to 220
Related Products
Additional information:
The modifications in subunit composition can also alter the sensitivity or affinity medicine man dispensary sinemet 110 mg with mastercard, or both medicine 95a order 110 mg sinemet overnight delivery, of the receptor for particular ligands treatment kidney disease purchase sinemet 300 mg without prescription. Depolarizing or agonist medicine such as succinylcholine and acetylcholine more easily depolarize immature receptors medicine wheel teachings generic 125 mg sinemet overnight delivery, thereby resulting in cation fluxes; doses one tenth to one hundredth of those needed for mature receptors can effect depolarization. Sensitivity to relaxants can begin to change between forty eight and 72 hours after an harm or hospitalization. The resulting hyperkalemia may cause harmful disturbances in cardiac rhythm, including ventricular fibrillation. However, hyperkalemia and cardiac arrest can occur after the administration of succinylcholine, even in the absence of denervation states. These effects are noticed in certain congenital muscle dystrophies by which the muscle membrane is vulnerable to damage by the depolarization produced by succinylcholine, leading to potassium launch through the membrane harm. They embody numerous combinations of -subunits (1 by way of 10) and -subunits (1 by way of 4) and one every of -, -, and -subunits. Because a fasciculation is, by definition, the simultaneous contraction of the multitude of muscle cells in a single motor unit and since only the nerve can synchronize all of the muscles in its motor unit, it turned apparent that succinylcholine should additionally act on nerve endings. The functional traits of prejunctional receptor channels may be different. For example, the depolarization of motor nerve endings initiated by the administration of acetylcholine can be prevented by tetrodotoxin, a particular blocker of sodium flux with no effect on the tip plate. Specific information on the molecular group of neuronal nicotinic receptors on the motor neuron terminal remains to be lacking. To emphasize the excellence between neural and muscle nicotinic receptors, the previous are typically designated Nn and the latter Nm. In other components of the nervous system, this constructive suggestions is complemented by a negative-feedback system that senses when the concentration of transmitter in the synaptic cleft has appropriately elevated and shuts down the discharge system. The motor nerve terminal is also known to bear a number of other receptors, such as opioid, adrenergic, dopamine, purine, and adenosine receptors, in addition to receptors for endogenous hormones, neuropeptides, and quite so much of proteins. At this point, each junction could have a couple of nerve terminal innervating it. Postnatal day 5 (P5): Approximately 5 days after start, the postsynaptic membrane invaginates to kind a gutter and small perforations develop on the plaque. The invaginations or clefts increase in numbers, resulting in extra perforations within the pretzelshaped junction. Postnatal day 30 (P30): the neuromuscular junction is completely developed at 30 days after birth. A distinct set of postsynaptic proteins and signaling molecules are selectively transcribed within the subsynaptic area, offering integrity to the neuromuscular junction and efficient neurotransmission. With continued maturation, the plaque is remodeled to a multiperforated pretzel-like construction. The polyinnervated end plate is transformed to a singly innervated junction due to a retraction of all however one terminal. The factors of contacts between the prejunctional and postjunctional membrane lower, leading to a decline in trophic interactions between nerve and muscle and stimulus transmission. Despite these structural and functional modifications associated with getting older, the overall margin of safety is better in the older particular person than within the neonate. Lennerstrand G, Bolzani R, Tian S, et al: Succinylcholine activation of human horizontal eye muscle tissue, Acta Ophthalmol 88:872-876, 2010. Katz B, Miledi R: Estimates of quantal content during "chemical potentiation" of transmitter launch, Proc R Soc Lond B Biol Sci 205:369-378, 1979. Jahn R, Fasshauer D: Molecular machines governing exocytosis of synaptic vesicles, Nature 490:201-207, 2012. Heidelberger R: Neuroscience: sensors and synchronicity, Nature 450:623-625, 2007. Schurch B: the position of botulinum toxin in neurourology, Drugs Today (Barc) 40:205-212, 2004. Schiavo G: Structural biology: dangerous liaisons on neurons, Nature 444:1019-1020, 2006. Karwa M, Currie B, Kvetan V: Bioterrorism: preparing for the inconceivable or the unbelievable, Crit Care Med 33:S75-95, 2005. Richtsfeld M, Yasuhara S, Fink H, et al: Prolonged administration of pyridostigmine impairs neuromuscular function with down-regulation of acetylcholine receptors with and without down-regulation, Anesthesiology 119:412-421, 2013. Jonsson M, Gulrey D, Dabrowski M, et al: Distinct pharmacologic properties of neuromuscular blocking agents on human neuronal nicotinic acetylcholine receptors: a potential rationalization for the train-of-four fade, Anesthesiology 105:521-533, 2006. Gullberg D: Cell biology: the molecules that make muscle, Nature 424:138-140, 2003. Equilibrium measurements utilizing tritium-hydrogen exchange, Biochemistry 28:40-48, 1989. Maelicke A, Coban T, Storch A, et al: Allosteric modulation of Torpedo nicotinic acetylcholine receptor ion channel activity by noncompetitive agonists, J Recept Signal Transduct Res 17:11-28, 1997. Liu L, Min S, Li W, et al: Pharmacodynamic changes with vecuronium in sepsis are related to expression of 7- and -nicotinic acetylcholine receptor in an experimental rat model of neuromyopathy, Br J Anaesth 112(1):159-168, 2014. Tsuneki H, Kimura I, Dezaki K, et al: Immunohistochemical localization of neuronal nicotinic receptor subtypes at the pre- and postjunctional sites in mouse diaphragm muscle, Neurosci Lett 196:13-16, 1995. Mkrtchian S, Kahlin J, Ebberyd A, et al: the human carotid physique transcriptome with give attention to oxygen sensing and inflammation-a comparative analysis, J Physiol 590:3807-3819, 2012. Wessler I: Control of transmitter launch from the motor nerve by presynaptic nicotinic and muscarinic autoreceptors, Trends Pharmacol Sci 10:110-114, 1989. Adverse respiratory results can happen throughout anesthesia,1 and essentially the most severe cases of antagonistic events contain hypoxemia. These events range from intractable hypoxemia brought on by loss of airway patency to postoperative respiratory despair from opioids or regional anesthesia (see Chapter 96). Important insights may be gained by understanding how characteristic abnormalities of blood O2 carriage. Methemoglobin (MetHb), shaped by the oxidation to Fe3+ (ferric) instead of the usual Fe2+ (ferrous), is less able to bind O2, resulting in diminished O2 content material and fewer O2 delivery. In addition, because MetHb has a blue-brown color, the affected person will seem blue, even when the fraction of MetHb is modest and specialized oximetry can separately measure MetHb ranges. These circumstances shift the Hb-O2 dissociation curve to the proper, which increases the offloading of O2 to the tissues. Either cessation of blood move or extreme alveolar ventilation relative to perfusion will cause a rise in lifeless space. This effort would trigger considerable dyspnea, in addition to the dyspnea induced by the lowered PaO2. Obstructive lung disease can lead to diversion of impressed air into (nonobstructed) ventilated, but poorly perfused, areas of the lung. The parts of total impedance to respiration results from elastance (the reciprocal of compliance), resistance, and inertia. Under regular circumstances, inflation of the lung is maintained because though the pressure inside (alveolar pressure) is zero, the surface pressure. The inward force is the "elastic recoil" of the lung and emanates from the elastic lung tissue fibers, contractile airway clean muscle, and alveolar floor pressure. The outward force is developed by passive recoil from the ribs, joints, and muscle tissue of the chest wall. First, inflating an already opened (inflated) lung is simpler than when the lung is already deflated. This is because complete collapse leads to liquid-only surfaces interfacing in alveoli (high floor tension), whereas alveoli in partially inflated lung have air-liquid interfaces (lower floor tension). Second, although perfusion in the lung is phasic, the frequency is rapid and the oscillations in move are low, leading to practically continuous circulate. Ventilation is totally different: the frequency is far slower and the scale of the oscillations far larger. Chest wall mechanics could be measured provided that complete rest of the respiratory muscular tissues could be achieved26; however, throughout mechanical air flow the respiratory muscular tissues can be utterly relaxed. Values of chest wall compliance are about the same as that of the lung and are decreased with obesity, chest wall edema, pleural effusions, and illnesses of the costovertebral joints. The major component of resistance is the resistance exerted by the airways (large and small), and a minor component is the sliding of lung and the chest wall tissue elements during inspiration (and expiration). Resistance (R) is calculated as driving strain (P) divided by the resultant gasoline circulate (F): R = P/F the value of airway resistance is approximately 1 cm H2O/L/sec, and is greater in obstructive lung illness. Two components explain why most (approximately 80%) of the impedance to gas flow occurs within the massive airways.
Usage: gtt.
These cells have a low content material of myofibrils and a distinguished nucleus medicine pacifier safe 300 mg sinemet, and so they include an abundance of gap junctions treatment yellow jacket sting sinemet 300 mg otc. Excitation System the cellular action potential originating in the specialised conduction tissue is propagated to particular person cells where it initiates the intracellular occasion that results in treatment impetigo sinemet 300 mg generic amex the contraction of the cell through the sarcolemmal excitation system symptoms before period order sinemet 110 mg without a prescription. Phases of cellular motion potentials and main related currents in ventricular myocytes. The preliminary section (0) spike and overshoot (1) are attributable to a fast inward sodium (Na+) current, the plateau phase (2) by a slow calcium (Ca2+) current via L-type Ca channels, and repolarization (phase 3) by outward potassium (K+) currents. In specialised conduction system tissue, spontaneous depolarization takes place during section 4 till the voltage leading to opening of the Na channel is reached. Repolarization (phase 3) is brought about when an efflux of K+ from the three outward K+ currents exceeds the inflow of Ca2+, thus returning the membrane to the resting potential. Very little ionic flux occurs throughout diastole (phase 4) in a fast-response action potential. In contrast, during diastole (phase 4), pacemaker cells that present slow-response action potentials have the potential of spontaneous diastolic depolarization and generate the automated cardiac rhythm. Pacemaker currents during part four are the outcomes of a rise within the three inward currents and a decrease in the two outward currents. The three inward currents that contribute to spontaneous pacemaker activity embody two carried by Ca2+, iCaL and iCaT, and one that is a blended cation current, If. When in contrast with the fast-response motion potential, part zero is much less steep, section 1 is absent, and phase 2 is indistinct from phase three in the slow-response action potential. The Na+-Ca2+ exchanger restores cellular ionic balance by actively transporting Ca2+ out of the cell against a focus gradient while moving Na+ into the cell in an energy-dependent method. Ion fluxes throughout plasma membranes result in depolarization (attaining a less unfavorable membrane potential) and repolarization (attaining a extra adverse membrane potential). Because these ion channel proteins open and shut the pores in response to changes in membrane potential, the channels are voltage gated. In the heart, sodium (Na+), potassium (K+), Ca2+, and chloride (Cl-) channels contribute to the motion potential. Mostly because of the inflow of Na+, the membrane potential turns into depolarized, which leads to a particularly speedy upstroke (phase 0). As the membrane potential reaches a important degree (or threshold) during depolarization, the action potential is propagated. Activation of the contractile system depends on an increase in free cytosolic Ca2+ and its subsequent binding to contractile proteins. These spatially and temporally patterned activations of localized Ca2+ launch, in turn, stimulate myofibrillar contraction. B, Extracellular (arrows A, B1, B2) and intracellular calcium flux (arrows C, D, E, F, and G) are shown. The thickness of the arrows signifies the magnitude of the calcium flux, and the vertical orientations describe their energetics: downward-pointing arrows characterize passive calcium flux, whereas upward-pointing arrows symbolize energy-dependent calcium transport. Calcium entering the cell from extracellular fluid through L-type calcium channels triggers the release of calcium from the sarcoplasmic reticulum. Sodium that enters the cell in trade for calcium (dashed line) is pumped out of the cytosol by the sodium pump. Calcium binding to (arrow E) and dissociation from (arrow F) high-affinity calcium-binding sites of troponin C activate and inhibit interactions of the contractile proteins. Arrow H depicts movement of calcium into and out of mitochondria to buffer the cytosolic calcium focus. Because it lies near the Ca2+-release channels, the saved Ca2+ can be shortly discharged for launch as soon as the Ca2+-release channels are stimulated. Cytosolic Ca2+ can be removed by extrusion through the sarcolemmal Ca2+ pump and the activity of the Na+-Ca2+ exchanger. The I band is located on both aspect of the A band and incorporates only actin filament. The regulatory troponin heterotrimer complicated is discovered at common intervals along tropomyosin. The heterotrimer troponins are made up of troponin C (TnC), the Ca2+ receptor; TnI, an inhibitor of actin-myosin interplay; and TnT, which hyperlinks the troponin complicated to tropomyosin. It is situated at the end of the thin-filament actin and caps the top to forestall any excessive elongation of the thin filament. These events, which ensue from the binding of Ca2+ to TnC, lead to conformational modifications in tropomyosin and allow attachment of the myosin head to actin. This exercise leads to the release of Ca2+ binding to TnC and the separation of the myosin-actin crossbridge. Myocyte rest relies on the kinetics of cross-bridge biking, the affinity of Ca2+ for TnC, and the exercise of the Ca2+-reuptake mechanisms. Relaxation is enhanced by the increased kinetics of cross-bridge biking, decreased Ca2+ affinity for TnC, and increased exercise of Ca2+-reuptake mechanisms. Structurally, titin consists of an inextensible anchoring section and an extensible elastic phase. Titin is the principal determinant of the passive properties of the myocardium at small ventricular volumes. A sarcomere is outlined as the gap between Z strains (Z is an abbreviation for the German word, Zuckung, which means contraction), which be a part of the sarcomeres in collection. Titin, the third filament protein, tethers the thick-filament myosin to the Z line. The Z traces at the two ends of the sarcomere are introduced nearer collectively throughout contraction because the thick-filament myosin heads work together with the thin actin filaments and slide over each other. Its clinical options are left ventricular hypertrophy and myocyte and myofibrillar disarray. Mutations in no much less than eight completely different genes encoding sarcomere proteins have been identified to be the molecular basis for the dysfunction. These genes are -cardiac myosin heavy chain, cardiac troponin T (TnT), -tropomyosin, cardiac myosinbinding protein C, important or regulatory myosin mild chain, cardiac troponin I (TnI), -cardiac actin, and titin. The contractile equipment throughout the cardiomyocyte consists of contractile and regulatory proteins. Tropomyosin, a double-stranded -helical regulatory protein, winds around the actin array and forms the spine for the thin-filament actin. The cytoskeleton is the protein framework throughout the cytoplasm that hyperlinks, anchors, or tethers structural parts contained in the cell. Microfilament proteins are actin filaments, both sarcomeric or cortical, relying on their location. Sarcomeric actin filaments are the skinny filaments within the contractile equipment which were beforehand described. Cortical actin filaments are discovered under the plasma membrane at the cell floor and are linked to several other microfilament proteins, together with dystrophin, vinculin, and ankyrin. They have been demonstrated to be necessary in regular mitochondrial function and behavior. The desmin intermediate filament in cardiomyocytes connects the nucleus to the plasma membrane and is essential within the transmission of the stress and pressure of contractile pressure between cells. The parasympathetic nervous system has a extra direct inhibitory effect in the atria and has a adverse modulatory impact within the ventricles. Both norepinephrine and acetylcholine bind to seventransmembrane�spanning G protein�coupled receptors to transduce their intracellular signals and have an effect on their practical responses. During train or stress, nevertheless, the sympathetic neural influence turns into more distinguished. Supraventricular tissue receives considerably more intense vagal innervation than do the ventricles. The principal parasympathetic goal neuroeffectors are the muscarinic receptors in the coronary heart. In basic, for intracellular signaling, M1, M3, and M5 receptors couple to Gq/11 protein and activate the phospholipase C�diacylglycerol�inositol phosphate system. On the opposite hand, the M2 and M4 receptors couple to the pertussis toxin�sensitive G protein, Gi/o, to inhibit adenylyl cyclase. M2 receptors can couple to sure K+ channels and influence the exercise of Ca2+ channels, If present, phospholipase A2, phospholipase D, and tyrosine kinases.
Tags: discount sinemet 300 mg online, 300 mg sinemet buy fast delivery, purchase sinemet 300 mg, buy sinemet 125 mg lowest price, sinemet 300 mg purchase overnight delivery, sinemet 300 mg generic free shipping, sinemet 110 mg buy cheap line, sinemet 300 mg generic with mastercard, order 300 mg sinemet with mastercard, order 110 mg sinemet, sinemet 125 mg quality, purchase 300 mg sinemet amex, order sinemet 125 mg on-line, sinemet 125 mg mastercard, sinemet 125 mg low cost, 300 mg sinemet cheap visa
8 of 10
Votes: 180 votes
Total customer reviews: 180
Customer Reviews
Ronar, 49 years: This study is one of very few that makes an attempt to establish apply traits rather than specific medicine or strategies that have an effect on anesthesia outcomes. For instance, when an opioid is combined with a hypnotic, the rate of restoration from anesthesia depends on the opioid and hypnotic concentrations, the speed of lower in each drug concentrations, and the relative synergy between them for lack of response to noxious stimulation.
Tangach, 52 years: Lucchinetti E, Hofer C, Bestmann L, et al: Gene regulatory management of myocardial vitality metabolism predicts postoperative cardiac perform in sufferers undergoing off-pump coronary artery bypass graft surgical procedure: inhalational versus intravenous anesthetics, Anesthesiology 106:444-457, 2007. These drugs are also effective in the prophylaxis, but not the therapy, of migraine headaches and in controlling acute panic signs and essential tremor.
Oelk, 58 years: A lower in hematocrit can additionally be related to a rise in tissue blood flow. Despite the concurrent administration of anticholinergic drugs, a excessive incidence of bradyarrhythmias is noticed following anticholinesterase reversal (up to 50% to 60% of sufferers in some studies).
