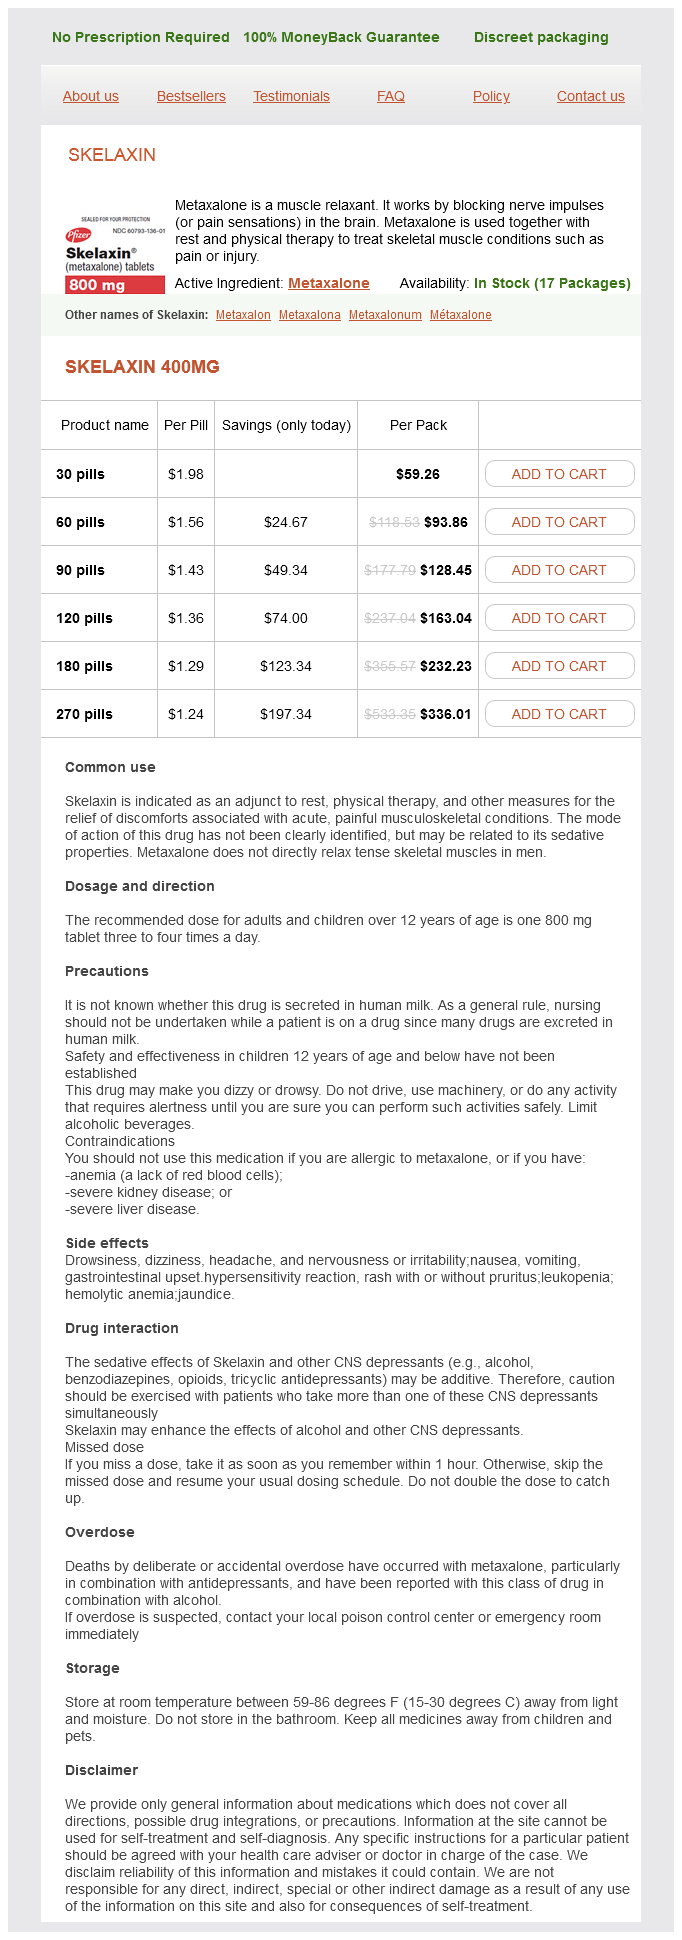
Skelaxin 400mg
- 30 pills - $59.26
- 60 pills - $93.86
- 90 pills - $128.45
- 120 pills - $163.04
- 180 pills - $232.23
- 270 pills - $336.01
Skelaxin dosages: 400 mg
Skelaxin packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills
In stock: 541
Only $1,32 per item
Description
For entry through the skin muscle relaxant herbs 400 mg skelaxin purchase, a spot roughly 1 inch lateral and 2 inches inferior to the sacral hiatus in the contralateral gluteal region on the affected facet for therapy is accessed muscle relaxant cyclobenzaprine dosage skelaxin 400 mg order fast delivery. This point of entry inherently permits the needle spasms in 7 month old buy 400 mg skelaxin with amex, in addition to the catheter bladder spasms 5 year old 400 mg skelaxin buy overnight delivery, to be directed toward the affected side. The nondominant index finger is used to set up the location of the sacral hiatus, and the finger stays at that location. Contralateral from the symptomatic aspect, 1 inch from the midline and 2 inches from the sacral hiatus on the gluteal mound, the pores and skin is infiltrated with a 25-gauge 1-1/2-inch needle with local anesthetic and is carried out along the tract to the sacral hiatus. Anteroposterior and lateral fluoroscopic views are taken and saved to make a three-dimensional evaluation if adjustment of depth or direction is required of needle placement. With the suitable correction, the needle is popped into the sacral canal through the sacral hiatus, and rotated one hundred eighty levels in order that the curve tip matches the direction of the sacral canal. The needle is superior to a level no greater than the S3 foramen to avoid damaging the sacral nerve roots. If venous runoff is famous, the needle tip is moved during injection until contrast media is seen spreading throughout the epidural house. As contrast media is injected into the epidural area, a "Christmas tree" form will be noted as the dye spreads into the perineural constructions contained in the bony canal and alongside the nerves as they exit the vertebral column. Epidural adhesions will forestall dye unfold, such that there might be a marked absence of dye outlining the concerned nerve roots. If the needle tip is subarachnoid, dye spread might be noted centrally and cephalad many ranges above L5. Prothrombin time, partial thromboplastin time, bleeding time, white blood cell depend with differential, urine evaluation, and magnetic resonance imaging of the affected space are normally reviewed. Radiological Studies Diagnostic findings must be documented previous to the procedure. Preprocedure Medication It could also be necessary to sedate the affected person with 1�2 mg midazolam and 25�50 g of fentanyl. For documentation functions, videotaping the fluoroscopy screen in the course of the process or printouts for subsequent review is commonly carried out. For personal security, the doctor should use applicable protecting measures similar to leaded gloves, apron, thyroid protect, and leaded glasses. An addition of a leaded skirt around the fluoroscopy table can further lower radiation exposure. The bevel of the needle should be going through the ventrolateral side of the caudal canal of the affected facet. This turning of the needle facilitates passage of the catheter to the specified side, and decreases the possibility of shearing the catheter. Because scar formation is often uneven, multiple passes could also be necessary to place the catheter into the scarred area. The contrast will improve the view of the outline of the nerve roots and the dura from the circumferential unfold inside the less-resistant subdural house. If blood is aspirated, the needle is first retracted caudally in the sacral canal till no blood may be aspirated. If that is unsuccessful, an attempt may be made to proceed with catheter placement into the proper location. Aspiration of this catheter ought to be unfavorable for blood, and lack of venous runoff should be confirmed by way of the injection of distinction agent. There is a learning curve that often takes 6�7 months to develop the mandatory three-dimensional abilities in accessing the sacral canal as described above. To thread the X-L catheter the steering is made simpler if a 1-inch, 15-degree bend is placed close to the tip. Early within the studying curve, a standard drawback develops from the tip of the needle being too close to the side wall of the sacral canal. The needle can be pushed or the tip rotated so that the threaded catheter is superior just short of the midline on the affected facet. Steering the catheter with the tip of the catheter pointing toward the neural foramen and the bent-tip elbow pointing medially often represents ventrolateral catheter tip placement. Note full filling defect on left at L4 and S1 and partial filling of the L5 spinal nerve. Next, 1500 U of hyaluronidase (Wydase) in resolution with 10 ml of preservative-free regular saline is injected rapidly. This extra quantity is useful in additional lysis of adhesions as a end result of the catheter tip is within the scar tissue. When correctly positioned, the patient usually reviews ache with injection in the dermatomal distribution of the scarred space. When the procedure is accomplished, the catheter ought to be secured to the pores and skin with 3-0 nylon on a cutting needle. Caution have to be taken to not puncture the catheter with the needle, as nicely as not minimize the catheter coating whereas wrapping it. Triple-antibiotic ointment, corresponding to polymyxin, and two 2 2-inch split gauze pads are used to cowl the catheter exit site. The surrounding skin is sprayed or lined with tincture of benzoin and, with a single loop of the catheter towards midline, the entire above is covered with a four 6�inch dimension sterile clear surgical dressing. On high of the clear dressing, we place two four 4�inch gauze pads over the puncture website and apply four pieces of 6-inch-long Hypafix tape over the world. Prior to undraping the sterile field, the catheter is linked to an adapter and a 0. Prophylactic antibiotics are given to forestall bacterial colonization, which is particularly hazardous in view of the epidurally administered steroid. It can also be our practice to ship a affected person residence on an oral antibiotic for five further days as epidural abscess prophylaxis. The objective of this positioning is to have a chronic hyperosmolar impact on the swollen painful nerve roots in order to cut back the edema and facilitate functional recovery. Please observe that the amount of hypertonic saline is similar or lower than the volume of local anesthetic previously injected. Occasionally, the affected person could complain of severe burning pain through the infusion. The burning is normally from the introduction of hypertonic saline to unanesthesized epidural tissue. Should this occur, the infusion must be stopped and a 3�5-ml bolus of extra native anesthetic is injected. After 5 minutes, the hypertonic saline infusion can be restarted without incident. The hypertonic saline has a gentle, reversible native anesthetic impact and likewise reduces edema of beforehand scarred or infected nerve roots. If the hypertonic saline spread is bigger than the protection space of the local anesthetic, the patient may have severe ache. The ache caused by the hypertonic saline in the epidural space not often persists more than 5 minutes. The absence of motor block from local anesthetic is an assurance of epidural placement. Hypertonic saline will broaden by osmotic effect to 11 instances the original injected quantity, so that whether it is injected in the subdural or subarachnoid spaces, the hypertonic saline would exert pressures on surrounding subdural constructions secondary to the volume expansion. Therefore, it could be very important use radiological, distinction, and pharmacological confirmation of placement to prevent the volume-related compression of structures within the dural sac. Fifteen minutes later, 9 ml of 10% saline is infused over 20 minutes for patient comfort. As with all hypertonic saline infusion collection, the catheter should be flushed with 1. A triple-antibiotic ointment is positioned on the wound and is roofed by a bandage or other applicable dressing. We have demonstrated in our laboratory that when methylprednisolone (Depo-Medrol) plus native anesthetic or triamcinolone (Aristocort) and native anesthetic are injected through a bacteriostatic filter, the filter screens out nearly all of the steroid. For the infusion, the patient is positioned within the lateral position with the painful side down and remains on this place for 30 minutes following the com- 416 Pelvis that the patient hold the realm dry for 48 hours after removing to decrease the prospect of infection. Showering is permitted after this period, however immersion of the wound such as in a bath or pool remedy ought to be averted for no much less than 7 to 10 days. This process is often followed by vital improvement in ache and motor function.
Duffle (Mullein). Skelaxin.
- How does Mullein work?
- What is Mullein?
- Dosing considerations for Mullein.
- Are there safety concerns?
- Use on the skin for wounds, burns, hemorrhoids, bruises, frostbite, and other uses.Use by mouth for earaches, colds, flu, asthma, diarrhea, migraines, gout, tuberculosis, croup, cough, sore throat, inflammation of the airways such as bronchitis, and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96569
Rasmussen L muscle relaxant hyperkalemia skelaxin 400 mg with amex, Lawaetz M spasms right flank 400 mg skelaxin cheap visa, Bjoern L muscle relaxant bruxism order skelaxin 400 mg, Blemings A muscle relaxant powder 400 mg skelaxin trusted, Eklof B: Randomized scientific trial comparing endovenous laser ablation and stripping of the nice saphenous vein with medical and duplex end result after 5 years. Currently, there are approximately a hundred and fifty transplant centers and a pair of,200 heart transplant procedures carried out yearly in the United States. Current immunosuppressive protocols encompass a mix of a calcineurin inhibitor with prednisone and mycophenolate mofetil. Immunosuppression begins both immediately preop or perioperatively and can continue all through the lifetime of the patient. Current 1-yr survival averages 85% in most facilities with 3-yr survival of roughly 80%, and a median survival approaching 10 years. I n grownup coronary heart transplantation, following median sternotomy, the pericardium is opened with care being taken to protect the phrenic nerve. This is followed by an incision via the atria, and the recipient coronary heart is eliminated. The donor heart is attached by a protracted, continuous suture line across the left atrium, followed by separate anastomoses to the inferior and superior vena cavae. Alternatively, the donor proper atrium is anastomosed to the recipient right atrium with a single long continuous suture. Multiple de-airing maneuvers are adopted by aortic unclamping and rewarming and resuscitation of the guts. Heparin is reversed, hemostasis is secured, and the chest is closed in a routine method. Following chest closure, these patients will typically have implanted defibrillators that might be eliminated. The coronary heart is then excised, and the transverse aortic arch is opened past the ductus arteriosus to minimize danger of late coarctation. The donor heart is prepared, with special attention given to trimming the transverse aortic tissue for subsequent reconstruction. Patients often have had earlier cardiac surgery, and reentry and excision of the native heart are complicated by the presence of adhesions and graft material from earlier attempts at palliative/corrective surgical procedure. Patients are often highly sensitized and should require intraoperative plasmapheresis whereas on cardiopulmonary bypass. Preparation for cardiopulmonary bypass is often similar to the adult coronary heart transplant affected person, and the implantation process is also similar. However, provisions must be made for extended cross-clamp times essential for implantation in the setting of abnormal systemic-cardiac or pulmonary-cardiac connections. A Hx of recent exacerbation of cardiac dysfunction must be sought, and all information should be interpreted in gentle of interval adjustments. After the patient is placed on the operating table, O 2 and noninvasive displays are applied. Dyspnea (a complication of the supine position) may be handled by raising the again of the desk. As infection is a critical complication in the immunosuppressed transplant affected person, aseptic approach is extraordinarily essential. The anesthesia machine should be geared up with a provide of air to control the FiO2. Subsequently, single-lung transplantation was efficiently carried out in 1984 and an en bloc, double-lung transplant in 1986. Clinical lung transplantation of those numerous types has elevated markedly in the final few years, and presently, approximately 600 single-lung transplants, a thousand bilateral lung transplants, and 30 heart/lung transplants are carried out in the United States annually. Recipients for single-lung transplant normally have end-stage pulmonary disease with out vital sepsis. This consists of patients with interstitial fibrosis, emphysema, and lymphangioleiomyomatosis. Bilateral lung transplantation is now carried out normally as a sequential single-lung transplant with the most important indications being septic lung disease, similar to cystic fibrosis, continual bronchiectasis, extreme bullous emphysema, or pulmonary vascular disease with or with out cardiac repair. Current immunosuppressive protocols include a mix of tacrolimus with prednisone and myophenolate mofetil, with or with out early induction therapy, using a cytolytic agent. Immunosuppression could start preop and continue throughout the lifetime of the patient. Current 1-yr survival rates average 70% for heart/lung transplants and 80% for lung transplants. Heart/lung transplants usually are performed through a median sternotomy, though often bilateral, transsternal thoracotomy has been used. Single-lung transplants (usually left side) and bilateral sequential lung transplants use a lateral thoracotomy, transsternal bilateral thoracotomy, or median sternotomy. For combined transplants, the recipient heart is removed as for standard heart transplantation (see Surgery for Heart Transplantation, p. Next, each recipient lung is excised, and the trachea is transected above the carina. Bilateral sequential lung transplants are carried out as in the occasion that they had been single-lung transplants. Prior to closure, intensive exploration for potential bleeding sites inside the posterior mediastinum is carried out with placement of proper and left pleural and mediastinal drainage. The commonplace preanesthetic analysis is supplemented with issues particular to these sufferers. Infection is a critical potential complication within the immunosuppressed transplant affected person; thus, aseptic technique is necessary. The progression of the disease is usually well documented; however, Hx of recent exacerbation of signs should be sought. Infection is a critical complication in the immunosuppressed transplant patient; thus, the aseptic approach is necessary. Della Rocca G, Pugliese F, Antonini M, et al: Hemodynamics during inhaled nitric oxide in lung transplant candidates. Feltracco P, Serra E, Barbieri S, et al: Anesthetic considerations in lung transplantation for extreme pulmonary hypertension. Macdonald P, Mundy J, Rogers P, et al: Successful therapy of life-threatening acute reperfusion injury after lung transplantation with inhaled nitric oxide. Mair P, Balogh D: Anaesthetic and intensive care issues for sufferers present process coronary heart or lung transplantation. To perform an esophagostomy, the esophagus is approached through a left cervical incision. The sternocleidomastoid muscle and carotid sheath are retracted laterally and the thyroid medially, exposing the cervical esophagus. The esophagus is mobilized with care being taken not to injure the left recurrent laryngeal nerve, which typically lies within the tracheoesophageal groove. The esophagus is introduced to the pores and skin surface as a loop or end stoma and sutured to the skin with absorbable sutures. They are associated with incomplete, or discoordinate, upper esophageal sphincter relaxation and the resultant elevated hypopharyngeal stress produces a narrow-mouthed posterior diverticulum. These diverticula incessantly present within the seventh decade and are 2�3 instances extra frequent in men. Early on, sufferers may complain of imprecise pharyngeal sensations, dysphagia, cough, and extra salivation. Later, more severe symptoms-such as extreme (or frequent) dysphagia, regurgitation of meals, halitosis, voice adjustments, aspiration, and odynophagia (painful swallowing)-may occur. B: As the diverticulum enlarges, it drapes over the cricopharyngeus sphincter and descends into the superior mediastinum in the prevertebral house. Multiple completely different operative approaches are advocated: diverticulectomy alone, cricopharyngeal myotomy, diverticulectomy with myotomy, and myotomy with suspension of the diverticulum. Myotomy alone, which corrects the underlying physiologic abnormality, is up to 78% effective and may be considered for sufferers with small (< 2 cm) diverticula. Diverticulectomy or suspension ought to be added if the diverticulum itself is massive or dependent. The upper esophagus is exposed by retracting the sternocleidomastoid muscle and carotid sheath laterally and the thyroid gland medially.
Specifications/Details
Strong contraindications embrace unfamiliarity with the procedure muscle relaxant lactation skelaxin 400 mg discount without prescription, patient refusal muscle relaxant 2632 discount 400 mg skelaxin with amex, an infection at web site spasms medication skelaxin 400 mg order with mastercard, and allergies to the agents getting used muscle relaxant in spanish skelaxin 400 mg low cost. The block can even present momentary reduction from muscle spasm or strain in the supraspinatus and infraspinatus muscular tissues. Other contraindications embrace pre-existing neuropathy, specific stature (short neck, stiff neck, and so on. Additional contraindications embody thorax deformity, dislocated healed clavicular fracture, pre-existing neuropathies, and the presence of overseas bodies within the space. This block can be indicated for arm and forearm surgical procedure, in addition to the insertion of arteriovenous grafts for hemodialysis. The interscalene catheter is indicated for acromioplasties, carcinologic surgical procedure and physiotherapy of the shoulder, rotator cuff repair, and total shoulder arthoplasty. Other contraindications embrace coagulopathy, prior neck surgery or radiation, ipsilateral/contralateral pneumothorax, contralateral phrenic and recurrent paresis, and chronic obstructive pulmonary disease. Although lidocaine and mepivacaine are commonly used for single-shot blocks, probably the most commonly most well-liked local anesthetics to be used in long-term ache relief and steady infusion are bupivacaine and ropivacaine. The metabolites also stay at insignificant levels with out inflicting any deleterious impact. However, steady infusions ought to be used with caution when treating sufferers with liver and kidney illness. Due to the elevated threat of inadvertent intravascular injection on this area, the native anesthetic should be injected slowly and with frequent aspiration. Also, because of this, use of bupivacaine is contraindicated because of its excessive cardiotoxicity. The risk�benefit ratio of using massive concentrations of local anesthetic throughout this strategy have to be examined prior to performing the block. The risk/benefit ratio of utilizing large concentrations of native anesthetic during this strategy should be examined prior to performing the block. Conventional electrocardiogram-type electrodes are suitable, however care should be taken to make positive that they make good contact with clean, dry pores and skin. The syringe containing the anesthetic resolution is attached to an extension set filled with anesthetic answer. The needle is advanced slowly, while the forearm and hand are noticed carefully for muscle actions. Flexion or extension of the elbow, wrist, or digits confirms that the needle is in shut proximity to nerve fibers of the brachial plexus, normally within 1�2 cm of the nerve. If the twitch decreases with needle advancement, the needle is likely to one aspect of the nerve and must be repositioned. After cautious aspiration, 1�2 ml of anesthetic answer is injected by way of the needle. The immobile needle method described by Winnie is appropriate in this scenario. It is essential to verify on the situation of the battery, as its failure might cause the muscle twitch to stop. In addition, muscle twitch cessation could occur as a outcome of a free connection, improper needle placement, or some other unknown purpose. Immediately after muscle motion has ceased, the remaining anesthetic solution ought to be injected by way of the needle. The onset of the block occurs initially within the area supplied by the nerve to the muscles that were twitching. Proximal muscle groups are typically paralyzed sooner than the incidence of sensory loss or sympathetic block. The Acromioclavicular joint Medial finish of the clavicle Coracoid process Head of the humerus Sternoclavicular joint the length of the clavicle is defined by finding the acromioclavicular junction and the sternoclavicular junction, and then figuring out the midpoint between them. Using the beforehand mentioned technique for utilizing a peripheral nerve stimulator, the stimulating needle is inserted at a 45-degree angle to the skin beneath the clavicle and advanced towards probably the most proximal level at which the axillary artery may be palpated. After acceptable nerve stimulation is elicited (preferably the medial nerve), 2 cc of saline are injected to know that the contraction of the muscle visualized is totally gone. Note the connection of the neurovascular structures within the brachial plexus sheath. The C-arm ought to be in anteroposterior place with the arm abducted to ninety degrees. Once the confirmation is obtained that the needle is correctly placed on the brachial plexus, as much as forty ml of native anesthetic are injected incrementally. As quickly because the stimulation of the catheter determines the right location, the stylette is eliminated and the catheter anchored well with a suture or steristrips. The landmarks used through the block embody the next: the axillary arterial pulse is palpated proximally and marked. The approximate location of the brachial plexus can be determined by percutaneous nerve stimulation. After the skin is antiseptically ready, local anesthetic is infiltrated subcutaneously at the needle insertion web site. Two fingers are then used to palpate the hole between the axillary artery and the coracobrachialis muscle with stress applied distally (minimizing the chance of inadvertent lateral or medial placement of the needle outdoors the sheath). The insulated needle is inserted at the lateral aspect of the coronary heart beat at a 45-degree angle and directed cephalad until median nerve stimulation is obtained (typically at a depth of 1�2 cm). After injection, the needle is removed and fixed digital pressure is maintained because the Sternal head of sternocleidomastoid muscle Clavicle head of sternocleidomastoid muscle Midclavicle After the pores and skin is antiseptically ready, the needle is inserted superior to the midpoint of the clavicle within the backward-inward-downward course. Note the insertion of the needle 1�2 cm superior to the midclavicular level in a backward-inwarddownward course towards the first rib. The musculocutaneous nerve lies in the coracobrachialis muscle, exterior the brachial plexus sheath at this site. Once stimulation is obtained, negatively aspirate for air or blood, after which inject 1�3 ml of local anesthetic. If no systemic results are detected after 5 minutes, the entire calculated volume of native anesthetic (typically forty ml) is injected incrementally. However, the usage of this approach is limited by the elevated danger of pneumothorax. To address these problems, Theiss carried out the supraclavicular utilizing the distinction medium underneath fluoroscopic guidance. The subclavian artery was identified by the groove the place the first rib begins to curve posteriorly. These circumstances may result in an inability to correctly localize the anatomic site for needle insertion and result in improper needle placement, thus resulting in inadequate ache control. The landmarks used during the block embody: Sternal notch Clavicle Sternal head of sternocleidomastoid muscle Clavicular head of sternocleidomastoid muscle Mastoid course of the clavicle, exterior jugular vein, and the posterior border of the clavicular head of the sternocleidomastoid muscle are marked with a pen. The level of entry is close to the purpose where the exterior jugular vein crosses the sternomastoid. The palpating hand should be gently but firmly pressed between the anterior and middle scalene muscular tissues, also referred to as the interscalene groove, to shorten distance from the skin to the brachial plexus. A stimulating needle is guided via insertion point and superior perpendicular to the skin plane and barely caudad; the needle ought to never be oriented cephalad. The slight caudad direction minimizes the possibility of inadvertent spinal of epidural placement. Once stimulation is achieved (the contraction occurring ideally under the shoulder) at a present of lower than zero. The benefit of this technique is that the catheter can stay in the interscalene groove longer and not become dislodged in a brief period. The proximity of the nerves to the axillary artery and other giant vessels causes an increased threat for inadvertent vascular punctures or local anesthetic toxicity from intravascular absorption. Because paresthesias are elicited, the potential for postblock, persistent paresthesia exists. The risk of pneumothorax is potentially greater than with different brachial plexus blocks and is associated with an overture of the clavicle�needle angle. Other problems can include phrenic paralysis, recurrent laryngeal nerve paralysis, and excessive spinal or epidural anesthesia.
Syndromes
- Advanced care directives
- Were you sick with a cold, flu, or other illness before the dizziness began?
- Nervousness
- Decreased muscle tone at birth
- Female (premenopausal): 30 to 400 pg/mL
- Babies of women who become infected during pregnancy are at risk for premature birth. The baby may develop brain infection (meningitis, encephalitis) , chronic skin infeciton, severe developmental delays, or death.
Related Products
Additional information:
Although the inner carotid artery and jugular bulb move through the center ear muscle relaxant drugs z proven 400 mg skelaxin, significant vascular harm is sort of rare spasms right side abdomen purchase skelaxin 400 mg on line. Most if not all bleeding may be readily managed with packing in the surgical area muscle relaxant anesthesia skelaxin 400 mg effective. Venous injury muscle relaxant definition purchase skelaxin 400 mg without a prescription, corresponding to laceration of the sigmoid sinus throughout mastoidectomy, can often be controlled utilizing bone wax or with different hemostatic materials. In the case of a big venous harm, a venous air embolism can potentially end result, and timely communication between the surgical and anesthesia groups can facilitate its identification and remedy. More severe arterial harm may require additional neuroradiologic or neurosurgical intervention. Even in these rare cases, hemodynamically important blood loss can often be prevented with prompt and secure packing. The temporal bone abuts the dura of the middle fossa above and the posterior fossa behind. Rarely, transgression of the dura can result either as the outcome of pathology or from dissection of adjoining tissues. When this happens, the surgeon can usually shut the leak using autologous tissues. The surgeon may request administration of a Valsalva maneuver to check the integrity of the restore. Usual preop diagnoses: Acute or persistent otitis media, cholesteatoma, listening to loss (conductive or sensorineural), otosclerosis, aural atresia (acquired or congenital), tympanic membrane perforation, temporal bone fracture, temporal bone neoplasm. In contrast, ossicular and tympanic membrane reconstruction with facial nerve preservation may final several hours. Patients presenting for external ear reconstructions could have related congenital abnormalities, which should be considered preop. Dal D, Celiker V Ozer E, et al: Induced hypotension for tympanoplasty: a, comparison of desflurane, isoflurane and sevoflurane. Erhan E, Ugur G, Alper I, et al: Tracheal intubation with out muscle relaxants: remifentanil or alfentanil in combination with propofol. Gupta A, Stierer T, Zuckerman R, et al: Comparison of recovery profile after ambulatory anesthesia with propofol, isoflurane, sevoflurane and desflurane: a systematic evaluate. Richa F, Yazigi A, Sleilaty G, et al: Comparison between dexmedetomidine and remifentanil for managed hypotension throughout tympanoplasty. Neurotologists primarily deal with lesions within the posterior fossa, which is bordered by the clivus (anterior), temporal bone (lateral), and occipital bone (posterior). An axial view of the skull via the level of the internal auditory canal and cerebellopontine angle. Removal of the skull base bone permits publicity to these lesions whereas minimizing cerebral and cerebellar retraction. This is certainly one of the mostly approached areas in cranium base surgery and lesions embrace vestibular schwannomas (91. Anatomical relationships of the cerebellopontine angle proven by way of a retrosigmoid posterior fossa craniotomy. The translabyrinthine strategy uses a postauricular incision to access the temporal bone. Retraction of the temporal lobe and cerebellum is minimized as the entire mastoid and labyrinth are removed to create access. This method leads to full sensorineural hearing loss and is mostly utilized in patients with massive tumors and/or nonserviceable listening to. Patients with serviceable listening to might elect for a hearing conservation approach for their tumors (retrosigmoid or middle fossa). The retrosigmoid approach uses a extra posterior craniotomy between the sigmoid and transverse sinuses. The cerebellum is retracted posterior away from the petrous face of the temporal bone. Disadvantages embody the increased Neurotological Skull Base Surgery incidence of postop headache and the need for rigid skull fixation. The center fossa method locations the craniotomy above the ear and requires retraction of the temporal lobe. This approach has the best fee of hearing conservation, but can only be utilized in smaller tumors without growing the chance of postop facial palsy. Typical left translabyrinthine posterior fossa craniotomy publicity of a medium-sized tumor. Inferiorly, the decrease cranial nerves (A) are seen, and the jugular bulb (B) has been identified. The facial nerve (F) takes a variable and infrequently serpentine course throughout the medial facet of the tumor. The retractor is engaged over the posterior lip of the petrous bone and retracts the temporal lobe. The facial nerve usually courses across the superior aspect of the tumor surface. Paragangliomas are divided into two groups: (a) adrenal paragangliomas (also often recognized as pheochromocytomas) and (b) extraadrenal paragangliomas situated in the stomach, chest, and head and neck areas. Less frequent pathologies in this area embody meningiomas and lower cranial nerve schwannomas. Glomus jugulare tumors are extremely vascular, and patients bear preop embolization before surgery. Two to four U of autologous or crossmatched blood are kept obtainable depending on the size and extent of the tumor. In addition to a lateral craniotomy much like the translabyrinthine strategy, a restricted neck dissection is performed to acquire vascular control of the jugular vein and carotid artery. This transjugular craniotomy exposes the complete jugular fossa and entails resection of the concerned sigmoid sinus and jugular vein. New decrease cranial nerve deficits occur in 25�50% of sufferers; therefore appropriate airway and aspiration precautions should be taken. Transjugular craniotomy illustrating the degree of intracranial exposure obtained following resection of the sigmoidjugular system and wide opening of the posterior fossa dura. Note the a quantity of small rootlets of the lower cranial nerves emanating from the lateral surface of the medulla. In distinction to extracranial procedures, the sigmoid sinus is ligated proximally rather than packed extralumenally. The sigmoid sinus has been controlled with a suture ligature just distal to the transverse-sigmoid junction. This allows room for the operating microscope, scrub assistant, and surgeon to all be placed across the head of the affected person. As lateral table rotation is often used throughout these instances, three straps should be used to safe the affected person, and the contralateral arm should be well padded so as to keep away from ulnar neuropathy. Operating room setup for posterior fossa craniotomy (translabyrinthine, retrosigmoid, and transjugular). Stable low blood pressure is beneficial in controlling slow bleeding within the surgical area. Significant hemodynamic blood loss is uncommon and may often be managed with secure packing. Large venous injuries may end in air embolism, and arterial accidents might require the help of interventional neuroradiology. Having 1 U of cross-matched blood out there is prudent in most craniotomies, whereas 2�4 U may be required in glomus jugulare cases. The same preop pharmacologic stabilization used for patients with a pheochromocytoma could additionally be required for these sufferers (see p. Intraop, the discharge of histamine and bradykinin can cause bronchospasm, tachycardia, and both hypotension and hypertension. The anterior cranium base is a typical location for lots of intradural and extradural cranial and/or facial pathologies. The anterior cranial base surgical procedure might contain combined transethmoid incision and bifrontal craniotomy approaches. With that approach, the intraop surgical navigation set is regularly used, and a lumbar drain could also be placed after induction of anesthesia.
Usage: p.o.
Other serious complications described are pulmonary embolism muscle relaxant before massage skelaxin 400 mg low price,24 muscle relaxant 16 cheap skelaxin 400 mg amex,25 cardiac arrest and death spasms upper back buy skelaxin 400 mg cheap,26 and reactivation of infections muscle relaxant name brands proven skelaxin 400 mg. In comparison to vertebroplasty, the cement used in kyphoplasty has the next viscosity and the stress wanted for application is significantly less. Other studies have reported an additional danger of the procedures in themselves producing altered mechanical forces that induce new fractures in the adjoining vertebrae. Sticker K, Orler R, Yen K, et al: Severe hypercapnia as a end result of pulmonary embolism of polymethylmethacrylate during vertebroplasty. Fribourg D, Tang C, Sra P, et al: Incidence of subsequent vertebral fracture after kyphoplasty. The percutaneous kyphoplasty technique1 is an extra growth of vertebroplasty. During a vertebral compression fracture, the cortical bone buckles and cracks while the cancellous bone collapses and turns into compacted, thereby decreasing the overall peak and volume of the vertebra. Some fractures could collapse acutely whereas others collapse progressively over time. Kyphosis compresses the chest and belly cavity with the potential penalties of continual, debilitating ache, decreased lung operate,4,5 decreased activities of day by day living, elevated dependence on members of the family, and a 23% enhance in mortality price. Open surgical remedy can address the deformity but is often reserved for instances of neurologic deficit. Multiple earlier surgeries or weight problems might impede proper identification of anatomical landmarks. With kyphoplasty, burst fractures with destruction of the posterior wall represent a relative contraindication as a end result of the risk of extravasation of the cement into the epidural area is theoretically lowered. Pre-existent neurological deficit is a contraindication, since any minor cement leakage might worsen the deficit. However, fractures older than 3 months are much less prone to benefit from the technique. As in vertebroplasty, prophylactic antibiotics are given intravenously (1 g cefazolin). Padding of strain factors is necessary to avoid rib fractures and to add comfort. The vertebral physique and the pedicles are identified, and the x-ray beam is obliqued sufficient to see the pedicle as a circle. The entry level for the transpedicular technique is within the lateral superior quadrant of the pedicle. In the higher thoracic region an extrapedicular route lateral to the pedicle is recommended. This strategy allows the needle tip to be angled extra towards the center of the vertebra and thus allows straightforward filling of the vertebra with a single needle. Local anesthesia is injected to the skin, subcutaneous layer, and the periosteum of the bone on the bony entry site. In the lateral view, the needle should be on the upper midpoint of the pedicle in order that the needle advances within the midpoint of the pedicle. In fractured vertebral bodies with vertebral end-plate depression, a extra horizontal direction may be required to avoid traversing the top plate. In osteoporotic vertebrae, the insertion of the cannula is straightforward, however in osteoblastic tumors it can be more durable. With a lateral fluoroscopic projection, on the posterior vertebral physique, the beveled needle is rotated a hundred and eighty levels to point medially and advanced into the anterior third portion of the vertebra, since this area is devoid of venous plexuses. The dimension of the balloon is selected on the premise of the vertebral body to be treated. After checking the positioning by anterior and lateral fluoroscopy, the balloons are inflated with radiopaque distinction medium by a particularly designed syringe with continuous control of strain and volume. This generates a radial drive that compacts the cancellous bone within the periphery, increasing the energy of the cortical bone and making a cavity inside the vertebral physique. The chance of injecting the cement beneath low pressure after having created a cave with the balloon, together with the restoration of vertebral physique peak, is an obvious theoretical benefit of the kyphoplasty technique over the vertebroplasty approach. The location of the treated stage seems to influence the extent of augmentation as well since kyphoplasties of the lumbar backbone usually have a tendency to achieve a major peak restoration than those of the thoracic backbone. The majority of kyphosis correction by kyphoplasty is proscribed to the vertebral body treated. It has been instructed that kyphoplasty is safer than vertebroplasty relating to the danger of cement leakage, even though a cement leakage is seen in 10% of instances. The actual mechanism by which this creates pain relief is yet to be totally understood. This thought led to the event of peripheral nerve and dorsal column stimulation. Other constructions within the mind have been explored as potential targets for stimulation, together with motor cortex. Nevertheless, the physiological rationalization for pain relief by somatosensory thalamic stimulation remains to be unclear. Several neurophysiological mechanisms have been proposed, starting from the activation of local inhibitory systems in the thalamus to activation of descending inhibitory techniques. Descending pathways from the nucleus raphe magnus to the dorsal horn have been described. There is proof for the existence of a quantity of descending antinociceptive systems within the midbrain, some involving endorphinergic and other monoaminergic mechanisms. Among these are the habenula, the locus coeruleus, the subcoeruleus-parabrachial complicated, the magnocellular a half of the nucleus reticularis gigantocellularis, and the K�lliker-Fuse nucleus region. Only a quantity of studies have examined the impact of stimulation in animal models of chronic pain. In distinction, no such experimental knowledge had been obtainable for the somatosensory thalamus. Although investigators found that after thalamic stimulation, B-endorphin ranges have been greater than twice the resting stage, no variations in B-endorphin ranges might be demonstrated between patients reporting full pain aid and people reporting solely partial aid. Five patients suffering from neuropathic pain for whom electrical stimulation of the somatosensory thalamus had produced passable long-term pain aid had been included within the research. A temporary trial stimulation is necessary before a neurostimulation gadget is implanted. This take a look at should be sufficiently lengthy, and the results should preferentially be evaluated by an unbiased third party. The purpose of the check is to ensure that the pain aid is adequate to justify permanent implantation and that the patient is able to use the neurostimulator gadget correctly. Therefore, an evaluation of the pathophysiology of the ache syndrome is of significance. An entry level is marked just anterior to the coronal suture, which defines the laterality of strategy based mostly on the ventricular width. Each electrode is tried individually (1�2 days of each) to cowl the world of ache and obtain maximum pain relief. This method was largely abandoned after the negative outcomes published in two multicenter trials within the Eighties. The effectiveness of the process is also shown in an N-of-one study27 by which the affected person with neuropathic pain information ache scores and the stimulator is randomly turned on or off. In apply, capturing the entire space of pain can be difficult, notably with hemi-body ache. Each electrode is moved intraoperatively proximally or distally alongside its track till the widest potential involved space is roofed with the center two contacts. The electrodes are fixed to the cranium prior to externalization for the trial stimulation part. A long-term success fee of greater than 80% was attained in sufferers with intractable low back pain and failed back surgery syndrome. Trial stimulation was successful in approximately 50% of sufferers with poststroke ache, and 58% of patients with permanent implantation achieved ongoing ache reduction. Moderately larger charges of success have been seen in sufferers with phantom limb pain and radiculopathies. The use of a quadripolar electrode permits stimulating a selection of sites in the brain by easy parameter adjustment. Of particular medical importance are the findings by Tsubokawa and colleagues32 that the neuronal hyperactivity within the subnucleus caudalis of the spinal trigeminal nucleus that appears after transection of the trigeminal nerve is healthier inhibited by motor cortex stimulation than by sensory cortex stimulation. They further hypothesized that the ache inhibitory function of the somatosensory lemniscal system continues to be operative above the level of the deafferentation and that precentral gyrus stimulation selectively prompts non-nociceptive neurons within the sensory cortex. The corticospinal tract originates because the axons of pyramidal neurons in layer V of (mainly) major motor cortex, travels by way of the pyramids of the brainstem, and eventually ends on or close to the -motor neurons.
Tags: 400 mg skelaxin discount free shipping, 400 mg skelaxin free shipping, buy discount skelaxin 400 mg on-line, generic 400 mg skelaxin, skelaxin 400 mg buy with amex, 400 mg skelaxin generic, skelaxin 400 mg safe, skelaxin 400 mg buy overnight delivery, 400 mg skelaxin purchase visa, cheap 400 mg skelaxin with visa, skelaxin 400 mg buy without a prescription, generic skelaxin 400 mg fast delivery, 400 mg skelaxin order free shipping, skelaxin 400 mg cheap mastercard, buy 400 mg skelaxin visa, buy skelaxin 400 mg
10 of 10
Votes: 168 votes
Total customer reviews: 168
Customer Reviews
Grim, 60 years: The examine excluded patients with dominant signs of low back pain, disc extrusion, sequestration, subarticular or foraminal stenosis, or a quantity of levels of herniation. Periodic analysis of the patient, together with vital signs, level of comfort, degree of consciousness, and visualization of the injection sites are really helpful.
Leif, 25 years: A double U-shaped 18- or 20-ga wire is handed underneath the arch of C1 from inferior to superior. Only when this portrait of viral activities and virus�host interactions in natural infections had emerged might growth start to establish appropriate experimental model systems that recapitulate real infections or selected elements of those infections.
Rasul, 55 years: When the contact with the bone is misplaced at a depth of 3�4 cm from the point of entrance, the needle is then advanced 0. Tsubokawa T: Motor cortex stimulation for the reduction of central deafferented pain.
Kan, 38 years: Bare sclera excision could be started from the corneal apex or by incising across the conjunctival body of the pterygium. Constant communication amongst surgeons, perfusionist, and anesthesiologist is mandatory for a clean operation.
Kurt, 41 years: Careful preblock neurologic assessment is important to keep away from later attribution of pre-existing neurologic deficits to the femoral nerve block. Fluoroscopic identification of the disc stage is performed with the aid of a needle placed at the pores and skin surface.
Tarok, 65 years: Blind clamping must be averted, but often, with good publicity, a Satinsky clamp may be placed. The head must be saved straight with the mouth barely open to relax the strain on the anterior cervical musculature.
Delazar, 22 years: Patients may suffer from repeated episodes of cholangitis or obstructive jaundice from particles occluding the anastomosis. Chronic pain might cause patients to overreact due to compromised ache tolerances and irregular psychology.
