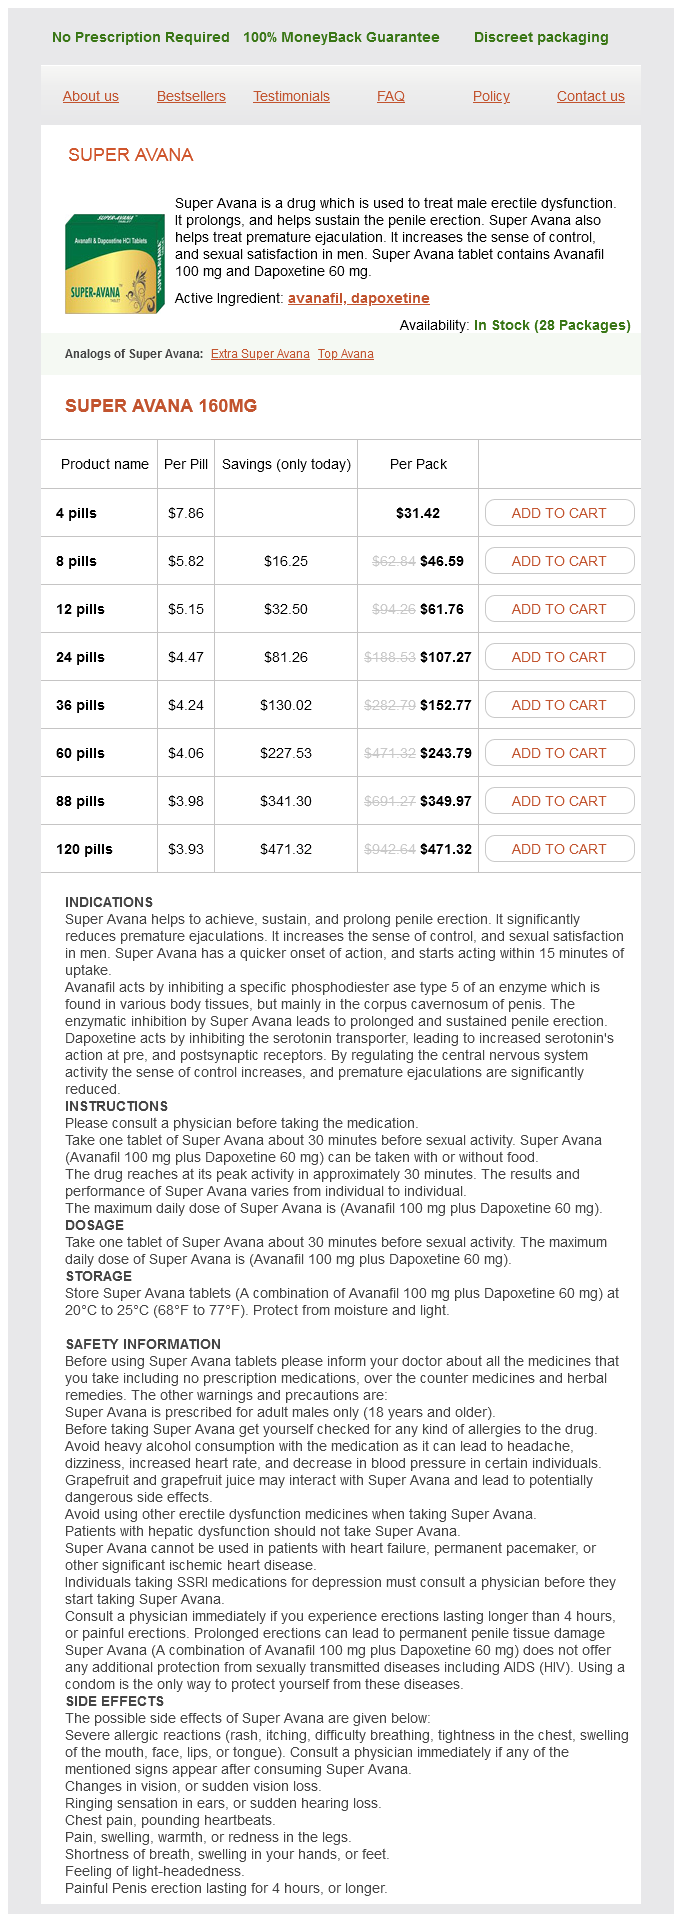
Super Avana 160mg
- 4 pills - $31.42
- 8 pills - $46.59
- 12 pills - $61.76
- 24 pills - $107.27
- 36 pills - $152.77
- 60 pills - $243.79
- 88 pills - $349.97
- 120 pills - $471.32
Super Avana dosages: 160 mg
Super Avana packs: 4 pills, 8 pills, 12 pills, 24 pills, 36 pills, 60 pills, 88 pills, 120 pills
In stock: 555
Only $4,17 per item
Description
Both the circular and the longitudinal muscle layers improve in thickness towards the duodenum erectile dysfunction tools super avana 160 mg buy cheap on-line. The musculature of the orad abdomen is skinny alcohol and erectile dysfunction statistics buy super avana 160 mg visa, contractions are weak erectile dysfunction treatment chinese medicine generic 160 mg super avana, and during the the rest of the digestive state erectile dysfunction treatment bodybuilding super avana 160 mg generic free shipping, pressures are essentially equal to intraabdominal stress, with superimposed tonic strain modifications. These pressure changes are predominantly of low amplitude and have durations of 1 minute or extra. The contractions that produce these stress modifications cut back the dimensions of the stomach because the stomach empties. These tonic contractions lead to lodging of the remaining gastric contents and propulsion of those contents into the caudad abdomen. A consequence of this minimal contractile exercise is that little mixing of ingested contents occurs within the orad stomach. Contents usually remain in relatively undisturbed layers for an hour or extra after consuming. As a result, salivary amylase (see Chapter 7), which is inactivated by gastric acid, can digest a important portion of the starch current in a meal. Little is understood in regards to the regulation of contractions within the orad abdomen throughout digestion. Sensors within the caudad region detect peristaltic contractions, which start within the midportion of the stomach and progress towards the gastroduodenal junction. The contractions enhance in force and velocity as they near the junction, and they repeat at multiple intervals of 12 to 20 seconds. The presence and drive of contractions depend on the digestive state of the person. After eating, phasic contractions of variable depth occur almost continuously. As contractions method the gastroduodenal junction, they improve in each pressure and velocity. At anybody locus of the human stomach, the length of every contraction ranges between 2 and 20 seconds, and the utmost frequency is roughly three contractions per minute. Between contractions, pressures in the caudad region are close to intraabdominal ranges. Contractions of the caudad area of the stomach serve to each combine and propel gastric contents. However, as a outcome of the peristaltic wave increases in velocity as it approaches the junction, the contraction overtakes the gastric contents. Before and through this contraction, a portion of the contents is propelled into the duodenum. Retropulsion causes an intensive mixing of the gastric contents and mechanically reduces the scale of stable particles. In the midregion, nonetheless, sluggish waves happen repeatedly at intervals of 12 to 20 seconds. Slow waves give the appearance of transferring via the caudad area at growing velocities. Smooth muscle cells on this area have a membrane potential that fluctuates rhythmically with cyclic depolarizations and repolarizations. These fluctuations are called gradual waves (also referred to as basic electrical rhythm, pacesetter potentials, and control activity). Slow waves have two elements: an initial upstroke potential and a secondary plateau potential. In the stomach, gradual waves can provoke vital contractions; thus some investigators refer to them as motion potentials. However, gradual waves are at all times current, regardless of the presence or absence of contractions. Rather, a phase lag happens; thus they seem to move from an area in the midstomach towards the gastroduodenal junction. This part lag between slow waves at equidistant points lessens because the gastroduodenal junction is neared. The frequency and velocity of the peristaltic waves are due to this fact controlled by the frequency and velocity of spread of the sluggish wave. Vagotomy disorganizes the sluggish waves so that the phase lag varies in both period and course. The hormone gastrin will increase the frequency of gastric sluggish waves, although it has little effect on the obvious propagation of the waves through the musculature. Once the brink is exceeded, the larger the amplitude of the plateau, the greater will be the force of contraction. The plateau potential could or may not be accompanied by superimposed fast oscillations known as spike potentials or spike bursts. These oscillations also appear to initiate contractions and are seen more incessantly in muscle of the caudad antrum. Thus the phasic and peristaltic nature of gastric contractions results from the presence of gradual waves. The thickened ring of round muscle between the two organs seems to behave independently. Note that a contraction is initiated solely by the slow wave of bigger amplitude and longer duration. Although their most frequency may be roughly 12 per minute within the digestive state, these contractions seldom occur in a steady method. Rather, single, isolated contractions, or small teams of contractions, separated by intervals of no contractions, are the norm. Most contractions of the small gut are of the segmenting kind (see Chapter 5). Thus relying on their number and pattern, duodenal contractions both impede or facilitate the emptying of contents from the abdomen. Only particles roughly 1 mm3 or smaller are readily emptied through the digestive part of gastric motility. The rate of emptying of each solids and liquids is dependent upon their chemical compositions. Materials that are excessive in lipids or hydrogen (H+) or that deviate markedly from isotonicity all empty at a slower price than that noticed for near-isotonic saline solutions. Changes in gastric emptying are caused by alterations within the motility of the stomach, gastroduodenal junction, and duodenum. Decreases in distensibility of the orad abdomen, increases within the drive of peristaltic contractions the digestive state of the individual and the character of the gastric contents. These events regulate not only the extent of the plateau of the slow wave but in addition the amount of spiking and subsequently each the frequency and strength of contractions. Vagal nerve transection results in a decrease in contractions, whereas vagal stimulation increases the quantity and force of contractions. There is a particular difference in the contractile actions of the stomach, on one side, and of the duodenum, on the other. Note the regular isolated contractions, and the elevated pressures (0 indicates atmospheric pressure in every tracing) between contractions, in the pylorus. This exercise is occurring at a time when no contractions are present in the stomach and duodenum. As nutrients emptied from the stomach are additional digested and absorbed within the small gut, they excite receptors positioned within the intestinal mucosa. Regulation of emptying results from the presence of receptors that lie in the higher small bowel. As indicated by the sharp lower in the fraction remaining within the abdomen, the liquid element began to empty nearly immediately, and it additionally emptied extra rapidly. Conversely, there was a lag time earlier than the emptying of the label attached to the solid element, and this label emptied more slowly. The reason for this slower emptying was that the solid element had to be lowered to small particles before being emptied into the duodenum. Receptor activation triggers a number of neural and hormonal mechanisms that inhibit gastric emptying.
Deer Antler (Deer Velvet). Super Avana.
- Dosing considerations for Deer Velvet.
- How does Deer Velvet work?
- What is Deer Velvet?
- Are there safety concerns?
- Boosting strength and endurance, muscle aches and pains, use as an aphrodisiac and for sexual problems, improving immune system function, high cholesterol, high blood pressure, asthma, indigestion, acne, cancer, and many other uses.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96785
Patient Education: May trigger serious problems with selected drugs; evaluate prescription and nonprescription medication with doctor or pharmacist erectile dysfunction etiology buy super avana 160 mg fast delivery. Do not drive or operate hazardous equipment till effects of fluconazole are recognized impotence vacuum pumps super avana 160 mg purchase line. Maternal/Child: Category D: safety to be used in being pregnant and breast-feeding not established otc erectile dysfunction pills that work 160 mg super avana generic otc. There have been rare instances of distinct congenital anomalies in infants exposed in utero to high-dose maternal fluconazole throughout most or the entire first trimester erectile dysfunction protocol by jason discount 160 mg super avana overnight delivery. However, a small variety of sufferers ranging from age 1 day to 6 months have been treated safely (unlabeled). Elderly: Differences in response in comparability with younger adults not identified; however, could additionally be at elevated risk for unwanted aspect effects. Use warning; consider decreased cardiac, hepatic, or renal operate and effects of concomitant disease or other drug therapy. Inhibits metabolism and increases serum levels of phenytoin, sirolimus (Rapamune), oral tacrolimus (Prograf), and theophyllines; cautious monitoring of their plasma ranges is required; nephrotoxicity has been reported with tacrolimus. Uveitis has been reported in patients receiving rifabutin and fluconazole concomitantly. Risk of cardiac arrhythmias elevated with cisapride (Propulsid), erythromycin, pimozide (Orap), and quinidine; concurrent use not recommended; see Contraindications. Fluconazole may inhibit metabolism and enhance plasma concentrations of carbamazepine (Tegretol); monitor carbamazepine concentrations. Potential for voriconazole toxicity stays if voriconazole is initiated inside 24 hours of the last dose of fluconazole. May decrease metabolism and enhance serum concentrations of selected benzodiazepines which are metabolized by the cytochrome P450 system. May improve serum concentrations and adverse results of alfentanil, buspirone (BuSpar), calcium channel blockers. Tolterodine dose must be restricted to no extra than 1 mg twice every day when coadministered with fluconazole. Dose discount required with coadministration; see tofacitinib prescribing information. May increase the plasma concentrations and therapeutic results of zolpidem (Ambien). An enhance in serum bilirubin and creatinine have been observed with concurrent use of cyclophosphamide (Cytoxan) and fluconazole (Diflucan). No important pharmacokinetic interaction between fluconazole and azithromycin (Zithromax) has been noticed. Overdose: Cyanosis, decreased motility, decreased respirations, hallucinations, lacrimation, lack of steadiness, salivation, urinary incontinence. Post-Marketing: Asthenia, cholestasis, fatigue, fever, hepatocellular injury, insomnia, malaise, myalgia, paresthesia, somnolence. Discontinue drug and notify doctor of abnormal liver function exams progressing to medical signs and signs of liver illness. Rash could be the first sign of an exfoliative skin dysfunction in immunocompromised patients; discontinue drug and notify doctor. Pediatric sufferers with solid tumors (unlabeled): Dose-limiting myelosuppression was observed with a loading dose of eight mg/M2 on Day 1 followed by a continuous infusion of 23. Maximum tolerated dose in solid tumor pediatric patients was a loading dose of 7 mg/M2/day followed by a continuous infusion of 20 mg/M2/day for 5 days. Decrease or delay dose based on evidence of hematologic or nonhematologic toxicity. Increased toxicity might occur in the elderly and in patients with renal insufficiency or bone marrow impairment. Adjust initial beginning doses for sufferers with renal impairment as indicated in the following chart. Filters: Specific data from research not out there; contact producer for additional data. Total physique clearance of the energetic metabolite is correlated with the CrCl, indicating the importance of renal excretion for drug elimination. Not beneficial for use in patients with severely impaired renal operate (CrCl lower than 30 mL/min). Not beneficial to be used together with pentostatin (Nipent); see Drug/Lab Interactions. Use with caution in superior age, renal insufficiency, or bone marrow impairment, or in sufferers with immunodeficiency or a history of opportunistic infection. Median time to nadir counts was 13 days for granulocytes and 16 days for platelets. Most sufferers have hematologic impairment at baseline because of disease or prior myelosuppressive therapy. Several situations of trilineage bone marrow hypoplasia or aplasia leading to pancytopenia, generally resulting in dying, have been reported. Clinically significant cytopenias lasted from 2 months to 1 yr and occurred in untreated and previously treated patients. Use of irradiated blood product is really helpful for patients requiring transfusions throughout fludarabine remedy as a end result of transfusion-associated graft-versus-host disease has been reported. Serious, generally fatal infections, including opportunistic infections and reactivations of latent viral infections. [newline]Severe neurotoxicity characterised by delayed blindness, coma, and death has been reported in patients who acquired doses that were approximately 4 instances greater than the beneficial dose. Significant neurotoxicity has additionally been reported in sufferers receiving doses in the really helpful vary. Monitor: Observe carefully for indicators of toxicity, each hematologic and nonhematologic. Repeat regularly to monitor hematopoietic suppression (especially neutrophils and platelets) and hemolysis. Nausea and vomiting usually much less severe than with many different antineoplastics; prophylactic administration of antiemetics could also be indicated. Prevention and treatment of hyperuricemia as a result of tumor lysis syndrome could additionally be accomplished with adequate hydration and, if needed, with uric acid�lowering medication. Patient Education: Avoid being pregnant; effective birth control beneficial for both males and females during remedy and for at least 6 months after fludarabine routine has been accomplished. Agitation, confusion, fatigue, seizures, visible disturbances, and weak point have been reported. Maternal/Child: Category D: each men and women should use efficient contraception and keep away from pregnancy; could trigger fetal harm; see Patient Education. The commonest unwanted aspect effects embrace myelosuppression (anemia, neutropenia, thrombocytopenia), chills, cough, diarrhea, fatigue, fever, an infection (including opportunistic and pneumonia), mucositis, nausea and vomiting, and weak point. Onset of flank pain and hematuria could point out tumor lysis syndrome (hyperkalemia, hyperphosphatemia, hyperuricemia, hypocalcemia, metabolic acidosis, urate crystalluria, and renal failure); one reported. Severe neurologic toxicity including delayed blindness, coma, and demise occurred from 21 to 60 days after the last dose in 36% of sufferers treated with doses solely four occasions higher than the recommended dose. Post-Marketing: Erythema multiforme, Stevens-Johnson syndrome, poisonous epidermal necrolysis, and pemphigus (some with deadly outcomes); uncommon cases of myelodysplastic syndrome and acute myeloid leukemia associated with prior, concomitant, or subsequent remedy with alkylating agents, topoisomerase inhibitors. Symptoms of pulmonary toxicity may enhance with the usage of corticosteroids; rule out an infectious origin before use. May be repeated at 1-minute intervals, assessing level of consciousness between every dose, till desired stage of consciousness achieved or a complete cumulative dose of 1 mg (10 mL) has been given (average dose to awakening is zero. If resedation occurs (may happen if flumazenil wears off before the benzodiazepine), the above process could also be repeated at 20-minute intervals as indicated. Do not give greater than a cumulative dose of 1 mg in a 20-minute interval or 3 mg in any 1 hour. Assess degree of consciousness between every dose until desired level of consciousness achieved or a complete cumulative dose of three mg (30 mL) has been given (average dose to awakening is 1 mg to 3 mg). If desired results are achieved and resedation happens (expected), no more than 1 mg given in 0. May repeat at 1-minute intervals, assessing stage of consciousness between every dose till desired level of consciousness achieved or a most total dose of 0. Reduce dose and prolong intervals after the initial dose in impaired liver perform. Slower titration charges and decrease whole doses could also be particularly necessary in these patients (see Precautions) to cut back emergent confusion and agitation, to forestall seizures, and to evaluate effect. Rapid injection may trigger withdrawal symptoms in sufferers with long-term publicity to benzodiazepines.
Specifications/Details
Variable disposition kinetics and electrocardiographic results of flecainide throughout repeated dosing in people: contribution of genetic factors erectile dysfunction caused by radical prostatectomy super avana 160 mg purchase on-line, dose-dependent clearance diabetic with erectile dysfunction icd 9 code effective super avana 160 mg, and interplay with amiodarone impotence at 18 buy discount super avana 160 mg on-line. Fludarabine is rapidly dephosphorylated to 2-fluoro-arabinoside-A (F-ara-A) erectile dysfunction remedies pump buy cheap super avana 160 mg line, transported into cells, and phosphorylated to the active triphosphate metabolite. Fludarabine: pharmacokinetics, mechanisms of action, and rationales for combination therapies. A for a lot longer (~20 h) terminal t1/2 has been reported, representing a slow redistribution of drug from tissues. Absolute bioavailability of oral immediate and sluggish launch fluphenazine in wholesome volunteers. Effect of renal illness and hemodialysis on foscarnet pharmacokinetics and dosing suggestions. Pharmacokinetics and absolute bioavailability of oral foscarnet in human immunodeficiency virus-seropositive sufferers. Pharmacokinetics of galanthamine in people and corresponding cholinesterase inhibition. Pharmacokinetic and security assessments of galantamine and risperidone after the 2 medication are administered alone and collectively. Rapidly metabolized intracellularly to active di- and triphosphate merchandise; intravenous administration. Gemcitabine in leukemia: a phase I medical, plasma, and mobile pharmacology research. A evaluate of its pharmacodynamic and pharmacokinetic properties, and therapeutic use in dyslipidaemia. Pharmacokinetics and security of glimepiride at clinically effective doses in diabetic sufferers with renal impairment. A long terminal t1/2 (15 h), reflecting redistribution from tissues, has been reported. Slow conversion from lowered haloperidol to mother or father compound probably answerable for extended terminal t1/2 (70 h) for haloperidol observed with 7-day sampling. Pharmacokinetics and pharmacodynamics of a low molecular weight heparin (enoxaparin) after subcutaneous injection, comparability with unfractionated heparin-a three way cross over examine in human volunteers. Bioavailability and disposition of metoprolol and hydrochlorothiazide combined in one pill and of separate doses of hydrochlorothiazide. Fosinopril/ hydrochlorothiazide: single dose and steady-state pharmacokinetics and pharmacodynamics. The principal metabolite, 3-glucuronide, accumulates to a lot greater (27-fold) levels than the mother or father drug and should contribute to some unwanted effects (not antinociceptive). Steady-state pharmacokinetics of hydromorphone and hydromorphone-3-glucuronide in most cancers sufferers after quick and controlled-release hydromorphone. Comparison of continuous subcutaneous and intravenous hydromorphone infusions for management of most cancers pain. Pharmacokinetics of hydromorphone after intravenous, peroral and rectal administration to human subjects. Hydroxychloroquine accumulates in purple blood cells with an average blood-to-plasma ratio of seven. A dose-ranging examine of the pharmacokinetics of hydroxychloroquine following intravenous administration to wholesome volunteers. Plasma concentrations of cetirizine exceed those of the father or mother drug; its t1/2 is just like that of hydroxyzine when fashioned from father or mother drug. Pharmacokinetics and antipruritic effects of hydroxyzine in children with atopic dermatitis. The pharmacokinetics and pharmacodynamics of hydroxyzine in sufferers with major biliary cirrhosis. Pharmacokinetic and pharmacodynamic studies of the H1-receptor antagonist hydroxyzine in the aged. Renal safety and pharmacokinetics of ibandronate in multiple myeloma sufferers with or with out impaired renal perform. Binding of every enantiomer is concentration dependent and is influenced by the presence of the optical antipode, leading to nonlinear elimination kinetics. Idarubicin metabolism and pharmacokinetics after intravenous and oral administration in cancer sufferers: a crossover research. Pharmacokinetics and pharmacodynamics of imatinib in a part I trial with continual myeloid leukemia sufferers. A reappraisal of its antibacterial activity, pharmacokinetic properties and therapeutic efficacy. Pegylated interferon-2b: pharmacokinetics, pharmacodynamics, security, and preliminary efficacy information. Pharmacokinetics of recombinant human interferon-ser in wholesome volunteers and its effect on serum neopterin. A review of its pharmacodynamic and pharmacokinetic properties and therapeutic use in the management of hypertension. Oral bioavailability and disposition traits of irbesartan, an angiotensin antagonist, in healthy volunteers. Higher percentages have been famous after intravenous administration, suggesting vital first-pass metabolism. Pharmacokinetics and metabolism of isosorbide-dinitrate after intravenous and oral administration. The 4-oxo-isotretinoin metabolite (4-oxo) is lively and found at larger concentrations than parent drug at steady state. Steady-state pharmacokinetics of isotretinoin and its 4-oxo metabolite: Implications for fetal safety. Labetalol pharmacokinetics and pharmacodynamics: proof of stereoselective disposition. Pharmacokinetics, absolute bioavailability, and absorption traits of lamivudine. Pharmacokinetics of lamivudine in human immunodeficiency virus-infected sufferers with renal dysfunction. Pharmacokinetics of lamotrigine in kids in the absence of other antiepileptic drugs. Comparison of the pharmacokinetics of lamotrigine in sufferers with chronic renal failure and healthy volunteers. Both parameters are a operate of the bioavailability of leflunomide and the extent of its conversion to A77-1726. Following a single 125-mg oral dose of levodopa given with carbidopa (100-mg 1 h earlier than and 50-mg 6 h after levodopa) in young (Y) and elderly (E) subjects. The impact of age on the pharmacokinetics of levodopa administered alone and in the presence of carbidopa. Pharmacokinetic profile of levofloxacin following once-daily 500-milligram oral or intravenous doses. The effect of erythromycin and fluvoxamine on the pharmacokinetics of intravenous lidocaine. Reduction of oral bioavailability of lignocaine by induction of first pass metabolism in epileptic patients. Plasma protein binding of lidocaine and warfarin in insulin-dependent and non-insulin dependent diabetes mellitus. Pharmacokinetic and pharmacodynamic profile of linezolid in wholesome volunteers and patients with gram-positive infections. Lisinopril population pharmacokinetics in elderly and renal disease patients with hypertension. Desloratadine demonstrates dose proportionality in healthy adults after single doses. A reappraisal of its pharmacological properties and therapeutic use in allergic problems. Pharmacokinetics of loratadine and pseudoephedrine following single and multiple doses of once- versus twice-daily mixture pill formulations in healthy adult males.
Syndromes
- Has the thickness changed?
- Infection with the bacteria that cause Lyme disease
- Your health care provider will tell you if you need to stop taking any medicines before you have this test.
- Obesity
- Quinethazone (Hydromox)
- Bernard-Soulier syndrome occurs when platelets lack a substance that sticks to the walls of blood vessels. This disorder may cause severe bleeding.
- Carpal tunnel syndrome
Related Products
Additional information:
Dose delays could also be required to enable recovery of blood cell counts within the event of hematologic toxicity; see Precautions impotence kidney disease purchase super avana 160 mg otc, Monitor erectile dysfunction treatment cincinnati super avana 160 mg discount otc, and Antidote impotence 28 years old buy 160 mg super avana amex. If no additional reactions occur erectile dysfunction drugs for sale purchase 160 mg super avana amex, infusion rate escalation could resume at increments and intervals as appropriate; see Rate of Administration. If no additional reactions happen, resume fee escalation at increments and intervals as acceptable; see Rate of Administration. Do not use if opaque particles, discoloration, or different overseas particles are present. Withdraw the calculated dose (48 mL in both of the previous examples) from the required number of vials. The diluted product should be used instantly but may be saved for up to 24 hours if refrigerated and shielded from light. Diluted solution could develop very small, translucent to white proteinaceous particles because daratumumab is a protein. Interrupt daratumumab infusion for infusion reactions of any severity and handle symptoms. To facilitate administration, the first 16 mg/kg dose at Week 1 could additionally be split over 2 consecutive days. Infusion Rates for Daratumumab (16mg/kg) Administration Dilution Volume Initial Rate (First Hour) Rate Incrementa Maximum Rate Week 1 Infusion Option 1 (Single-dose infusion) Week 1, Day 1 (16 mg/kg) Option 2 (Split-dose infusion) Week 1, Day 1 (8 mg/kg) Week 1, Day 2 (8 mg/kg) Week 2 (16 mg/kg) infusionb Subsequent (Week 3 onward, 16 mg/kg) infusionsc a b 1,000 mL 50 mL/hr 50 mL/hr each hour 200 mL/hr 500 mL 500 mL 500 mL 500 mL 50 mL/hr 50 mL/hr 50 mL/hr a hundred mL/hr 50 mL/hr each hour 50 mL/hr every hour 50 mL/hr each hour 50 mL/hr each hour 200 mL/hr 200 mL/hr 200 mL/hr 200 mL/hr Consider incremental escalation of the infusion price only within the absence of infusion reactions. Use a dilution volume of 500 mL for the sixteen mg/kg dose provided that there have been no infusion reactions the earlier week. Otherwise, continue to use directions indicated in the chart for the Week 2 infusion fee. Half-life is 9 to 27 days when administered as monotherapy and is comparable when administered as mixture therapy. Interference with these assays can have an result on the willpower of full response and of disease progression in some sufferers with IgG kappa myeloma protein; see Drug/Lab Interactions. Immediately interrupt the infusion for infusion reactions of any grade/severity; see Dose Adjustments and Antidote. Based on its mechanism of action, daratumumab may cause fetal myeloid or lymphoid-cell depletion and decreased bone density. This can lead to a false-positive end result for patients with IgG kappa myeloma protein and affect the initial evaluation of full responses. The most frequently reported side effects included arthralgia, asthenia, again pain, bronchitis, chills, constipation, cough, decreased urge for food, diarrhea, dizziness, dyspnea, fatigue, fever, infusion reactions, insomnia, muscle spasms, nausea, neutropenia, peripheral edema, peripheral sensory neuropathy, pneumonia, thrombocytopenia, higher respiratory tract infections, and vomiting. Less incessantly reported unwanted facet effects embody anxiousness, bone pain, extremity ache, headache, herpes zoster reactivation, hypertension, hyperglycemia, hypocalcemia, hypokalemia, musculoskeletal chest pain, nasal congestion, nasopharyngitis, noncardiac chest ache, paresthesia, tremor, and urinary tract infections. The most frequent serious unwanted effects have been atrial fibrillation, bronchitis, dehydration, diarrhea, fever, common physical well being deterioration, influenza, infusion reactions, pneumonia, pulmonary edema, and higher respiratory tract infections. Treatment-emergent hematology laboratory abnormalities, together with anemia, leukopenia, lymphopenia, neutropenia, and thrombocytopenia, have been reported. For sufferers with Grade 1, 2, or 3 reactions, cut back the infusion fee when restarting the infusion; see Dose Adjustments and Rate of Administration. Permanently discontinue daratumumab for recurrence of a third Grade 3 or a Grade 4 (life-threatening) hypersensitivity/infusion response occurs. Treat a hypersensitivity/infusion reaction with oxygen, epinephrine (Adrenalin), antihistamines. Adult and pediatric sufferers: Rate of hemoglobin enhance is dose dependent and varies among patients. If a patient fails to reply or maintain a response, different etiologies must be considered and evaluated. Administer darbepoetin as soon as per week in patients who had been receiving epoetin alfa 2 to 3 occasions every week and as quickly as every 2 weeks in patients who were receiving epoetin alfa once per week. If the hemoglobin stage approaches or exceeds 12 Gm/dL, reduce or interrupt the dose of darbepoetin. Allow enough time earlier than adjusting a dose; increased hemoglobin levels may not be observed for two to 6 weeks. Supplied in vials or prefilled syringes with needle guards (needle cowl contains a spinoff of latex). No vital loss of potency expected with use of non�protein binding filters of an analogous measurement or larger. Production of endogenous erythropoietin is impaired in sufferers with persistent renal failure, and erythropoietin deficiency is the first explanation for their anemia. Darbepoetin has the same biologic results as erythropoietin produced naturally by the kidneys. Limitations of use: Not indicated for use in sufferers with cancer receiving hormonal brokers, therapeutic biologic merchandise, or radiotherapy until receiving concomitant myelosuppressive chemotherapy. To decrease these risks, as well as the risks of serious cardiovascular and thrombovascular events, use the bottom dose needed to keep away from a purple blood cell transfusion. The incidence of antibody improvement in patients receiving darbepoetin has not been decided. Evaluate any patient who develops a sudden lack of response to darbepoetin alfa accompanied by extreme anemia and low reticulocyte depend. Physicians might contact the manufacturer (Amgen) for help with analysis of these sufferers. Erythropoietin receptors are additionally discovered on the surfaces of regular, nonhematopoietic tissue and a few malignant cell traces. Monitor: Normal iron stores required to assist epoetin-stimulated erythropoiesis. Transferrin saturation should be at least 20% and ferritin at least 100 ng/mL (100 mcg/L). Continue until stable and the upkeep dose has been established, then monitor at common intervals (at least monthly). Initiation or intensification of antihypertensive remedy and dietary restrictions could additionally be needed. Patient Education: Risk of seizures, particularly for first several months of therapy. Consider the advantages and risks of darbepoetin for the mom and attainable risks to the fetus. Other reported antagonistic reactions embrace angina, arteriovenous graft thrombosis, fluid overload, rash, and vascular entry complications. Pediatric continual kidney illness sufferers: Commonly reported opposed reactions include convulsions, hypertension, injection web site pain, and rash. Cancer patients receiving chemotherapy: Commonly reported adverse reactions include belly pain, edema, and thrombovascular events. Seizures, severe cutaneous reactions, and critical hypersensitivity reactions have also been reported. Reduce dose of darbepoetin in sufferers with a rise in hemoglobin of greater than 1 Gm/dL in 2 weeks. Adjustments in dialysis prescription could additionally be required throughout dialysis to forestall clotting. Verify drug name and dose earlier than preparation and administration to avoid dosing errors. Before initiating each cycle of Vyx- eos, calculate the prior cumulative anthracycline publicity for the patient; see Precautions. A full Vyxeos course consists of 1 to 2 cycles of induction and as much as 2 cycles of consolidation. Do not start consolidation cycles till absolutely the neutrophil count recovers to higher than 500/mm3 and the platelet rely recovers to larger than 50,000/mm3 in the absence of unacceptable toxicity. Consolidation: Administer the first consolidation cycle 5 to 8 weeks after the beginning of the last induction. Reduce the rate of infusion or discontinue treatment as outlined in the following chart. Consider premedication with antihistamines and/or corticosteroids for subsequent doses. For subsequent doses, premedicate with antihistamines and/or corticosteroids earlier than initiating infusion on the identical fee. Treat according to the usual of care to manage signs, and monitor the patient until symptoms resolve.
Usage: gtt.
Guidelines for Dilution of Epoprostenol to Various Concentrations To Make 100 mL of Solution With Final Concentration (ng/mL) of: three erectile dysfunction book super avana 160 mg safe,000 ng/mL Directions Dissolve contents of one 0 erectile dysfunction causes and cures buy 160 mg super avana visa. Withdraw entire vial contents and add enough equivalent diluent to make a total of 100 mL erectile dysfunction doctor in virginia super avana 160 mg purchase on-line. Withdraw complete vial contents and add enough volume of the similar diluent to make a total of one hundred mL erectile dysfunction circumcision super avana 160 mg discount without prescription. Prepare in a drug supply reservoir appropriate for the infusion pump with a total reservoir volume of at least one hundred mL. In common, 3,000 ng/mL and 10,000 ng/mL concentrations ought to be passable to deliver between 2 and 16 ng/kg/min in adults. Storage: All merchandise: Vials are for single use only; discard any unused diluent or unused reconstituted answer. Before use, reconstituted options (Flolan and generic) should be refrigerated and shielded from mild. Flolan diluted with pH 12 sterile diluent: Freshly ready reconstituted solutions or reconstituted solutions which have been refrigerated at 2� to 8� C (36� to 46� F) for not than eight days may be administered from 12 to seventy two hours at specific temperatures; see prescribing data. Veletri: Unopened vials could also be saved at 20� to 25� C (68� to 77� F) in the carton to defend from direct daylight. Maximum duration of administration ranges from 24 to seventy two hours and is dependent on ambient temperature, ultimate concentration, and length of refrigerated storage before administration; see Prescribing Information. Flolan and generic diluted with sterile diluent: When used at room temperature, reconstituted solutions are steady for up to Manufacturer states, "Stable only when reconstituted with the offered or recommended diluent. Must not be reconstituted or combined with another parenteral medicines or solutions previous to or during administration. If dose-limiting pharmacologic results occur, lower infusion fee slowly until pharmacologic effects are tolerated; see Dose Adjustments. Produces dose-related will increase in cardiac index and stroke quantity and dose-related decreases in pulmonary vascular resistance, complete pulmonary resistance, and imply systemic arterial stress. Has been shown to improve train capacity, enhance hemodynamic standing, and prolong survival. Consider the potential of related pulmonary veno-occlusive disease in these patients; see Contraindications. Monitor: Frequent monitoring of important indicators beneficial throughout acute dose initiation. Patient Education: After initial dose titration and coaching, it is a self-administered drug. Must assume duty for drug reconstitution, drug administration, and care of the everlasting central venous catheter. Decreased organ perform (cardiac, hepatic, renal), concomitant illness, and different drug remedy could cause concern. Abdominal ache, agitation, anorexia, anxiety/nervousness, again ache, bradycardia, chest pain, dizziness, dyspepsia, dyspnea, hyperesthesia, hyperkinesias, musculoskeletal pain, myalgia, paresthesia, respiratory disorders, sepsis, sweating, tachycardia, tremor, urticaria, and many other side effects may happen. Chronic continuous infusion: Any of the above and arthralgia, bleeding at numerous websites, chills, diarrhea, fever, flu-like symptoms, infection (may be local at web site of catheter insertion), jaw ache, pallor, pulmonary edema, rash, sepsis, thrombocytopenia. Post-Marketing: Anemia, hepatic failure, high-output cardiac failure, hypersplenism, hyperthyroidism, pancytopenia, pulmonary embolism, splenomegaly, thrombocytopenia. A calculated CrCl higher than or equal to 50 mL/min is required in patients receiving the following doses. Continue infusion until hospital discharge or for up to 18 to 24 hours, whichever comes first. Pci In patients with a calculated CrCl less than 50 mL/min, give a bolus of a hundred and eighty mcg/kg. The 10-mL vial contains 20 mg of eptifibatide; the 100-mL vials contain seventy five mg or 200 mg of eptifibatide. Recovery of platelet perform after termination of the eptifibatide infusion is speedy. Recommended regimens of a bolus adopted by an infusion produce quick inhibition of platelet aggregation and an early peak stage, adopted by a small decline, with regular state achieved within four to 6 hours. Limited data on the utilization of eptifibatide in sufferers receiving thrombolytic agents. Monitor serial platelet counts, assess the presence of drug-dependent antibodies, and provoke applicable remedy as indicated. Use excessive precautionary strategies and only compressible sites if these procedures are absolutely needed. Apply pressure for half-hour to any invaded web site after which apply pressure dressings. The femoral artery sheath could additionally be eliminated during eptifibatide infusion, but solely after heparin has been discontinued and its effects largely reversed. Sheath hemostasis ought to be achieved no much less than 2 to 4 hours earlier than hospital discharge. Laboratory findings associated to bleeding embrace decrease in hemoglobin, hematocrit, and platelet rely and occult blood in urine and feces. Other unwanted effects that have been reported include hypersensitivity reactions, hypotension, and thrombocytopenia (acute and profound). Acute toxicity: Specific information not available for people, but decreased muscle tone, dyspnea, loss of righting reflex, petechial hemorrhages within the femoral and abdominal areas, and ptosis occurred in animals. If acute profound thrombocytopenia happens or the platelet depend drops to lower than 100,000/mm3, heparin and eptifibatide should be discontinued. A artificial fluorocycline antibacterial inside the tetracycline class of antibacterial medication. Eravacycline disrupts bacterial protein synthesis by binding to the 30s ribosomal subunit, thus preventing the incorporation of amino acid residues into elongating peptide chains. Protein binding to human plasma proteins will increase with rising plasma concentrations. Known hypersensitivity to eravacycline, tetracycline-class antibacterial drugs, or to any of the excipients. Eravacycline is structurally just like different tetracycline-class antibacterial drugs and ought to be not be administered to patients with identified hypersensitivity to any drug on this class. This opposed reaction is extra frequent throughout long-term use of the tetracycline-class medicine but has additionally been observed following repeated short-term programs. Consider in sufferers who current with diarrhea during or after remedy with eravacycline. Patient Education: Promptly report extreme diarrhea, S/S of hypersensitivity reactions, or another aspect impact. May cause everlasting tooth discoloration of deciduous enamel and reversible inhibition of bone growth when administered during the second and third trimesters of being pregnant. Elderly: No general differences in security or efficacy had been noticed between elderly sufferers and youthful patients. The most common opposed reactions are infusion web site reactions, nausea, and vomiting. Less generally reported adverse reactions included diarrhea, hypotension, and wound dehiscence. Discontinue eravacycline on the first sign of a hypersensitivity response or if the event of any tetracycline-class antagonistic drug reaction is suspected. If toxicities resolve or improve to Grade 2 or much less by Day 15, administer at a reduced dose as outlined within the following chart and initiate the next cycle no before 2 weeks later. Recommended Dose Reductions for Eribulin Mesylate Event Description Recommended Eribulin Dose 1. Do not administer in the identical intravenous line concurrent with different medicinal merchandise. Inhibits the growth phase of microtubules without affecting the shortening phase and sequesters tubulin into nonproductive aggregates. Exerts its effects through a tubulin-based antimitotic mechanism leading to G2/M cell-cycle block, disruption of mitotic spindles and, ultimately, apoptotic cell dying after extended mitotic blockage. Prior therapy ought to have included an anthracycline and a taxane in either the adjuvant or metastatic setting. Deaths from complications of febrile neutropenia and neutropenic sepsis have been reported.
Tags: 160 mg super avana generic fast delivery, purchase super avana 160 mg online, super avana 160 mg buy visa, super avana 160 mg discount line, generic super avana 160 mg on-line, purchase super avana 160 mg mastercard, buy super avana 160 mg, 160 mg super avana purchase free shipping, super avana 160 mg cheap, purchase 160 mg super avana with mastercard, super avana 160 mg order fast delivery, super avana 160 mg discount on line, super avana 160 mg discount amex, super avana 160 mg generic free shipping, super avana 160 mg buy with visa, super avana 160 mg generic amex
8 of 10
Votes: 45 votes
Total customer reviews: 45
Customer Reviews
Shawn, 62 years: The glucose residues are removed sequentially from the nonreducing ends till a 1 to 6 department level is reached.
Pranck, 35 years: This is probably a benign inflamed diverticulum and it resolved on follow-up imaging.
