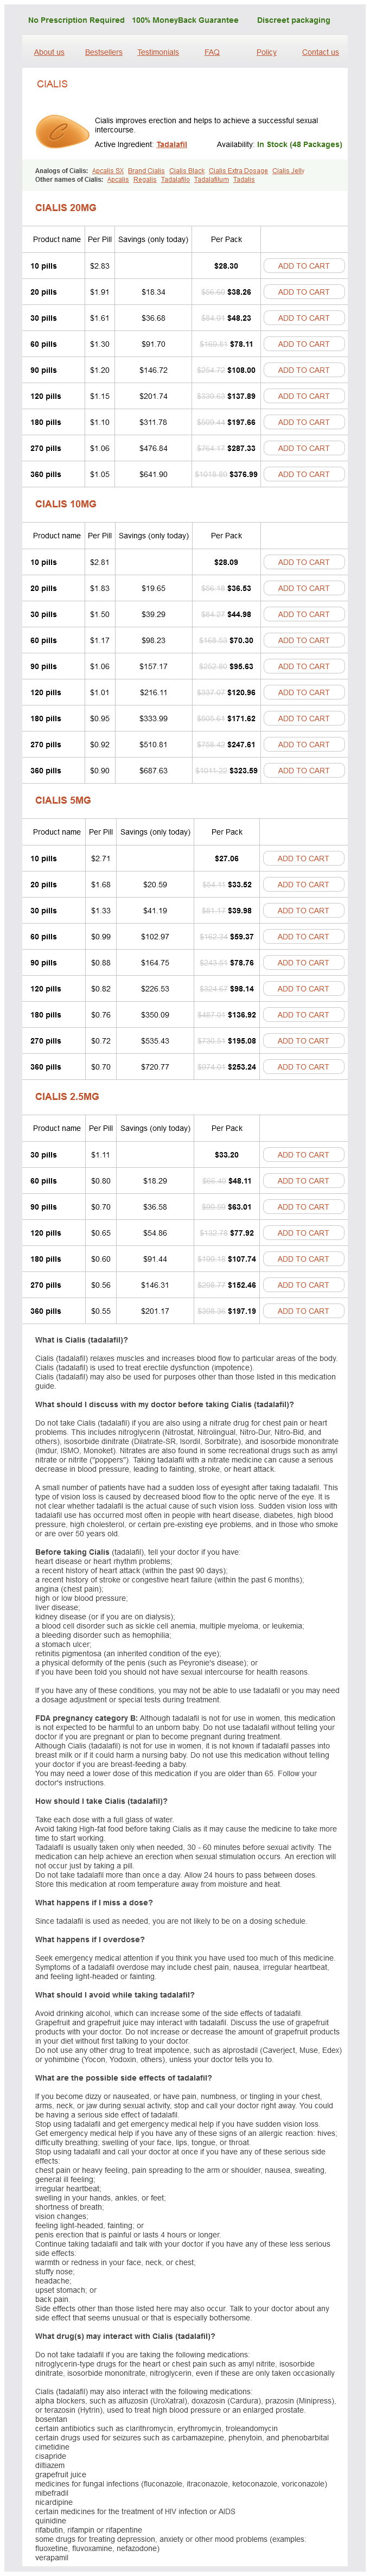
Cialis 20mg
- 10 pills - $28.30
- 20 pills - $38.26
- 30 pills - $48.23
- 60 pills - $78.11
- 90 pills - $108.00
- 120 pills - $137.89
- 180 pills - $197.66
- 270 pills - $287.33
- 360 pills - $376.99
Cialis 10mg
- 10 pills - $28.09
- 20 pills - $36.53
- 30 pills - $44.98
- 60 pills - $70.30
- 90 pills - $95.63
- 120 pills - $120.96
- 180 pills - $171.62
- 270 pills - $247.61
- 360 pills - $323.59
Cialis 5mg
- 10 pills - $27.06
- 20 pills - $33.52
- 30 pills - $39.98
- 60 pills - $59.37
- 90 pills - $78.76
- 120 pills - $98.14
- 180 pills - $136.92
- 270 pills - $195.08
- 360 pills - $253.24
Cialis 2.5mg
- 30 pills - $33.20
- 60 pills - $48.11
- 90 pills - $63.01
- 120 pills - $77.92
- 180 pills - $107.74
- 270 pills - $152.46
- 360 pills - $197.19
Tadalafil dosages: 20 mg, 10 mg, 5 mg, 2.5 mg
Tadalafil packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 943
Only $0,58 per item
Description
The surgeon can adjust the rate of flow instantly at the control panel of the machine throughout the range allowed by the producer diabetic with erectile dysfunction icd 9 code generic 2.5 mg tadalafil with visa. When the phaco needle is fully occluded erectile dysfunction causes and solutions tadalafil 10 mg cheap with visa, outflow ceases buy erectile dysfunction pills online uk 10 mg tadalafil amex, however the pump will continue to turn buying erectile dysfunction pills online tadalafil 2.5 mg discount, producing vacuum throughout the handpiece and the tubing connecting it to the pump. When the vacuum reaches the limit set by the surgeon, the pump stops turning (or might turn very slowly to compensate for leakage of vacuum). It is obvious from a consideration of the above that the pace of pump rotation (flow rate) will decide how quickly the preset vacuum is reached. The surgeon could favor a modest flow rate during surgery (say 30 mL/min), but as soon as occlusion has occurred s/he might set the machine to increase (or decrease) the circulate fee as soon as occlusion is detected, thus dashing (or slowing) the rise in vacuum to the target degree. Briefly summarized, this takes benefit of the reality that as a fluid (liquid or gas) passes through a restriction or narrowing in its passage, the stress is lowered, and this can lead to entraining air through a sideport. A greater commanded vacuum in the cassette will generate a higher fee of outflow for a given combination of needle and tubing. As in a flow-based pump, the rate of flow for a given pressure difference will depend upon the degree of occlusion of the phaco needle and the viscosity of the fluid being aspirated. When the phaco needle is occluded, outflow ceases, and the lumen of the phaco handpiece and tubing quickly develop the identical unfavorable pressure because the cassette. When the tip of the phaco needle is absolutely occluded by lens material then the whole of the needle lumen, the handpiece and the tubing connecting to the pump/cassette is at a unfavorable strain (vacuum) set by the machine. When the occlusion is damaged as a outcome of the lens fragment is both emulsified or has been dislodged, fluid quickly flows from the small volume into the much bigger quantity across this pressure gradient. It is under these circumstances, significantly when dealing with the last chunk of nucleus, that the posterior capsule or even the iris could be aspirated into the phaco needle, or the cornea is dimpled inward onto the instruments. Compliance is also present in the tubing surrounding the rollers of a conventional peristaltic pump, and is added if air bubbles are present inside the tubing. Resistance to move within a tube is immediately proportional to the size of the tube, and inversely related to the fourth energy of the radius. Some surgeons use lengthy, coiled outflow tubing to join the handpiece, using the increased resistance due to size to modulate the surge. Most manufacturers, nevertheless, have tended to cut back the diameter of their outflow tubing and to manufacture it with elevated rigidity. There is a steadiness to be struck, nonetheless, between the lowered diameter which improves surge management and larger diameter which would reduce the tendency to clog due to lens particle aspiration. It is a device which fits between the phaco handpiece and the conventional outflow tubing. Needle with a silicone sleeve requires a larger incision, but the area for leakage is far much less because the silicone is compressible. Note that with every combination, the quantity of surge is directly proportional to the vacuum. The highest line compared to the following one reveals the influence of recent pump technologies in lowering surge. The lowest line compared to the one above shows the impact of a wider irrigation sleeve on reducing the surge. In bimanual methods, the phaco needle, without an irrigation sleeve, is positioned through one incision and the infusion is thru a separate incision. Often, the infusion is through a dual objective instrument similar to an infusion chopper. The fluidics challenge presented by this method is the significantly larger passive outflow from the attention because of incisional leakage. With two incompletely sealed incisions subsequently there shall be vital further outflow. The maximum vacuum used (and also in some cases the aspiration move rate) is often adjusted downward when performing bimanual microincisional surgical procedure so as to keep away from postocclusion surge issues. The theoretical fluidics benefit of the bimanual approach is that it dissociates the currents of the irrigation influx from the aspiration port. This may make phaco-aspiration simpler as the holding drive of vacuum might not have competing circulating aqueous currents tending to disrupt tip occlusion. In micro-coaxial phaco, the surgeon makes use of specifically developed irrigation sleeves (of the normal silicone material) that have thinner walls, and a microsmooth outer floor, permitting it to be easily inserted into small incisions of 2. However, the challenge to the fluidics is in the lowered inflow potential by way of the reduced measurement irrigation sleeve. Therefore this kind of sleeve must be used only with a machine that has good postocclusion surge protection, and should be coupled with a phaco needle with some type of outflow restriction. The ultimate issue a surgeon should be aware of is the dimensions and configuration of the phaco needle. Because resistance to circulate is related to the 4th energy of the radius, the flared needle has 1. If none of those checks reveals an issue, then both enhance the bottle height in order to improve the inflow or lower the vacuum and probably move so as to decrease the quantity of postocclusion surge outflow, or each. Flow charges are typically set on the low aspect in flow-based machines (say 20 mL/min), as is the vacuum (say 50�90 mmHg). In vacuum-based machines, the vacuum can be set at ~30�50 mmHg, and this would generate an appropriate circulate fee. During chopping or quadrant elimination the surgeon should take benefit of the good fluidics performance of modern phaco machines. A relatively high circulate price should be chosen on flow-based machines (say 30�40 mL/min). This ensures that nuclear materials is attracted to the tip, and once grasped, ensures that the goal vacuum is reached rapidly. The maximum vacuum should be set at a comparatively excessive level to find a way to maximize the phaco-aspiration as properly as to maintain the material against the tip, counteracting the repulsion caused by the rapid forward strokes of the phaco needle. Poor followability may be less of a problem if inflow is separated from outflow (biaxial technique). Alternatively, the issue may not truly be followability, however repulsion of nuclear materials by the jack�hammer effect of the phaco needle. This can be reduced by appropriate power modulation (rapid pulses or brief bursts) or by utilizing a nonrepulsive phaco mode (torsional phaco recently introduced by Alcon laboratories). The effect of this shall be to reduce the intraocular pressure and also to reduce the circulate of fluid via the eye. However, the utmost vacuum must also be reduced so as to scale back the potential for postocclusion surge with the lowered influx potential from a lower bottle height. The move price should also be decreased so as to minimize probably disruptive turbulence. Khng C, Packer M, Fine I H, et al: Intraocular stress during phacoemulsification. Kageyama T, Yaguchi S: In vitro evaluation of stress fluctuations with differing height of the infusion bottle in phacoemulsification. For this purpose, preoperative evaluation of the lens permits opening of the anterior capsule as controllable as possible. Especially tearing of the anterior capsulorrhexis edge could entail severe problems like posterior capsule rupture with prolapse of the vitreous body and even lack of the nucleus into the vitreous. If pseudoexfoliation is present, one ought to at all times consider the potential for unfastened zonules. In mature lenses with poor or no red reflex opening of the anterior capsule is hardly potential without tearing the sting of the rhexis except particular methods (high-frequency diathermy, staining of the capsule) are employed. In nearly all instances pupil size may be estimated following slit-lamp examination, so the proceedings can be completely deliberate. If patients have been taking a myotic agent over an extended time frame, the extent of myosis should be assessed preoperatively, and surgical procedure be postponed if essential till the impact of the myotic has worn off. Loose zonules with lentodonesis could be recognized throughout slit-lamp examination when the affected person seems from left to right. Unfortunately, the situation of the posterior capsule is crucial for safe implantation of a posterior chamber lens. Rare instances of preexistent posterior capsule defects have been described which result in surprising capsular rupture during surgery.
Garlic. Tadalafil.
- What other names is Garlic known by?
- Preventing tick bites.
- Lung cancer.
- Preventing colon cancer, rectal cancer, stomach cancer.
- Breast cancer.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96322
The detached retina is normally thin impotence from vasectomy tadalafil 20 mg generic with mastercard, with a quantity of small equatorial breaks hidden by the vitreous membrane erectile dysfunction effects on relationship trusted 5 mg tadalafil. McPherson and coworkers18 and Orellana5 state that the band ideally should be transected 3�6 months postoperatively to permit normal ocular progress erectile dysfunction drug mechanism 5 mg tadalafil purchase otc. The distance between the temporal optic disk and the center of the macula stays four mm from preterm to maturity erectile dysfunction new zealand cheap tadalafil 2.5 mg amex. Second, the retinal interaction with retinal pigment epithelium is crucial to normal retinal growth. An interruption of the normal configuration for even a few days may end in irreversible dysmorphic adjustments. More than 50% of patients had passable anatomic ends in most different studies. However, solely 20% of the operated eyes were judged by the author to have useful imaginative and prescient. However, because the duration of retinal detachment influences prognosis, because the retina becomes atrophic after relatively transient durations of detachment,18 scleral buckling should be thought-about early in progressive traction detachments and in giant exudative detachments. Cryotherapy or laser remedy is often carried out on the time of retinal detachment surgical procedure, particularly in traction or exudative instances with continued energetic neovascularization. Cryotherapy can be applied to the lively neovascular ridge if the detachment is shallow. The laser can be applied on the ridge on the buckle after external drainage of subretinal fluid and after the retina is attached. Greven and Tasman15 beneficial scleral dissection in some patients and fluid drainage in practically all sufferers. Optimal results are achieved by meticulous removing of proliferative membranes; this can be assisted by intraoperative injection of triamcinolone into the attention to assist in the visualization of the vitreous and membranes. The small size of the eye and in depth proliferation necessitated several modifications of the standard closed-vitrectomy approach utilized in grownup eyes. When the retina is pulled up to now anteriorly that it abuts the lens, the devices must be inserted via the iris root or anterior ciliary body to keep away from coming into the subretinal house. Alternatively, infusion can be positioned within the anterior chamber after elimination of the lens (three-port). The vessels of the detached retina are seen through the thin retrolental fibrous membrane. This has the advantage of maintaining the anterior chamber deep and the retina back, especially when devices are exchanged by way of the surgical wound. The disadvantage of the anterior chamber infusion is that the infusion fluid can push the lens posteriorly and pressure the indifferent retina behind it inflicting a retinal dialysis. Additional ports may be made to permit for extra full dissection and removing of the membranes. It often is carried out in eyes which were handled beforehand by laser photocoagulation or cryotherapy. This technique is more difficult if the membrane to be cut and cleaned is anterior to the equator as a result of the comparatively massive size of the crystalline lens at this age. The sclerotomy is thru the pars plicata or pars plana and never by way of ablated retina. Despite technical difficulties, several groups have reported successful case series. Despite these successes, many of the stage 4a cases may not advance and may not require surgery. Then the cornea is eliminated with a 7- to 8-mm trephine and stored in culture medium throughout surgical procedure. Then the dissection is sustained centrally to the opening of the funnel of the detachment. In order to make space inside of the funnel bigger and make the placement of the adhesion of the membrane to the retina visible hyaluronic acid is injected into the mouth of the funnel. In order to view the within of the funnel better, flat round coverglass, 5 mm in diameter, is used to touch the surface of the hyaluronic acid filling the funnel. The fibrous mass filling the funnel of detached retina is minimize near the optic nerve head and eliminated en bloc. The iridotomies, if made, are closed with 10-0 polypropylene sutures, and the corneal button is changed with 10-0 nylon sutures. Hyaluronic acid is injected to deepen the anterior chamber, in addition to into the open mouth of the funnel. When the intraocular strain goes up and the retina is found to be still extremely elevated, the subretinal fluid is drained externally and hyaluronic acid is additional injected into the vitreous cavity. At the end of the surgical procedure the detached retina must be positioned away from the again of the iris. Scleral buckling was performed by Hirose and colleagues45 4�8 weeks later if the retina showed no sign of reattachment. Eyes with the closed�closed configuration had a 29% reattachment fee; all other eyes had reattachment rates of larger than 60%. McPherson and coworkers30 had a 22% anatomic success price with open funnels and an 11% success rate with closed funnels using the open-sky method, whereas Tasman and associates 31 had a 35% anatomic success price. The preoperative presence of subretinal hemorrhage in stage 5 confers a poor prognosis. At this stage, though the traction retinal detachment is often nonetheless an open funnel, adhesion of the membrane to the retina may be very strong, making full removal of the fibrous tissues from the retina extremely tough. Thus, the potential practical advantage of operating early have to be weighed in opposition to the increased issue of extracting adherent membranes and the elevated postoperative hemorrhage and fibrin manufacturing (with improvement of secondary membranes) if vitrectomy is performed too quickly. The timing of vitrectomy in relation to the progression of stage 4a and 4b disease is likely very important as well. In eyes which failed first procedures, vitreous haze or organization and plus disease were discovered to be important in stage four eyes, while 6 clock hours of ridge elevation and plus illness have been discovered to be vital in stage 5 eyes. Hartnett recommends additional laser be carried out before surgical procedure in eyes manifesting neovascularization or plus disease. The optimal time for surgery may be after 6 months of age however earlier than the affected person is 1 year old. One could function earlier if the attention has been treated with cryotherapy or photocoagulation and the fundus exhibits no sign of energetic vasoproliferation. Even when surgery is delayed for years, it may be price attempting repair in some circumstances as a outcome of ambulatory acuity has been obtained postoperatively in patients with long-standing retinal detachment as a lot as three years of age. The advantage of the closed technique is the avoidance of elimination and alternative of the corneal button. The disadvantages embrace the need for a pars plicata or iris root entry web site because of the acute anterior displacement of the retina and the problem maneuvering vitrectomy instruments throughout the small closed space of the untimely infant eye. Reported disadvantages of the open-sky technique embody elevated complexity of postoperative administration due to the need for a corneal graft, prolonged hypotony, and a longer working time. Some circumstances that would be inoperable by the closed approach could be repaired utilizing the open-sky method. Stage 5 instances with the open�open configuration have the best prognosis; the closed�closed configuration is least more probably to end in recovery of helpful imaginative and prescient. Eyes that underwent vitrectomy had a decrease incidence of glaucoma and shallow anterior chamber in contrast with unoperated eyes. The rates of corneal opacity, hypotony, and vitreous hemorrhage have been related in the two teams. The improved anatomic success rates of vitreoretinal surgical procedure have been confounded by disappointingly poor visible function. Still, surgical procedure ought to be pursued when indicated, as even attaining hand-motion visual acuity permits many patients to stay ambulatory, and anatomic success might avoid the necessity for enucleation. Further modifications of therapy protocols, with an emphasis on preventing retinal detachment, will be essential earlier than significantly higher acuity may be retained in eyes with extreme phases of this devastating illness. Cryotherapy for Retinopathy of Prematurity Cooperative Group: Multicenter trial of cryotherapy for retinopathy of prematurity: ophthalmological outcomes at 10 years. Terasaki H, Hirose T: Late-onset retinal detachment associated with regressed retinopathy of prematurity. Cryotherapy for Retinopathy of Prematurity Cooperative Group: Multicenter trial of cryotherapy for retinopathy of prematurity.
Specifications/Details
Furthermore erectile dysfunction caused by radiation therapy tadalafil 10 mg discount overnight delivery, extreme stress exerted on the attention throughout a contact lens analysis could induce vasovagal reactions corresponding to fainting and nausea benadryl causes erectile dysfunction discount tadalafil 2.5 mg line. To use this lens erectile dysfunction reviews cheap tadalafil 2.5 mg with mastercard, a broad vertical slit beam is first rotated to illuminate the fundus from virtually a straight-on direction until the red reflex is clearly seen through the oculars how do erectile dysfunction pills work tadalafil 20 mg cheap free shipping. The resultant picture is actual, inverted, and of top of the range if a superior highpower aspherical lens made for this function is used. Because some slit-lamp focusing tracks are limited in journey away from the patient, it could be inconceivable to get hold of a clear fundus image with certain low-power oblique lenses. Shadows of the retinal vessels are seen on the pigment epithelial level, indicating the presence of subretinal fluid and a shallow serous detachment of the sensory retina. A high-power minus lens placed in front of the cornea varieties a digital image of the fundus. Moving a lever on the lens holder focuses the image, which is observed via the slit-lamp binoculars. Scleral depression could be attempted whereas viewing the fundus through these lenses, but this method requires considerable apply and is technically difficult. A viscous, clear liquid corresponding to methylcellulose or hydroxypropyl methylcellulose (Goniosol) is placed in the concave portion of the lens to optically couple the lens to the cornea. When fundus pictures is scheduled directly after elimination of the diagnostic contact lens, any residual interface solutions remaining on the cornea can degrade the retinal image. Each mirror has a different inclination between its floor and the axis of the lens. Through the central posterior pole portion, the sector of view is ~30� for an emmetropic eye. The smallest mirror is used to view the anterior chamber angle and occasionally the far periphery of the fundus. This is achieved by rotating a collar or knob on the slit lamp, which, in flip, rotates the slit beam. With the affected person gazing straight forward, the best image is obtained when the entrance floor of the lens is stored perpendicular to the viewing axis of the slit lamp. By rotating the examination mirror and readjusting the slit beam, all meridians of the retina may be evaluated. If the patient strikes her or his eye towards the mirror, a extra posteriorly positioned portion of the fundus comes into view. If the affected person looks toward the particular mirror getting used for viewing, a extra posterior region of the fundus will be seen. The fovea could inadvertently appear inside the remedy mirror of the lens on extreme gaze. Failure to acknowledge the fovea on this situation can lead to its destruction by photocoagulation. The middle-sized or smallest mirror should be inserted into the place opposite the depressor location. One type of lens holder incorporates an adjustable depressor that may be moved more posteriorly alongside the sclera in any meridian. The adjoining mirrors (A, B, C) are each inclined at totally different angles to the optical axis of the lens, offering visible entry to different areas of the fundus, as depicted at right. The picture plane is located fairly anterior to the lens surface, nonetheless, making it difficult to view the fundi of patients with hyperopia or exophthalmos when using slit lamps with limited ahead journey. This examination approach (transillumination ophthalmoscopy) requires that gentle be transmitted via the sclera and choroid. If an eye fixed accommodates a solid pigmented mass, transillumination is beneficial in that the tumor will appear dark, whereas different choroidal lesions, such as a choroidal detachment, might be much more brightly illuminated. Alternately, a transillumination gentle may be placed on the cornea so that it shines through the pupil. The examiner then observes the floor of the sclera, which ought to glow a uniformly orange colour. A pigmented tumor or foreign physique throughout the choroid will stop the transillumination light from illuminating the sclera beneath it, and a dark shadow might be present throughout the affected scleral quadrant. Placement of the Goldmann lens into a conical holder containing a scleral depressor at its periphery allows the examiner to carry out scleral depression whereas utilizing the slit-lamp biomicroscope. The flange and smaller contact diameter make this lens tougher to dislodge if the affected person squeezes the eyelids. When the meniscus lens is positioned on the cornea, the resultant picture of the fundus is inverted, real, minified, and situated properly ahead of the anterior lens surface. Magnification offered by the slit lamp counteracts the minification produced by the lens configuration. A wide-angle view of the fundus in an emmetropic eye, extending from the fovea to the equatorial region, is produced by such a panfunduscopic lens. The globe is illuminated, via the sclera on this illustration, by way of a fiberoptic mild source positioned on the globe externally or on the cornea. A dark choroidal lesion will block the transmission of light via the eye wall and will seem as a dark shadow surrounded by the pink glow of the rest of the sclera. Strong Since its introduction in the early Sixties, fluorescein angiography has become an important software within the understanding, analysis, and remedy of retinal problems. While direct examination of the fundus with slit-lamp biomicroscopy and indirect ophthalmoscopy is indispensable in the diagnosis of retinal disease, fluorescein angiography offers extra data concerning the anatomy, physiology, and pathology of the retina and choroid. Photographic or video photographs taken because the dye programs through the eye can demonstrate abnormalities within the neurosensory retina, pigment epithelium, sclera, choroid, and optic nerve, providing clinically useful data for practically the whole spectrum of posterior phase problems. As the molecules return to their authentic energy degree, they emit mild of a different, usually longer wavelength. Unlike phosphorescence, which continues to happen after the excitation supply is removed, fluorescence requires steady excitation. Once the excitation supply is removed, emission of fluorescence stops nearly immediately (10�8 s). Fluorescence happens naturally in certain compounds and will occasionally be observed in the human eye. Optic nerve drusen, astrocytic hamartomas, lipofuscin pigments in the retina, and the aging human lens are all believed to exhibit natural fluorescence that can be documented with varied photographic techniques. Fluorescein sodium absorbs blue gentle, with peak excitation occurring at wavelengths between 465 and 490 nm. In powdered or concentrated answer kind, fluorescein sodium seems orange�red in colour. In broad-spectrum illumination, diluted fluorescein sodium appears shiny yellow�green in shade. When illuminated with blue gentle, the yellow�green colour intensifies dramatically. The fluorescent properties of this dye have made it useful in a wide range of industrial, scientific, navy, and medical functions. Many of the medical and ophthalmic purposes of fluorescein are analogous to its uses in plumbing or industrial flow dynamics. In 1959, two medical students, Harold Novotny and David Alvis worked on a research project to develop a photographic approach to estimate blood oxygen concentrations within the retinal vascular bed as a visible phase of the cerebral circulation. They combined fluorescein with a blood sample and measured it with a spectrofluorometer to determine the excitation and emission wavelengths of fluorescein. They found the height excitation of fluorescein to be 490 nm and peak emission, 520 nm. Then they outfitted a fundus camera with broadband absorption filters, a Kodak Wratten 47B for excitation and a Kodak Wratten fifty eight green for the barrier. Alvis lost, so he was the topic of the first profitable fluorescein angiogram in a human. After their initial success, they refined the approach on numerous patients with diabetes and hypertension. The landmark paper describing their technique was printed in the journal Circulation in 1961, after being rejected by the ophthalmic literature as unoriginal work. In 1910, Burke described fluorescent staining of retinal and choroidal lesions in white mild, after ingestion of a mix of fluorescein in espresso. MacLean and Maumenee carried out fluorescein angioscopy with a blue exciter mild to diagnose a choroidal hemangioma following intravenous injection in 1960. The angiogram is used to determine the extent of damage, to develop a therapy plan or to monitor the results of treatment.
Syndromes
- You can use an over-the-counter drink, such as Pedialyte or Infalyte. Do not water down these drinks.
- Epiglottitis
- Ureterocele tissue falls down (prolapse) through the female urethra and into the vagina
- Eye infections
- · Lose weight if you need to.
- Swollen liver
Related Products
Additional information:
Lens subluxation erectile dysfunction commercials 5 mg tadalafil discount mastercard, pseudoexfoliation erectile dysfunction vitamins buy 2.5 mg tadalafil with amex, iridodonesis erectile dysfunction treatment san francisco tadalafil 20 mg buy discount on line, and phacodonesis should be documented erectile dysfunction medications online tadalafil 20 mg cheap line. The size of the dilated pupil and the brightness of the fundus red reflex can also be helpful in assessing the suitability of the lens. When informed consent is obtained, the patient is advised about other surgical options and the need to minimize head motion throughout surgery. Patient satisfaction tends to correlate with improvement in visual acuity and the elimination of preoperative glare. Often sufferers with equal bilateral preoperative visual acuities and postoperative outcomes report higher satisfaction with their first procedure. The peripheral retina must be observed for pathologies that require preoperative Argon laser barrage. Patients with mature cataract ought to undergo ocular ultrasound examination to rule out retinal detachment and posterior section masses. Potential acuity meter may be used to consider the potential for visible restoration in sufferers with multiple ocular situations. Preoperative analysis ought to embrace slitlamp examination for phaco or iridodonesis that will indicate poor zonular attachment. These are recognized when the patient strikes his eyes or when the examiner clamps the slit-lamp desk. Floppy iris syndrome ought to be suspected in all patients who had systemically obtained alpha-1 blocker, tamsulosin and this drug could additionally be discontinued for 2 weeks before surgery. Uveitic sufferers may obtain prophylactic topical and systemic corticosteroids for 1 week to stop postoperative flare-up. Posterior polar, mature and hard rock nuclei require specific intraoperative precautions (discussed later). Patients with dry eyes could also be handled with frequent nonpreserved artificial tears, topical antiinflammatory brokers such as cyclosporine A or delicate corticosteroids and punctal occlusion relying on the severity of the situation. Surgical candidates obtain dilation eye drops (cyclopentholate 1% and phenylephrine 10% in adults and cyclopentholate 0. Codeine pill is given to coughing sufferers and inhalation to sufferers with lively bronchial asthma and chronic obstructive pulmonary illness. An knowledgeable consent must be signed after the commonest and most serious potential issues have been explained. Consultation with different physicians as nicely as acquiring full blood count, electrocardiogram and chest radiograph may be required and patients on anticoagulants may be advised to discontinue them every week earlier than surgical procedure. The affected person is evaluated concerning the sort of anesthesia and chance for a supine position. The affected person is hooked up to blood strain and coronary heart monitors and oxygen is supplied via nasal prongs or pipe (normally 3�4 L/min and in continual obstructive lung disease 2 L/min). Sterilization of the eyelids and the face on the operated facet is finest performed with povidone iodide 5%. It is finest to enhance the magnification of the microscope and to decrease manually the microscope until a sharp picture of the conjunctival blood vessels is obtained. The preliminary and final steps of the surgery are 1442 Phacoemulsification � Theory and Practice performed underneath the bottom magnification, whereas the remaining beneath greater magnification. In such circumstances, surgery may be deferred for optimal situations under basic anesthesia, Poor blood strain control can be a sign to defer surgical procedure. Circumferential perilimbal injection of diluted 4% lidocaine with a 30-gauge needle ~4 mm posterior to the limbus also results in glorious anesthesia during phacoemulsification but is extra painful. The needle is directed parallel to the adjoining orbital wall and may move the airplane of the globe equator. Although direct penetration to the optic nerve can be prevented, globe penetration, peribulbar hemorrhage, muscle damage and central retinal artery occlusion can happen. Retrobulbar anesthesia and muscle akinesia are achieved by injection of 2�4 mL of 2% lidocaine, 0. Before injection, topical anesthetic is applied and the patient is asked to look away from the needle. The more recent pattern is toward the use of anesthesia related to minimal problems. Patients are usually not patched at the completion of the surgery, and visual recovery is instant. Adverse reactions embrace toxicity to the corneal epithelium (which could additionally be minimal if lidocaine is used7) and the absence of akinesia. Topical anesthesia with or with out sedation could also be used alone or together with intracameral injection. Alternatively, a sponge soaked with preservative-free lidocaine or bupivacaine could also be positioned underneath the fornices whereas exterior strain on the eyelids is applied8. The visual recovery and distinction sensitivity return to normal ~4 h after the intracameral injection as a substitute of almost instantly after topical anesthesia alone. Transient visible loss has been reported after posterior capsular tear in cases of intracameral lidocaine use. When topical anesthesia is being used you will want to clarify to the patient each step of the procedure and the anticipated feeling. Modes of Anesthesia Topical Advantages Anesthesia No perforation Rapid visible restoration No injection pain No akinesia Some discomfort (pain) Intracameral Iris manipulation Less patient discomfort Subconjunctival Anesthesia Less Peribulbar Anesthesia Akinesia Avoid some retrobulbar issues Complications: globe penetration, muscle damage Retrobulbar Anesthesia Akinesia General Sparing patient cooperation Disadvantages No akinesia No akinesia Major problems: orbital hemorrhage, Optic nerve/ muscle harm Anesthesia dangers. The needles are directed parallel to the orbital partitions within the location comparable to the superior and inferior lateral third of the orbital rim. Eyelid akinesia may be achieved by 1�2 mL anesthetic injection from the lateral aspect, alongside and adjacent to the rim and parallel to the floor. The anesthesia and akinesia are usually fast, but possible issues embody inadvertent penetration of the globe (especially in myopic eyes) or the optic nerve, injection to the optic nerve sheath, muscle injury, retrobulbar hemorrhage, oculocardiac reflex, and possible systemic toxicity and allergic reactions. In addition to these modes, general anesthesia is indicated for uncooperative patients. The needle is launched immediately superior to the lateral third of the inferior orbital rim. The needle is passed parallel to the orbital flooring and angled superomedially immediately past the globe equator. When viscoelastic agent is injected into the anterior chamber, the maintainer and irrigating fluid must be closed. The primary surgical wound must be customary earlier than hydrodissection and hydrodelineation are performed and they want to be performed through this incision. Paracenteses are used to inject viscoelastic agents, performing capsulorrhexis, or insertion of chopper and spatula. All cannulas which might be inserted into the eye ought to be filled with a small amount (0. If intraocular bleeding occurs during surgical procedure, elevation on the infusion bottle related to an anterior chamber maintainer ought to be enough. Air bubbles in the anterior chamber may be aspirated with the phaco tip in position 2 (aspiration/ irrigation) and not in place three (phacoemulsification) or with the aspiration/irrigation tip. The advantages of anterior chamber maintainer are that it preserves the depth of the anterior chamber in case of inadvertent sudden surge and it also allows infusion of brokers into the eye. The paracentesis is directed slightly posterior and obliquely to be able to keep away from circulate toward the endothelium or the capsulorrhexis margins. The maintainer could also be inserted firstly of the surgical procedure with its opening faced posteriorly to keep away from water jet damage to the endothelium. Additional one or two paracenteses are normally carried out between 2 and three clock hours from and on both facet of the main incision to allow injection of viscoelastic agent or the introduction of a second instrument in bimanual cataract extraction. Such incisions promote more speedy therapeutic, decrease astigmatism, scale back potential infections, and supply rapid visual rehabilitation. A temporal incision is often used if against-the-rule astigmatism is current before surgery. Access to the anterior chamber is simpler via a temporal incision due to the shallow lateral orbital wall. Three patterns of external incisions are generally employed; the standard curvilinear, the straight, and the frown incisions. The opposite-shaped frown incision theoretically provides the greatest assist and induces the least quantity of astigmatism.
Usage: q._h.
In this manner impotence and age order tadalafil 5 mg line, fibers of each shell lie atop fibers of the beforehand formed shell and beneath the fibers of the subsequently formed shell erectile dysfunction and diabetes treatment tadalafil 20 mg with amex. As a results of its continuous production throughout life erectile dysfunction medicine online tadalafil 20 mg generic with mastercard, the lens capsule becomes the thickest basement membrane within the body erectile dysfunction blood pressure medications side effects tadalafil 5 mg buy with mastercard. Clockwise from higher left, the thickened lens placode overlying the bulging optic vesicle; the invagination of the lens placode into the developing optic cup; the growing lens vesicle before pinching off from the presumptive cornea; the inverted hole lens vesicle and the onset of main fiber cell differentiation from posterior lens vesicle cells; progressive obliteration of the lens vesicle lumen by elongating primary fiber; embryonic nucleus composed of the first fiber mass and the overlying anterior lens epithelium; the human lens at delivery, the fetal nucleus composed of the embryonic nucleus (white primary fiber mass) surrounded by secondary fibers (stippled fibers). In this manner, the lens has a everlasting document of all of its fibers arranged in order of ascending age from its periphery to its interior. Because of the simple method that extra fibers are added to the lens over a lifetime, it has usually been accepted that lens development is achieved solely by secondary fiber formation. However, examination of primate lens epithelial cell dimension, density, and structure as a operate of age 1292 reveals that the lens epithelium also undergoes lifelong progress, however with vital zonal variations as a perform of age. This is achieved by variable increases in cell measurement and by concomitant increases or decreases in cell number as a perform of zonal epithelial location. The variation in total lens anterior floor area and epithelial cell measurement and number in normal primate lenses from delivery through old age is shown in Table 104. At any age, the gz comprises roughly the outer 10% of the anterior surface of the lens epithelium (additionally, the tz includes the most peripheral segment of this area). The cz and pgz account for the remaining 90% of the anterior surface area of the lens epithelium. Although all zones of the lens epithelium increase in dimension as a operate of age, mitotic activity is restricted primarily to the gz. This zonal management of mitotic activity raises the next important questions: Is the everexpanding floor space of the cz stuffed simply by cells of elevated dimension Is the ever-expanding floor area of the pgz, gz, and tz filled just by cells of increased size, by the addition of Biology of the Lens: Lens Transparency as a Function of Embryology, Anatomy, and Physiology with the average number of secondary fibers. The prediction of a variable zonal epithelial cell measurement as a perform of age and concomitant variation in zonal cell density as a operate of age is confirmed by entire mount cell counts. Thus, the cumulative epithelial cell quantity declines by 17% from young grownup (638 069) to old age (545 440) lenses. Failure to consider the zonal variation in lens epithelial cell density leads to a gross overestimation of complete epithelial cell number as a function of age. Necrosis is a pathologic type of cell death resulting from noxious harm or trauma. Second, apoptotic cells are characterized by distinct morphologic options which are essentially diametrically opposed to necrotic cells. Initially, apoptotic cells spherical up and shrink, somewhat than swell, thus losing intercellular contact between neighboring cells. Marked condensation of both cytoplasm and nucleoplasm as well as nucleosomal fragmentation of chromatin additionally characterize apoptotic cells. At the sunshine microscopic level, apoptotic cells and our bodies are often seen as dark cells. The apoptotic our bodies are then phagocytozed by surrounding parenchymal cells or macrophages. The complete process of apoptosis can happen as quickly as within a quantity of hours, but usually its duration is closer to a day. This form of cell death has usually been missed in regular tissues, and quantification of apoptotic cells in normal tissues is consequently very difficult. Studies have shown that in mature rat lenses, some cz cells are usually eliminated through apoptosis. A extremely simplified schematic diagram showing the main structural options of all crystalline lenses. The undifferentiated lens epithelial cells exist as a monolayer directly beneath the anterior lens capsule. Toward the latter levels of fiber elongation, the aforementioned intracellular organelles are eradicated, and fiber crystallin proteins type a uniform, homogeneous cytoplasm that minimizes gentle scattering. With dehydration and concentration of cytoplasmic proteins, the refractive index will increase and short-range order is established. Throughout the fiber mass, the spatial fluctuations in cytoplasmic density are small relative to the wavelength of light. Orderly development in the absence of vasculature, lymphatics, and nerves results in a transparent, refractile tissue consisting of closepacked hexagonal fibers. The development of transparent fiber structure may be studied in postnatal lenses as nicely as in embryonic lenses, as a result of fiber formation happens throughout life. If the increasing pgz, gz, and tz are crammed with additional new cells, is this through appositional or intercalary development In a number of studies analyzing lens epithelial cell dimension and number as a function of age, it has been discovered that each vary as a function of zonal location within the epithelium. Light micrographs of bovine nuclear fibers cross-sectioned in the equatorial plane. Lens Anterior Surface Area and Epithelial Cell Size and Number as a Function of Age At Birth Anterior floor area* cz epithelial cell floor area gz epithelial cell surface area cz epithelial cell number gz epithelial cell quantity Total epithelial cell quantity 31. Measurements have been made previous to any chemical preservation of lenses for microscopy. Cell dimension was calculated in two ways: First, a minimum of 10 scanning electron micrographs (at 300 magnification) had been taken of the cz and gz from the anterior floor of various aged primate (monkey) lenses. Second, 50 random cells from every micrograph were further magnified to a thousand and measured on a Calcomp 9100 digitizer (California Computer Products, Inc. No considerable distinction was noted in common cell measurement calculated by the two strategies. These cells, which are sometimes characterised by fragmented nuclei and condensed chromatin, have normally been attributed to artifacts of preparation. It has also been suggested that intercellular membranous debris seen in a selection of lens electron micrographs could symbolize the detritus of devitalized epithelial cells. Low-magnification scanning electron micrographs displaying the apical surfaces of (a and c) germinative (gz), and (b and d) central zone (cz) lens epithelial cells, from young grownup (7 year old; a and b), and old (24. If the aforementioned speculations are valid, then each the lens epithelium and fiber mass are populations of variably aged cells. Furthermore, it has been pointed out that some, however not all, of the daughter cells terminally differentiate into fibers. Furthermore, are these cells kept in a state of reversible growth arrest regulated by extrinsic (soluble growth inhibitory substances) and intrinsic (signal transducers) controls Furthermore, it has been proven that exterior elements identified to induce apoptosis can result in an experimental cataract. The shape of the anterior half of the lens approximates one-half of a 15� spheroid, whereas the shape of the posterior half approximates one-half of a 30� spheroid. The equatorial axis of the human lens is oriented primarily perpendicular to the sagittal airplane, and the polar axis of the lens is oriented basically parallel to the sagittal aircraft. As described earlier, lens epithelial cells are separated into distinct subpopulations;10 the cz, pgz, gz, and tz. The adult lens mass consists of three distinct fiber populations; the elongating fibers, the cortical fibers, and the nuclear fibers. Consequently, this region of the lens is characterised by an everchanging inhabitants of cells as nascent secondary fibers are added to the lens periphery, or the beginning of the elongating fiber region, and mature fibers are added to the periphery of the lens cortex as they exit the elongating fiber area. The elongating fibers represent an essential population of lens cells for the next reason. Diagrammatic representations of the gross form, anatomic orientation, and developmentally outlined areas of a standard human grownup lens. Clockwise from upper left, the asymmetric oblate spheroid form of the lens considered alongside the equatorial axis; the anterior surface of the lens considered alongside its polar axis; the approximate areas of the different zones of the lens epithelium; the cortical and nuclear regions of the lens; and the cortical and subdivided nuclear regions of the lens. As is explained in the lens physiology section, it had been thought that the lens epithelium, which has a full complement of organelles, was solely answerable for the upkeep of the underlying fiber mass, which lacks organelles. It is now recognized that the elimination of organelles as a perform of fiber terminal differentiation occurs to a fantastic extent after fiber elongation has been accomplished. In a young grownup lens, the nucleus consists of all the fibers, each primary and secondary, shaped earlier than sexual maturation. The fetal nucleus consists of the embryonic nucleus and all of the secondary fibers added onto it until parturition. The infantile nucleus consists of the fetal nucleus and all the secondary fibers added onto it via roughly the primary 4 years of life. The juvenile nucleus consists of the childish nucleus and all secondary fibers added onto it until sexual maturation.
Tags: purchase tadalafil 5 mg free shipping, purchase tadalafil 20 mg line, tadalafil 5 mg buy generic on-line, 20 mg tadalafil purchase with mastercard, tadalafil 2.5 mg buy free shipping, tadalafil 2.5 mg without prescription, tadalafil 10 mg trusted, 20 mg tadalafil purchase with visa, tadalafil 2.5 mg line, 2.5 mg tadalafil mastercard, tadalafil 5 mg discount with visa, tadalafil 20 mg without prescription, discount tadalafil 2.5 mg free shipping, 5 mg tadalafil order free shipping, purchase tadalafil 10 mg with amex, buy tadalafil 20 mg cheap
8 of 10
Votes: 277 votes
Total customer reviews: 277
Customer Reviews
Ines, 43 years: Approximately 50�60% of untreated patients could have a ultimate visual acuity of 20/40 or higher. Dislocation of the small amount of cortex or small nuclear fragments could also be tolerated and may not require intervention. These pathways occur between epithelial cells, between fibers, and possibly between fibers and epithelial cells. When this stage is performed, the surgeon ought to look forward to posterior capsular folds.
Hatlod, 51 years: Capsulorrhexis allows safer manipulations within the bag than different types of anterior capsulotomy. Three months after surgery there was an improvement in ocular signs (diplopia and halos) and a major improve in the treated optical zone in topography. Tolentino M, Miller J, Gragoudas E, et al: Intravitreous injections of vascular endothelial development factor produce retinal ischemia and microangiopathy in an grownup primate. Neuropathy in decrease extremities may alter mobility in such a method that restoration and upkeep of as a lot vision as potential is necessary.
