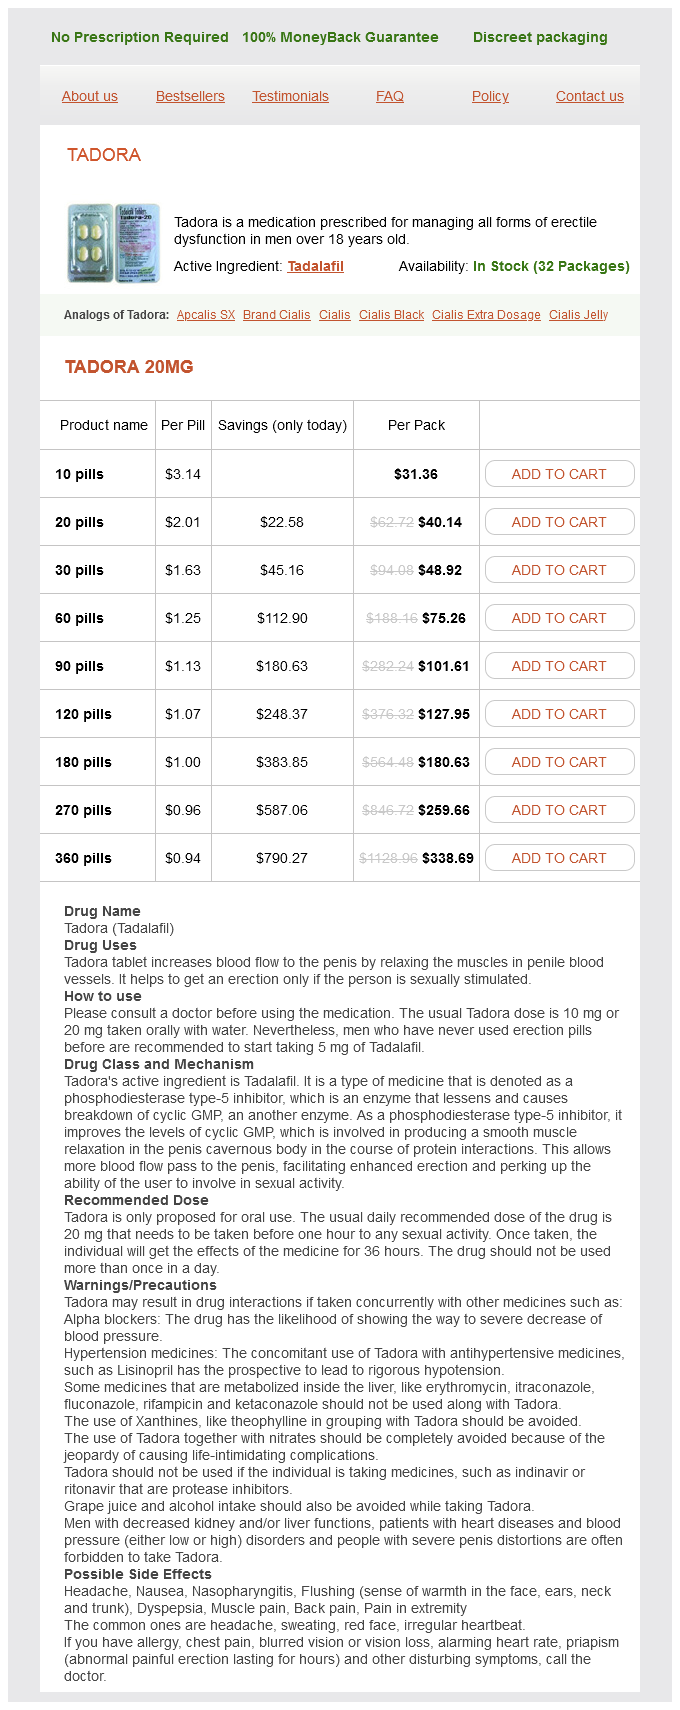
Tadora 20mg
- 10 pills - $31.36
- 20 pills - $40.14
- 30 pills - $48.92
- 60 pills - $75.26
- 90 pills - $101.61
- 120 pills - $127.95
- 180 pills - $180.63
- 270 pills - $259.66
- 360 pills - $338.69
Tadora dosages: 20 mg
Tadora packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 732
Only $1 per item
Description
Its major function is to act as a valve regulating the outflow of intrathoracic and intraabdominal pressures erectile dysfunction jacksonville fl tadora 20 mg discount without a prescription, though it can additionally affect phonation erectile dysfunction commercial bob tadora 20 mg buy with mastercard. These mucosa-lined compartments demarcate two areas of significance: the preepiglottic space and the paraglottic house erectile dysfunction video generic tadora 20 mg mastercard. A laryngoscopic view of the larynx reveals the vestibule as that portion of the larynx from the tip of the epiglottis to the false vocal or vestibular folds erectile dysfunction endovascular treatment buy tadora 20 mg mastercard. Thus, the vestibule is sure by the epiglottis anteriorly, the aryepiglottic folds laterally, and the arytenoid and corniculate cartilages with the interarytenoid muscle posteriorly. In the laryngoscopic view, the anterior commissure is frequently hidden by the protuberance of the epiglottis known as the tubercle. As previously mentioned, the vestibular folds are shaped by mucosa overlying the vestibular ligament (inferior border of the quadrangular membrane). The secretions produced by these exocrine glands provide both mechanical and immune (lysozyme) safety for the vocal folds. The ventricle or sinus of Morgagni is the small house between the false and true vocal folds. The ventricle is commonly hidden throughout laryngoscopic examination of the larynx unless uncovered by lateralization of the false vocal fold. At the anterior finish of the ventricle is a diverticulum known as the laryngeal saccule. The saccule (of Hilton) is lined with mucous glands, which are thought to lubricate the vocal folds. Fibers of the thyroarytenoid muscle line the walls of the saccule and are thought to categorical mucus from the saccule after they contract. The size of the saccule is type of variable; however, it seldom extends above the superior border of the thyroid cartilage. The infraglottic cavity extends from the glottis down to the inferior border of the cricoid cartilage. Its lateral boundary is shaped by the conus elasticus and partitions of the cricoid cartilage. Although the pyriform sinus is anatomically part of the hypopharynx, understanding its anatomy and its relationship to the larynx is important. The pyriform sinus is a gutter shaped by the aryepiglottic fold, arytenoid cartilage, and superior a part of the cricoid cartilage medially and the 3486 thyrohyoid membrane and inner surface of the thyroid lamina laterally. Thus, most cancers invasion of the apex implies the need of removing a portion of the cricoid if conservation laryngectomy is planned. Anteriorly within the flooring of the sinus, a small fold can be seen, which marks the course of the superior laryngeal nerve. This submucosal course of the nerve makes it possible to anesthetize the nerve topically in the pyriform sinus. The second, more variable landmark is the protrusion made into the sinus from the superior cornu of the thyroid cartilage. The mucosa of the larynx is of two sorts: pseudostratified ciliated columnar cell (respiratory) epithelium and squamous cell epithelium. Much of the larynx is surfaced by respiratory epithelium; nevertheless, the superior portion of the epiglottis, upper portions of the aryepiglottic folds, and free edges of the vocal folds are surfaced by squamous cell epithelium. Beneath this covering epithelium is a variable basement membrane, and separating these two is a layer of loose fibrous stroma. It ought to be noted that this loose fibrous layer is absent on the true vocal folds as nicely as the laryngeal (posterior) surface of the epiglottis. The absence of this layer on the posterior floor of the epiglottis accounts for the extra intense swelling of the lingual (anterior) surface of the epiglottis in inflammatory conditions of the larynx. The preepiglottic space, as its name implies, lies anterior 3487 to the epiglottis, which serves as its posterior boundary. It is certain superiorly by the hyoepiglottic ligament and mucosa of the valleculae and inferiorly by the thyroepiglottic ligament. The anterior boundaries are the thyrohyoid membrane and the internal surfaces of the thyroid laminae. Cancer on the infrahyoid portion of the epiglottis can penetrate the epiglottis and achieve entry to the preepiglottic house. This space lies above and beneath the true and false vocal folds and is essential within the transglottic and extralaryngeal spread of neoplasms. Medially, the space is sure by the quadrangular membrane, ventricle, and conus elasticus. Anterosuperiorly, the house opens in the posterior portion of the preepiglottic space. The relationships of this paraglottic house make it necessary in contemplating the unfold of laryngeal cancer. Vocal Folds the anatomy of the vocal folds is advanced and is thus thought-about separately. The vocal fold is considered the structure between the vocal strategy of the arytenoid and the anterior commissure. The vocal folds and the slit between them (rima glottidis) represent the glottis. The glottis could be divided by a horizontal line between the ideas of the vocal processes. This imaginary line divides the glottis into an intermembranous portion and an intercartilaginous portion. The anterior to posterior (length) ratio of the intermembranous portion to the intercartilaginous is three:2; nonetheless, the ratio of cross-sectional areas defined by them is 2:3. Thus, owing to its more rectangular form, the intercartilaginous portion is bigger. Between these exists a transition zone composed of the intermediate (elastic) and deep (collagenous) layers of the lamina propria. According to this idea, the vocal folds include a multilayered vibrator with 3488 rising stiffness from the duvet to the body. Thus, the duvet is liable for many of the vibratory action of the vocal folds. At the anterior and posterior ends of the vocal folds exist an anterior and a posterior macula flava, respectively. These are primarily a thickening of the intermediate (elastic) layer of the lamina propria and are thought to perform as "cushions" protecting the ends of the vocal folds from vibratory damage. In the senile larynx, the elastic layer and the vocalis muscle are inclined to atrophy, whereas the collagenous layer thickens. The cover turns into thickened and edematous secondary to modifications in the superficial layer of the lamina, whereas the epithelium itself adjustments little. Thus, the false folds passively impede egress of air, whereas the true folds impede its ingress. Working with cadaver larynges, Brunton and Cash demonstrated that the false folds offered a resistance equaling 30 mmHg to the egress of air from below, whereas the true folds provided a resistance equaling a hundred and forty mmHg to the ingress of air from above. Phylogenetically this supports the protective nature of the true vocal folds, whereas allowing little resistance to the egress of airflow. The arterial provide to the larynx consists of the superior and inferior laryngeal arteries. This artery then runs anteromedially with the interior branch of the superior laryngeal nerve to enter the thyrohyoid membrane inferior to the nerve. It then enters the submucosa of the pyriform sinus and is distributed to intralaryngeal structures. The superior thyroid additionally gives off a cricothyroid department that programs horizontally beneath the thyroid cartilage. The inferior laryngeal artery is a department of the inferior thyroid artery that comes off the thyrocervical trunk branching from the subclavian artery. After coursing posterior to the cricothyroid joint with 3489 the recurrent laryngeal nerve, the artery enters the larynx by passing by way of a spot in the inferior constrictor muscle known as the Killian-Jamieson area. This space is a region between the indirect and transverse fibers of the cricopharyngeal muscle. The artery is then distributed to the remainder of the internal larynx, making multiple anastomoses with the superior laryngeal artery. An appreciation of the lymphatics of the larynx is prerequisite to understanding the spread of cancer of the larynx, in addition to the operative procedures designed to eradicate the illness. The deep network is additional divided into right and left halves, with little communication between them. These two halves can be further divided into supraglottic, glottic, and subglottic, with special consideration given to the ventricle within the supraglottic region.
Anemone pratensis (Pulsatilla). Tadora.
- Are there safety concerns?
- Conditions of the male or female reproductive system, tension headache, hyperactive states, insomnia, boils, skin diseases, asthma and lung disease, earache, migraines, nerve problems, general restlessness, digestive and urinary tract problems, and other conditions.
- How does Pulsatilla work?
- What is Pulsatilla?
- Dosing considerations for Pulsatilla.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96625
While fluoroscopy may suggest the presence of malignant neoplasms erectile dysfunction ka desi ilaj tadora 20 mg buy amex, probably the most sensitive technique of detecting esophageal most cancers is endoscopy with biopsy erectile dysfunction doctor miami 20 mg tadora order otc. Most signs of esophageal carcinoma are nonspecific and embody weight loss impotence use it or lose it 20 mg tadora sale, vomiting erectile dysfunction protocol book scam tadora 20 mg order free shipping, and delicate hematemesis. With rare exception, all sufferers with strong food dysphagia ought to be evaluated for esophageal carcinoma by esophagoscopy. More than half of patients with esophageal malignancies have distant metastases at the time of prognosis. Squamous cell carcinoma of the esophagus has been historically considered the most common malignancy of the esophagus, but that is altering. Among cancers, the incidence of adenocarcinoma of the esophagus is the fastest rising in America and is now greater than its squamous cell counterpart. On esophagoscopy, adenocarcinoma might appear as a mucosa-covered nodule or as an ulcerative mass with esophageal obstruction in more advanced cases. As mentioned earlier, esophageal malignancies could spread all through the length of the esophagus from any major site because of the intensive, interconnected lymphatic community. Therefore, the entire esophagus is usually treated regardless of the major location in the esophagus. Primary surgical therapy, often with whole esophagectomy and gastric pull-up or colonic interposition, is the standard mainstay of esophageal carcinoma therapy, with chemotherapy and radiotherapy used for lesions that invade the muscularis or deeper. In the presence of distant metastases, palliation with esophageal stents is normally the only treatment supplied. Survival from adenocarcinoma has improved considerably in latest years, presumably from earlier prognosis. In a examine of 263 sufferers present process surgical procedure for esophageal adenocarcinoma, Portale et al, reported a 46. Functional pharyngoesophagoscopy: a model new method for diagnostics and analyzing deglutition. Tracheobronchoscopy and esophagoscopy in present ear-nose-throat pracice: an update. Bronchoscopy and Esophagoscopy: A Manual of Peroral Endoscopy and Laryngeal Surgery. Comparison of rigid and flexible esophagoscopy in the analysis of esophageal illness: diagnostic accuracy, issues and value. A randomized potential trial evaluating unsedated esophagoscopy via transnasal and transoral routes utilizing a 4 mm video endoscope with conventional endoscopy with sedation. Trans-nasal oesphagoscopy: value implications for a change in practice: how we do it. Paper introduced at: 87th Annual Meeting of the American Broncho-Esophageal Association; April 26�27, 2007. Wireless pH testing as an adjunct to unsedated transnasal esophagoscopy: the safety and efficacy of transnasal telemetry capsule placement. Unsedated transnasal esophagogastroduodenoscopy for the evaluation of dysphagia following treatment for earlier main head [sic] neck most cancers. Prediction of simultaneous esophageal lesions in head and neck squamous cell carcinoma. Detection of metachronous esophageal squamous carcinoma in sufferers with head and neck most cancers with use of transnasal esophagoscopy. Functional oesophagoscopy: endoscopic analysis of the oesophageal phase of deglutition. Patient tolerance of in-office pulsed dye laser remedies to the higher aerodigestive tract. Perforation after inflexible pharyngooesophagoscopy: when do signs and indicators develop Eroglu A, Turkyilmaz A, Aydin Y, et al Current administration of esophageal perforation: 20 years experience. Esophageal perforation in adults: aggressive, conservative therapy lowers morbidity and mortality. Prevalence of penetration and aspiration on videofluoroscopy in regular individuals without dysphagia. Eosinophilic esophagitis: scientific features, endoscopic findings and response to remedy. Eosinophilic esophagitis in children and adults: a scientific review of sufferers with dysphagia brought on by benign issues of the distal esophagus. Eosinophilic esophagitis in adults: an rising downside with unique esophageal features. Endoscopic evaluation of esophagitis: scientific and practical correlates and additional validation of the Los Angeles classification. Chicago classification criteria of esophageal motility issues outlined in high resolution esophageal pressure topography. Esophageal motility issues in terms of stress topography: the Chicago Classification. Bethanechol improves easy muscle operate in sufferers with extreme ineffective esophageal motility. Esophageal motility issues (distal esophageal spasm, nutcracker esophagus, and hypertensive lower esophageal sphincter): trendy management. Use of botulinium toxin for analysis and administration of cricopharyngeal achalasia. Flexible versus inflexible endoscopy for remedy of foreign physique impaction within the esophagus. Ingestion of acid and alkaline brokers: outcome and prognostic worth of early upper endoscopy. Steroids for the therapy of corrosive esophageal harm: a statistical evaluation of past research. Sudden death as a result of asphyxia by esophageal polyp: two case reports and evaluation of asphyxial deaths. Modern 5-year survival of resectable esophageal adenocarcinoma: single establishment expertise with 263 sufferers. The sequence of accelerating resistance, persistent respiratory effort, hypoventilation, and obstruction ultimately lead to loud night time breathing and sleep apnea. The start line of sleep disordered breathing is a structurally small or susceptible higher airway. Understanding this complexity is critical to profitable remedy and superior care of the sufferers with medical and surgical sleep disorders. Accurate determinations of prevalence of sleep apnea and snoring measurements are confounded by various definitions of illness and by age, ethnicity, and gender results. A community-based objective research demonstrated 80% of subjects snored at least 10% of the night and 20% snored for higher than 50% of the night time. Habitual frequent or "at all times" loud night time breathing affects more than 21% of men and 8% of girls. Sleep apnea is estimated to have an result on 34 to 60% of recurring snorers when defined by having symptoms of fatigue and noticed apneas. Obesity, getting older, smoking, and postmenopausal standing alter the incidence of snoring and presumably sleep apnea. Few knowledge exist about prevalence of different less common problems of sleep disordered breathing including central sleep apnea syndromes and obesity hypoventilation (Pickwickian syndrome). The common vary varies from 1 to 10%; nonetheless, some populations such as obese Asian youngsters have a prevalence of 33%. Since the primary symptoms are widespread within the population, symptoms poorly predict disease. Clinical impression has solely 60% sensitivity and specificity in figuring out apnea sufferers in a sleep-clinic inhabitants. Table 98-1Symptoms of Sleep Apnea in Adults and Children Symptoms and Signs Adults Children Major signs Major symptoms Chronic and loud loud night breathing Noisy respiration (snoring) Gasping or choking episodes throughout Mouth respiration 3991 sleep Excessive daytime sleepiness Agitated sleep Personality modifications or cognitive difficulties related to fatigue Nocturnal awakenings Sleepiness throughout driving or different activities requiring alertness Learning difficulties Abnormal daytime habits Hard to get up and daytime fatigue Other symptoms Other symptoms Morning headaches Persistent enuresis Sexual dysfunction Sleepwalking with or without night time terrors Restless sleep Failure to thrive Diaphoresis Repeated higher respiratory infections Recent weight gain Worsening of recurring loud night time breathing Signs Signs Obesity Obesity Conditions related to decreased upper airway dimension Enlarged tonsils (grade 3 or 4) 3992 Systemic hypertension Enlarged adenoid (adenoid index > zero. These include fatigue, daytime impairment, despair, change in temper, poor long- or short-term memory, decreased executive functioning and an increased risk of accidents. Unfortunately, none of those symptoms alone predict apnea although all may have major impression on the affected person and disease severity. Since apnea has important health issues, patients with greater threat corresponding to severe cardiovascular disease, atrial fibrillation, poorly controlled hypertension, and others warrants further evaluation.
Specifications/Details
Treatment the primary line for phonotraumatic lesions is behavioral intervention with speech and singing therapy low cost erectile dysfunction drugs 20 mg tadora discount otc. This remedy modality will maximize the effectivity of phonation and minimize the vocal patterns that propagated these lesions erectile dysfunction treatment cost in india buy 20 mg tadora. Concurrent therapeutic effort should handle laryngopharyngeal reflux and poor vocal hygiene (dehydration) erectile dysfunction pill brands 20 mg tadora buy visa, as these circumstances can exacerbate mucosal friability at the level of the glottis erectile dysfunction drugs at walgreens cheap tadora 20 mg without a prescription. A combination of therapy is often very profitable for such lesions however enchancment in voice could not correlate to regression of the causative lesion. Given the potential for vocal fold scarring, multiple elements ought to be mentioned with the affected person previous to present process invasive remedy. The major goal of surgical intervention ought to be to return the larynx to a pre-morbid state, thus restoring normal laryngeal function. These strategies are referred to as microflap, minimicroflap, or subepithelial resections. In sure circumstances, the advantages of eradicating pathology may not outweigh the dangers of performing microsurgery. Unfortunately, the perfect surgical affected person is commonly the patient least more doubtless to profit from surgical intervention. Those patients embody people with low vocal calls for and accessible pathology (large polyps). The sufferers that will doubtless profit essentially the most from intervention (those with high vocal demand) are also these most-likely affected from any complication of the procedure. It is an extension of the laryngeal ventricle and spans posterolaterally to the sting of the laryngeal floor of the epiglottis. Both laryngoceles and saccular cysts involve enlargement of the saccule to form a mass. Laryngoceles by definition contain air within the lumen, whereas saccular cysts are fluid-filled lots. Laryngoceles include a patent communication with the laryngeal lumen, thus allowing air passage. External laryngoceles are positioned totally outside of the laryngeal framework and blended laryngoceles include both inner and exterior elements. Saccular cysts are additionally classified according to their location and are caused by abnormal dilation of the saccule. Traditionally, saccular plenty are seen in people who develop excessive intralaryngeal pressures (glass blowers, trumpet players). Superinfection can lead to speedy growth and acute presentation with worsening signs, fever, and sometimes airway obstruction. Diagnostic Principles Patients with laryngoceles and saccular cysts report a spectrum of dysphonia, dysphagia and even airway obstruction depending on the size and location of the lesion. The diagnosis is most commonly made by bodily examination including transnasal or transoral laryngeal imaging and neck examination. In the case of anterior saccular cysts, a mass may be seen emanating from the vestibule to the laryngeal lumen while lateral saccular cysts and laryngoceles present as a submucosal mass within the false vocal fold. External and mixed laryngoceles can present as a neck mass that enlarges with valsalva. Fluid-filled mass arising from the saccule and protruding into the laryngeal lumen. Treatment Principles Although controversy exists in the literature as to the surgical management of laryngoceles and saccular cysts, most authors agree that surgery is the definitive management. Endoscopic therapy of those lesions involves both complete resection versus marsupialization. However, with superior instrumentation, visualization, and surgical technique, laryngofissure is commonly pointless. Axial computed tomography displaying air-filled dilation of the saccule extending through the thyrohyoid membrane into the neck. These are caused by an exophytic tissue response to acute and chonic inflammatory processes. Mechanical causes embrace vocal hyperfunction and continual chough, and nonvocal laryngeal trauma as seen in intubation injury. Any supply of inflammation can lead to native tissue damage that will then cascade into a similar exophytic response. Compounding this situation is the fact that these patients are additionally more doubtless to develop vocally abusive behaviors corresponding to chronic cough and throat clearing which can additional the inflammatory response. Globus sensation and throat pain can be localized to the greater cornu of the thyroid cartilage, usually on the ipsilateral aspect. A thorough historical past should embrace questions detailing circumstance surrounding the onset of symptoms, for instance, intubation, higher airway infection, coughing, changing vocal demands. Patients with lesions that current in an atypical location or with an appearance worrisome for malignancy ought to endure biopsy for prognosis, significantly if the patient has danger elements for carcinoma. In the occasion of failure of outpatient management, the patient must be referred to a gastroenterologist for additional workup, and other sources of ongoing vocal trauma should be investigated. Persistent dysphonia despite maximal medical remedy can be an indication for surgical procedure. Microsurgical resection involves amputation of the granuloma at its base sustaining the integrity of the underlying cartilage. Care must be taken working within the posterior a part of the glottis to decrease trauma and prevent scarring or damage to the cricoarytenoid joint. Patients may benefit from a short course of post-operative voice relaxation to promote therapeutic. Injection of the laryngeal adductory musculature with botulinum toxin may be of benefit as an adjuvant remedy. Bilateral, right bigger than left, postintubation granulomas on the vocal processes. Theories for the congenital and bought pathogenesis of sulcus vocalis have been introduced. Vocal-fold scarring is classed based on its underlying etiology: traumatic (blunt, penetrating, radiation, surgery, glottic carcinoma), iatrogenic (vocal twine surgery, extended intubation, tracheostomy), and inflammatory (inhalation injury, rheumatic diseases). Typical complaints are of dysphonia characterized by hoarseness, breathy voice quality, and vocal fatigue. Endoscopic findings for these two entities are additionally related and embrace an asymmetric spindle-shaped glottic closure pattern medial furrows or troughs on the glottic margin, and supraglottic hyperfunction. High-resolution videostroboscopic imaging with careful analysis is most often essential to establish these subtle lesions. This examination will show disruption of mucosal wave with focal adynamic segments on the website of the lesion. Treatment Principles Treatment for sulcus vocalis and vocal-fold scarring must be directed at bettering glottal effectivity and voice high quality. Voice remedy ought to be instituted early to encourage optimum phonatory efficiency and cessation of maladaptive behaviors. Surgery may be thought of when patients have failed maximal medical 3572 administration. Surgical methods embrace medialization thyroplasty, injection thyroplasty, local corticosteroid injection, fat or fascia implantation, and mucosal elevation and redraping. Videostroboscopy reveals vocal folds with elevated mucosal wave amplitude, lowered elementary frequency, and vibratory aperiodicity. Inspiratory phonation is a useful approach to draw the polypoid vocal folds into the lumen of the airway revealing the true dimension of the lesions. On histologic examination, the polypoid degeneration of the vocal folds seems because the formation of extra lamina propria. Once airway patency is confirmed or addressed, therapy is then targeted on enhancing vocal efficiency. Smoking cessation and administration of hypothyroidism, if current, are step one within the remedy of Reinke edema. Patients wishing to undergo elective remedy for voice improvement should be endorsed specifically in regards to the danger of recurrence with ongoing smoking, vocal-fold scarring and failure to enhance the voice. Surgical intervention follows the cautious microsurgical principles described for phonotraumatic lesions. Some advocate staging bilateral disease to reduce threat of an online formation and bilateral scarring.
Syndromes
- Is the pain in the forearms, hands, lower legs, or feet?
- Unsteadiness
- Tube through the mouth into the stomach to wash out the stomach (gastric lavage)
- Pulls self to standing position
- Falls are a major cause of injury in preschoolers. Climbing to new and adventurous heights, preschoolers may fall off playground equipment, bikes, down stairs, from trees, out of windows, and off roofs. Lock doors that access dangerous areas (such as roofs, attic windows, and steep staircases) and have strict rules for the preschooler about areas that are off-limits.
- Blood thinner medicine (heparin) to prevent blood clotting
Related Products
Additional information:
When the right and left cricothyroid muscular tissues contract erectile dysfunction pills review purchase tadora 20 mg overnight delivery, they rotate the cricoid at the cricothyroid joint what is erectile dysfunction wiki answers 20 mg tadora buy with mastercard. This motion brings the anterior arch of the cricoid superiorly toward the inferior border of the thyroid laminae while displacing the posterior cricoid lamina (and the arytenoid cartilages) inferiorly beer causes erectile dysfunction order 20 mg tadora free shipping. This inferior displacement increases the space between the vocal processes and the anterior commissure; the outcomes of this action is to decrease erectile dysfunction 60784 tadora 20 mg buy cheap on line, stretch, and skinny the vocal folds while bringing them right into a paramedian position. Biomechanically, this translates into a higher basic frequency produced by the vocal folds and helps to control vocal pitch. It is seated in a despair on the posterior floor of the cricoid lamina, and its fibers run obliquely superior and lateral to connect onto the muscular process of the arytenoid cartilage. Contraction of these fibers brings the muscular course of medial, posterior, and inferior whereas laterally rotating and elevating the vocal process. This action abducts, elongates, and thins the vocal folds while causing the vocal-fold edge to be rounded. The complicated operate of this muscle has been studied in the canine during which three distinct neuromuscular compartments are discovered. It is proposed that the vertical and oblique bellies normally trigger vocal-fold abduction during respiration, whereas the horizontal belly is primarily used to modify the place of the vocal course of throughout phonation. The lateral cricoarytenoid muscle is the principle antagonist of the posterior cricoarytenoid. It attaches along the superior border of the cricoid cartilage and sends fibers posteriorly to insert on the anterior portion of the muscular course of. Contraction of this muscle brings the muscular course of anterolaterally whereas adducting and reducing the vocal process. The edge of the vocal fold turns into sharper, and its component layers are passively stiffened. The interarytenoid muscle is the only unpaired intrinsic muscle, consisting of two kinds of muscle fibers. The bulk of the muscle consists of transverse fibers passing from the posterior surface of 1 arytenoid cartilage to the posterior floor of the other. This muscle contracts to bring together the arytenoid cartilages, thus aiding in closing the posterior portion of the glottis. These oblique fibers pass from the posterior portion of the arytenoid on one side to the apex of the arytenoid on the opposite facet, thus crossing within the midline. Some fibers insert at the apex, whereas others travel along the quadrangular membrane. Those fibers touring alongside the quadrangular membrane (thus the aryepiglottic fold) represent the aryepiglottic muscle. Heavy arrows indicate the direction of muscle action; nice arrows indicate the movement of vocal ligaments; and open arrows point out the motion of cricoid and thyroid cartilages. The left column reveals the location of the cartilages and the sting of the vocal folds when the laryngeal muscle tissue are activated individually. The right column presents contours of frontal sections on the center of the membranous portion of the vocal fold. The thyroarytenoid muscle is classically divided into the thyroarytenoid internus and externus. These have the identical attachments, however the internus lies deep or inside to the externus. The thyroarytenoid externus arises from the anterior commissure and inserts onto the lateral surface of the arytenoid cartilage. It contracts to convey the vocal process and anterior commissure closer to each other, thus adducting the vocal folds. The externus sends a few slips of muscle fibers onto the quadrangular membrane to establish the thyroepiglottic muscle. The thyroarytenoid internus or vocalis muscle attaches on the anterior 3483 commissure and inserts onto the vocal course of, sending a number of slips of fibers under the vocal ligament onto the conus elasticus. It contracts to adduct, shorten, thicken, and decrease the vocal fold while rounding its edge. The physique (muscle) of the vocal fold is actively stiffened, whereas the cover is passively slackened. Recently, immunohistochemical staining for myofibrillar adenosine triphosphatase reveals that almost all of fibers within the internus are slow-twitch and those within the externus fast-twitch, suggesting its unique human specialization for speech perform. The musculature underlying the ventricular folds has been somewhat sick outlined and infrequently confused as a superior extension of the thyroarytenoid muscle. However, histologic analysis of the ventricularis demonstrates fibers oriented in the anterior-posterior orientation, in comparison to the extra inferiorly oblique oriented fibers of the thyroarytenoid. The drainage of the supraglottic buildings (aryepiglottic folds and false folds) follows the superior laryngeal and superior thyroid vessels. Thus, the lymphatics circulate from the pyriform sinus through the thyrohyoid membrane to finish primarily in the deep jugular chain across the carotid bifurcation. It ought to be noted that the epiglottis is a midline construction; thus, its lymphatic drainage is bilateral. The lymphatic drainage of the ventricle is completely different from the other supraglottic structures. Dye injected into the ventricle enters the paraglottic space and is shortly unfold by the lymphatic system via the cricothyroid membrane and also into the ipsilateral lobe of the thyroid (justifying its resection in laryngectomy). The true vocal folds themselves are devoid of lymphatics, accounting for the excessive curability of cancer localized to this construction. One system follows the inferior thyroid vessels to end within the decrease portion of the deep jugular chain of lymph nodes as properly as the subclavian, paratracheal, and tracheoesophageal chains. This system appears to receive lymphatics from both sides of the larynx and disseminate bilaterally to the center deep cervical lymph nodes in addition to the prelaryngeal (Delphian) lymph nodes. Innervation the pattern of innervation to and from the larynx and the type and distribution of its receptors decide the practical capabilities of the larynx. The superior laryngeal nerve leaves the nodose ganglion to move between the carotid artery and the laryngohyoid complicated. The internal department pierces the thyrohyoid membrane with the superior laryngeal artery and turns into the sensory provide to the ipsilateral supraglottic portion of the larynx, whereas the external branch innervates the cricothyroid and inferior constrictor muscle tissue. The inferior laryngeal nerve originates from the recurrent laryngeal nerve and runs within the tracheoesophageal groove. It enters the larynx posterior to the cricothyroid joint and classically divides into an anterior adductor and a posterior abductor department. This branching, however, is sort of variable, as is the muscular innervation from the branches. The mucosal receptors reply to stimuli such as touch, mucosal deformation (mechanoreceptors), and liquids. The articular receptors are situated within the joint capsule and respond to deformation of the capsule. The myotatic receptors reply to muscular stretch and seem to be most plentiful in the vocalis muscle. The sensory innervation to the mucosa of the supraglottic portion of the larynx is carried by the internal branch of the ipsilateral superior laryngeal nerve, which is divided into three divisions. The superior division mainly supplies the mucosa of the laryngeal surface of the epiglottis, the middle division provides the mucosa of the true and false vocal folds and the aryepiglottic fold, and the inferior division supplies the mucosa of the arytenoid, a half of the subglottis, the anterior wall of the hypopharynx, and the upper esophageal sphincter. The inferior laryngeal nerve supplies the main portions of mucosa beneath the glottis as properly as muscle spindles of intrinsic muscular tissues. The exterior branch of the 3491 superior laryngeal nerve contains afferent fibers from the cricothyroid joint and from deep muscle receptors. Histologic examination has revealed the presence of free nerve endings, Merkel cells, Meissner corpuscles, and style buds scattered in the larynx. Mechanoreceptors are located either in the superficial mucosa or in the muscle tissue and laryngeal joints. Some of them are spontaneously energetic, whereas others are silent till stimulated. A massive number of style buds populate the laryngeal floor of the epiglottis and lengthen caudally alongside the aryepiglottic folds, reaching peak density at the caudal excessive of the folds. The style buds of the larynx are inclined to be most delicate to the pH and tonicity of the stimulus. In this regard, the water receptors of the epiglottis appear to play a task within the manufacturing of prolonged apnea. When stimulated, they lead to a slowing of respiration with a rise in tidal volume. The afferent impulses generated are delivered to the tractus solitarius by way of the ganglion nodosum.
Usage: gtt.
Fibromyalgia and overlapping problems: the unifying concept of central sensitivity syndromes impotent rage definition 20 mg tadora generic with amex. Central Sensitivity Syndromes: a new paradigm and group nosology for fibromyalgia and overlapping conditions erectile dysfunction treatment supplements discount 20 mg tadora fast delivery, and the related issue of illness versus sickness erectile dysfunction pills non prescription effective tadora 20 mg. Developing the communicative participation merchandise bank: Rasch analysis results from a spasmodic dysphonia sample erectile dysfunction medications generic 20 mg tadora free shipping. Statistic analysis on modifications in speech due to pedagogic treatment (the accent method. Acoustic evaluation of practical dysphonia earlier than and after voice therapy (Accent method). Chant therapy for treating vocal fatigue amongst public school teachers: a preliminary examine. Understanding Voice Problems: A Physiological Perspective for Diagnosis and Treatment. Outcome of resonant voice remedy for feminine teachers with voice issues: perceptual, physiological, acoustic, aerodynamic and useful measurements. Voice training and remedy with a semi-occluded vocal tract: rationale and scientific underpinnings. The resonance tube methodology in voice remedy: description and sensible implications. The effectiveness of group therapy for students with mild voice disorders: a controlled medical trial. Influence of physique posture and lung volume on subglottal pressure management throughout singing. Principles and strategies of manual therapy: utility in the administration of dysphonia. In contrast to the paranasal sinuses and recesses of the tympanic cavity, however, the mucosal surfaces of the larynx, trachea and esophagus are readily accessible for examination within the workplace setting. In this chapter, the upper aerodigestive tract will be divided into three anatomical sections: larynx, trachea and esophagus. The significance of historical past and physical examination is emphasised; interpretation of imaging studies is commonly useless or misleading with out this information. While understandably alarming for potential occult carcinoma inflicting this increased sign, 15 of the 17 patients had been found to have "false-positive" research; the improved uptake was felt to reflect the increased metabolic exercise of the compensating vocal fold musculature and never from occult laryngeal most cancers. Although this is a dramatic example, it suffices to say that sufferers are higher served by the wedding of scientific and radiographic information. Other common makes use of for laryngeal imaging embrace the evaluation of vocal-fold paralysis with out an apparent precipitating trigger, acute external trauma as properly as in the assessment of airway stenosis. Hirano and colleagues dissected 20 larynges and found that the majority, if not all, had some asymmetrical options. Structural Abnormalities of the Larynx: Benign Masses, Trauma, and Stenosis Benign Masses. Whereas the inner laryngocele usually presents with hoarseness, sense of fullness, or throat clearing, an external laryngocele will manifest as a variable neck mass with or with out the opposite laryngeal symptoms of an internal laryngocele. Small, internal laryngoceles may be managed endoscopically with marsupialization9,10 (removal of the false vocal fold to open the sac into the aditus of the larynx). The relative lucency within the anterior portion of each false vocal fold represents the laryngeal ventricle. The pyriform sinus approaches its apex at the stage of the true vocal folds below. The cartilages seen simply posterolateral to the cricoid are the inferior cornua of the thyroid cartilage. The recurrent laryngeal nerve lies in shut proximity to this cricothyroid articulation on both aspect. The regular, undistended pyriform sinuses are seen bilaterally lateral to the aryepiglottic folds and supraglottic buildings. The external components of the laryngocele are emerging laterally through the left facet of the thyrohyoid membrane. The administration of airway stenosis represents one of the nice ongoing challenges in laryngology. In different words, it may be unwise to traverse a 5-mm airway with a 4-mm endoscope in the outpatient setting except completely necessary. In one evaluation from the Massachusetts General Hospital,thirteen many alternative configurations were noted in a collection of idiopathic 3845 laryngeal stenoses; these configurations included an hourglass-shaped airway in 53% of sufferers and an eccentric airway within the other 47% of sufferers. The superior and inferior margins of the stenotic space have been smooth in 60% of patients and irregular and lobulated within the the rest. Note the airway obstruction above the extent of the body of the arytenoid cartilage, the presence of the hyoid bone, and air in the pyriform sinus. Carretta and colleagues supplied an fascinating comparability between endoscopic and radiographic evaluation of airway stenosis in their analysis of postintubation laryngeal and laryngotracheal stenosis. Because this study was small and limited to patients present process open surgical procedure, caution have to be taken before making use of these findings to patients with airway problems generally. Three-dimensional (3-D) reconstruction of airway imaging is an exciting frontier in laryngology. Patients complain of unilateral throat pain, hoarseness, and in some ipsilateral otalgia. The differential prognosis to consider in these patients is acute vagal neuropathy from intubation or damage from the operative procedure itself. The most common appearance of arytenoid damage is of anterior and medial dislocation leading to ipsilateral vocal fold adduction. Delay in appropriate analysis may end up in scarring of the adjacent vocal fold and everlasting joint disruption with subsequent vocal fold dysfunction. Mechanical disruption of the cricothyroid articulation, additionally resulting in pain and hoarseness, has been described along with its imaging features. It is estimated that one in 23,000 emergency room admissions consists of the analysis of blunt or penetrating laryngeal trauma. If the injured affected person is in distress, there will not be time for radiographic imaging. A surgical airway or, in some cases, intubation precedes imaging; as soon as the airway is secure, the surgeons may discover the neck, including the laryngeal framework, or cease the process at that time and obtain the radiographic investigations. Airway administration is determined by sensible, conservative medical evaluation; a modest laryngeal damage in an in any other case compromised patient, for instance, systemic harm, anticipated tough intubation, and/or mental status modifications, could mandate an pressing surgical airway, in distinction to some severe isolated laryngeal accidents in a slender, cooperative patient in whom immediate radiographic investigation prior to surgery is appropriate. Characteristics of cartilaginous fractures embody disruption of the continuity of the thyroid alae or the cricoid ring. Few scholarly comparisons have been made to element the respective roles of laryngoscopy and radiographic imaging; as noted 3848 above, the medical situation could impact the roles significantly. Many fractures lead to extra-visceral air which represents air escaping into the delicate tissues of the neck. A giant quantity of sentimental tissue air in the setting of a subglottic airway damage might, nonetheless, observe superiorly and obscure indicators of a extra refined concurrent supraglottic or pharyngeal perforation. Recently, ultrasound has been studied in the laboratory as a potential tool for the assessment of laryngeal damage following trauma. A small study investigating the usefulness of ultrasound in pediatric trauma patients, demonstrated feasibility of this investigative device in the emergency department. Squamous cell carcinoma of the larynx continues to be a significant supply of morbidity and mortality. Laryngeal cancer has, remarkably, turn into more deadly for the rationale that early Nineteen Nineties, the only solid neoplasm during which the five-year survival price has fallen up to now 10 years. Radiography is used in the care of laryngeal most cancers patients for 2 main goals: initial staging and subsequent tumor surveillance. Of these, the bulk come up in the glottis, with the majority of the remainder being supraglottic in origin. Many of the medical staging parameters are associated to the extent of regional subsite involvement of the first neoplasm and their metastases. As such, cautious attention to imaging to determine exact extent of neoplastic unfold can have a profound impression on staging and thus therapy and prognosis Table 94-1). This is very true in neoplasms of the larynx by which disease eradication is simply a part of the goal of remedy at the side of an try and preserve phonation and airway safety with a larynx preserving procedure. T2 also describes a tumor that affects the movement of the vocal fold, without paralyzing the vocal fold.
Tags: 20 mg tadora buy fast delivery, tadora 20 mg order without a prescription, discount tadora 20 mg, order tadora 20 mg with amex, trusted tadora 20 mg, order tadora 20 mg amex, generic tadora 20 mg, discount 20 mg tadora, 20 mg tadora order overnight delivery, tadora 20 mg buy with mastercard, tadora 20 mg order line, order 20 mg tadora with visa, cheap 20 mg tadora mastercard, buy tadora 20 mg visa, 20 mg tadora generic, buy generic tadora 20 mg online
9 of 10
Votes: 121 votes
Total customer reviews: 121
Customer Reviews
Ben, 23 years: Pollei at al conducted a multicenter retrospective evaluate of a single-institutions experience 4167 with transoral surgical procedure from 1994-2012. The objective of airway analysis is to define the pathology of the mass through biopsy, determine the extent of airway obstruction, and evaluate for other possible lesions.
Kerth, 31 years: During inspiration, 16 of 17 sufferers had normal configuration; on expiration, all of the patients demonstrated some extent of abnormality, the "frown signal" being the most common, seen in 9 of 17 patients. A youngster in acute airway misery clearly mandates emergent evaluation in the operating room.
Tizgar, 36 years: In his suspension system, Killian used the bladelike laryngoscopes designed by Kirstein to cut back strain on the higher incisors. Indeed, the majority (~75%) of exposures occur within the storage areas for such cleansing liquids, particularly the kitchen and toilet.
Kent, 25 years: Table 88-4 Reflux Symptom Index Within the Last Month, How Did the Following Problems Affect You This development of genetic events was first described in colorectal neoplasmigenesis and an identical mannequin has since been established for head and neck most cancers.
