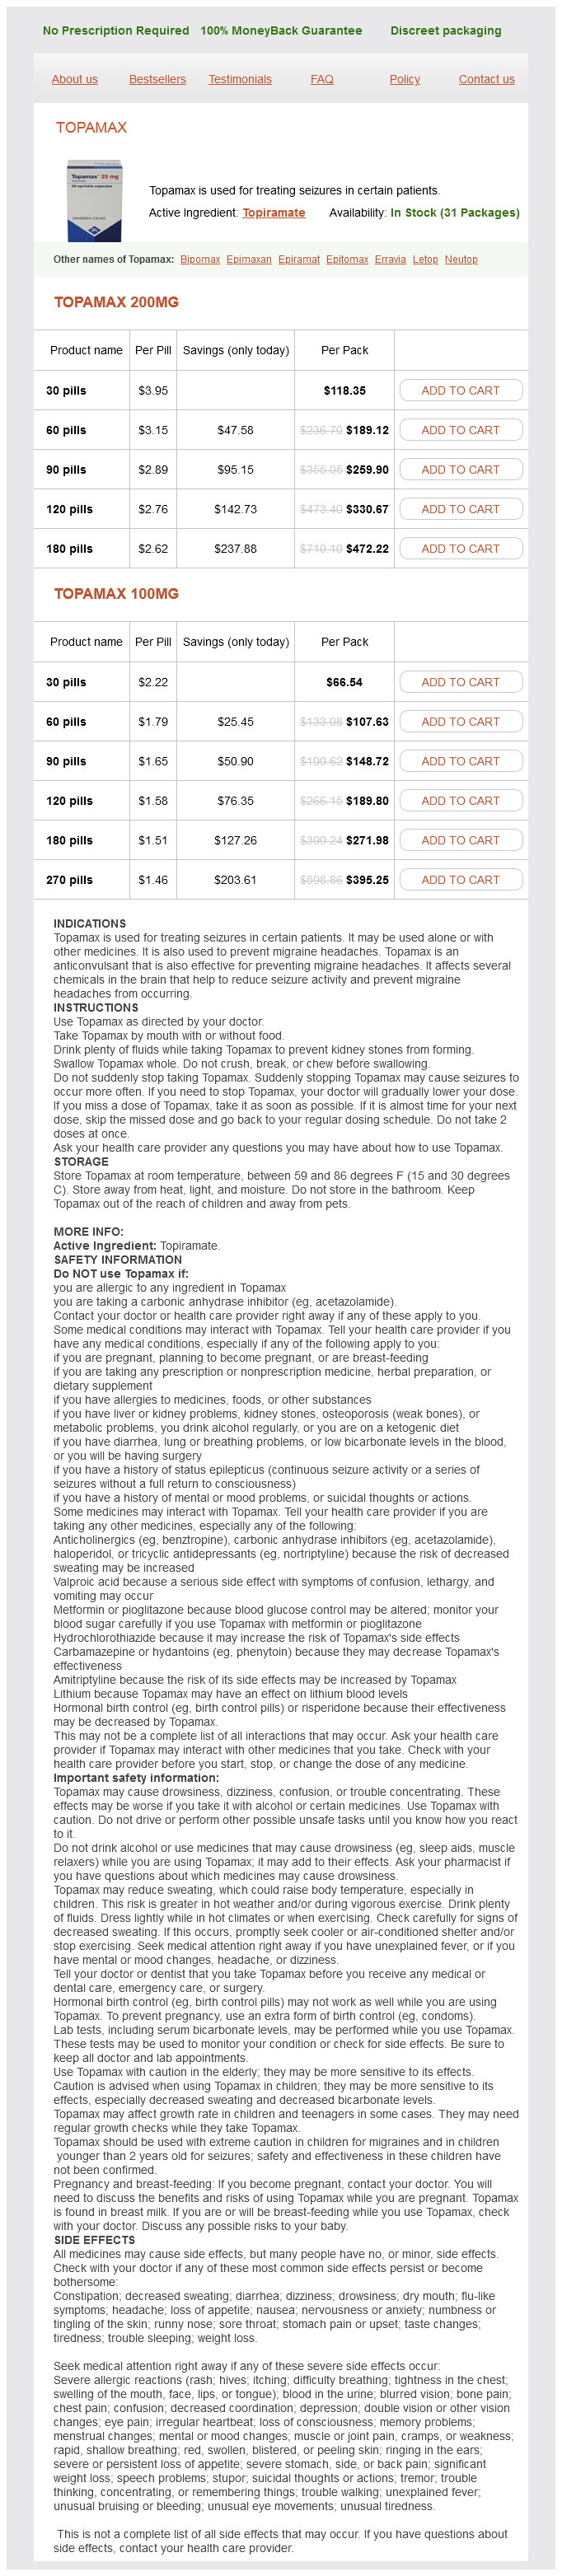
Topamax 200mg
- 30 pills - $118.35
- 60 pills - $189.12
- 90 pills - $259.90
- 120 pills - $330.67
- 180 pills - $472.22
Topamax 100mg
- 30 pills - $66.54
- 60 pills - $107.63
- 90 pills - $148.72
- 120 pills - $189.80
- 180 pills - $271.98
- 270 pills - $395.25
Topamax dosages: 200 mg, 100 mg
Topamax packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills
In stock: 528
Only $1,56 per item
Description
Risk Factors History of earlier amputation symptoms tuberculosis topamax 200 mg order without prescription, peripheral vascular disease medications covered by medi cal 200 mg topamax order free shipping, and peripheral neuropathy has also been identified as significant threat components for extreme foot an infection medicine 014 buy 200 mg topamax otc. Renal insufficiency and a history of walking barefoot are additionally risk elements for growth of infections medicine vials purchase topamax 200 mg free shipping. Evaluation History the analysis of a patient with a potential diabetic foot infection begins with the historical past. A complete diabetic history is important and should embrace the period of illness, earlier problems or ulcerations, insulin dependence, and the evaluation of current glycemic control. Past medical history should assess for the presence of diabetes associated problems or comorbidities similar to liver, renal, heart problems, retinopathy and neuropathy. Information on current drugs, together with present or previous antibiotics also wants to be obtained. Social historical past should also be obtained and embody alcohol or tobacco use, activity level, train and food plan. The limb and foot, is examined to search for proximal spread of an infection or by way of lymphatic channels to regional lymph nodes. Assessment of the neurovascular status of the limb is an important component of the bodily examination. Following the above assessments, evaluate the wound by first removing any necrotic material or callous. Finally, regardless of the location of the wound, the plantar arch must be palpated for the presence of ache or fullness, which can point out a deep plantar space abscess. Imaging Radiographs the initial imaging modality must be plain movie radiography. It can provide information regarding the delicate tissue as well as the underlying osseous constructions, and any deformity or foreign bodies. The classical triad of osteomyelitis consists of periosteal response, osteolysis, and bone destruction. Hypothermia (<36�C) or fever (38�C), hypotension, tachycardia, and tachypnea counsel extreme an infection and sepsis. However, Laboratory Evaluation Serum chemistry analysis and hematological testing ought to at all times be performed. Recently, procalcitonin has become a newly identified inflammatory marker with some diagnostic utility in diabetic foot infections. Empiric antibiotic routine ought to be chosen on the premise of the severity of the infection and the doubtless causative organism. Intravenous therapy is most popular for all severe, and some reasonable infections no less than initially. When the affected person is systemically properly and tradition outcomes turn out to be out there, oral agents can then be initiated. Many diabetic foot infections present with an obvious need for surgical intervention, ranging from easy debridement to emergent amputation in the setting of important limb ischemia or necrotizing fasciitis. It is the most common type of inflammatory arthritis, affecting 1% of males and 3% of women. Diagnostic criteria as defined by the American Rheumatism Association, include morning stiffness, swelling, nodules, optimistic laboratory checks and radiological findings. Principles of Treatment the goals of therapy are the control of ache and preservation of motion. A multidisciplinary approach is necessary involving rheumatologists, physicians, occupational therapists and orthopedic surgeons. Medications for particular person patients are decided by the rheumatologist taking a quantity of components into consideration. For planning treatment, weight-bearing radiographs are necessary to evaluate any deformity. Alignment of the forefoot to the hindfoot is estimated by a line drawn through the longitudinal axis of the 1st metatarsal, which passes by way of the long axis of the talus. A dorsoplantar view of the foot could present destruction of the forefoot and calcaneocuboid joint. Surgical therapy contains preservation of joints by radioactive isotope synovectomy, surgical synovectomy, axial correction and arthrodesis, resection arthroplasty or joint replacement. Orthotics Numerous research have proven a significant discount in ache and disability by custom designed orthotics and really helpful their early use. Correction of the forefoot should permit stable realignment, improve the patients strolling and permit easier fitting of sneakers. Arthrodesis of the first ray maintains alignment and protects the hallux and lesser metatarsophalangeal joints from recurrent deformity and subsequent metatarsalgia. For the lesser toes, the resection of the metatarsal head and base of proximal phalanx is advocated. A smooth arc of resection of the lesser metatarsal heads with meticulous debridement of the bone and synovium is really helpful. Hindfoot Early synovitis is greatest handled by immobilization and bodily treatment. If this fails operative synovectomy to avoid rupture and instability of the tendons is necessary. Arthrodesis: the talonavicular joint is essentially the most commonly involved and isolated arthrodesis may be indicated if the hindfoot is versatile or neutral. Triple arthrodesis is indicated in a hard and fast valgus hindfoot with forefoot in supination and abduction. The subtalar joint is often mounted first after which the talonavicular and calcaneocuboid joints are fixed. The advantages embody a variety of movement, which allows strolling with decreased stress on adjacent joints. A Acknowledgments I am grateful to the following colleagues for their help in the preparation of this chapter: Mr M Carter, Orthotist for his useful help and advice; Mr Rahul Dalal and Mr David Leonard, Medical Students for his or her assist in preparing the text and illustrations. The American Rheumatism Association 1987 revised criteria for classification of rheumatoid arthritis. Arthrodesis of the first metatarsophalangeal joint for hallux valgus in rheumatoid arthritis. Keller arthroplasty in combination with resection arthroplasty of the lesser metatarsophalangeal joints in rheumatoid arthritis. Rheumatoid forefoot deformity: a comparability research of two functional strategies of reconstruction. Complications in surgery of the foot and ankle in sufferers with rheumatoid arthritis. Surgery of the rheumatoid forefoot with particular reference to the plantar strategy. Pedodynographic measurements after forefoot reconstruction in rheumatoid arthritis sufferers. How do varied operative procedures on the forefoot affect the rheumatoid foot. Management of the rheumatoid hindfoot with particular reference to talonavicular arthrodesis. Radiographic evaluation of rheumatoid arthritis and related situations by commonplace reference films. Also the variety of specialist rheumatologists to cater to the patient load is grossly insufficient resulting in inadequate care. The common consciousness in regards to the therapy modalities for these deformities is kind of low within the society at massive as also medical profession. Hence, these sufferers current late with severe deformities where salvage of joint is often not possible and arthrodesis and/or resection arthroplasties remain the one viable choice. Rheumatoid foot deformities are common in Indian sufferers with incidence rates corresponding to the printed western information. It is postulated that as a result of unhindered resistance to medial deviation as prevalent in most footwear which the overall inhabitants put on, medial deviation is more pronounced. Custom-made accommodative footwear are suggested for sufferers with these deformations taking care to offload the areas of extreme plantar pressures and callosities formation.
Veld Grape (Cissus Quadrangularis). Topamax.
- Are there safety concerns?
- Obesity and weight loss, diabetes, metabolic syndrome, and high cholesterol, bone fractures, osteoporosis, scurvy, cancer, upset stomach, hemorrhoids, stomach ulcer, menstrual discomfort, asthma, malaria, pain, and body building.
- Dosing considerations for Cissus Quadrangularis.
- How does Cissus Quadrangularis work?
- What is Cissus Quadrangularis?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97110
Etiopathogenesis Staphylococcus aureus is the most typical micro organism causing infection (up to 60%) followed by gramnegative organisms medicine expiration dates topamax 100 mg with amex. Propionibacterium acnes medicine zithromax discount topamax 200 mg with mastercard, an organism of low virulence symptoms at 4 weeks pregnant best 100 mg topamax, has been reported as inflicting delayed an infection in spinal instrumentation treatment synonym purchase 200 mg topamax visa. Hence, absolutely the value of this take a look at in the initial postoperative period is uncertain. Staining, and culture and sensitivity of the discharge in an open wound may identify the micro organism responsible for the an infection and its sensitivity to antibiotics. However, in many instances, the tradition could show no growth because the patient is already on antibiotics and repeated and prolonged cultures may be required to determine low virulence organisms. It must be emphasized that the fabric must be collected with utmost care to stop contamination by skin flora. Headache and neck stiffness may also be present either as a result of erector spinae spasm or dural irritation. Late infections normally present with a discharging sinus or swelling on the operative site. Higher values of rise are seen in open versus minimally invasive procedures and double versus single degree surgical procedures Source:Dataadaptedfromreference21. PostoPerative sPinal infection Biopsy by percutaneous discectomy approach has been advised which permits for samples to be collected directly from the affected house. The completely different yield of constructive cultures in numerous collection is talked about in Table 3. Xrays are normally normal in the early section of postoperative spinal an infection as bone demineralization and collapse has not but set in. Plain radiography has a reported sensitivity of 82%, specificity of 57% and accuracy of 73%18 and may be confused with degenerative changes. In the cervical spine a big prevertebral collection may be seen as an elevated softtissue shadow with shifting of the trachea. Depending on the virulence of the organism and progression of illness process radiological changes may seem 2�3 weeks later. Appearance of disc space narrowing and subchondral radiolucency may take 8�10 weeks. Healing is heralded by increased density of the endplates and sclerosis of bone because of reactive bone formation. Xrays can also assist in identifying implant loosening and retained international body in the wound. Computed tomography is useful to delineate fluid assortment, presence of air and early endplate destruction. Several findings assist to differentiate postopera tive adjustments from infection within the postoperative period. As expected higher rises are seen in fusion surgeries however the sample of rise and fall stays the identical Source:Dataadaptedfromreference22. Skin preparation and draping must be adequate and extend nicely beyond the deliberate incision area in order that sudden adjustments requiring extension of surgical suite will be in a prepared zone. Softtissue trauma should be minimal, muscle dissection subperiosteal with minimal use of cautery. The wound should be regularly irrigated to wash out bone mud and particulate matter and periodic launch of retraction must be carried out. Hemostasis have to be achieved previous to closure as collected blood is an efficient tradition medium for organisms to grow. The wound have to be closed in layers with meticulous closure of the fascial layer and inverted sutures being used for the subcutaneous layer. Various tracers have been used in the radionuclide imaging of postoperative spinal infection. These embody technetium (Tc)99mmethylene diphosphonate, gallium67 and indium111leukocyte scan. Opinion varies relating to optimal length; these medication are to be continued but the vast majority favor between three doses and 5 doses. In instances of instrumentation, we invariably continue injectable antibiotics until drain elimination is completed. Postoperatively, besides antibiotics, attention have to be paid to sufficient nutrition, periodic place change (in bedridden patients) and vigorous chest and limb physiotherapy. Early mobi lization must be encouraged and a high index of suspicion should all the time be maintained to look for any postoperative complication. Superficial dressing and suboptimal antibiotics are inadequate and to be condemned, due to risks of meningitis, loss of structural integrity of the spinal column, septicemia and demise. The objectives of the remedy are, due to this fact, infection eradication, good wound closure, and maintaining spinal stability, all without compromising the purpose of the initial surgical procedure. Various therapy decisions are current starting from antibiotics alone, to wound explorations and secondary suturing, to radical debridements with or with out fixation and hardware removal, to closed suction inflowoutflow irrigation methods. Likewise they classified patients of being in three classes: (1) with normal systemic defenses, (2) with local or multiple systemic ailments (including cigarette smoking) and (3) immunocompromised (or severely malnourished). They advocated easy debridement and irrigation and closure over suction drainage for the primary group, multiple radical debridements (up to 3) with closed inflowoutflow suction irrigation techniques for the second group and multiple radical debridements (up to 6) with delayed flap closure for the third group. Superficial soft-tissue collections (above the lumbodorsal fascia) can either be handled with common dressing and urgent the wound to categorical all assortment with focused antibiotic therapy. If so deemed match the wound could be left open and closed later in a secondary method. Epidural abscess inflicting mass impact on the spinal cord might present with neurological worsening and is a surgical emergency. The strategy, anterior or posterior, is determined by the loca tion of the abscess with respect to the spinal wire. The prognosis for restoration is directly associated to the diploma and length of paralysis. Anterior decompression could necessitate vertebral debridement, anterior graft placement and likewise posterior reconstruction. Longsegment abscesses which might be still liquid can be treated by a laminotomy at the inferior finish of the abscess and irrigation of the epidural area with a fantastic silicon catheter (like an exterior ventricular drain). Intraoperative maneuvers like primary dural repair, application of Onlay fat or gelfoam or employment of fibrin sealants must be done. Postoperative spondylodiskitis is probably the most recalcitrant of all these infections requiring lengthy period of antibiotic therapy due to poor osseous penetration of the antibiotics. The majority of sufferers could be successfully treated with organismspecific antibiotics and spinal immobilization. Culture negative cases must be treated as presumed Grampositive infection because essentially the most commonly recognized micro organism is Staphylococcus. They have reported passable results with this in their sequence of 17 patients of postoperative diskitis. Operative intervention should be accomplished in sufferers who fail to respond to nonoperative therapy or within the presence of neurologic worsening. The patient should not be explored in a half hearted style in the lateral place underneath native anesthesia. Painting and draping should be accomplished in an aseptic manner and care should be taken to keep away from contamination of the wound by different pores and skin flora. All layers must be fully opened up sequentially after debriding every aircraft successively. All absorbable sutures must be taken out and devitalized tissues have to be radically debrided. A particular search must be made for international bodies like retained gauze pieces or bone wax, and these have to be removed. Bony fragments, grafts loosened during lavage and those engulfed in purulent materials should be eliminated. All surfaces of implants 2456 textbook of orthoPedics and trauma their cases with an infection settled down with a single therapy. During this entire process, neural tissue must be handled fastidiously to forestall secondary damage.
Specifications/Details
Histological research suggest three phases of rotator cuff therapeutic on to the bone after repair symptoms questionnaire buy 200 mg topamax with amex. Finally symptoms internal bleeding 200 mg topamax generic fast delivery, type three collagen is changed by kind 1 collagen and cuff heals on to the footprint with scar tissue formation treatment yeast infection home order 200 mg topamax with amex. Local icepacks or cryotherapy are fairly helpful in decreasing ache and inflammation and decrease the utilization of analgesics medicine 10 day 2 times a day chart topamax 200 mg generic on-line. Phase 2 (2�4 months): Initiate active assisted progressing to achievement of full lively vary of movement. However, the anti-inflammatory and anti-angiogenesis effect of local steroid could be counter-productive in cuff healing course of. Recent advances in cuff remedy: Current research is aimed to facilitate therapeutic process after cuff repair, especially in old degenerative tears. Constant analysis on use of progress components (bone morphogenetic protein, fibroblast progress issue, platelet derived growth factor, reworking progress factor), stem cells augmentation of tendon healing and rotator cuff repair, or gene remedy is underway. Scaffold not only mechanically reinforce faulty part of the tendon, but in addition stimulates intrinsic healing potential of tendon. Currently, scaffolds are derived from mammalian extracellular matrix (human, porcine, bovine and equine), artificial copolymers (Poly-L-Lactide, Poly carbonate poly, polyurethane urea) and combinations thereof. More than 9 mammalian scaffolds are currently out there in market such as Graft Jacket (porcine dermis, wright medicals), Arthroflex (Human dermis, Arthrex), Tissue Mend (Bovine fetal dermis, Stryker), etc. Partial Thickness Cuff Tear Partial thickness cuff tears are quite frequent in presentation. Subacromial (for bursal facet tear) or intra-articular (articular aspect tear) injection of steroid is debatable. Stiffness of shoulder Infection Non-healing and rerupture of repaired tendon Anchor loosening and migration Deltoid dehiscence Injury to axillary nerve Reflex sympathetic dystrophy. Role of local steroids in cuff pathology: Intra-articular or subacromial steroid injection has been used to provide pain aid in rotator cuff illness since lengthy. It is quite regularly used in adhesive capsulitis RotatoR Cuff teaRs lowering irritation. After the affected person is pain free or has less pain, rehabilitation of cuff and scapular muscular tissues and capsular tightness is targeted. However, there are concerns that steroid can damage the collagen fibers of intact cuff, hinder the traditional reparative process and may additional damage the degenerate cuff. Also, as quickly as the affected person is comparatively ache free, he may overuse his shoulder stressing the traditional and broken fibers leading to additional progression of tear. Conservative treatment lasts for 6�18 months and most sufferers respond depending upon measurement and site of tear. If tear entails greater than 50% of thickness, it could want in situ restore or restore after completing the tear. Rotator cuff tears in asymptomatic people: a clinical and ultrasonographic screening research. The demographic and morphological features of rotator cuff illness: a comparison of asymptomatic and symptomatic shoulders. Tears of the rotator cuff of the shoulder associated with pathological changes within the acromion: a examine in cadavera. The effects of overuse mixed with intrinsic or extrinsic alterations in an animal mannequin of rotator cuff tendinosis. Sonography of the shoulder in sufferers with tears of the rotator cuff: accuracy and worth for selecting surgical options. A randomized medical trial evaluating open to arthroscopic acromioplasty with mini-open rotator cuff restore for full-thickness rotator cuff tears: disease-specific high quality of life consequence at a median 2-year followup. Arthroscopic vs mini-open rotator cuff restore: a top quality of life impairment study. All-arthroscopic versus mini-open rotator cuff restore: a long-term retrospective end result comparison. The role of platelet-rich plasma in arthroscopic rotator cuff repair: a systematic review with quantitative synthesis. Platelet-rich plasma for arthroscopic repair of enormous to massive rotator cuff tears: a randomized, singleblind, parallel-group trial. Are platelet-rich merchandise essential during the arthroscopic repair of full-thickness rotator cuff tears: a meta-analysis. The affect of arm and shoulder place on the bear-hug, belly-press, and lift-off checks: an electromyographic research. Humeral insertion of the supraspinatus and infraspinatus: new anatomical findings regarding the footprint of the rotator cuff. The bursal and articular sides of the supraspinatus tendon have a unique compressive stiffness. Histologic and biomechanical characteristics of the supraspinatus tendon: reference to rotator cuff tearing. The affect of variations of the coracoacromial arch on the event of rotator cuff tears. The relationship between acromial morphology and conservative remedy of sufferers with impingement syndrome. Correlation of acromial morphology with impingement syndrome and rotator cuff tears. Pathogenesis of partial tear of the rotator cuff: a scientific and pathologic research. Complete rupture of the supraspinatus tendon: operative therapy with report of two profitable circumstances. Overuse activity injures the supraspinatus tendon in an animal mannequin: a histologic and biomechanical examine. Overexpression of antioxidant enzyme peroxiredoxin 5 protects human tendon cells towards apoptosis and lack of cellular perform throughout oxidative stress. Debridement of partial-thickness tears of the rotator cuff without acromioplasty: long-term follow-up and evaluate of the literature. Arthroscopic rotator cuff debridement without decompression for the treatment of tendinosis. Natural history of asymptomatic rotator cuff tears: a longitudinal analysis of asymptomatic tears detected sonographically. Intraoperative assessment of rotator cuff vascularity utilizing laser doppler flowmetry. Contrast-enhanced ultrasound characterization of the vascularity of the rotator cuff tendon: ageand activity-related adjustments in the intact asymptomatic rotator cuff. Anterior acromioplasty for the chronic impingement syndrome within the shoulder: a preliminary report. Factors stopping downward dislocation of the adducted shoulder joint: an electromyographic and morphological examine. Effect of suprascauular and axillary nerve blocks on muscle force in upper extremity. A stepwise approach to arthroscopic rotator cuff repair primarily based on biomechanical principles. The effect of coracoacromial ligament excision and acromioplasty on superior and anterosuperior glenohumeral stability. The combined dynamic and static contributions to subacromial impingement: a biomechanical analysis. Shoulder impingement syndrome: prognosis, radiographic analysis, and treatment with a modified Neer acromioplasty. Correlation of age, acromial morphology, and rotator cuff tear pathology identified by ultrasound in asymptomatic sufferers. Coracoacromial ligament: in situ load and viscoelastic properties in rotator cuff illness. The function of the coracoacromial ligament within the impingement syndrome: a clinical, radiological and histological research. Ruptures of the supraspinatus tendon: the importance of distally pointing acromioclavicular osteophytes. The acromion: morphologic condition and age-related changes: a examine of 420 scapulas. Impingement of the deep floor of the supraspinatus tendon on the posterosuperior glenoid rim: an arthroscopic study.
Syndromes
- Encephalopathy
- Respiratory infections, including pneumonia, acute bronchitis, whooping cough, croup, and others
- 24-hour urine collection
- Keep activities such as taking a bath, brushing teeth, reading stories, saying prayers, and so forth in the same order every night.
- 8 years after you are diagnosed with severe disease, or when most of, or the entire, large intestine is involved
- Raise the affected area to reduce swelling
Related Products
Additional information:
Summary Endoscopic discectomy combines the benefits of both microdiscectomy and endoscopic procedure medicine 2 200 mg topamax. The reduced dimension of access route minimizes muscular trauma and postoperative pain; this considerably facilitates the fast resumption of physical activities and quicker return to work 4 medications walgreens topamax 100 mg buy generic on line. Procedure may be accomplished as day care process and sufferers appreciate aesthetic scar treatment dry macular degeneration discount topamax 100 mg line. Total Disc Replacement Lumbar disc degeneration is a major cause of back pain with large economical consequences symptoms quitting weed topamax 100 mg generic on line. When all treatments have failed, fusion can be indicated, and a great end result could be anticipated. This ends in a floating middle of rotation, allowing angular motion and translation. To encourage bony ingrowth, the tip plates are lined with plasmasprayed titanium and electrochemically coated with calcium phosphate. This has been proven in animal research to end in 48% osseointegration, compared with the 10�30% ingrowth seen in successful hip and knee replacement prostheses. This ends in a ball-and-socket joint that limits translation and allows rotation. A central keel on the top plates and plasma-sprayed titanium coating enable for bony fixation and ingrowth. On the lateral view, the anterior and posterior vertebral physique cortices ought to be easily identifiable. Standard "retroperitoneal or transperitoneal" approaches to the spine are then carried out. Once the anterior disc has been uncovered and the appropriate degree of dissection verified, the midpoint of the disc area is marked underneath fluoroscopic imaging. A small curved curette ought to at all times be placed alongside the posterior ridge of each vertebral our bodies. This palpation will assist within the release of the posterior longitudinal ligament and elimination of extruded disc fragments and posterior inflammatory granulation tissue when indicated. Depending on the sort of end plate configuration in addition to surgeon desire, the choice for a keeled or spiked implant is then made. The distractor or sizer instrument is then placed into the disc area, and the disc space is concurrently distracted and measured by turning the handle of this instrument. If a keeled implant is chosen, the appropriate chisel trial is placed fastidiously in the midline of the disc area, and chiseling is then carried out. First, though an indirect insertion is to be performed, vascular mobilization roughly 2 cm previous the midline of the vertebral interspace is beneficial. Second, the radiolucent trial is placed on the disc area before discectomy, and a small notch is made on the superior vertebra, thereby defining the insertional angle for the ultimate prosthesis. If in any respect possible, full release of the anterior annulus should be carried out to enable for correct balancing of the backbone to avoid causing iatrogenic scoliosis. Case-1 A 24-year girl with extreme mechanical again pain with sitting intolerance confirmed by diagnostic discography. Case-2 A 40-year-old lady complains extreme mechanical again pain not responding to 6 months of conservative remedy. Complications14 � Device-related problems embody implant subsidence, loosening, migration or extrusion, malposition, and materials put on. Future Nucleus Replacement Total disc replacement and nucleus alternative are part of disc arthroplasty, which is meant to provide a substitute for fusion for sufferers with discogenic back pain and sciatica. It is intended to obtain this by utilizing the tip plate geometry for correct placement. Uncontained � Hydrogel adhesive (examples: NuCore, BioDisc) � Nonhydrogel nonadhesive (example: Sinux) 2. The implant-bone interface and the fabric stability are of explicit interest because of the different elasticity modules between bone and implant and also due to the biomechanical dorsal strains, particularly relating to shear forces. The design of the gadget influences the load of the implant-bone interface and the load of the implant itself. A stability between the extent of mobility of the implant to avoid an overload of the bone-implant interface and an effective stabilization of the spinal motion section must be found. The reason for ache is the irregular high quality of motion that could be in irregular course or in an increased diploma of translation, thus distributing abnormal loads throughout the disc house. A dynamic stabilization system either restricts movement to a zone the place normal or near regular loading � Facet joints which are absent, fractured or severely degenerated � Obesity, as defined by a physique mass index of larger than 35 � Active systemic or local infection within the area of the deliberate surgical procedure � Incompetent annulus. Posterior Dynamic Stabilization the essential precept for dorsal dynamic stabilization is mainly based mostly on screw fixation in adjoining pedicles and vertebral bodies. Because the ventral sections of the backbone carry out the segmental switch of axial load as a lot as about 80%, the replacement seems to be of much less importance. In contrast to this, primarily dorsal procedures with the option of function-preserving stabilization could additionally be indicated in circumstances of dorsal pathologies of the backbone. Furthermore, a dorsal dynamic stabilization is particularly useful in older sufferers with a better price of morbidity with the anterior strategy or decreased bone-loading capability. Posterior dynamic stabilization (Table 3): � Screws and connectors � Interspinous system. Case-3 A 22-year football participant with severe mechanical low back pain exhibits L4-5, L4-3, L3-2 disc degeneration. Mobile Screw Parts the heads of screws are mobile with respect to the screw piston by way of a special mechanism. For instance, the "Cosmic Posterior Dynamic System" the thread of the screw is connected by a hinge, for a permanent movable connection between screw and rod. The full system allows axial load distribution and prevents any rotation and translation. Mobile Connectors In 1994, "Dynesys" was implanted for the first time as a dorsal dynamic instrumentation, which has cords of polyethylene terephthalate with a tube made from polycarbonate urethane slid over them and stuck to two adjacent pedicle screws with nuts. The screws are made from a titanium alloy and are coated with hydroxyapatite if required. Coflex is a functionally dynamic interspinous implant for levels L1-L5, which is compressible in extension, permits flexion, and has slight rotational stabilization. The implant wings can be crimped to achieve adequate fixation to the spinous processes. The spacer is suited to a limitation of the extension and flexion, without influence on rotation and lateral bending. The first part is implanted subsequent to and underneath the spinous process, and the second part is positioned on the other side of the spinous process and is then attached to the first. Radiographic confirmation of no angular or translator instability of the backbone at index or adjoining levels (instability as outlined by White and Panjabi: sagittal airplane translation >4. Neurogenic claudication as defined by leg/buttocks or groin ache that can be relieved by flexion similar to sitting in a chair. Contraindications � More than two vertebral ranges requiring surgical decompression � Prior fusion, implantation of a total disc replacement, complete laminectomy � Radiographically compromised vertebral bodies. The system consists of two stems which might be mounted within the pedicles and concave discs linked to them, which allow two spherical elements (one on each side) to move on their surfaces. The two spherical components are connected to the stems in the pedicles of the adjacent vertebra. Because the implant is completely made of metallic, there are metal-metal articulating surfaces. Facet Arthroplasty the function-retaining replacement of the side joints must be considered critically because the arthritis of these joints usually outcomes from a degeneration of the intervertebral disc. In elderly sufferers with a extreme narrowed spinal canal, the elimination of side joints could be essential. It have to be determined whether or not these sufferers would benefit from stabilization with motion preservation or rigid stabilization. Minimal Access Robotic-Assisted Spine Surgery Pedicle screws are the muse of spinal fixation and may afford multidimensional control and supply substantial rigidity to facilitate fusion. The need for improved accuracy and consistency in pedicle screw placement has led to the development of various new techniques, including computer-navigated and robotic-assisted spine surgical procedure.
Usage: p.o.
This osteotomy is contraindicated earlier than 15 years of age because loss of angulation occurs during development interval medications prescribed for depression topamax 200 mg buy lowest price. It is done in femoral neck fractures with viable head and in youngsters and adults lower than 60 years as their neck is pretty preserved medications 1 topamax 100 mg generic without prescription. In this osteotomy treatment e coli cheap topamax 100 mg without a prescription, the surfaces are brought together by displacing the proximal end of the shaft medially and abducting the limb medicine to stop vomiting 200 mg topamax order. Dunn and Hass Osteotomy Along with the osteotomy of larger trochanter resection of proximal femoral metaphysis is finished. In Slipped Femoral Epiphysis Osteotomy is indicated in persistent slipping with reasonable or extreme displacement. The level of osteotomy contains: � Subcapital region � Basilar neck region � Subtrochanteric region. High incidence of avascular necrosis and chondrolysis has been reported following the subcapital osteotomizes that area distal to the capsular attachment posteriorly and thus the blood supply is spared. The proximal finish of the distal fragment is displaced medially beneath the femoral head to affect stability. This osteotomy is now completely abandoned for the disrepute it obtained because of amount of instability and shortening. The osteotomy is finished just below the higher trochanter, the distal fragment is kidnapped 60� and stuck with a plate. Exact stage of osteotomy is of utmost significance and must be precisely on the lowermost level of fractured proximal fragment. Osteotomy under this will give inadequate help across fracture and if above, transposition is tough. Compensatory Basilar Osteotomy of Femoral Neck by Kramer, Garig and Noel It is safer osteotomy as a result of the road of osteotomy is distal to the major blood supply within the posterior retinaculum. Anteriorly the road of osteotomy is simply proximal to the base of higher trochanter in order that the abductor operate is preserved. Widest part of epiphysis in anterior and superior side, this corrects varus and retroversion part. The distal osteotomy line is minimize first, perpendicular to the femoral neck following the intertrochanteric line from proximal to distal. Second osteotomy is made with osteotome oblique and avoiding the retinacular vessels. It is fixed with Steinman pins by abducting and internally rotating the extremity. Shearing forces on the nonunion website at the second are transformed to compressive forces with valgization at the trochanteric degree Osteotomies carried on femoral neck are: � Traditional technique of closing wedge osteotomy of Martin � Technique of Fish � Technique of Dunn � Base of neck technique of Kramer, Craig and Noel. Malunited Slipped Capital Femoral Epiphysis A trochanteric osteotomy is indicated here to produce an opposite deformity by doing osteotomy through extremely vascular bone on the stage of lesser trochanter. After the bone is split, the proximal section consisting of slipped epiphysis, neck and greater trochanter assume characteristic angle of: � Abduction due to varus � External rotation because of backward displacement of epiphysis � Hyperextension due to protrusion of proximal neck anteriorly. In order to exchange the capital epiphysis within acetabulum the triple deformity of proximal phase is exaggerated by fixing the distal section, the femoral shaft in abduction, internal rotation and flexion. Closing Wedge Osteotomy of Neck by Martin Wedge is removed from the anterosuperior neck with the apex of wedge on the posteroinferior aspect. Cuneiform Subcapital Osteotomy of Femoral Neck by Fish Believed to be the only operation that restores an correct anatomic relationship between the femoral head and neck of femur and beneficial for severe slips larger than 60�. The wedge is faraway from the neck, adjoining to the epiphyseal plate, with the base anteriorly and superiorly. Reduction of epiphysis is finished by flexion, abduction, and inside rotation of the limb and fixing with 3�4 pins. The three components of deformities are corrected by keeping the distal fragment internally rotated, flexed and kidnapped. Slip of femoral head strips the periosteum from the again of femoral neck and a break of recent bones is laid down beneath it. A lateral method helps to strip the periosteum and its contained vessels and keep away from injury to the vessels. Two osteotomy cuts are made one in the lengthy axis of neck to take away the bones beak and the second at right angle to the neck to shorten it by 3�4 mm. Lesser trochanter is left undisturbed to act as a buttress medially when the varus is corrected. Deformity is corrected by abduction, inner rotation and flexion of distal fragment. Measured Biplane Intertrochanteric Osteotomy of Southwick this osteotomy is most useful when head has slipped from 30� to 70�. Then becoming a member of the 2 angles tin templates can normally 20�36� anteriorly and 45� laterally. The inferior fringe of wedge to be removed is marked as transverse mark at lesser trochanter level. The proximal fragment is stationary after bone division and the distal fragment, i. A Wagner Intertrochanteric Osteotomy It couples a medial and anteriorly based mostly wedge elimination, resulting in each varus and flexion of the distal fragment. The function is to convey posterior and lateral femoral head into the burden bearing space and to bring the sequestrum anteriorly out of contact. The rationale is to reposition the necrotic anterosuperolateral a half of the femoral head to a nonweight bearing area. To do that, the femoral head and neck segment is rotated anteriorly around its longitudinal axis by way of a transtrochanteric osteotomy, which additionally osteotomizes the higher trochanter, in order that now the weight bearing portion is the posterior articular floor. Then a transtrochanteric osteotomy 10 mm distal to the intertrochanteric line at 90� to the long axis of femoral neck is made. Second osteotomy at proper angles to the primary at the superior fringe of lesser trochanter to leave the lesser trochanter with the distal fragment. Then the osteotomy is mounted with giant screws and washers and larger trochanter is reattached to both fragments. Postoperative radiograph reveals ventral rotation osteotomy performed at trochanteric stage and stabilized with cancellous screws. We prefer to supplement this with muscle pedicle graft In Legg-Calve-Perthes Disease Along with other pelvic osteotomies, varus derotational osteotomy of Axer is rated successful. Distinct benefits embody the flexibility to obtain most coverage of the femoral head especially in older youngsters, and skill to correct excessive femoral anteversion at identical osteotomy. A small four gap plate is bent and contoured to the desired angle and a subtrochanteric osteotomy is done adopted by derotation and varus angulation of the shaft. Apart from preoperative radiographs, subcutaneous tenotomies could also be required before ample abduction can be secured in order that reduction can be achieved. Failure to scale back even after tenotomies is a contraindication for varus osteotomy. The shaft is then internally rotated and extended to appropriate the external rotation and flexion deformity. This makes it harder to right rotation and to apply the best angled plate. Original Miller strategy of excision of broad primarily based medial wedge with distal osteotomy cut transversely throughout shaft at simply above the extent of lesser trochanter. Present strategy of Miller using small half wedge minimize immediately and transposed laterally. After the varus osteotomy the large compressive pressure appearing near the edge of the acetabulum and evoking extremely high stress, turns into smaller and strikes to the center of the weight bearing floor. Osteoarthritis of the Hip Osteotomy right here aims at restoring the disturbed biomechanical equilibrium between the resistance of the tissue and the magnitude of the articular stress. It is extremely difficult to alter biologic components, the only therapeutic maneuver is to influence the mechanical part. Since the articular stress is decided by the load and by the load bearing surface, there are in precept two methods of reducing it: � Decreasing the load, i. For lowering the articular strain by growing the weight bearing surface in the case of incongruent articular surfaces two operations had been developed. In addition to the rise in the surface of the weight bearing areas, the concomitant muscle launch results in a lower of the compressive drive appearing on the joint. Bombelli believes the benefits of a proximal femoral osteotomy are mechanical and immediately related to sustaining a horizontal acetabular weight-bearing surface. Adam, Spence, Campbell, Jackson and Trueta give biologic explanation of pain relief secondary to increased vascularities of femoral head.
Tags: buy discount topamax 100 mg online, topamax 200 mg trusted, purchase topamax 100 mg with visa, topamax 100 mg discount on-line, purchase topamax 200 mg free shipping, buy discount topamax 100 mg, topamax 200 mg buy discount on line, 100 mg topamax cheap mastercard, 200 mg topamax generic fast delivery, 100 mg topamax cheap free shipping, topamax 100 mg discount overnight delivery, buy cheap topamax 200 mg online, buy topamax 200 mg, 200 mg topamax sale, generic topamax 200 mg on line, topamax 200 mg generic without a prescription
8 of 10
Votes: 54 votes
Total customer reviews: 54
Customer Reviews
Kamak, 48 years: According to Displacement the distal fragment is rotated with respect to that of proximal fragment longitudinal axis being collinear.
Sven, 54 years: However, it has been proven that talectomy alters hindfoot biomechanics, produces shortening of the limb and makes subsequent reconstructive procedures tough.
Rasul, 55 years: Care should be taken to preserve the thickness of the capsule during dissection for later closure.
