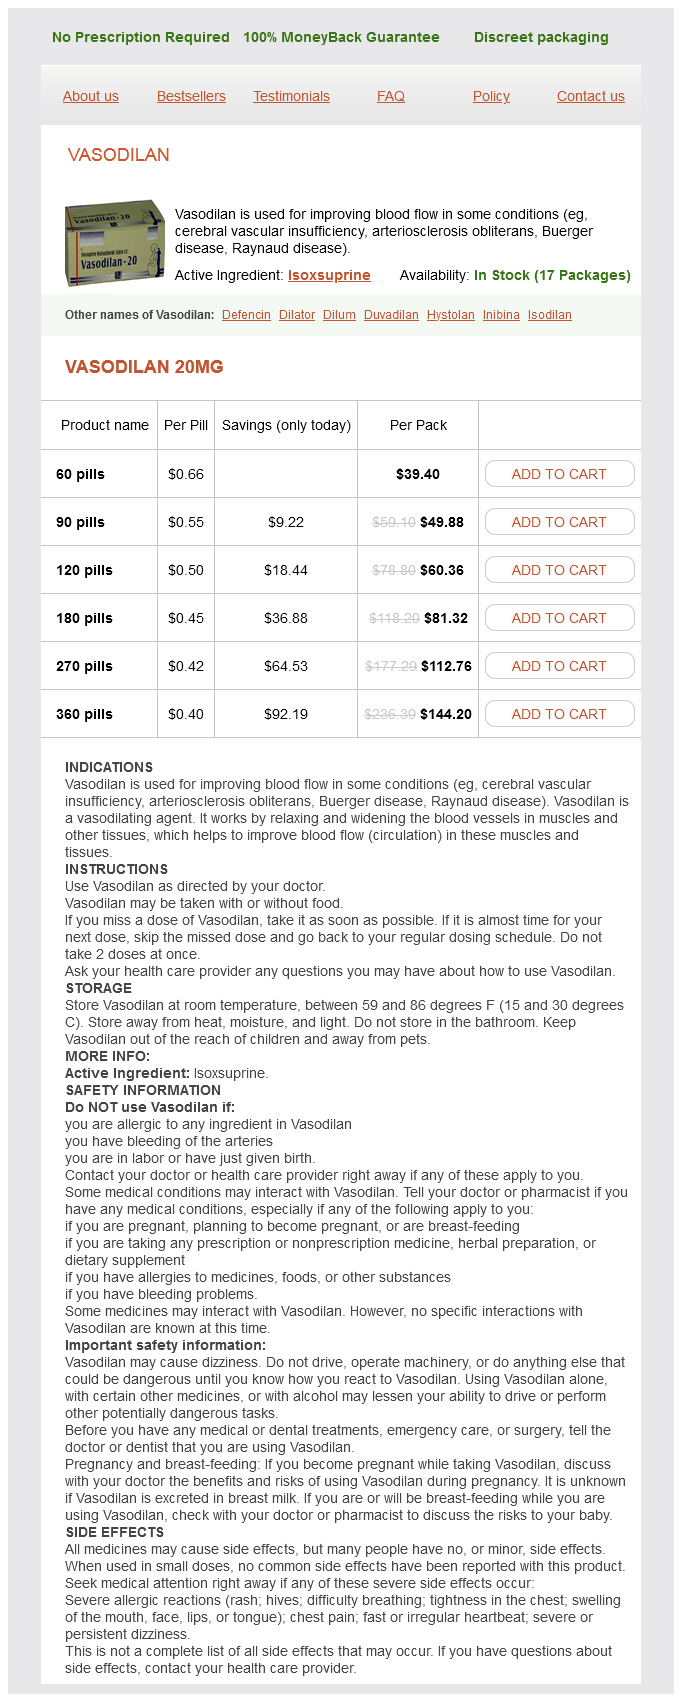
Vasodilan 20mg
- 60 pills - $39.40
- 90 pills - $49.88
- 120 pills - $60.36
- 180 pills - $81.32
- 270 pills - $112.76
- 360 pills - $144.20
Vasodilan dosages: 20 mg
Vasodilan packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 779
Only $0,43 per item
Description
They are extra commonly situated in the upper outer quadrant of the breast and are more common in African American sufferers blood pressure medication depression cheap vasodilan 20 mg visa. They can usually be identified based mostly on bodily examination blood pressure chart youth vasodilan 20 mg generic on line, because these plenty are clean blood pressure young male 20 mg vasodilan buy with visa, well circumscribed arteria elastica vasodilan 20 mg buy generic on-line, cellular, and nontender. Mammography has little to no utility in this population secondary to the denseness of the breast tissue and should be averted as a end result of the unnecessary publicity to both radiation and discomfort. These lesions can be noticed, with surgical excisional biopsy reserved for those with growth over time, tenderness, household anxiety regarding the presence of a breast mass, or very giant lesions. Vomiting is the first presenting symptom of youngsters with a variety of circumstances from benign response to minor infectious disease to the primary manifestation of life-threatening intraabdominal disease. To decide the significance of the vomiting, it could be very important characterize what the emesis looks like, how sick the patient is, and the age of the affected person, along with any associated symptoms. The varied causes of gastrointestinal obstruction that require surgical intervention could be categorized by age and the anatomic degree of obstruction. These may be divided into two age classes: (1) neonates and infants to cowl the first 12 months of life and (2) toddlers and older kids. Some sufferers develop reflux-associated problems related to esophageal or extraesophageal symptoms. These embrace pain, bleeding, dysphagia, and failure to thrive secondary to esophagitis. Recurrent pneumonia, otitis media, hoarseness, respiratory misery, and apneic spell may occur secondary to reflux. Several research are useful for diagnostic affirmation, but typically these tests are extra delicate than specific. In addition, an higher gastrointestinal collection is quite helpful for delineating the anatomy of the esophagus and stomach. It may show pyloric stenosis, malrotation, and the presence of any webs, membranes, or stenosis in these buildings, as nicely as hiatal hernias. Impedance probe testing uses a drop in resistance (impedance) throughout occasions rather than pH and is in all probability going more sensitive. Distal esophageal mucosal biopsies may be useful in a subset of patients to more precisely establish those that might benefit from extra aggressive antireflux therapy. The utility of liquid-phase gastric radionuclide scintigraphy ("milk scan") is questionable, as a result of it tends to over-call reflux, under-call aspiration, and unreliably determine gastric emptying. Antireflux surgery is reserved for these medically refractory patients with issues of reflux or in whom the potential complications from reflux pose too nice a danger. Surgery may be highly effective at minimizing reflux with the main unwanted aspect effects being the potential difficulty with emesis (not universal) and gas bloating. Nonbilious Emesis the most common explanation for nonbilious emesis in neonates and infants is overfeeding. These infants could develop hypochloremic, hypokalemic, metabolic alkalosis in the setting of persistent emesis. Failure to provide sufficient resuscitation preoperatively might go away the toddler at danger of postoperative apnea. Bilious Emesis Without Abdominal Distention Bilious emesis is a crucial discovering in the pediatric population. Its presence ought to always raise a pink flag in the evaluation of a vomiting infant. The principal concern is malrotation with midgut volvulus, which is a surgical emergency. This sometimes presents with out abdominal distention, because the extent of obstruction is at or close to the ligament of Treitz. Malrotation is the failure of the midgut (small bowel, proper colon, and one-third of transverse colon) to endure adequate rotation and retroperitoneal fixation during embryonic growth. Severe brief bowel syndrome or death might occur from delayed recognition, prognosis, and remedy of this important condition. This affected person additionally demonstrates a visual wave of peristalsis, which strikes from left to proper. Males are affected more generally than females with a 4-5: 1 male to feminine ratio. The etiology is unknown, however both environmental and genetic elements seem to play a task. The emesis is usually method but may also reveal proof of gastritis if it has been going on for a while. If the analysis is made early, the infant will typically seem comparatively nicely hydrated. However, if the signs have been ongoing for some time, the infant could also be extraordinarily dehydrated, skinny, and torpid. The lesion itself is often palpable within the epigastrium, between the midline and proper midclavicular line, and it has the consistency of a small olive. Palpating the hypertrophied pylorus requires a calm toddler and a affected person examiner. A, Ultrasonographic scan of the upper abdomen demonstrates the thickened pyloric muscle, indicated by the cursors. B, Barium study of the stomach (right) reveals skinny streaks of barium within the pyloric canal. The hypertrophic pyloric muscle bulged into the gastric antrum produces a "reversed 3" configuration. An appendectomy is commonly accomplished during the operation to keep away from diagnostic errors later in life, as a end result of the cecum sometimes resides in the left higher quadrant on the end of the operation. Duodenal atresia and different duodenal anomalies are important concerns in patients who present with bilious emesis. In 85% of neonates with duodenal atresia, the entry of the bile duct is proximal to the extent of obstruction; due to this fact, the emesis is bilious. Vomiting could occur shortly after delivery or could current later in the setting of annular pancreas, duodenal stenosis, and incompletely obstructing duodenal webs. Duodenal atresia has an incidence of approximately 1 in 6000 stay births with males being affected extra commonly than females. Additional congenital anomalies are recognized in over 50% of patients with duodenal atresia, with trisomy 21 occurring in approximately one-third of these sufferers. This anomaly could additionally be recognized antenatally based mostly on findings on the prenatal ultrasound with an indication of a dilated, fluid-filled abdomen and proximal duodenum. In the setting of an antenatal prognosis, and confirmatory plain x-ray in the newborn, no further imaging is required. Survival rates exceed 90% with operative intervention with mortality largely stemming from associated cardiac anomalies. Bilious Vomiting With Abdominal Distention Bilious emesis with related stomach distention is more characteristic of distal small bowel obstruction seen in situation similar to intestinal atresia, meconium disease, incarcerated hernias, or Hirschsprung disease, rather than proximal bowel obstruction. Small bowel and colonic atresias are hypothesized to be the sequelae of intrauterine vascular accidents and are believed to be a comparatively late gestational occasion. They can occur at any point alongside the intestinal tract with the very best incidence in the jejunum followed by the ileum and at last the colon. The presence of a proximal obstruction on plain film requires no additional testing prior to surgical procedure. Air in the distal gastrointestinal tract fails to rule out complete obstruction from volvulus and distinguishes the prognosis from duodenal atresia. In an atresia, a contrast enema will show a failure of the distinction material to reflux into the dilated loops of bowel. Small bowel atresias are sometimes isolated circumstances, however different anomalies could also be current in 25% of patients. Meconium ileus illness is the preliminary presentation of cystic fibrosis in up to 20% of youngsters, and these findings could additionally be appreciated on antenatal ultrasound imaging. Thick, viscous inspissated meconium in the distal small bowel causes an intestinal obstruction. Marked proximal small bowel dilation occurs, and the abdomen presents a "soap bubble" or "floor glass" look on plain radiography due to air bubbles which might be trapped in the inspissated meconium. Air-fluid levels are unusual because of the dense concentration of meconium in the intestinal loops. Contrast enema with a excessive osmotic water-soluble agent reveals the presence of a microcolon and inspissated meconium pellets within the distal ileum. Duodenal obstruction could also be partial (caused by Ladd bands, as seen here) or full (caused by volvulus). Contrast enema ought to be carried out after the neonate has been adequately resuscitated, recognizing that significant volume could also be needed during and after the procedure because of the osmotic nature of the enema.
Giant Knotweed (Hu Zhang). Vasodilan.
- Constipation, menstrual problems, hot flashes, heart disease, high cholesterol, cancer, skin burns, liver disease, gout, and gallstones.
- What is Hu Zhang?
- Are there any interactions with medications?
- Are there safety concerns?
- How does Hu Zhang work?
- Dosing considerations for Hu Zhang.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97057
The quantity and distribution of red (hematopoietic) and yellow (fatty) marrow change with age arrhythmia in cats buy cheap vasodilan 20 mg on-line. Conversion from red to yellow marrow proceeds from the extremities to the axial skeleton arrhythmia used in a sentence order vasodilan 20 mg otc, occurring within the distal bones of the extremities (feet and hands) first heart attack would feel like a heart attack purchase vasodilan 20 mg without prescription, and progressing finally to the proximal bones (humeri and femora) arteria sacralis vasodilan 20 mg buy cheap. The common scan aircraft is coronal with further planes being added, relying on the indication. For appropriate analysis of the bone marrow in the pediatric age group, understanding the traditional sample of marrow transformation is crucial. Coronal T1-weighted fat-saturated picture with distinction demonstrates bone marrow an infection with cortical breakthrough and associated subperiosteal abscess (arrow) in the proximal right tibial metaphysis. Diagram of axial and appendicular marrow distribution as a operate of age, as red marrow progressively converts to yellow marrow. Highresolution photographs of the cranial vault and brain with 2D and 3D reconstructions allow detailed analysis of craniosynostosis or other cranial anomalies (see Chapter 23). Systemic elements that will result in nephrotoxicity from iodinated distinction embody dehydration, anuria, creatinine higher than 3 mg/dL, diabetes, hepatorenal syndrome, a number of myeloma, and metformin use. However, if intracranial or intraorbital extension is suspected, then a contrast-enhanced scan is indicated (see Chapter 24). In the setting of a suspected mass, a contrast-enhanced examination must be carried out. The left caudate and putamen are hyperdense, as are the thalami; the central and peripheral gray matter appear normal. There is a cystic expansile mass of the proper maxillary sinus without calcifications or a matrix. C, Coronal picture on the bone window setting delineates expansion and remodeling of the partitions of the right maxillary sinus with a tooth (dotted arrow) protruding into the cyst. These studies of the backbone are generally accomplished without intravenous or intrathecal contrast. B, Soft tissue window setting at the similar level demonstrates regular enhancement of the right venous sinuses (solid arrow) and no enhancement of the left venous sinuses, with a big area of hypoattenuation (dotted arrow) appropriate with epidural abscess and venous sinus thrombosis. Comminuted fractures of the vertebral body (solid arrows) and proper transverse course of and pedicle (dashed arrows) are visible. B, Comminuted fracture of the supra-adjacent vertebral body (solid arrow) with posteriorly displaced fragment (dashed arrow) narrowing the spinal canal. C, Sagittal reconstruction, midline picture, delineating the fractures of both vertebral our bodies (solid arrows) and the associated loss of top and acute kyphosis. D, Sagittal reconstruction, paramedian image, delineating multilevel posterior element fractures (dashed arrows) in addition to the comminuted vertebral physique fractures (solid arrows) representing trauma to the anterior and posterior columns and therefore an unstable thoracic spine damage. B and C, Coronal reconstructed picture and axial picture delineate a cleft in the C3 vertebral body (arrows) suitable with a congenital butterfly vertebra. The midline sagittal picture was taken through the cleft, therefore the appearance of hypoplasia. Right: Axial image at the similar stage on the bone window setting delineates a nondisplaced fracture of the best frontal bone (arrow). Bottom left: Three-dimensional (3D) reconstruction of the calvarium, seen from the vertex, with the extent of the fracture well delineated. Bottom right: 3D reconstruction of the calvarium, viewed from the left lateral projection with delineation of the full extent of the fracture from the coronal to lambdoid suture. Double-headed crooked arrow, coronal suture; straight arrow, sagittal suture; Z line, lambdoid suture. Typical look for benign extra-axial collections of infancy, a benign selflimiting course of. Gradient echo, susceptibility, and diffusion-weighted images are usually severely compromised. Significant mass impact and dilatation of the best temporal horn/obstructive hydrocephalus are seen. B, Contrast-enhanced examination carried out on the identical day reveals marked relative hypoattenuation of the hematoma. B, Axial picture just under the dissection reveals a comparatively narrow caliber of the proper inner carotid artery (arrow) compared with the left internal carotid artery. D, Coronal reconstruction indicating regular look of the left internal carotid artery. B, Axial picture on the bone window setting delineates associated bone erosion (solid arrows) and invasion of the left jugular foramen (dashed arrow). C, Sagittal gentle tissue reconstruction delineates extent of the mass into both the naso- and oropharynx, as properly as its intracranial extension (arrows). D, Sagittal reconstruction on the bone window setting delineates the extent of clival erosion (arrows). B, Axial picture on the bone window setting delineates advanced, comminuted, and displaced fractures of the medial orbital walls/lamina papyracea (posterior arrows) and cribriform plate (anterior arrows). C, Coronal reconstruction delineates the advanced comminuted fractures, which also embrace the frontal sinuses and fovea ethmoidalis (diverging arrows) and left orbital roof (upper arrow), and redemonstrates the in depth fracture of the medial orbital wall/lamina papyracea (lower arrow). D, Lateral view of the three-dimensional (3D) reconstruction demonstrates the marked posterior displacement of the nasoethmoidal advanced (long arrow) in relation to the frontal sinus/ frontal bone (short arrow). Threedimensional (3D) reconstruction of the calvarium and face demonstrates lower facial hypoplasia due to maxillary and mandibular hypoplasia (long arrows) and their midline fusion (short midline arrow). Axial picture via the orbits delineates a large proper orbital cyst (arrow) with connection to a hypoplastic proptotic globe. Associated opacification of the left center ear and mastoid and pneumocephalus are additionally seen. All provide sensitive noninvasive analysis of brain metabolites and mobile biochemical changes, used in assessing brain maturation, brain ischemia, injury, and encephalopathy. In the analysis and characterization of inborn errors of metabolism, it is most likely not specific however might help to slim the entities to be thought of. Opacification of the left middle ear and mastoid is related to extension of the mass into the eustachian tube. A, Axial contrastenhanced picture by way of the neck slightly below the extent of the hyoid demonstrates a discrete cystic mass, just to the right of midline, with no discernible wall or enhancement (solid arrow). B, Sagittal reconstruction delineates the mass on the stage of the fiducial placed to localize the mass (arrow). A, Axial contrast-enhanced image on a soft tissue window setting by way of the lower thoracic backbone delineates a heterogeneous expansile damaging mass (solid arrows) involving the vertebral physique and more extensively the posterior components with intraspinal encroachment. B, Same axial picture on a bone window setting delineates bone expansion/remodeling and destruction. C, Sagittal reconstruction on a delicate tissue window setting delineates the marked narrowing of the spinal canal and thecal sac (arrows) by the mass. It can also be utilized in differentiating tumor progression from posttreatment modifications. This depends on native changes in cerebral blood move and changes in oxyhemoglobin and deoxyhemoglobin with targeted brain activation. Cortical activation by a focal task, or by a visible or auditory stimulus, ends in local elevated metabolic demand and therefore an increase in local blood move, which raises the concentration of oxyhemoglobin and decreases the focus of deoxyhemoglobin. Subtraction of pre- and postactivation pictures results in localization of the area of the brain activated by the duty or stimulus. B, Axial contrast-enhanced image just below delineates right anterior rim, enhancing epidural fluid collection. It is also used in assessing cognition, language, and motor skill acquisition and behavioral dysfunction. They are enough for assessing ventricular dimension and shunt place in patients with shunted hydrocephalus. Feed and bundle method is routinely utilized for small infants to get rid of need for sedation. Adrenoleukodystrophy is one of the entities for which a contrast examination may present important data. Also famous is a dense middle cerebral artery (vertical arrow), a finding related to vascular thrombosis/occlusion. B, Axial T2 magnetic resonance picture on the stage of the basal ganglia demonstrates hyperintensity/signal abnormality in the best basal ganglia and adjoining cortex in a center cerebral artery distribution. Techniques like 3D and 2D time-of-flight use inflow effect of blood protons, whereas phase-contrast angiography or venography are carried out using pulses to detect section shift brought on by flowing blood. A and B, Axial T2 magnetic resonance picture at the level of the lateral ventricles: In the neonatal interval (A) and at 6 months (B).
Specifications/Details
Solid masses throughout the substance of the testis should be thought-about malignant until proven in any other case blood pressure chart 80 year old 20 mg vasodilan order. Severe fusion could also be related to dysuria blood pressure chart log excel generic vasodilan 20 mg on-line, postvoid dribbling as the urine voided into the vagina drains out hypertension new guidelines generic vasodilan 20 mg with visa, or urinary tract an infection hypertension with hypokalemia vasodilan 20 mg mastercard. Although most adhesions lyse spontaneously as puberty approaches and the vaginal epithelium cornifies, problems of hygiene and discomfort convey many girls to the doctor for evaluation and remedy. Lysis may additionally be performed easily in the office-merely spreading the labia or mechanically separating the adhesions with an ointment-covered gloved finger will often suffice. Some practitioners believe that lysis ought to be followed by the application of estrogen cream to the area for a number of days to thicken the vaginal mucosa. Urethral Prolapse Prolapse of the urethra occurs nearly exclusively in AfricanAmerican females. Treatment options embody conservative management together with aggressive management of constipation, sitz baths, and topical steroids. These usually are thin mucosal tags that cause no signs and require no particular therapy. Fleshy polyps or multiple polyps should be examined carefully and biopsied to exclude malignancy, such as sarcoma botryoides (see Chapter 12). Prolapse of an ureterocele could additionally be related to a palpable distended bladder or flank mass (hydronephrosis). Ultrasonography of the bladder and kidneys demonstrates unilateral or bilateral hydronephrosis or hydronephrosis of a segment of a complete ureteral duplication, usually the upper pole of an obstructed renal unit. Ureteroceles are cystic dilations Ectopic Ureter Ureteral ectopia could additionally be associated with a single collecting system or an entire duplication of the amassing system (complete ureteral duplication). In females, an ectopic ureter could drain into the bladder neck, urethra, urethrovaginal septum, vagina, or uterus. This is a continual case in which the initial hemorrhagic nature of the acute prolapse has resolved with remark, leaving a protuberant, edematous urethra. A, A drop of urine exits from the orifice of an ectopic ureter positioned slightly below the urethral meatus in the urethrovaginal septum. B, Retrograde pyelography of the identical ureter reveals an enormous, tortuous ureter subtending the higher pole of a right complete ureteral duplication. [newline]A ectopic ureter into the urethra, urethrovaginal septum, or vagina might have a traditional voiding sample but with a continuous dribbling incontinence of small amounts of urine. The recognition of irregular genitalia is step one within the evaluation of intersex. The mixture of hypospadias and bilateral or unilateral cryptorchidism should be thought of as representative of intersex until confirmed in any other case. Paraurethral Cysts Cystic lesions of the paraurethral or vaginal mucosa could additionally be found on routine examination and are often asymptomatic. They hardly ever cause voiding symptoms and infrequently current in older women as palpable interlabial masses. Normal mucosa overlies the cyst, which often displaces the urethral meatus barely from the midline. Congenital Obstruction of the Vagina Vaginal obstruction could happen as a end result of an imperforate hymen, vaginal atresia or septa, or urogenital sinus malformation. Fusion anomalies of the M�llerian buildings may lead to a septate vagina or bicornuate uterus with one obstructed phase. Neonates could have abdominal masses or urinary retention; women with a didelphic or bicornuate uterus might have pelvic ache or menstrual irregularities at puberty. Examination of the toddler could reveal a distended vagina (hydrometrocolpos) with a bulging hymenal membrane. If a vaginal septum or atresia is the cause of the obstruction, exterior genital examination may be regular and a complete pelvic examination with vaginoscopy may be essential. All women with uterine or vaginal anomalies ought to have imaging of the upper urinary tract, given the high incidence of upper tract anomalies on this group. As a corollary, ladies with confirmed unilateral renal agenesis ought to be monitored via puberty for the development of M�llerian anomalies, commonly uterus didelphys with an obstructed unilateral uterine horn or vagina ipsilateral to the side of the absent kidney. Pelvic ultrasound examination within the peripubertal interval is an efficient way to monitor these girls. Genital Ambiguity Associated With Imperforate Anus the embryologic deformity that produces a excessive imperforate anus in women occasionally additionally influences the formation of the exterior genitalia by presumed native factors. A, Sagittal ultrasound of the pelvis in a neonate with a big pelvic hydrometrocolpos secondary to distal vaginal atresia. B, Catheter drainage of released white mucoid drainage with disappearance of the pelvic mass. The testicular tunics have been intact, and primary skin closure produced a wonderful end result. Although genital trauma is in all probability not life-threatening, correct management may be essential to the later well-being and psychosocial improvement of the patient. This is definitely dominated out within the emergency division or x-ray department by injecting contrast (intravenous contrast in case of extravasation into vascular structures) through the urethral meatus, using a blunt-tipped syringe or a small catheter. Once urethral injury has been excluded, urethral catheterization may be carried out safely. Ultrasound examination of the testes may be useful if huge edema or hematoma precludes thorough examination. Trauma to the feminine genitalia and perineum normally requires examination underneath anesthesia to allow a complete evaluation of the injury, with concomitant repair when necessary. Criteria, etiologies, and classification, Johns Hopkins Med J 146(4):156�163, 1980. Techniques and interpretation of the pediatric neurologic examination are primarily based largely on data of normal growth and improvement. The examination is preceded by an intensive historical past of the presenting drawback, including timing and mode of onset; course; and a past medical historical past that focuses on the antenatal, perinatal, and neonatal intervals for possible prior insults. Abnormalities of birth weight; the need for resuscitation after supply; early neonatal problems with hypoglycemia, hypocalcemia, or extreme jaundice; and abnormalities in exercise or issue feeding shortly after start often serve as pink flags. This is adopted by an in depth historical past of habits; growth and development with attention to evidence of delay, slowing, cessation, or regression of developmental milestones; and any potential affiliation with prior sickness or trauma. Obtaining a household history of neurologic, neuromuscular, or developmental problems can be necessary. The systematic neurologic evaluation proceeds from assessment of psychological status and language features through analysis of cranial nerves, gross motor function, muscle energy, gait and station, balance and coordination, sensory techniques, and deep tendon reflexes. It is applicable to older children and adolescents without vital modification from the analysis geared to the grownup. Tools essential to the neurologist embody the reflex hammer, bright penlight, ophthalmoscope, and stethoscope. For analysis of the first sensory modalities of sunshine contact, ache, temperature, and vibration, wisps of cotton, sterile disposable pins, glass take a look at tubes (to hold hot and cold water), and a tuning fork (256 Hz for kids and young adults, 126 Hz for older persons) are used. Derangements of main sensory operate may be present with lesions on the level of the nerve roots, plexuses, or peripheral nerves. Neurologic examination of the younger child requires flexibility and a mild, staged approach. Facies, head form, physique habitus, spontaneous movements, position, and posture are famous, together with spontaneous vocalizations and quality and pitch of cry in infants. In the kid sufficiently old to walk, stance and gait, in addition to the power to run, stoop, and get well; climb onto a stool; and rise from the ground (when developmentally appropriate), are observed. Much of the rest of the neurologic examination additionally lends itself to play, and within the second stage of remark a extra detailed evaluation of mental status, language, handedness, and fine and gross motor expertise is carried out by partaking the kid in play. Williams number of rattles, keys, spinning and mechanical toys, dolls, automobiles, small blocks, noise makers, tennis balls, hand puppets, crayons, and picture books supplement the traditional instruments. If further statement of gait is critical, the examiner can have the kid walk to or with the parent. Pat-a-cake video games are in style for testing quickly alternating actions with younger youngsters. Asking younger children to make faces, stick out their tongues, and blow up balloons is another useful approach in assessing cranial nerves. These are normally brisk, or 3+, within the young infant, turning into 2+ by 6 months old. If immediately tapping on the tendon seems upsetting to the kid, it might assist to place a finger over the tendon to be percussed and faucet that.
Syndromes
- Has the child always been on the small side of the growth charts?
- Dehydration
- Damage to the nerve in this area
- Toast
- Your doctor will puncture the varicose vein.
- Hoarseness occurs in a child less than 3 months old
Related Products
Additional information:
Many issues of the decrease extremities occurring in childhood are congenital and may end up in lifelong incapacity if they continue to be unrecognized or are unsuccessfully handled blood pressure ranges for young adults vasodilan 20 mg buy generic on-line. Knowledge of the traditional anatomy and function of the hip blood pressure j curve vasodilan 20 mg buy without a prescription, knee hypertension quiz buy 20 mg vasodilan mastercard, ankle blood pressure normal value vasodilan 20 mg buy discount line, and foot is critical to accurately recognize and treat abnormalities in this area (see the Lower Extremity Examination part, earlier). Developmental Dislocation of the Hip Developmental dislocation of the hip, previously referred to as congenital dislocation of the hip, consists of displacement of the femoral head from its regular relationship with the acetabulum. Female infants are affected significantly more incessantly than male infants, and unilateral dislocation is twice as frequent as bilateral. Idiopathic dislocation is more frequent, and patients usually have a constructive household history for the defect. Its severity varies from subluxated, to dislocated and reducible, to dislocated and irreducible. This type of developmental dislocation may be related to irregular intrauterine positioning or restriction of fetal movement in utero, which impedes sufficient improvement and stability of the hip joint complex. The relaxing effect of hormones on gentle tissue during pregnancy can also contribute, with affected infants perhaps being more delicate to the pelvic relaxation effects of maternal estrogen. Teratogenic dislocations of the hip symbolize a more severe type of the dysfunction and are most likely the results of a germ plasm defect. They happen early in fetal growth and result in malformation of both the femoral head and the acetabular socket. Associated congenital anomalies are widespread in infants whose dislocations are teratogenic, including clubfoot deformity, congenital torticollis, metatarsus adductus, and childish scoliosis. Early diagnosis enables prompt establishment of therapy and leads to a greater outcome. Knowledge of the scientific indicators and ability in methods of examination are essential. Typically, the infant with a dislocated hip has no noticeable difference within the place during which the leg is held, although some affected infants could maintain the leg in a position of adduction and external rotation. This foreshortening is accentuated by holding the hips and knees in 90 levels of flexion (Galeazzi sign). In sufferers with reducible dislocations, the Ortolani sign is positive when a palpable clunk is felt on abduction and inside rotation (relocation) of the hip. The Barlow check is positive if, with the knees flexed and hips flexed to 90 levels, the hips are gently adducted with pressure applied on the lesser trochanter by the thumb. A palpable clunk indicating posterior dislocation is appreciated if the hip is unstable or dislocated. When the hip is dislocated and irreducible, solely limitation of abduction is apparent. Furthermore, in developmental dislocation, ossification could additionally be delayed even longer, as a outcome of regular articulation forces are absent. In teratogenic hip dislocation, there could additionally be hypoplasia of both the acetabular and femoral sides with non-congruent development of one or each of these structures. Successful correction of congenital hip dislocation depends on early analysis and establishment of appropriate treatment. In the first 6 months of life, use of a Pavlik harness, which allows gentle motion of the hip in a flexed and abducted place, could obtain and maintain a satisfactory reduction. Between 6 and 18 months old, mild closed discount and immobilization in a spica forged with or without surgical release of the contracted iliopsoas and adductor muscles is indicated. After 18 months old, discount by manipulative measures is tough owing to contractures of the related delicate tissues. In instances of teratogenic dislocation, underlying maldevelopment makes the result less passable, even with optimum administration. With early recognition and applicable therapy, a relatively regular hip with satisfactory function can be anticipated in instances of idiopathic hip dislocation. Failure of concentric reduction or complications, corresponding to avascular necrosis of the femoral head, ensuing from overzealous attempts at closed discount in long-standing instances, could lead to a lifelong disability characterised by ache and stiffness in the hip; an antalgic, lurching gait; and shortening of the concerned limb. Legg-Calv�-Perthes Disease In Legg-Calv�-Perthes disease (coxa plana), impairment of the blood provide to the growing femoral head ends in avascular necrosis. Current theories implicate traumatic disruption of the blood provide and recurrent episodes of synovitis, during which increased intraarticular pressure compromises blood flow to the growing ossific nucleus, as causative. The dysfunction usually becomes manifest between four and 11 years old, with a better incidence in boys. Affected youngsters usually exhibit delayed skeletal maturation and are small for his or her age. Unilateral involvement is the rule, and if a bilateral case is suspected, some form of epiphyseal dysplasia have to be ruled out. The severity of the disease varies tremendously, relying on the extent to which the femoral head is affected. Younger children usually have milder involvement, as a larger portion of the femoral head continues to be cartilaginous and less depending on vascular provide. The baby might present with symptoms attribute of toxic synovitis with out radiographic findings. Many children present with a painless limp, and others complain of thigh or knee ache, fatigue on strolling, or hip stiffness. Pain and limitation of motion are encountered on makes an attempt at inner rotation and abduction. The Trendelenburg sign (failure to keep a degree pelvis when standing on the concerned limb) is constructive. A, In instances of unilateral dislocation, the concerned extremity is foreshortened and the thigh and groin creases are uneven. C, In this anteroposterior radiograph obtained in a 3-month-old child, the proximal left femur is displaced upward and laterally, and the acetabulum is shallow. D, In the frog-leg view, the long axis of the affected left femur is directed towards a degree superior and lateral to the triradiate cartilage, in distinction with that of the right, which points directly toward this structure. Early radiographic findings might include failure of progressive improvement of the femoral ossific nucleus, a subchondral radiolucent fracture line (Caffey sign), and proof of slight subluxation. However, in early instances, radiographs may be utterly normal, although a nuclear bone scan may be helpful in verification of impairment of the blood supply to this area. Although revascularization and reconstitution of the femoral head all the time occur, loss of mechanical integrity of the top with flattening and fragmentation of its surface could end in an irreversible predisposition to degenerative change. Most therapies are primarily based on the principle of "containment" and the maintenance of a traditional relationship of the femoral head inside the acetabulum so as to reduce everlasting joint incongruity. In more extreme instances, abduction casting, bracing, or surgical therapy with femoral or acetabular osteotomy to reposition the femoral head deeper within the acetabulum could additionally be employed. He is bearing much less weight on the concerned proper leg (note the marginally flexed proper knee). B, In this anteroposterior radiograph, the best femoral epiphysis is flattened and fragmented. Slipped Capital Femoral Epiphysis Slipped capital femoral epiphysis, a dysfunction seen early in puberty, entails displacement of the femoral head from the femoral neck through the epiphyseal plate. It is seen extra regularly in males and happens bilaterally in approximately 25% of cases. Most generally, it occurs on the onset of puberty in overweight children with delayed sexual maturation. This situation differs from traumatic epiphyseal fractures, because the translational displacement happens via a unique portion of the growth plate. In some circumstances, an underlying connective tissue disorder (such as Marfan syndrome) or an endocrinologic problem (such as hypothyroidism) could be recognized. The clinical presentation is characteristic, though the length of symptoms varies. The patient presents with a painful limp and should or could not have a history of recent trauma, which is often minor, or pain may have developed after jumping. This harm could have precipitated a slip within the previously weakened epiphysis or may have increased the degree of displacement of a slip that was already in progress. A flexion contracture could also be famous, and vary of hip movement tends to be diminished in all planes, notably inner rotation.
Usage: q.d.
Eggertsen G blood pressure diary 20 mg vasodilan buy otc, et al: Molecular cloning and expression of rabbit sterol 12-hydroxylase hypertension stage 1 vasodilan 20 mg low cost. Johansson G: Effect of cholestyramine and food regimen on hydroxylations in the biosynthesis and metabolism of bile acids blood pressure medication when pregnant buy vasodilan 20 mg fast delivery. Axelson M blood pressure video buy vasodilan 20 mg, et al: the plasma level of 7a-hydroxy-4-cholesten-3one displays the exercise of hepatic cholesterol 7a-hydroxylase in man. Inoue T, et al: Developmental pattern of 3-oxo-delta 4 bile acids in neonatal bile acid metabolism. Sumazaki R, et al: Gene evaluation in D4-3-oxosteroid 5b-reductase deficiency [letter]. Bj�rkhem I: Mechanism of degradation of the steroid side chain within the formation of bile acids. Andersson S, et al: Cloning, construction, and expression of the mitochondrial cytochrome P-450 sterol 26-hydroxylase, a bile acid biosynthetic enzyme. Dahlback H, Holmberg I: Oxidation of 5b-cholestane-3a,7a,12atriol into 3a,7a,12a-trihydroxy-5b-cholestanoic acid by cytochrome P-450(26) from rabbit liver mitochondria. Rosen H, et al: Markedly reduced bile acid synthesis but maintained ranges of ldl cholesterol and vitamin D metabolites in mice with disrupted sterol 27-hydroxylase gene. Bj�rkhem I, Hansson M: Cerebrotendinous xanthomatosis: an inborn error in bile acid synthesis with defined mutations but still a challenge. Shefer S, et al: A 25-hydroxylation pathway of cholic acid biosynthesis in man and rat. Salen G, et al: Cholic acid biosynthesis: the enzymatic defect in cerebrotendinous xanthomatosis. Prydz K, et al: Subcellular localization of 3a,7a-dihydroxy- and 3a,7a,12a-trihydroxy-5b-cholestanoyl-coenzyme A ligase(s) in rat liver. Ferdinandusse S, et al: Mutations in the gene encoding peroxisomal 2-methyl-acyl-CoA racemase trigger adult-onset sensory motor neuropathy. An inducible fatty acyl-CoA oxidase, a noninducible fatty acyl-CoA oxidase, and a noninducible trihydroxycoprostanoylCoA oxidase. Bj�rkhem I, Gustafsson J-�: On the conversion of cholestanol into allocholic acid in rat liver. Formation of 12a-hydroxyl derivatives and companions from 5a-sterols by rabbit liver microsomes. Shoda J, et al: Similarity of bizarre bile acids in human umbilical wire blood and amniotic fluid from newborns and in sera and urine from grownup patients with cholestatic liver illnesses. Gustafsson J-�, Anderson S, Sj�vall J: Bile acid metabolism during development: metabolism of lithocholic acid in human fetal liver. Dumaswala R, et al: Identification of 3a,4b,7a-trihydroxy-5bcholanoic acid in human bile: reflection of a new pathway in bile acid metabolism in people. Molecular cloning and expression of human liver bile acid CoA:amino acid N-acyltransferase. In Paumgartner G, Stiehl A, Gerok W, editors: Bile acids in hepatobiliary illnesses: fundamental research and medical utility, Dordrecht/Boston/London, 1997, Kluwer Academic, pp 43�47. Radominska-Pyrek A, et al: Glucuronides of monohydroxylated bile acids: specificity of microsomal glucuronyltransferase for the glucuronidation site, C-3 configuration, and aspect chain length. Radominska-Pyrek A, et al: Glucuronidation of 6a-hydroxy bile acids by human liver microsomes. Matern H, Matern S, Gerok W: Formation of bile acid glucosides by a sugar nucleotide-independent glucosyltransferase isolated from human liver microsomes. Scholmerich J, et al: Influence of hydroxylation and conjugation of bile salts on their membrane-damaging properties-studies on isolated hepatocytes and lipid membrane vesicles. Partial purification and characterization of an enzyme from rat liver that catalyzes the sulfation of bile salts. Loof L, Hjerten S: Partial purification of a human liver sulphotransferase active in course of bile salts. In vivo and in vitro evidence for a selective conjugation reaction of 7b-hydroxylated bile acids in humans. Mallory A, et al: Patterns of bile acids and microflora within the human small gut. Danielsson H, Einarsson K, Johansson G: Effect of biliary drainage on particular person reactions in the conversion of ldl cholesterol to taurocholic acid. Makishima M, et al: Identification of a nuclear receptor for bile acids [see comments]. Haas D, et al: Differential prognosis in patients with suspected bile acid synthesis defects. Iser J, Dowling R, Murphy G: Congenital bile salt deficiency associated with 28 years of intractable constipation. Dai D, et al: Liver disease in infancy attributable to oxysterol 7 alphahydroxylase deficiency: successful treatment with chenodeoxycholic acid. Mathis U, Karlaganis G, Preisig R: Monohydroxy bile salt sulfates: tauro-3b-hydroxy-5-cholenoate-3-sulfate induces intrahepatic cholestasis in rats. Yamato Y, et al: 3beta-hydroxy-delta5 -C27-steroid dehydrogenase deficiency: analysis and remedy. Fischler B, et al: Cholestatic liver illness in adults could also be due to an inherited defect in bile acid biosynthesis. Gonzales E, et al: Oral cholic acid for hereditary defects of primary bile acid synthesis: a safe and efficient long-term remedy. Molho-Pessach V, et al: Homozygosity mapping identifies a bile acid biosynthetic defect in an grownup with cirrhosis of unknown etiology. Ichimiya H, et al: Bile acids and bile alcohols in a toddler with hepatic 3b-hydroxy-D5-C27-steroid dehydrogenase deficiency: effects of chenodeoxycholic acid treatment. Egestad B, et al: Fast atom bombardment mass spectrometry in the analysis of cerebrotendinous xanthomatosis. Stieger B, et al: Differential interplay of bile acids from patients with inborn errors of bile acid synthesis with hepatocellular bile acid transporters. Ichimiya H, et al: Treatment of continual liver illness caused by 3b-hydroxy-D5-C27- steroid dehydrogenase deficiency with chenodeoxycholic acid. Riello L, et al: Titration of bile acid supplements in 3beta-hydroxyDelta 5-C27-steroid dehydrogenase/isomerase deficiency. Impairment of bile acid biosynthesis related to incomplete degradation of the ldl cholesterol facet chain. Kuriyama M, et al: Cerebrotendinous xanthomatosis: clinical and biochemical analysis of eight sufferers and review of the literature. Kibe A, et al: Occurrence of bile alcohols in the bile of a affected person with cholestasis. Peynet J, et al: Cerebrotendinous xanthomatosis: remedies with simvastatin, lovastatin, and chenodeoxycholic acid in three siblings [see comments]. Nakamura T, et al: Combined treatment with chenodeoxycholic acid and pravastatin improves plasma cholestanol ranges associated with marked regression of tendon xanthomas in cerebrotendinous xanthomatosis. Savolainen K, et al: A mouse model for alpha-methylacyl-CoA racemase deficiency: adjustment of bile acid synthesis and intolerance to dietary methyl-branched lipids. Eyssen H, et al: Bile acid abnormalities and the diagnosis of cerebro-hepato-renal syndrome (Zellweger syndrome). Van Maldergem L, et al: Orthotopic liver transplantation from a living-related donor in an infant with a peroxisome biogenesis defect of the childish Refsum disease sort. Evidence that peroxisomes are of importance within the normal biosynthesis of each cholic and chenodeoxycholic acid. Stellaard F, et al: Bile acids in amniotic fluid: promising metabolites for the prenatal diagnosis of peroxisomal problems. Christensen E, et al: A new peroxisomal disorder: di- and trihydroxycholestanaemia due to a presumed trihydroxycholestanoylCoA oxidase deficiency. Przyrembel H, et al: Di- and trihydroxycholestanoic acidaemia with hepatic failure. Bj�rkhem I, et al: Unsuccessful makes an attempt to induce peroxisomes in two cases of Zellweger illness by therapy with clofibrate.
Tags: vasodilan 20 mg discount on-line, vasodilan 20 mg purchase on line, purchase vasodilan 20 mg with visa, vasodilan 20 mg buy discount on-line, vasodilan 20 mg without a prescription, vasodilan 20 mg for sale, discount vasodilan 20 mg with amex, 20 mg vasodilan purchase with mastercard, vasodilan 20 mg buy cheap, vasodilan 20 mg discount with mastercard, 20 mg vasodilan generic free shipping, vasodilan 20 mg buy generic on-line, vasodilan 20 mg with amex, generic vasodilan 20 mg on line, vasodilan 20 mg discount visa, 20 mg vasodilan cheap free shipping
8 of 10
Votes: 30 votes
Total customer reviews: 30
Customer Reviews
Mamuk, 28 years: Prenatal or postnatal premature fusion is known as craniosynostosis, which causes irregular cranium shape by limiting development in the path of the fusion, and can result in abnormal intracranial stress as the mind grows towards a set restriction.
Ashton, 25 years: In reality, patients with pain, indicators of nerve root compression, or evidence of new-onset peripheral neurologic deficits should undergo thorough analysis for a treatable underlying trigger.
Pyran, 53 years: Use of a speculum is typically not required but is helpful in conditions that necessitate visible inspection of the vaginal cavity or cervix, together with these listed in Box 19.
