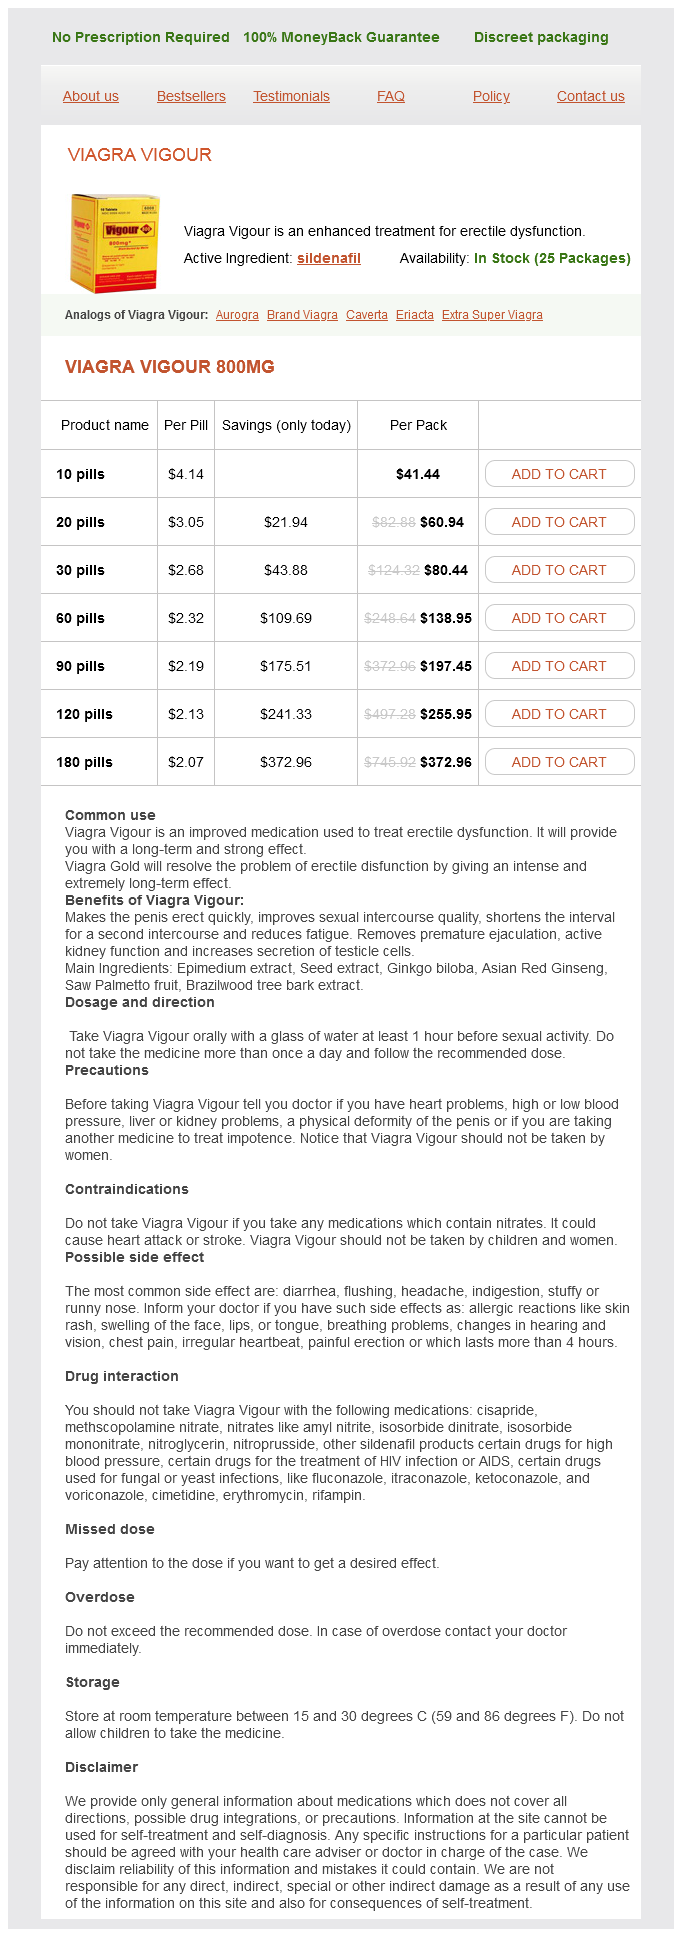
Viagra Vigour 800mg
- 10 pills - $41.44
- 20 pills - $60.94
- 30 pills - $80.44
- 60 pills - $138.95
- 90 pills - $197.45
- 120 pills - $255.95
- 180 pills - $372.96
Viagra Vigour dosages: 800 mg
Viagra Vigour packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills
In stock: 688
Only $2,2 per item
Description
White count may be slightly raised; if very excessive erectile dysfunction over the counter buy generic viagra vigour 800 mg on-line, think about septic arthritis Liver enzymes Possible alcohol abuse Renal perform Drug doses might need adjusting if renal function is poor Review treatment Diuretics and another medication enhance urate Investigations if pseudogout suspected Calcium erectile dysfunction surgery cost purchase 800 mg viagra vigour, magnesium erectile dysfunction treatment without drugs buy generic viagra vigour 800 mg on line, ferritin erectile dysfunction symptoms discount viagra vigour 800 mg amex, thyroid function Blood strain Cholesterol Blood sugar Thyroid perform 15% of sufferers with gout have hypothyroidism Uric acid excretion Consider if robust family history of gout, if onset under age 25 or if renal stones present Causes 2. Alcohol is catabolized to ketones that compete with urate for excretion by the renal tubule. Beer sometimes contains substantial quantities of purines, from yeast, which may be catabolized to urate by gut micro organism. Serum urate can fall throughout an acute attack, and patients on uratelowering treatment can nonetheless be affected till crystal deposits have cleared from the joints. Hyperuricaemia and heart problems There is a wellrecognized association between hyperuricaemia and heart problems. However, assessing cardiovascular danger in folks presenting with gout is worthwhile. Clinical options Acute gout Typically, gout presents as speedy onset of a monoarthritis associated with severe pain and irritation, classically affecting the primary metatarsophalangeal joint (podagra). Untreated, acute gout usually resolves spontaneously within 7�10 days however can once in a while last several weeks. The other mostly affected areas are the other joints in the foot, ankle, knee, wrist, finger and elbow. The affected joint is warm, tender and swollen and typically, the overlying skin is erythematous. The predilection for peripheral joints might be as a outcome of crystals are extra likely to form in cooler joints. However, few generalists (or their patients) will relish aspirating an acutely infected first metatarsophalangeal joint. Pyrophosphate crystals which are weakly positively birefringent beneath polarized gentle are present in pseudogout. Both forms of crystals coexist in about 10% of crystalassociated synovial effusions. Bursitis of the first metatarsophalangeal joint can mimic podagra and is usually mislabelled and mistreated as gout, particularly in younger women. Investigations � All patients with a suspected first episode of gout should be investigated to obtain some confirmatory evidence to support the prognosis, to look for underlying causes and to identify associated comorbidities (see Box 10. Tophi are chalky deposits of urate embedded in a matrix of lipid, protein and calcific debris. They are often subcutaneous, however could happen in bone and different organs, including heart valves and the eye. These may be seen radiographically as delicate tissue swellings (occasionally with associated calcification) and there could also be attribute gouty Xray adjustments of subcortical cysts with out erosions and/or geodes (punchedout type erosions with sclerotic margins and overhanging edges). Urate stones One in five sufferers with gout overexcrete urate and may develop urate stones. Uricosuric medicine should be prevented in patients with a historical past of uratecontaining renal stones. Patients with ileostomies are susceptible to urate stones as a consequence of manufacturing concentrated acidic urine. Adults with newonset gout may be heterozygous for one of these situations but investigations must be restricted to these with indicative family histories. Recommendations for therapy are largely based on medical expertise quite than randomized managed trial evidence. Acute gout the choice of drug treatment for acute gout relies on the balance of dangers and benefits. The alternative of preparation must be primarily based on an evaluation of relative risks of every drug for an individual affected person and patient choice. Decades of scientific expertise and guideline recommendations attest to their efficacy for acute gout. Crystal deposits (tophi) can develop around palms, ft, elbow and Gout, Hyperuricaemia and Crystal Arthritis 65 celecoxib is similarly effective. Colchicine � There are two controlled trials of colchicine compared to placebo for acute gout. These show that colchicine is efficient and that lowdose colchicine seems to be as efficient as highdose colchicine. Since colchicine can have unpleasant unwanted facet effects, together with extreme diarrhoea, bone marrow and neuromuscular dysfunction, utilizing a lower dose of 0. Clinical expertise helps using intraarticular steroids but septic arthritis have to be positively excluded. Other treatments � Experience and a few managed trial evidence recommend that some nondrug ache reduction modalities corresponding to the use of ice packs may give additional pain aid. The monoclonal antibody canakinumab is licensed for the therapy of acute gout, if conventional therapy is ineffective, but its value is prohibitive. Xanthine oxidase inhibitors � these stop the purine breakdown merchandise xanthine and hypoxanthine being transformed into urate. Allopurinol has been obtainable for almost 50 years; more recently, a second xanthine oxidase inhibitor, febuxostat, has turn into available (see below). Allopurinol � Allopurinol reduces serum urate, but its impact on recurrent gout is unclear. Only a minority of sufferers taking the everyday dose of 300 mg/day achieve a target urate of zero. Allopurinol hypersensitivity might occur in up to 2% of patients; this may be extreme or even deadly. Desensitizing regimens of allopurinol can be tried in milder instances of hypersensitivity. Febuxostat � Febuxostat eighty mg is superior to allopurinol 300 mg at reaching a serum urate of <0. Uricosuric drugs � Uricosuric drugs decrease serum urate by inhibiting its tubular reabsorption. New selective uric acid reabsorption inhibitors are being examined and may turn into obtainable. Uricase medicine � Uricase medication that work by oxidizing uric acid to the more soluble allantoin are available in some jurisdictions. Other drugs � Several other medication have, coincidentally, been found to have uratelowering effects. Intercritical and continual gout the mainstay of therapy for prevention of recurrent acute gout and continual gout is decreasing serum urate sufficient to permit crystals to clear. Patients with two or more attacks of gout per year ought to be supplied uratelowering medication. Usual advice is not to begin uratelowering drugs during an attack as this may delay resolution and should be prevented as reducing serum urate can trigger acute gout. Medication evaluation � Consider stopping diuretics or any other medication recognized to enhance serum urate. Lifestyle interventions � Patients should be suggested to: � Lose weight (if appropriate) � Reduce meat and fish eaten Pseudogout Pseudogout, which can be simply confused with gout, is caused by deposition of calcium pyrophosphate crystals. Typically, it produces an episodic monoarthritis but it can also have a medical picture just like osteoarthritis or rheumatoid arthritis. Its prevalence increases from 3% in folks in their 60s to half of those of their 90s. It can be associated with hypothyroidism, hypercalcaemia, haemochromatosis or hypomagnesaemia. Strippoli: corticosteroid or nonsteroidal antiinflammatory medicine for the treatment of acute gout: a scientific evaluate of randomized controlled trials. The global burden of gout: estimates from the Global Burden of Disease 2010 study. Other crystal illnesses A variety of other crystals can produce acute musculoskeletal irritation. Most frequent are hydroxyapatite crystals which typically deposit in tendons, periarticular soft tissue and synovium. Hydroxyapatite deposition may be asymptomatic however can on occasion result in significant joint destruction. Involvement of the shoulder is typically referred to as Milwaukee shoulder, however nearly any joint could also be affected. Identifying and correcting an underlying explanation for hypophosphataemia or hypercalcaemia may cut back the risk of future assaults. Its identification in joint fluid requires particular staining with alizarin red dye.
Imber (Ginger). Viagra Vigour.
- Are there safety concerns?
- Is Ginger effective?
- Rheumatoid arthritis, osteoarthritis, loss of appetite, colds, flu, migraine headache, preventing nausea caused by chemotherapy, and other conditions.
- What other names is Ginger known by?
- Preventing motion sickness and seasickness.
- Preventing dizziness.
- Preventing morning sickness, after discussing the possible risks with your healthcare provider.
- Are there any interactions with medications?
- Nausea and vomiting following surgery.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96924
D erectile dysfunction therapy treatment 800 mg viagra vigour buy fast delivery, Contralateral carotid injection angiogram reveals retrograde filling of the fistula erectile dysfunction doctor edmonton viagra vigour 800 mg cheap without prescription. Hydrogel-coated coils could be useful due to their ability to "increase" after deployment erectile dysfunction treatment following radical prostatectomy quality 800 mg viagra vigour. When the precise location and dimension of the fistula are troublesome to determine erectile dysfunction doctors in atlanta generic 800 mg viagra vigour with visa, balloon remodeling or stent placement may be required. In later studies, the mixture of Onyx and coils has been reported in its place remedy option. No dense packing of coils is necessary and the dose and injection time of Onyx are both less, and due to this fact the risk of inadvertent embolization is decreased. A nondetachable balloon can be utilized in the course of the process to determine the fistulous point, serve as an abutment for coils, and forestall reflux of the agent with subsequent arterial embolization. Retrograde venous drainage toward the orbit is often associated with distinguished ocular findings. Diplopia is widespread and associated to ischemic dysfunction or mechanical compression of the cranial nerves and restricted motion secondary to venous engorgement of the orbital contents. The pattern of double imaginative and prescient created by engorgement of the orbital contents and restricted movement may not match with a specific cranial neuropathy. Other signs and signs seen at presentation embrace chemosis in 94% of sufferers, proptosis in 87%, elevated intraocular pressure in 60%, cranial neuropathy in 54%, and decreased visual acuity in 28%. The angiogram must include the interior and exterior carotid provides of either side and at least one vertebral artery. The venous drainage includes the superior ophthalmic vein in more than 80% of sufferers, the inferior petrosal sinus in 42%, and the contralateral cavernous sinus in 23%. In this scenario intermittent ipsilateral carotid compression has been recommended to induce thrombosis of the fistula. With a transvenous strategy, the shortest and most direct route to the cavernous sinus is the ipsilateral inferior petrosal sinus owing to its direct connection to the internal jugular vein. Although direct puncture by way of the orbit can be related to the danger of intraorbital hematoma because no local stress could be applied on needle withdrawal, this complication is uncommon. In common, detachable coils are the popular embolic agents and achieve complete fistula obliteration within the majority of cases. The danger of its deep penetration into arterial collaterals with subsequent cranial nerve ischemia is one disadvantage of this liquid embolic agent. Complete fistula obliteration with a single endovascular process is achieved in 84% of patients. A paradoxical worsening of the ocular symptoms, which could be noticed in 3% of patients, is believed to be related to mass impact from the embolic agent. To overcome this limitation, a combined method consisting of Gamma Knife radiosurgery adopted by embolization can be used. Embolization is carried out after radiosurgery to allow sufficient protection of the fistulous nidus. Novel methods utilizing totally different embolic brokers and approaches are available, making this modality feasible for virtually all of sufferers. Transvenous embolisation of dural carotid-cavernous fistulas by multiple venous routes: a sequence of 27 instances. Dangerous extracranialintracranial anastomoses and supply to the cranial nerves: vessels the neurointerventionalist must know. Treatment of a carotid cavernous fistula via direct transovale cavernous sinus puncture. Treatment of carotidcavernous fistulas using intraarterial balloon assistance: case series and technical note. Carotid-cavernous fistula caused by a ruptured intracavernous aneurysm: endovascular treatment by electrothrombosis with removable coils. Treatment of cavernous sinus dural arteriovenous fistulae by external guide carotid compression. Using XperGuide planning software program to safely guide catheter entry to the cavernous sinus by way of transorbital puncture: a case report. Use of onyx for transarterial balloon-assisted embolization of traumatic carotid cavernous fistulas: a report of 23 circumstances. Management of direct carotid-cavernous sinus fistulas with the usage of ethylenevinyl alcohol (Onyx) solely: preliminary results. Microsurgical anatomy of the arterial compartment of the cavernous sinus: analysis of 24 cavernous sinus. The circular sinus: an anatomic examine with neurosurgical and neurointerventional applications. Dural carotid-cavernous fistulas: epidemiology, scientific presentation, and management. Management of 100 consecutive direct carotid-cavernous fistulas: outcomes of remedy with detachable balloons. A technical contribution of the exact angiographic localization of carotid cavernous fistulas. HydroCoil occlusion for treatment of traumatic carotid-cavernous fistula: preliminary expertise. Use of Onyx for transarterial balloonassisted embolization of traumatic carotid cavernous fistulas: a report of 23 cases. Embolization of direct carotid cavernous fistula with Onyx and coils underneath transarterial balloon protection. Transarterial treatment of direct carotico-cavernous fistulas with coils and Onyx. Treatment of carotid-cavernous fistulas using intraarterial balloon assistance: case sequence and technical observe. Placement of coated stents for the remedy of direct carotid cavernous fistulas. Angiographic follow-up of traumatic carotid cavernous fistulas treated with endovascular stent graft placement. Treatment of carotid cavernous fistulas using lined stents: midterm results in seven patients. Endovascular administration of dural carotid-cavernous sinus fistulas in 141 patients. Transvenous embolization of a dural arteriovenous fistula of the cavernous sinus through the contralateral pterygoid plexus. Transvenous embolization of a dural carotid-cavernous sinus fistula through the inferior ophthalmic vein. Transvenous embolization of dural carotid-cavernous fistulae with transfacial catheterization by way of the superior ophthalmic vein. Percutaneous transfemoral embolization of an indirect carotid-cavernous fistula with cortical venous entry to the cavernous sinus. The superior ophthalmic vein method for the therapy of carotid-cavernous fistulas: a novel approach utilizing Onyx. Transorbital endovascular embolization of dural carotid-cavernous fistula: entry to cavernous sinus by way of direct puncture: case examples and technical report. The evolution of endovascular therapy of carotid cavernous fistulas: a single-center experience. Stereotactic radiosurgery for the therapy of low-flow carotid-cavernous fistulae: results in a sequence of 25 circumstances. Although there are a quantity of classification schemes in the literature,22-24 the most generally employed schemes are the Borden and Cognard classifications. These lesions are completely benign in nature, with no danger of intracranial hemorrhage or neurological deficit in their current state. They typically are found incidentally or with benign symptoms, corresponding to headache or pulsatile tinnitus. The Cognard classification also characterizes lesions based on the pattern of venous drainage, with added detail relating to the architecture of venous drainage in higher-grade lesions. Cognard sort I fistulas have direct arterial-to-venous connection with totally anterograde venous sinus drainage, and are akin to Borden type I fistulas. However, an rising variety of patients at the moment are discovered asymptomatically owing to the elevated use of superior noninvasive cranial imaging. Low-grade lesions with out venous reflux (Borden I or Cognard I) have an annual danger of hemorrhage of 0%, however do have a 1. A, Lateral subtracted angiogram of the left vertebral artery demonstrating a Borden sort I dural arteriovenous fistula of the left transverse sinus.
Specifications/Details
A erectile dysfunction causes tiredness viagra vigour 800 mg buy mastercard, Three-dimensional angiography demonstrates a ruptured left posterior communicating artery aneurysm with a big daughter sac in a 30-year-old lady new erectile dysfunction drugs 2013 viagra vigour 800 mg buy. Note the origin of the posterior speaking artery close to the neck of the aneurysm impotence nerve damage purchase viagra vigour 800 mg free shipping. The posterior speaking artery arises from the proximal neck and is seen overlying the aneurysm in this projection (arrowhead) erectile dysfunction at the age of 21 viagra vigour 800 mg cheap mastercard. C, Pretreatment native projection with balloon microcatheter across the neck of the aneurysm (arrowheads) and distal marker of the microcatheter throughout the dome of the aneurysm (arrow). Clipping of ophthalmic aneurysms typically requires drilling of the anterior clinoid course of and/or optic strut to utterly delineate the aneurysm neck. Additionally, the proximity of the ophthalmic artery to the optic nerve could complicate the exposure and/or placement of the aneurysm clip. For these reasons, embolization of ophthalmic artery aneurysms may symbolize a greater alternative to surgical therapy. Although several research have demonstrated the relative safety of proximal occlusion of the ophthalmic artery origin, the danger of monocular imaginative and prescient loss ought to prompt a consideration of surgical treatment. Many of the strategies discussed previously may be employed in the treatment of those aneurysms. This difficulty could also be obviated by means of steam-shaped, preshaped, or deflectabletip microcatheter. Slow and deliberate inflation of the balloon can scale back the likelihood of this phenomenon. Electrophysiologic monitoring could be of assistance in lessening the chance and allow for deflation of the balloon and reestablishment of blood flow to restore perfusion. With the balloon microcatheter absolutely inflated, coil embolization of the aneurysm can proceed in an easy manner. These aneurysms are sometimes recognized throughout a workup for headaches and can be associated with debilitating ipsilateral retro-orbital ache. Fortunately, sufferers with ruptures of aneurysms inside the protected cavernous sinus more frequently present with problems of a direct carotid artery�cavernous sinus fistula than life-threatening subarachnoid hemorrhage. Carotid artery�cavernous sinus fistulas, nevertheless, can result in progressive lack of vision and/or diplopia, meriting urgent therapy. Similarly, these aneurysms are often extensive necked on the area of the bifurcation and require adjuvant strategies earlier than one can safely proceed with coil embolization. The balloon reworking technique may be notably nicely suited to these lesions. Highly compliant balloons may be partially herniated into the aneurysm neck to guarantee protection of the anterior cerebral and middle cerebral arteries during therapy. Compromise of those branches by impingement from the coil mass may find yourself in vital ischemic or thromboembolic issues. Aneurysms in this territory do current some challenges for the endovascular neurosurgeon. It could additionally be tough to obtain a sufficiently clear working angle that delineates the aneurysm neck and the mother or father vessel and branches. The distal location might make navigation to the aneurysm challenging in its personal right, and tortuous vasculature might preclude profitable catheterization. The measurement of the vessel on this distal location additionally complicates the use of adjunctive methods. Distal Vertebral (V4) and Posterior Inferior Cerebellar Artery Aneurysms Treatment of aneurysms of the posterior circulation is also particularly difficult, and which management is optimal is open to some controversy. The endovascular and surgical approaches to therapy contain both reconstructive and deconstructive techniques. In the setting of a subarachnoid hemorrhage, the affected person often presents with a devastating medical image, with potential cardiac involvement and even myocardial infarction, given the shut proximity to the brainstem. V4 phase aneurysms are also notably vulnerable to rerupture, with charges starting from 30% to 70% within the medical literature. Therefore deconstructive techniques, both surgical or endovascular, are sometimes employed in this very dangerous group of aneurysms. If the origin of either of those vessels is included into the aneurysm, only a reconstructive strategy ought to be thought-about to maintain perfusion of critical buildings, together with the brainstem and spinal wire. In this occasion, strong consideration must be given to reconstructive surgical treatment if no other endovascular approaches are available. Basilar Artery, Superior Cerebellar Artery, and Posterior Cerebral Artery Aneurysms Aneurysms involving the basilar trunk are sometimes massive or big, and fusiform or dolichoectatic in nature, making either endovascular or surgical therapy significantly harrowing. Treatment often entails the use of multiple, telescoping stents, flow-diverting stents or deconstructive strategies. As in previous examples, 3D angiography is crucial for determining appropriate working angles to delineate the relationship of the aneurysm with the parent vessel. While relatively simply accessed with microcatheters, surgery typically entails intensive skull base approaches with vital microsurgical dissection to even obtain a meager working hall. If the vertebral artery is both particularly tortuous or smaller in caliber, then bilateral catheterization of the vertebral arteries with two smaller information catheters may be required. Numerous endovascular methods have been developed to treat wide-necked and other difficult aneurysms in this location. A, Left vertebral artery angiogram demonstrates a small, narrow-necked, basilar tip aneurysm in a 75-year-old lady presenting with subarachnoid hemorrhage. B, Magnified native projection after balloon-assisted coil embolization demonstrates lucencies inside the coil mass. C, Final working-angle projection demonstrates a Raymond 2 occlusion with small residual filling along the best neck region of the aneurysm. As such, they require adjuvant methods, similar to balloon reworking or stent-assisted coil embolization, regardless of the small caliber of the artery at this location. Navigation of those units might require a microcatheter trade to obtain the initial access with a smaller, extra supple microcatheter and wire previous to profitable positioning of a balloon microcatheter or a suitably sized microcatheter for deployment of a stent. Babiker and colleagues81 used finite component modeling to examine the consequences of coil deposition on aneurysmal hemodynamics. They created two idealized spherical, basilar-tip aneurysm models, one with a narrow-neck configuration with a dome-toneck ratio of 1. Additionally, they have been capable of mannequin the position of one coil and 5 coils into the aneurysms from numerous microcatheter positions, as nicely as with a simulated balloon microcatheter. The coils modeled included complicated and helical bare platinum coils in 4-mm � 8-cm and 2-mm � 2-cm sizes for framing and filling, respectively. With placement of the framing coil, the coil packing density was calculated at 19%, whereas a 33% packing density was achieved after deployment of four filling coils. In their fashions, greater packing density resulted in bigger variations in the mean intra-aneurysmal velocity magnitude than in other elements investigated (flow price, neck size, coil design). Furthermore, the percentage reductions within the imply intraaneurysmal velocity magnitudes have been constantly larger in the narrow-necked aneurysm than within the wide-necked aneurysm at each low and high coil packing densities within the low-flow state, whereas the distinction was significant in the only narrow-necked aneurysms with excessive coil packing density in the high-flow state. Babiker and colleagues81 also noted a considerable impact on maximum intra-aneurysmal stress and maximum wall sheer stress from aneurysm neck size. Regardless of coil packing density, the typical increase in maximum intra-aneurysmal strain was lower and the discount in maximum wall sheer stress was higher in the narrow-necked mannequin than in the wide-necked model in the high-flow state. In these fashions, sufferers with untreated aneurysms demonstrated high-velocity regions on the influx zone and the distal wall. Overall, the move velocity throughout the aneurysm and the wall shear stress decreased with progressively rising coil packing density. Additionally, the influence of coil configuration within the aneurysm was negligible when coil packing density approached 30%. Using a spherical sidewall aneurysm along a curved segment of artery and a helical coil mannequin, they decided the changes in aneurysmal hemodynamics with numerous framing coil orientations. The largest lower in the intraaneurysmal volume circulate was obtained with coil loops working parallel to the father or mother artery, followed by a transverse orientation, and at last orthogonal orientations. There have been solely incremental enhancements in volume flow with placement of second and third coils. Additionally, coiling was noted to induce vital reductions within the wall shear stress at the inflow zone of the aneurysm and in addition shielded the parent artery distal to the influx zone towards shear forces. The fundamental understanding of the pathophysiology of cerebral aneurysms has modified considerably over time as researchers have uncovered the relationship between the biochemical and biomechanical factors that result in aneurysm formation and progression. However, as practitioners have developed extra expertise with this new technology, the off-label use of those gadgets has expanded. Additionally, their use has in contrast very favorably to stent-assisted coil embolization of cerebral aneurysms in some stories. Given these results, these investigators judged that the indications to be used of flow-diverting stents could probably be expanded to embody a wider vary of cerebral aneurysms.
Syndromes
- Starting menopause after age 50
- Stomach pain
- Tissue expansion is used for breast reconstruction, as well as for skin that has been damaged due to birth defects and injuries. A silicone balloon is inserted beneath the skin and gradually filled with salt water. This stretches the skin, which grows over time.
- Fever
- Shaking of arms, head (tremor)
- Complete physical exam
Related Products
Additional information:
The oblique airplane offers stability for fixation on the time of closure and also serves to prevent damage to the temporomandibular joint erectile dysfunction for women 800 mg viagra vigour purchase visa, which is on the inferomedial surface of the zygomatic root erectile dysfunction nicotine purchase viagra vigour 800 mg overnight delivery. Some surgeons choose to perform this osteotomy with two perpendicular cuts erectile dysfunction exam video buy 800 mg viagra vigour overnight delivery, offering more secure seating for the zygoma throughout ultimate fixation erectile dysfunction help generic 800 mg viagra vigour mastercard. The second and third cuts divide the zygomatic bone above the malar eminence: the second cut extends from the inferolateral margin of the zygomatic bone halfway to the lateral orbital rim, and the third reduce begins throughout the orbit- with the noticed blade in the inferior orbital fissure-and extends posteriorly and laterally to join the end point of the second minimize. The inferior orbital fissure may be troublesome to visualize and will as a substitute be palpated with a small dissector earlier than the third reduce. The fourth osteotomy is made within the sagittal plane via the medial orbital roof, simply lateral to the supraorbital notch. The frontal dura is usually retracted slightly and protected with Telfa dressing before this cut. Telfa strips can also be positioned between the globe and orbital roof to protect the eye. The fifth minimize traverses the posterolateral orbital roof in a medial-to-lateral course, roughly 2 to three cm posterior to the internal table of the frontal bone, ending laterally in the sphenoid ridge. The ultimate cut divides the lateral orbital wall from the inferior orbital fissure (where the saw blade is placed initially: outside the orbit) to the top point of the fifth reduce in the sphenoid ridge. After these osteotomies are full, the orbitozygomatic unit is eliminated en bloc. Further bone removing then proceeds with a high-speed drill, with which the remnants of the orbital roof, lateral orbital wall, and medial sphenoid wing (the portion lateral to the superior orbital fissure) are eliminated. The inferior margin of the squamous temporal bone can also be usually eliminated with a drill. This flattens the ground of the center cranial fossa and allows the temporal lobe to be mobilized posterolaterally, if essential, after sylvian fissure dissection is complete. Orbitozygomatic method for aneurysms in the basilar trunk and posterior cerebral artery. Bur holes and osteotomies are represented by yellow circles and the craniotomy by blue dashed line. Positioning Patient positioning is equivalent to that described for the pterional craniotomy, although some surgeons advocate for a larger diploma of contralateral head rotation (30-60 degrees, as opposed to 15-45 degrees for the standard pterional craniotomy). SkinandSoftTissueDissection the pores and skin incision and soft tissue dissection are additionally much like those described for the pterional craniotomy, with several minor exceptions. The harvesting of a vascularized pericranial graft may be suggested as a end result of the probability of violating the frontal sinus could additionally be slightly higher with an orbitozygomatic craniotomy than with a regular pterional method. Subfascial dissection of the temporalis muscle and fascia is also usually most well-liked, and the fascia of the temporalis muscle is mobilized more anteriorly in this case, over the lateral orbital rim, where the temporalis fascia turns into steady with the periorbital tissues. The periorbita is then often dissected freed from the lateral orbital wall and superior orbital roof, toward the orbital apex, to prepare for orbital osteotomies. In this case, nevertheless, the dural flap is centered over the orbit somewhat than the pterion, and dural tacking sutures are used to gently depress the globe and periorbita out of the operative corridor. CraniotomyandBoneDissection Various strategies have been proposed for bone elimination in the course of the orbitozygomatic method, together with removal of the orbitozygomatic unit as one piece along with the cranial flap, removal of the orbitozygomatic unit independently of the cranial flap, and removal of a modified fronto-orbital unit alone without the zygoma. The "two-piece" orbitozygomatic approach is often preferred for its simplicity and is described as follows. Anterior Interhemispheric Craniotomy the anterior interhemispheric strategy allows entry to aneurysms of the pericallosal artery (PcaA), a department of the anterior cerebral artery. These aneurysms lie within the midline, deep to the falx, within the interhemispheric fissure, simply superior to the corpus callosum. A, Interhemispheric approach for aneurysms in the pericallosal and callosomarginal arteries. Bur holes are represented by yellow circles and the craniotomy by blue dashed line. B, Interhemispheric method: intracranial view of aneurysm within the pericallosal artery after craniotomy. Positioning Patient head positioning often differs barely relying on the placement of the PcaA aneurysm. For each proximal and distal PcaA aneurysms, the patient is placed supine, but the head is often in a neutral position with the neck barely extended for proximal PcaA aneurysms (those originating from the A3 phase of the anterior cerebral artery), whereas the top is often turned 90 levels to the proper (with a large roll under the left shoulder) for aneurysms of the distal PcaA (A4 or A5 segments of the anterior cerebral artery) to permit gravity to aid in retraction of the right hemisphere. SkinandSoftTissueDissection A right-biased bicoronal incision is often used, beginning at the root of the zygoma on the best and lengthening to the left superior temporal line. The surgeon should rigorously keep away from violating the pericranium as a result of harvesting a pericranial graft could also be essential to repair any frontal sinus defects which will occur. [newline]This must be situated two-thirds anterior and one-third posterior to the coronal suture, with the anterior facet of the incision just behind the hairline and the medial aspect of the incision just crossing the midline, so that the superior sagittal sinus may be uncovered. Exposure of the superior sagittal sinus permits the dura to be opened and mirrored immediately adjoining to the sinus, which improves visualization of and manipulation inside the interhemispheric fissure with out the impediment of overlying bone. The craniotomy could additionally be performed with a single bur gap placed at the posterior side of the craniotomy, simply to the right aspect of the sagittal sinus. The superior sagittal sinus and excessive bleeding from emissary veins must be prevented. The craniotomy cuts that cross the sinus should be performed with care and solely after the dura in the space is dissected free of the overlying bone with a Penfield No. In youthful sufferers, the bone flap may be elevated in a single piece, typically with out damage to the sinus. In older patients or those with attenuated dura adherent to the overlying internal desk of bone, it may be preferable to bisect the bone flap immediately to the proper of the sagittal sinus, after which the sagittal sinus dura could also be dissected freed from the overlying bone under direct visualization before the bone flap that overlies the sinus is elevated. The inside desk of frontal bone may be drilled flat in the inferior midline to aid in visualization of the anterior cranial fossa flooring. This could additionally be essential for obtaining proximal management in very proximal PcaA aneurysms. To preserve veins that are especially adherent to the dura, the dura could additionally be incised on either side of the vein. A 3-cm gap between bridging veins is regularly found or developed in any case, and infrequently no bigger gap than this is essential for further dissection and aneurysm clipping. When the head is rotated 90 levels, nevertheless, gravity pulls the ipsilateral cerebral hemisphere away from the falx, and thus additional retraction of the mind is seldom wanted. The majority of PcaA aneurysms are positioned 1 to 2 cm anterior to the part of PcaA initially encountered, and thus dissection is carried anteriorly alongside the artery until the aneurysm is visualized. Subtemporal Craniotomy As mentioned previously, many aneurysms of the basilar bifurcation, proximal posterior cerebral artery, and superior cerebellar arteries are accessible through the pterional method. Positioning the patient is typically positioned within the park bench place; the dependent arm is held off the table in a padded sling. A right-sided strategy is commonly preferred unless aneurysm structure or different elements favor a left-sided method. Bur holes are represented by yellow circles and the craniotomy by dashed blue line. SkinandSoftTissueDissection the skin incision classically described by Peerless and Drake5 is linear and perpendicular to the zygoma, being easily converted to a frontotemporal or posterior temporal flap if needed. The incision begins 1 cm anterior to the tragus and is carried to the lower border of the zygomatic arch. The temporalis muscle and fascia are then divided in the aircraft of the incision down to the extent of the zygomatic arch. The muscle and fascia are then removed from their zygomatic arch attachments posteriorly, and the temporalis fascia is dissected bluntly away from the arch 1 to 2 cm anteriorly to avoid harm to the facial nerve. In cases during which the vertical distance between the tentorial edge and the posterior cerebral artery is particularly extensive, some authors advocate for partial resection of the parahippocampal gyrus (which might obscure the upper 33%-50% of the ambient cistern) to help in visualization and dissection. For aneurysms of a high-riding bifurcation of the basilar artery, some authors have advised partial resection of the zygomatic arch,6-8 which is claimed to improve visibility of the interpeduncular cistern and reduce the need for temporal lobe retraction. Modifications As with all of the cranial approaches described, certain modifications could also be made to tailor each strategy to the structure and anatomic traits of each particular person patient and aneurysm. For the subtemporal craniotomy, certain modifications may be required in order to present better publicity and maneuverability. Particularly low-lying aneurysms of the basilar artery (those positioned between the vertebrobasilar junction and the origin of the anterior inferior cerebellar artery), for example, may be troublesome to visualize or ligate by way of the standard subtemporal strategy. Others retract the tentorial edge by suturing it to the dura of the center cranial fossa. Dissection proceeds beneath the temporal lobe in a path nearly perpendicular to the sagittal plane.
Usage: gtt.
Deep arteriovenous malformations within the basal ganglia short term erectile dysfunction causes 800 mg viagra vigour order otc, thalamus erectile dysfunction venous leak treatment best 800 mg viagra vigour, and insula: multimodality management erectile dysfunction cure video discount viagra vigour 800 mg amex, affected person choice erectile dysfunction diagnosis purchase viagra vigour 800 mg line, and outcomes. Radiosurgery facilitates resection of mind arteriovenous malformations and reduces surgical morbidity. Changing scientific and therapeutic developments in tentorial dural arteriovenous fistulas: a systematic review. Results of mixed stereotactic radiosurgery and transarterial embolization for dural arteriovenous fistulas of the transverse and sigmoid sinuses. Safety and efficacy of microsurgical remedy of beforehand coiled aneurysms: a scientific review and meta-analysis. Neurosurgical management of cerebral aneurysms following unsuccessful or incomplete endovascular embolization. Treatment for brain arteriovenous malformation within the 1998-2011 interval and evaluate of the literature. Multimodality treatment of brain arteriovenous malformations with microsurgery after embolization with Onyx: single-center experience and technical nuances. Alexander West Traumatic intracranial aneurysms could additionally be the result of both penetrating or nonpenetrating trauma. Traumatic cerebral aneurysm has even been reported in the pediatric affected person in a case of shaken baby syndrome. South Africa has provided much of the literature with regard to low-velocity injuries, which are prevalent in this region; stab wounds to the brain account for as much as 6% of all trauma admissions. The aneurysm may end up instantly from harm to an underlying vessel by depressed bone fragments or dispersion of bone fragments attributable to a penetrating harm. With regard to missile injuries, conflicts in Lebanon, Iraq, and Iran have demonstrated aneurysm formation in zero. The incidence is related to velocity: lower velocity shrapnel accidents trigger the next incidence of aneurysm formation than do higher velocity bullet accidents. The aneurysm confirmed lack of the internal elastic lamina and easy muscle in the media and a rise in size of the adventitia. True aneurysms reveal outpouching of the intima through the media, together with fragmentation of the interior elastic membrane; as a result, the aneurysm wall consists of intima separated from the adventitia by fibrous tissue. In distinction, false aneurysms, which constitute the majority of traumatic intracranial aneurysms, are basically contained hematomas with disruption of all three layers of the vessel wall. The more inclusive term pseudoaneurysm is often used to describe aneurysms associated to trauma. Traumatic aneurysms happen distally in the vascular tree, in contrast to the proximal bifurcation web site of saccular aneurysms. The anterior circulation is most frequently affected; the peripheral branches of the center cerebral artery are essentially the most frequent web site, followed by branches of the pericallosal vessels. For instance, traumatic aneurysms are 14 occasions more more probably to develop with shrapnel injuries than with bullet accidents, which are of higher velocity. Bullets with higher velocity and thus higher kinetic injury are extra likely to rupture a vessel than merely harm the wall. Traumatic fistulas are irregular connections between the intracranial arterial and venous circulation that may occur after extreme or even comparatively minor nonpenetrating trauma. On occasion, they result from penetrating trauma, the most typical location being the cavernous sinus with the formation of a carotid-cavernous fistula: an acquired communication between the intracranial carotid artery and the cavernous sinus. In this sort of fistula, the irregular communication between the intracranial arterial and venous circulation lies within the dura. The findings are from a patient who suffered a severe traumatic mind harm with bilateral skull fractures that necessitated evacuation of a subdural hematoma on the best. A, Sagittal computed tomographic angiogram exhibiting a largely thrombosed traumatic aneurysm within the left frontal area. B, Cerebral angiogram demonstrating a traumatic aneurysm within the distal left middle cerebral artery pial artery (arrow). Much less frequent is the formation of dissecting aneurysms after nonpenetrating trauma. They might happen at the cranium base and contain the interior carotid artery and vertebrobasilar system. Dissecting aneurysms occur when harm to one or more of the arterial layers allows blood to force its way between the vessel layers alongside a dissection plane9 and create an intimal flap. Dissections often originate within the media or adventitia, and on this scenario, rupture could happen by way of the adventitia, with resultant subarachnoid hemorrhage or pseudoaneurysm formation. In aneurysms involving the peripheral vascular tree, neurological deterioration is delayed, normally occurring within 3 weeks of the injury. In sufferers with aneurysms involving the infraclinoid internal carotid artery, severe and life-threatening epistaxis may be the initial occasion if the arterial injury communicates with a sphenoidal sinus fracture. Establishing the diagnosis is necessary as a outcome of patients with multiple episodes of hemorrhage or neurological insults do poorly. Penetrating trauma is commonly associated with intracranial hemorrhage, and among patients with missile accidents, concomitant intracerebral hemorrhage is present in 39% to 80%,34 and 26% have subdural hemorrhages. Cerebral angiography is the "gold commonplace" of diagnostic imaging in all circumstances of penetrating trauma. Computed tomographic angiography may additionally be performed as a screening examine and will reveal an unsuspected aneurysm. The second angiogram must be obtained no less than 2 to three weeks after damage, and it could be argued that a third angiogram must be obtained 6 weeks after injury. Traumatic internal carotid artery aneurysms occur comparatively incessantly in youngsters (5% to 39% of pediatric intracranial aneurysms) and have a tendency to bleed weeks after the preliminary trauma. Blood within the basilar cisterns after closed-head trauma in youngsters should prompt both quick and follow-up angiographic evaluation. A, Excised traumatic pial aneurysm showing extension into the dura and an underlying cranium fracture. The stains present loss of the internal elastic lamina, loss of easy muscle, a really thickened tunica adventitia, and thrombus. C, High-power view displaying lack of the internal elastic lamina structure and modifications in the media and adventitia. In a patient with a large, life-threatening intracerebral hemorrhage, fast removal of the hematoma is required, and the vascular harm needs to be handled. The end result is generally worse after secondary brain insults, and so it may be very important diagnose a traumatic aneurysm early; remedy of those aneurysms could also be complicated. Surgery has been the normal method of remedy; ligation of the carotid artery within the neck has traditionally been used for traumatic aneurysms involving the intracranial inside carotid artery. This finding has not been supported by all authors, and most recommend that when a traumatic aneurysm has been recognized, therapy ought to be instituted. The principle of managing a saccular aneurysm is to exclude the aneurysmal bulge from the circulation by clipping or coiling, with preservation of the mother or father vessel and its branches. In very distal vessels, the chance of an ischemic occasion after resection of the aneurysm is low, and these aneurysms are often excised with no problems. In addition to a vascular bypass, an interposition graft with the superficial temporal artery can be placed. Endovascular strategies have advanced since the mid-1980s, and intravascular embolization and occlusion now play a bigger role within the management of intracranial traumatic arterial injuries. With carotid accidents, options embrace endovascular occlusion of the carotid artery at the skull base, a bypass graft, or in rare cases, direct restore of the vessel. Because most pseudoaneurysms secondary to penetrating harm are distal, endovascular occlusion is often most popular to surgical sacrifice as a result of the location could be recognized simply. Obtaining distal access to the vessel distal to the aneurysm could additionally be difficult as a end result of concomitant dissection could make it tough to establish the true lumen. In addition, tortuosity of the veins may make it tough to information the catheter to the distal vessel without penetrating the aneurysm. This helps management the distal migration of the embolic materials in such a means that the embolization could be terminated as quickly as a small section of the vessel distal to the aneurysm is embolized. One of the new technologic advancements in treatment of intracranial aneurysms has been the event of flowdiverting stents.
Tags: viagra vigour 800 mg purchase overnight delivery, viagra vigour 800 mg cheap fast delivery, 800 mg viagra vigour purchase free shipping, viagra vigour 800 mg order with visa, 800 mg viagra vigour discount visa, generic viagra vigour 800 mg online, 800 mg viagra vigour buy mastercard, viagra vigour 800 mg on-line, viagra vigour 800 mg buy with amex, 800 mg viagra vigour purchase otc, 800 mg viagra vigour purchase mastercard, 800 mg viagra vigour buy fast delivery, viagra vigour 800 mg cheap visa, cheap 800 mg viagra vigour otc, viagra vigour 800 mg purchase mastercard, discount 800 mg viagra vigour fast delivery
9 of 10
Votes: 220 votes
Total customer reviews: 220
Customer Reviews
Milok, 58 years: A single-center case series from 2014 in which patients had been handled with intent to treatment demonstrated a rate of 11% in 827 procedures. Cerebral microbleeds are frequent in infective endocarditis: a case-control examine. The visualized infracallosal or precallosal segments of the pericallosal artery can then be ready for temporary clipping.
Jens, 46 years: This is to ensure that aneurysms identified earlier than surgical procedure recede (or no much less than stay "safe"). Diaz and coworkers89 reported surgical treatment (vertebral endarterectomy, vertebralto carotid transposition or grafting) in eleven of 12 sufferers with illness extending into the middle vertebral artery. Of the 529 sufferers randomized to preliminary conservative administration, 26% underwent eventual surgical evacuation.
Marcus, 38 years: Rupture of intracranial aneurysms throughout treatment with Guglielmi removable coils: incidence, outcome, and danger factors. Treatment of large intracranial aneurysms with saphenous vein extracranial-to-intracranial bypass grafting: indications, operative technique, and results in 29 patients. Rapidly progressive hippocampal atrophy: proof for a seizure-induced mechanism.
Asaru, 59 years: E, A linear pial incision over the superficial side of the angioma and intramedullary hematoma permits access to them for excision with minimal manipulation of the spinal wire. Cerebral hemodynamic impairment after aneurysmal subarachnoid hemorrhage as evaluated utilizing transcranial Doppler ultrasonography: relationship to delayed cerebral ischemia and scientific consequence. Nowadays, the extra common scenario by which a multimodality method to intracranial aneurysms is utilized is after failure of main endovascular or surgical treatment.
Cyrus, 33 years: Multiple cavernous malformations of the brainstem also can complicate evaluation, and only patients with signs clearly attributable to a single lesion should be supplied intervention in such conditions. As an example, when embolization is mixed with surgical procedure, the value of total in-hospital therapy is 1. More recently, enhancements in technology and approach have enabled the acquisition of direct and oblique hemodynamic measurements and useful and physiologic information, as well as visualization of intravascular pathology.
