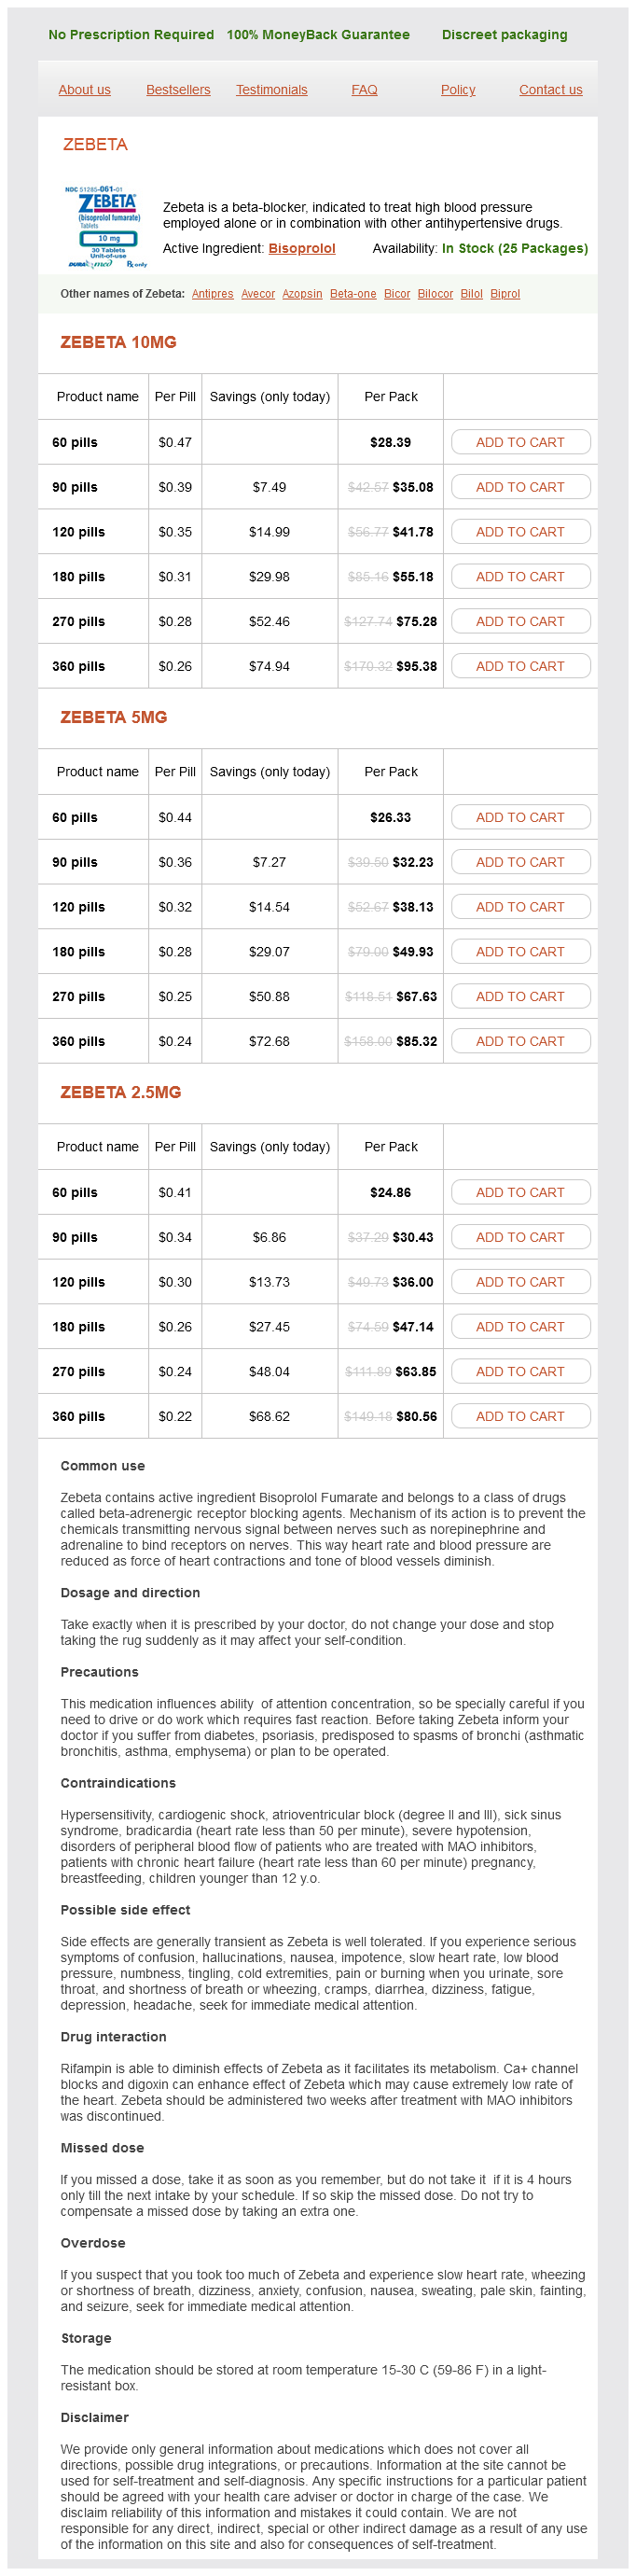
Zebeta 10mg
- 60 pills - $28.39
- 90 pills - $35.08
- 120 pills - $41.78
- 180 pills - $55.18
- 270 pills - $75.28
- 360 pills - $95.38
Zebeta 5mg
- 60 pills - $26.33
- 90 pills - $32.23
- 120 pills - $38.13
- 180 pills - $49.93
- 270 pills - $67.63
- 360 pills - $85.32
Zebeta 2.5mg
- 60 pills - $24.86
- 90 pills - $30.43
- 120 pills - $36.00
- 180 pills - $47.14
- 270 pills - $63.85
- 360 pills - $80.56
Zebeta dosages: 10 mg, 5 mg
Zebeta packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 899
Only $0,24 per item
Description
These exams include the completely mounted radiation monitor contained in the remedy room and its remote indicator, handheld radiation monitor, affected person viewing and communication techniques, door interlock, timer termination of exposure, treatment pause and emergency stops, and a take a look at of all required beam status indicators and alarm indicators blood pressure fluctuation causes 5 mg zebeta discount free shipping. These runs include a sectorpositioning verify to verify proper functioning of the automated collimator setup blood pressure medication and weight loss buy zebeta 5 mg overnight delivery. Strategies for Optimal Frame Placement for the Leksell Gamma Knife Model 4C To target lower lesions (skull base tumors, acoustic tumors, cerebellar metastatic lesions in general), the body is positioned decrease by putting the ear bars within the high holes of the earpieces on the Leksell G body prehypertension que es zebeta 5 mg low cost. For higher lesions (sagittal sinus meningioma, metastases excessive within the frontal or parietal lobe), the body is positioned larger by putting the ear bars within the bottom holes of the earpieces arteria nasi externa zebeta 5 mg cheap online. For anterior targets (anterior frontal lobe tumors, cavernous sinus tumors, sellar lesions and lesions anterior to the sella, anterior temporal lesions), the body is shifted ahead by placing the earpieces posteriorly on the base ring of the frame. For anterior targets, short posterior posts are preferred to avoid collision of the posterior post/pin assembly with the collimator helmet. To goal posterior lesions (occipital lobe tumors, transverse sinus tumors, cerebellar lesions), the frame is shifted backward by positioning the earpieces forward. The Application of the Stereotactic Guiding Device For Gamma Knife radiosurgery, appropriate stereotactic body placement is the initial important facet of the procedure. Before frame placement, the radiosurgery staff should review the preoperative photographs and discuss the optimum body placement strategy. The preoperative photographs must be saved in plain view whereas applying the pinnacle body. Effort must be made to keep the lesion as close to the middle of the body as possible. The anterior posts are positioned as little as potential on the supraorbital area to avoid collision of the frontal post/pin meeting with the collimator helmet. For radiosurgical planning, a better gamma angle (120 to 140 degrees) is used if a collision is detected at the default angle of 90 degrees. To reach lateral targets (lateral metastases, convexity tumors, far lateral tumors), the body is shifted laterally (right or left) toward the lesion. While shifting the body laterally, it is very important be positive that enough space is available on the contralateral aspect to allow positioning of the fiducial box on the base ring of the body. Alternatively, T1-weighted sagittal scout images (3-mm-thick slices 1 mm apart) utilizing a spin echo pulse sequence may be obtained for localization of lesions. An extra 3D T2 sequence can be utilized for vestibular schwannomas to visualise the cochlea. A half dose of paramagnetic contrast material is usually given to picture pituitary adenomas. For thalamotomy planning, an extra quick inversion restoration sequence is carried out to differentiate basal ganglia from white matter tracts. Patients with brain metastases obtain a double dose of distinction agent, and the entire brain is imaged in 2-mm slices to determine all the lesions. Tight becoming of the adaptor might trigger neck discomfort, especially throughout a protracted treatment. The frame cap verify offers information about the geometry of all stereotactic body components, together with posts and screws, as nicely as details about patient head geometry in relation to the therapy planning system. This information is needed for prediction of potential collisions or shut contact with the Gamma Knife collimator system. Techniques of Stereotactic Imaging Aside from body application, the following most important side of radiosurgery is correct imaging of the target. Stereotactic Magnetic Resonance Imaging the highlights of stereotactic imaging embody optimal distinction between regular and abnormal tissues, in addition to excessive spatial resolution, short scan time, and thin slices in order that correct target localization may be achieved. At our establishment, a high-resolution, gadolinium-enhanced, 3D localizer (T2* images) image sequence is used first to localize the tumor in axial, sagittal, and coronal photographs. This sequence (3-mm-thick slices 2 mm apart) takes simply 45 seconds for 11 axial, eleven sagittal, and eleven coronal slices. Before eradicating the angiography catheter, the photographs ought to be reviewed to be positive that all the fiducials are seen on the photographs. Digital subtraction strategies, regardless of the potential for radial distortion error, provide passable spatial accuracy. Image accuracy is checked for each picture sequence by comparing the recognized frame measurement with image measurements, along with the gap from the posterior fiducials to the middle fiducials. The measurements are once more checked and compared with the identified frame measurement and likewise the gap to the middle fiducial to verify the absence of any distortion during image transfer. If a special gamma angle is used, the plan have to be rechecked for accuracy and adjusted if needed. Because simply 4-, 8-, and 16-mm collimators are available, solely a mixture of these three different collimators can be used to cover the complete goal volume. This computerized procedure will present options to block selected sectors for defense of volumes defined as important constructions. Different levels to minimize back the dose delivered to important constructions could be selected. The remedy planning system then mechanically calculates which sectors ought to be blocked for each particular person shot. One ought to be aware that every blocking will considerably enhance complete exposure time. The third approach is to make use of isocenters composed of different beam diameters, sectors, and blocked sectors. Any pattern of sectors, including 4-, 8-, and 16-mm collimators and blocks, could be generated. This can help significantly in shaping the dose distribution, especially for irregular volumes. For instance, it is extremely straightforward to design an elongated dose distribution by utilizing a mixture of small and huge collimators. Composite shots also can scale back the dose delivered to important buildings in shut proximity to the handled target quantity. Use of composite shots consisting of any sectors, a mixture of various collimators, or blocking is freed from time penalty as a outcome of all sector place changes are done routinely and take less than 5 seconds. Determination of Target Volume or Volumes Target dedication is a vital step in making a conformal plan. However, for brand spanking new centers, especially those by which physicists assume the preliminary accountability for planning, target definition turns into an essential first step. By defining goal quantity and volumes of crucial buildings, higher evaluation and quantification of the treatment plan may be achieved. Various parameters similar to dose-volume histograms for the target quantity and critical buildings and conformity indices can be obtained. Techniques of Conformal Dose Planning Leksell Gamma Knife Model 4C In the process of treatment planning, a number of methods can be utilized. Another approach is to begin at the bottom or top and construct from the start line. Beginners also can use the inverse dose-planning algorithm (Wizard) to create a plan after which optimize it manually. When planning a therapy with the use of trunnions solely, one may tend to make use of bigger collimators (especially for bigger lesions) to scale back the time and maximize coverage of the goal. For example, for a medium-sized acoustic tumor, in the trunnion mode one would possibly use a few 14-mm collimators for virtually all of the tumor and some 4-mm collimators for the intracanalicular portion of the tumor. As lengthy because the isocenters are in shut proximity to one another, the software program would routinely put them into the identical treatment run and the patient would move from one set of coordinates to the following until all isocenters of 1 collimator size were handled. Other techniques can be used in planning, corresponding to using a steep (125 degree) gamma angle for posterior lesions (cerebellar or occipital) to keep away from frame collisions. Another technique available for single-isocenter lesions is to match the gamma angle to the angle of the target. In trunnion treatment, the x, y, and z coordinates of each isocenter are set manually and double-checked to keep away from error. The operator selects the run (a combination of isocenters of the identical beam diameter) that matches the collimator helmet on the Gamma Knife unit. After the clearance verify, the system prompts the surgeon to hold out place checks. The staff monitors the affected person and coordinates of the different isocenters on the management pc. In the longer term, more accurate imaging techniques, improved software program to deal with these images, and superior inverse planning software program will present better treatment and end in higher patient outcomes. Radiation-induced epilation because of sofa transit dose for the Leksell gamma knife mannequin C. First medical experience with the automated positioning system and Leksell gamma knife Model C.
CITRUS MEDICA LIMONUM (Lemon). Zebeta.
- How does Lemon work?
- What is Lemon?
- Dosing considerations for Lemon.
- Treating scurvy (as a source of vitamin C), the common cold and flu, kidney stones, decreasing swelling, and increasing urine.
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96546
This chapter describes the background and surgical follow of anterior instrumentation of the thoracic backbone blood pressure reading 400 zebeta 10 mg fast delivery. In the Seventies, advances in construct design were launched by Dwyer,4,5 Zielke,6 and colleagues heart attack zippo zebeta 5 mg fast delivery. The screwcable assemble of Dwyer and the screw-rod assemble of Zielke efficiently corrected scoliotic deformities arrhythmia journal cheap 10 mg zebeta free shipping. In the late Nineteen Seventies, Dunn developed a double-rod, double-screw assemble that offered adequate stability for anterior thoracolumbar reconstruction hypertension question and answers zebeta 5 mg without a prescription. Less optimal outcomes with an elevated incidence of postoperative issues have historically been related to posterior decompression for anterior metastatic illness. An anterior strategy offers a direct technique of addressing ventral pathology and reconstructing the backbone at the major website of instability. Important issues for applicable affected person selection include age, preoperative useful standing, presence of medical comorbid situations, life expectancy, and wish for tissue prognosis. The value of restoring neurological operate, such as ambulation or sphincter control, have to be judged on a person basis. Other considerations in deciding on patients for operative intervention include the sort of tumor, compromise of the spinal canal, extent of neurological deficits, degree of pain, and degree of instability. Adjuvant remedy similar to radiotherapy, chemotherapy, or hormonal remedy could also be indicated in particular circumstances. Additionally, nonoperative intervention stays an possibility for patients with steady myelopathy regardless of spinal cord compression. Neurological deterioration is uncommon after operative intervention for metastatic spinal illness. Perioperative mortality rates range from 6% to 8%, and general complication rates range from 8% to 11%. Spinal neoplasms could be manifested as pain, progressive deformity, or neurological deficits. Operative intervention is acceptable for tissue prognosis, neurological decompression, and spinal stabilization. Posterior fusion and fixation may be appropriate in the absence of a ventral deformity or anterior spinal canal compromise. Lesions producing ventral compression or vital biomechanical compromise of the anterior and middle columns are indications for an anterior approach. Previous reviews have documented higher outcomes with an anterior approach than with isolated posterior stabilization. Loss of the posterior pressure band may require supplementation with a posterior stabilization assemble. Patients with a whole spinal wire harm should still profit from spinal stabilization. In such circumstances, surgical stabilization optimizes the rehabilitation course of and presumably decreases the length of hospitalization. Exposure of the upper thoracic backbone is complicated by the complex anatomy of the superior mediastinum, presence of the great vessels, depth of exposure, and kyphotic angulation of the spine. A midline sternotomy can be utilized but typically necessitates the help of a thoracic surgeon. Pathology affecting the middle to lower thoracic spine (T5-10) can be accessed with either a posterolateral (lateral extracavitary) or anterolateral (retropleural thoracotomy) approach. For the thoracolumbar area (T10-L2), a thoracoabdominal method during which one of many approaches for the decrease thoracic backbone is mixed with a retroperitoneal strategy offers wonderful access. A extra intensive sternal-splitting approach is normally necessary for anterior entry to the decrease vertebrae, sometimes as much as the fourth or fifth thoracic vertebrae, or for patients with brief stout necks. These exposures ought to be carried out with the help of an skilled thoracic surgeon and are past the scope of this textual content. It is ideally suited to lesions with a significant anterior paraspinal extension, with or without a substantial intraspinal part. This method supplies a well-recognized publicity and orientation for neurosurgeons and in depth access to all three spinal compartments. In addition, circumferential stabilization of the backbone is feasible by way of a single incision. The lateral extracavitary approach is versatile and could be modified in accordance with the scale of the tumor, level of involvement, relationship to neural structures, and wish for spinal stabilization. Once anesthesia is induced, the patient is placed in a threequarter or full susceptible place. Rotating operative tables permit the patient to be turned during the procedure to gain increased visualization of the ventral spinal compartment. A variety of incisions can present entry through the lateral extracavitary strategy, together with midline, hockey stick, semicircular, and paramedian incisions. If a "hockey stick" kind of incision is used, enough caudal publicity is required earlier than the incision is prolonged laterally, or the caudal extent of the publicity will be restricted. Routine subperiosteal dissection of the paraspinal muscle tissue is carried out with a Cobb dissector and monopolar cauterization. The takedown is performed bilaterally if posterior publicity is required for laminectomy or instrumentation; otherwise, unilateral exposure is sufficient. The lateral limb of the "hockey stick" incision is opened by transecting the transversely oriented thoracic muscle tissue. The myocutaneous flap is elevated to expose the longitudinally oriented erector spinae musculature. An extended midline incision can present comparable entry with less musculoligamentous harm and doubtlessly an improved beauty result. Once the transversely oriented muscles are retracted, the lateral margin of the erector spinae is identified and dissected medially to show the underlying ribs. Surgery is usually reserved for kyphosis greater than 30 degrees, as well as radiographic evidence of progression of the deformity. Clinical indications for operative intervention embody intractable axial or radicular ache and progressive neurological deficits. At the thoracolumbar junction, instrumentation is important to withstand the dynamic biomechanical forces encountered at this degree. Most of those rare lesions could be resected successfully via a posterolateral approach without the addition of fusion and fixation. Mobilization of the erector spinae muscle permits access to the lateral spinal compartment. The longitudinal muscle mass is wrapped in a moist sponge to avoid desiccation and positioned medially or laterally to allow the surgeon to work on both aspect. Complete dissection of the vertebral components above and under the pathologic degree ensures adequate ventral publicity. The dorsal and lateral rib surfaces are exposed with a Cobb elevator as a lot as the articulation of the vertebral body. The ventral delicate tissue is dissected free in subperiosteal style with a Doyen rib dissector. The uncovered transverse process on the stage of the pathology, along with 6 to 8 cm of the corresponding rib, is then resected with a rib cutter and rongeur. The costotransverse and costovertebral joints are disarticulated and transected sharply. Resection of the rib head exposes the anterolateral surface of the backbone, including the pedicle and intervertebral foramen. Resection of 3 to four cm of the adjacent ribs can improve ventral publicity; nonetheless, extreme rib resection can lead to a flail chest deformity. Once the rib and transverse processes are eliminated, the neurovascular bundle is identified inside the endothoracic fascia, deep to the intercostal musculature. The segmental nerves above and at the stage of the pathology are dissected free and divided, with the proximal stump elevated medially toward the intervertebral foramen. Unlike the scenario on the lumbar levels, nerves on the thoracic levels can be sacrificed with out incurring a practical deficit. Once the nerve is free, the parietal pleura is displaced ventrally to provide access to the anterolateral spinal compartment.
Specifications/Details
Not all infections arrive within the backbone via an arterial route-transvenous dissemination may also happen, somewhat akin to metastasis of genitourinary and gastrointestinal malignancies to the spine heart attack jack heart attack order 10 mg zebeta. Gram-negative organisms such as Escherichia coli, Pseudomonas, Salmonella, Enterobacter, Klebsiella, Haemophilus, and Proteus are less frequent and could additionally be related to gastrointestinal or genitourinary sources of an infection prehypertension systolic blood pressure discount zebeta 10 mg otc. Care ought to be taken to process all material submitted for culture, each aerobically and anaerobically heart attack 86 years old 5 mg zebeta buy free shipping. Systemic indicators of an infection such as fever or an elevated leukocyte rely may be absent blood pressure questionnaire buy 5 mg zebeta with visa. Heusner described the medical evolution of epidural abscess in 4 phases: pain, radiculopathy, weak spot, and paralysis. Patients may be seen anywhere alongside a spectrum *See references 4, 15, 20, 22, 26, 28, 30, fifty one, sixty one, sixty three. The presence of systemic manifestations may herald bacteremia and is an opportune time to obtain blood for culture. Unusual traits of the again pain, such as a midline location over the thoracic or upper lumbar spine that worsens with recumbency, particularly at evening, and the association of a thoracic radiculopathy should immediate consideration of a nondegenerative cause of the pain. Neurological signs are extra commonly seen with infections of the cervical and thoracic spine than with infections within the lumbar region. The fee of development of infection and neurological deficits is variable- some infections are relatively indolent, whereas others can progress quickly and end in profound neurological deficits in just a matter of hours. When the an infection has a outstanding bone part, a gibbus deformity may be clinically obvious. A dermatomal level of sensory, motor, or combined deficits is common in patients with deficits. The examination is often in preserving with an acute spinal twine damage with bladder and bowel involvement. Measurement of postvoid bladder residual adopted by bladder catheterization offers an objective measure of the urologic dysfunction and prevents secondary damage of the detrusor muscle. Rarely, with relatively indolent infections, chronic compression of the spinal wire might occur and long-tract signs could additionally be present. Changes which might be seen on plain radiographs several weeks after onset of the infection increasingly consist of prevertebral and paravertebral delicate tissue volume, loss of disk top, trabecular erosion, and, eventually, destruction of the complete vertebral end plate on both facet of a disk. Vertebral collapse, lack of regular lordosis across the affected degree, and the development of a kyphotic deformity happen with advanced an infection. It is an excellent parameter to monitor in determining the response to therapy and should be measured at the preliminary evaluation even when the prognosis is already clear. Gallium binds to iron-binding proteins on the web site of irritation, whereas technetium reflects blood circulate to the bone. In comparison, scans utilizing white blood cells tagged with radionuclide are more particular for the detection of infection, however their sensitivity is far decrease. Chronic infections can sometimes lead to false-negative results with indium scanning. Various other potential peptide markers are being investigated to aid in early diagnostic imaging. Imaging should be carried out without and with the administration of paramagnetic contrast agents. Unenhanced T1-weighted images reveal a hypointense sign in the vertebral physique, especially on the end plates; the traditional hyperintense fat signal within the vertebral bone marrow is lost. T2-weighted imaging reveals excessive sign (edema) within the disk space and infrequently in the bone and paravertebral soft tissues. Bacteriologic Diagnosis the second element of the diagnostic analysis is bacteriologic characterization of the an infection. As famous earlier, the backbone may be hematogenously seeded from other websites of an infection such because the respiratory tract, urinary tract, or an endovascular supply. Cultures of urine and sputum should be carried out in sufferers with these potential sources. If the blood cultures are constructive, the causative organism is recognized in 25% to 59% of instances. A bigger bore needle that obtains a core of tissue might yield microbiologic results superior to that of aspirates of fluid from bone. The use of a nucleotome for percutaneous suction-aspiration of the infected disk space has additionally been described. In sufferers with neurological deficits, antibiotics must be withheld till specimens are collected intraoperatively. In a small number of instances, no organism may be cultured despite a quantity of makes an attempt. Once this risk is fairly excluded, empirical antibiotic remedy is the only possibility. Patients handled empirically with antibiotics need to be monitored closely to substantiate a response to the treatment being administered. Because the risk for bacterial endocarditis is especially high, sufferers should be examined for cardiac murmurs and evidence of embolization to the retina and the pores and skin. If endocarditis is suspected, echocardiography, preferably through a transesophageal route, must be carried out to search for valvular vegetations. Frequently, a cutaneous pyogenic lesion that represents the index location of the infection continues to be current when the patient is evaluated by a neurosurgeon. Patients also wants to endure assessment for risk factors responsible for the infection. In some cases of indolent an infection, the drug abuse might even have occurred a number of months previously. Infections can monitor alongside fascial planes adjacent to the infected vertebrae and end in psoas abscess, paraspinous muscle abscess, empyema, sympathetic pleural effusion, and retropharyngeal abscess. Although all patients want antibiotic remedy, the time period "medical administration" within the current context refers to using antibiotics with out planned surgical d�bridement at the web site of infection. In the past, the choice to undertake emergency surgical procedure was often made solely on the idea of an enhancing epidural part. The tenet has been that an epidural abscess constitutes a neurosurgical emergency. Entirely liquid "abscesses" are uncommon, and typically a phlegmon with minimal, if any, liquid abscess is seen. Such heterogeneity also applies to the medical manifestations of epidural collections-some produce quickly progressive neurological deficits, whereas others produce no deficits. Emergency surgical intervention should be thought of in all patients with neurological deficits, regardless of the period of the weak point, except the deficits are minimal. Surgical intervention for neurological deficits wants to deal with the location of the compressive lesion, such as ventral or dorsal to the spinal cord or cauda equina. Simplistic although this sounds, ignoring this principle may end in destabilization of an already compromised backbone, with worsening deficits. Finally, the various anatomic regions of the spine dictate the potential approaches available and the likelihood of postoperative instability. In the cervical spine, the surgical method usually coincides with the location of the compressive lesion. Certain circumstances might sometimes be somewhat tougher to distinguish with imaging alone. Involvement of the vertebral physique more than the disk house and the event of paravertebral abscesses quite early in the midst of the an infection recommend a tubercular somewhat than a pyogenic etiology. They can usually be differentiated from infection; a degenerated disk is usually dehydrated and due to this fact hypointense, whereas an contaminated disk is hyperintense on T2-weighted imaging. The presence of gasoline inside the disk, the vacuum disk phenomenon, is far more suggestive of degeneration than infection. Changes within the intravertebral vacuum clefts are seen as a consequence of spinal loading and unloading. T2-weighted imaging carried out immediately after the affected person lies supine on the scanner reveals a hypointense sign because of the presence of air, but as fluid enters the cleft, this sign becomes hyperintense. Although partial sternotomy or manubrial resection may provide adequate access in such circumstances, technical challenges with d�bridement and reconstruction of the anterior column remain. Furthermore, a kyphotic deformity produced by the an infection can make entry to the apex of the deformity through an anterior approach tougher.
Syndromes
- In girls, the ovaries begin to increase production of estrogen and other female hormones.
- Drug dependence - resources
- HTLV-1 infection
- Eat fewer animal products that contain cheese, cream, or eggs.
- Too much physical activity or effort
- Blindness
Related Products
Additional information:
An error is to deal with a portion of the global condition and neglect to totally handle the sagittal imbalance hypertension and headaches discount zebeta 10 mg mastercard. In this case, the lumbar pain is said partly to fatigue of the spinal extensor muscle tissue and to coexistent pseudarthrosis hypertension 2 buy cheap zebeta 5 mg. A affected person with decompensated sagittal steadiness stands with the knees flexed and the hips in extension to keep up an upright posture arrhythmia nclex 10 mg zebeta discount. The sagittal and coronal profiles demonstrate the true extent of the sagittal imbalance, pelvic obliquity, and coronal plane deformity hypertension guidelines jnc 7 zebeta 10 mg buy generic line. Treatment of fixed sagittal imbalance entails performing osteotomies to shorten the posterior parts of the backbone or performing anterior column osteotomy to launch or lengthen the anterior column. This process is extremely efficient in restoring sagittal stability in sufferers with a set sagittal aircraft deformity. By performing asymmetrical elimination of the posterior components, correction of each sagittal and coronal plane deformities could be achieved. With elimination of the pedicle bilaterally, two nerve roots exit through the reconstructed neural foramina at the level of the osteotomy and are at risk for damage. Smith-Petersen (Extension) Osteotomy Smith-Petersen and associates had been the primary to explain a posterior osteotomy for correction of fastened sagittal deformity in patients with rheumatoid arthritis. Sagittal correction is then achieved by posterior compression with instrumentation, which finally ends up in anterior osteoclasis through the vertebral physique or distraction via rupture of the anterior longitudinal ligament and disk area. The extension osteotomy creates hyperextension by closing the posterior elements and opening the anterior parts. The threat for morbidity and even mortality results from distraction damage to the anterior vascular buildings or neural parts or the event of superior mesenteric artery syndrome. This method might end in decompensation of the spine if the instrumentation fails before fusion. As a general rule, roughly 1 degree of correction could be anticipated for every millimeter of posterior bone resected during the procedure. Lagrone and coauthors reported an average initial correction of twenty-two levels in Pedicle Subtraction Osteotomy Pedicle resection plus transpedicular wedge resection of the vertebral physique to restore sagittal stability was first reported in sufferers with ankylosing spondylolysis in 1985. This aggressive osteotomy ends in removal of the posterior parts, including the pedicle and transverse process. A number of problems have been reported, together with pseudarthrosis, implant failure, inadequate initial correction, loss of correction, and a need for further surgical intervention. The aim of surgical procedure is to restore sagittal balance such that the plumb line intersects the posterosuperior nook of the S1 vertebra-in different phrases, to finish up with the head centered over the sacrum. This will allow the affected person to face with out knee flexion and hip hyperextension, thereby diminishing the overall ache. Patients with flattening of the lumbar backbone however with out thoracolumbar kyphosis may be handled by osteotomies under the level of the conus medullaris. Bernhardt and Bridwell and coworkers have shown that the common thoracic kyphosis is 30 degrees, or roughly 2. Sagittal alignment dictates that there ought to be 30 levels more lumbar lordosis than thoracic kyphosis. The angle at which the backbone is redirected at the osteotomy website (the osteotomy angle) is dependent upon the level of the osteotomy. When the osteotomy is carried out at a better level, the angle of osteotomy have to be higher than that of an osteotomy carried out at the decrease ranges of the backbone to achieve the same diploma of correction to restore sagittal stability. The inverse tangent of the angle of correction at the vertebral physique level will decide the amount of bone removing needed on the initial pedicle�vertebral physique interface. This measurement is the perpendicular distance, and it diminishes because the osteotomy is developed in a wedge fashion alongside the vertebral physique toward the anterior cortical surface. It is preferable to perform pedicle subtraction through areas of previous fusion to minimize back the danger for pseudarthrosis. Thus, the maximum physiologic lordotic curvature that could be achieved shall be in this space. Asymmetrical osteotomy may additionally be carried out to deal with any coronal plane deformity. An anterior process may involve anterior release with interbody bone grafting to scale back the risk for pseudarthrosis, notably when the instrumentation extends previous the lumbosacral junction. Anterior and posterior surgery may be performed in levels, depending on surgeon choice, the extent of surgical procedure wanted, and the general medical status of the patient. However, if the fusion is prolonged across the lumbosacral junction, an anterior Polysegmental Osteotomies In 1949, Wilson and Turkell reported on using multiple osteotomies to right sagittal stability in a patient with ankylosing spondylitis. This approach involves eradicating the side joints at several levels after which compressing the posterior parts to create lordosis. The correction is achieved by way of deformation of the disk spaces without rupture of the anterior longitudinal ligament with the use of transpedicular instrumentation. The quantity of correction achieved with polysegmental osteotomies is less than that achieved with the other strategies described. Bridwell and colleagues noted a median increase of 34 degrees and a median enchancment within the sagittal plumb line of thirteen. Anterior structural bone grafting can achieve arthrodesis when an extended assemble is prolonged to the sacrum. Bridwell and coworkers additionally really helpful anterior surgical procedure if extra spinal segments are added proximal to the earlier fusion. Proponents of the staged procedure attribute its security to discount of hemodynamic stress, fluid shifts, surgeon fatigue, pressure sores, and neurological danger. In contrast, others argue that same-day anterior and posterior procedures are related to less total blood loss, shorter hospitalization, fewer pulmonary problems, and early mobilization. Rhee and colleagues reviewed their ends in forty two consecutive grownup sufferers with deformity who underwent staged posterior surgery. It was carried out successfully in high-risk patients with low blood loss and no main medical issues. Iliac screw fixation with tricortical sacral screw placement minimizes distal assemble failure and pseudoarthrosis. Neuromonitoring can be utilized to detect any possible intraoperative neurological harm whereas correcting the deformity. The danger for neurological injury is highest during the correction of junctional kyphosis. Immediately after correction of the deformity, motor evoked potentials must be checked. Close consideration must be paid to positioning of the patient throughout spinal deformity surgical procedure because the patient will be inclined for an prolonged interval. A Jackson table is appropriate as a result of it barely increases hip extension and thus accentuates the lumbar lordosis. The affected person also wants to be positioned in a slight reverse Trendelenburg place because it could theoretically scale back the risk for intraoperative blindness secondary to ischemia throughout a chronic procedure. The operating room setup ought to include a fluoroscopy unit with a heads-up display monitor to facilitate placement of instrumentation and to evaluate the outcomes of the osteotomy. If an associated coronal plane deformity is present, the fluoroscope must be positioned on the side of the curve, which will facilitate its adjustment with respect to the curvature of the backbone. Surgical Technique After the initial planning, the procedure is approached in stepwise trend. Clear understanding of the objective of the surgical procedure facilitates sequential progression of the occasions. A minimum of two levels above and below the positioning the place the osteotomy is to be performed should be meticulously exposed. The exposure may be more in depth, depending on the nature of the deformity and preoperative planning for the instrumentation. It is crucial that thorough exposure of the bony anatomy and fusion mass be achieved. The space involving a pseudoarthrosis or floating fusion mass needs to be fastidiously uncovered and the bony anatomy rigorously delineated. The objective should be harmonious placement of pedicle screws to facilitate software of the contoured rod.
Usage: q._h.
New modifications use a drill to create bleeding surfaces without full resection of the tip plates prehypertension blood pressure diet purchase 10 mg zebeta with amex. A 1- to 2-mm posterior shelf of bone is created in the superior facet of the inferior vertebral physique to forestall migration of the graft into the spinal canal blood pressure medication voltaren zebeta 5 mg generic free shipping. For corpectomy sites, the top plates are ready in an analogous fashion as for diskectomy pulse pressure 2013 cheap zebeta 10 mg without prescription. More just lately, a quantity of studies have highlighted the morbidity associated with harvesting autografts symptoms 0f hypertension 5 mg zebeta purchase visa. Allograft is related to fusion rates much like these of autograft and is less expensive than many manmade alternatives. Careful preparation of the top plate ensures profitable incorporation of the graft and prevents it from being dislodged. In both diskectomy and corpectomy, the grafts are placed whereas the tip plates are distracted. Lateral radiographs are obtained to evaluate for proof of overdistraction, which may trigger postoperative ache, and to confirm good boneto-graft floor contact. The intention of this chapter is not to promote or focus on any specific plating system intimately. Rather, the fundamental rules of anterior instrumentation and plating might be discussed. Some of the benefits of cervical plating embody increased segmental stiffness, prevention of graft-related issues, and restoration of cervical lordosis. Improvement in fusion success charges with anterior cervical plating for a one-level fusion has been questioned. Such removing can be performed with a high-speed drill or with Leksell or pituitary rongeurs. Careful consideration is required to avoid removing the anterior cortex of the vertebral physique as a end result of it offers a major quantity of resistance to screw pullout. When a corpectomy autograft is used, the graft itself may be secured to the plate with a bicortical screw. The screw should be positioned in dense bone tissue within the subchondral region of the bone without violating the top plate. Violation of the tip plate by the screw can lead to physiomechanical alteration of a standard adjoining phase. If stripping happens, the assemble may be secured with a larger diameter rescue screw or by moving the complete plate and redirecting new screw trajectories. In addition, methyl methacrylate could be infused into the initial hole to bolster buy of the screw. When multilevel diskectomies or corpectomies are being carried out, multiple fixation factors can provide a extra biomechanically sound assemble. The self-retaining retractors are removed, and meticulous hemostasis is achieved with bipolar cauterization. The esophagus and carotid artery are inspected with handheld retractors for evidence of damage. The wound is irrigated with an antibiotic-containing resolution, and the platysma layer is closed with interrupted absorbable suture. Patients undergoing one-level diskectomies seldom require a tough cervical collar after surgical procedure. We recommend a delicate cervical collar when neck ache develops in these patients, and we encourage discontinuation of its use when sufferers are comfy. Patients with multilevel diskectomies, corpectomies, or trauma-associated injuries are normally maintained in a hard collar for roughly 6 weeks. At that time, cervical radiographs in flexion and extension views are obtained to evaluate incorporation of the graft. In the absence of complicating options, patients are asked to slowly wean themselves from use of the collar over a period of several weeks and to start isometric workouts to strengthen their cervical neck musculature. Individuals with metabolic derangements or with poor bone integrity, such as these with rheumatoid arthritis, are typically managed with a longer course of a tough collar or halo vest, or each, relying on the extent of their construct. Breathing difficulties could end result from swelling of sentimental tissue after prolonged and excessive retraction or from postoperative hematomas. Several very important buildings are also at risk for injury during anterior spinal approaches, including the carotid artery, jugular veins, trachea, and esophagus. Careful dissection and meticulous consideration to retractor placement should prevent accidents to these constructions. The retractors have to be placed beneath direct vision beneath the longus colli muscle bilaterally to avoid inadvertent damage to the esophagus. Although uncommon, esophageal injuries carry vital morbidity with the potential growth of mediastinitis and lethal abscesses. After surgery is accomplished, the size of the esophagus needs to be inspected completely to verify for rents. Methylene blue dye could be instilled into the pharynx whereas any suspicious areas are carefully visualized for extravasation of dye. Treatment of an infected esophageal restore requires surgical revision, drainage, nasogastric aspiration, intravenous or local antibiotics (or both), and in some cases esophageal diversion. If postoperative neurological deterioration is encountered, an epidural hematoma must be suspected and addressed in emergency trend. Vertebral artery accidents are also uncommon and result from loss of midline orientation, screw placement, or aggressive resection of laterally positioned disk osteophytes. Complications from iliac crest harvest can embrace localized pain, meralgia paresthetica from disruption of the lateral femoral cutaneous nerve, wound infections, and hip fractures. Use of an oscillating saw somewhat than an osteotome would possibly cut back the incidence of hip fractures. Depending on the signs, these extruded grafts may require surgical intervention. A threat for pseudarthrosis has been reported in most sequence addressing anterior cervical diskectomy and fusion. However, after sufferers with symptomatic pseudarthrosis endure posterior fusion at the involved levels, their signs might resolve. Other potential complications with instrumentation embrace esophageal erosion and hardware failure. Once the diagnosis has been narrowed to the cervical spine, an applicable therapy plan should be devised. The degree and extent of neurological dysfunction determine the need for conservative or surgical management. Patients with radicular signs could also be treated conservatively, whereas patients with myelopathic signs require careful and expeditious administration. The anterior cervical method has enjoyed acceptance amongst spine surgeons and has evolved tremendously over the past 5 a long time. This extraordinarily versatile strategy allows surgeons full entry to most if not all anterior pathologic parts responsible for clinical symptoms. Foraminal distraction, spinal wire decompression, and restoration of lordotic curvature could be carried out by placement of a graft and subsequent stabilization if required. Fusion may be enhanced via meticulous finish plate preparation, maximization of bone-to-graft contact, and compression. Surgical therapy of vertebral artery insufficiency attributable to cervical spondylosis. Complications of anterior cervical discectomy with out fusion in 450 consecutive sufferers. Vocal cord paralysis associated with anterior cervical fusion: considerations for prevention and therapy. Posterior-lateral foraminotomy as an unique operative approach for cervical radiculopathy: A review of 846 consecutively operated instances. Anterolateral cervical disc removal and interbody fusion for cervical disc syndrome. Surgical remedy of cervical spondylotic myelopathy: time for a managed trial. Adverse effects related to highdose recombinant human bone morphogenetic protein-2 use in anterior cervical backbone fusion. Prognostic elements for deterioration of sufferers with cervical spondylotic myelopathy after nonsurgical therapy. Biomechanical issues within the surgical administration of cervical spondylotic myelopathy. Although many options are held in widespread with rheumatoid arthritis, the lack of seropositivity for rheumatoid issue led to the designation seronegative spondyloarthropathies.
Tags: 5 mg zebeta amex, zebeta 5 mg cheap with amex, 5 mg zebeta purchase free shipping, order zebeta 10 mg amex, 10 mg zebeta purchase overnight delivery, zebeta 10 mg generic fast delivery, zebeta 5 mg low cost, buy discount zebeta 10 mg, zebeta 10 mg purchase line, discount zebeta 5 mg overnight delivery, zebeta 5 mg line, zebeta 5 mg order fast delivery, safe zebeta 5 mg, zebeta 5 mg generic free shipping, order zebeta 5 mg free shipping, cheap 10 mg zebeta amex
9 of 10
Votes: 134 votes
Total customer reviews: 134
Customer Reviews
Dolok, 38 years: Extramedullary tumors, primarily nerve sheath tumors or meningiomas, contain the intradural space twice as regularly as the extradural house. Among the incomplete spinal wire syndromes, Brown-S�quard syndrome has one of the best prognosis, with approximately 90% of patients regaining the ability to ambulate independently and control sphincter perform.
Ketil, 22 years: Sacroiliitis may be unilateral, however ossification and syndesmophyte formation of the joint are uneven. In most cases, nonetheless, a reasonably well-defined benign glial tumor is identified.
Chris, 61 years: All the patients have been mobilized immediately after instrumentation, and none of the sufferers had evidence of persistent an infection eventually follow-up. Several studies noticed that patients exhibited a major loss of vary of motion after laminoplasty.
Larson, 55 years: When the spinal process is completed, the posterior peritoneum is closed with absorbable suture. This is due, in part, to the truth that vertically oriented excitatory chains of neurons terminating on the cortical motor neuron are blocked by anesthetics, thus abolishing indirect activation of the motor neuron and the associated oblique (I) waves.
Stan, 63 years: Cervical Radiculopathy the aim of surgery for primarily radicular signs ought to be decompression of the affected nerve root or roots. While maintaining compressive force, the caps are tightened and the rod is secured to the screw.
Tarok, 26 years: Finally, the flexibility to carry out spinal radiosurgery within the outpatient setting is an advantage that may spare sufferers with spinal tumors both time and the morbidity of hospitalization. Evidence of cervical degeneration was noticed in 90% of men older than 50 years and 90% of ladies older than 60.
