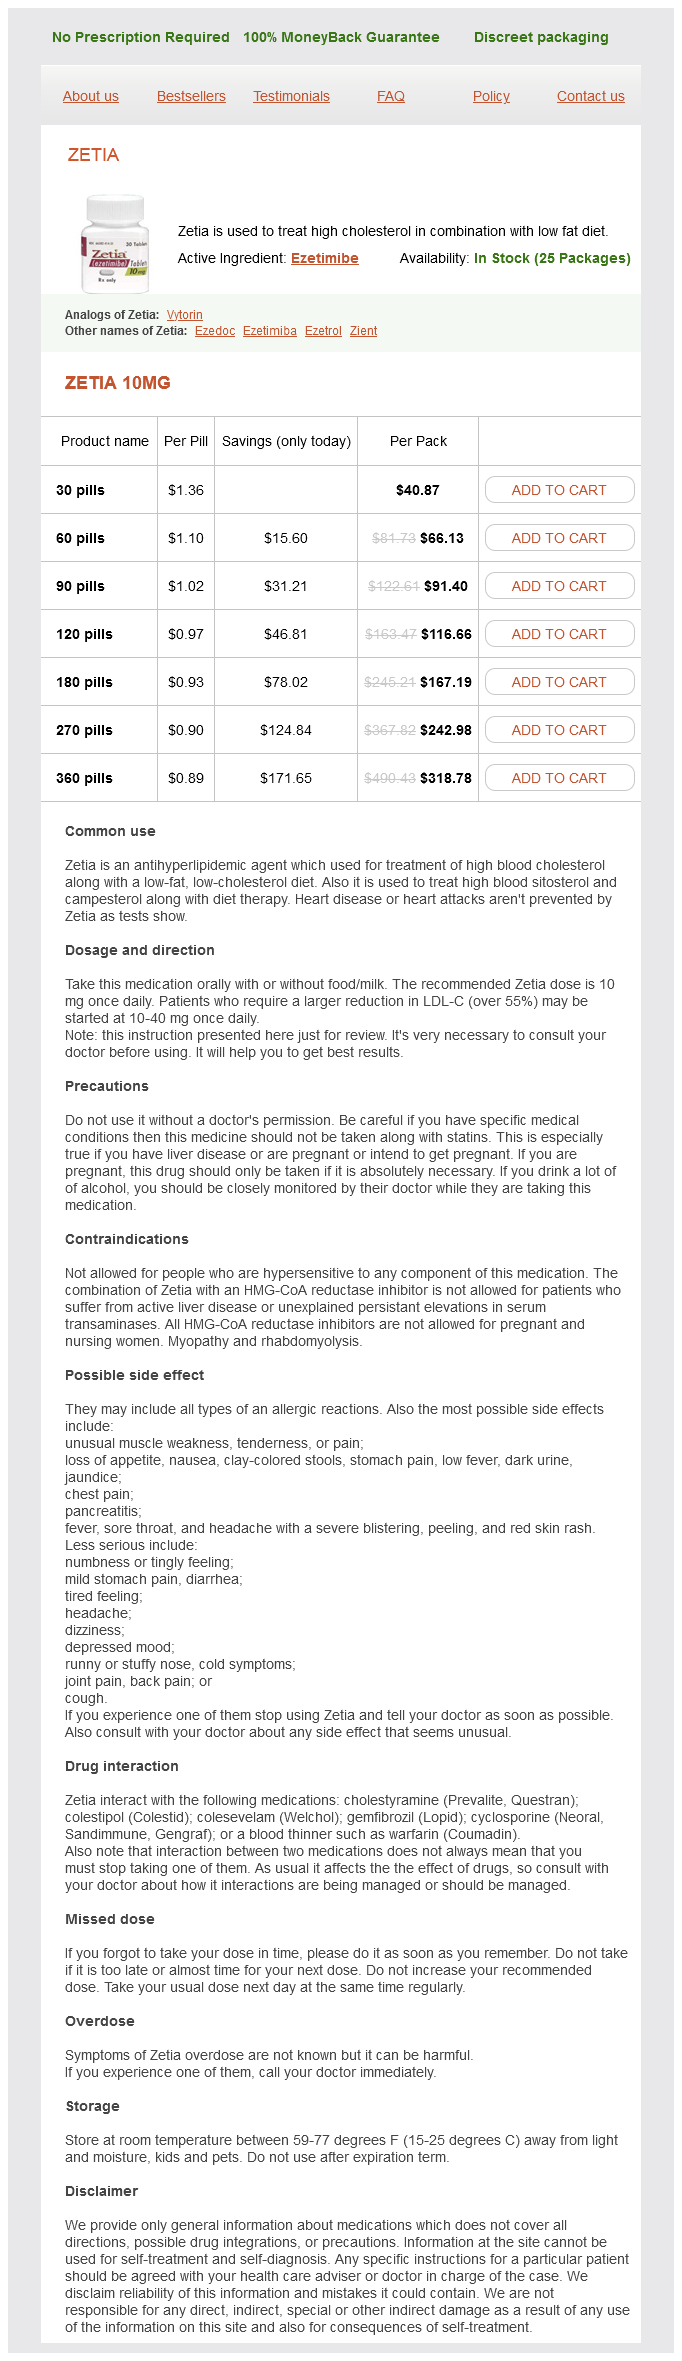
Zetia 10mg
- 30 pills - $40.87
- 60 pills - $66.13
- 90 pills - $91.40
- 120 pills - $116.66
- 180 pills - $167.19
- 270 pills - $242.98
- 360 pills - $318.78
Zetia dosages: 10 mg
Zetia packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 949
Only $0,94 per item
Description
The analysis may be challenging in adolescents whose applicable psychologic improvement contains Addressing Suicidal Thoughts and Attempts Suicide is the second leading reason for death in adolescents cholesterol levels eyes zetia 10 mg buy discount online, and assessing the danger of suicide is a critical part in the evaluation of any child or teen cholesterol guidelines chart zetia 10 mg best. Although melancholy is an important danger factor for suicide cholesterol ratio most important generic zetia 10 mg otc, only half of adolescents who attempt suicide have clinically diagnosable despair cholesterol definition biology online zetia 10 mg order amex. In those without despair, strong predictors of suicide are impulsivity and low frustration tolerance. The strategy to evaluating suicidality is complicated and includes a stepwise means of probing first for latent thoughts of suicidality (Table 27. Key to this process is assessing whether or not the child is considering appearing on ideas of demise or suicide. To assess risk, the interviewer ought to focus on the danger components for completed suicide, which embrace the next: 1. Have you carried out anything, started to do something, or ready to do anything to end your life Item 1 � Mental Health Referral at discharge Item 2 � Mental Health Referral at discharge Item three � Care Team Consultation (Psychiatric Nurse) and Patient Safety Monitor/Procedures Item four � Psychiatric Consultation and Patient Safety Monitor/Procedures Item 5 � Psychiatric Consultation and Patient Safety Monitor/Procedures Item 6 � If over a year in the past, Mental Health Referral at discharge If between 1 wk and 1 yr in the past, Care Team Consultation (Psychiatric Nurse) and Patient Safety Monitor If 1 wk ago or much less, Psychiatric Consultation and Patient Safety Monitor From Posner K. Anxiety, fear, or physical signs cause important misery or impairment the lifetime prevalence of generalized nervousness disorder is approximately 5%, with most instances initially presenting during childhood or adolescence. Comorbid diagnoses embrace temper disorders, other anxiousness problems, and substance use issues. In adjustment disorder with nervousness, the maladaptive response manifests as extreme worry. Stressors that kids and adolescents may encounter embrace social separations, parental divorce, illness, harm, shifting, educational failure, and peer conflict. Obsessions are recurrent and persistent ideas, urges, or What is the primary symptom Individual fears that she or he will act in a method that shall be negatively evaluated three. Fear or anxiety persists 6 months or longer Social phobias most frequently start in adolescence and are twice as common in boys as in ladies. Children with social anxiety often refuse group play, stay close to familiar adults, and seem excessively timid in unfamiliar conditions. Children may report somatic complaints, similar to headaches or stomachaches, which abate when the kid is allowed to remain house. Social phobia could also be comorbid with panic disorder, other anxiety issues, mood problems, and substance abuse. The core fear in separation anxiousness disorder is separation from a particular attachment figure or figures. Fear of separation is normal in infants and children aged 6-30 months however must be considered abnormal if increasing or not declining past this age range. Somatic complaints when separation happens or is anticipated the prevalence of separation anxiety disorder is as excessive as 5%, with onset sometimes in early childhood. Patients with separation anxiety dysfunction usually show their worries as demands or behavioral outbursts, which can trigger significant family battle. Comorbid conditions include main depressive disorder and panic disorder with agoraphobia. Patients with selective mutism have a persistent failure to speak in specific, but not all, situations. Children with selective mutism are sometimes shy in public but controlling at home in order to keep proximity to mother and father. Common obsessions embrace concern of contamination or illness, guilt concerning sexual ideas, pictures of violent or horrific scenes, and urges to injure oneself or others. Compulsions are repetitive and extreme acts the patient performs to cut back the nervousness elicited by obsessions. Compulsions may embody actions, corresponding to repetitive hand-washing or checking locks, or psychological acts, corresponding to repeating certain phrases or counting internally. Some sufferers must perform a particular action a selected variety of instances to have the ability to fulfill the compulsion. While females are more incessantly affected in general, males have a higher prevalence throughout childhood. Children usually current with imprecise nervousness symptoms or poor focus earlier than clear obsessions and compulsions are seen. It has additionally been instructed that a broad spectrum of infectious agents might have the flexibility to set off exacerbations in youngsters with these neurobehavioral disorders. Conditions Characterized by Fear Fear is an intense emotion centered on a belief that something is dangerous or painful. While all folks expertise concern as an emotion, in these problems it causes vital functional impairment. The hallmark of a selected phobia is intense fear upon publicity to a selected stimulus or state of affairs, or often upon serious about or visualizing the stimulus. The concern response in kids typically manifests as clinging, crying, having a tantrum, or "freezing. Social anxiety dysfunction is a particular phobia during which the stimulus is either a social or efficiency task. Diagnostic standards include the next: Fears Arising from Traumatic Events A traumatic event is defined as an exposure to actual or threatened dying, critical injury, or sexual violence. Responses to traumatic events include hyperarousal, avoidance of circumstances harking again to the occasion, or re-experiencing the occasion by way of nightmares and flashbacks. Symptoms are divided into four clusters: intrusion, avoidance, adverse alteration in cognition and mood, and marked alterations in arousal and exercise. Exposure to the traumatic event consists of directly experiencing the event, witnessing the occasion, learning the event occurred to a family member or close good friend (caregiver for youngsters beneath 6), or experiencing repeated or extreme publicity to particulars of a traumatic event. Dissociative reactions in which the person feels the event is recurring (flashbacks) (in youngsters, could also be reenactment in play) d. Avoidance or efforts to keep away from distressing memories (children could avoid places or bodily reminders) b. Avoidance of exterior reminders (children could avoid individuals, conversations, or interpersonal relationships) three. Inability to keep in mind an necessary facet of the traumatic occasion (not a criterion for a child beneath 6 years of age) b. Persistent and exaggerated adverse beliefs (not a criterion for a kid under 6 years of age) c. Persistent, distorted ideas about trigger or penalties of trauma (not a criterion for a child beneath 6 years of age) d. Persistent inability to expertise optimistic feelings (express positive emotions in children) four. Reckless or self-destructive behaviors (not a criterion in a toddler underneath 6 years of age) c. Sleep disturbance While as many as 30% of children will have some symptoms of acute stress dysfunction following a trauma, solely 10% will meet diagnostic criteria. These medical situations embrace ischemic heart illness, cancer, chronic lung disease, skeletal fracture, and liver illness. The age of onset is bimodal, with the largest peak occurring in adolescence and a smaller one in the mid-30s. Patients with panic disorder are also at nice danger for substance abuse as a consequence of self-medicating. Diagnosis requires that the anxiety manifest in a minimum of 2 of the following situations: 1. Being outdoors of the home alone the anxiousness is current nearly each time an individual is exposed to the state of affairs they fear and can also develop when the kid is conscious of that she or he may be positioned in certainly one of these situations. While agoraphobia does present in childhood, the height of onset is late adolescence and early maturity. Agoraphobia is usually preceded by panic dysfunction, phobias, and separation nervousness disorder. Other comorbidities, such as despair and substance use dysfunction, usually follow the presentation of agoraphobia. Finally, the mental standing change ought to be categorized as either acute or chronic.
Pini Atheroleum (Pine). Zetia.
- Are there safety concerns?
- Upper and lower respiratory tract swelling (inflammation), mild muscle pain, nerve pain, blood pressure problems, common colds, cough or bronchitis, and fevers.
- What is Pine?
- How does Pine work?
- Dosing considerations for Pine.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96143
The clusters happen through the transitions between wakefulness and sleep cholesterol levels daily order 10 mg zetia visa, so are commonest within the early morning and night cholesterol lowering foods american heart association buy zetia 10 mg without a prescription, or sometimes round naptimes cholesterol levels high during pregnancy 10 mg zetia with amex. The extent of muscle involvement varies from a strong contraction that jackknifes the physique to minimal contraction of truncal muscle tissue that causes only stiffening vap cholesterol test quest discount zetia 10 mg fast delivery. Eye actions are commonly related to the spasm, either as deviation or as repetitive nystagmoid upward jerks. As the spasms continue, there could also be insidious loss of developmental motor milestones similar to sitting, rolling, babbling, or head management. Another commonly described regression is a decline in visual attentiveness, that means that the child now not simply regards faces, tracks shifting objects, or reaches for toys. The differential diagnosis can include colic, exaggerated Moro reflexes, or normal myoclonic jerks on falling asleep or waking. Multiple myoclonic seizure syndromes, both benign and otherwise, occur in this age group and should be distinguished from infantile spasms by a neurologist. Infantile spasms could be attributable to a broad variety of neurologic insults; the commonest etiologic issue is perinatal hypoxic-ischemic encephalopathy. If infantile spasms are seen along side agenesis of the corpus callosum and retinal abnormalities on eye examination, this suggests a diagnosis of Aicardi syndrome. Approximately 95% of kids with an identified trigger (structural, genetic, or metabolic) have a prognosis of moderate-to-severe neurologic harm, including refractory epilepsy, cognitive impairment, or everlasting developmental sequelae. This subset of sufferers is prone to have a a lot better longterm outcome: 38% of those patients are regular or mildly impaired, in comparison with solely 5% of symptomatic sufferers. A unique subset of patients who may develop childish spasms is children with trisomy 21 (Down syndrome). Persistence of the epilepsy in most of the patients is associated with lack of the spasms and improvement of other seizure types, similar to tonic seizures, focal seizures, and tonic-clonic seizures. Seizures very comparable in look to childish spasms (brief myoclonic or tonic seizures occurring in clusters) could recur later in childhood, and these are referred to as epileptic spasms. Both therapy regimens generally final 8-12 weeks, and both require frequent monitoring for unwanted aspect effects. The pediatrician may be called upon to monitor electrolytes, blood pressures, or indicators of sickness while the child is underneath remedy. Live vaccinations are typically held for 6-12 months after a course of immunomodulatory therapy. However, this treatment is presently strictly regulated in its prescription, and patients on vigabatrin require examinations by an ophthalmologist every 3 months due to the small risk of permanent peripheral imaginative and prescient loss with extended use of the treatment. Many other antiepileptic medicines, including topiramate, lamotrigine, valproic acid, and benzodiazepines, have had some efficacy in isolated instances, however this response is unpredictable. The child might present with febrile or afebrile seizures, normally with normal psychomotor growth preceding the onset of seizures, and sometimes with a household historical past of epilepsy. The seizures are generalized or unilateral clonic seizures; myoclonic seizures appear later (and will not be a serious function of the disorder, regardless of the name), between 8 months and 4 years of age; and focal seizures and atypical absences may happen. Antiepileptic medications that may worsen seizures or be ineffective in Dravet syndrome embrace phenytoin, lamotrigine, carbamazepine, oxcarbazepine, and vigabatrin. Childhood the paroxysmal issues of childhood (2-12 years) are given in Table 30. Typically, there are symptom-free intervals lasting weeks to months, and recurrence is unpredictable. There may be a powerful household history of migraine, and there seems to be some overlap of the cyclic vomiting with migraine. Children might have phonic tics (such as tongue clicking or throat clearing), motor tics (such as blinking, sniffing, or shrugging), or any mixture of both. The presentation of migraines in children may be markedly totally different than that in adolescents and adults; "migraine equivalents" are paroxysmal issues which may be strongly related to the later improvement of migraines and may share related underlying pathophysiologic mechanisms. This temporal association has led to the misunderstanding that the stimulant medications have caused the tics. Tourette syndrome is identified when a toddler has had a quantity of motor tics and no less than 1 phonic tic current for longer than 1 yr. Other tic problems could be purely motor or purely phonic, and are categorized according to their signs and duration (transient vs. Sleepdisorders � Peak presentation: age 2-7 years � Classical features: occurring a couple of hours after falling asleep ("round midnight"), nonstereotyped behaviors, screaming, agitation, and inconsolability despite being apparently awake, no reminiscence of scary imagery � Acuity: low � Prognosis: glorious, although kids with frequent episodes could need to be monitored by their dad and mom to forestall harm throughout a panicked state Night terrors and confusional arousals. Night terrors are a standard phenomenon in children and are most frequent in boys aged 5-7 years. Up to 15% of youngsters younger than 7 years have skilled some form of these episodes. The attacks are characterized by sudden arousal from sleep, usually screaming in terror, after which crying with agitation and tachycardia. There may be vigorous and doubtlessly injurious motor exercise in older children, corresponding to working or hitting the bed or wall. The hanging function of these episodes is that the kid is inconsolable but seemingly awake. Prior sleep deprivation, febrile sickness, emotional stress, and some drugs (sedatives/hypnotics, neuroleptics, stimulants, antihistamines) may be precipitants. In distinction to the experience of nightmares, youngsters are amnestic for the occasions and their distress in night terrors. Confusional arousals are much less dramatic attacks with comparable origin from slow-wave sleep and are extra typical in younger children. Nocturnal frontal lobe seizures happen throughout sleep and may have bizarre hypermotor behaviors corresponding to rolling, turning, choosing, yelling, and fumbling. In school-aged youngsters, benign rolandic epilepsy manifests itself as seizures when popping out of sleep with gurgling, salivation, hemifacial and hemibody twitching, and infrequently partially preserved consciousness of the occasion. Important distinguishing historic factors between seizures and parasomnias are the time of onset (seizures: shortly after falling asleep or early within the morning), duration (most seizures final 1-2 minutes, and parasomnias can have a considerably longer duration), and any related tongue chunk, urinary incontinence, or insidious behavioral or developmental regression. Approximately 15% of youngsters have walked of their sleep, especially in the 2-3 years old age group, and a pair of. There is a household history of sleepwalking and other parasomnias in 60-80% of sufferers. These episodes of apparent unresponsiveness and "automatisms" could probably be mistaken for focal dyscognitive seizures or a postictal state. Repetitive purposeless movements could also be carried out by kids on the autism spectrum or with cognitive disabilities. Combined with unresponsiveness, these behaviors may be mistaken for automatisms in focal dyscognitive seizures. The necessary features that distinguish such habits from epileptic exercise are the setting in which it occurs, the variable content and duration of the "attacks," and the complete failure of the episodes to interrupt extra stimulating actions. Acute Symptomatic Seizures and Occasional Seizures Febrile convulsions stay one of the widespread causes of occasional seizures in early childhood. Head harm is more widespread in childhood than in infancy, but the list of other potential causes of seizures, together with mind tumor, intracranial an infection, and poisoning, is very comparable. In addition, some metabolic and neurodegenerative disorders manifest in childhood, not in infancy (Table 30. There is a group of idiopathic partial epilepsies beginning in children without abnormalities on neurologic examination or neuroimaging studies, and frequently, with a household historical past of epilepsy. The seizures are brief and stereotyped in an individual, although they differ amongst patients. The sharp waves or spikes have a characteristic structure and are sometimes very frequent, rising during sleep. Brief hemifacial motor seizures with anarthria and drooling are typical, regularly when popping out of sleep. Consciousness is often preserved, though this is probably not true with longer seizures. A somatosensory aura involving the tongue, cheek, or gums may precede the motor seizure. Many seizures occur at night as tonic-clonic seizures, presumably secondary generalized with unwitnessed partial onset. If seizures are rare and nocturnal, the option of no remedy should be discussed. Benign childhood epilepsy with occipital paroxysms types a subset of idiopathic partial epilepsies of childhood.
Specifications/Details
Hyperkalemia could be caused by (1) lowered urinary potassium excretion preferred cholesterol ratio 10 mg zetia mastercard, (2) increased potassium consumption cholesterol levels for 50 year old male purchase zetia 10 mg, (3) release of intracellular potassium cholesterol vaccine cheap zetia 10 mg with mastercard, and/or (4) impaired cellular potassium uptake (Table 46 cholesterol medication affect kidneys purchase zetia 10 mg amex. Renal Failure Potassium excretion is decreased in each acute and continual renal failure. In sufferers with continual renal failure, potassium balance is maintained by increased K+ secretion per functioning nephron and likewise by enhanced excretion of K+ through the gastrointestinal tract. Hypoaldosteronism Low ranges or absence of aldosterone (or aldosterone receptor defects) could end result from a selection of situations (Addison illness, congenital adrenal hyperplasia [deficiency of 21-hydroxylase], and hyporeninemic hypoaldosteronism). In addition to hyperkalemia, hyponatremia and hyperchloremic metabolic acidosis are the related features in these problems. The analysis could be confirmed by measurement of renin activity and aldosterone ranges. Primary Tubular Defects In some patients, hyperkalemia happens on account of low urinary K+ excretion regardless of regular renin and aldosterone levels. The presence of a selective defect in K+ secretion has been described in subjects with renal transplant rejection and lupus nephritis. Increased Potassium Intake/Tissue Release Acute will increase in potassium intake, normally via parenteral administration, may lead to hyperkalemia. The hyperkalemia is often transient because regular kidneys have a big capability for excreting potassium. Similarly, trauma, intravascular hemolysis, transfusion of saved blood, and catabolic states similar to an infection or excessive fever are related to release of K+ from the cells; however, hyperkalemia is rare as long as renal function is regular and regular to excessive urine output is maintained with fluid therapy. This protecting effect is type of speedy but comparatively short-lived; therefore, other measures to scale back the concentration of serum potassium are essential. Potassium could be shifted from the extracellular to the intracellular compartment by administration of glucose and insulin, or 2adrenergic agonists, as detailed in Table forty six. Although the intracellular shift of potassium can be accomplished quite quickly, this is only a brief lived measure, and additional steps should be taken to set up a negative potassium stability. In patients with aldosterone deficiency, fludrocortisone increases renal potassium excretion. Alkalinizing the urine by way of systemic base administration can further improve urinary potassium losses. Cation trade resins really take away potassium from the body and are effective in acute situations, particularly when poor renal operate is current. Dialysis is needed in sufferers with extreme hyperkalemia, especially within the presence of advanced renal failure or when accompanied by a hypercatabolic state or severe tissue necrosis. For urgent potassium elimination, hemodialysis is more effective than continuous hemodiafiltration or peritoneal dialysis. Redistribution Acidosis and insulin deficiency lead to egress of intracellular potassium. Consequences of Hyperkalemia Overt clinical manifestations are unusual with hyperkalemia, but cardiac arrhythmias are doubtlessly life-threatening. This can be rapidly adopted by atrioventricular dissociation and ventricular tachycardia or fibrillation. All potassium intake (parenteral diet, medications with potassium salt) and medications that trigger hyperkalemia, similar to potassium-sparing diuretics, angiotensinconverting enzyme inhibitors, and trimethoprim, ought to be discontinued. The therapy modalities normally belong to the following 3 categories: (1) antagonism of membrane excitability, (2) shifting of potassium into the intracellular compartment, and (3) elimination of excess potassium (Table forty six. Sodium homeostasis is coupled with water homeostasis; subsequently, problems of sodium homeostasis often happen as a end result of imbalances of each sodium and water quite than an isolated imbalance of both sodium or water. Sodium excretion, which is regulated by the renin-angiotensin-aldosterone system and atrial natruretic peptide, will increase in response to an expanded intravascular volume, as may occur with a high sodium intake. In response to a decreased intravascular volume, the urine could be made just about sodium free. A detailed historical past of the underlying illness, meals and fluid consumption, fluid losses in the form of stool, emesis, and urine should be obtained. The medical options associated with alterations in plasma osmolality are nonspecific. Osmolality is regulated by thirst and vasopressin manufacturing, which determines renal water excretion. A low serum osmolality could produce lethargy and confusion, whereas a high serum osmolality could result in irritability, a high-pitched cry, and a doughy skin texture. The dedication of plasma osmolality requires a direct laboratory measurement or can be estimated from the following formulation: Serum osmolality (mOsm) = 2 � [Na+]mEq/L + [glucose]mg/dL /18 + [urea]mg/dL /2. Hyponatremia ought to be differentiated from pseudohyponatremia and factitious hyponatremia. Pseudohyponatremia happens within the presence of extreme quantities of plasma proteins and lipids, which lower the share of plasma water and thus artificially decrease the plasma sodium concentration. Therefore, a niche between measured and calculated osmolalities can indicate pseudohyponatremia. Factitious hyponatremia results from high plasma concentrations of impermeable solutes similar to glucose or mannitol that trigger movement of water from the intracellular to the extracellular area. In distinction to pseudohyponatremia, the low plasma sodium focus in these conditions is a real worth, and plasma osmolality is elevated because of the presence of the extra solutes. In true hyponatremia, the plasma osmolality is low (<280 mOsm/ kg), and the pathophysiologic processes are attributable to (1) lack of both plasma sodium and water (sodium losses exceeding water losses), (2) enhance in plasma water (without edema), or (3) increase in both complete body water and sodium (increase in water exceeding that of sodium; often with edema). Apart from managing the underlying situation, sufferers with cerebral salt-wasting syndrome require full replacement of urinary sodium and water losses. In all sufferers with renal losses of sodium as a reason for hypovolemic hyponatremia the urinary sodium concentration is often greater than 20 mEq/L, regardless of the presence of hypovolemia. Attempts to appropriate the hyponatremia with sodium administration cause a rise in urinary sodium excretion and little change in the plasma sodium concentration. Nonetheless, sodium administration is needed if severe hyponatremia results in neurologic symptoms. Infants younger than 1 12 months fed water with out electrolytes may develop hyponatremia and related symptoms similar to lethargy, seizures, and hypothermia. Hypovolemic Hyponatremia Hypovolemia hyponatremia happens when urinary and/or gastrointestinal sodium losses exceed these of water, fluids are sequestered into third spaces such because the peritoneal cavity, subcutaneous tissue, or bowel lumen, or uncommonly, sodium losses in sweat for patients with cystic fibrosis or excessively hot climatic zones. Fistulas and varied kinds of gastrointestinal drainage tubes can also result in an analogous clinical image. The normally functioning kidneys reply by conserving sodium, and the urine sodium focus is usually less than 20 mEq/L. The urinary sodium losses are elevated during the recovery section of acute tubular necrosis, after aid of urinary tract obstruction, and in sure renal ailments (salt-wasting nephropathies) such as medullary cystic disease, polycystic kidney illness, and tubulointerstitial diseases. Some kids with acute or persistent central nervous system damage (closed-head trauma, surgical procedure, tumors, or meningitis) current with extreme renal sodium losses and develop hypovolemic hyponatremia. The situation, generally identified as cerebral (renal) salt-wasting syndrome, may occur due to secretion of atrial natriuretic hormone or other undetermined components. Cerebral salt losing is usually related to hypovolemia but could additionally be confused with the syndrome of inappropriate Hypervolemic Hyponatremia In the absence of renal disease, sufferers with hypervolemic hyponatremia have decreased effective circulating blood quantity with resulting sodium and water retention. Central nervous system signs nearly all the time reduce when the serum sodium concentration is increased by 10 mEq/L. It is beneficial that the preliminary serum sodium correction not exceed one hundred twenty five mEq/L with this therapy. Whereas water restriction is sufficient for patients with mild hyponatremia, patients with symptoms should receive intravenous furosemide adopted by intravenous hypertonic saline. In circumstances of severe salt and water overload associated with renal failure, dialysis is the simplest therapy. These sufferers often have very delicate signs because the brain has time to adapt to the disturbance with a decrease within the intracellular osmolytes. Rapid correction of hyponatremia can result in cellular shrinkage and may trigger an osmotically induced demyelination syndrome, significantly in the pons. The sufferers with in depth lesions can have flaccid quadriplegia, dysphagia, and dysarthria. Although each sodium and water are retained, hyponatremia develops due to proportionately greater water retention. The urinary sodium is usually less than 10 mEq/L because of avid sodium reabsorption as a consequence of decreased effective blood volume and decreased renal perfusion.
Syndromes
- Bone, joint, and muscle pain
- Only women who have a low risk for stroke, heart disease, blood clots, or breast cancer should take estrogen.
- Blurred vision
- If the child vomits, or if saliva and mucus build up in the mouth, turn the child to the side or on the stomach. This is also important if it looks like the tongue is getting in the way of breathing.
- Low birth weight babies
- You might drink the contrast before your scan. When you actually drink the contrast depends on the type of exam being done. The contrast liquid may taste chalky, although some are flavored to make it taste a little better. The contrast eventually passes out of your body through your stools.
- Carbamazine (Tegretol)
Related Products
Additional information:
B ideal cholesterol ratio for an individual would include zetia 10 mg online, Longitudinal plane reveals inside bowel loops (white arrows) telescoping through outer bowel loops (black arrows) lowering cholesterol by eating oatmeal zetia 10 mg buy low price. Small bowel follow-through examination permits evaluation of the small bowel from the ligament of Treitz to the ileocecal valve cholesterol lowering vegetarian diet zetia 10 mg order online. In cases of intussusception cholesterol levels scale uk zetia 10 mg generic with amex, the enema not only aids in diagnosis but can also be therapeutic. Crohn disease and ulcerative colitis may be advised by outcomes of this test, but endoscopy is necessary for histologic confirmation of these diagnoses. Abdominal Ultrasound An ultrasound could also be helpful in patients with suspected liver disease to evaluate for portal hypertension. Patients must be awake and capable of keep still via the prolonged examine, which limits its utility in younger patients. Arrow signifies abnormal space of increased uptake in decrease abdomen above bladder, in preserving with gastric mucosa containing Meckel diverticulum. Angiography Angiography might help establish the source of bleeding however is just sensitive for an energetic bleed at a fee of no less than 0. Nevertheless, angiography can identify extravasation of distinction in a Meckel diverticulum or the presence of vascular malformations of the bowel, which can be acquired or congenital. False-negative results have been reported regularly because of inadequate gastric tissue mass, downstream washout of isotope, impaired blood provide, or suboptimal methods. Positive identification could also be improved by the administration of ranitidine to stop excretion of pertechnetate from gastric tissue. Bleeding scans are performed by intravenously injecting technetium sulfur colloid. The agent is distributed quickly and is quickly taken up by the reticuloendothelial system. However, because the technetium is taken up by the reticuloendothelial system, this will hinder the seek for bleeding websites behind the liver or spleen. Finally, the clearance may be very rapid, with a half-life of 2 minutes, which means that bleeding has to be occurring on the time of the scan. In cases of intermittent bleeding, a single injection of labeled cells allows repeated scans for as much as 24 hours. Endoscopic visualization of the stomach and duodenum must be carried out even when the bleeding is thought to originate from esophageal varices. Of patients with proven esophageal varices, 50% may manifest bleeding from gastritis or peptic ulcer disease somewhat than the varices. Erythromycin could be given previous to endoscopy to accelerate gastric emptying and removing of blood from the abdomen. Procedures frequently utilized in kids embody proctosigmoidoscopy and versatile colonoscopy. With the patient underneath appropriate sedation, lower gastrointestinal endoscopy permits for full exploration of the colon; identifies the presence of multiple lesions; permits for therapeutic intervention to bleeding lesions via electrocoagulation, laser remedy, or thermocoagulation; and allows for elimination of bleeding lesions, similar to polyps. One disadvantage is that large quantities of luminal blood obscure visualization of a lesion. Before decrease gastrointestinal colonoscopy, intestinal lavage with oral administration of polyethylene glycol must be used to remove as a lot of the luminal blood and stool as attainable. Small bowel enteroscopy, or evaluation of the jejunum or proximal ileum, may be helpful within the analysis of occult bleeding. While its diagnostic yield varies by study, it permits for direct intervention if the source of bleeding is found. In addition, it has been employed intraoperatively to assist determine lesions and guide surgical intervention. Capsule Endoscopy Wireless capsule endoscopy could additionally be useful in sufferers with occult or apparent bleeding when different work-up, including an upper and lower endoscopy, have been negative. The major threat is capsule retention and so children have to be of a sure measurement and be evaluated for possible stricture prior to the study. Resuscitation Treatment the severity of bleeding determines the final pointers for therapy. For extreme bleeding, preliminary management reestablishes and maintains the intravascular volume. Subsequently, the positioning of blood loss must be determined and attempts made to cease the hemorrhage. Severe anemia also necessitates packed pink blood cell transfusions after the intravascular volume deficit is corrected (Table 13. Although dad and mom tend to overestimate the amount of blood misplaced by their baby, a serious error within the management of gastrointestinal bleeding is underestimating blood loss. If orthostatic blood strain adjustments or tachycardia are current, the initial aim of treatment ought to be to hemodynamically stabilize the patient, preserve the intravascular volume, and provide sufficient oxygen supply to the tissues. Blood loss should be replaced instantly with a crystalloid resolution, corresponding to regular saline or lactated Ringer answer. Initially, a fluid push of 20 mL/kg must be given, though resuscitation must be performed cautiously in patients who could have portal hypertension as overly aggressive resuscitation raises the venous stress and will worsen bleeding from varices. In these sufferers, small, repeated fluid boluses with close monitoring are most popular to giant quantity boluses. If blood loss continues and the affected person seems to be at risk for hypovolemic shock, infusion of regular saline or colloid solutions (5% albumin) can be continued until blood is out there. Once bleeding has stopped, transfusions of packed purple blood cells ought to continue, to slowly increase the hematocrit to 30% (10 g/dL hemoglobin) (for sufferers with variceal bleeding the aim is instead hemoglobin of 8-9 g/ dL). If continued blood loss necessitates a number of transfusions, freshfrozen plasma and calcium must be given to exchange coagulation elements and correct the hypocalcemia brought on by the citrate in blood merchandise. The platelet count in such patients must be monitored as a result of thrombocytopenia may develop. A 12-French tube is used in infants and preschool youngsters; a 14- or 16-French tube is suitable for youngsters of elementary college age or older. The shade of the gastric lavage fluid gives the physician a sign of the speed of bleeding. Lavage returns which would possibly be brilliant red indicate important ongoing bleeding; pink-tinged or brown flecks in the solution point out less vital or minimal bleeding. Maintaining a gastric pH of greater than 4 is taken into account commonplace therapy for higher gastrointestinal mucosal bleeding. This may be accomplished with both H2-receptor antagonists or proton pump inhibitors. Vasoactive Agents In sufferers with suspected variceal bleeding, a continuous infusion of octreotide could additionally be began. This agent reduces splanchnic blood circulate with minimal disturbance to different organs. It is safer than vasopressin however has not been shown to have profit in nonvariceal bleeding. Customarily, a bolus of octreotide (1-2 �g/kg) is given over 5-10 minutes, and this is followed by a steady infusion of 1 �g/kg/hr, though larger doses may be required. The infusion could assist management the bleeding until definitive remedy (banding or sclerotherapy) is performed. Endoscopic Modalities Most sufferers with gastrointestinal bleeding will undergo higher and/ or lower endoscopy for definitive prognosis and therapy. For patients with mucosal lesions, corresponding to ulcers or bleeding polyps, there are multiple therapeutic interventions available. Injection with a diluted epinephrine answer, thermal coagulation, laser photocoagulation, and endoscopic clips can be used to cease energetic bleeding. For patients with colitis, colonoscopy is used primarily to confirm analysis and extent of disease. Ideally, the banding takes place after good control of acute bleeding, affording the endoscopist an unobstructed view of the varices. Side results of this remedy are minimal, and the procedure is repeated weekly to monthly till the varices are obliterated. Sclerotherapy is also efficient in controlling the acute bleeding from esophageal varices and may be carried out weekly to monthly till the varices resolve. In young children whose higher esophageal sphincter is just too small for the endoscopic banding device to cross, sclerotherapy may be the only possibility.
Usage: q._h.
Anemias are categorized on the idea of the adequacy of the reticulocyte response cholesterol test brisbane zetia 10 mg buy without prescription. In patients with average or extreme anemia cholesterol hdl ratio canadian values purchase 10 mg zetia otc, the reticulocyte depend could seem elevated cholesterol medication for elderly 10 mg zetia purchase amex, however in absolute phrases how much cholesterol in one large shrimp zetia 10 mg purchase with amex, it might be insufficient for the diploma of anemia. Microcytosis is associated with iron deficiency, thalassemia, and long-standing anemia of inflammation (Table 37. Macrocytosis, an uncommon discovering in children, is related to vitamin B12 or folate deficiency, bone marrow failure syndromes (Fanconi anemia, Diamond�Blackfan anemia), and some cases of hypothyroidism (Table 37. Capillary blood sampling could be related to substantial error, relying on the problem in performing the procedure and the use of mechanical pressure necessary to promote blood move. When laboratory or sampling errors are suspected, a venipuncture sample must be obtained for confirmation. For instance, leukopenia, neutropenia, and/or thrombocytopenia occurring in a patient with anemia of underproduction are suggestive of aplastic anemia or infiltrative bone marrow illness corresponding to leukemia. Thrombocytosis could additionally be current in patients with iron deficiency, blood loss, inflammatory illness, an infection, malignancy, or asplenia. Immune-mediated hemolytic anemia must be suspected when anemia, jaundice, reticulocytosis, splenomegaly, and microspherocytes are famous. A low serum iron degree, elevated whole iron-binding capacity, and a low share of iron saturation (% saturation = serum iron/total ironbinding capacity � 100) and/or decreased serum ferritin level are useful in establishing a analysis of iron deficiency. Hemoglobin identification by way of electrophoresis or high-performance liquid chromatography is critical to determine hemoglobinopathies similar to sickle cell illness or thalassemia. True macrocytic anemia should prompt assessment for vitamin B12 or folate deficiency. Bone marrow aspirate and biopsy should strongly be thought of when other cytopenias exist such as thrombocytopenia or neutropenia. The pale youngster who appears seriously sick requires pressing evaluation and acceptable therapeutic intervention. Anemia Secondary to Acute Blood Loss Significant blood loss on an acute or subacute basis results in anemia. In subacute bleeding, the fall in hemoglobin happens gradually and a period of about 24 hours may be required for full intravascular equilibration after acute blood loss. Therefore, in the setting of extreme blood loss, blood stress, heart fee, adequacy of peripheral perfusion, and mental status are one of the best ways to assess patients. In most instances, an obvious historical past of blood loss is apparent (epistaxis, hematemesis, decrease gastrointestinal bleeding, trauma). Large amounts of blood could accumulate within the gastrointestinal tract before the development of hematemesis, hematochezia, or melena. Intraabdominal bleeding might occur after trauma or might end result from an ulcer (see Chapter 13) and may be related to progressive anemia within the absence of an apparent source of bleeding. If hemorrhage has ceased, the hemoglobin level ought to progressively enhance except supervening elements similar to iron deficiency exist. Severe hemorrhage associated with intravascular quantity depletion warrants quick intervention to avoid shock. Transfusions could also be needed when the oxygen-carrying capability of the blood is diminished to the purpose of impending tissue hypoxia. In these cases, the necessity for transfusion therapy is predicated on scientific symptoms together with tachycardia, dyspnea, heart failure, fatigue, or lightheadedness. Associated clinical signs can provide clues to the etiology of underproduction, especially for nonhematologic causes of anemia. Common nonhematologic causes of underproduction embody continual renal illness, continual irritation, or an infection. With pancytopenia Malignant disease (bone marrow infiltration) Anemia of acute inflammation/infection Transient erythroblastopenia of childhood Renal failure Hypothyroidism C. Microangiopathy (disseminated intravascular coagulation, hemolytic uremic syndrome, thrombotic thrombocytopenic purpura) 4. Any factor that diminishes the provision or utilization of these components ends in microcytic anemia. Review of the peripheral blood smear additionally offers further proof regarding variability in cell size and form. Iron deficiency outcomes when dietary intake is insufficient to meet calls for related to development and/or blood loss. Infants are at explicit risk for the event of iron deficiency since their fast progress and expanding blood quantity impose considerable iron demands. Premature infants are at the highest danger as a end result of most in utero iron is transferred to the fetus during the last trimester of being pregnant and postnatal growth rate is fast. Adolescent females are at very excessive threat due to menstrual blood loss and inadequate diet. Risk for iron deficiency is excessive in adolescent females particularly through the 1st yr after menarche. When iron deficiency occurs outside of the setting of infancy, toddlers, or adolescent females a pathologic source of blood loss have to be strongly thought-about and occult gastrointestinal bleeding is a crucial supply to think about as iron deficiency anemia can be the first clue to the presence of inflammatory bowel illness. Nutritional sources of iron embrace iron-fortified infant formulation (12 mg/L), iron-fortified infant cereal, beef, fish, and fowl. The American Academy of Pediatrics recommends iron-fortified infant method or breast milk till the age of 1 yr and the introduction of iron-rich foods after 6 months of age. Iron supplementation is important for preterm infants, most adolescent females, and pregnant ladies and should be strongly thought-about for all exclusively breast-fed infants regardless of food plan. Iron deficiency have to be seen as a systemic deficiency dysfunction, only 1 manifestation of which is anemia (Table 37. This must be carried out initially in youngsters between 9-12 months of age and once more between 18-24 months of age as toddlers are especially vulnerable to iron deficiency anemia during the transition from 670 Section 8 HematologicDisorders production of the -globin chain occurs, resulting in mild microcytic anemia of underproduction. Thus, an index of lower than thirteen is suggestive of thalassemia trait, whereas an index of more than 13 is generally suggestive of iron deficiency anemia. The peripheral blood smear demonstrates microcytosis, hypochromia, and target cells. The significance of diagnosing -thalassemia trait is twofold: (1) its confusion with iron deficiency (hence, patients may be treated unnecessarily with repeated programs of iron and undergo repeated unnecessary blood studies) and (2) its genetic implications. A mating between 2 individuals with -thalassemia trait carries a 25% danger per being pregnant of offspring with homozygous -thalassemia (thalassemia major), a extreme hematologic disorder. Parents and siblings of a kid with a diagnosis of -thalassemia trait ought to be appropriately screened and recommended. Homozygous -Thalassemia, also referred to as -thalassemia main or Cooley anemia, results from the inheritance of the -thalassemia trait mutation from each mother or father. Excess -globin chains precipitate inside growing erythroid elements within the marrow and lead to brisk intramarrow destruction of growing erythroid components (ineffective erythropoiesis). As a end result, sufferers with -thalassemia main current throughout infancy at 6-12 months of age with extreme anemia and an inadequate reticulocyte count during the time when transition from fetal hemoglobin to adult hemoglobin occurs. Frontal bossing and distinguished cheek bones (maxillary hyperplasia) may be famous and result from expansion of the marrow space in an try to compensate for the extreme anemia. Long-term transfusion therapy adequate to suppress ineffective erythropoiesis (maintaining hemoglobin stage >10 g/dL) could also be related to relatively normal progress, growth, and functional capabilities. Longterm iron chelation to forestall iron overload allows for prolonged survival and avoidance of transfusional hemosiderosis (hepatic, endocrine, and cardiac dysfunction). Four genes code for the -globin chains of hemoglobin: 2 genes on every chromosome sixteen. A serum ferritin degree of lower than 12 ng/dL or an iron saturation of less than 10% confirms the prognosis. Such children could have pallor, irritability, fatigue, glossitis, blue sclera, and in extreme circumstances indicators and symptoms of high-output cardiac failure (dyspnea, diaphoresis, pallor, tachycardia, gallop rhythm, and hepatomegaly). When mild anemia is detected within the healthy, menstruating adolescent female, chronic blood loss is normally the etiology. If the hemoglobin degree has normalized after 1 month of remedy, a presumptive analysis has been established and the affected person should obtain a further 2-3 months of therapeutic doses of iron to replete stores. Heiner syndrome ought to be thought-about when persistent iron deficiency anemia exists with related cough, wheeze, or diagnosis of "bronchial asthma. The optimum method to iron deficiency anemia in infants and children is prevention. The thalassemia syndromes symbolize a heterogeneous group of inherited issues of decreased globin production that result in microcytic anemia, which can be mistaken for iron deficiency. The baby with microcytic anemia, without evidence of iron deficiency, ought to be evaluated for thalassemia.
Tags: zetia 10 mg effective, zetia 10 mg, purchase zetia 10 mg without a prescription, zetia 10 mg trusted, purchase 10 mg zetia with mastercard, zetia 10 mg buy overnight delivery, buy generic zetia 10 mg line, zetia 10 mg purchase mastercard, zetia 10 mg proven, generic zetia 10 mg visa, cheap zetia 10 mg with mastercard, zetia 10 mg discount with visa, zetia 10 mg cheap, zetia 10 mg order amex, zetia 10 mg buy cheap on line, trusted 10 mg zetia
9 of 10
Votes: 303 votes
Total customer reviews: 303
Customer Reviews
Sugut, 33 years: Hereditary fructose intolerance is brought on by a recessively inherited deficiency of hepatic fructosealdolase, which transforms fructose-1-phosphate to the triosephosphates. The response to ventral suspension allows evaluation of tone of the trunk, neck, and extremities. The interleukin-12/interleukin12-receptor system: Role in normal and pathologic immune responses. Intractable cases are quite rare and may be handled with vasopressin infusion, balloon tamponade, angiographic embolization, or surgery.
Abbas, 50 years: The an infection could additionally be self-limited but remedy of more severe instances requires incision and debridement of the central core from each lesion. Because cysts are shed within the stool on an intermittent foundation, examination of a number of fecal specimens may be required for identification. Stereoacuity testing may demonstrate higher visible acuity than the affected person is reporting. Normalization: By simply describing common patterns of signs or behaviors, the clinician might assist the affected person feel extra comfy by endorsing the presence of similar patterns in his or her behaviors.
Gancka, 22 years: The serum cholesterol values are elevated in minimal change nephrotic syndrome and are normally larger than 250 mg/dL; ranges within the range of 500-600 mg/dL could happen. Evidence of alteration in psychological status suggests either sepsis related to decreased organ perfusion or primary meningoencephalitis. There are 2 phases to a startle response: the preliminary startle adopted by an orienting response to find the stimulus. Critical illness neuromuscular disease: medical, electrophysiological, and prognostic features.
Nemrok, 49 years: Some adolescents and adults go for a modified Atkins food plan as a substitute, again underneath close supervision of a ketogenic dietitian. Hyperkalemia can be brought on by (1) reduced urinary potassium excretion, (2) increased potassium consumption, (3) launch of intracellular potassium, and/or (4) impaired cellular potassium uptake (Table forty six. Most individuals are unfamiliar with the term consanguinity, but the examiner can ask whether there are ancestors in common or inquire about the hometown and the dimensions of the neighborhood from which the families derive. However, in virtually 66% of contaminated patients between 5 and 17 years of age, a symptomatic illness with jaundice develops.
Marus, 42 years: Treatment initiation is done beneath medical supervision and care is taken to administer the medicine with feeds to limit the unwanted side effects. Cool extremities, pallor, mottling, peripheral cyanosis, and capillary refill of greater than 2 seconds point out poor perfusion. Conjugated hyperbilirubinemia can happen as a outcome of hepatocellular dysfunction, biliary obstruction, and irregular excretion of bile acids or bilirubin. Both H+ and anions accumulate in the body, leading to slow consumption of bicarbonate stores.
