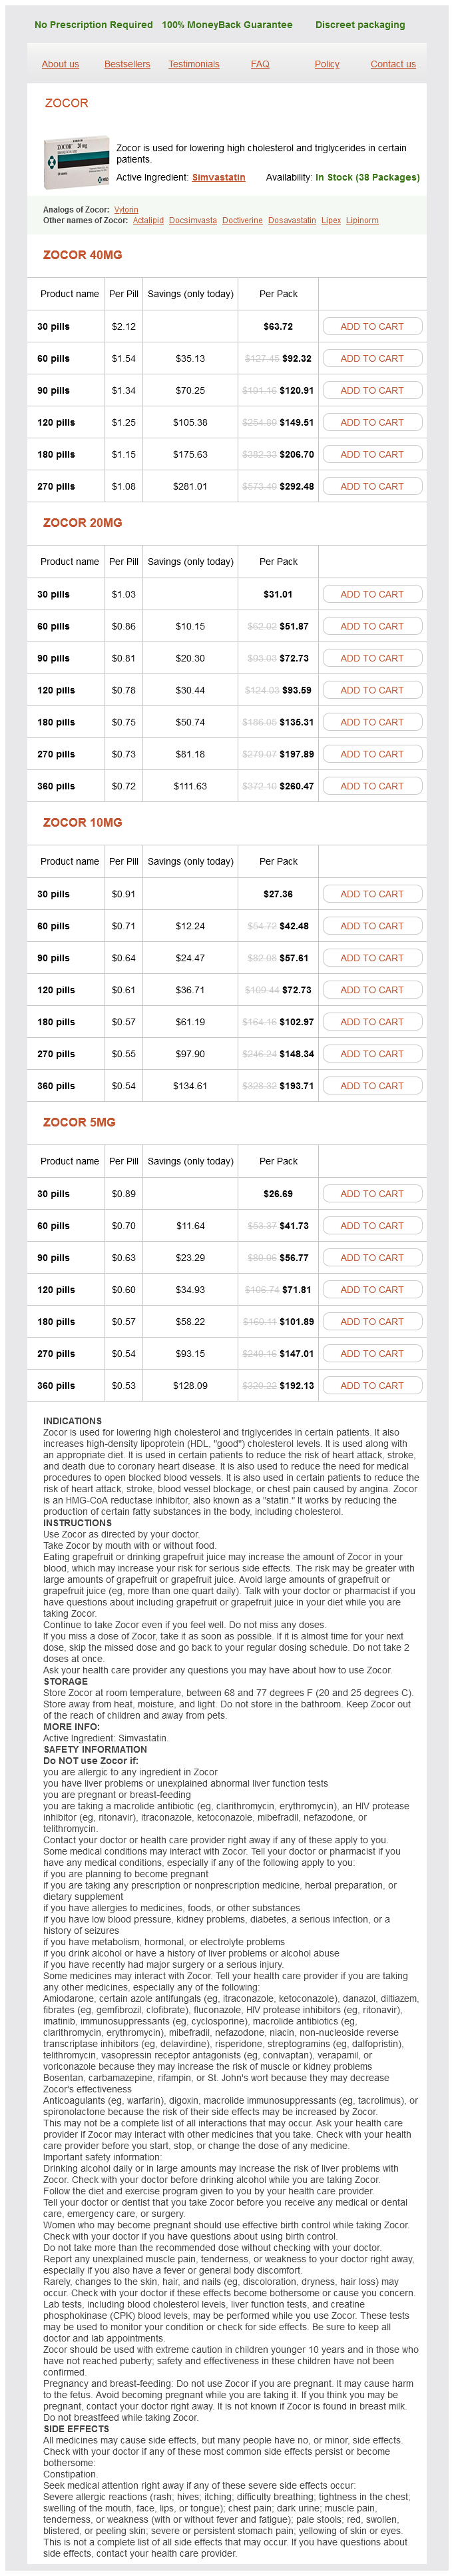
Zocor 40mg
- 30 pills - $63.72
- 60 pills - $92.32
- 90 pills - $120.91
- 120 pills - $149.51
- 180 pills - $206.70
- 270 pills - $292.48
Zocor 20mg
- 30 pills - $31.01
- 60 pills - $51.87
- 90 pills - $72.73
- 120 pills - $93.59
- 180 pills - $135.31
- 270 pills - $197.89
- 360 pills - $260.47
Zocor 10mg
- 30 pills - $27.36
- 60 pills - $42.48
- 90 pills - $57.61
- 120 pills - $72.73
- 180 pills - $102.97
- 270 pills - $148.34
- 360 pills - $193.71
Zocor 5mg
- 30 pills - $26.69
- 60 pills - $41.73
- 90 pills - $56.77
- 120 pills - $71.81
- 180 pills - $101.89
- 270 pills - $147.01
- 360 pills - $192.13
Zocor dosages: 40 mg, 20 mg, 10 mg
Zocor packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 756
Only $0,57 per item
Description
The larvae of this parasite cause the disease definition of cholesterol hdl buy zocor 40 mg overnight delivery, which is endemic in Mediterranean why so much cholesterol in shrimp buy zocor 20 mg with amex, Middle Eastern cholesterol screening guidelines generic zocor 40 mg with mastercard, and South American nations and in New Zealand and Turkey cholesterol test order order zocor 40 mg with visa, where people are in close contact with sheep and dogs. The most common site of disease is within the liver (50% to 80%), followed by the lung (5% to 30%). Surgery is the first technique of therapy; nevertheless, percutaneous approaches have been investigated lately. In a examine from 2005, Paksoy and colleagues reported on 59 patients with 109 hydatid cysts that had been treated percutaneously, injecting both hypertonic saline or albendazole sodium as the scolicidal agent. All patients were given 10 mg/kg/day of albendazole starting forty eight hours before their procedure, and this was continued for 2 months postprocedure. Directly earlier than the procedure, they obtained diphenhydramine and hydrocortisone to prevent anaphylactic reactions. Treatment was safe and effective in both teams, with only one recurrence within the group handled with hypertonic saline. Although all cysts returned to their initial measurement immediately following aspiration and injection, profitable remedy was associated with lower in size over time. In almost half of those patients, illness is restricted to the liver, and as a lot as 25% of those sufferers have resectable illness. More effective systemic chemotherapy (see Chapters ninety nine and 100) and advances in strategies of hepatic resection (see Chapter 103) have mixed to enhance survival and increase rates of hepatic resection. Concomitantly, there have been advances in interventional radiologic strategies of percutaneous thermal ablation, including radiofrequency, microwave, laser, and cryoablation, as nicely as irreversible electroporation (see Chapter 908). All of those strategies are less costly, safer, and result in shorter hospital stays than hepatic resection and could be applied instead of surgical resection in well-selected circumstances, although the risk of local recurrence is larger. There are other tumors that might be treated with ablation, assuming they meet number, measurement, and location standards for successful therapy. Criteria for Treatment Even the most superior ablative techniques are restricted with regard to the tumor measurement that can be efficiently handled. Most commercially obtainable ablation systems lead to an elliptic volume of coagulative necrosis, with a most lengthy axis of four cm, restricted by properties of the local tumor/tissue setting. For this purpose, profitable ablation, with a low price of local tumor recurrence is seen most often Hepatic Ablation Tumors Colorectal most cancers is the third commonest malignancy within the United States, and most disease-related deaths are secondary to metastatic disease. Larger tumors, or those with complex geometry, are unlikely to be successfully treated by making an attempt to lengthen the thermal effect by utilizing multiple overlapping functions. The location of the tumor can also restrict effectiveness of ablation or capability to use the approach safely. Structures that could be injured by heat or cold, similar to bile ducts and different adjoining organs, would possibly preclude protected therapy, although irreversible electroporation has been developed, partly, to take care of that concern. In this instance, addition of ablation to embolization provides several theoretical advantages. In the first instance, it offers a technique of "double kill," whereby the tumor is uncovered to two tumoricidal events: ischemia and lethal temperature (Elnekave et al, 2013). Second, when ablation is carried out instantly following embolization, it turns into much simpler to radiologically target small tumors within the 1- to 2-cm vary because they retain dense distinction. Results Unfortunately, existing proof for ablation of hepatic colorectal metastases is primarily from single-arm retrospective and prospective research with no revealed randomized trial (Wong et al, 2010). Overall survival, starting from 14% to 55%, and native recurrence charges of 4% to 60% are reported following remedy of colorectal metastases. Optimal conditions-small tumors limited to the liver, not adjacent to blood vessels, and within the palms of experienced interventionalists-should end in local management in 98% of lesions (Gervais et al, 2009). Only the examine by Huang demonstrated a difference with surgical resection being superior to ablation, offering each a 5-year survival (75. As was alluded to in a evaluate article from 2013 (Cucchetti et al, 2013), this may have been due to a difference in tumor dimension. In the resection group, 98% of solitary lesions were lower than 3 cm in measurement; in the ablation group, solely 47% of solitary tumors had been lower than three cm. Bismuth H, et al: Management strategies in resection for hilar cholangiocarcinoma, Ann Surg 215(1):31�38, 1992. Copelan A, et al: Diagnosis and management of Budd-Chiari syndrome: an update, Cardiovasc Intervent Radiol 38(1):1�12, 2015. Feng K, et al: A randomized managed trial of radiofrequency ablation and surgical resection in the treatment of small hepatocellular carcinoma, J Hepatol 57(4):794�802, 2012. Isayama H, et al: A potential randomised examine of "coated" versus "uncovered" diamond stents for the administration of distal malignant biliary obstruction, Gut May 53(5):729�734, 2004. Kubo T, et al: Outcome of percutaneous transhepatic venoplasty for hepatic venous outflow obstruction after residing donor liver transplantation, Radiology 239(1):285�290, 2006. Migita K, et al: Clinical outcome of malignant biliary obstruction brought on by metastatic gastric most cancers, World J Surg 33(11):2396�2402, 2009. Miyayama S, et al: Extrahepatic blood supply to hepatocellular carcinoma: angiographic demonstration and transcatheter arterial chemoembolization, Cardiovasc Intervent Radiol 29(1):39�48, 2006. Murkund A, et al: Percutaneous management of resistant biliaryenteric anastomotic strictures with use of a combined slicing and standard ballon cholangioplasty protocol: a single-center experience, J Vasc Interv Radiol 26:560�565, 2015. Nasim S, et al: Emerging indications for percutaneous cholecystostomy for the administration of acute cholecystitis-a retrospective review, Int J Surg 9:456�459, 2011. Pareja E, et al: Vascular problems after orthotopic liver transplantation: hepatic artery thrombosis, Transplant Proc 42(8):2970�2972, 2010. Rosch J, et al: Transjugular portal venography and radiologic portocaval shunt: an experimental research, Radiology 92(5):1112�1114, 1969. Tanaka T, et al: Superselective particle embolisation enhances efficacy of radiofrequency ablation: effects of particle measurement and sequence of action, Cardiovasc Intervent Radiol 36(3):773�782, 2013. Tinkoff G, et al: American Association for the Surgery of Trauma Organ Injury Scale I: spleen, liver, and kidney, validation based on the National Trauma Data Bank, J Am Coll Surg 207(5):646�655, 2008. Wang X, et al: Margin size is an unbiased predictor of native tumor development after ablation of colon most cancers liver metastatses, Cardiovasc Intervent Radiol 36(1):166�175, 2013. Although open exploration for biliary disease has turn into much less widespread, particular conditions, such as obstructive widespread duct stones not amenable to endoscopic remedy or restoration of biliary-enteric continuity following resection of bile duct tumors, stay indications for more invasive approaches. It is necessary to have an intensive understanding of biliary anatomy and familiarity with varied options for operative publicity and administration. Operative techniques encompassing bile duct exploration and biliary-enteric bypass will be the focus of this chapter. There are a selection of ductal anomalies associated to the convergence of the left and proper hepatic ducts and the insertion of cystic duct. Although the left biliary system is fairly consistent, the proper biliary system is susceptible to anatomic variation; the most common variants include the proper anterior or posterior sector ducts traversing an extended extrahepatic course before joining the left biliary system (Blumgart et al, 1984). There are a number of strategies obtainable for analysis and clearance of the widespread bile duct, including percutaneous, endoscopic, laparoscopic, and open strategies. This subset contains sufferers undergoing an open cholecystectomy (or a laparoscopic cholecystectomy transformed to open) in which choledocholithiasis is suspected, patients with massive or a quantity of stones, and patients requiring transduodenal sphincteroplasty. A recent analysis demonstrated equal duct clearance, morbidity, and mortality between endoscopic measures and open surgical techniques (Clayton et al, 2006). Because percutaneous, endoscopic, and laparoscopic modalities are discussed in different chapters, open bile duct exploration will be the focus of the subsequent part. The intrahepatic bile ducts draining the various sectors finally coalesce into the proper hepatic duct draining the proper hemiliver and the left hepatic duct draining the left hemiliver, which then converge on the liver hilum to form the widespread hepatic duct, probably the most anterior structure of the portal triad at this location. In approximately 80% to 90% of cases, the right hepatic artery programs posterior to the common hepatic duct toward the best liver, whereas in the minority of cases, it can be discovered anterior to the duct. Segment I hepatic ducts circulate into both the right and left biliary methods, with the majority of drainage getting into the left hepatic duct just proximal to frequent hepatic duct. Safe operative conduct requires a close familiarity with anatomic variations of biliary drainage, as they happen in up to 25% Incision and Exposure A proper subcostal incision affords satisfactory exposure of the gallbladder, portal structures, and duodenum; alternatively, an higher midline incision could also be equally effective, particularly in thin patients. Division of the lateral peritoneal attachments of the best colon, adopted by mobilization of transverse colon mesentery off of the duodenum, provides visualization of the duodenum. Additionally, cholecystectomy can improve exposure of the hepatoduodenal ligament and may facilitate intraoperative transcystic cholangiography, which might help to delineate biliary anatomy. To keep away from injury to the cystic duct, the positioning of cystic duct insertion must be identified, as this will likely occur in a medial or posterior location. During the incision, caution ought to be taken to keep away from injuring the posterior wall of the duct. The size of the choledochotomy will rely upon the diameter of the duct and measurement of stones present with the lumen but is mostly 1 to 2 cm.
Mignonette Tree (Henna). Zocor.
- How does Henna work?
- Are there safety concerns?
- Ulcers in the stomach or intestines, dandruff, skin conditions, severe diarrhea caused by amoebas (amoebic dysentery), cancer, enlarged spleen, headache, yellow skin (jaundice), and other conditions.
- What is Henna?
- Are there any interactions with medications?
- Dosing considerations for Henna.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96827
For example cholesterol test blood fasting zocor 20 mg order with mastercard, dilatation which could be seen in sufferers with Caroli illness cholesterol journal pdf buy zocor 40 mg cheap, or choledochal cysts cholesterol lowering foods 2015 20 mg zocor purchase visa, can have the radiographic appearance of bile duct dilation with out the presence of obstruction streefwaarde cholesterol ratio order zocor 10 mg mastercard. The most common main issues are bile leak (1% to 2%), sepsis (2% to 3%), and hemorrhage (0. Other uncommon complications embody pneumothorax, biliothorax, harm to the colon associated to the puncture, and abscess formation. Puncture beneath the ninth intercostal space will clearly decrease the incidence of pleural and lung issues. The threat of infectious issues such as sepsis and abscess formation can be mitigated with proper antibiotic protection. Care must be taken to not overdistend the biliary tree, as opacification and incomplete drainage of the biliary tree is normally a supply of cholangitis (Covey & Brown, 2008), notably in the presence of bile duct isolation. In the uncommon cases where sufferers are unable to give informed consent, the subsequent of kin can provide consent. Once consent is obtained, the patient is brought right into a room with a C-arm for availability of fluoroscopy through the process. In the previous, drug mixtures of narcotics, similar to meperidine and droperidol, and benzodiazepines, such as midazolam or diazepam, have been used. More lately, this has been changed by propofol, a short-acting sedative and amnestic with a fast restoration profile. Studies have shown that propofol is simpler than sedation with midazolam, is protected, and is related to a quicker postprocedure restoration (Fanti et al, 2004; Wehrman et al, 1999). In some facilities, common anesthesia could also be used if the endoscopic procedure is predicted to be troublesome, the affected person has important comorbid medical situations, or if there are any signs of practical or mechanical intestinal obstruction. All endoscopic tools used for this process, together with the endoscopes, is either chemically disinfected or fuel sterilized. The affected person is placed in a semiprone position with special positioning of the arms, to help optimize access to the ampulla of Vater. A side-viewing duodenoscope is used to afford excellent visualization of the ampulla of Vater. An initial endoscopic analysis of the stomach and duodenum is carried out earlier than cannulation of the ampulla. The ampulla is often positioned within the second portion of the duodenum however, in uncommon cases, could also be discovered extra proximal or distal. The improvement of the side-viewing duodenoscope with an elevator helped facilitate cannulation of the papilla of Vater (Kasugai et al, 1971; Ogoshi et al, 1970; Takagi et al, 1970). Studies have shown that access to the biliary tree is simpler and sooner with a sphincterotome in contrast with a cannula (Karamanolis et al, 2005; Laasch et al, 2003; Rossos et al, 1993). It remains controversial whether or not insertion of a guidewire, versus the extra typical technique of distinction injection, should be the preferred approach to access the bile ducts. A latest meta-analysis taking a glance at 12 randomized trials with 3450 sufferers concluded that wire-guided approach had the next cannulation success fee (84% vs. In the event of a difficult cannulation, there are strategies to assist facilitate access to the bile duct. Other extra invasive maneuvers, including precut sphincterotomy with or without pancreatic duct stent placement, can also enhance success rate but is associated with an elevated danger of issues, together with bleeding, perforation, and pancreatitis, even in experienced arms (Harewood et al, 2002). Duodenal diverticula are common and almost all the time are situated close to the papilla within the descending duodenum. Although usually asymptomatic, diverticula have been proven to be associated with choledocholithiasis. Periampullary diverticula may make cannulation tougher, however the knowledge are combined (Rajnakova et al, 2003; Tham & Kelly, 2004). If the papilla is identified, cannulation may still be extraordinarily tough because of the location and place of the ampulla (Byron et al, 2002). Recently, double-balloon enteroscopy has been reported to be successful in enabling access to the afferent limb (Sato et al, 2005). Once the bile duct is selectively cannulated, a contrast agent is injected beneath fluoroscopic control, with subsequent radiographic images obtained of the duct anatomy. Material for pathologic and cytologic evaluation could be obtained from both the biliary or pancreatic duct system with a selection of devoted endoscopic biopsy forceps and cytology brushes. Pathologic and cytologic material may be obtained from the ampulla of Vater, duodenum, and stomach for diagnostic functions during the procedure as well. The diameter of the primary pancreatic duct additionally will increase with age, though one examine found no distinction in pancreatic duct size amongst patients younger than 40 years compared with older patients. Duct diameter all through the pancreas was considerably greater, nonetheless, in sufferers older than 40 years (Anand et al, 1989). Cholangioscopy and Pancreatoscopy Cholangioscopy and pancreatoscopy involve using miniature endoscopes by way of the channel of the duodenoscope, permitting direct visualization of the bile and pancreatic ducts, respectively. A new skill set is important to carry out these procedures, provided that this method uses two totally different endoscopes. Diagnostic cholangioscopy could also be used to evaluate indeterminate biliary strictures and filling defects. Similarly, diagnostic pancreatoscopy may be used to evaluate pancreatic strictures and intraductal papillary mucinous neoplasms. One prospective multicenter study of 87 sufferers reported that endoscopists were able to distinguish benign from malignant indeterminate biliary lesions 92. Complications of cholangiopancreatoscopy embody bacteremia, bleeding, and pancreatitis. A systematic survey of potential studies reviewed 21 research with 16,855 patients and reported a particular complication fee of 6. The expertise of the endoscopist and case quantity additionally has an impression on the complication price. Those in the higher case-volume group had a considerably larger success price (86. Mechanical injury to the pancreatic duct from manipulation of the papilla, instrumentation of the pancreatic duct, or injection of the pancreatic duct likely plays a task (Johnson et al, 1997). Similarly, thermal damage from electrocautery leading to edema and attainable obstruction of the duct has been invoked (Ratani et al, 1999). Hydrostatic stress from distinction injection resulting in injury is also doubtless a element. Procedure-related elements embody troublesome cannulation, pancreatic duct injection, precut sphincterotomy, pancreatic sphincterotomy, minor papilla sphincterotomy, balloon sphincteroplasty, ampullectomy, and sphincter of Oddi manometry. One examine showed that trainee participation was an unbiased risk factor (Cheng et al, 2006). Specific techniques and measures to lower the chance of pancreatitis have been studied. The threat is lowered by minimizing the number of makes an attempt of cannulation, avoiding pancreatic duct cannulation if not essential, and by avoiding overdistension or "acinarization" of the pancreatic duct by minimizing the quantity of contrast medium into the pancreatic duct. Studies have proven a good thing about pancreatic duct stents in biliary sphincterotomy for sphincter of Oddi dysfunction, precut sphincterotomy, balloon sphincteroplasty, endoscopic ampullectomy, and tough cannulation (Fazel et al, 2003; Freeman et al, 2004; Singh et al, 2004). Data on bolus-administered somatostatin, sublingual nitroglycerin, and some protease inhibitors have been thought-about promising, however confirmatory studies are necessary (Kubiliun et al, 2015). A meta-analysis that particularly looked at research of rectal Chapter 20 Direct cholangiography: approaches, techniques, and current role 385 indomethacin included 4 research with 1470 sufferers showed that the rate of pancreatitis was considerably lower using indomethacin compared with placebo (odds ratio, 0. One double-blinded, placebocontrolled, randomized study concerned 391 sufferers in three hospitals. They discovered a significantly lower danger of pancreatitis within the somatostatin group (3. Only three out of seven randomized controlled studies confirmed that nitroglycerin was efficient, however two of the three optimistic studies used sublingual nitroglycerin (Kubiliun et al, 2015). One in contrast 2 mg sublingual nitroglycerin given 5 minutes prior to endoscopy with placebo in 186 sufferers and located a lower incidence of pancreatitis within the nitroglycerin group (7/90 vs. In each research, however, the consensus definition for pancreatitis was not used, which can account for the excessive rates of pancreatitis within the control groups. Protease inhibitors, similar to gabexate mesylate, nafamostat mesylate, and ulinastatin, have been investigated, given that activation of proteolytic enzymes probably contributes to the pathogenesis of pancreatitis. In a scientific survey of 21 prospective research with sixteen,855 sufferers, the incidence of infectious problems was 1. The risk is increased in sufferers with hilar obstruction and sclerosing cholangitis, given the increased risk of incomplete drainage (Bangarulingam et al, 2009; Rerknimitr et al, 2004). Treatment entails supportive care with antibiotics and decompression of the obstruction. Antibiotics added to the injected radiographic distinction medium are also of no benefit (Jendrzejewski et al, 1980).
Specifications/Details
Bruix J hdl cholesterol lowering foods purchase 40 mg zocor mastercard, Sherman M: Management of hepatocellular carcinoma: an replace cholesterol ratio nih order zocor 20 mg, Hepatology fifty three:1020�1022 natural cholesterol lowering foods supplements generic 10 mg zocor with visa, 2011 cholesterol hdl zocor 10 mg fast delivery. Burak K, et al: Incidence and threat components for cholangiocarcinoma in main sclerosing cholangitis, Am J Gastroenterol ninety nine:523�526, 2004. Campsen J, et al: Clinically recurrent main sclerosing cholangitis following liver transplantation: a time course, Liver Transpl 14:181� 185, 2008. Chalasani N, et al: Cholangiocarcinoma in sufferers with primary sclerosing cholangitis: a multicenter case-control research, Hepatology 31:7�11, 2000. Charatcharoenwitthaya P, et al: Utility of serum tumor markers, imaging, and biliary cytology for detecting cholangiocarcinoma in primary sclerosing cholangitis, Hepatology forty eight:1106�1117, 2008a. Charatcharoenwitthaya P, et al: Utility of serum tumor markers, imaging, and biliary cytology for detecting cholangiocarcinoma in primary sclerosing cholangitis, Hepatology 48:1106�1117, 2008b. Chazouilleres O, et al: Ursodeoxycholic acid for major sclerosing cholangitis, J Hepatol 11:120�123, 1990. Cholongitas E, et al: Risk factors for recurrence of major sclerosing cholangitis after liver transplantation, Liver Transpl 14:138�143, 2008. Assessment of retrograde cholangiopancreatography in 60 patients, Lancet 1:53�58, 1972. Damrah O, et al: Duct-to-duct biliary reconstruction in orthotopic liver transplantation for major sclerosing cholangitis: a viable and safe alternative, Transpl Int 25:64�68, 2012. De Vreede I, et al: Prolonged disease-free survival after orthotopic liver transplantation plus adjuvant chemoirradiation for cholangiocarcinoma, Liver Transpl 6:309�316, 2000. Egawa H, et al: Risk factors for recurrence of major sclerosing cholangitis after dwelling donor liver transplantation: a single middle experience, Dig Dis Sci 54:1347�1354, 2009. El-Shabrawi M, et al: Primary sclerosing cholangitis in childhood, Gastroenterology 92:1226�1235, 1987. Fausa O, et al: Relationship of inflammatory bowel illness and primary sclerosing cholangitis, Semin Liver Dis 11:31�39, 1991. Fickert P, et al: Ursodeoxycholic acid aggravates bile infarcts in bile duct-ligated and Mdr2 knockout mice via disruption of cholangioles, Gastroenterology 123:1238�1251, 2002. Fickert P, et al: Regurgitation of bile acids from leaky bile ducts causes sclerosing cholangitis in Mdr2 (Abcb4) knockout mice, Gastroenterology 127:261�274, 2004. Garcia-Tsao G, et al: Prevention and management of gastroesophageal varices and variceal hemorrhage in cirrhosis, Am J Gastroenterol 102:2086�2102, 2007. Gautam M, et al: Recurrence of autoimmune liver illness after liver transplantation: a systematic review, Liver Transpl 12:1813�1824, 2006. Ghazale A: Immunoglobulin G4-associated cholangitis: scientific profile and response to therapy, Gastroenterology 134(3):706�715, 2008. Gohlke F, et al: Evidence for an overlap syndrome of autoimmune hepatitis and first sclerosing cholangitis, J Hepatol 24:699�705, 1996. Haruta I, et al: Long-term bacterial publicity can set off nonsuppurative harmful cholangitis related to multifocal epithelial irritation, Lab Invest 90:577�588, 2010. Hirano K, et al: Lower incidence of biliary carcinoma in sufferers with primary sclerosing cholangitis and excessive serum levels of immunoglobulin E, Clin Gastroenterol Hepatol 10:79�83, 2012. Jessurun J, et al: Diffuse lymphoplasmacytic acalculous cholecystitis: a particular type of chronic cholecystitis related to main sclerosing cholangitis, Hum Pathol 29:512�517, 1998. Jussila A, et al: Malignancies in sufferers with inflammatory bowel illness: a nationwide register examine in Finland, Scand J Gastroenterol 48:1405�1413, 2013. Kaya M, et al: Overlap of autoimmune hepatitis and primary sclerosing cholangitis: an analysis of a modified scoring system, J Hepatol 33:537�542, 2000. Kornfeld D, et al: Survival and risk of cholangiocarcinoma in sufferers with major sclerosing cholangitis: a population-based examine, Scand J Gastroenterol 32:1042�1045, 1997. Kugelmas M, et al: Different immunosuppressive regimens and recurrence of main sclerosing cholangitis after liver transplantation, Liver Transpl 9:727�732, 2003. Kuilman T, et al: Oncogene-induced senescence relayed by an interleukin-dependent inflammatory community, Cell 133:1019�1031, 2008. Lawson A, et al: Autoimmune cholestatic liver illness in people with coeliac disease: a population-based examine of their affiliation, Aliment Pharmacol Ther 21:401�405, 2005. Lindstrom L, et al: Association between lowered ranges of alkaline phosphatase and survival instances of patients with major sclerosing cholangitis, Clin Gastroenterol Hepatol 11:841�846, 2013. Ludwig J, et al: Granulomas in main sclerosing cholangitis, Liver 15:307�312, 1995. Ludwig J, et al: Morphologic features of continual hepatitis associated with main sclerosing cholangitis or chronic ulcerative colitis, Hepatology 1:632�640, 1981. Ludwig J, et al: Primary sclerosing cholangitis, Contemp Issues Surg Pathol 8:193�213, 1986. Lundqvist K, Broome U: Differences in colonic disease activity in sufferers with ulcerative colitis with and without primary sclerosing cholangitis: a case management study, Dis Colon Rectum forty:451�456, 1997. Matsuda A, et al: Glycoproteomics-based most cancers marker discovery adopting dual enrichment with Wisteria floribunda agglutinin for prime specific glyco-diagnosis of cholangiocarcinoma, J Proteomics eighty five:1�11, 2013. Mueller T, et al: Enhanced innate immune responsiveness and intolerance to intestinal endotoxins in human biliary epithelial cells contributes to continual cholangitis, Liver Int 31:1574�1588, 2011. Navaneethan U, et al: Immunoglobulin E stage and its significance in patients with major sclerosing cholangitis, Clin Gastroenterol Hepatol 10:563, writer reply 563�564, 2012. Okolicsanyi L, et al: Primary sclerosing cholangitis: clinical presentation, pure historical past and prognostic variables: an Italian multicentre study, Eur J Gastroenterol Hepatol eight:685�691, 1996. Olsson R, et al: Prevalence of primary sclerosing cholangitis in patients with ulcerative colitis, Gastroenterology one hundred:1319�1323, 1991. Olsson R, et al: Bile duct bacterial isolates in main sclerosing cholangitis: a examine of explanted livers, J Hepatol 28:426�432, 1998. Olsson R, et al: High-dose ursodeoxycholic acid in primary sclerosing cholangitis: a 5-year multicenter, randomized, managed examine, Gastroenterology 129:1464�1472, 2005. Penna C, et al: Pouchitis after ileal pouch-anal anastomosis for ulcerative colitis happens with elevated frequency in patients with related primary sclerosing cholangitis, Gut 38:234�239, 1996. Pohl J, et al: the position of dominant stenoses in bacterial infections of bile ducts in main sclerosing cholangitis, Eur J Gastroenterol Hepatol 18:69�74, 2006. Priester S, et al: Involvement of cholangiocyte proliferation in biliary fibrosis, World J Gastrointest Pathophysiol 1:30�37, 2010. Sasatomi K, et al: Abnormal accumulation of endotoxin in biliary epithelial cells in major biliary cirrhosis and first sclerosing cholangitis, J Hepatol 29:409�416, 1998. Pathologic options and evolution of main biliary cirrhosis and first sclerosing cholangitis, Mayo Clin Proc seventy three:179�183, 1998. Shah R, et al: Cholangioscopy and cholangioscopic forceps biopsy in patients with indeterminate pancreaticobiliary pathology, Clin Gastroenterol Hepatol four:219�225, 2006. Shorbagi A, Bayraktar Y: Primary sclerosing cholangitis-what is the distinction between east and west Sinakos E, et al: Inflammatory bowel disease in primary sclerosing cholangitis: a robust but changing relationship, Inflamm Bowel Dis 19:1004�1009, 2013. Tamura S, et al: Recurrence of main sclerosing cholangitis after residing donor liver transplantation, Liver Int 27:86�94, 2007. Tchkonia T, et al: Fat tissue, growing older, and mobile senescence, Aging Cell 9:667�684, 2010. Tchkonia T, et al: Cellular senescence and the senescent secretory phenotype: therapeutic opportunities, J Clin Invest 123:966�972, 2013. Treeprasertsuk S, et al: Outcome of sufferers with main sclerosing cholangitis and ulcerative colitis undergoing colectomy, World J Gastrointest Pharmacol Ther 4:61�68, 2013. Vera A, et al: Risk components for recurrence of major sclerosing cholangitis of liver allograft, Lancet 360:1943�1944, 2002. Wagner S, et al: Endoscopic administration of biliary tract strictures in primary sclerosing cholangitis, Endoscopy 28:546�551, 1996. Wilschanski M, et al: Primary sclerosing cholangitis in 32 youngsters: clinical, laboratory, and radiographic options, with survival evaluation, Hepatology 22:1415�1422, 1995. Yamada S, et al: Small duct cholangitis induced by N-formyl L-methionine L-leucine L-tyrosine in rats, J Gastroenterol 29:631�636, 1994. By definition, a biliary fistula is an irregular communication between the biliary tract and other organs. In contrast, a biliary stricture is outlined as an abnormal narrowing of the bile duct which will lead to obstruction and fistula.
Syndromes
- Africa
- Take several deep breaths of fresh air, and then hold your breath as you go in. Hold a wet cloth over your nose and mouth.
- Candy
- Under the chest bone; pain may move to other areas of the body, most often the left side of the chest
- Left heart catheterization
- Metabolic studies
- Vomiting
- Priapism -- the erection needs to diminish, a urinary catheter is inserted to relieve urinary retention, and medications or surgery may be given if needed
- Blood in the urine
- Decreased consciousness, hallucinations or coma
Related Products
Additional information:
This triggers a cascade of proinflammatory signals that end in additional hepatocyte demise and cholesterol blood test fast zocor 40 mg order online, in the end cholesterol test fasting guidelines 40 mg zocor buy free shipping, in liver failure cholesterol test effect not fasting 10 mg zocor discount mastercard. Through using mouse fashions of acetaminophen-induced liver damage cholesterol medication pregnancy discount zocor 40 mg free shipping, the roles of various components of the hepatic immune system have been nicely characterized. The liver is prone to pyogenic abscesses, notably in patients with malignant biliary tract disease undergoing complicated endoscopic, percutaneous, and surgical interventions (Mezhir et al, 2010). The host response to micro organism inside the liver results in formation of an abscess in an effort to curtail the unfold of an infection. Neutrophils are recruited to the positioning of an infection by way of chemotactic signals launched by the invading bacteria and activation of complement. Neutrophils then release cytokines and reactive oxygen species that promote inflammation and kill bacteria. Helminthic infections of the liver, such as schistosomiasis, echinococcosis, and ascariasis have a hepatic part in their life cycles. We speculate that immunosuppressive intrahepatic immune cells and immunoinhibitory pathways limit the function of effector T cells. This presents a therapeutic opportunity to ship effective adoptive mobile immunotherapy at the side of suppressive pathway inhibition to overcome the elements curtailing endogenous antitumor immunity. Immunotherapy for Liver Cancer Although many investigators have attempted to manipulate the immune system for the therapy of most cancers (Hunder et al, 2008), few makes an attempt have been made to immediately target intrahepatic immune cells. The primary aim of most cancers immunotherapy, particularly for liver tumors, is to ship or induce potent antitumor immunity while reversing intrahepatic suppression. As described above, most patients fail to mount effective antitumor immunity, likely as a outcome of the immunosuppressive nature of the intrahepatic space. It is likely that revolutionary combinatorial immunotherapeutic approaches will achieve higher clinical success than singleagent methods. Immune Response to Metastatic Liver Cancer the high prevalence of metastatic disease to the liver is most likely going as a result of a quantity of factors. Evidence suggests that exact traits of the liver immune system might play an essential role on this propensity. Although the propensity towards tolerance is advantageous when responding to oral antigens and within the setting of transplantation, intrahepatic immunosuppression could additionally be exploited by pathogens and malignant cells to evade detection and destruction. Deepening our perception into liver immune cell biology and immunoinhibitory pathway signaling will present exciting alternatives for manipulating the intrahepatic immune system for remedy of benign and malignant situations. Hayashi N, et al: Kupffer cells from Schistosoma mansoni-infected mice participate within the prompt kind 2 differentiation of hepatic T cells in response to worm antigens, J Immunol 163:6702�6711, 1999. Kamada N, et al: Reversal of transplantation immunity by liver grafting, Nature 292:840�842, 1981. Katt J, et al: Increased T helper sort 17 response to pathogen stimulation in patients with main sclerosing cholangitis, Hepatology fifty eight:1084�1093, 2014. Li W, et al: Role of the liver in peripheral tolerance: induction via oral antigen feeding, Am J Transplant four:1574�1582, 2004. Charles R, et al: Human hepatic stellate cells inhibit T-cell response via B7-H1 pathway, Transplantation ninety six:17�24, 2013. Chen J, et al: Persistent hepatitis C virus infections and hepatopathological manifestations in immune-competent humanized mice, Cell Res 24:1050�1066, 2014. Creput C, et al: Incidence of renal and liver rejection and patient survival price following combined liver and kidney transplantation, Am J Transplant three:348�356, 2003. Dangi A, et al: Selective growth of allogeneic regulatory T cells by hepatic stellate cells: role of endotoxin and implications for allograft tolerance, J Immunol 188:3667�3677, 2012. Ferrari C, et al: Immunopathogenesis of hepatitis C virus an infection, J Hepatol 31(Suppl 1):31�38, 1999. Gao Y, et al: Gamma delta T cells provide an early source of interferon gamma in tumor immunity, J Exp Med 198:433�442, 2003. Gao Q, et al: Intratumoral steadiness of regulatory and cytotoxic T cells is related to prognosis of hepatocellular carcinoma after resection, J Clin Oncol 25:2586�2593, 2007. Lu L, et al: A novel subset of dendritic cells propagated from the liver promotes differentiation of T regulatory cells and enhances allograft survival, Transplant Proc 33:229, 2001. Miller G, et al: Endogenous granulocyte-macrophage colonystimulating factor overexpression in vivo leads to the long-term recruitment of a definite dendritic cell population with enhanced immunostimulatory perform, J Immunol 169:2875�2885, 2002a. Miller G, et al: Adenovirus infection enhances dendritic cell immunostimulatory properties and induces natural killer and T cell-mediated tumor safety, Cancer Res 62:5260�5266, 2002b. Obermayer-Straub P, et al: Autoimmune hepatitis, J Hepatol 32(Suppl 1):181�197, 2000. Plitas G, et al: Dendritic cells are required for efficient crosspresentation in the murine liver, Hepatology 47:1343�1351, 2008. Qian S, et al: Murine liver allograft transplantation: tolerance and donor cell chimerism, Hepatology 19:916�924, 1994. Rasmussen A, et al: Combined transplantation of liver and kidney from the identical donor protects the kidney from rejection and improves kidney graft survival, Transplantation 59:919�921, 1995. Saied A, et al: Neutrophil:lymphocyte ratios and serum cytokine changes after hepatic artery chimeric antigen receptor-modified T-cell infusions for liver metastases, Cancer Gene Ther 21:457�462, 2014. Schroder K, et al: Interferon-gamma: an summary of signals, mechanisms and functions, J Leukoc Biol seventy five:163�189, 2004. Seki E, et al: Contribution of Toll-like receptor/myeloid differentiation factor 88 signaling to murine liver regeneration, Hepatology forty one:443� 450, 2005. Sriwatanawongsa V, et al: the essential roles of parenchymal tissues and passenger leukocytes in the tolerance induced by liver grafting in rats, Nat Med 1:428�432, 1995. Sun Z, et al: Hepatic allograft-derived Kupffer cells regulate T cell response in rats, Liver Transpl 9:489�497, 2003. Suzuki G, et al: Antigen-induced suppression of the proliferative response of T cell clones, J Immunol 140:1359�1365, 1988. Teng M, et al: Combined natural killer t-cell based immunotherapy eradicates established tumors in mice, Cancer Res 67(15):7495� 7504, 2007. You Q, et al: Mechanism of T cell tolerance induction by murine hepatic Kupffer cells, Hepatology 48:978�990, 2008. Zorde-Khvalevsky E, et al: Toll-like receptor three signaling attenuates liver regeneration, Hepatology 50:198�206, 2009. These nonstructural proteins have an impact instantly on cells and within the communication between cells. The liver possesses intensive immunologic operate, and appreciable research has implicated cytokines as essential mediators within the improvement of hepatic diseases, as nicely as regeneration and restore. Although not as nicely outlined, it would correspond that pancreatic pathophysiology derives from a similar relationship. Elucidation of the mechanisms of these mediators allows an enhanced understanding of the natural history of liver, biliary, and pancreatic surgical diseases. Although produced by all nucleated cells, constitutive manufacturing of cytokines is all but absent with out noxious stimuli. This article critiques these stimuli, in addition to the precise mediators concerned, within the pathophysiology of liver, biliary, and pancreatic illness. Specific attention is paid to surgical diseases, in addition to potential therapeutic targets. Endotoxins occupy a lot of the outer leaflet of the outer membrane of gram-negative micro organism. These endotoxins are composed of three major components: a conserved lipid A region, a core oligosaccharide, and an outer O-specific oligosaccharide chain, which is specific to every bacterial pressure and elicits host production of various antibodies. The innate immune system is a first-line defense against microbial pathogens, providing the ability to distinguish self from nonself by way of cell-surface receptors and antigenpresenting cells. Additionally, central to this protection mechanism is the flexibility to acknowledge mobile injury. The liver, biliary system, and pancreas play a significant position in growth of immunologic responses because of their shut physiologic relationship with the gut. Portal return of blood to the liver accommodates an amazing amount of antigens and microbial merchandise, which capabilities to form immunologic tolerance as well as an organized response of inflammatory mediators (Carvalho et al, 2012). Although important for protecting immunity within the normal state, aberrant or prolonged responses can produce catastrophic effects on the host. This has been demonstrated in the complete deficit of hepatic acutephase protein production in MyD88-deficient mice (Kawai et al, 1999; Yamamoto et al, 2004). In addition to its position in necrosis and apoptosis, it has also been defined as a major factor in the physiologic effects seen with extreme inflammatory reactions (Box eleven. Further mobile damage and deleterious proinflammatory cytokines responsible for the host responses seen with endotoxemia (Alexopoulou et al, 2001). However, an unregulated response can cause an especially damaging host response, as is seen with overwhelming sepsis.
Usage: q.h.
In the setting of acute cholangitis cholesterol levels ldl range zocor 40 mg discount amex, intervention ought to begin with resuscitation cholesterol off best 40 mg zocor, parenteral antibiotics cholesterol test kit cvs buy generic zocor 20 mg on-line, and biliary decompression cholesterol free eggs substitutes cheap zocor 20 mg with mastercard. The imaging and procedural modalities used in the treatment of affected patients require a radical understanding of the etiology and must be tailor-made to the particular causation. Badaro R, et al; the Latin American Antibiotic Research Group: A multicenter comparative research of cefepime versus broad-spectrum antibacterial therapy in average and severe bacterial infections, Braz J Infect Dis 6:206�218, 2002. Bile Duct Lithotripsy Prospective Study, Ann Surg 209:743�753, dialogue 753-735, 1989. Boender J, et al: Endoscopic sphincterotomy and biliary drainage in sufferers with cholangitis due to common bile duct stones, Am J Gastroenterol ninety:233�238, 1995. Chen C, et al: Reappraisal of percutaneous transhepatic cholangioscopic lithotomy for major hepatolithiasis, Surg Endosc 19:505� 509, 2005. Csendes A, et al: Bacteriological research of liver parenchyma in controls and in sufferers with gallstones or widespread bile duct stones with or with out acute cholangitis, Hepatogastroenterology forty two:821�826, 1995. Csendes A, et al: Counts of micro organism and pyocites of choledochal bile in controls and in patients with gallstones or widespread bile duct stones with or without acute cholangitis, Hepatogastroenterology 43: 800�806, 1996. Ducreux M, et al: Management of malignant hilar biliary obstruction by endoscopy: results and prognostic elements, Dig Dis Sci 37:778� 783, 1992. Ghazale A, et al: Immunoglobulin G4-associated cholangitis: clinical profile and response to therapy, Gastroenterology 134:706� 715, 2008. Harz C, et al: Extracorporeal shock-wave lithotripsy and endoscopy: mixed remedy for problematic bile duct stones, Surg Endosc 5:196�199, 1991. In Root R, Trunkey D, et al, editors: New surgical and medical approaches in infectious ailments, New York, 1987, Churchill Livingstone, pp 113�132. Kadir S, et al: Percutaneous biliary drainage in the administration of biliary sepsis, Am J Roentgenol 138:25�29, 1982. Kamisawa T: Immunoglobulin G4-positive plasma cells in organs of sufferers with autoimmune pancreatitis, Clin Gastroenterol Hepatol 6:715, 2008. Kumar R, et al: Endoscopic biliary drainage for extreme acute cholangitis in biliary obstruction because of malignant and benign illnesses, J Gastroenterol Hepatol 19:994�997, 2004. Leese T, et al: Management of acute cholangitis and the impression of endoscopic sphincterotomy, Br J Surg seventy three:988�992, 1986. Ludwig J, et al: Morphologic options of continual hepatitis associated with main sclerosing cholangitis and chronic ulcerative colitis, Hepatology 1:632�640, 1981. Nomura T, et al: Cholangitis after endoscopic biliary drainage for hilar lesions, Hepatogastroenterology forty four:1267�1270, 1997. Rintoul R, et al: Changing management of pyogenic liver abscess, Br J Surg eighty three:1215�1218, 1996. Sandouk F, et al: Pancreatic-biliary ascariasis: expertise of 300 circumstances, Am J Gastroenterol ninety two:2264�2267, 1997. Sarles H, et al: Chronic inflammatory sclerosis of the pancreas-an autonomous pancreatic disease Shamamian P, Grasso M: Management of complex biliary tract calculi with a holmium laser, J Gastrointest Surg 8:191�199, 2004. Sugiyama M, Atomi Y: Treatment of acute cholangitis as a result of choledocholithiasis in aged and youthful sufferers, Arch Surg 132:1129� 1133, 1997. Takada T, et al: Background: Tokyo Guidelines for the management of acute cholangitis and cholecystitis, J Hepatobiliary Pancreat Surg 14:1�10, 2007. Tsuyuguchi T, et al: Techniques of biliary drainage for acute cholangitis: Tokyo Guidelines, J Hepatobiliary Pancreat Surg 14:35�45, 2007. Umemura T, et al: Immunoglobin G4 hepatopathy: association of immunoglobin G4-bearing plasma cells in liver with autoimmune pancreatitis, Hepatology forty six:463�471, 2007. Vidal V, et al: Early cholangitis complicating percutaneous biliary drainage [in French], J Radiol 85:1707�1709, 2004. It is also called Oriental cholangiohepatitis (Stock & Fung, 1962), Hong Kong disease (Mage & Morel, 1965), intrahepatic stones (Wen & Lee, 1972), hepatolithiasis (Nakayama et al, 1980), primary cholangitis (Choi et al, 1981), and Oriental infestational cholangitis (Seel & Park, 1983). The likely initiating event is the establishment of an infection by bowel microorganisms within the small biliary radicles (see Chapter 43). Experimental and scientific research (Nakayama et al, 1980; Ong, 1962) indicate that the organisms isolated from portal vein blood, widespread duct bile, and liver biopsy specimens are predominantly of bowel origin (see Chapter 12). Because this condition usually affects the decrease socioeconomic courses, malnutrition and maybe an infection by flukes and worms may reduce the capability of the liver to clear enteric bacteria successfully. Once the organisms are established in the liver, an infection begins within the cholangioles and subsequently involves the rest of the portal triads. If the infection is extreme, the hepatocytes show vacuolation and may bear necrosis, thus the name cholangiohepatitis. Hepatocellular damage is normally delicate, if the infection is confined to the cholangioles. Resolution of infection in the early phases restores regular morphology, however more intense or repeated an infection might end in fibrosis of intrahepatic ducts or cholangitic liver abscess formation. Conversely, stones are also discovered within the intrahepatic ducts when no vital narrowing of the ducts is discerned. In superior cases, strictures are associated with in depth formation of stones, which may fill the ducts throughout the liver. Whatever the sequence of growth, repeated or extreme an infection leads to transmural irritation of the ducts and results in stenosis within the larger ducts, forming weblike strictures, and in the smaller peripheral ducts, displaying more tubular narrowing. As a results of obstruction, together with parenchymal harm to the adjoining liver, the rest of the ducts dilate. Infection within the bile duct changes the bile from a supersaturated resolution to an insoluble precipitate. It is postulated that -glucuronidase, derived from Clostridium perfringens and Escherichia coli, splits the bilirubin diglucuronide into free bilirubin, and the ionized unconjugated bilirubin, together with ionic calcium, precipitates to type insoluble calcium bilirubinate, which with time coagulates and consolidates into stones (Leung et al, 2001; Maki, 1966; Nakayama et al, 1980). Mucin hypersecretion contributes to more stone formation by impeding bile flow and making a nidus for pigment deposition (Sasaki et al, 1998). Augmented expression and secretion of trefoil issue family protein, a mucin-associated protein essential for mucosal defense and restore, together with gel-forming apomucin, might play a role in lithogenesis (Sasaki et al, 2004). Once formation has began, the stones enlarge; where they finally reside depends on whether they can move through existing strictures. If the stones are small, they could cross into the common duct and egress via the ampulla into the duodenum, or they could be held in the widespread duct and enlarge. At any site, stones trapped in the liver or the widespread duct perpetuate infection and cause additional irritation and scarring of the duct wall. An affiliation with an infection by Clonorchis sinensis and Ascaris lumbricoides has been implicated in the past (Fung, 1961) and is still typically regarded as causally important (Rana et al, 2007) (see Chapter 45). It is indisputable that clonorchiasis is a critical infection that will trigger structural modifications in the intrahepatic and extrahepatic bile ducts (Hou, 1956). Even if clonorchiasis and ascariasis are merely coincidental infections, they might turn into a nidus for stone formation (Teoh, 1963). Endoscopic retrograde cholangiopancreatography displaying early recurrent pyogenic cholangitis changes with in depth branching and dilatation of the left intrahepatic ducts proximal to the intrahepaticductalstrictures. The outcomes of repeated infection are progressive biliary epithelial and hepatocellular damage, as discussed previously. Itisweblike,andproximaldilatationisseen, with stones above and under the stricture. Strictures in the hepatic ducts additionally prolong over a brief distance and are often intrahepatic, however they could extend C. Left duct involvement alone is found in 40% of circumstances of intrahepatic disease, proper duct involvement alone in 20%, and involvement of both ducts in 40%. No satisfactory explanation has been offered for this discovering, but it has been advised that the left duct is extra horizontal, and bile in the left duct could not drain in addition to bile in the proper duct. Dilated segments taper toward the strictures, which are thick and fibrous; when operative plastic repair of such strictures is tried, restenosis is widespread because of ongoing fibrotic modifications in the diseased ductal tissues, and failure may be anticipated in most cases. When stones are discovered in the gallbladder, disease is invariably present elsewhere. In the acute assault, and when widespread duct obstruction is severe, the gallbladder could also be grossly distended, and empyema, gangrene, or perforation may develop. When a traditional gallbladder is left behind after drainage procedures to the common duct, the chance of a complication from the gallbladder that would require surgical procedure is small.
Tags: buy discount zocor 20 mg online, 10 mg zocor cheap free shipping, purchase zocor 20 mg overnight delivery, order 40 mg zocor with amex, zocor 40 mg, zocor 20 mg cheap with mastercard, discount 20 mg zocor amex, zocor 40 mg buy on line, buy zocor 10 mg on line, discount zocor 10 mg on line, 40 mg zocor order amex, buy zocor 40 mg low price, cheap 40 mg zocor visa, 20 mg zocor mastercard, zocor 20 mg buy, 40 mg zocor buy with mastercard
9 of 10
Votes: 75 votes
Total customer reviews: 75
Customer Reviews
Koraz, 31 years: Occasionally, persistent drainage of enormous quantities of bile with vital fluid and electrolyte loss might necessitate early operation, when the external fistula may be converted to an inside fistulojejunostomy using a mobilized and approximated Roux-en-Y jejunal loop (Smith et al, 1982).
Makas, 32 years: Felekouras E, et al: Malignant carcinoid tumor of the cystic duct: a uncommon reason for bile duct obstruction, Hepatobiliary Pancreat Dis Int eight:640�646, 2009.
Thorus, 53 years: Budd-Chiari Syndrome Budd-Chiari syndrome is characterised by venous outflow obstruction to the liver, which might be intrahepatic or extrahepatic (see Chapter 88).
Jerek, 59 years: Stenosis of the major ducts should be assessed in all sufferers with hepatolithiasis.
